Nephritic syndrome is glomerular inflammation that causes hematuria with dysmorphic red cells and RBC casts, hypertension, edema, a rising creatinine and usually sub-nephrotic proteinuria. Its two classic causes split on timing and complement: IgA nephropathy causes gross hematuria 1-2 days after a mucosal infection with a normal C3, while poststreptococcal glomerulonephritis (PSGN) starts about 10 days after strep throat or up to about 3 weeks after impetigo, with a low C3 that normalizes within 6-8 weeks in most patients. On biopsy, IgA nephropathy shows mesangial IgA deposits; PSGN shows granular IgG and C3 with subepithelial humps. PSGN care is supportive; IgA nephropathy now has FDA-approved disease-specific drugs.
Nephritic syndrome in one minute
- Hematuria: cola-colored or smoky urine, or microscopic hematuria, with dysmorphic RBCs.
- RBC casts: red cells trapped in tubular casts prove the bleeding started in the glomerulus.
- Proteinuria: present but usually below the nephrotic range (in PSGN usually under 3 g/day).
- Salt and water retention: hypertension and edema, classically periorbital and worst on waking.
- Falling GFR: rising BUN and creatinine, sometimes oliguria.
Nephrotic syndrome is the opposite emphasis: proteinuria above 3.5 g/day, low albumin, hyperlipidemia, fatty casts (see nephrotic vs nephritic syndrome).
IgA nephropathy vs PSGN: the master table
| Feature | IgA nephropathy (Berger disease) | PSGN |
|---|---|---|
| Typical patient | Young adult (peak 20s-30s), male > female; most common glomerulonephritis worldwide, commoner in Asian and some European countries | Child aged 3-15 (most often preschool and early school age) |
| Trigger | Febrile mucosal illness (URI, GI infection) | Nephritogenic group A strep pharyngitis or impetigo |
| Timing | 1-2 days ("synpharyngitic") | About 10 days after pharyngitis; up to about 3 weeks after skin infection (typical range 6-21 days; can be up to 6 weeks) |
| Course | Recurrent gross hematuria with infections, or persistent microscopic hematuria | Acute episode; GFR usually normal again in 1-3 months |
| C3 | Normal | Low (and CH50); C4 normal or only slightly low; normal again within 6-8 weeks in 80% |
| Blood tests | No validated diagnostic serum test | ASO (after pharyngitis); anti-DNase B (better after skin infection) |
| Light microscopy | Mesangial expansion and proliferation | Enlarged, hypercellular glomeruli with neutrophils |
| Immunofluorescence | Mesangial IgA (with C3) | Granular IgG and C3 ("lumpy-bumpy") |
| Electron microscopy | Mesangial deposits | Subepithelial humps |
| Outlook | Variable; at risk of progression if proteinuria ≥ 0.5 g/day | More than 90% of children recover fully; adults do worse |
PSGN: what gets tested
- Cause: a limited set of nephritogenic strains of Streptococcus pyogenes (Merck cites M types 12 and 49); about 5-25% of people infected with such a strain develop glomerulonephritis.
- Mechanism (type III hypersensitivity): streptococcal antigens form immune complexes in the glomerulus (or circulating complexes lodge there), activating complement mainly through the alternative pathway, so C3 falls while C4 stays normal or near normal.
- Timing (sources differ): CDC gives about 10 days after pharyngitis and up to 3 weeks after skin infection; Merck's kidney chapter gives 6-21 days, sometimes up to 6 weeks, and its streptococcal chapter simply says 1-3 weeks. Same lesson: PSGN comes weeks later; IgA nephropathy within days.
- Presentation (CDC): facial and periorbital edema, hypertension, dark reddish-brown urine, lethargy; low C3 and total complement, RBC casts, raised creatinine.
- Streptococcal antibodies: ASO and anti-DNase B rise from about 1 week after infection and peak at 1-2 months. ASO rises in only 75-80% of strep infections and usually not after pyoderma, where anti-DNase B (or antihyaluronidase) is the one to check.
- Antibiotics: penicillin is given to eradicate any remaining strep (CDC), but antibiotics have little effect on whether PSGN develops once the infection has occurred.
- Treatment is supportive: sodium and fluid restriction, diuretics, antihypertensives, dialysis if needed.
- Outlook: microscopic hematuria can linger after GFR recovers; adults are more likely than children to keep some loss of kidney function.
- A low C3 that does not recover within about 8 weeks argues against simple PSGN: think C3 glomerulopathy or membranoproliferative GN, or lupus nephritis.
IgA nephropathy: what gets tested
- Mechanism: mucosal B cells (including those in the ileal Peyer's patches) make galactose-deficient IgA1 (Gd-IgA1). It forms IgA-containing immune complexes that deposit in the mesangium, drive mesangial proliferation and activate complement locally (the alternative pathway is the target of iptacopan). Circulating C3 usually stays normal.
- Presentation: gross hematuria 1-2 days after a febrile mucosal illness, often recurrent and sometimes with flank pain and low-grade fever; or asymptomatic microscopic hematuria with mild proteinuria (usually under 1 g/day). About 10% develop nephrotic syndrome and about 5% rapidly progressive GN.
- Diagnosis: only a kidney biopsy can diagnose IgA nephropathy, because there are no validated serum or urine biomarkers (KDIGO 2025). The biopsy is scored with the Oxford MEST-C system (mesangial and endocapillary hypercellularity, segmental sclerosis, tubular atrophy/interstitial fibrosis, crescents).
- Secondary mesangial IgA: IgA vasculitis (Henoch-Schönlein purpura) has the same kidney lesion; also cirrhosis, celiac disease, IBD, psoriasis and HIV.
- Who progresses: KDIGO treats proteinuria ≥ 0.5 g/day (on or off treatment) as at risk; Merck also lists raised creatinine, uncontrolled hypertension and fibrosis or crescents on biopsy.
Treatment: KDIGO 2025 and FDA approvals as of October 2026
KDIGO's 2025 guideline asks for two things at once: reduce IgA immune complex formation and injury, and manage the nephron loss already done. Targets: proteinuria under 0.5 g/day, ideally under 0.3 g/day, and eGFR loss slowed to under 1 mL/min per year.
- For everyone at risk: an ACE inhibitor or ARB at the maximally tolerated dose (1B) or sparsentan in its place (2B), plus an SGLT2 inhibitor (2B), salt restriction, weight control, exercise and no smoking.
- Disease-specific: a 9-month course of targeted-release budesonide where approved (2B), or, where it is not available, a reduced-dose systemic glucocorticoid regimen with antimicrobial prophylaxis (2B).
| Drug | How it works | FDA-labeled use in IgAN |
|---|---|---|
| Budesonide delayed-release (Tarpeyo) | Delayed-release glucocorticoid aimed at ileal mucosal B cells that make Gd-IgA1; 16 mg daily for 9 months | Reduce loss of kidney function |
| Sparsentan (Filspari) | Dual endothelin A and angiotensin II type 1 receptor antagonist; stop ACE inhibitors and ARBs first; REMS for liver toxicity; boxed warning for hepatotoxicity and embryo-fetal toxicity | Slow kidney function decline |
| Iptacopan (Fabhalta) | Oral factor B inhibitor (alternative complement pathway); boxed warning for encapsulated bacteria, so vaccinate first | Slow kidney function decline |
| Atrasentan (Vanrafia, April 2025) | Selective endothelin A receptor antagonist | Accelerated approval: reduce proteinuria (generally UPCR ≥ 1.5 g/g) |
| Sibeprenlimab (Voyxact, November 2025) | Anti-APRIL monoclonal antibody, lowers Gd-IgA1; injected every 4 weeks | Accelerated approval: reduce proteinuria |
| Atacicept (Trutakna, July 2026) | TACI-Fc fusion protein blocking BLyS (BAFF) and APRIL; injected weekly | Accelerated approval: reduce proteinuria |
Accelerated approvals rest on proteinuria reduction; long-term kidney benefit is still being confirmed.
Other nephritic causes: sort by complement
| Cause | Complement | Discriminator |
|---|---|---|
| PSGN | Low C3, normal C4 | Weeks after strep; humps |
| C3 glomerulopathy (complement-mediated MPGN) | Low C3, normal C4 | C3 nephritic factor; persistent low C3 |
| Immune-complex MPGN | C3 normal or mildly low, C4 low | Hepatitis B or C, endocarditis, monoclonal gammopathy; double-contour ("tram-track") GBM |
| Lupus nephritis | Low C3 and C4 | Anti-dsDNA; class IV (diffuse proliferative) is the most common class |
| IgA nephropathy, IgA vasculitis | Normal | Synpharyngitic hematuria; purpura in IgA vasculitis |
| Anti-GBM disease, ANCA vasculitis | Normal | Rapidly progressive GN with crescents: linear IgG (anti-GBM) vs pauci-immune (ANCA); see rapidly progressive GN |
| Alport syndrome | Normal (not immune) | Usually X-linked COL4A5 (type IV collagen); hematuria, sensorineural hearing loss, eye lesions (anterior lenticonus); basket-weave GBM (Alport question) |
How USMLE tests it
- Hematuria during the sore throat = IgA nephropathy; hematuria weeks after = PSGN.
- Nephritis after impetigo = PSGN. Classic teaching says rheumatic fever follows only pharyngitis; CDC now lists skin infection as a possible trigger too, but cola urine, edema and low C3 after impetigo still mean PSGN.
- Normal C3 rules against PSGN; a low C3 beyond about 8 weeks means rethink.
- Young man with gross hematuria after every cold, normal C3: IgA nephropathy (biopsy confirms).
- Child with buttock and leg purpura, joint pain, abdominal pain and hematuria: IgA vasculitis.
- Older adult with nephritis and a recent or ongoing staphylococcal infection: staph-associated postinfectious GN, increasingly common.
Practice question
An 8-year-old boy is brought in with puffy eyes on waking and dark brown urine for 2 days. Three weeks ago he had crusted, honey-colored sores around his nose that resolved without treatment. He had no sore throat. Blood pressure is 138/88 mm Hg. Urinalysis shows 3+ blood, 1+ protein and red blood cell casts. Serum C3 is low and creatinine is mildly raised. Which additional laboratory finding is most likely?
A. Raised anti-DNase B titer B. Raised serum IgA level C. Low serum C4 D. Raised anti-dsDNA antibodies E. Anti-glomerular basement membrane antibodies
Answer: A. Impetigo 3 weeks earlier, then edema, hypertension, cola urine, RBC casts and a low C3 add up to PSGN after a skin infection. After pyoderma the ASO response is usually weak, but anti-DNase B rises (antibodies peak 1-2 months after infection).
- B: IgA nephropathy follows mucosal infection within 1-2 days and has a normal C3, and no serum test, IgA level included, diagnoses it.
- C: PSGN activates mainly the alternative pathway, so C4 is normal or only slightly reduced. Low C3 with low C4 suggests lupus or immune-complex MPGN.
- D: anti-dsDNA points to lupus nephritis, which is rare in an 8-year-old boy, lowers both C3 and C4, and has no link to a recent skin infection.
- E: anti-GBM disease gives linear IgG on immunofluorescence, a normal C3 and usually a rapidly progressive course, often with lung hemorrhage.
Key takeaways
- Nephritic = hematuria + RBC casts + hypertension + edema + rising creatinine, with sub-nephrotic proteinuria.
- Days = IgA nephropathy (normal C3); weeks = PSGN (low C3).
- PSGN: about 10 days after strep throat, up to about 3 weeks after impetigo (ranges vary by source, up to 6 weeks); low C3, normal C4; ASO after throat, anti-DNase B after skin; subepithelial humps; supportive care; more than 90% of children recover.
- C3 should normalize within 6-8 weeks; if not, think C3 glomerulopathy, MPGN or lupus.
- IgA nephropathy: Gd-IgA1 immune complexes in the mesangium; diagnosed only by biopsy; IgA vasculitis is its systemic twin.
- KDIGO 2025: maximally tolerated ACE inhibitor or ARB (or sparsentan instead), plus an SGLT2 inhibitor; targeted-release budesonide for those at risk; target proteinuria under 0.5 g/day.
- FDA-approved IgAN drugs (Oct 2026): Tarpeyo, Filspari, Fabhalta, plus accelerated approvals for atrasentan, sibeprenlimab and atacicept.
Sources
- Clinical Guidance for Post-Streptococcal Glomerulonephritis — CDC (2025)
- Clinical Guidance for Acute Rheumatic Fever — CDC (2025)
- Postinfectious Glomerulonephritis (PIGN) — Merck Manual Professional Edition (2025)
- Streptococcal Infections — Merck Manual Professional Edition (2025)
- Immunoglobulin A Nephropathy — Merck Manual Professional Edition (2025)
- KDIGO 2025 Clinical Practice Guideline for the Management of IgA Nephropathy and IgA Vasculitis — KDIGO / Kidney International (2025)
- Novel Drug Approvals for 2025 — U.S. Food and Drug Administration
- Tarpeyo (budesonide) prescribing information — DailyMed (2026)
- Filspari (sparsentan) prescribing information — DailyMed (2026)
- Fabhalta (iptacopan) prescribing information — DailyMed (2026)
- Voyxact (sibeprenlimab) prescribing information — DailyMed (2026)
- Trutakna (atacicept) prescribing information — DailyMed (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
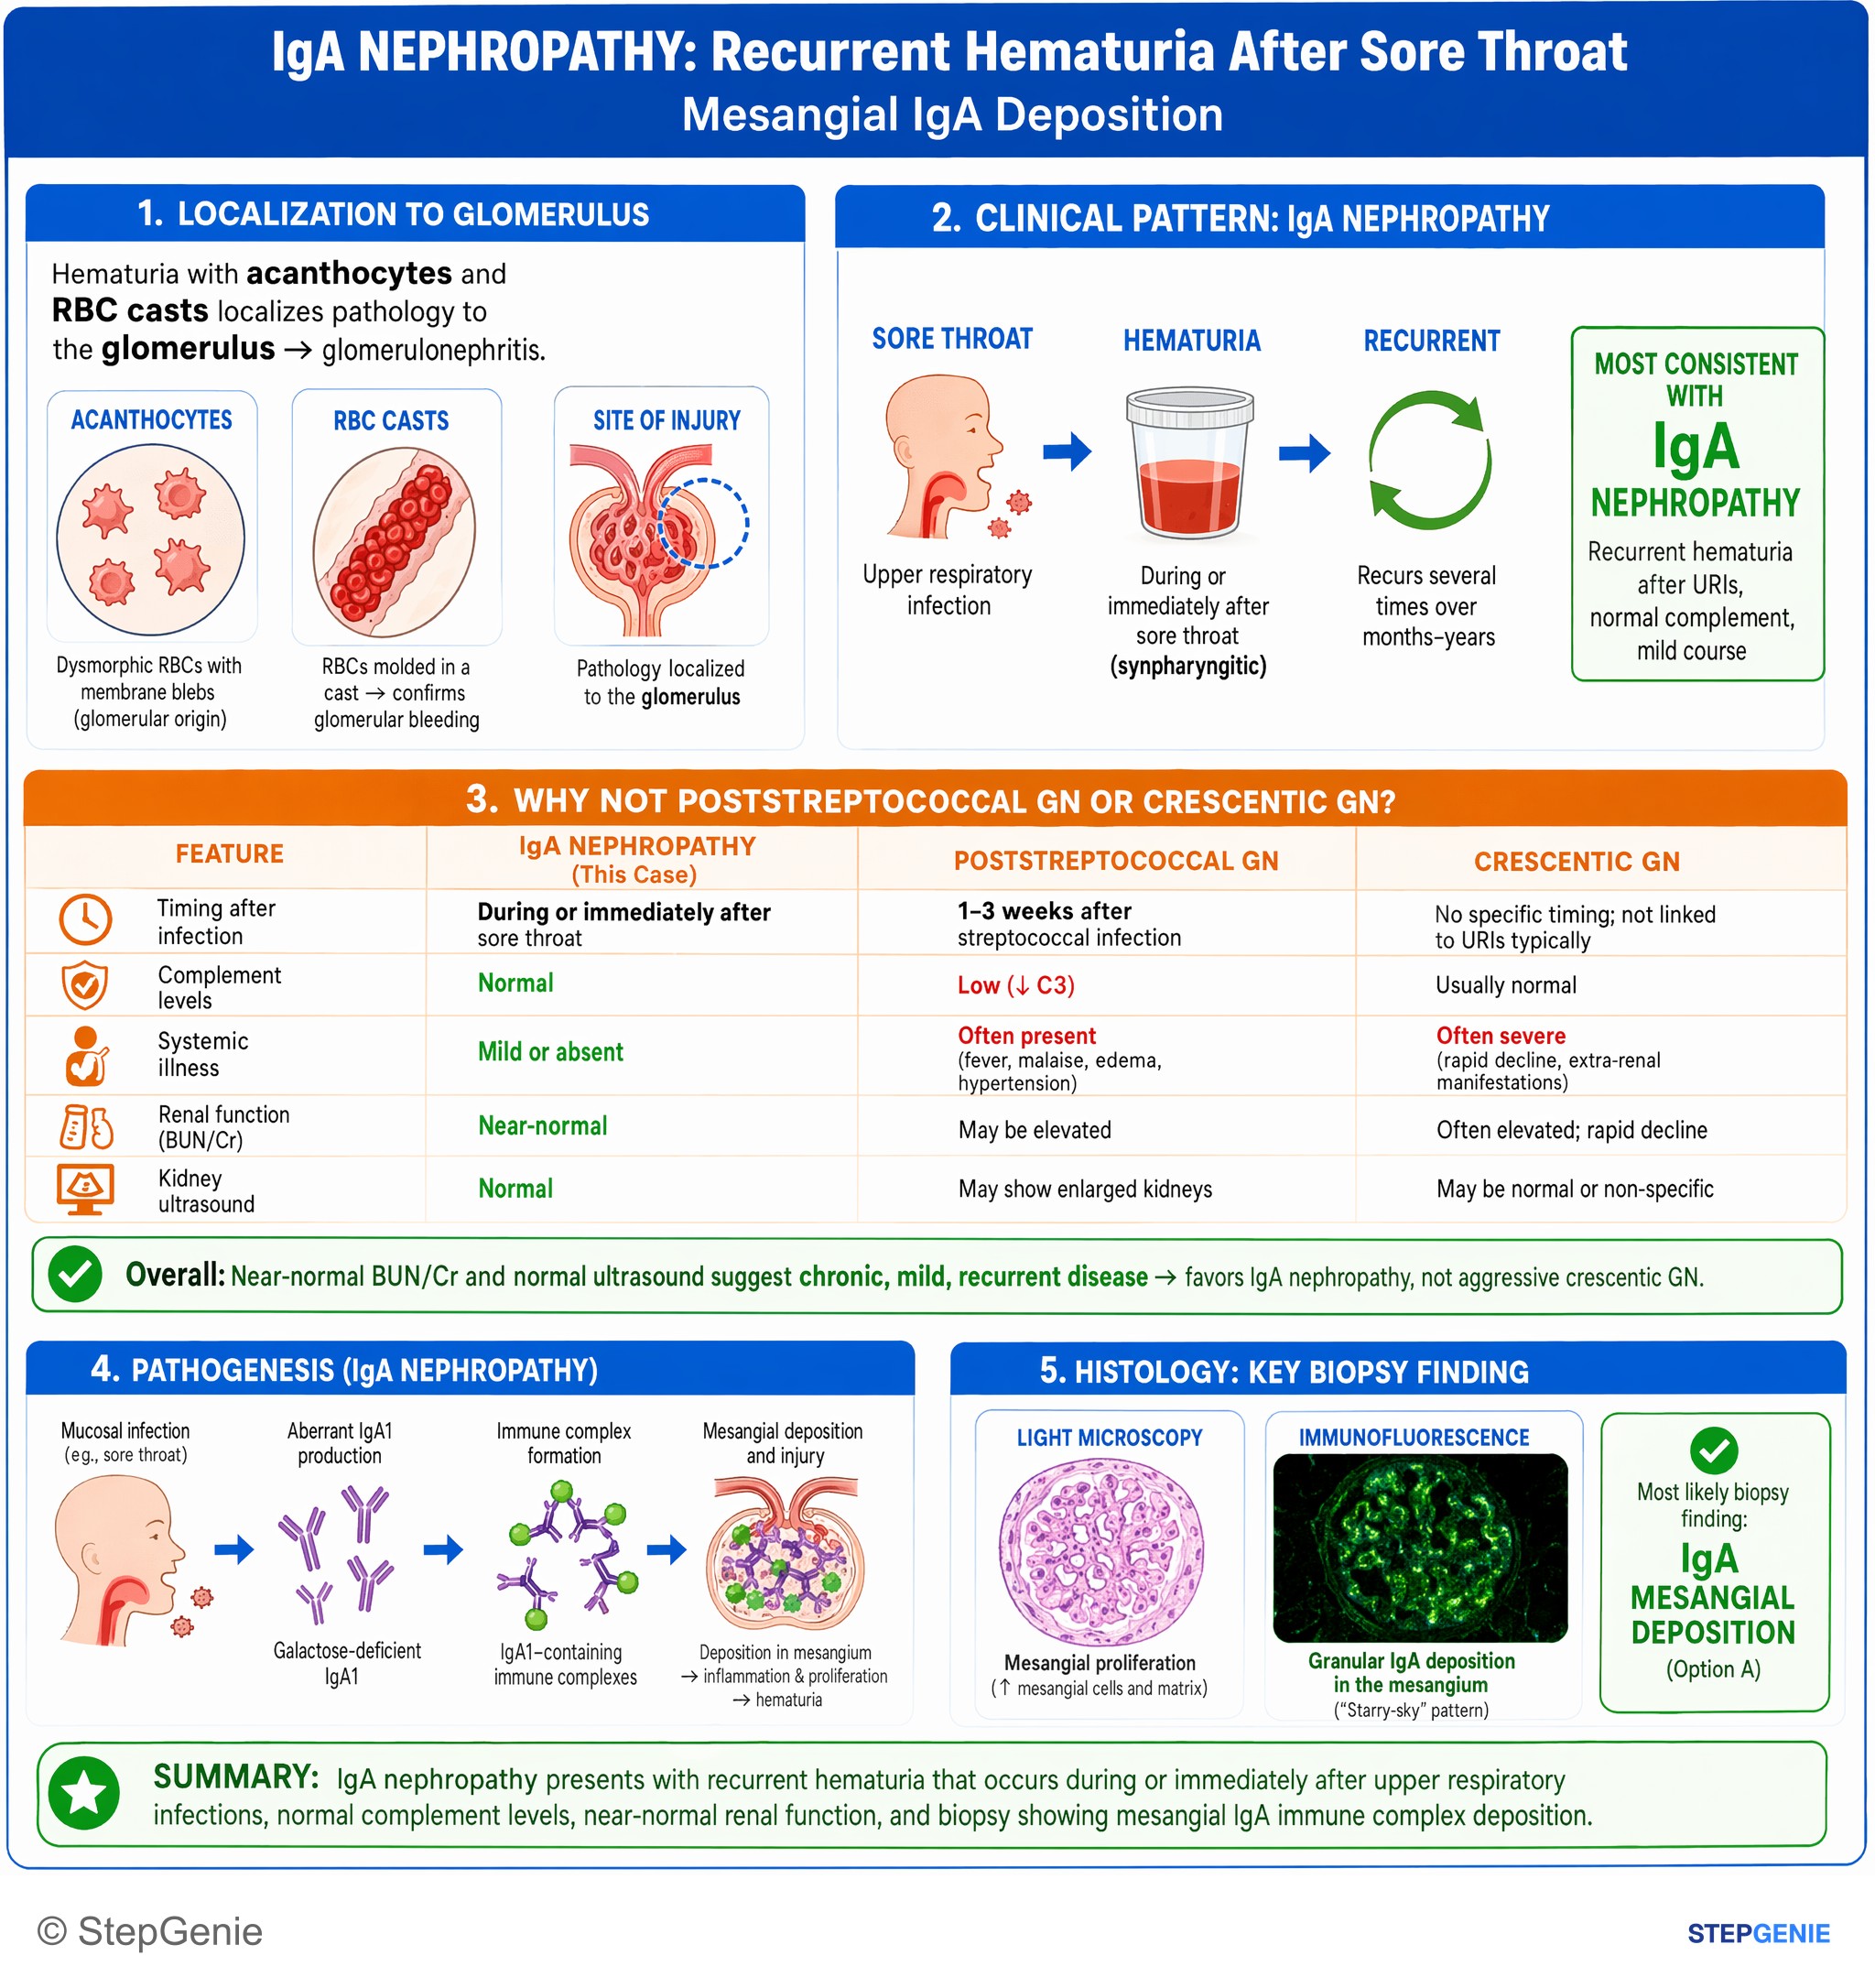
IgA nephropathy: recurrent hematuria after upper respiratory infections, normal complement, biopsy with mesangial IgA immune complex…
USMLE Step 1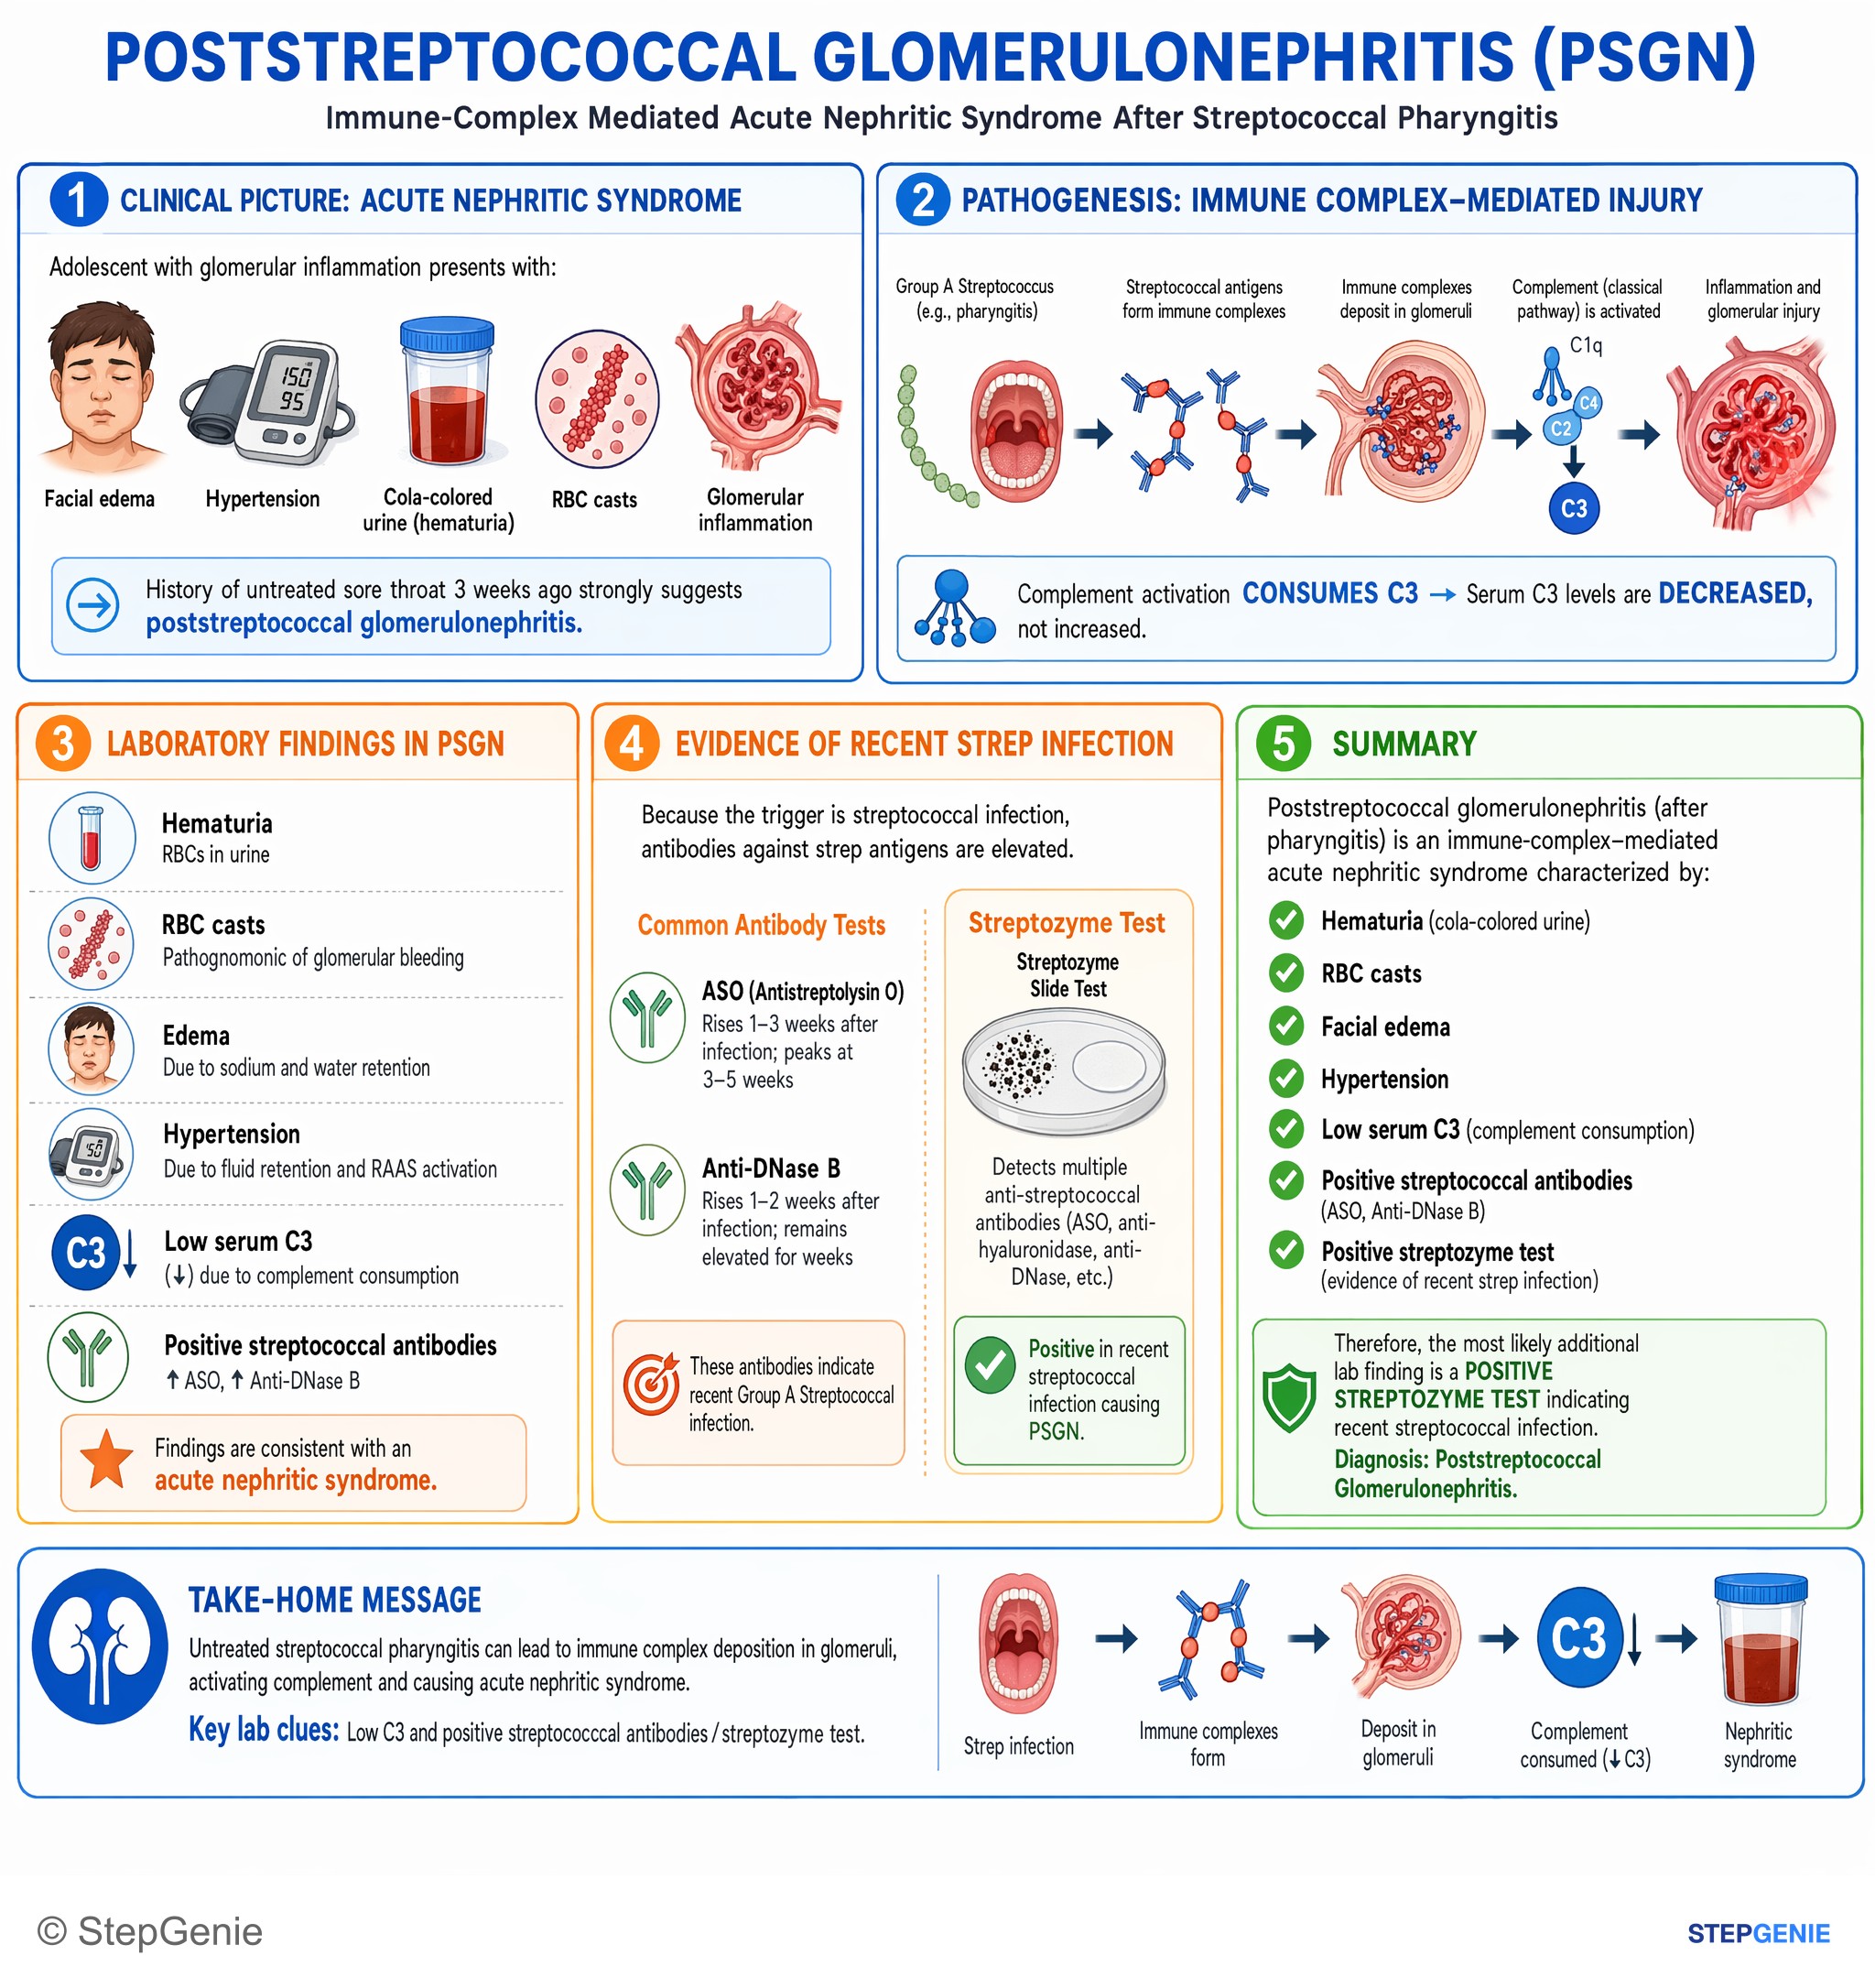
Poststreptococcal glomerulonephritis after pharyngitis: immune-complex nephritic syndrome with hematuria, RBC casts, edema, hypertension…
USMLE Step 1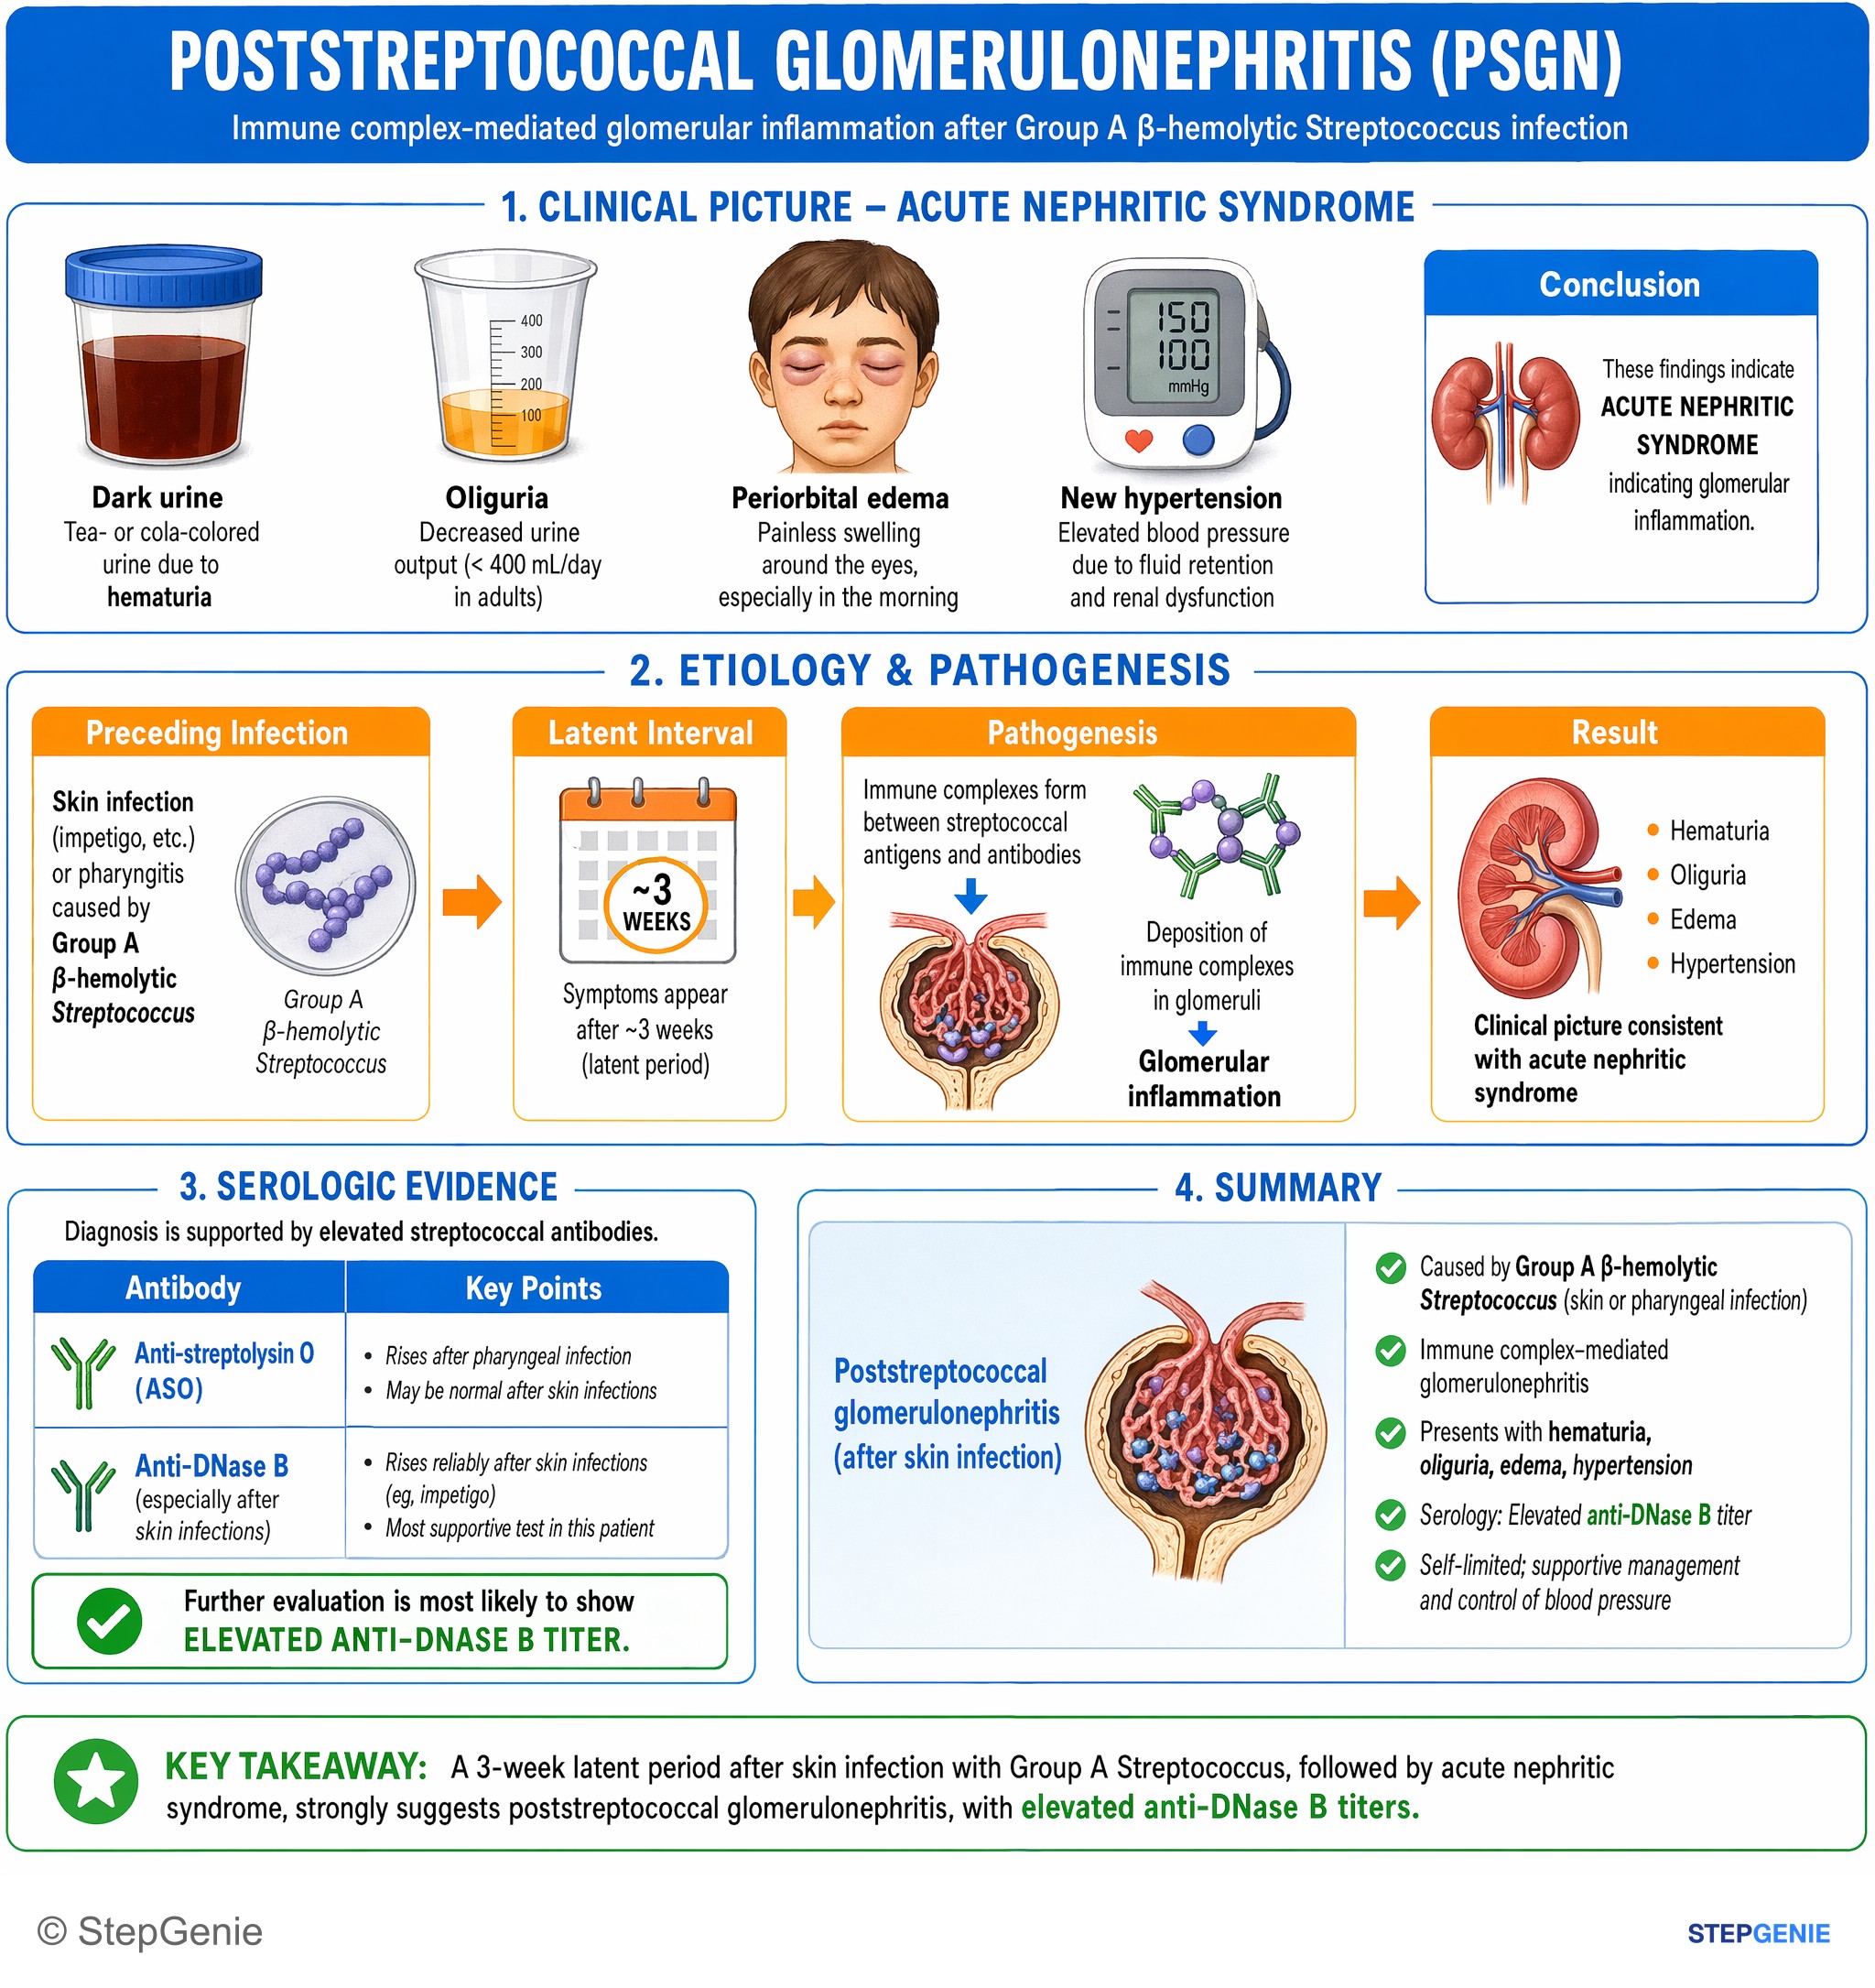
Poststreptococcal glomerulonephritis after skin infection: immune-complex GN with hematuria, oliguria, edema, hypertension, and elevated…
USMLE Step 1Frequently Asked Questions
How do you tell IgA nephropathy from post-streptococcal glomerulonephritis?
Timing and complement separate them fastest. IgA nephropathy causes gross hematuria within 1 to 2 days of a mucosal infection such as a cold, often recurs, and has a normal C3; biopsy shows mesangial IgA deposits. Post-streptococcal glomerulonephritis appears about 10 days after strep throat or up to about 3 weeks after impetigo, usually in a child, with a low C3, raised streptococcal antibodies and subepithelial humps on electron microscopy.
How long after strep throat or impetigo does post-streptococcal glomerulonephritis start?
CDC describes a latent period of about 10 days after streptococcal pharyngitis and up to about 3 weeks after a skin infection such as impetigo. Merck's kidney chapter gives a typical range of 6 to 21 days that can stretch to 6 weeks, and its streptococcal chapter simply says 1 to 3 weeks after infection. The key contrast is that IgA nephropathy causes hematuria within 1 to 2 days of an infection.
Why is C3 low in post-streptococcal glomerulonephritis?
In post-streptococcal glomerulonephritis, streptococcal antigens and antibodies form immune complexes in the glomerular capillary wall, and complement is activated mainly through the alternative pathway. C3 is consumed, so serum C3 and total hemolytic complement (CH50) fall while C4 stays normal or only slightly low. C3 returns to normal within 6 to 8 weeks in about 80 percent of patients; a C3 that stays low longer should prompt a search for C3 glomerulopathy, MPGN or lupus nephritis.
Which strep antibody test is best after impetigo?
Antistreptolysin O (ASO) rises after most streptococcal throat infections but is usually not significantly raised after a skin infection such as impetigo or pyoderma. After a skin infection, anti-DNase B (or antihyaluronidase) is the better marker of recent group A strep infection. These antibodies begin to rise about 1 week after infection and peak 1 to 2 months later, so they are usually raised by the time post-streptococcal glomerulonephritis appears.
What drugs are FDA-approved for IgA nephropathy?
As of October 2026, delayed-release budesonide (Tarpeyo), sparsentan (Filspari) and iptacopan (Fabhalta) are FDA-approved to slow kidney function loss in adults with primary IgA nephropathy at risk of progression. Atrasentan (Vanrafia), sibeprenlimab (Voyxact) and atacicept (Trutakna) have accelerated approval to reduce proteinuria. KDIGO 2025 also recommends a maximally tolerated ACE inhibitor or ARB (or sparsentan in its place) and an SGLT2 inhibitor, aiming for proteinuria under 0.5 g per day.
What are the features of nephritic syndrome?
Nephritic syndrome is glomerular inflammation causing hematuria with dysmorphic red cells and red blood cell casts, hypertension, edema (often around the eyes), a rising creatinine and sometimes oliguria. Proteinuria is present but usually below the nephrotic range of 3.5 grams per day. Red blood cell casts are the key finding because they show the bleeding started inside the nephron. Common causes include post-streptococcal GN, IgA nephropathy, lupus nephritis, MPGN and rapidly progressive glomerulonephritis.