Renal clearance is C = UV/P (urine concentration × urine flow rate ÷ plasma concentration): the volume of plasma completely cleared of a substance per minute (mL/min). Inulin clearance equals GFR (about 120 mL/min), PAH clearance equals effective renal plasma flow (about 600 mL/min), and filtered load equals GFR × plasma concentration.
Compare a clearance with the GFR to see what the tubule did: equal means filtered only, lower means net reabsorption, higher means net secretion. Check units first: U and P must match, and V must be in mL/min.
Drug (pharmacokinetic) clearance is covered in the drug clearance question breakdown.
Renal clearance formulas at a glance
| Quantity | Formula | Typical adult value |
|---|---|---|
| Clearance (mL/min) | Varies by substance | |
| GFR | 120–130 mL/min/1.73 m² (young adults) | |
| Filtered load | GFR × unbound | Glucose about 125 mg/min (180 g/day) |
| Reabsorption or secretion | Filtered load − (positive = reabsorbed, negative = secreted) | Glucose: essentially all reabsorbed |
| Fractional excretion | FENa normally below 1% | |
| Effective RPF | About 600 mL/min | |
| True RPF | About 600–720 mL/min | |
| Renal blood flow | RPF / (1 − Hct) | About 1 L/min (about 20% of cardiac output) |
| Filtration fraction | GFR / RPF | About 0.20 |
| Free water clearance | , with | Positive with dilute urine |
The renal clearance equation: C = UV/P
- is the urine concentration, the urine flow rate (24-hour volume ÷ 1,440 minutes) and the plasma concentration. U and P cancel, so they must share units, leaving mL/min.
- is the excretion rate; the equation assumes a steady state, with stable plasma levels during the collection.
- Example: urine creatinine 120 mg/dL, V = 1 mL/min, plasma creatinine 1.0 mg/dL: = 120 mL/min. Enter urine creatinine as 1.2 mg/mL against 1.0 mg/dL in plasma and you get 1.2 mL/min, a 100-fold error.
| Substance | Tubular handling | Clearance vs GFR |
|---|---|---|
| Inulin | Filtered only | Equal (about 120 mL/min) |
| Glucose (normal level) | Filtered, almost all reabsorbed (mostly by SGLT2) | About 0 |
| Sodium | More than 99% of the filtered load reabsorbed | Under 1% of GFR |
| Urea | 40–60% reabsorbed, more at low urine flow | Well below |
| Creatinine | Filtered and slightly secreted | About 10–20% above |
| PAH (low plasma level) | Filtered and avidly secreted | About 600 mL/min, close to RPF |
Filtered load formula: excretion, reabsorption and secretion
- Only unbound solute is filtered. About 40% of serum calcium is protein-bound, so calcium's filtered load is GFR × its ultrafilterable fraction (about 60%); even phosphate is only about 90% ultrafilterable.
- Excretion = ; net reabsorption = filtered load − excretion; net secretion = excretion − filtered load.
| Example (GFR 125 mL/min) | Filtered load | Result |
|---|---|---|
| Glucose 100 mg/dL (1 mg/mL) | 125 mg/min, about 180 g/day | Essentially all reabsorbed |
| Sodium 140 mEq/L | About 25,200 mEq/day (180 L/day × 140) | Excreting 150 mEq/day is an FENa of 0.6% |
| Substance Y 0.5 mg/mL (GFR 120) | 60 mg/min | 40 mg/mL × 2 mL/min = 80 mg/min excreted: net secretion 20 mg/min; = 160 mL/min |
Glucose threshold and transport maximum (). Reabsorption rises with filtered load until the transporters saturate: about 375 mg/min in men and 300 in women (OpenStax), though StatPearls gives 0.9–2.0 mmol/min (about 160–360 mg/min). Glucosuria starts above about 180 mg/dL, the commonly accepted renal threshold (Merck: 160–180; OpenStax: about 200). At 400 mg/dL, the filtered load is 500 mg/min; with a of 375, about 125 mg/min is excreted, a glucose clearance of about 31 mL/min, still below GFR.
- Pregnancy lowers the threshold; age and diabetic glomerulosclerosis raise it.
- SGLT2 handles over 90% of glucose reabsorption, so SGLT2 inhibitors lower the threshold and raise glucose clearance (tubular reabsorption and secretion breakdown).
PAH clearance formula: effective RPF, true RPF and RBF
- PAH (para-aminohippurate) is filtered and actively secreted by the proximal tubule via the organic anion transporters OAT1 and OAT3. At low plasma levels (1–2 mg/dL), an average of 90% is removed from renal blood in one pass, so PAH clearance is effective RPF, slightly below true RPF.
- Extraction ratio: (arterial and renal venous PAH); true RPF = , which needs a renal vein sample.
- Renal blood flow: RBF = RPF / (1 − Hct).
Worked example: arterial PAH 0.02 mg/mL, renal vein PAH 0.002 mg/mL, urine PAH 9 mg/mL, V = 1.2 mL/min, hematocrit 40%.
- = 9 × 1.2 / 0.02 = 540 mL/min (effective RPF)
- = (0.02 − 0.002) / 0.02 = 0.90
- True RPF = 540 / 0.90 = 600 mL/min
- RBF = 600 / (1 − 0.40) = 1,000 mL/min
- With a GFR of 120 mL/min, FF = 120 / 600 = 0.20 (0.22 with effective RPF)
PAH clearance underestimates RPF when plasma PAH is high (40–60 mg/dL saturates secretion; used to measure PAH), when competing organic anions are present (probenecid, penicillin, salicylates), and when tubules are injured: extraction is not constant in sepsis or AKI, and after renal ischemia in rats, uncorrected PAH clearance underestimated RPF about threefold.
Inulin clearance formula and measured GFR
- Why inulin: a plant polysaccharide that is freely filtered and not reabsorbed, secreted, made or metabolized by the kidney; because it needs a continuous infusion, it is used mostly in research.
- Example: plasma 0.25 mg/mL, urine 25 mg/mL, V = 1.25 mL/min: GFR = 25 × 1.25 / 0.25 = 125 mL/min.
- Normal values: 120–130 mL/min/1.73 m² in young adults, about 75 by age 70; roughly 180 L of filtrate a day in men, about 99% of it reabsorbed. Indexing to 1.73 m² of body surface area compares people of different size. In pregnancy, GFR rises 30–50% and creatinine falls to about 0.5–0.7 mg/dL.
- Today's gold standard (KDIGO 2024) is measured GFR (mGFR): urinary or plasma clearance of iohexol, iothalamate, chromium-51 EDTA or technetium-99m DTPA. Plasma methods need no urine collection.
Creatinine clearance and eGFR: CKD-EPI 2021 vs the classic answer
Why creatinine clearance overestimates GFR: creatinine, made from muscle creatine at a fairly steady rate, is freely filtered and also secreted by the tubules, so exceeds GFR by about 10–20% with normal kidney function and by up to 50% in advanced kidney failure.
24-hour collection, worked: 1,440 mL in 24 hours (V = 1 mL/min), urine creatinine 120 mg/dL, serum creatinine 1.0 mg/dL: = 120 mL/min. That is 1,728 mg/day of creatinine, about 25 mg/kg/day for a 70-kg man (normal 14–26 in men, 11–20 in women); lose half the urine and the result falls to a falsely low 60 mL/min. KDIGO 2024 calls timed collections "highly prone to errors" (mean bias 25%, in both directions) and reserves them for when mGFR is unavailable and the creatinine-cystatin C estimate seems inaccurate.
Serum creatinine traps:
- At steady state, production equals excretion (about GFR × plasma creatinine): doubling serum creatinine means GFR has roughly halved, and creatinine can stay normal until about half of kidney function is lost.
- Muscular people run higher levels, older or undernourished people lower ones; a cooked-meat meal can add about 0.23 mg/dL.
- Blocked secretion raises creatinine without changing GFR: trimethoprim (by about 15–22%), cimetidine, dolutegravir. On dolutegravir, 24-hour creatinine clearance fell 9–13% while iohexol GFR and PAH clearance were unchanged; its label cites inhibition of OCT2 (and possibly MATE1).
CKD-EPI 2021 uses serum creatinine (mg/dL), age and sex, with no race term, and reports mL/min/1.73 m²:
κ is 0.7 for women and 0.9 for men; α is −0.241 for women and −0.302 for men. For a 60-year-old man with creatinine 1.2 mg/dL: 142 × 0.708 × 0.689 ≈ 69 mL/min/1.73 m²; the same creatinine in a 60-year-old woman gives about 52.
Cockcroft-Gault, the classic formula, estimates creatinine clearance in mL/min, not indexed to body size:
A 72-year-old, 60-kg man with creatinine 1.3 mg/dL: 68 × 60 / (72 × 1.3) ≈ 44 mL/min, against a CKD-EPI 2021 eGFR of about 58. KDIGO notes that it predates standardized creatinine assays and relies on weight, which edema and obesity distort.
| Question | Classic USMLE answer | Current practice (KDIGO 2024; NKF-ASN) |
|---|---|---|
| Best measure of GFR | Inulin clearance | mGFR (iohexol, iothalamate or a radiotracer) |
| First test | Creatinine or 24-hour creatinine clearance | eGFR from a validated equation; in the US, race-free CKD-EPI 2021 |
| Creatinine misleading (amputation, muscle wasting, cirrhosis, drugs) | 24-hour creatinine clearance | Add cystatin C; measure GFR if a decision hinges on it |
| Race | Black race coefficient (MDRD, 2009 CKD-EPI) | Avoid race |
| Drug dosing | Cockcroft-Gault | Validated eGFR for most drugs; non-indexed eGFR (mL/min) at extremes of body size |
- Cystatin C, made by all nucleated cells, is filtered, then reabsorbed and broken down by the proximal tubule, so it is a serum marker, not a urine clearance. Muscle barely affects it; adiposity, smoking, thyroid disease, glucocorticoid excess and inflammation do.
- CKD stages (G1 to G5) are set by eGFR (CKD stages mnemonic); marker-choice questions are in the GFR estimation question breakdown.
Filtration fraction: the ratio of GFR to RPF
About 20% of the plasma reaching the glomeruli is filtered; a higher FF leaves more concentrated protein in the peritubular capillaries and increases proximal reabsorption. Use plasma flow, not blood flow. Net filtration pressure is glomerular capillary pressure − (Bowman's space pressure + capillary oncotic pressure), about 55 − (15 + 30) = 10 mm Hg.
| Change | RPF | GFR | FF | Classic cause |
|---|---|---|---|---|
| Afferent constriction | ↓ | ↓ | No change | NSAIDs (loss of afferent-dilating PGE2 and PGI2) |
| Efferent constriction | ↓ | ↑ | ↑ | Angiotensin II |
| Efferent dilation | ↑ | ↓ | ↓ | ACE inhibitors, ARBs |
| ↑ Plasma protein | No change | ↓ | ↓ | Multiple myeloma |
| ↓ Plasma protein | No change | ↑ | ↑ | Nephrotic syndrome (in patients, podocyte injury lowers Kf, so GFR is usually normal or low) |
| ↑ Bowman's space pressure | No change | ↓ | ↓ | Ureteral obstruction (stone) |
| Volume depletion | ↓↓ | ↓ | ↑ | Dehydration |
- ACE inhibitors and ARBs cut GFR most when angiotensin II is propping it up: renal artery stenosis (bilateral or in a solitary kidney), volume depletion or diuretics; adding an NSAID is a relative contraindication (ACE inhibitor and ARB mnemonic).
- SGLT2 inhibitors raise distal sodium delivery, increasing tubuloglomerular feedback and lowering intraglomerular pressure: expect a small, reversible early eGFR dip.
- ANP dilates the afferent and constricts the efferent arteriole, raising GFR (renal blood flow autoregulation).
Fractional excretion: FENa and FEUrea
FE is the clearance of x divided by the creatinine clearance; urine flow cancels, so a spot urine sample works.
- FENa below 1% suggests prerenal AKI (tubules holding on to sodium); above 2% suggests acute tubular necrosis (Merck uses above 1%). Other prerenal clues: urine sodium below 20 mEq/L and BUN:creatinine above 20 (below 10 in tubular injury).
- FEUrea below 35% suggests prerenal and above 50% intrinsic AKI; use it in patients taking diuretics.
- Worked: urine Na 20 mEq/L, plasma Na 140, urine creatinine 100 mg/dL, plasma creatinine 2.0: FENa = (20 × 2.0)/(140 × 100) × 100 = 0.29%. Urine Na 60, plasma Na 135, urine creatinine 40, plasma creatinine 4.0: 4.4%.
| Pitfall | FENa | Note |
|---|---|---|
| Diuretics | Falsely high | Use FEUrea |
| Contrast nephropathy, acute glomerulonephritis, vasculitis | Can be below 1% | GFR falls, tubular function kept |
| Heart failure, cirrhosis | May stay low | Does not exclude tubular injury |
| Reduced baseline GFR (CKD) | Higher | Fewer nephrons excrete the same sodium intake |
| Nonoliguric AKI | Unreliable | Indices help mainly in oliguria |
| No AKI | Normally below 1% | Not a diagnosis by itself |
No single marker reliably separates the causes of AKI (StatPearls, 2026); see prerenal vs intrinsic vs postrenal AKI.
Free water clearance
is solute-free water excreted per minute; a negative value is free water reabsorption ().
| Urine | ADH (AVP) | Examples | |
|---|---|---|---|
| Positive | Dilute (hypotonic) | Low or ineffective | Primary polydipsia; AVP deficiency (central DI); AVP resistance (nephrogenic DI) |
| Zero | Isosmotic | Urine osmolality = plasma osmolality | Osmolar clearance equals urine flow |
| Negative | Concentrated (hypertonic) | Acting | Dehydration; SIADH (urine usually hypertonic to plasma) |
Worked: V = 10 mL/min, urine 100 and plasma 290 mOsm/kg: = 3.4 mL/min, so = +6.6 mL/min. SIADH with V = 0.5 mL/min, urine 600 and plasma 270 mOsm/kg: −0.6 mL/min. AVP deficiency and AVP resistance are the new names for central and nephrogenic DI (central vs nephrogenic diabetes insipidus).
Electrolyte-free water clearance uses urinary sodium and potassium instead of total osmolality:
- A Furst ratio, , above 1 suggests fluid restriction alone will fail, though in a 2025 prospective study it predicted failure only modestly (AUC 0.65). Plasma Na 125 with urine Na + K 160 mEq/L gives 1.28: at 1 mL/min, = −0.28 mL/min.
- A positive value is not automatically reassuring: a 2026 review says values above about 500–800 mL/day predict a response to fluid restriction (SIADH vs psychogenic polydipsia).
- Thiazides act in the distal convoluted tubule and impair free water generation; they are the most common cause of drug-induced hyponatremia needing admission (thiazide mnemonic).
USMLE traps: classic teaching vs current evidence
| Trap | What's actually true |
|---|---|
| Glucose 100 mg/dL × GFR 125 mL/min = 12,500 mg/min | Convert to mg/mL first: 125 mg/min |
| RBF = RPF × (1 − Hct); FF = GFR / RBF | RBF = RPF / (1 − Hct); FF = GFR / RPF (plasma, not blood) |
| PAH clearance = true RPF | It is effective RPF; true RPF = / extraction, and extraction is unreliable in AKI and sepsis |
| 24-hour creatinine clearance is the accurate test | Secretion inflates it and collection errors go both ways; eGFR first, then cystatin C, then mGFR |
| Rising creatinine = falling GFR | Not if secretion is blocked (trimethoprim, cimetidine, dolutegravir) or generation rose |
| Filtered calcium = GFR × total calcium | Only the unbound fraction is filtered |
| FENa below 1% = prerenal | Also contrast nephropathy, acute GN, vasculitis; on diuretics use FEUrea |
| Positive free water clearance = sodium will rise | Compare electrolyte-free water clearance with intake |
More renal topics are on the Nephrology hub.
Worked USMLE-style vignettes
Vignette 1: inulin, PAH and substance X. A volunteer receives continuous inulin and PAH infusions; urine flow is 2 mL/min. Inulin: plasma 0.5 mg/mL, urine 30 mg/mL. PAH: plasma 0.02 mg/mL, urine 6 mg/mL. Substance X (freely filtered): plasma 1 mg/mL, urine 30 mg/mL. Which statement is correct?
- A. GFR 120 mL/min, FF 0.20, net reabsorption of X 60 mg/min
- B. GFR 120 mL/min, FF 0.20, net secretion of X 60 mg/min
- C. GFR 60 mL/min, FF 0.10, X filtered only
- D. GFR 600 mL/min, FF 5.0, net reabsorption of X
- E. GFR 120 mL/min, FF 0.50, X completely reabsorbed
Answer: A. = 30 × 2 / 0.5 = 120 mL/min; = 6 × 2 / 0.02 = 600 mL/min, so FF = 0.20. X: filtered 120 mg/min, excreted 60 mg/min, so 60 mg/min is reabsorbed.
- B: excretion is below the filtered load, so X was reabsorbed.
- C: 60 mL/min is the clearance of X, not the GFR.
- D: 600 mL/min is the PAH clearance; FF cannot exceed 1.
- E: complete reabsorption would leave no X in the urine.
Vignette 2: creatinine rise on a new drug. A 34-year-old man with HIV starts a dolutegravir-based regimen. Four weeks later his creatinine has risen from 0.90 to 1.05 mg/dL and stays there; blood pressure, potassium and urinalysis are normal, and iohexol GFR is unchanged. What explains the rise?
- A. Afferent arteriolar constriction
- B. Efferent arteriolar dilation
- C. Acute interstitial nephritis
- D. Inhibition of tubular creatinine secretion
- E. Increased creatinine generation by muscle
Answer: D. Dolutegravir blocks creatinine secretion (OCT2, possibly MATE1); its label reports an early, stable creatinine rise with unchanged iohexol GFR and PAH clearance.
- A and B: both lower GFR (the NSAID and ACE inhibitor patterns), but measured GFR did not change.
- C: kidney injury would lower GFR.
- E: nothing suggests more muscle or creatine intake.
Vignette 3: FENa on furosemide. A 76-year-old woman with heart failure takes furosemide and has eaten poorly for a week. Creatinine is 2.0 mg/dL (baseline 1.0), BUN 56 mg/dL, plasma sodium 134 mEq/L. Spot urine: sodium 64 mEq/L, creatinine 40 mg/dL, urea nitrogen 280 mg/dL, a few hyaline casts. Ultrasound shows no hydronephrosis or retained urine. Most likely cause of her AKI?
- A. Acute tubular necrosis
- B. Prerenal AKI
- C. Postrenal obstruction
- D. Acute interstitial nephritis
- E. Rapidly progressive glomerulonephritis
Answer: B. FENa = (64 × 2.0)/(134 × 40) × 100 = 2.4%, but furosemide raises urinary sodium. FEUrea = (280 × 2.0)/(56 × 40) × 100 = 25% (below 35%), and BUN:creatinine is 28: prerenal.
- A: the high FENa is a diuretic effect; FEUrea argues against tubular necrosis.
- C: no hydronephrosis or retained urine.
- D: furosemide can cause interstitial nephritis, but there is no rash or abnormal sediment.
- E: no red cell casts or dysmorphic red cells.
Key takeaways
- C = UV/P in mL/min, with U and P in the same units; versus GFR: equal = filtered only, lower = net reabsorption, higher = net secretion.
- Filtered load = GFR × unbound plasma concentration; reabsorption = filtered − excreted; secretion = excreted − filtered.
- Inulin (or iohexol) clearance = GFR; creatinine clearance overestimates it by 10–20% (secretion). Clinically: race-free eGFR, then cystatin C, then measured GFR.
- PAH clearance = effective RPF (about 600 mL/min); true RPF = / extraction; RBF = RPF / (1 − Hct); FF = GFR / RPF (about 0.20).
- FENa below 1% suggests prerenal AKI, above 2% tubular necrosis; on diuretics, use FEUrea (below 35% = prerenal).
- : positive with dilute urine, negative with concentrated urine.
Sources
- Physiology, Glomerular Filtration Rate — StatPearls (2023)
- Physiology, Renal Blood Flow and Filtration — StatPearls (2023)
- Creatinine Clearance — StatPearls (2024)
- Renal Function Tests — StatPearls (2024)
- Physiology, Glycosuria — StatPearls (2023)
- Prerenal Kidney Failure — StatPearls (2023)
- Acute Kidney Injury — StatPearls (2026)
- Physiology, Calcium — StatPearls (2026)
- Angiotensin-Converting Enzyme Inhibitors — StatPearls (2023)
- Syndrome of Inappropriate Antidiuretic Hormone Secretion — StatPearls (2023)
- Glucosuria — Clinical Methods (1990)
- BUN and Creatinine — Clinical Methods (1990)
- Urinary Clearance Measurements — National Research Council (1995)
- Primary Disorders of Phosphate Metabolism — Endotext (2025)
- The Neurohypophysis — Endotext (2025)
- Free Water Clearance Definitions — Laboratory Manual of Kidney Perfusion Techniques (2017)
- KDIGO 2024 CKD Guideline — Kidney International (2024)
- CKD-EPI Creatinine Equation (2021) — National Kidney Foundation
- Inker LA, et al. GFR Equations without Race — N Engl J Med (2021)
- Delgado C, et al. NKF-ASN Task Force on GFR Estimation — Am J Kidney Dis (2022)
- Evaluation of the Patient With Renal Issues — Merck Manual (2025)
- Acute Kidney Injury — Merck Manual (2026)
- Physiology of Pregnancy — Merck Manual (2024)
- Type 1 Diabetes Mellitus — Merck Manual (2025)
- 25.5 Physiology of Urine Formation — OpenStax (2022)
- 25.6 Tubular Reabsorption — OpenStax (2022)
- 25.8 Endocrine Regulation of Kidney Function — OpenStax (2022)
- p-Aminohippuric Acid — PubChem, NLM
- Bischoff A, et al. PAH Clearance After Renal Ischemia — Physiol Rep (2014)
- Langenberg C, et al. Renal Blood Flow in Sepsis — Crit Care (2005)
- Guasch A, Myers BD. Hypofiltration in Minimal Change Nephropathy — J Am Soc Nephrol (1994)
- Martínez-Sánchez FD, et al. Hyponatremia: Evolving Diagnostics — World J Nephrol (2026)
- Chienwichai K, et al. Urine Electrolytes and Fluid Restriction in SIAD — Kidney360 (2025)
- Nadal J, et al. Thiazide-Induced Hyponatremia — Curr Hypertens Rep (2018)
- Tivicay (dolutegravir) label — DailyMed (2026)
- Jardiance (empagliflozin) label — DailyMed (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
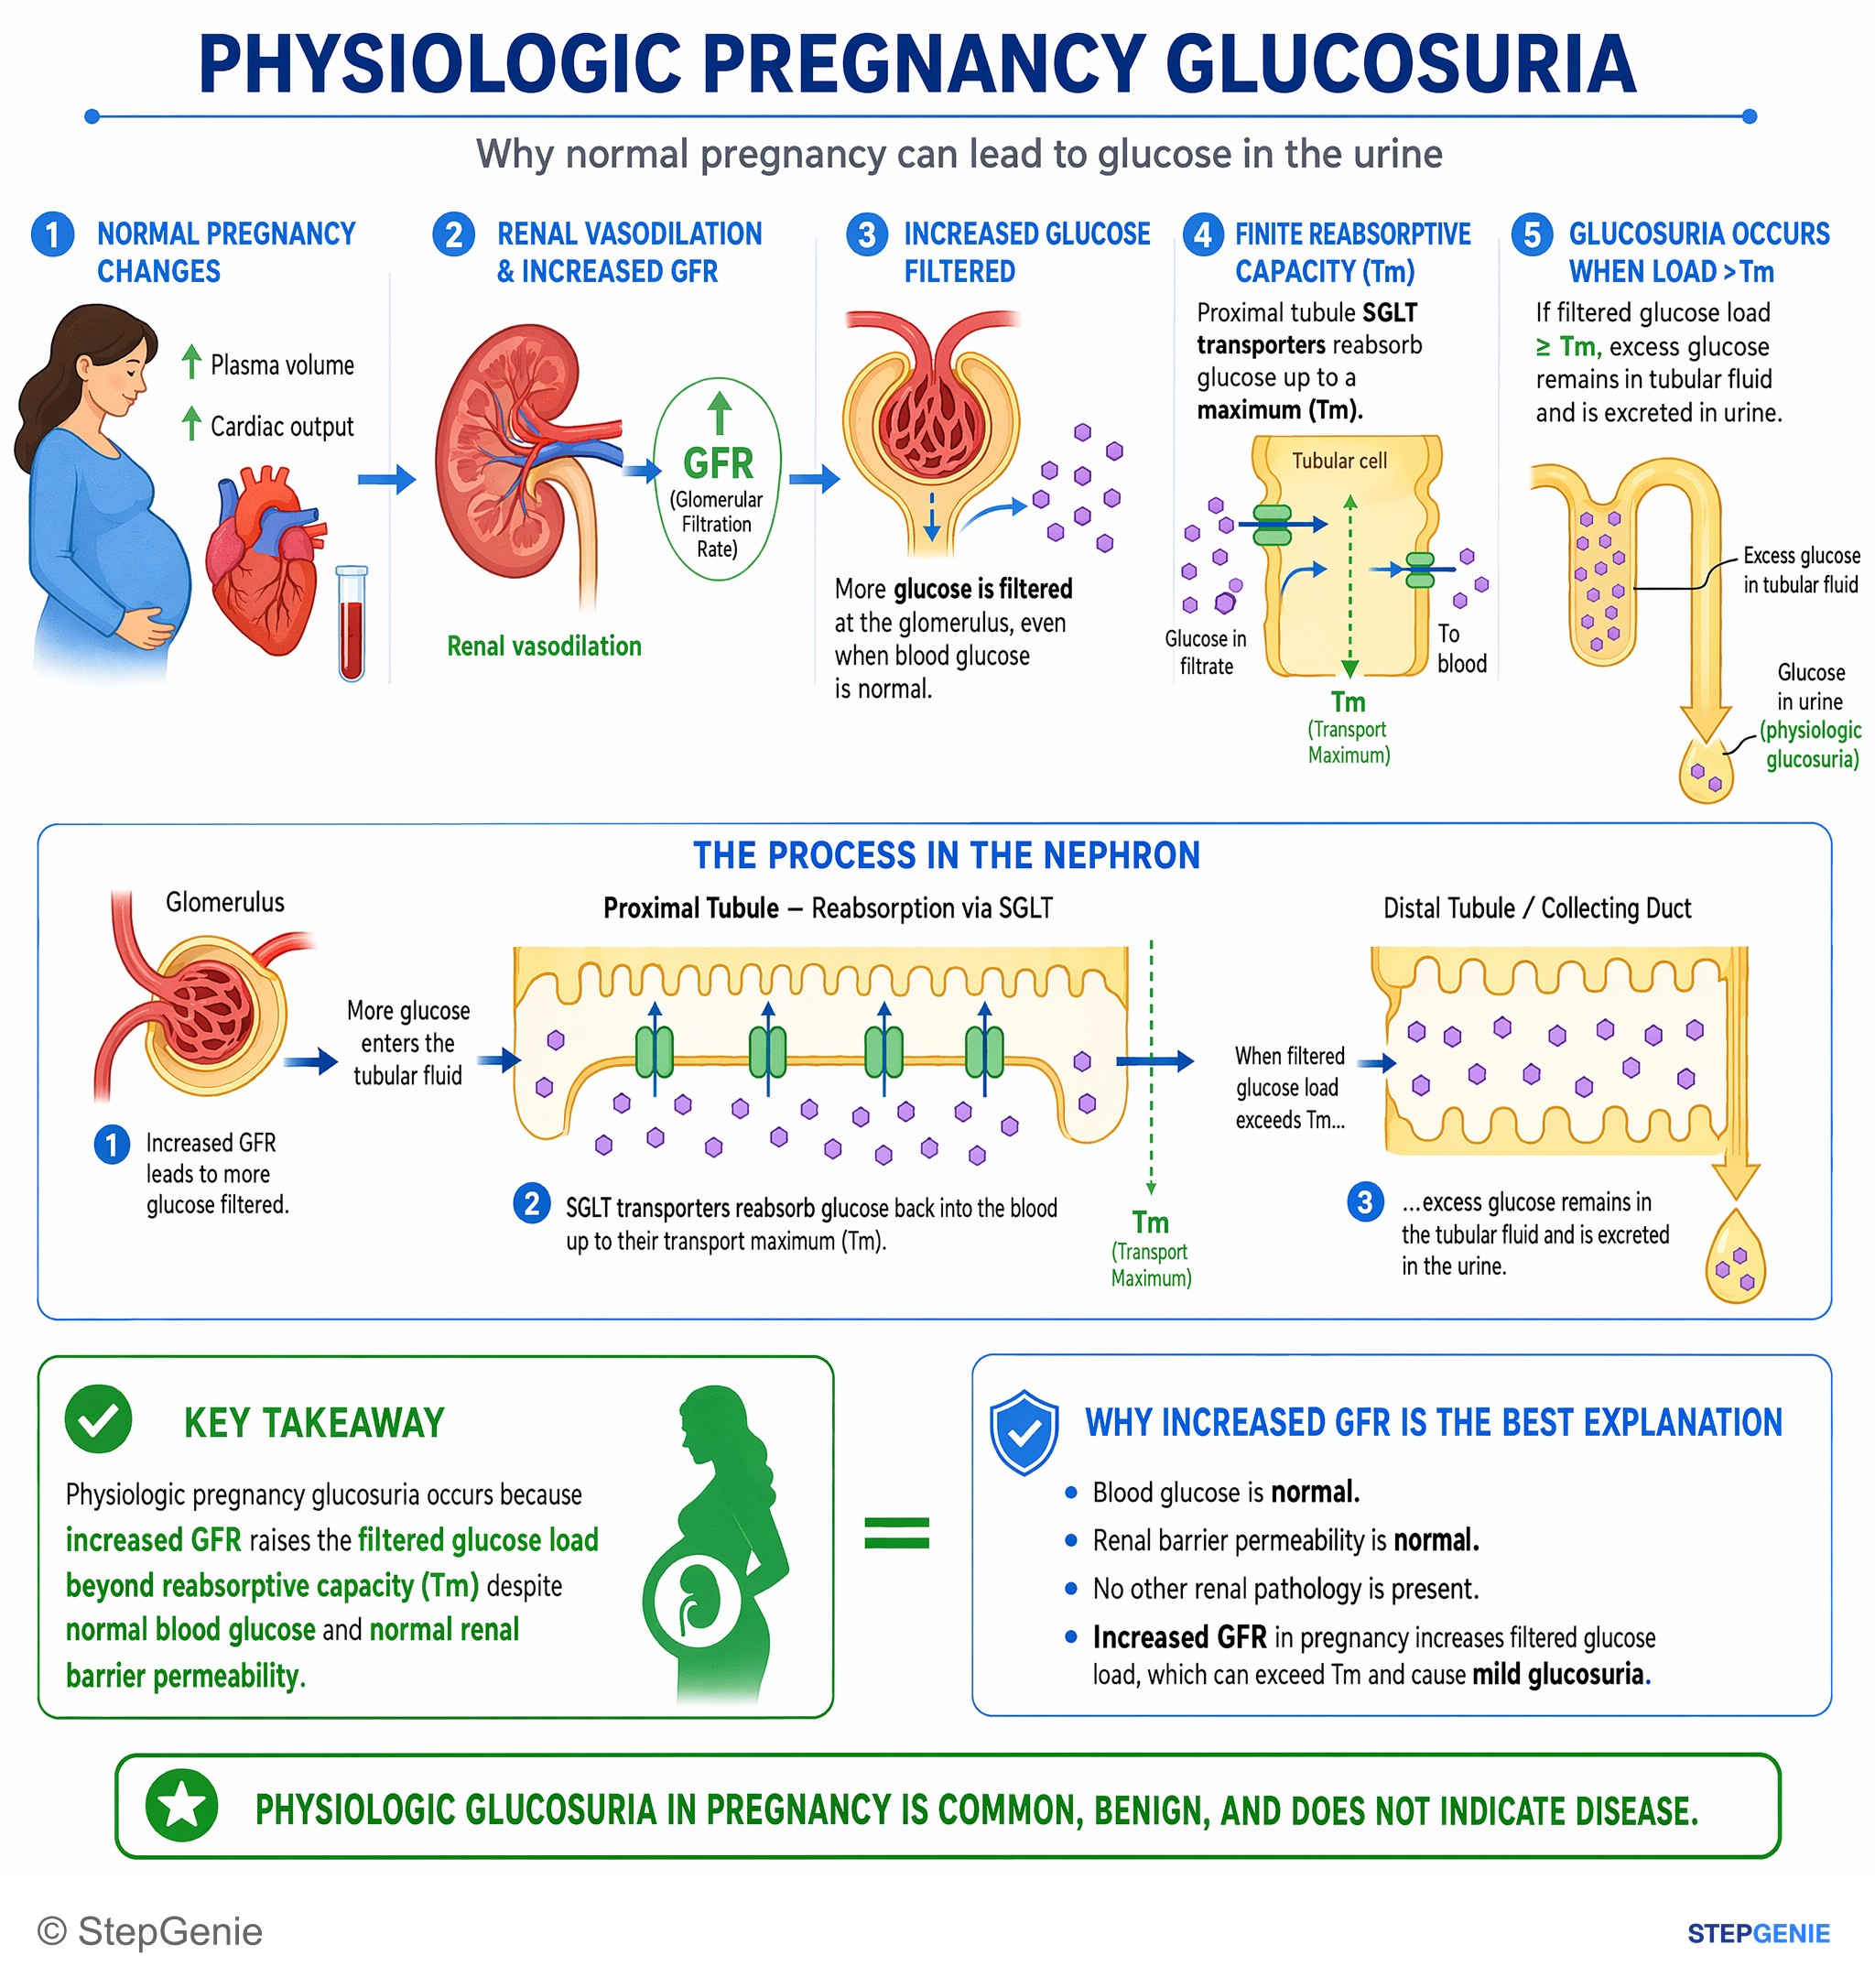
Physiologic pregnancy glucosuria: increased GFR raises filtered glucose load beyond reabsorptive capacity despite normal blood glucose and…
USMLE Step 1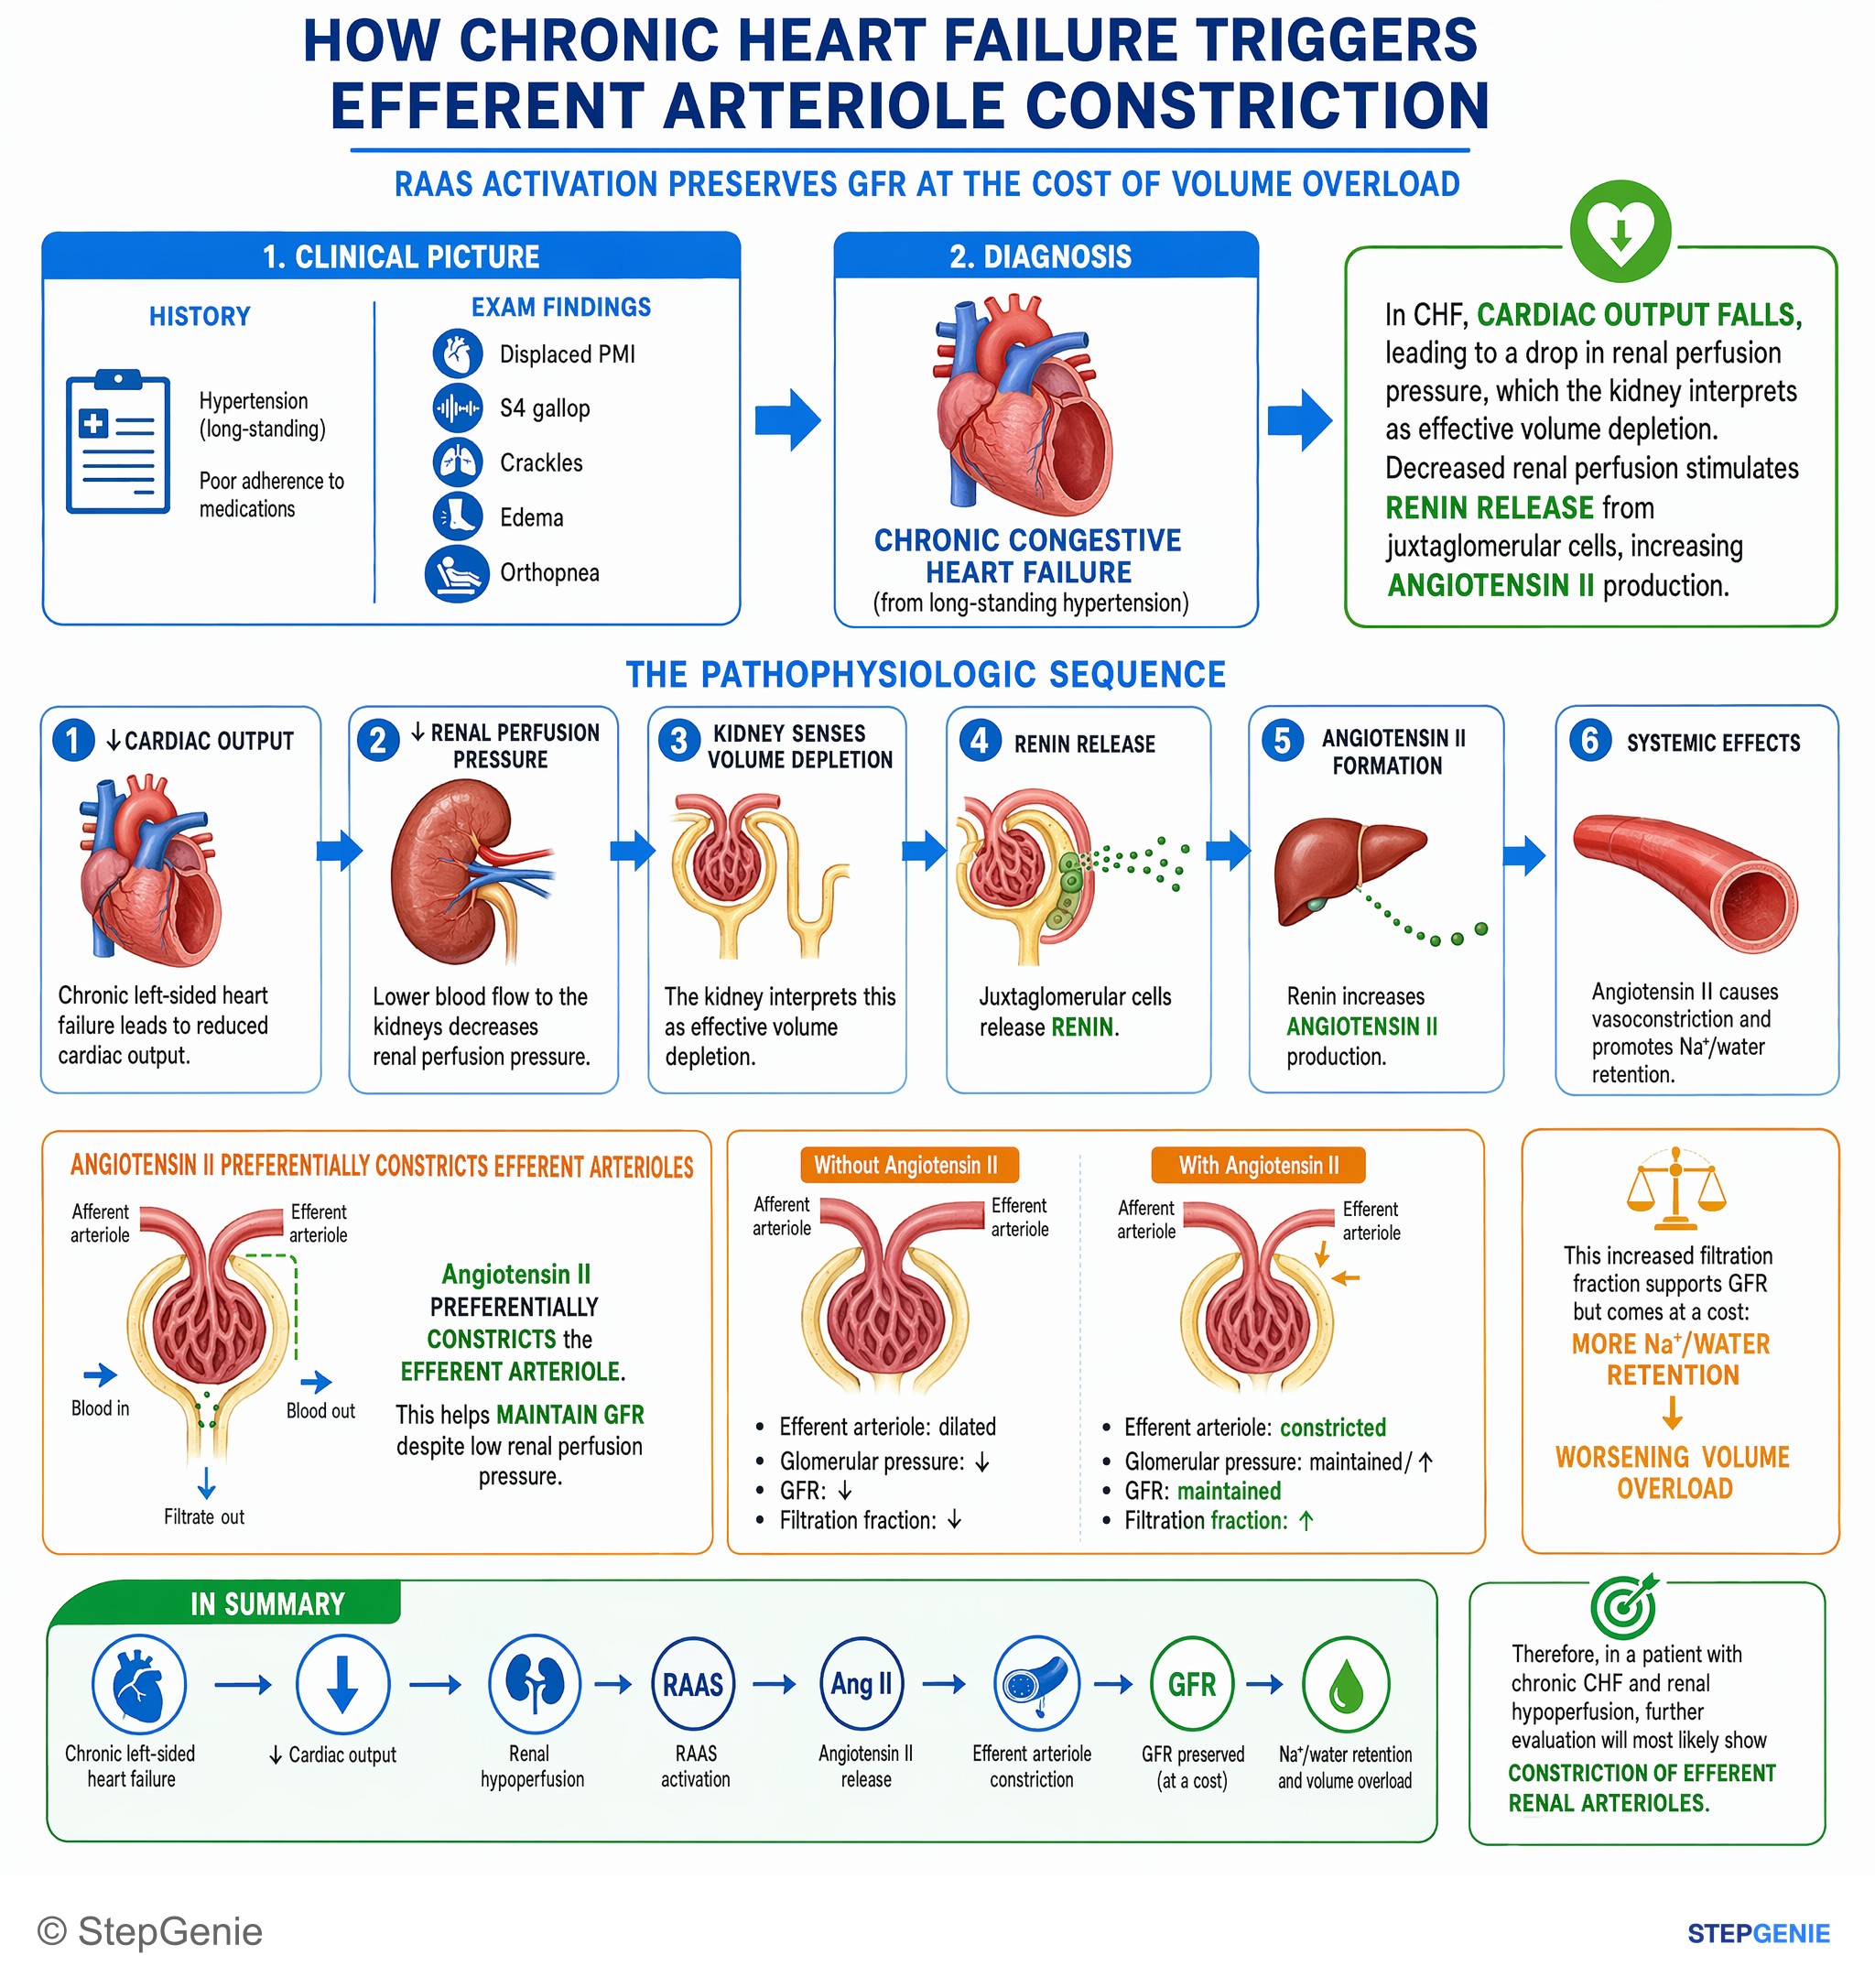
Chronic left-sided heart failure → ↓ cardiac output and renal hypoperfusion → RAAS activation → angiotensin II–mediated efferent arteriole…
USMLE Step 1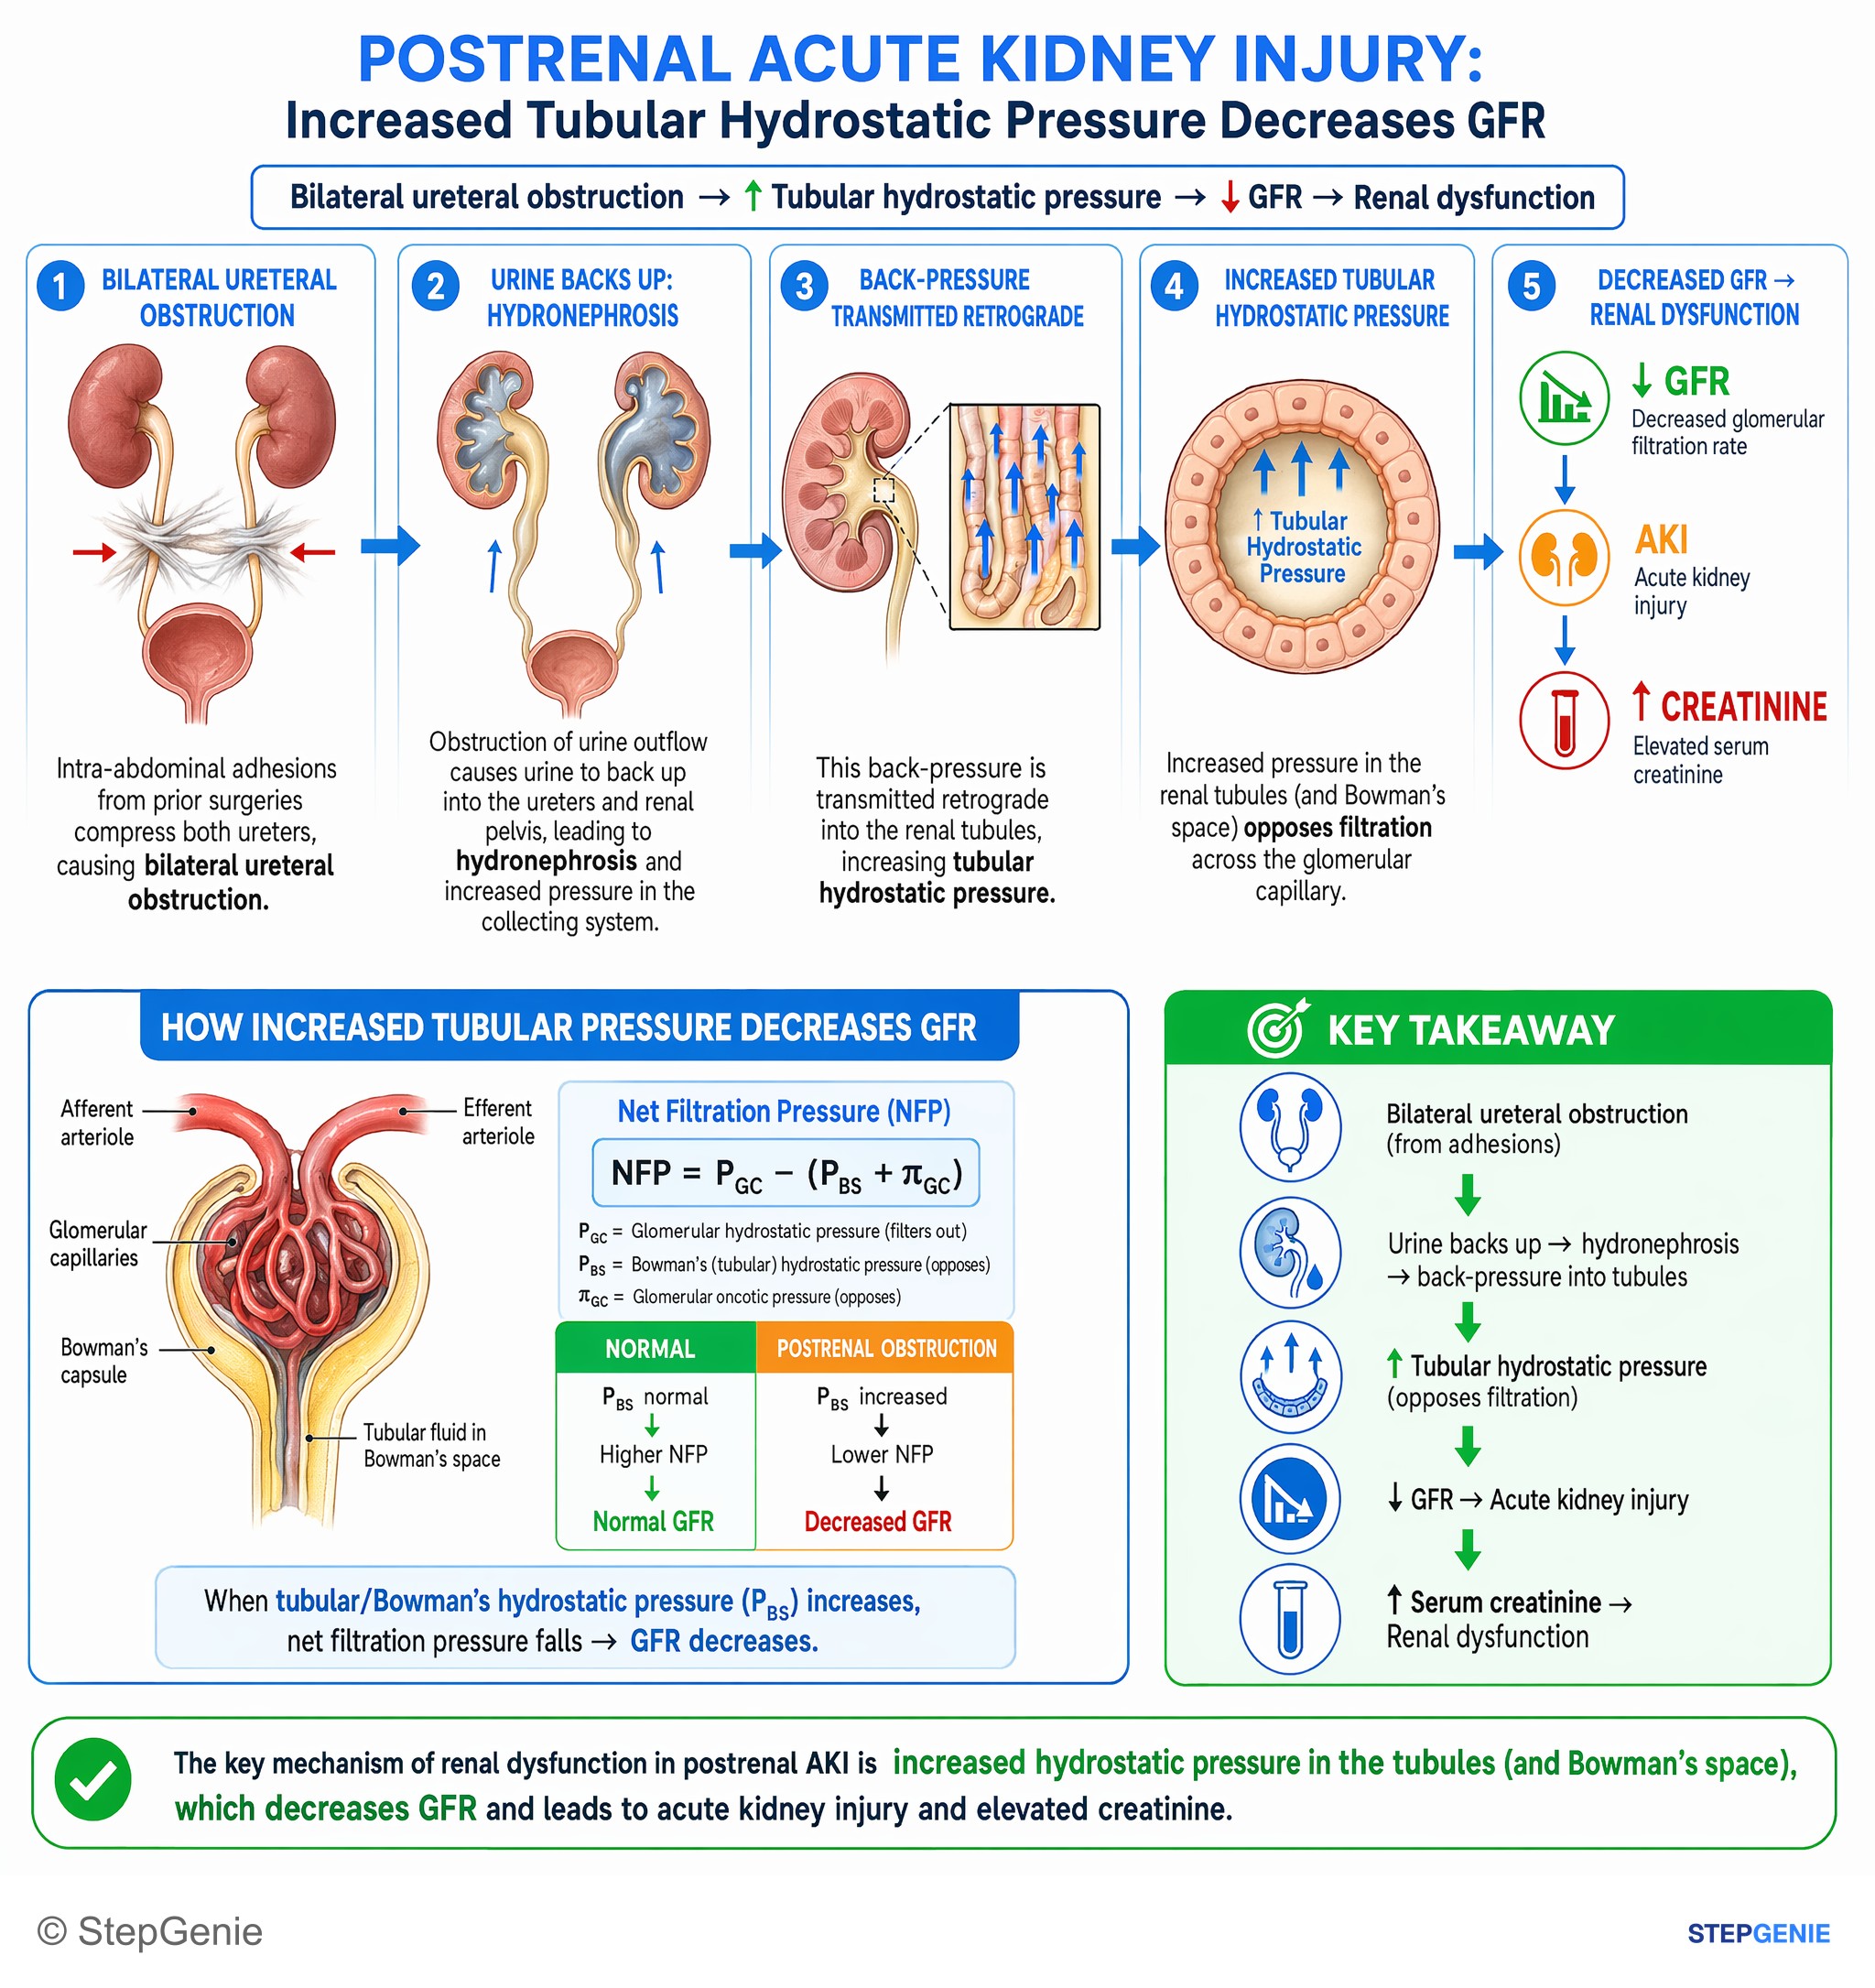
Postrenal acute kidney injury from bilateral ureteral obstruction causes increased tubular hydrostatic pressure, decreasing GFR and…
USMLE Step 1Frequently Asked Questions
What is the renal clearance formula (C = UV/P)?
Renal clearance is C = UV/P: the urine concentration of a substance times the urine flow rate, divided by its plasma concentration. U and P must be in the same units and V in mL per minute, so clearance comes out in mL/min. It is the virtual volume of plasma completely cleared of the substance each minute. A clearance equal to the GFR means the substance is only filtered; lower means net reabsorption, and higher means net secretion.
What is the filtered load formula?
Filtered load equals GFR times the plasma concentration of the freely filtered, unbound substance. With a GFR of 125 mL/min and a plasma glucose of 100 mg/dL (1 mg/mL), the filtered load is 125 mg/min, about 180 g a day. Convert mg/dL to mg/mL before multiplying. Net reabsorption is the filtered load minus urinary excretion (urine concentration times urine flow), and net secretion is excretion minus the filtered load.
What is the PAH clearance formula, and why does it measure effective renal plasma flow?
PAH clearance is urine PAH times urine flow divided by plasma PAH. PAH is filtered and actively secreted by the proximal tubule, so at low plasma levels about 90% is removed in a single pass and its clearance, about 600 mL/min, approximates renal plasma flow. Because extraction is incomplete, it is called effective RPF. True RPF is PAH clearance divided by the extraction ratio, and renal blood flow is RPF divided by one minus the hematocrit.
What is the inulin clearance formula, and why does it equal GFR?
Inulin clearance is urine inulin times urine flow divided by plasma inulin. Inulin is freely filtered and is not reabsorbed, secreted, made or metabolized by the kidney, so all of it in the urine got there by filtration and its clearance equals the GFR, about 120 to 130 mL/min/1.73 m² in young adults. Because it needs a continuous infusion, measured GFR in practice uses markers such as iohexol or iothalamate.
Filtration fraction is the ratio of what?
Filtration fraction is the ratio of GFR to renal plasma flow (FF = GFR/RPF), normally about 0.20, so roughly a fifth of the plasma reaching the glomeruli is filtered. It uses plasma flow, not blood flow. Efferent constriction by angiotensin II and volume depletion raise it; efferent dilation from ACE inhibitors or ARBs, high plasma protein and ureteral obstruction lower it. Afferent constriction from NSAIDs lowers GFR and RPF together, leaving FF unchanged.
Does creatinine clearance overestimate GFR, and which eGFR equation is used now?
Yes. Creatinine is filtered and also secreted by the tubules, so creatinine clearance overestimates GFR by about 10 to 20% with normal kidney function and by up to 50% in advanced kidney failure. KDIGO 2024 advises estimating GFR with a validated equation that does not use race; in the US that is the 2021 CKD-EPI equation. Cystatin C is added, or GFR measured, when creatinine is likely to mislead.