Rhabdomyolysis-induced acute kidney injury (AKI) is one of those “you either recognize it instantly or you miss it” Step scenarios: muscle breakdown + dark urine + rising creatinine after trauma/exertion/statins. The good news is you can draw the whole pathophysiology in 20 seconds—and that sketch basically is the management plan.
The one-liner (what to remember on test day)
Rhabdomyolysis → myoglobin release → pigment nephropathy (tubular obstruction + direct toxicity + renal vasoconstriction) → AKI, often with hyperkalemia and hypocalcemia early.
Draw-it-out method (20-second sketch)
Step-by-step doodle
Grab a scrap paper and draw this left-to-right:
- A “broken” muscle (jagged biceps)
- An arrow to a spilled ink bottle labeled “Mb” (myoglobin)
- An arrow to a kidney tubule shaped like a U
- Inside the tubule, draw dark “plugs” (casts)
- Next to it, write “Fe/ROS” (free iron → reactive oxygen species)
- Over the afferent arteriole, draw a tight clamp (vasoconstriction)
- End with ↑Cr and peaked T waves (hyperK)
The mnemonic picture
“Mb = Mud + Metal + Clamp”
- Mud = pigment casts obstruct tubules (classically worse in acidic urine)
- Metal = heme iron drives oxidative injury to tubular cells
- Clamp = renal vasoconstriction → worsens ischemia
High-yield triggers (the “why is this happening?” list)
Common USMLE-friendly setups:
- Crush injury, prolonged immobilization (found down)
- Seizures, status epilepticus
- Extreme exertion (esp. heat-related)
- Statins (risk increased with interacting drugs)
- Cocaine/amphetamines, alcohol
- Malignant hyperthermia / NMS
- Severe hypokalemia or hypophosphatemia (less common, but testable)
Pathophysiology you actually need (without the fluff)
Rhabdo releases myoglobin, K, phosphate, and CK from damaged skeletal muscle.
How myoglobin causes AKI (3 mechanisms)
| Mechanism | What’s happening | Why Step cares |
|---|---|---|
| Tubular obstruction | Myoglobin + Tamm–Horsfall protein → pigment casts (esp. in acidic urine) | Explains AKI + “muddy” urine; supports fluids ± alkalinization |
| Direct tubular toxicity | Heme iron → oxidative stress → tubular epithelial injury | Ties to ATN physiology |
| Renal vasoconstriction | Volume depletion + vasoactive mediators | Supports aggressive IV fluids |
Classic clinical & lab clues
Presentation
- Muscle pain, weakness, swelling
- Dark “tea-colored” urine (often without many RBCs)
- Signs of volume depletion in exertional/heat cases
Labs (high yield)
- CK massively elevated (often thousands; can be >10,000)
- Hyperkalemia (life-threatening arrhythmia risk)
- Hyperphosphatemia
- Hypocalcemia early (calcium deposits in injured muscle)
- Later during recovery: rebound hypercalcemia can occur
- ↑Creatinine (AKI)
Urinalysis pattern (a favorite trick)
- Dipstick “blood” positive (heme detects myoglobin)
- Microscopy: few/no RBCs
USMLE translation: “heme-positive urine without RBCs” = think myoglobin (or hemoglobin) rather than true hematuria.
AKI type: what is it, mechanistically?
Most consistent with acute tubular necrosis (ATN) from pigment nephropathy.
Supportive Step-style findings:
- Muddy brown granular casts (ATN can show this; pigment casts may also be described)
- FeNa often > 2% once established (contrast with prerenal); early cases can be mixed if volume depleted
Management (what you do first vs what’s controversial)
Immediate priorities (the “don’t miss” actions)
- Aggressive IV isotonic fluids (e.g., normal saline)
- Goal: restore perfusion + flush pigment through tubules
- Treat hyperkalemia immediately if present (ECG changes or high K)
- Calcium gluconate (stabilize), insulin + glucose, albuterol, bicarbonate as indicated
- Stop offending cause (statin, exertion, toxins), evaluate for compartment syndrome
What about bicarbonate and mannitol?
- Urine alkalinization (bicarbonate): sometimes used to reduce myoglobin precipitation in tubules, but evidence is mixed; still appears in board-style questions as a consideration.
- Mannitol: not routine; may be considered in select cases but not standard first-line.
When dialysis enters the chat
Dialysis is for complications, not “myoglobin clearance” per se:
- Refractory hyperkalemia
- Refractory volume overload/pulmonary edema
- Severe acidosis
- Uremic complications
Quick “question stem translator”
If you see…
- Crush injury + tea urine + CK 20,000 → rhabdo
- Urine dip blood+, no RBCs → myoglobin
- Peaked T waves → hyperkalemia from rhabdo
- AKI after prolonged immobilization → rhabdo until proven otherwise
Rapid recap (sticky bullets)
- Rhabdo → myoglobin → ATN/pigment nephropathy → AKI
- UA: heme+ dip with few/no RBCs
- Electrolytes: ↑K, ↑phos, ↓Ca early (± rebound ↑Ca later)
- First step treatment: aggressive IV fluids
- Biggest immediate killer: hyperkalemia
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
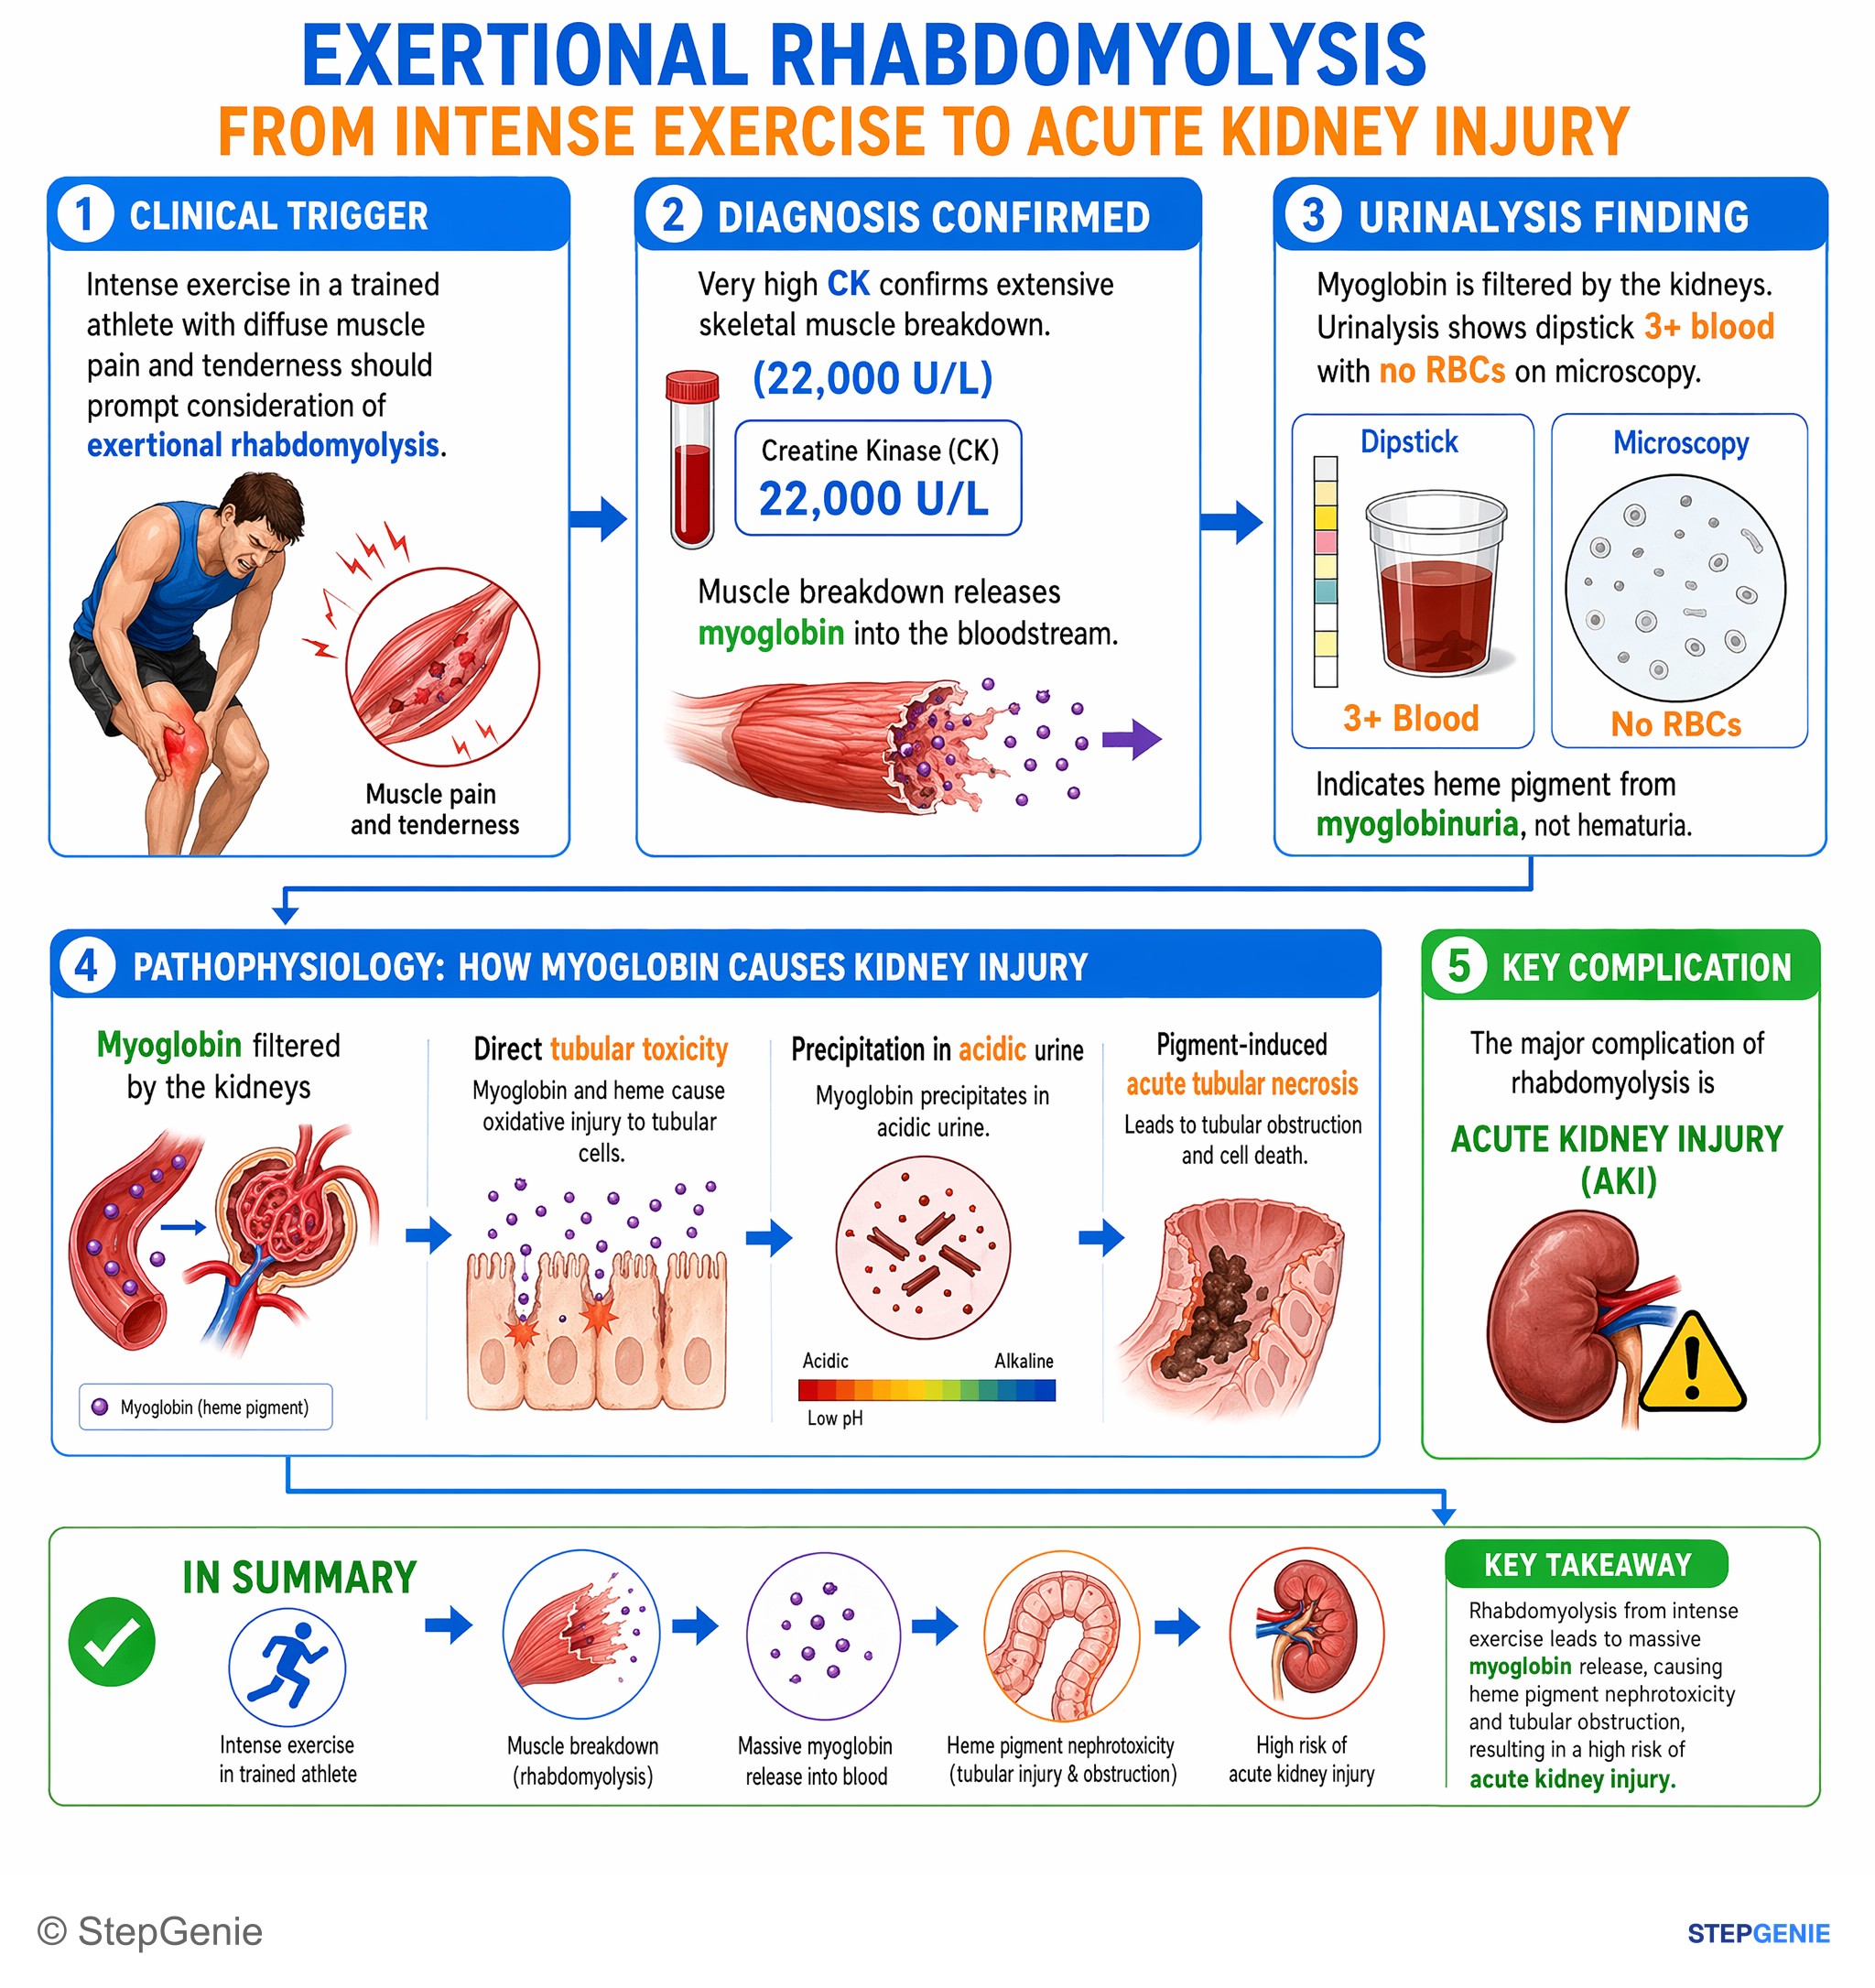
Rhabdomyolysis from intense exercise → massive myoglobin release (heme pigment nephrotoxicity, tubular obstruction) → high risk of acute…
USMLE Step 1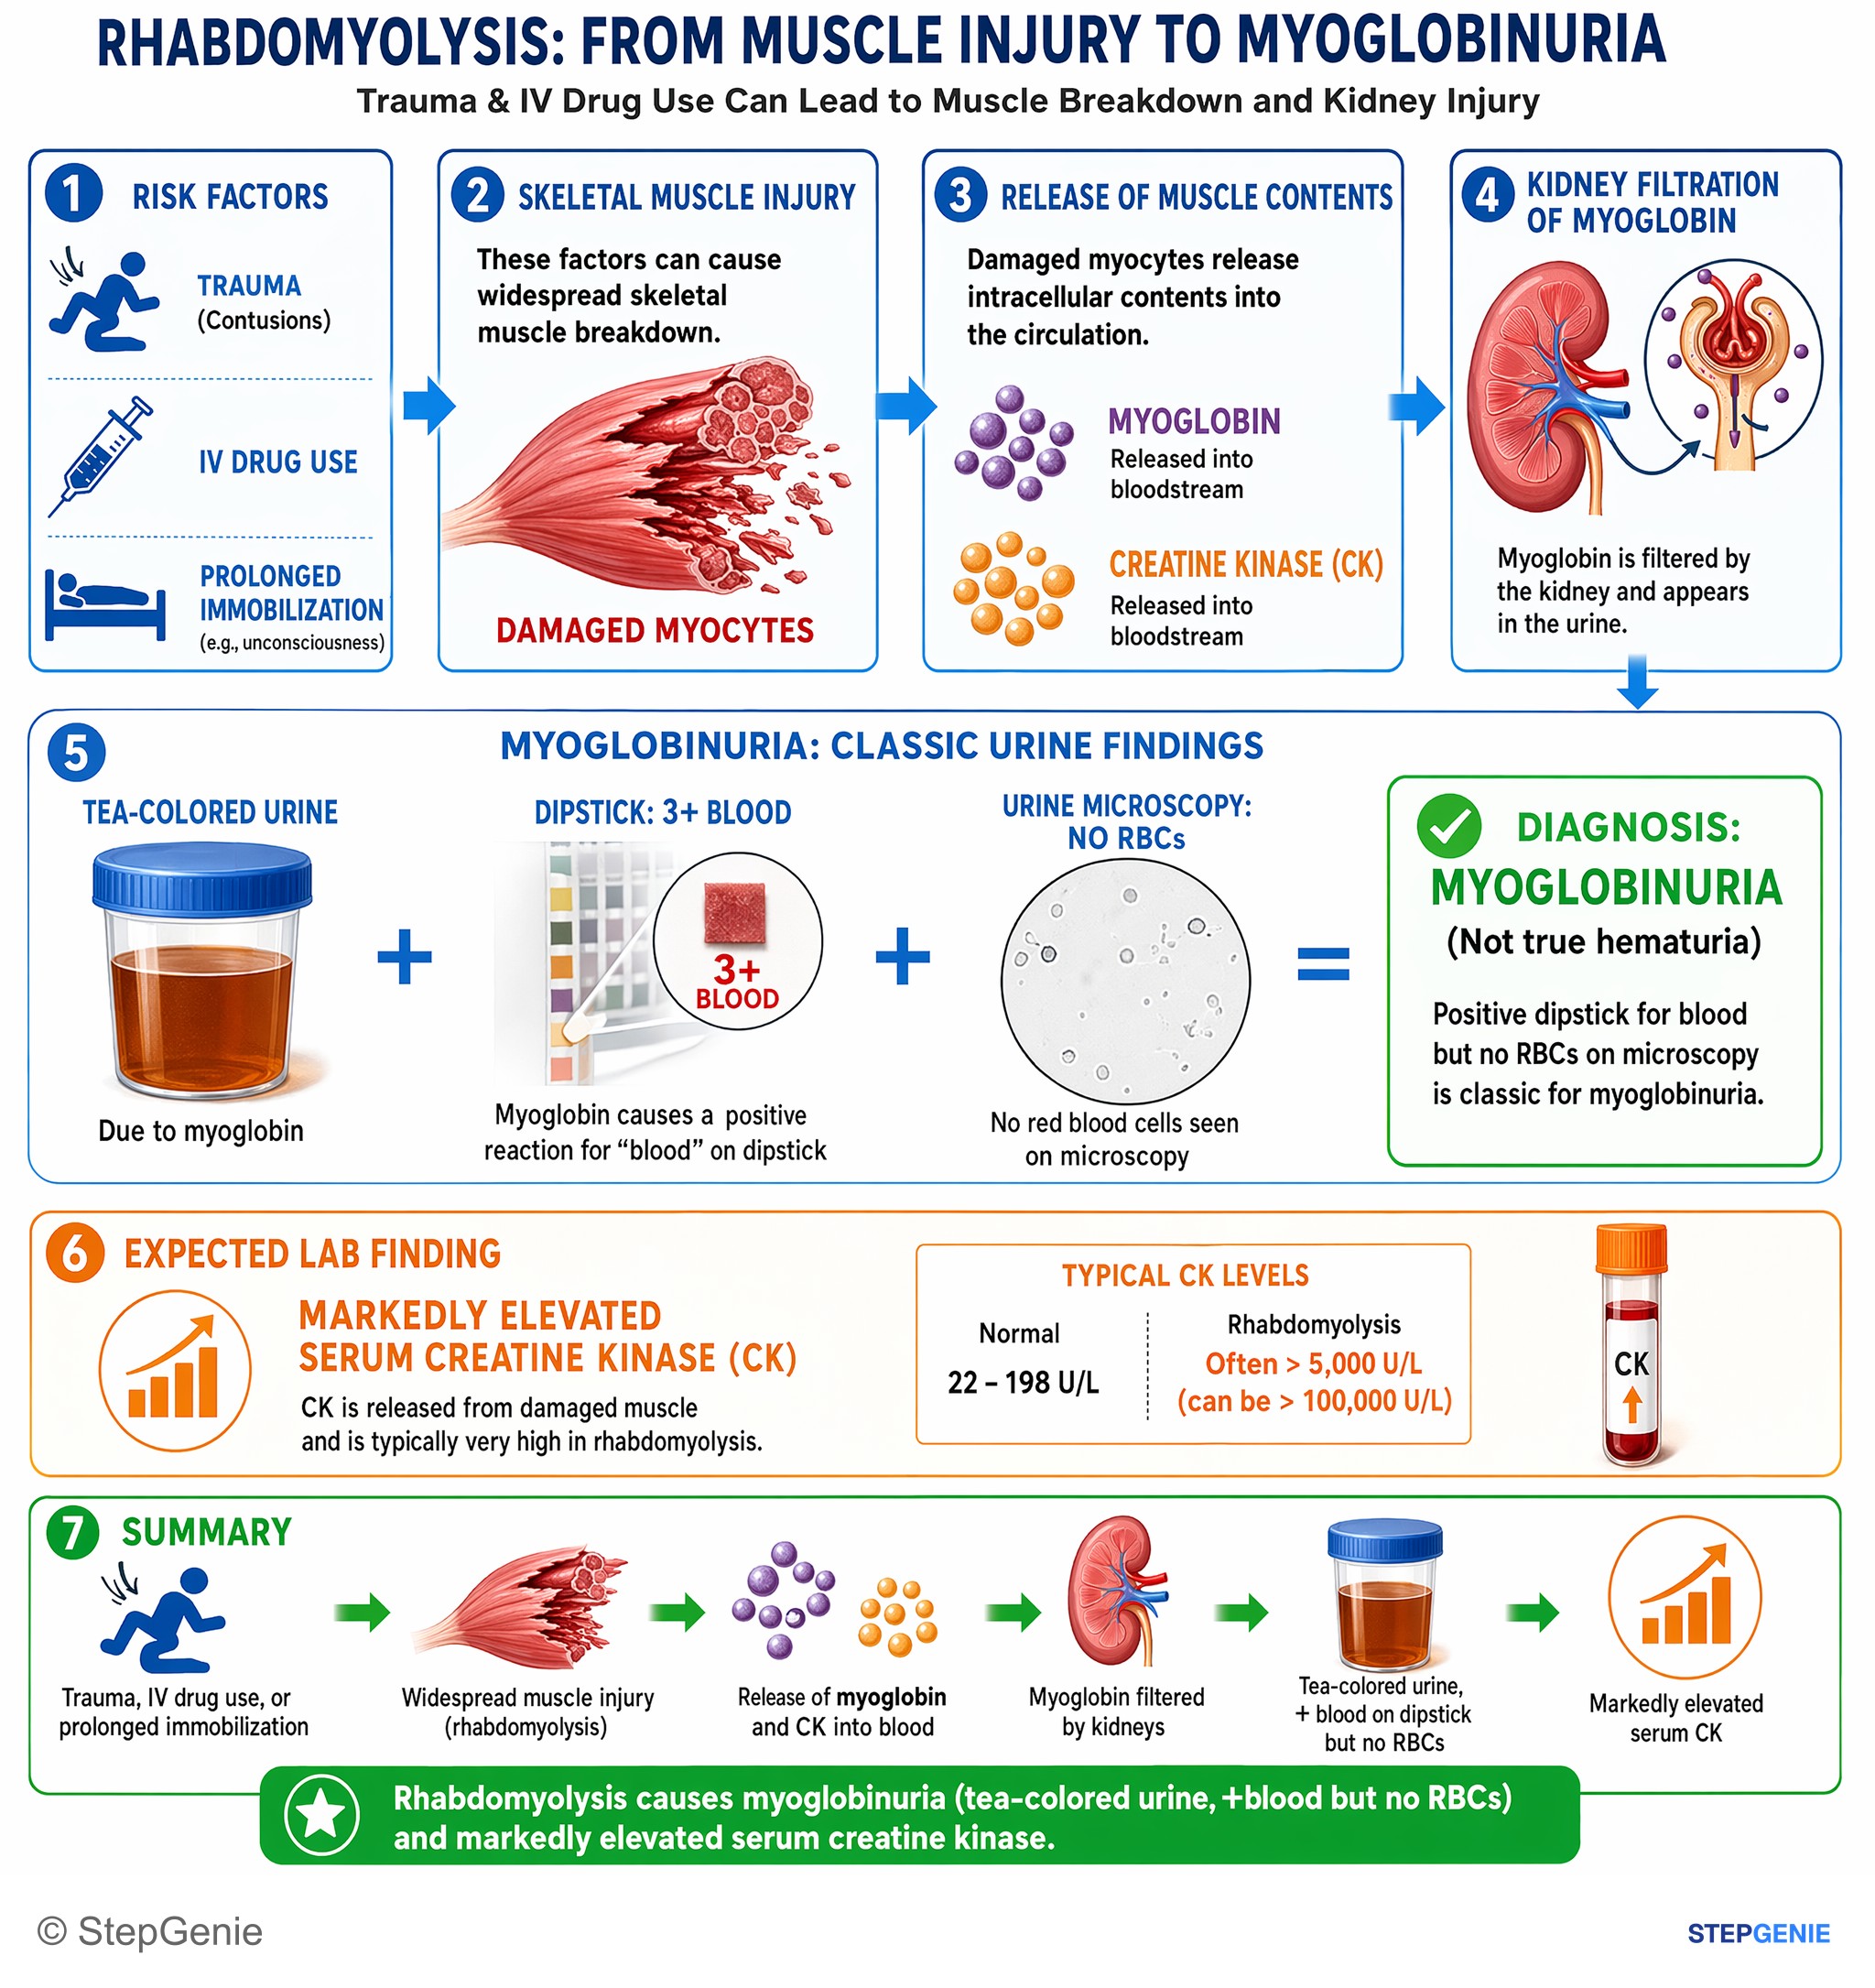
Rhabdomyolysis from trauma/drug use causes myoglobinuria (tea-colored urine, +blood but no RBCs) and markedly elevated serum creatine…
USMLE Step 2Frequently Asked Questions
How does rhabdomyolysis cause acute kidney injury?
Rhabdomyolysis causes AKI through myoglobin-mediated pigment nephropathy. Damaged skeletal muscle releases myoglobin, which contributes to tubular obstruction by forming pigment casts, directly injures tubular cells through heme iron–driven oxidative stress, and worsens ischemia through renal vasoconstriction. This overall picture is most consistent with acute tubular necrosis and commonly presents with rising creatinine after trauma, exertion, immobilization, or statin exposure.
Why is the urine dipstick positive for blood in rhabdomyolysis even when there are few or no red blood cells?
The dipstick is positive because it detects heme, and myoglobin contains heme. In rhabdomyolysis, muscle breakdown releases myoglobin into the urine, producing dark tea-colored urine and a heme-positive dipstick despite microscopy showing few or no RBCs. That pattern points to myoglobinuria rather than true hematuria and is a classic test clue for rhabdomyolysis-induced kidney injury.
What is the first-line treatment for rhabdomyolysis-induced AKI?
The first-line treatment is aggressive IV isotonic fluids, such as normal saline. The goal is to restore renal perfusion and flush myoglobin pigment through the tubules to reduce obstruction and ischemic injury. At the same time, the offending cause should be stopped and the patient assessed for complications like compartment syndrome, but fluids are the key initial management step.
What electrolyte abnormalities are classic in rhabdomyolysis, and which one is the most dangerous right away?
The classic abnormalities are hyperkalemia, hyperphosphatemia, and early hypocalcemia, with possible rebound hypercalcemia during recovery. The most immediately dangerous problem is hyperkalemia because it can cause life-threatening arrhythmias, including peaked T waves on ECG. Rhabdomyolysis releases potassium from damaged muscle, so hyperkalemia must be treated right away if present, especially with ECG changes.
When should dialysis be used in rhabdomyolysis-induced AKI?
Dialysis is used for complications, not simply to clear myoglobin. Indications include refractory hyperkalemia, refractory volume overload or pulmonary edema, severe acidosis, and uremic complications. This is important because board questions may tempt you to think dialysis is for pigment removal, but the key reason to start it is failure of supportive management or development of urgent AKI complications.