Uremia (the uremic syndrome) is the multisystem toxicity that appears when kidney function falls very low, usually a GFR below 15 mL/min/1.73 m² (CKD G5) or severe acute kidney injury; urea and creatinine are only markers for the retained toxins, so no single BUN value defines it. The highest-yield complications are encephalopathy (confusion, asterixis, myoclonus, seizures), fibrinous pericarditis (friction rub, often without the classic diffuse ST elevation) and platelet dysfunction (mucosal bleeding with a normal platelet count, PT and PTT, reversed short term with desmopressin). Each of these is symptomatic uremia, the "U" in AEIOU, and a reason to start dialysis now.
Uremia complications by organ system
More than 100 retained solutes (urea, parathyroid hormone, β2-microglobulin, indoxyl sulfate and others) act together; no single toxin explains the syndrome. Lassitude, fatigue, anorexia and poor concentration usually come first, and neuromuscular signs appear as eGFR falls below about 15 (see the CKD stages by GFR mnemonic).
| System | Complication | What the stem gives you |
|---|---|---|
| Neurologic | Uremic encephalopathy | Fatigue, poor concentration, then confusion, asterixis, myoclonic jerks, seizures, coma |
| Neurologic | Neuropathy and muscle symptoms | Distal sensory and motor neuropathy, restless legs, cramps, twitching, hyperreflexia |
| Cardiac | Fibrinous pericarditis, effusion | Pleuritic chest pain and a friction rub; tamponade if fluid builds up |
| Cardiac | Hypertension, heart failure | Hypertension in more than 80% of advanced CKD, mostly from volume overload |
| Pulmonary | Pulmonary edema, pleuritis | Dyspnea and crackles from fluid overload; pleuritic pain |
| Hematologic | Platelet dysfunction | Mucosal bleeding and oozing with a normal platelet count, PT and PTT |
| Hematologic | Normocytic, normochromic anemia | Low erythropoietin; hematocrit often 20-30% |
| GI | Anorexia, nausea, vomiting, stomatitis, bad taste | Weight loss and tissue wasting; GI ulceration and bleeding late |
| Skin | Pruritus, dry yellow-brown skin, uremic frost | Excoriations; frost is urea from sweat crystallizing on the skin (rare, very advanced) |
| Acid-base, electrolytes | Metabolic acidosis, hyperkalemia | Bicarbonate typically 15-20 mmol/L; potassium climbs once failure is advanced or with K⁺-raising drugs |
| Bone and mineral | CKD-mineral and bone disorder | High phosphate, low calcium (less calcitriol), secondary hyperparathyroidism, renal osteodystrophy |
Tip 1: Pericarditis in kidney failure: uremic or dialysis-associated?
Both inflame the pericardium in kidney failure: uremic pericarditis is classically fibrinous (or serofibrinous), while the effusion of dialysis-associated pericarditis is often serosanguinous. What separates them is timing, and timing tells you what to do with dialysis.
| Uremic pericarditis | Dialysis-associated pericarditis | |
|---|---|---|
| When | Before dialysis or within the first 8 weeks of starting it | After at least 8 weeks on maintenance dialysis |
| What it signals | Untreated uremia | Often underdialysis: missed or inadequate sessions |
| Treatment | Start dialysis, intensively | Intensify dialysis |
| Response to dialysis | About 85% respond to starting dialysis | About 56% improve with intensification |
- Clues: chest pain, a friction rub, fever, dyspnea. Hypotension, JVD, pulsus paradoxus or muffled heart sounds suggest tamponade.
- ECG: the classic diffuse ST elevation with PR depression is uncommon; nonspecific changes from LVH or electrolyte disturbances are more typical. A "normal-looking" ECG does not rule it out.
- Dialysis is the treatment. One published protocol uses 4 hours of dialysis daily (or six sessions a week) for 7-14 days, with an echocardiogram every few days; intensive dialysis succeeds in about 85% of uremic pericarditis.
- Avoid systemic heparin during those sessions (heparin-free or regional anticoagulation): heparin exposure and bleeding into the pericardium have been proposed as contributors, and uremic platelets already bleed easily.
- Drain it for tamponade or a large effusion that does not respond: pericardiocentesis with a drain first, a surgical window for recurrence.
- NSAIDs and colchicine are not the first-line answer here. In kidney failure, NSAIDs improved fever but not chest pain, rub or effusion size, and they can precipitate bleeding into the pericardium; colchicine has scant supporting data and a significant risk of toxicity. Glucocorticoids (systemic or intrapericardial) are reserved for refractory cases; early reports linked systemic steroids to more serious infections.
Tip 2: Bleeding with a normal platelet count means uremic platelet dysfunction
- Mechanism: retained toxins impair platelet adhesion to the vessel wall and aggregation; the exact defect is still not defined. Anemia makes it worse.
- Labs (classic exam framing): normal platelet count, normal PT/INR and PTT, prolonged bleeding time. Mucosal bleeding with a normal count and normal coagulation tests = a platelet function problem.
- Presentation: epistaxis, gum bleeding, easy bruising, oozing from IV, dialysis-access or biopsy sites, GI bleeding.
- Treat only when it matters: active bleeding, or before surgery or a kidney biopsy. Asymptomatic patients need nothing.
| Option | How it helps | Practical point |
|---|---|---|
| Desmopressin (DDAVP), 0.3 mcg/kg IV or SC | V2 agonist that releases von Willebrand factor and factor VIII from endothelial Weibel-Palade bodies | Rapid (IV blood levels peak in 30-60 min); the usual pick for active bleeding or before a procedure; watch for hyponatremia |
| Cryoprecipitate | Supplies von Willebrand factor and fibrinogen | Short-lived effect |
| Conjugated estrogens | Hormonal option (Merck: 2.5-5 mg orally once daily) | Effect may last several days, longer than the other options |
| Dialysis | Clears the toxins | "Vigorous" dialysis reduces bleeding |
| Correct anemia | Transfusion or an erythropoiesis-stimulating agent to Hb above 10 g/dL | Reduces bleeding; see anemia of CKD |
Desmopressin, cryoprecipitate and transfusion are short-term fixes; conjugated estrogens last longest (several days). Desmopressin works the same way it does in von Willebrand disease.
Tip 3: Know when to dialyze (AEIOU), and what KDIGO actually says
| Letter | Indication | Exam detail |
|---|---|---|
| A | Acidosis | Severe metabolic acidosis that does not respond to medical therapy |
| E | Electrolytes | Hyperkalemia that cannot otherwise be controlled (Merck's example: K⁺ above 6 mmol/L) |
| I | Intoxications | Dialyzable toxins: ethylene glycol, methanol, lithium, salicylates, theophylline. Dialysis does little for drugs with a large volume of distribution or heavy tissue binding (digoxin, tricyclics) |
| O | Overload | Pulmonary edema or fluid overload refractory to diuretics |
| U | Uremia | Pericarditis, pleuritis, encephalopathy, neuropathy, uremic bleeding, persistent nausea and vomiting |
- CKD (KDIGO 2024): start dialysis on a composite assessment of symptoms, signs, quality of life, preferences, GFR and labs. Triggers are symptoms or signs attributable to kidney failure (neurologic uremic signs, pericarditis, anorexia, refractory acid-base or electrolyte problems, intractable pruritus, serositis), volume or blood pressure that cannot be controlled, or progressive malnutrition or cognitive impairment. This "often but not invariably" happens at a GFR of 5-10 mL/min/1.73 m²; the IDEAL trial found no survival advantage to starting early.
- AKI (KDIGO 2012, still the current published version): start kidney replacement therapy emergently for life-threatening fluid, electrolyte or acid-base changes; otherwise weigh the whole clinical picture and lab trends, not single BUN or creatinine thresholds. KDIGO adds that it is now rare to wait for uremic complications in AKI. A KDIGO 2026 AKI/AKD update has been through public review but was not yet published as of October 2026.
- Exam rule: no BUN number on its own mandates dialysis; a complication that medicine cannot control does. The full mnemonic is in dialysis indications: AEIOU.
Pruritus and dialysis-related complications
- Uremic (CKD-associated) pruritus: lower phosphate (diet and binders) if it is high; KDIGO 2024 lists gabapentinoids with careful titration, topical agents (capsaicin, emollients for dry skin) and ultraviolet B therapy. Difelikefalin (Korsuva), a kappa-opioid receptor agonist, is FDA-approved for moderate-to-severe CKD-associated pruritus in adults on hemodialysis: 0.5 mcg/kg IV into the venous line at the end of each session (label revised July 2025). It is not recommended for peritoneal dialysis. Main warnings: dizziness, somnolence, mental status changes and gait disturbances, including falls.
- Dialysis disequilibrium syndrome: too-rapid removal of urea and other osmolytes moves water into the brain. Headache, nausea and vomiting can be part of it; severe cases cause disorientation, blurred vision, confusion, seizures and even death.
- Dialysis-related amyloidosis: β2-microglobulin deposits after years of hemodialysis cause carpal tunnel syndrome, bone cysts and arthritis; it is now much less common with high-flux dialyzers.
How USMLE tests it
- Pericarditis plus kidney failure: dialysis (heparin-free), not the NSAID-plus-colchicine regimen used for viral pericarditis. On dialysis for more than 8 weeks? Ask about missed sessions and intensify.
- Bleeding with a normal platelet count, PT and PTT in CKD: uremic platelet dysfunction; desmopressin is the fast fix, dialysis the definitive one.
- Asterixis with confusion in kidney failure: uremic encephalopathy, a "U" indication. Hepatic encephalopathy is the other classic cause, so check the liver.
- New confusion or seizures during or right after a dialysis session: disequilibrium syndrome, not worsening uremia.
- Hyperkalemia: IV calcium gluconate plus insulin with dextrose come first, but they do not lower total-body potassium; binders, diuretics or dialysis must follow (see hyperkalemia).
Practice question
A 61-year-old man with type 2 diabetes and CKD G5 who has not yet started dialysis has 4 days of sharp chest pain that eases when he sits forward, with nausea and itching. Blood pressure is 138/84 mm Hg and pulse 96/min, with no pulsus paradoxus. A three-component friction rub is heard. BUN is 148 mg/dL, creatinine 9.1 mg/dL, potassium 5.3 mEq/L and bicarbonate 17 mEq/L. ECG shows left ventricular hypertrophy with nonspecific ST-T changes and no diffuse ST elevation. Echocardiography shows a small circumferential effusion without chamber collapse. Which is the most appropriate next step?
A. Start hemodialysis without systemic heparin B. Ibuprofen plus colchicine C. Urgent pericardiocentesis D. High-dose oral prednisone E. Coronary angiography
Answer: A. Pericarditis before dialysis has started is uremic pericarditis, a symptomatic-uremia ("U") indication. Intensive dialysis resolves most cases, and avoiding systemic heparin lowers the risk of bleeding into the pericardium.
- B: standard for viral or idiopathic pericarditis, but in kidney failure NSAIDs do not shrink the effusion or settle the rub and add bleeding risk, and colchicine carries a high toxicity risk. Neither treats the cause.
- C: drainage is for tamponade or a large effusion that fails dialysis. This effusion is small and he is hemodynamically stable.
- D: glucocorticoids are kept for refractory cases and raise infection risk; they do not treat uremia.
- E: positional pleuritic pain, a rub and no ischemic ECG pattern point to pericarditis, not acute coronary syndrome.
Key takeaways
- Uremia appears with a very low GFR (usually below 15) or severe AKI; BUN and creatinine are markers, not the toxins.
- The classic triad of urgent "U" complications: encephalopathy with asterixis, fibrinous pericarditis and platelet-dysfunction bleeding.
- Uremic pericarditis comes before dialysis or within its first 8 weeks: start dialysis. Dialysis-associated comes later: intensify dialysis. Go heparin-free and drain only for tamponade or a refractory large effusion.
- Uremic bleeding: normal platelet count, PT and PTT; desmopressin first, plus dialysis, correction of anemia, cryoprecipitate or conjugated estrogens.
- AEIOU = refractory Acidosis, Electrolytes (K⁺), Intoxications, Overload, Uremia; KDIGO bases timing on symptoms and signs, not a lab number.
- Difelikefalin treats moderate-to-severe CKD-associated pruritus in adults on hemodialysis only.
Sources
- Chronic Kidney Disease — Merck Manual Professional Edition (2026)
- Acute Kidney Injury (AKI) — Merck Manual Professional Edition (2026)
- Hemodialysis — Merck Manual Professional Edition (2026)
- Acquired Platelet Dysfunction — Merck Manual Professional Edition (2026)
- General Principles of Poisoning — Merck Manual Professional Edition (2026)
- Uremia — StatPearls, NCBI Bookshelf (2024)
- Desmopressin — StatPearls, NCBI Bookshelf (2023)
- Management of Patients with Kidney Failure and Pericarditis — Clinical Journal of the American Society of Nephrology (2023)
- Understanding Hemodialysis-Associated Pericarditis: Causes, Symptoms, and Management Strategies — Journal of Clinical Medicine (2025)
- KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease — KDIGO (2024)
- KDIGO Clinical Practice Guideline for Acute Kidney Injury — KDIGO (2012)
- KORSUVA (difelikefalin) injection label — DailyMed, National Library of Medicine (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
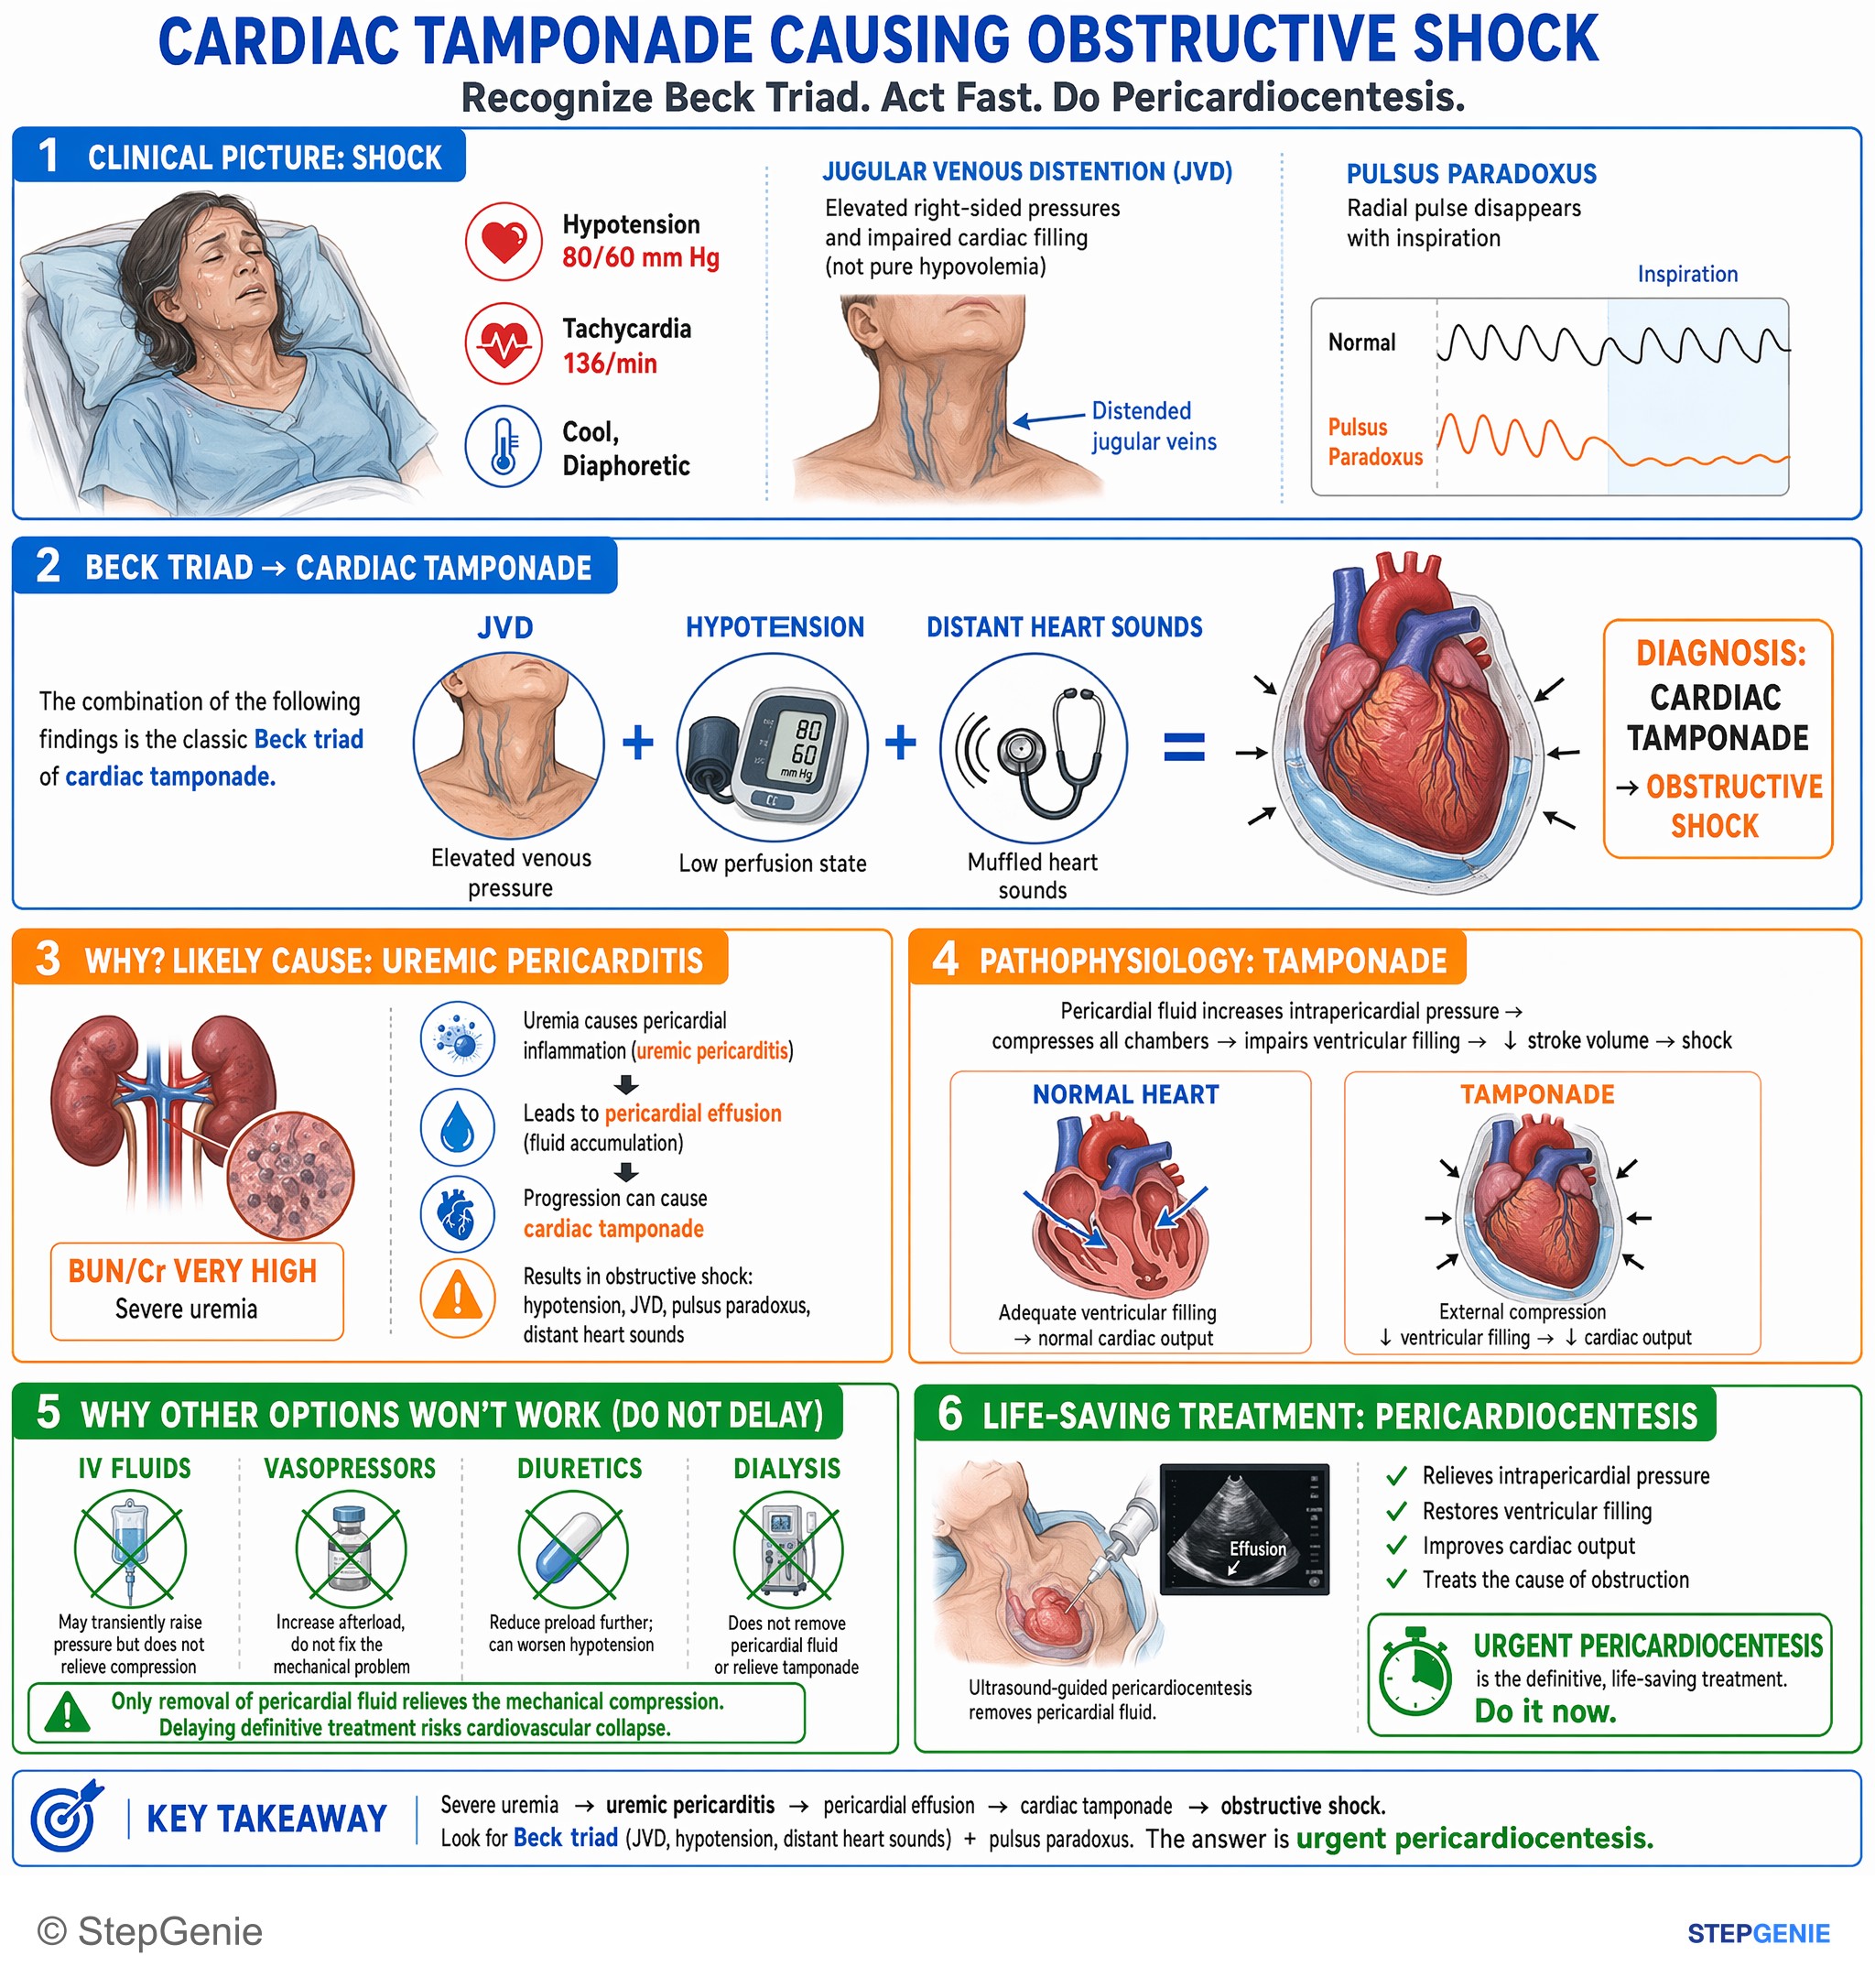
Cardiac tamponade from likely uremic pericarditis causing obstructive shock → hypotension, JVD, pulsus paradoxus, distant heart sounds →…
USMLE Step 2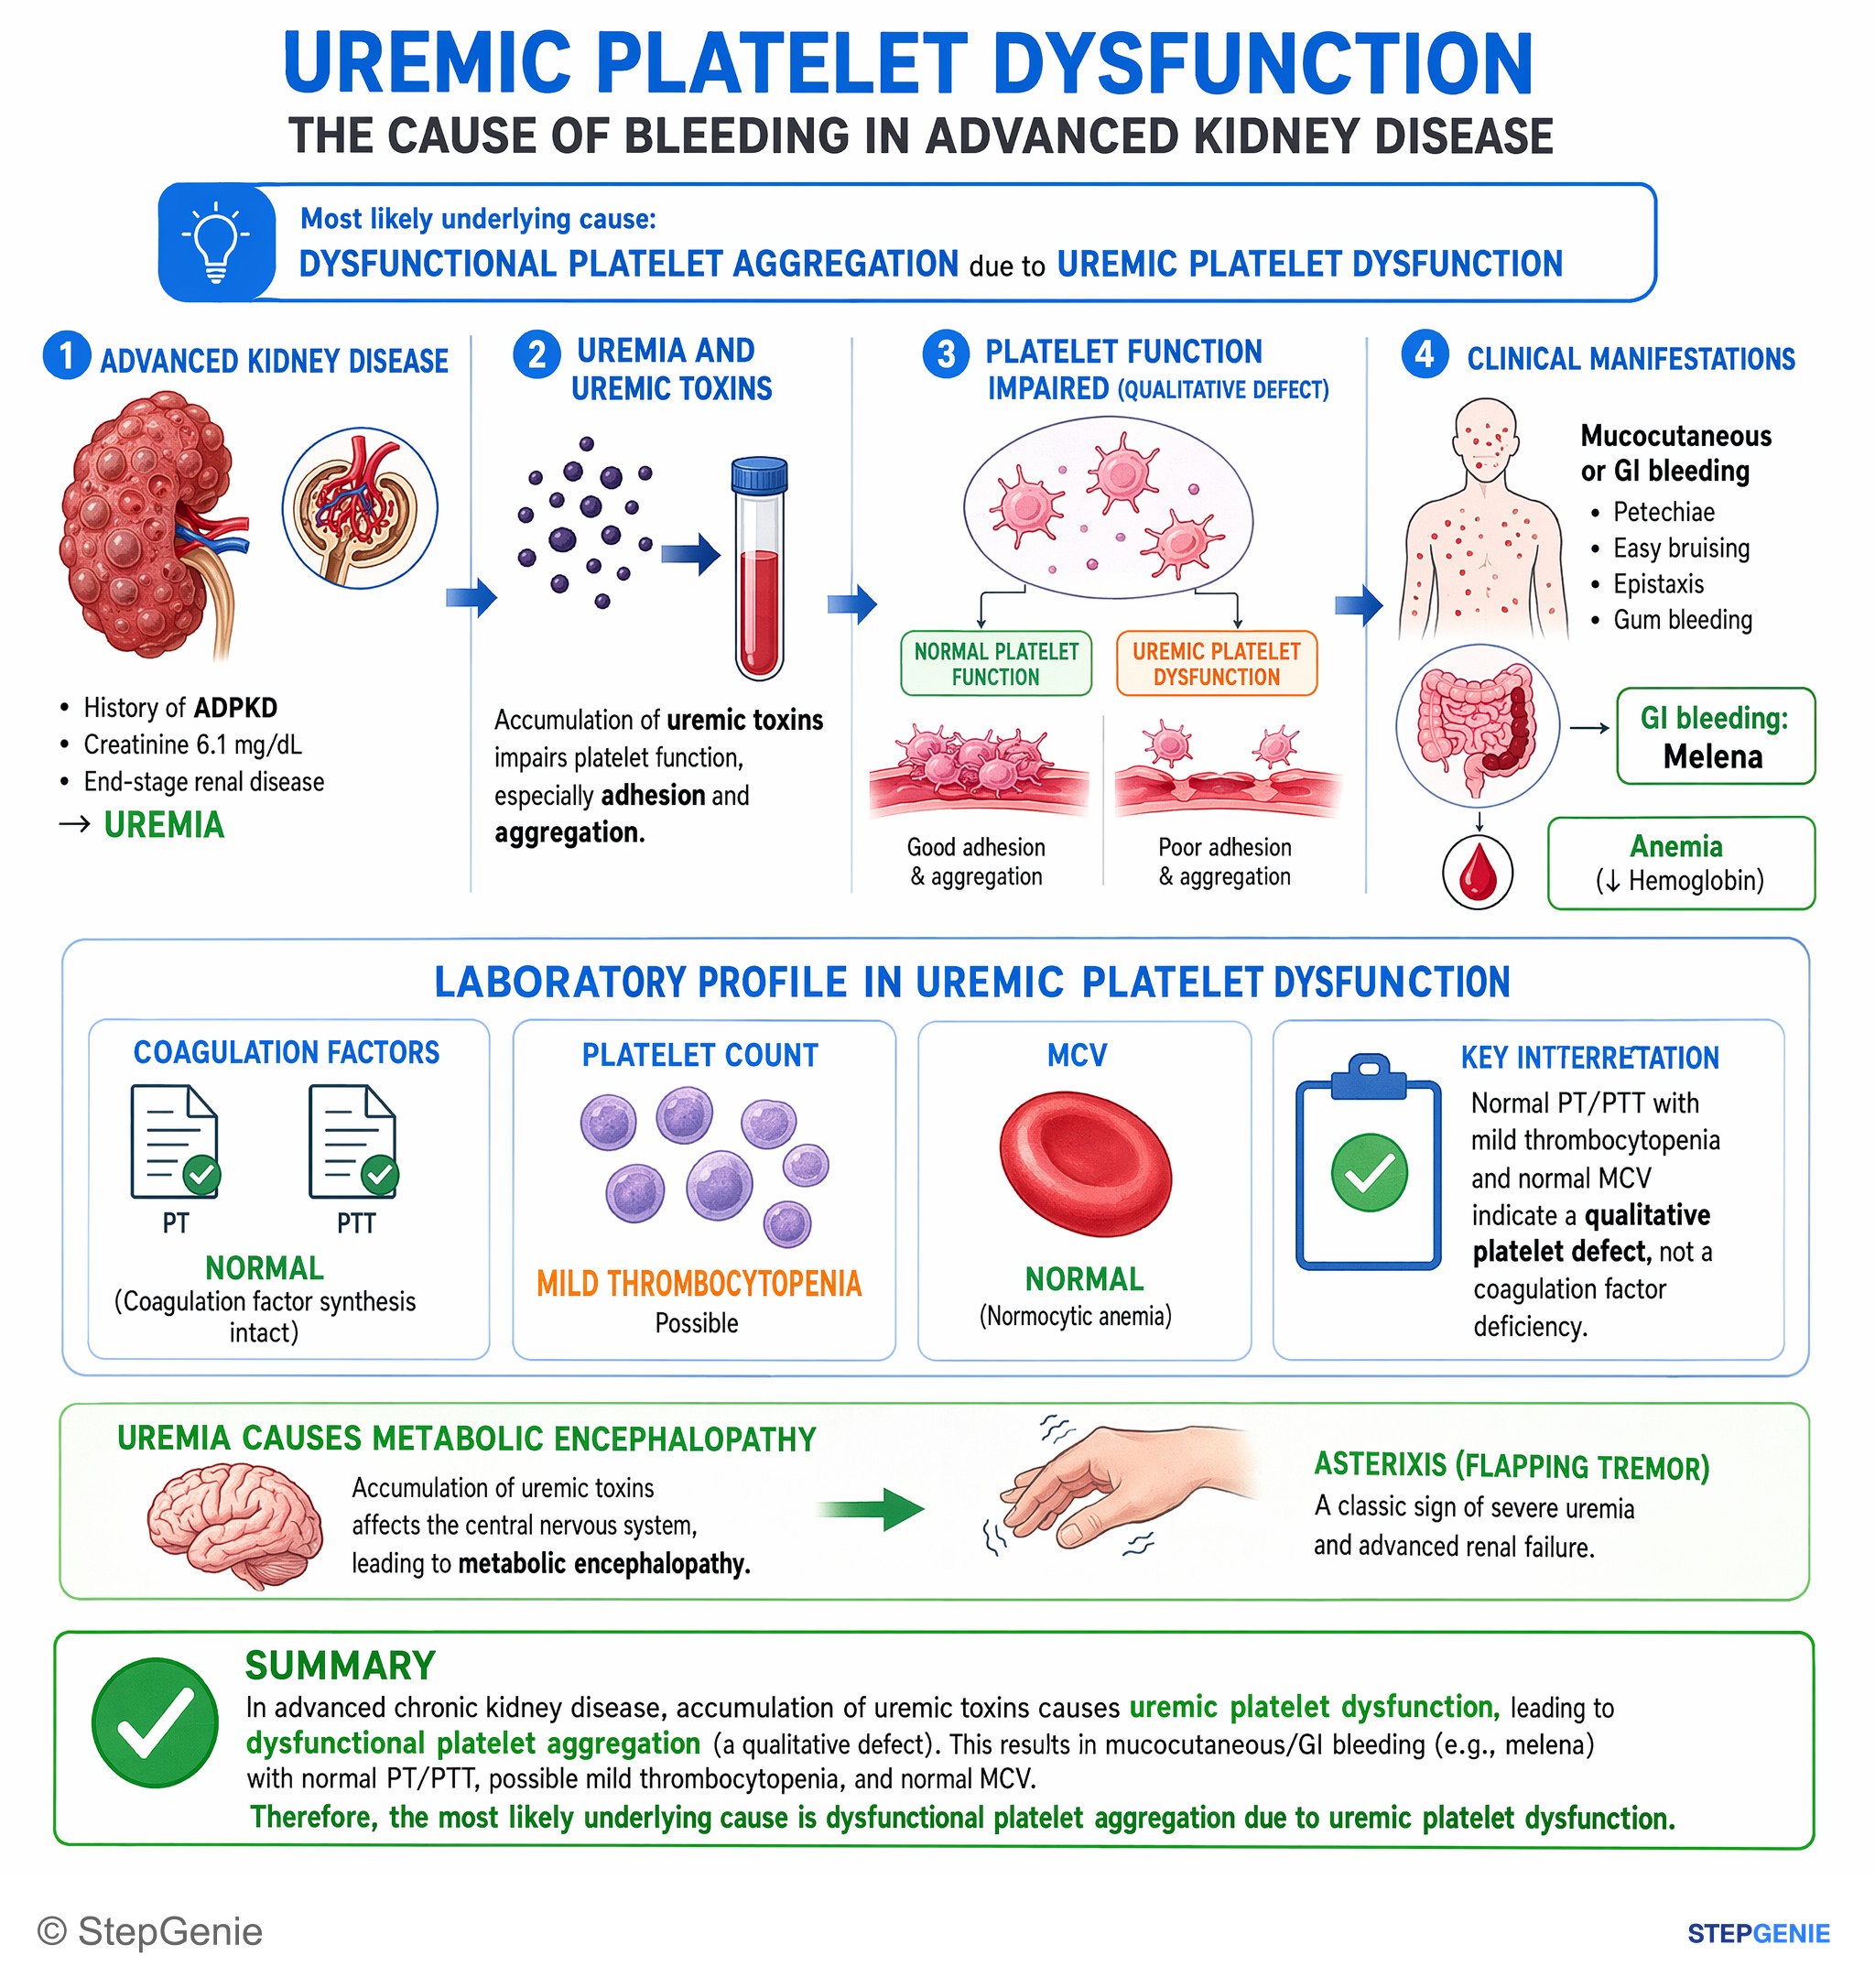
Uremic platelet dysfunction from advanced chronic kidney disease causes qualitative platelet defects → mucocutaneous/GI bleeding with…
USMLE Step 1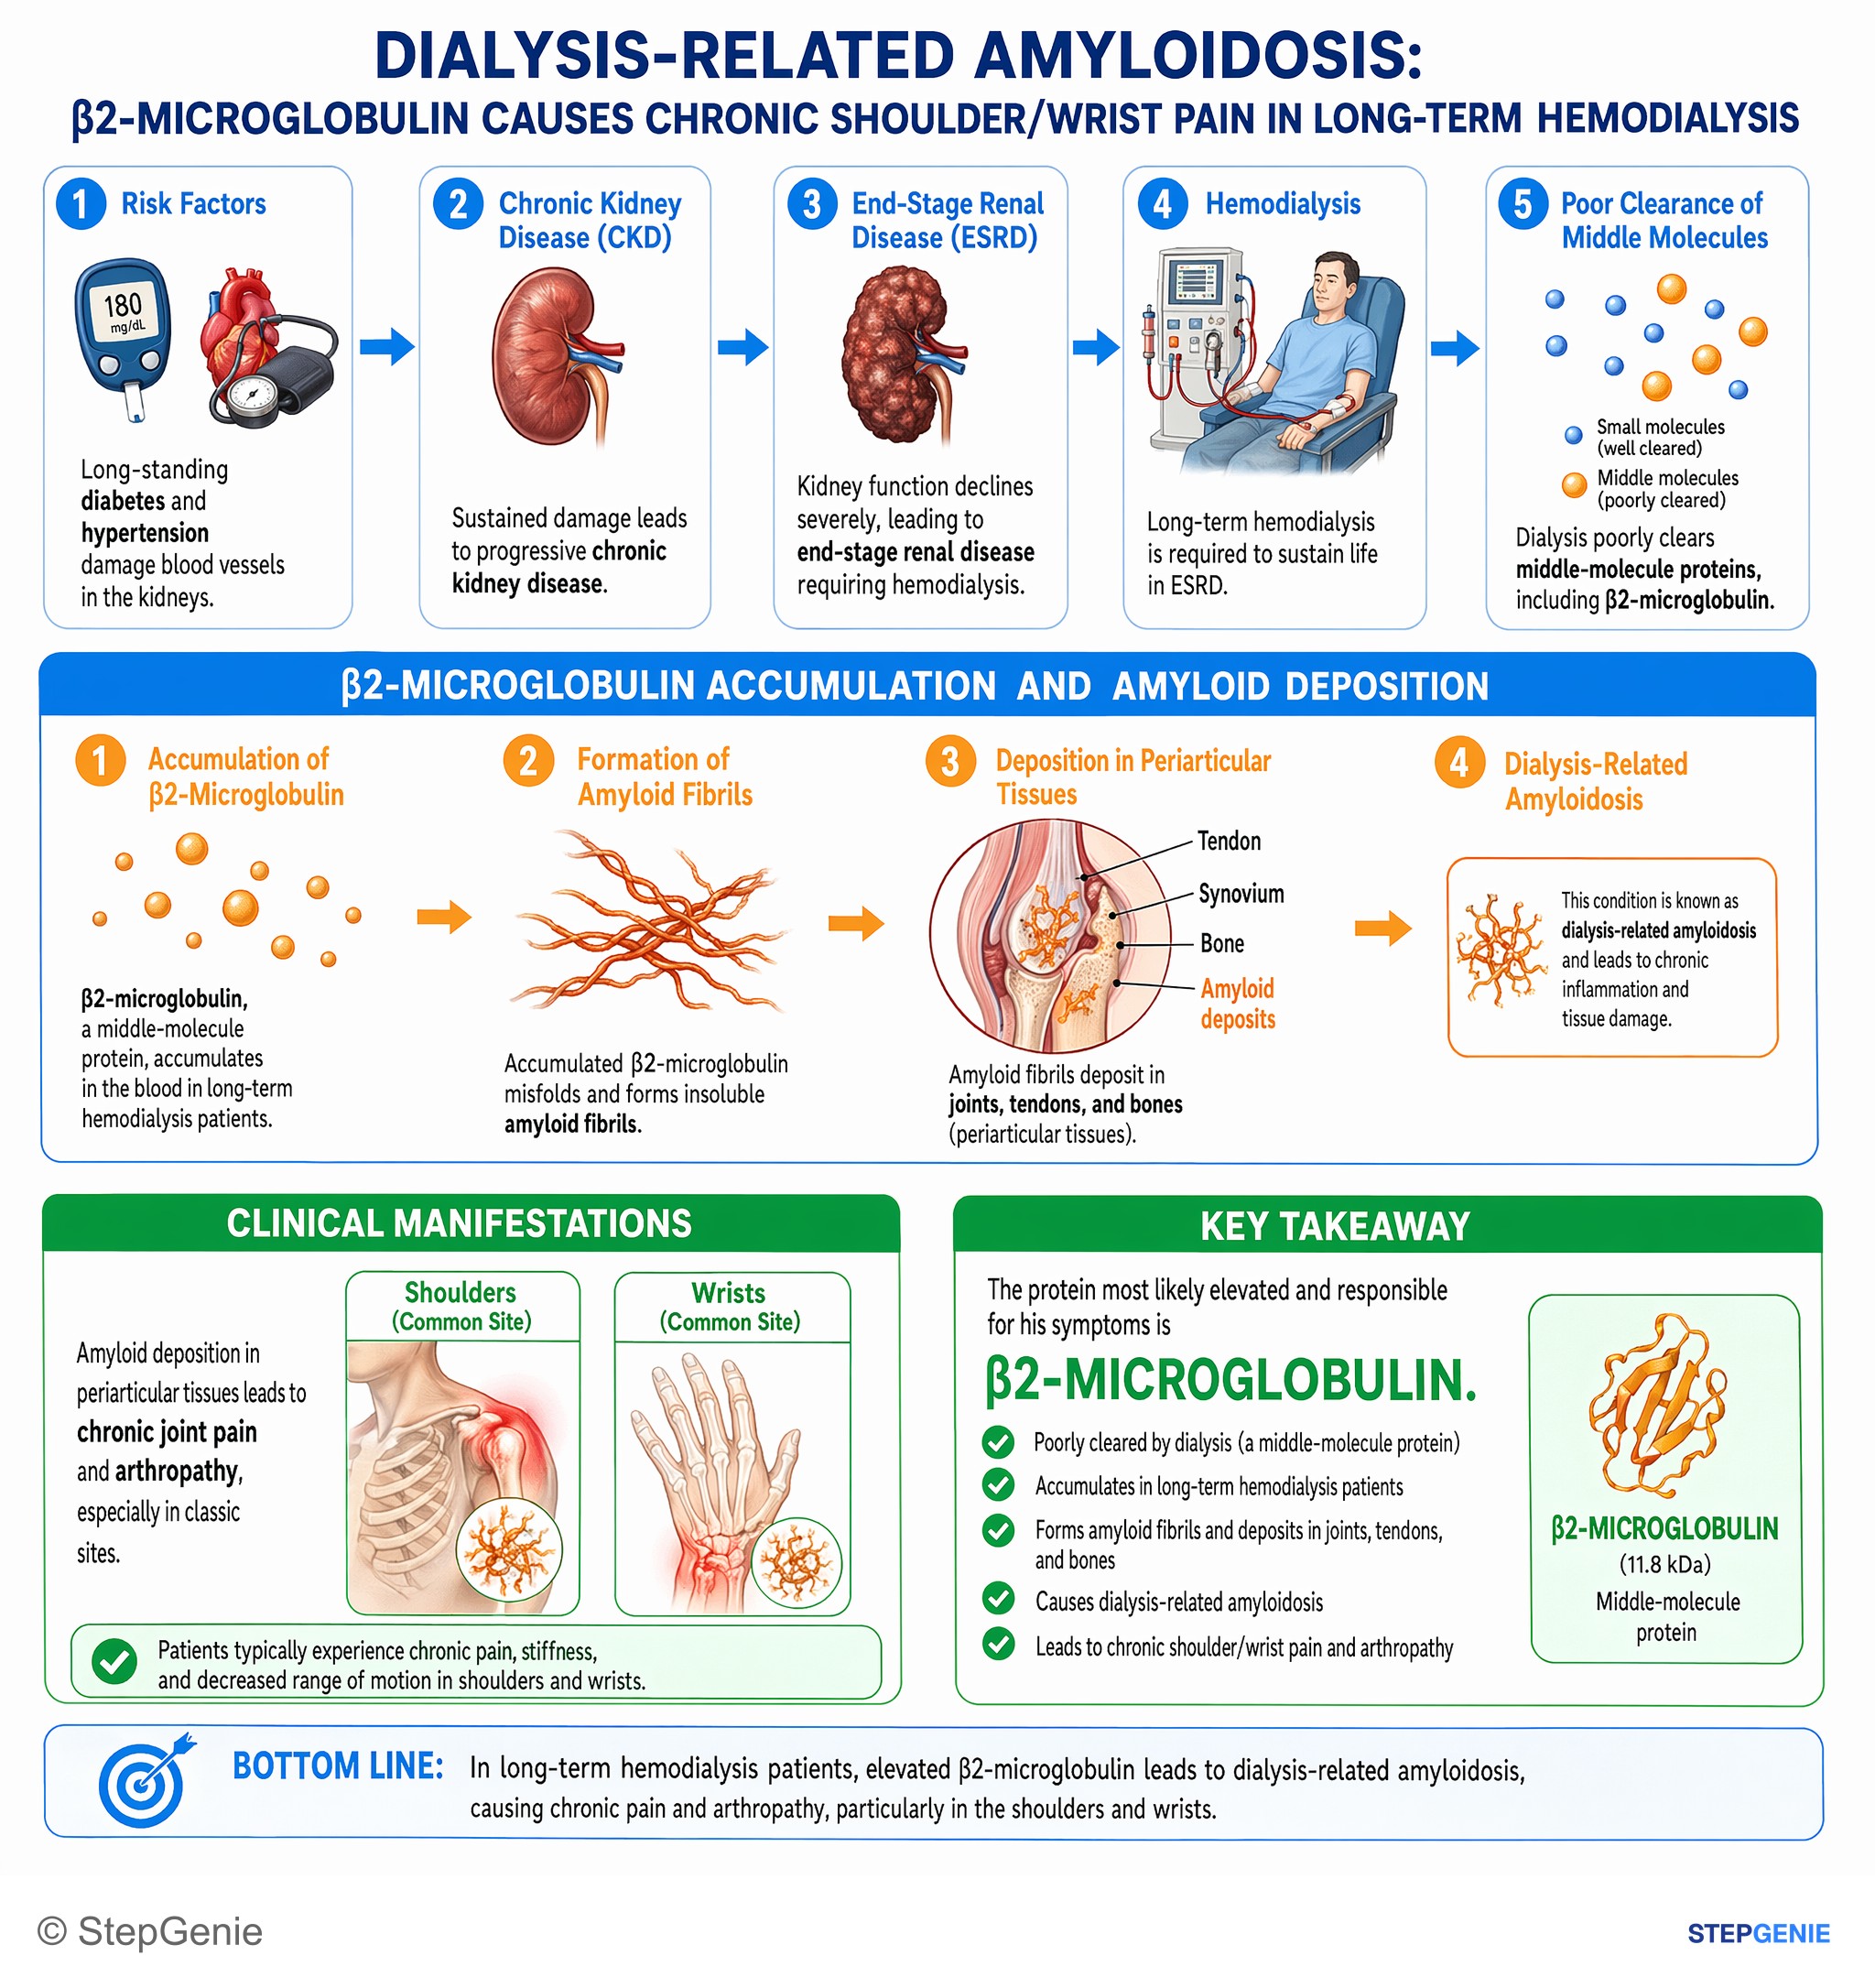
Dialysis-related amyloidosis from elevated β2-microglobulin causes chronic shoulder/wrist pain and arthropathy in long-term hemodialysis…
USMLE Step 1Frequently Asked Questions
What are the main complications of uremia?
Uremia affects nearly every organ. The classic urgent complications are uremic encephalopathy (confusion, asterixis, myoclonus, seizures), fibrinous pericarditis and bleeding from platelet dysfunction. Others include peripheral neuropathy and restless legs, anorexia, nausea and vomiting, pruritus and, rarely, uremic frost, normocytic anemia, metabolic acidosis, hyperkalemia, volume overload with hypertension and pulmonary edema, and mineral and bone disease from high phosphate, low calcitriol and secondary hyperparathyroidism. Symptoms usually appear when GFR falls below about 15 mL/min/1.73 m² or in severe AKI.
What is the difference between uremic pericarditis and dialysis-associated pericarditis?
The difference is timing. Uremic pericarditis develops before dialysis or within the first 8 weeks of starting it and reflects untreated uremia; about 85% of patients respond to starting dialysis. Dialysis-associated pericarditis appears after at least 8 weeks on maintenance dialysis, often after missed or inadequate sessions, and is treated by intensifying dialysis, with a lower response rate of around 56%. In both, sessions are run without systemic heparin, and drainage is reserved for tamponade or a large effusion that does not respond.
Why does uremia cause bleeding when the platelet count is normal?
Retained uremic toxins impair platelet adhesion to the vessel wall and platelet aggregation, so platelets are present but work poorly, and anemia makes it worse. The classic lab pattern is a normal platelet count, normal PT and PTT, and a prolonged bleeding time. Patients have mucosal bleeding, easy bruising, oozing from puncture sites or GI bleeding. Treatment is needed only for active bleeding or before a procedure: desmopressin acts quickly, and dialysis, raising hemoglobin above 10 g/dL, cryoprecipitate or conjugated estrogens also help.
How does desmopressin treat uremic bleeding?
Desmopressin (DDAVP) is a vasopressin V2 receptor agonist that releases von Willebrand factor and factor VIII from endothelial Weibel-Palade bodies, improving platelet adhesion. The usual dose is 0.3 micrograms per kilogram IV or subcutaneously, and blood levels peak within 30 to 60 minutes of an IV dose, which makes it a fast option before a kidney biopsy or surgery or during active bleeding. The effect is temporary, so dialysis and anemia correction are used for longer control. Sodium should be monitored because desmopressin can cause hyponatremia.
When does uremia require dialysis?
Symptomatic uremia, such as pericarditis, encephalopathy or neuropathy, or bleeding from uremic platelet dysfunction, is an indication for dialysis. It is the U in AEIOU, alongside refractory acidosis, refractory hyperkalemia, dialyzable intoxications and diuretic-resistant fluid overload. KDIGO 2024 advises starting dialysis in CKD based on symptoms, signs, quality of life, preferences and laboratory findings rather than a single number; this often happens at a GFR of 5 to 10. No BUN level on its own mandates dialysis.
What is the treatment for uremic pruritus?
First address contributors such as a high phosphate level with diet and binders, and treat dry skin with emollients. KDIGO 2024 lists gabapentinoids with careful dose titration, topical agents such as capsaicin, and ultraviolet B phototherapy. Difelikefalin (Korsuva), a kappa-opioid receptor agonist, is FDA-approved for moderate-to-severe CKD-associated pruritus in adults on hemodialysis, given as 0.5 micrograms per kilogram IV at the end of each session. It is not recommended in peritoneal dialysis and can cause dizziness, somnolence and falls.