You’re doing a renal question, you pick the “right” answer, and then… you move on. That’s how you miss half the learning. In renal physiology, every distractor is basically a mini-lecture on where solutes go, how they get there, and what drugs/diseases mess with the process. Let’s walk through a classic tubular transport vignette and then dismantle every answer choice like you’re reviewing with a strong M3 who actually remembers physiology.
Clinical Vignette (Q-bank style)
A 23-year-old woman is brought to the ED after ingesting an unknown substance at a party. She is somnolent and tachypneic. Labs show:
- pH: 7.25
- : 14 mEq/L
- : 30 mm Hg
- Anion gap: elevated
- Urinalysis: no glucose, no ketones
- Serum creatinine: normal
The team suspects ingestion of an organic acid. A nephrology fellow explains that renal elimination of many organic acids depends on a transporter in the proximal tubule that can become saturated and is competitively inhibited by certain drugs.
Which of the following substances is most directly secreted by the same proximal tubule transporter system used for many organic acids?
A. Glucose
B. Para-aminohippurate (PAH)
C. Sodium
D. Urea
E. Bicarbonate
Correct Answer: B. Para-aminohippurate (PAH)
Why PAH is the classic “organic anion secretion” molecule
PAH is:
- Freely filtered at the glomerulus
- Actively secreted in the proximal tubule by organic anion transporters (OATs)
- So efficiently removed that at low plasma concentrations, its renal clearance approximates renal plasma flow (RPF)
The transporter concept that Step loves
In the proximal tubule, secretion happens through basolateral uptake and apical efflux:
- Organic anions (OAT system): PAH, penicillins, NSAIDs, urate, many toxins/acidic drugs
- Organic cations (OCT system): creatinine, cimetidine, metformin, etc.
These systems are:
- Saturable (limited transport maximum, )
- Competitively inhibited (one substrate can block secretion of another)
Clinical hook: You can intentionally inhibit OAT with probenecid to decrease renal secretion of certain drugs (historically penicillin) and prolong their half-life.
High-Yield Physiology: Reabsorption vs Secretion (quick map)
| Segment | Big job | Reabsorbs | Secretes |
|---|---|---|---|
| Proximal tubule | Bulk handling, reclaim “good stuff,” secrete “toxins” | Na⁺, water, glucose, amino acids, HCO₃⁻, phosphate | PAH, many drugs/toxins, H⁺, NH₄⁺ |
| Thick ascending limb | “Diluting segment” | Na⁺-K⁺-2Cl⁻ | — |
| DCT | Fine-tunes electrolytes | NaCl (NCC), Ca²⁺ (PTH) | — |
| Collecting duct | Final adjustments | Na⁺ (ENaC), water (ADH), urea (inner medullary) | K⁺ (principal), H⁺ (α-intercalated), HCO₃⁻ (β-intercalated) |
Now the real learning: Why each distractor is wrong (and what it’s testing)
A. Glucose — Reabsorbed, not secreted
Glucose is the poster child for proximal tubular reabsorption via:
- SGLT2 (early proximal tubule; high capacity)
- SGLT1 (late proximal tubule; high affinity)
Key Step facts
- Glucose reabsorption has a transport maximum ()
- When filtered load exceeds , glucose appears in urine (glucosuria)
- SGLT2 inhibitors (e.g., empagliflozin) → glucosuria, mild osmotic diuresis, can cause euglycemic DKA
Why it’s not the same system: Glucose uses Na⁺-coupled cotransport on the apical side, not OAT secretion.
C. Sodium — filtered + heavily reabsorbed; secretion is not the concept here
Sodium handling is mostly about reabsorption, not secretion.
High-yield distribution of Na⁺ reabsorption
- Proximal tubule: ~65%
- Thick ascending limb (NKCC2): ~25%
- DCT (NCC): ~5%
- Collecting duct (ENaC): ~2–5% (aldosterone-sensitive)
Testable pearl: “Secretion” is usually reserved for solutes like H⁺, K⁺, NH₄⁺, PAH/drugs—not Na⁺ (even though Na⁺ can move in either direction depending on conditions).
D. Urea — reabsorbed and recycled; not OAT-mediated secretion
Urea is a favorite because it’s confusing: it’s filtered, sometimes reabsorbed, sometimes secreted—but not via OAT, and not primarily for toxin elimination.
What Step wants you to know
- Proximal tubule: urea is passively reabsorbed (follows water)
- Thin descending limb: urea can enter the tubule from the medulla (part of recycling)
- Inner medullary collecting duct: ADH increases urea permeability (UT-A1/UT-A3) → urea reabsorption → helps maintain the medullary osmotic gradient
Bottom line: Urea handling supports urine concentration; it’s not the classic “active secretion of organic acids.”
E. Bicarbonate — reclaimed in proximal tubule via carbonic anhydrase (not secreted)
Bicarbonate is mainly reabsorbed, especially in the proximal tubule.
Mechanism (super high-yield)
- Tubular cells secrete H⁺ (via Na⁺/H⁺ exchanger)
- Luminal combines with filtered →
- Carbonic anhydrase converts
- diffuses into cell → reconverted → transported to blood
Drug tie-in: Acetazolamide inhibits carbonic anhydrase → bicarbonaturia → metabolic acidosis, alkaline urine.
Where secretion does happen: β-intercalated cells can secrete in alkalosis—but that’s collecting duct physiology, not proximal tubule OAT-mediated secretion.
The takeaway algorithm: How to spot “OAT/PAH-type secretion” questions fast
Clues in the stem:
- “Organic acid,” “drug/toxin elimination”
- “Competitive inhibition” or “saturation”
- “Proximal tubule secretion”
- Mentions of probenecid, penicillin, urate, NSAIDs, diuretics, toxins
What they’re aiming at:
- OAT: PAH, many acidic drugs, urate
- OCT: cimetidine, creatinine, metformin (and interactions that raise serum creatinine without true GFR drop)
Exam Pitfalls (things they love to trick you with)
1) “Clearance greater than GFR” = secretion
If a substance has clearance > GFR, it’s being secreted (net).
- Inulin: clearance = GFR (filtered only)
- PAH: clearance ≈ RPF (filtered + secreted; at low concentrations)
2) Saturable transport = concept
Classic -limited processes:
- Glucose reabsorption (SGLT)
- PAH secretion (OAT) — at high concentrations, secretion saturates and clearance falls
3) Acid-base tie-in: proximal tubule is the bicarbonate workhorse
If the stem emphasizes bicarbonate wasting or carbonic anhydrase, you’re in proximal tubule reabsorption, not drug secretion.
One-liner summary
PAH is the prototype for proximal tubule organic anion secretion (OAT): active, saturable, competitively inhibited—exactly how the kidney clears many organic acids and drugs.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
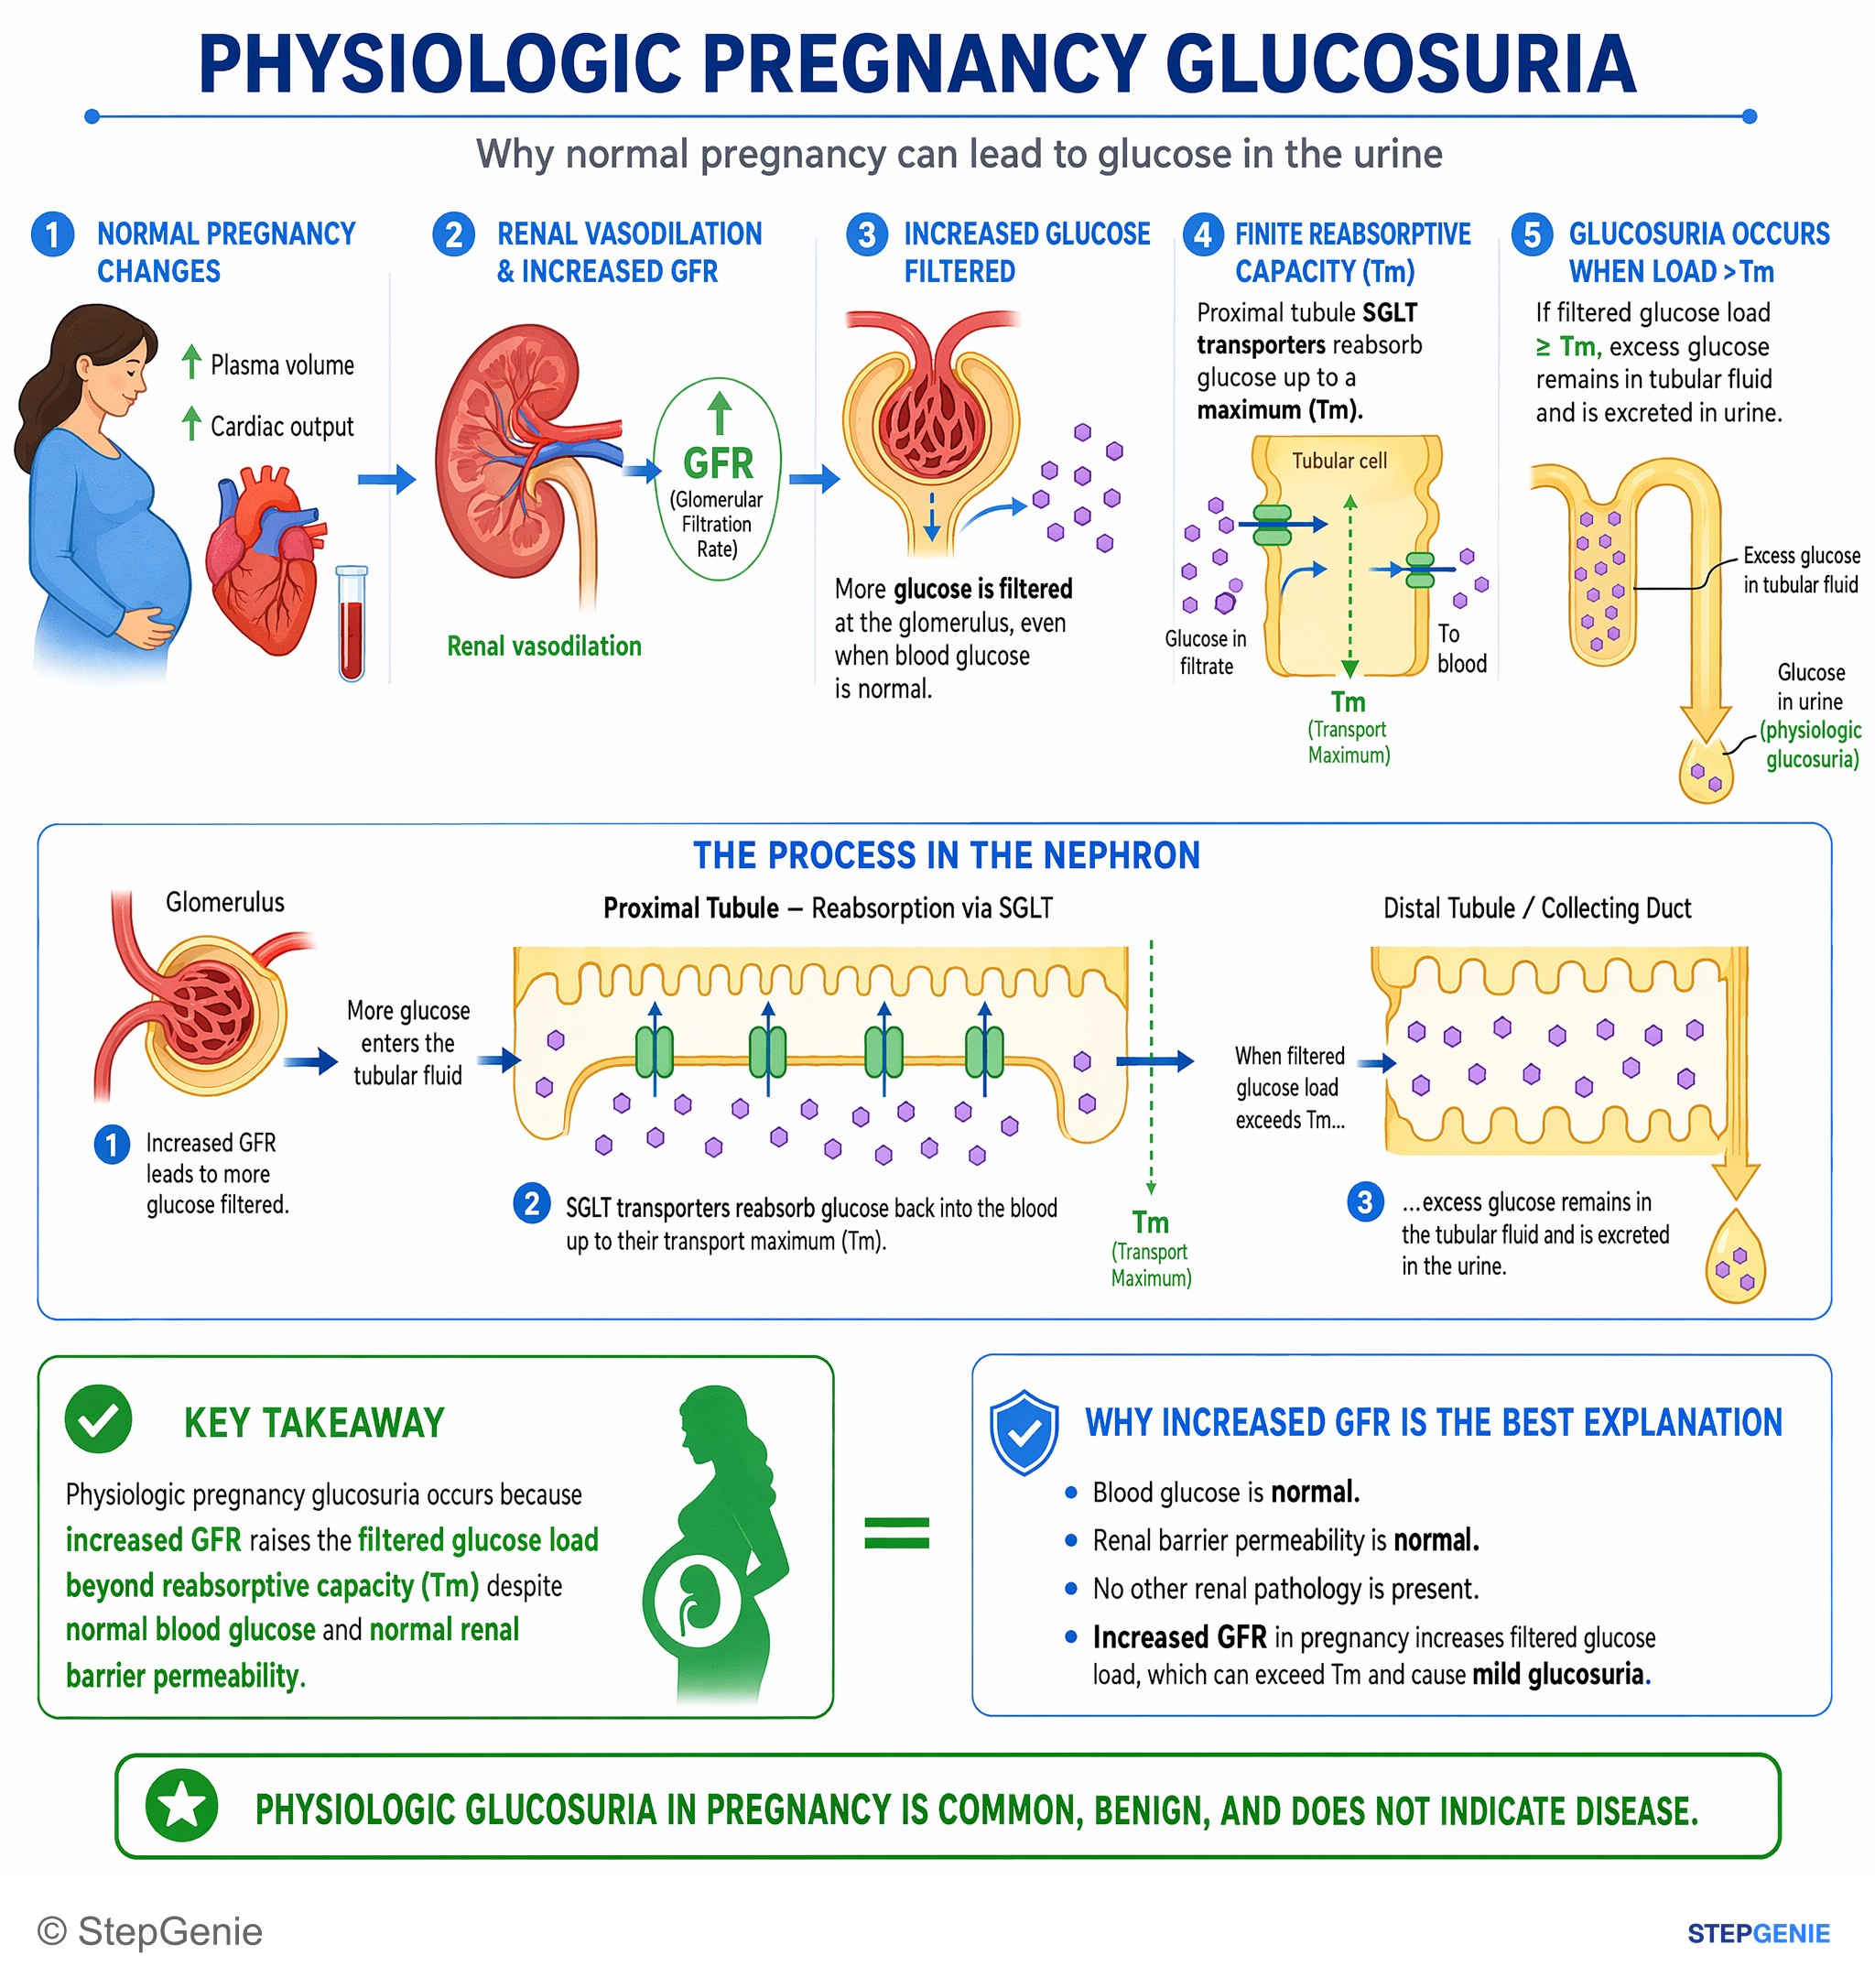
Physiologic pregnancy glucosuria: increased GFR raises filtered glucose load beyond reabsorptive capacity despite normal blood glucose and…
USMLE Step 1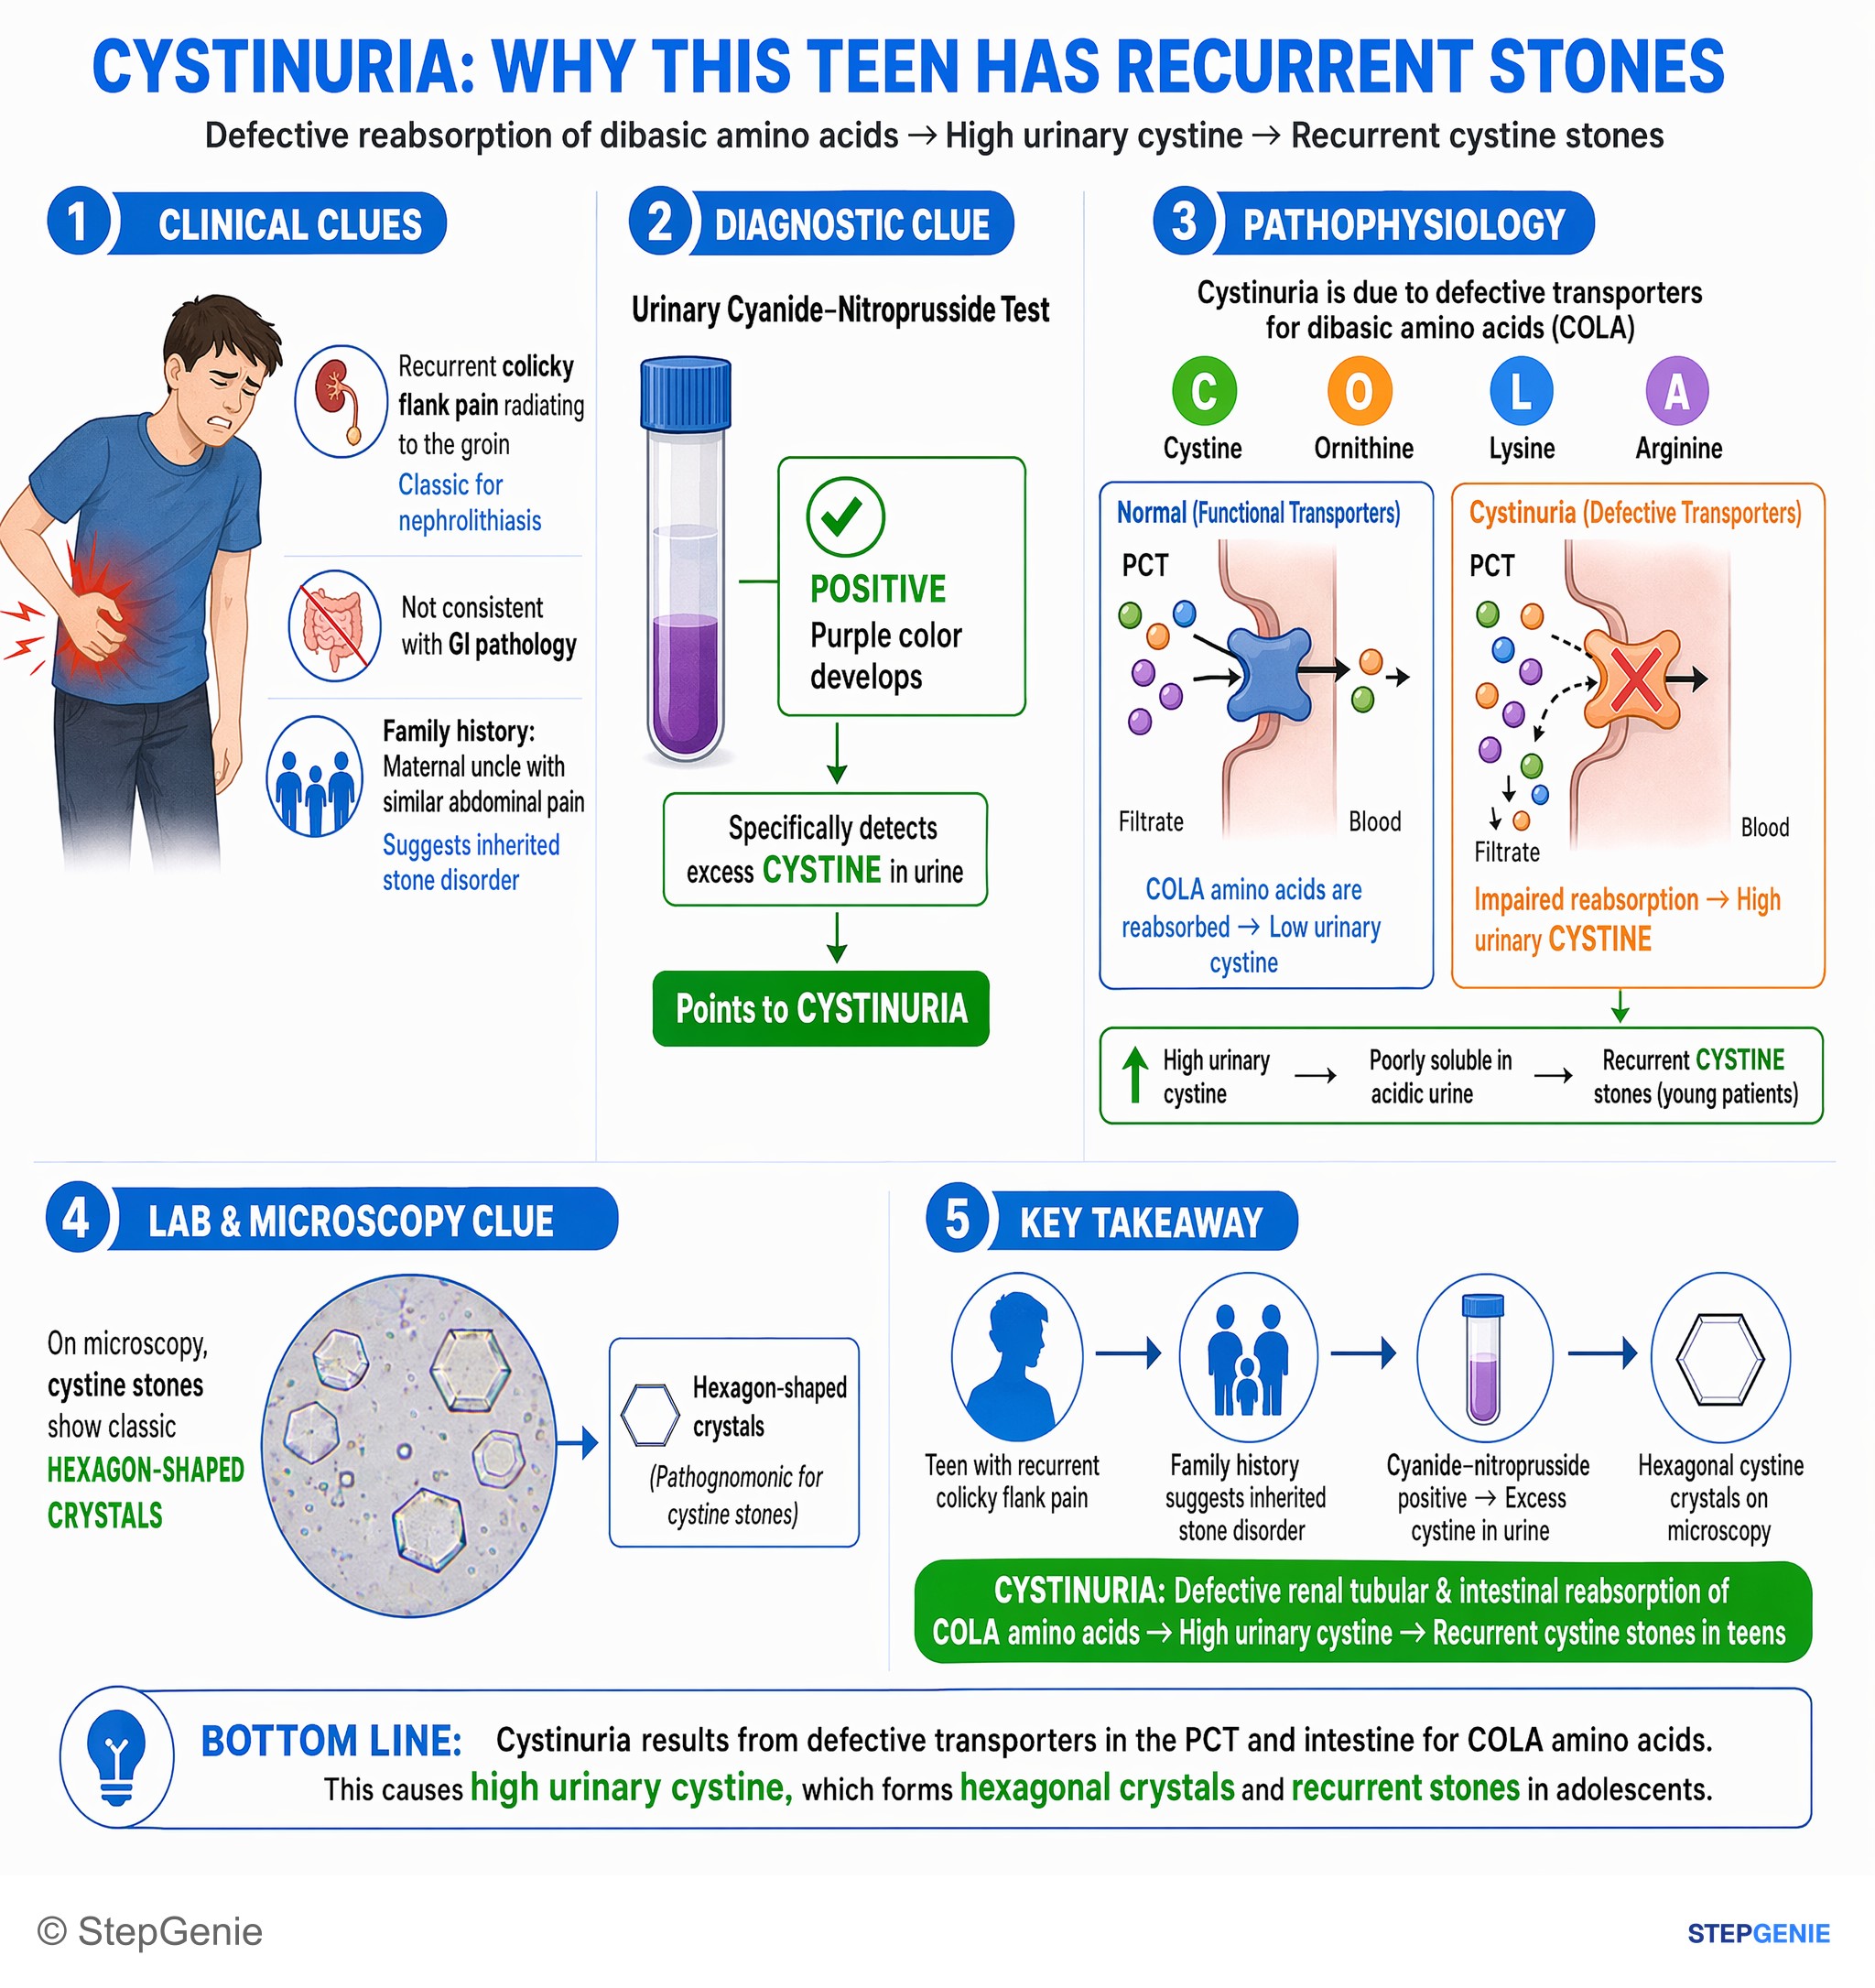
Cystinuria from defective renal tubular reabsorption of COLA amino acids → recurrent stones in teens, cyanide-nitroprusside positive…
USMLE Step 1Frequently Asked Questions
What is the classic substance secreted by the proximal tubule organic anion transporter system?
Para-aminohippurate, or PAH, is the classic substance secreted by the proximal tubule organic anion transporter system. It is freely filtered at the glomerulus and then actively secreted in the proximal tubule by organic anion transporters. Because it is removed so efficiently at low plasma concentrations, its renal clearance approximates renal plasma flow.
How do you recognize an OAT secretion question on a renal physiology vignette?
You should think of OAT-mediated secretion when the stem mentions an organic acid, drug or toxin elimination, proximal tubule secretion, saturation, or competitive inhibition. Common clues also include probenecid, penicillin, urate, NSAIDs, diuretics, and toxins. These details point to the proximal tubule organic anion transport system rather than simple filtration or reabsorption.
Why isn’t glucose handled by the same proximal tubule transporter as PAH?
Glucose is not handled by the PAH transporter because it is reabsorbed, not secreted, and it uses a different mechanism. In the proximal tubule, glucose is reclaimed by sodium-coupled cotransport through SGLT2 early and SGLT1 later. That is distinct from organic anion transporter-mediated secretion, which moves substances like PAH and many organic acids.
Why is bicarbonate not the right answer for proximal tubule organic acid secretion?
Bicarbonate is mainly reabsorbed rather than secreted by the proximal tubule organic anion transport system. Its handling depends on secreted hydrogen ions and carbonic anhydrase, which allow filtered bicarbonate to be converted, taken up, and returned to the blood. Although beta-intercalated cells can secrete bicarbonate in alkalosis, that occurs in the collecting duct, not through proximal tubule OATs.
How is urea handling different from classic proximal tubule organic acid secretion?
Urea is different because its renal handling is tied to passive reabsorption and recycling, not OAT-mediated toxin secretion. In the proximal tubule, urea is passively reabsorbed as water is reabsorbed. It can later enter the tubule in the thin descending limb, and ADH increases urea permeability in the inner medullary collecting duct to help maintain the medullary osmotic gradient.