A pneumothorax is air in the pleural space. A spontaneous pneumothorax happens without trauma: primary when there is no known lung disease (classically a tall, thin young male smoker with ruptured apical blebs) and secondary when lung disease, most often COPD, is present. A tension pneumothorax acts as a one-way valve: pleural pressure stays positive, venous return falls and obstructive shock follows, with hypotension, JVD, a silent hyperresonant hemithorax and late tracheal deviation away from it. Tension is a clinical diagnosis: decompress first (adults: 4th/5th intercostal space, just anterior to the midaxillary line, per ATLS 10th edition and current trauma references), then place a chest tube; never wait for an x-ray.
Tension vs spontaneous pneumothorax at a glance
| Primary spontaneous | Secondary spontaneous | Tension | |
|---|---|---|---|
| Typical patient | Tall, thin man in his teens or 20s, often at rest | Older adult with lung disease, most often severe COPD | Ventilated, trauma or post-procedure patient; sometimes a spontaneous pneumothorax that progresses |
| Mechanism | Rupture of subpleural apical blebs or bullae | Rupture of a bulla or of diseased lung | One-way valve: air gets in but can't get out |
| Symptoms | Sudden pleuritic chest pain and dyspnea; can be mild | Worse for the same size (less reserve) | Severe distress, then shock or PEA arrest within minutes |
| Vital signs | Usually stable | More likely hypoxemic or unstable (less reserve) | Falling SpO2 and tachycardia early, hypotension late; rising airway pressures if ventilated |
| Chest exam | ↓ breath sounds, hyperresonance, ↓ tactile fremitus on the affected side | Same | Same, plus JVD and tracheal deviation away (late) |
| First move | Upright chest x-ray | Chest x-ray and admission | Decompress now, no imaging first |
The vignette
A 23-year-old man who smokes a pack of cigarettes a day comes to the emergency department 40 minutes after sudden right-sided pleuritic chest pain and shortness of breath began while he was sitting at his desk. He is 191 cm (6 ft 3 in) tall and weighs 66 kg (145 lb). He is agitated and diaphoretic. Pulse is 136/min, blood pressure 76/44 mm Hg, respirations 36/min and SpO2 84% on a non-rebreather mask. His neck veins are distended and his trachea is deviated to the left. The right hemithorax is hyperresonant with absent breath sounds; heart sounds are normal. Which is the most appropriate next step in management?
A. Upright chest x-ray B. Immediate needle decompression of the right chest C. Tube thoracostomy (chest tube) D. Rapid sequence intubation and mechanical ventilation E. 2-L crystalloid bolus and norepinephrine infusion F. Pericardiocentesis G. IV alteplase for presumed massive pulmonary embolism H. High-flow oxygen and a repeat chest x-ray in 4 hours
Answer: B, immediate needle decompression
The story starts as a primary spontaneous pneumothorax (tall, thin young smoker, onset at rest), but the vital signs say it has become a tension pneumothorax: one silent, hyperresonant hemithorax plus hypotension, JVD and tracheal deviation away from the affected side. That is obstructive shock, and the fix is to let the air out now. Merck's trauma chapter places a 14- or 16-gauge needle (or a finger thoracostomy) in the 4th or 5th intercostal space at the midaxillary line, and tube thoracostomy must follow immediately.
Why every other answer is wrong
- A. Upright chest x-ray: the right first test for a stable patient with a suspected simple pneumothorax. Here it wastes minutes: tension pneumothorax is diagnosed clinically, and treatment should not wait for radiographic confirmation.
- C. Tube thoracostomy: the definitive treatment and the very next step after decompression, but it takes longer to set up, so a crashing patient is decompressed first. In trauma care a finger thoracostomy at the same 4th/5th intercostal site is the alternative, and RCEM advises thoracostomy rather than a needle in peri-arrest patients. More on drains in chest tube indications.
- D. Intubation: positive-pressure ventilation pushes more air through the leak, and mechanical ventilation is the most common cause of tension pneumothorax (Merck). Intubating before decompressing can precipitate PEA arrest.
- E. Fluids and norepinephrine: the shock is mechanical (blocked venous return), not hypovolemic or distributive. Pressors don't relieve the obstruction.
- F. Pericardiocentesis: tamponade is the other obstructive shock with JVD and hypotension, but breath sounds are equal and percussion is normal; expect muffled heart sounds and pulsus paradoxus. Unilateral absent breath sounds and hyperresonance separate tension pneumothorax from tamponade.
- G. Alteplase: massive PE also causes obstructive shock, JVD and hypoxemia, but the chest exam is symmetric, with no hyperresonance or tracheal shift (see the pulmonary embolism memory palace).
- H. High-flow oxygen and repeat x-ray: observation with repeat imaging suits only a stable, minimally symptomatic primary spontaneous pneumothorax, and never a patient in shock. Supplemental oxygen can speed reabsorption of pleural air, but Merck notes that giving it to non-hypoxemic patients has minimal evidence and is not part of current recommendations.
Why tension pneumothorax kills
- One-way valve. Air enters the pleural space on inspiration but can't leave, so pleural pressure becomes positive throughout the respiratory cycle.
- Hypoxemia. The collapsed lung is still perfused but not ventilated, a shunt that extra oxygen barely corrects (see dead space vs shunt), and the shifted mediastinum compresses the other lung.
- Shock. Rising intrathoracic pressure and mediastinal shift cut venous return, so preload and cardiac output fall: hypotension with distended neck veins.
- Timing. Chest pain, distress and falling saturations come first; hypotension and tracheal deviation are late in a spontaneously breathing patient. On a ventilator it is fast: abrupt desaturation, hypotension, tachycardia and rising ventilation pressures.
- Causes. Mechanical ventilation (barotrauma), blunt or penetrating chest trauma, central line attempts, CPR, and a simple pneumothorax that converts.
Where to put the needle: ATLS vs the classic site
| Classic site | ATLS adult site | |
|---|---|---|
| Location | 2nd intercostal space, midclavicular line | 4th or 5th intercostal space, just anterior to the midaxillary line |
| Who | Children (still the site taught); still printed in some references, including Merck's pulmonary chapter and the European Trauma Course | Adults (ATLS 10th edition; Merck's 2026 trauma chapter; RCEM) |
| Needle | 14- or 16-gauge catheter | ATLS 10: 5 cm in small adults, 8 cm in larger adults |
| Chest wall | Thicker on average | Thinner on average |
A 2025 meta-analysis found that, in imaging-based studies, the needle failed to reach the pleural cavity about a third of the time (32.8%), and each extra centimeter of needle length cut the failure rate by about 7.8 percentage points. Once needle length was accounted for, failure rates did not differ significantly between the two sites, so length matters as much as location. ATLS 11 (2025) is now the current edition: its skills labs make finger and tube thoracostomy mandatory and needle thoracostomy optional. Older questions may still give the 2nd intercostal space; for adults, ATLS 10th edition and current trauma references (Merck, RCEM) teach the 4th/5th space.
Spontaneous pneumothorax: primary vs secondary
| Primary (PSP) | Secondary (SSP) | |
|---|---|---|
| Definition | No clinically apparent lung disease | Underlying lung disease |
| Who | Tall, thin men in their teens and 20s | Older adults (typically 60-65) |
| Cause | Ruptured subpleural apical blebs or bullae | Bulla rupture in severe COPD (most common); also cystic fibrosis, PCP in HIV, TB, asthma, IPF, LAM, lung cancer, sarcoidosis |
| Risk factors | Smoking (tobacco or marijuana), tall thin build, family history, diving, high-altitude flying | The underlying lung disease |
| Severity | Usually benign | More serious: less pulmonary reserve |
| Recurrence | 19-29% at 1 year (Merck) | Higher than PSP |
Other causes the exam likes:
- Genetic and connective tissue: Marfan syndrome (see the Marfan syndrome question), Ehlers-Danlos syndrome and Birt-Hogg-Dubé syndrome (FLCN, autosomal dominant: lung cysts and pneumothorax, benign skin tumors on the face and neck, kidney tumors).
- Catamenial pneumothorax: within 48 hours of the onset of menstruation, caused by thoracic endometriosis.
- Iatrogenic: transthoracic needle aspiration (the leading cause), thoracentesis, central venous catheters, mechanical ventilation and CPR.
Diagnosis: x-ray and ultrasound signs
- Upright chest x-ray: a thin visceral pleural line with no lung markings between it and the chest wall. Large pneumothoraces shift the trachea and mediastinum away.
- Supine film (trauma): the deep sulcus sign, an abnormally deep costophrenic angle.
- Size: older guidelines used size cut-offs to decide on drainage. BTS 2023 says size is no longer an indication for invasive management, although it dictates whether an intervention is safe (in general, a rim of ≥2 cm laterally or apically on chest x-ray).
- Bedside ultrasound (eFAST): absent lung sliding, absent comet-tail artifacts and a lung point (where sliding lung meets the pneumothorax); up to 94% sensitive and 100% specific in skilled hands, better than chest x-ray.
- CT: detects occult pneumothoraces, which are usually not clinically significant.
- Tension: none of the above first. Treat on clinical grounds.
Management: BTS 2023 for spontaneous pneumothorax
- Asymptomatic or minimally symptomatic PSP (no significant pain or breathlessness, no physiological compromise): conservative management regardless of size, with follow-up.
- Symptomatic PSP: choose with the patient between avoiding a procedure, an ambulatory device and rapid relief with needle aspiration or a chest drain.
- High-risk characteristics in the BTS pathway: hemodynamic compromise (tension), significant hypoxia, bilateral pneumothorax, underlying lung disease, age ≥50 with a significant smoking history, and hemopneumothorax.
- SSP: managed in hospital, usually with a small-bore (<14 Fr) chest drain (Merck). Chemical pleurodesis can be considered even after a first episode, for example in severe COPD.
- Recurrence prevention: surgery (VATS bullectomy and/or pleurodesis) for a second ipsilateral, first contralateral or synchronous bilateral pneumothorax or a persistent air leak, and considered at the first episode after a tension pneumothorax or in at-risk professions (pilots, divers). If unfit for surgery with a persistent air leak: autologous blood pleurodesis or endobronchial therapy.
- Counseling (BTS): stop smoking, because it raises recurrence risk; fly no sooner than 7 days after an x-ray shows full resolution; avoid scuba diving permanently unless a definitive procedure such as surgical pleurectomy has been done.
- Complication to know: re-expansion pulmonary edema after rapid re-expansion of a collapsed lung.
How USMLE tests it: change one detail
| If the stem shows... | Think | Best next step |
|---|---|---|
| Tall, thin young smoker, stable, mild symptoms | PSP | Chest x-ray; conservative care if minimally symptomatic |
| Stable PSP with significant pain or breathlessness | PSP | Needle aspiration, ambulatory device or chest drain |
| COPD or HIV with PCP, sudden worse dyspnea | SSP | Admit, small-bore chest drain, plan recurrence prevention |
| Ventilated patient: ↑ airway pressures, ↓ SpO2, ↓ BP | Tension | Decompress, then chest tube |
| Trauma: shock, JVD, one silent hyperresonant hemithorax | Tension | Decompress, then chest tube |
| Shock, JVD, muffled heart sounds, equal breath sounds | Tamponade | Pericardiocentesis |
| Chest wound that sucks air with each breath | Open pneumothorax | Three-sided dressing, then chest tube |
Key takeaways
- Primary spontaneous = no lung disease, tall thin young male smoker, apical blebs; secondary = lung disease (COPD most often), more dangerous.
- Tension = one-way valve → ↓ venous return → obstructive shock: JVD, a silent hyperresonant hemithorax, late tracheal deviation away.
- Tension is clinical: decompress before imaging, then place a chest tube; don't intubate first.
- Adult site (ATLS 10th edition, Merck, RCEM): 4th/5th intercostal space just anterior to the midaxillary line; the 2nd intercostal space, midclavicular line, is the classic site and is still used in children.
- BTS 2023: symptoms and high-risk features, not size, drive treatment; a minimally symptomatic PSP can be managed conservatively at any size.
- Ultrasound: absent lung sliding and a lung point. X-ray: visceral pleural line; deep sulcus sign when supine.
Sources
- Pneumothorax — Merck Manual Professional Edition (2025)
- Tension Pneumothorax — Merck Manual Professional Edition (2026)
- Pneumothorax — StatPearls, NCBI Bookshelf (2023)
- Tension Pneumothorax — StatPearls, NCBI Bookshelf (2025)
- BTS Guideline for Pleural Disease — British Thoracic Society (2023)
- BTS Guideline for Pleural Disease: Summary of Guideline — British Thoracic Society (2023)
- BTS Guideline for Pleural Disease, Appendix 1: Clinical Pathways — British Thoracic Society (2023)
- Meta-analysis of the optimal needle length and decompression site for tension pneumothorax and consensus recommendations on current ATLS and ETC guidelines — World Journal of Emergency Surgery (2025)
- Thoracic Trauma — RCEMLearning (2026)
- Advanced Trauma Life Support (ATLS 11) — American College of Surgeons
- ATLS 11th Edition Learning Labs — American College of Surgeons (2025)
- Birt-Hogg-Dubé syndrome — MedlinePlus Genetics
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
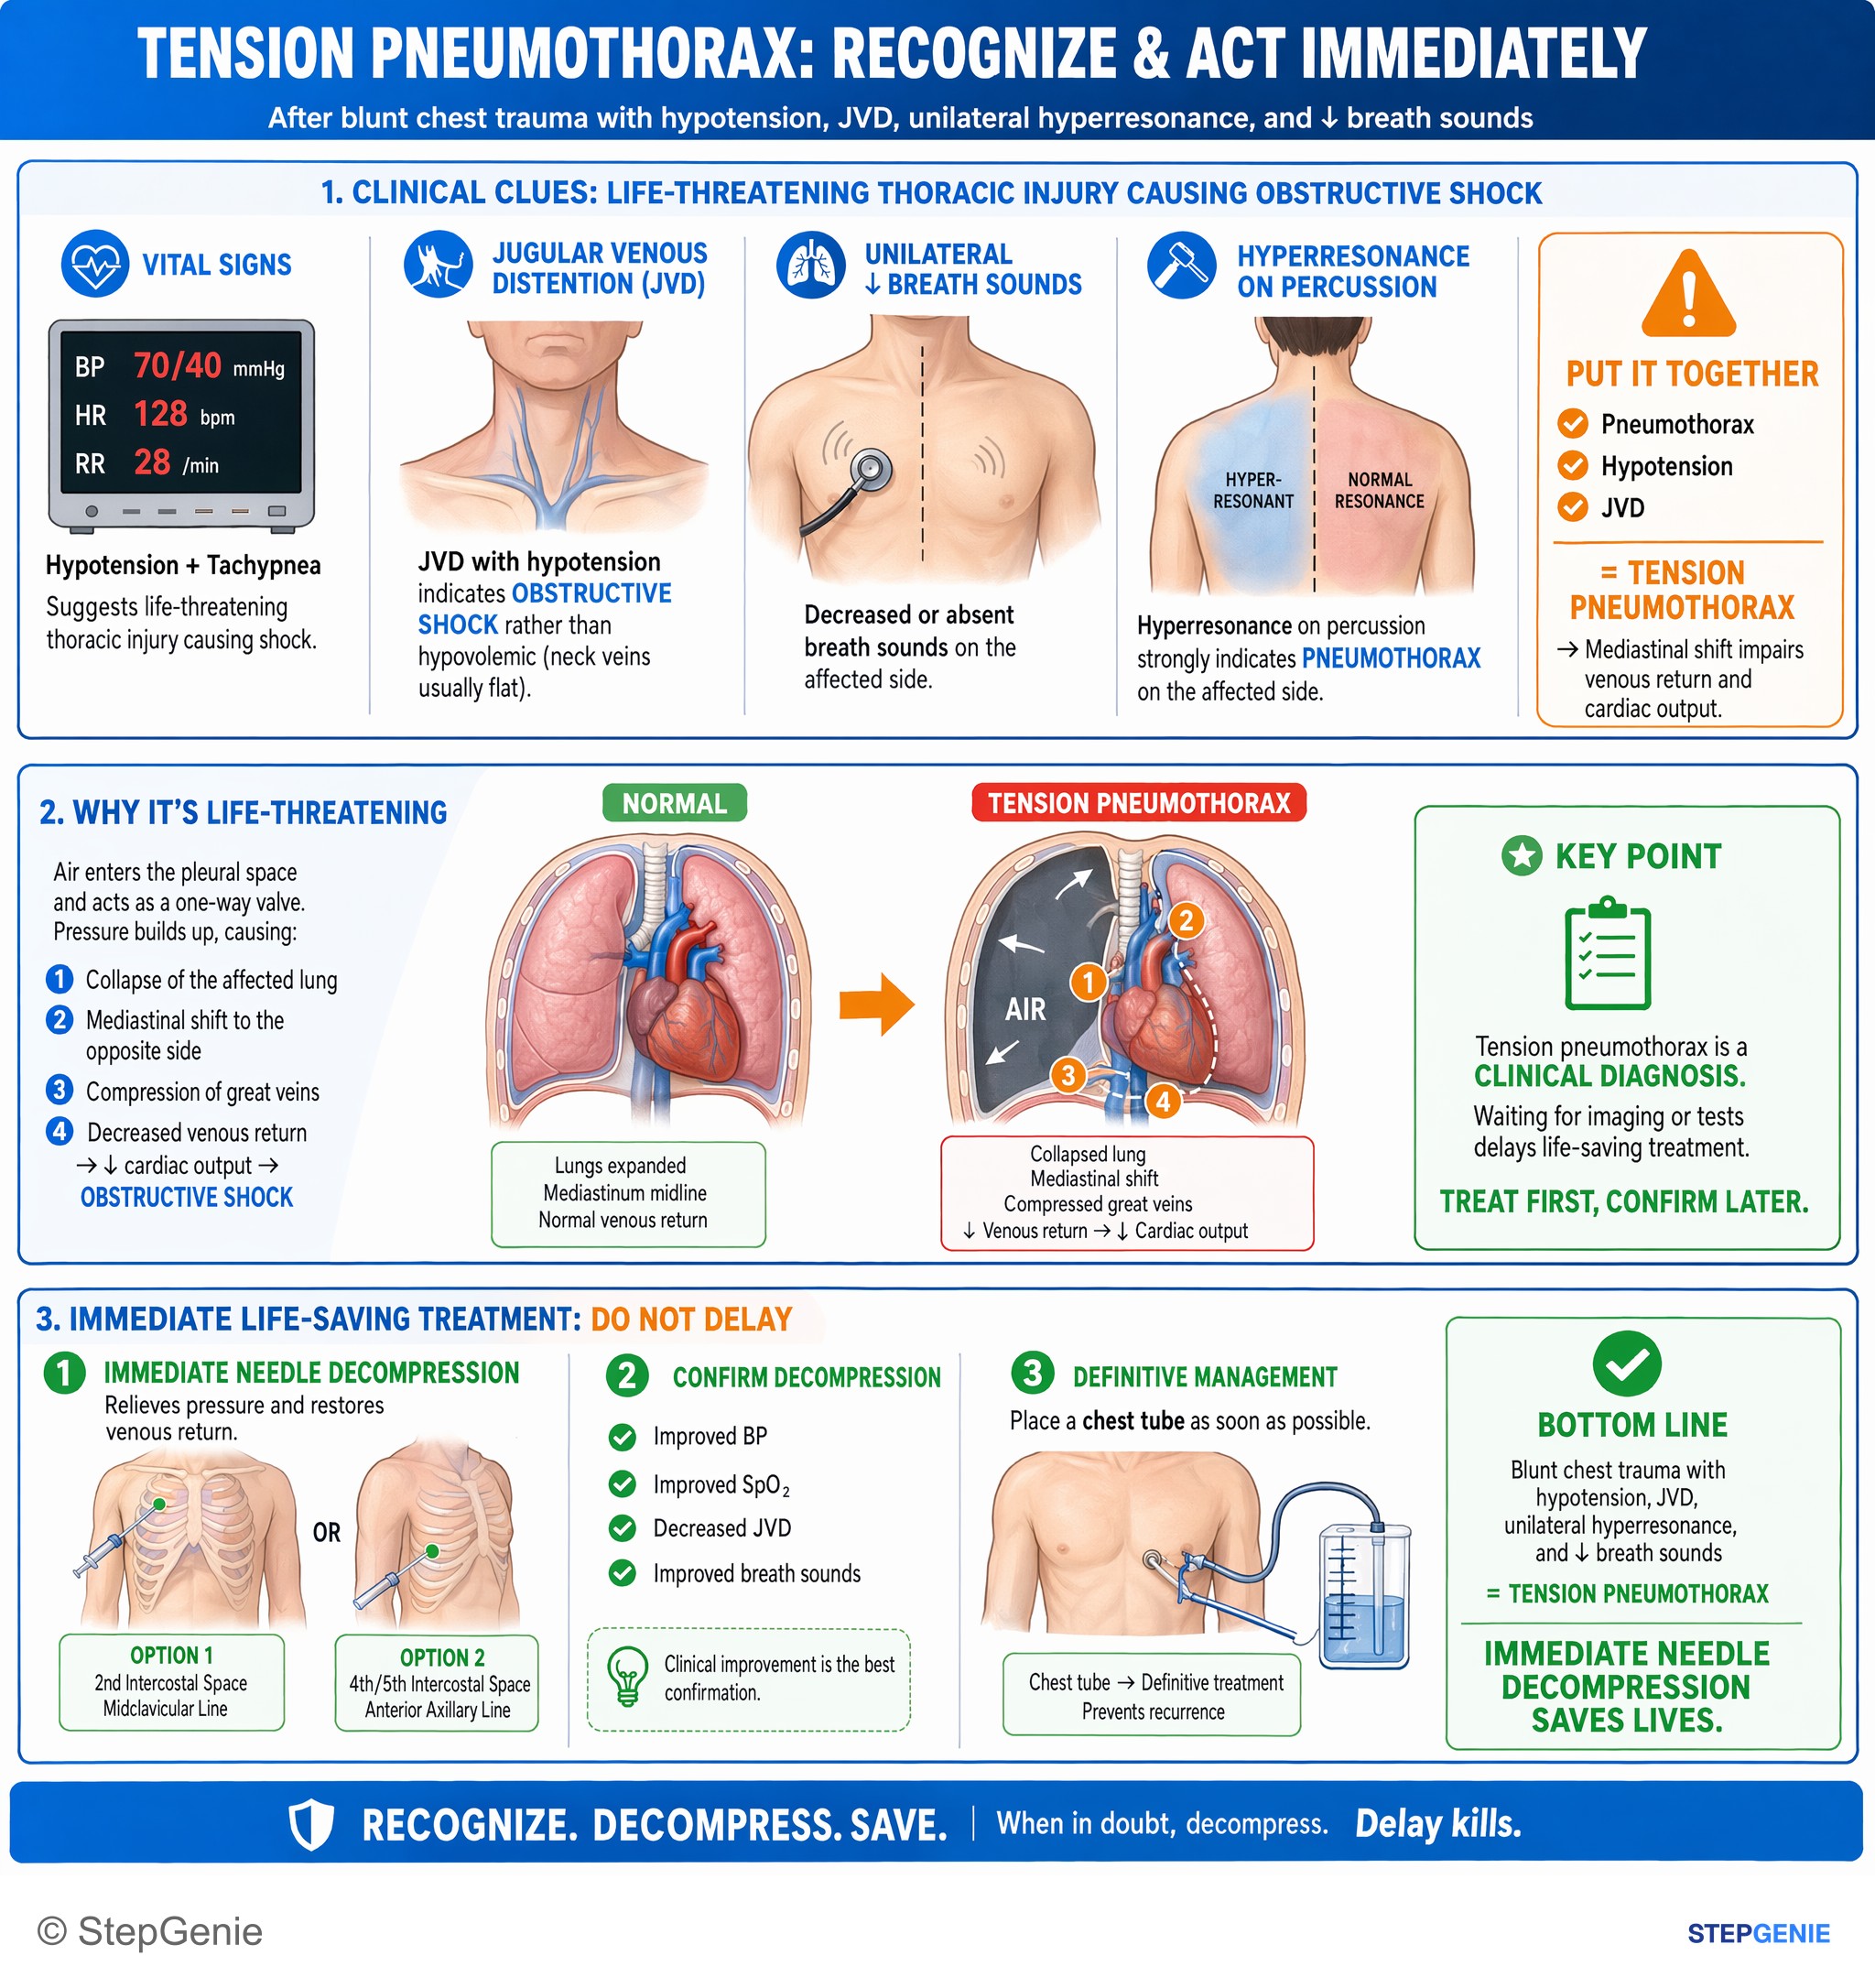
Tension pneumothorax after blunt chest trauma: hypotension, JVD, unilateral hyperresonance, ↓ breath sounds ⇒ immediate needle…
USMLE Step 2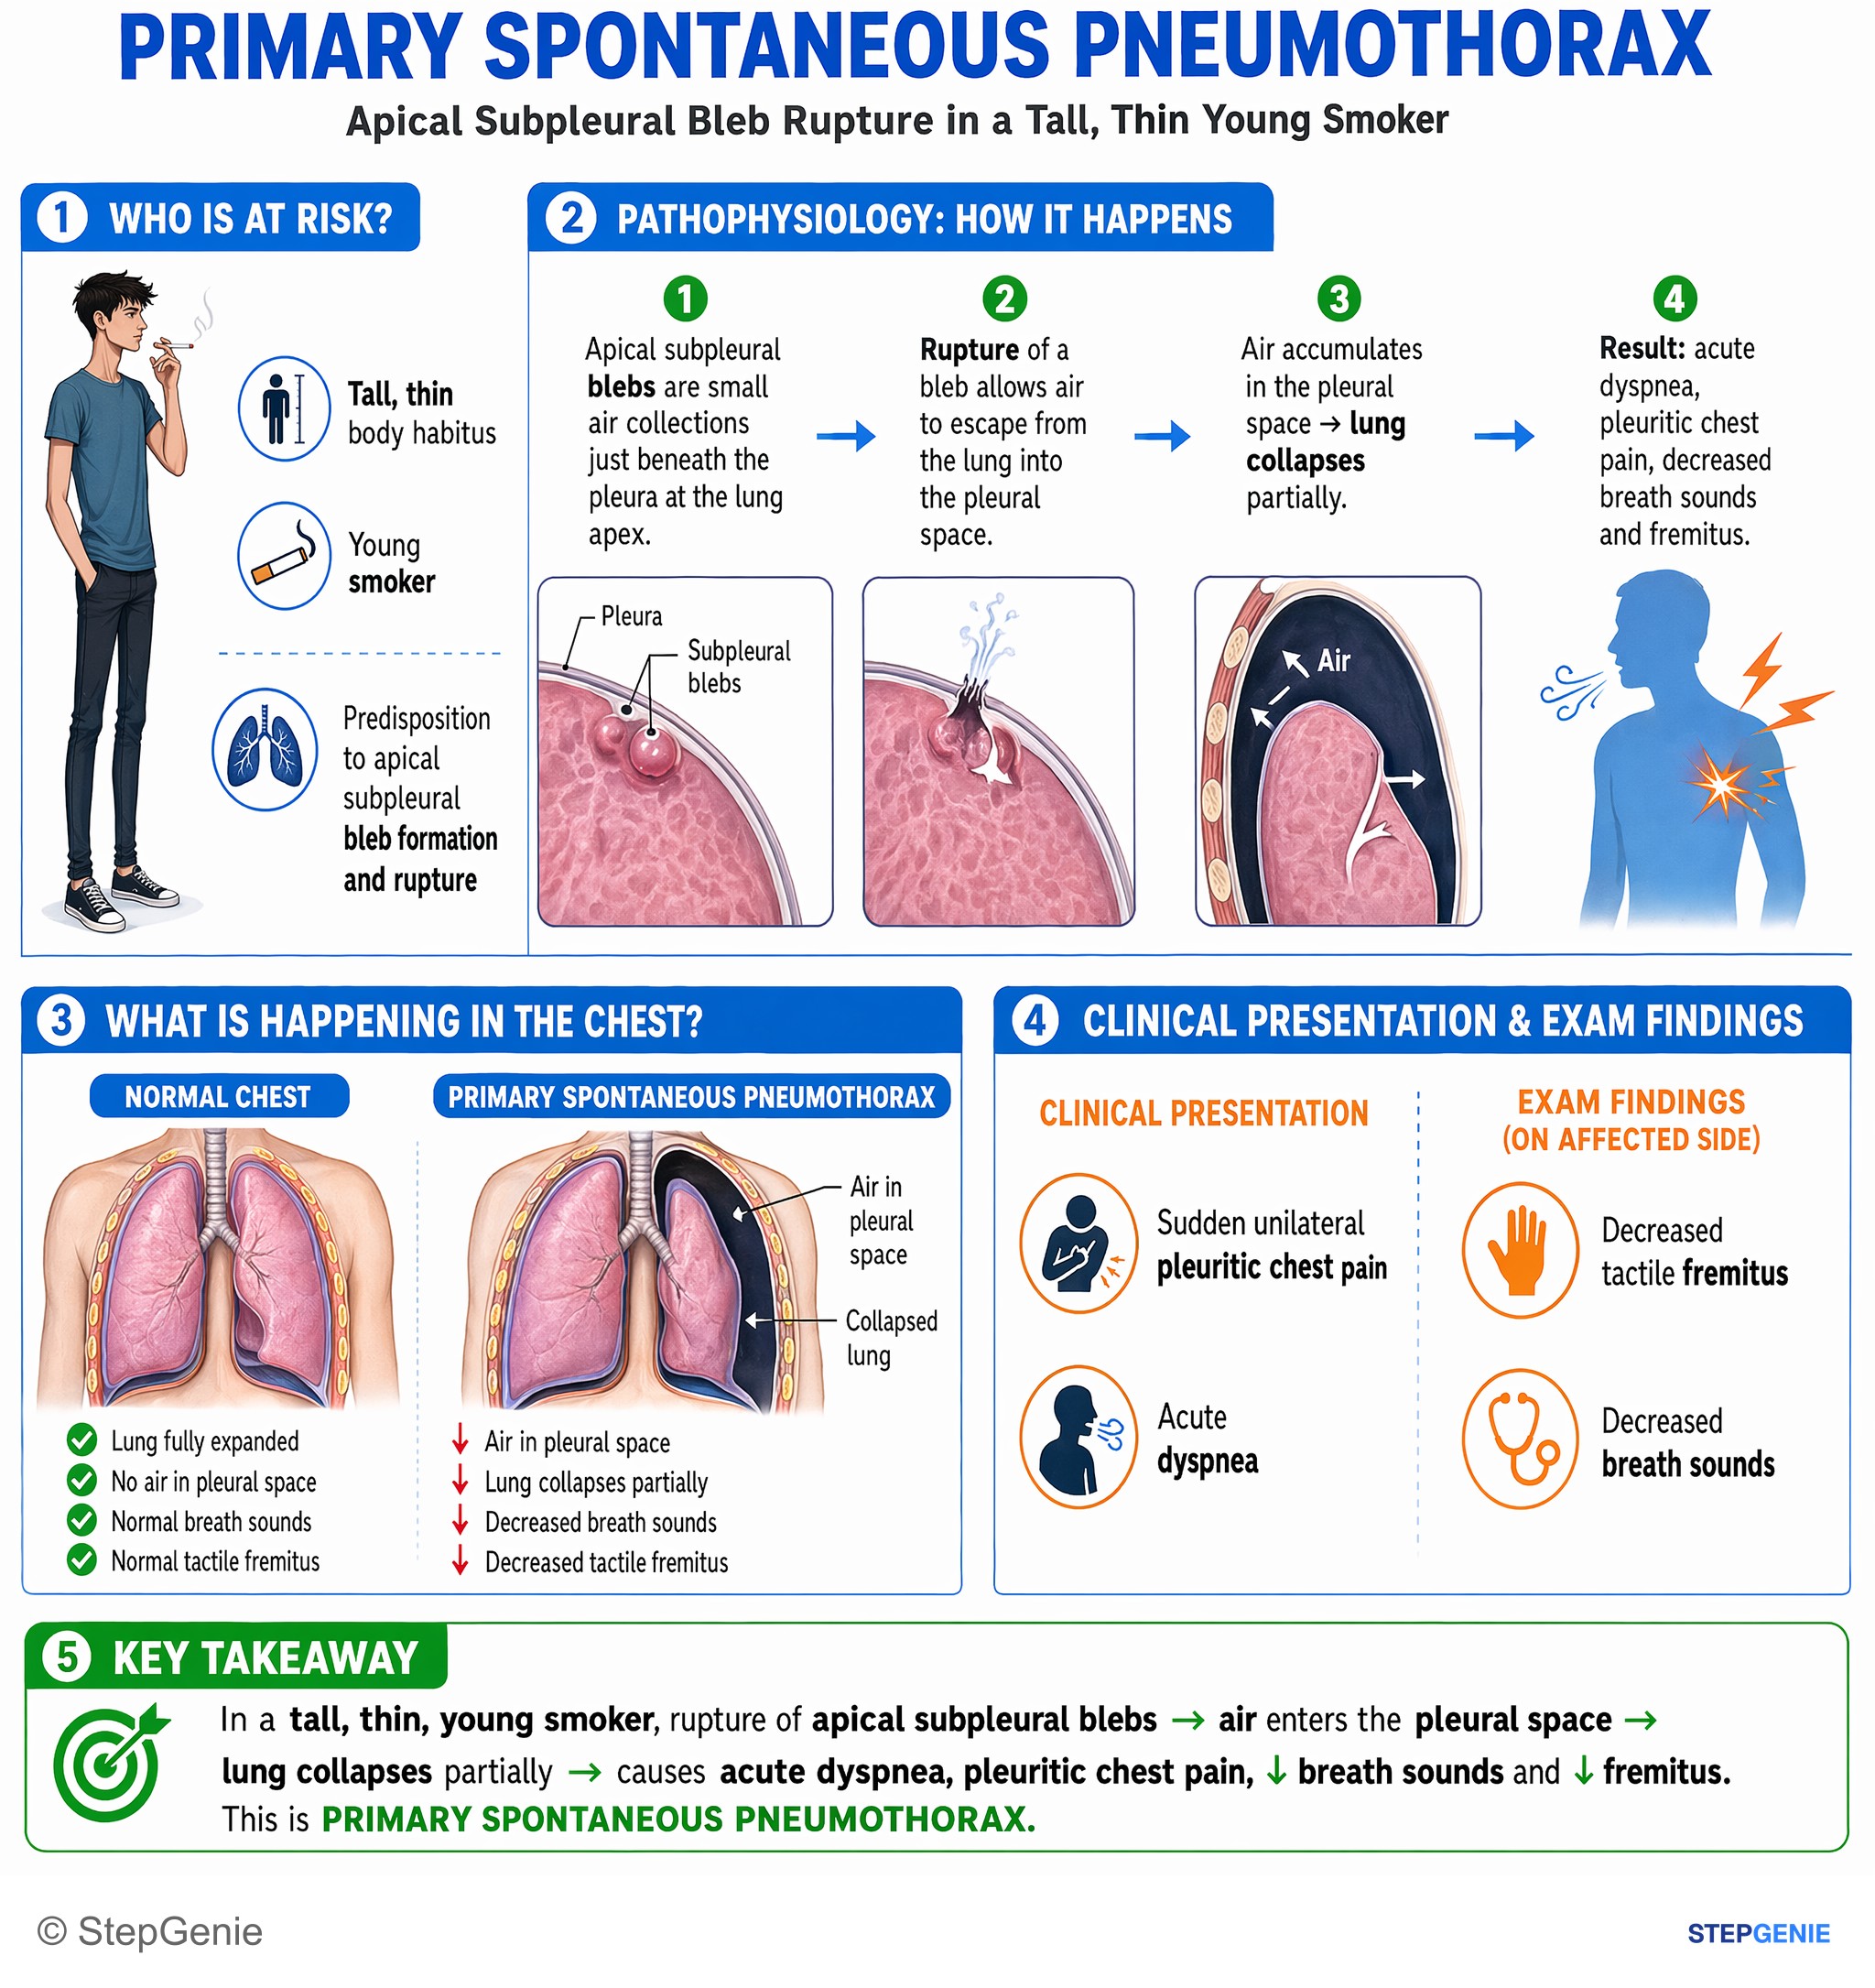
Primary spontaneous pneumothorax from apical subpleural bleb rupture in tall, thin young smoker → acute pleuritic chest pain, dyspnea, ↓…
USMLE Step 1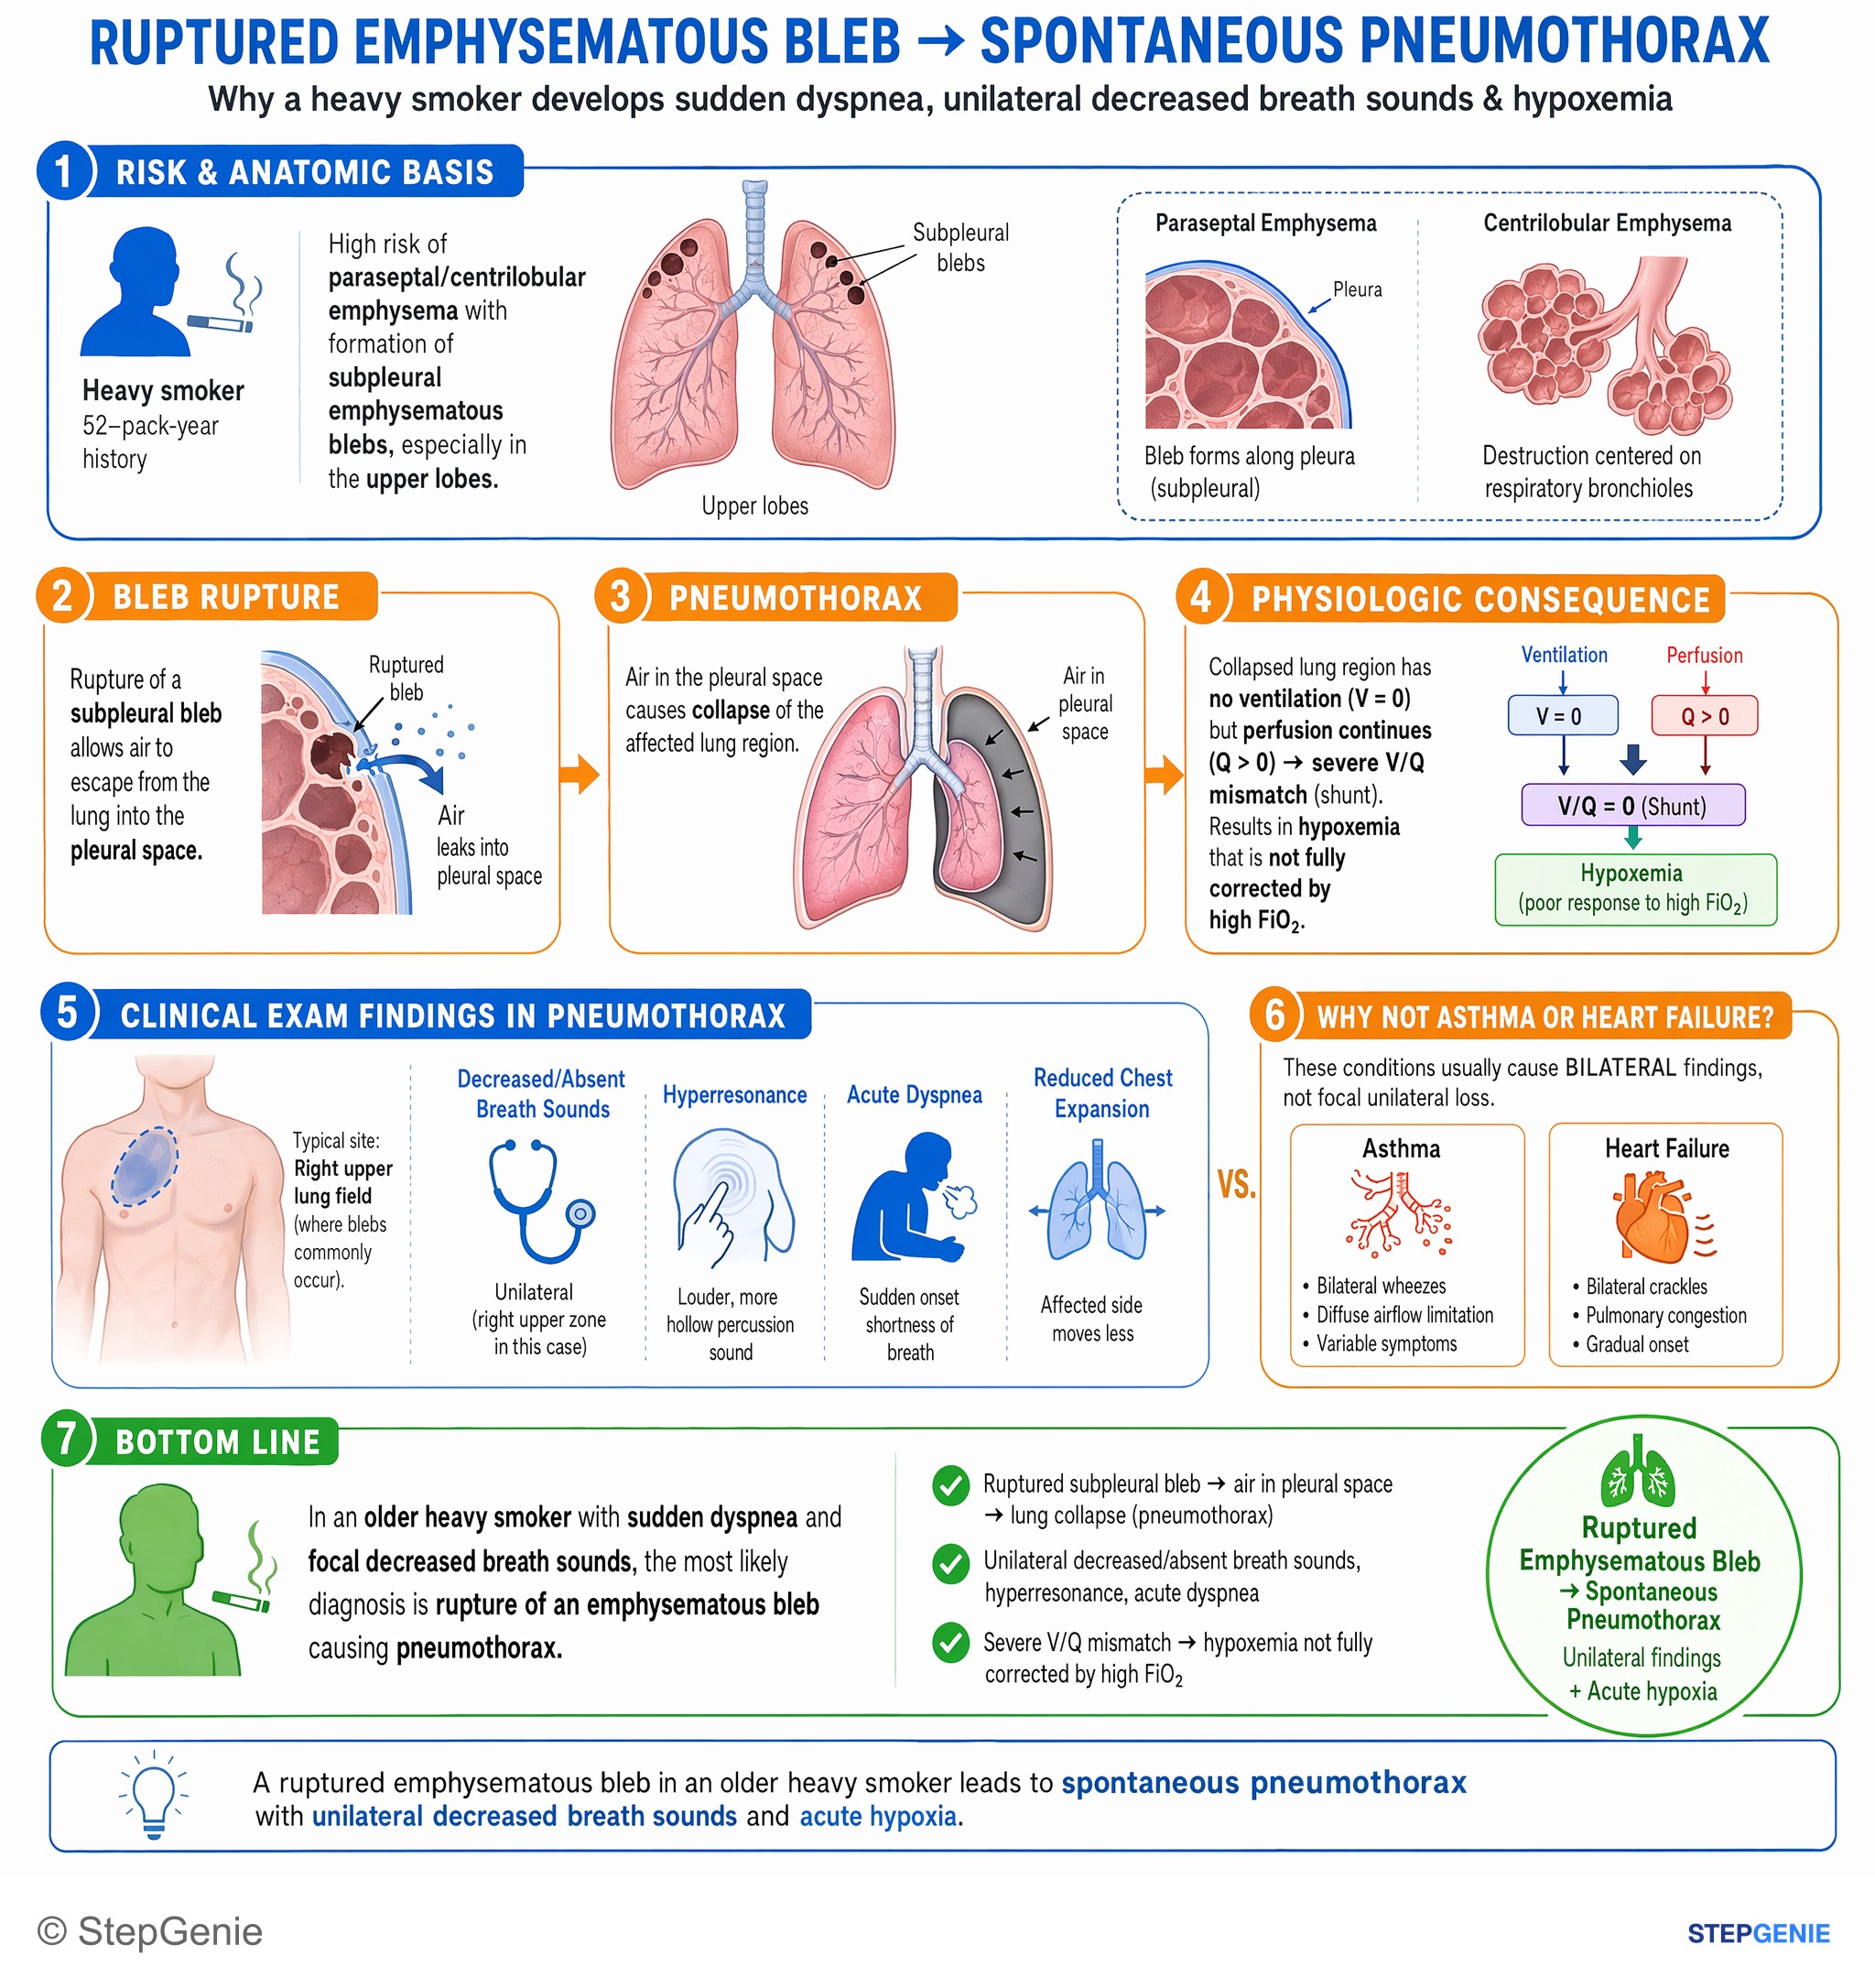
Ruptured emphysematous bleb in an older heavy smoker → spontaneous pneumothorax with unilateral decreased breath sounds and acute hypoxia.
USMLE Step 2Frequently Asked Questions
What is the difference between tension and spontaneous pneumothorax?
Spontaneous pneumothorax describes the cause: air leaks into the pleural space without trauma, either in someone with no known lung disease (primary, classically a tall, thin young male smoker with apical blebs) or in someone with lung disease such as COPD (secondary). Tension pneumothorax describes the physiology: air gets in but cannot get out, pleural pressure stays positive, venous return falls and obstructive shock follows. A spontaneous pneumothorax can progress to tension, especially with positive-pressure ventilation.
Where is needle decompression done for tension pneumothorax?
For adults, ATLS 10th edition teaching, also used in Merck's 2026 trauma chapter and by RCEM, is the 4th or 5th intercostal space just anterior to the midaxillary line, with a 14- or 16-gauge catheter long enough to reach the pleura (ATLS suggests 5 cm in small adults and 8 cm in larger adults). The classic site, the 2nd intercostal space in the midclavicular line, is still used in children and still appears in some references. A chest tube must follow immediately.
What are the signs of tension pneumothorax?
Early signs are chest pain, respiratory distress, tachycardia and falling oxygen saturation. As pressure builds, hypotension, distended neck veins, absent breath sounds with hyperresonance on one side, and tracheal deviation away from the affected side appear; hypotension and tracheal deviation are late signs. In ventilated patients it develops fast, with sudden desaturation, hypotension and rising airway pressures. It is treated on clinical grounds, without waiting for an x-ray.
What are the risk factors for primary vs secondary spontaneous pneumothorax?
Primary spontaneous pneumothorax occurs without known lung disease, classically in tall, thin men in their teens and 20s; smoking tobacco or marijuana is the main modifiable risk, and a family history also raises risk. Secondary spontaneous pneumothorax complicates lung disease, most often severe COPD, but also cystic fibrosis, Pneumocystis pneumonia in HIV, tuberculosis, interstitial lung disease and lymphangioleiomyomatosis. Inherited conditions such as Marfan syndrome and Birt-Hogg-Dube syndrome also predispose. Secondary cases are more dangerous because of reduced reserve.
How is spontaneous pneumothorax treated under the 2023 BTS guideline?
The 2023 British Thoracic Society guideline uses symptoms and high-risk features rather than size to decide on treatment. Asymptomatic or minimally symptomatic primary spontaneous pneumothorax can be managed conservatively regardless of size, with follow-up. Symptomatic patients can choose an ambulatory device, needle aspiration or a chest drain. High-risk features include hemodynamic compromise, significant hypoxia, bilateral pneumothorax, underlying lung disease, age 50 or over with a significant smoking history, and hemopneumothorax.
What does a pneumothorax look like on x-ray and ultrasound?
On an upright chest x-ray there is a thin visceral pleural line with no lung markings beyond it, and a large pneumothorax shifts the trachea and mediastinum away. On a supine trauma film, look for the deep sulcus sign, an abnormally deep costophrenic angle. On bedside ultrasound, pneumothorax shows absent lung sliding, absent comet-tail artifacts and a lung point, where sliding lung meets the air. In skilled hands ultrasound is more sensitive than chest x-ray.