A pleural effusion is an exudate if it meets any one of Light's criteria: pleural fluid-to-serum protein ratio above 0.5, pleural fluid-to-serum LDH ratio above 0.6, or pleural fluid LDH above two-thirds of the upper limit of normal for serum LDH. A transudate meets none and reflects a systemic pressure problem, most often heart failure.
Exudates come from a diseased pleura or blocked lymphatics: pneumonia (the most common cause of exudates), cancer, pulmonary embolism and tuberculosis. Light's criteria catch nearly all exudates but mislabel about 20-25% of transudates, mostly heart failure treated with diuretics; a serum-minus-pleural albumin gradient above 1.2 g/dL then points back to a transudate.
In pneumonia, a pleural fluid pH of 7.2 or lower means the space needs a drain (BTS 2023). Below, a worked Q-bank question explains every answer choice.
Light's criteria: the three rules
| Light's criterion | Exudate if | Compare with |
|---|---|---|
| Pleural fluid protein ÷ serum protein | Above 0.5 | Patient's serum protein, drawn with the tap |
| Pleural fluid LDH ÷ serum LDH | Above 0.6 | Patient's serum LDH, drawn with the tap (Merck) |
| Pleural fluid LDH | Above two-thirds of the upper limit of normal (ULN) for serum LDH | The lab's reference range, not the patient's LDH |
- Any one positive = exudate; all three negative = transudate (BTS 2023; Porcel and Light). Memory hook: the cutoffs climb 0.5, 0.6, then two-thirds (about 0.67).
- ULN is the top of the laboratory's reference range for serum LDH (BTS: "the upper limits of laboratory normal value"). A ULN of 220 U/L gives a cutoff of about 147 U/L; a ULN of 250 U/L gives about 167 U/L. The 1972 paper, built on 150 effusions, used a fixed pleural LDH above 200 IU, later modified to two-thirds of the ULN (Sundaralingam et al. 2020).
- Sensitive, not specific: 98% and 77% in Merck's table. The criteria miss almost no exudates but label about 20% (Merck) to 25% (Light 2013) of transudates as exudates, mostly in patients on diuretics.
- LDH-only exudates (protein ratio not met) are usually parapneumonic or malignant (Porcel and Light).
Transudative vs exudative: what each one means
| Transudate | Exudate | |
|---|---|---|
| Mechanism | Higher hydrostatic or lower oncotic pressure pushes fluid across a normal pleura (Starling forces) | Inflamed, infected or infiltrated pleura leaks protein (higher capillary permeability), or lymphatic drainage is blocked |
| Light's criteria | None met | At least one met |
| Most common causes | Heart failure, then cirrhosis and nephrotic syndrome | Parapneumonic effusion, cancer, pulmonary embolism, tuberculosis |
| What you do next | Treat the cause; little workup needed | Find the cause (see the clues table below) |
Heart failure is the most common cause of any pleural effusion (about 500,000 US cases a year in Light's estimates, ahead of pneumonia and cancer).
Causes of transudative and exudative effusions
| Cause | Type | Clue |
|---|---|---|
| Heart failure | Transudate | Bilateral in 81%, right-sided in 12%, left-sided in 7% (Merck); JVD, S3, edema |
| Cirrhosis (hepatic hydrothorax) | Transudate | Ascites crosses diaphragmatic defects; about 70% right-sided; occasionally no visible ascites |
| Nephrotic syndrome, hypoalbuminemia | Transudate | Low oncotic pressure; usually bilateral, often subpulmonic; anasarca |
| Peritoneal dialysis, constrictive pericarditis, atelectasis, urinothorax | Transudate | Dialysate-like fluid; pericardial constriction; collapsed lung; obstructed urinary tract |
| Hypothyroidism | Either | Transudate when a pericardial effusion is also present |
| Parapneumonic effusion, empyema | Exudate | Neutrophils; low pH and glucose, very high LDH when complicated |
| Cancer | Exudate | Lung, breast, lymphoma; mesothelioma after asbestos exposure; lymphocytic, may be bloody, recurs |
| Pulmonary embolism | Exudate (almost always) | In about 40% of PE; often bloody; dyspnea out of proportion to the effusion |
| Tuberculosis | Exudate | Usually unilateral; lymphocytes; low-normal glucose; ADA above 40 U/L |
| Post-CABG | Exudate | Small left effusion common; bloody with eosinophils early, clear and lymphocytic after 30 days |
| Rheumatoid arthritis | Exudate | Older men with nodules; low glucose, low pH, high LDH |
| SLE | Exudate | May be the first sign; can be bilateral |
| Pancreatitis | Exudate | About 35% of acute pancreatitis; high amylase |
| Esophageal rupture | Exudate | Very ill after retching or endoscopy; low pH, salivary-type amylase |
| Chylothorax | Usually exudate (86% in Maldonado 2009) | Often milky; triglycerides above 110 mg/dL; thoracic duct injury or lymphoma |
| Drugs | Exudate | Tyrosine kinase inhibitors such as dasatinib lead (BTS 2023); amiodarone, nitrofurantoin, bromocriptine, dantrolene |
The diuretic trap: albumin and protein gradients
Diuresis is thought to remove water from the effusion faster than lymphatics clear protein, so protein and LDH concentrate past Light's cutoffs (Wijayaratne et al. 2024). About 20% of heart failure effusions meet exudate criteria after diuretics (Porcel and Light); in 364 cardiac effusions, 29% were mislabeled (Bielsa et al. 2012).
How to use the rescue tests:
- Use them when the picture says transudate (clear heart failure or cirrhosis) but the fluid is an exudate by a small margin; Merck prefers the protein gradient for patients on diuretics with no value more than 15% above its cutoff.
- Calculate a gradient: serum value minus pleural value, not a ratio.
- Never use a gradient instead of Light's criteria: alone, gradients misclassify many true exudates (Porcel and Light).
| Test | Favors a transudate when | Evidence |
|---|---|---|
| Serum albumin minus pleural fluid albumin | Above 1.2 g/dL | Reclassified 83% of heart failure false exudates; preferred (Bielsa 2012) |
| Serum protein minus pleural fluid protein | Above 3.1 g/dL | Reclassified 55% (Bielsa 2012); the test Merck and Light name |
| Pleural fluid-to-serum albumin ratio | Below 0.6 | Best of the three in cirrhosis (Bielsa 2012) |
| Serum NT-proBNP | Raised | BTS 2023: consider it to support heart failure in a unilateral effusion, never alone |
| Pleural fluid NT-proBNP | Above 1,500 pg/mL | Not superior to serum, so not routine (BTS 2023) |
The Q-bank question: why every answer choice matters
A 68-year-old man with ischemic cardiomyopathy (ejection fraction 25%) has 2 weeks of worsening exertional dyspnea and orthopnea. He is afebrile and has no chest pain. He has jugular venous distension, an S3 gallop, bibasilar crackles and bilateral pitting leg edema, with dullness and decreased breath sounds at the right base. Chest x-ray shows cardiomegaly and a moderate right pleural effusion, with none on the left. Ultrasound-guided thoracentesis yields straw-colored fluid:
| Test | Pleural fluid | Serum |
|---|---|---|
| Total protein | 1.8 g/dL | 7.0 g/dL |
| LDH | 80 U/L | 200 U/L (upper limit of normal 220 U/L) |
| Glucose | 110 mg/dL | 120 mg/dL |
| pH | 7.46 | not measured |
| Gram stain | No organisms | not applicable |
Which of the following is the most likely mechanism of this effusion?
A. Increased capillary hydrostatic pressure from heart failure
B. Bacterial infection spreading from an adjacent pneumonia
C. Pleural metastases from an occult cancer
D. Pulmonary infarction from an embolus
E. Delayed-type hypersensitivity to Mycobacterium tuberculosis
F. Leakage of pancreatic enzymes in acute pancreatitis
G. Esophageal perforation after forceful vomiting
H. Ascitic fluid crossing small defects in the diaphragm
I. Low plasma oncotic pressure from urinary protein loss
Step 1: run Light's criteria (any one positive = exudate).
- Protein ratio: 1.8 ÷ 7.0 = 0.26 (cutoff 0.5): not met
- LDH ratio: 80 ÷ 200 = 0.40 (cutoff 0.6): not met
- Pleural LDH: 80 U/L vs two-thirds of 220 U/L = 147 U/L: not met
No criterion is met, so this is a transudate. The normal glucose and alkaline pH fit a pleura that is not inflamed.
Answer: A. The low ejection fraction, S3, JVD and edema point to heart failure, the most common cause of pleural effusion (left vs right heart failure). A right-sided effusion does not argue against it (12% of heart failure effusions are right-sided only), but it is why he was tapped: a unilateral effusion, fever, pleuritic pain, no cardiomegaly or no response to diuresis justifies thoracentesis in heart failure (Porcel and Light). About 10% of heart failure effusions resist diuresis and need therapeutic taps or an indwelling pleural catheter (Wijayaratne et al. 2024).
Why every other choice is wrong:
- B. Parapneumonic effusion: an exudate, usually neutrophil-predominant, with fever, cough and consolidation; a complicated one has a low pH and glucose and an LDH often above 900 U/L. Pus means empyema.
- C. Malignant effusion: an exudate, often lymphocytic, sometimes bloody, prone to recur (lung, breast, lymphoma). Cytology is positive in only about half (46% pooled in BTS 2023; about 60% in Porcel and Light). Recurrent ones get an indwelling pleural catheter or talc pleurodesis, by patient choice (BTS 2023); if the lung cannot re-expand, pleurodesis is contraindicated and a catheter is used (Merck).
- D. Pulmonary embolism: an effusion appears in about 40% of patients with pulmonary embolism; it is almost always exudative and often bloody, with dyspnea out of proportion to its size.
- E. Tuberculous pleuritis: a hypersensitivity reaction producing a lymphocyte-predominant exudate with a low-normal glucose and an ADA above 40 U/L, plus fever and weight loss (see primary vs reactivation TB).
- F. Pancreatitis: an exudate with a high pleural fluid amylase, seen in about 35% of acute pancreatitis, in a patient with epigastric pain.
- G. Esophageal rupture: a toxic patient after retching (Boerhaave syndrome); the exudate has a low pH and salivary-type amylase. It is a medical emergency.
- H. Hepatic hydrothorax: the strongest distractor, because it is also a transudate and about 70% are right-sided. Expect ascites and stigmata of cirrhosis, not an S3 and a low ejection fraction. Treat with salt restriction and diuretics, tap for symptoms, avoid chest drains, and consider TIPS or transplant (Wilkins et al. 2024).
- I. Nephrotic syndrome: also a transudate, from low oncotic pressure, with heavy proteinuria, hypoalbuminemia and edema; effusions are usually bilateral and often subpulmonic. Compare nephrotic vs nephritic syndrome.
Pleural fluid clues that name the cause
| Finding | Think |
|---|---|
| pH below 7.2 | Complicated parapneumonic effusion or empyema; also esophageal rupture, rheumatoid effusion, some cancers and TB |
| Glucose below 60 mg/dL | Complicated parapneumonic effusion or empyema, rheumatoid effusion; TB (about 20%), cancer (under 10%) |
| LDH above 900-1,000 U/L | Pleural infection; also about 40% of TB effusions |
| Neutrophils over 50% | Parapneumonic effusion, pulmonary embolism, abdominal disease |
| Lymphocytes over 50% | Cancer, TB, pulmonary embolism, post-CABG; over 90% suggests TB or lymphoma |
| Eosinophils over 10% | Not diagnostic; often air or blood in the pleural space; up to a third unexplained |
| ADA above 40 U/L | TB (90-100% sensitive, 85-95% specific, best in lymphocytic exudates); also empyema |
| Amylase above normal | Pancreatitis; salivary-type amylase in esophageal rupture and some cancers |
| Triglycerides above 110 mg/dL | Chylothorax (chylomicrons confirm it) |
| Cholesterol above 200 mg/dL, cholesterol crystals | Pseudochylothorax: long-standing TB or rheumatoid effusion |
| Hematocrit at least half the blood hematocrit | Hemothorax |
Collect pH correctly: anaerobically, run on a blood gas analyzer. Leftover heparin or local anesthetic in the syringe falsely lowers the pH; delay or air raises it (BTS 2023). Frank pus is not sent for pH: it already means drain.
Parapneumonic effusion and empyema: when to drain
Every parapneumonic effusion gets antibiotics; the question is whether it also needs a drain. The ACCP (2000) risk categories:
| ACCP category | Findings | Risk of poor outcome | Drain? |
|---|---|---|---|
| 1 | Minimal free-flowing effusion (under 10 mm on lateral decubitus), not sampled | Very low | No |
| 2 | Free-flowing, over 10 mm but under half the hemithorax; Gram stain and culture negative; pH 7.20 or higher | Low | No |
| 3 | Any of: half the hemithorax or more, loculations, thickened parietal pleura, positive Gram stain or culture, pH below 7.20 (glucose below 60 mg/dL if no pH) | Moderate | Yes |
| 4 | Pus | High | Yes |
BTS 2023 (pH-led):
- pH 7.2 or lower: high risk; insert a chest drain if ultrasound shows enough accessible fluid.
- pH above 7.2 and below 7.4: intermediate risk; measure LDH and consider a drain if it is above 900 IU/L, especially with ongoing fever, a large effusion, low glucose, CT pleural enhancement or septations.
- pH 7.4 or higher: low risk; no immediate drainage.
- No pH available: a glucose below 3.3 mmol/L (about 60 mg/dL) signals likely infection.
- Low-pH, loculated mimics: rheumatoid effusion, advanced cancer, mesothelioma.
Escalation (BTS 2023; ERS/ESTS 2023):
- Small-bore chest tube (14F or smaller), ideally image-guided, plus antibiotics; early VATS is not preferred as first treatment.
- Drainage stops but a collection remains: intrapleural tPA plus DNase, 10 mg tPA and 5 mg DNase twice daily for 3 days. In MIST2 the combination improved drainage and cut surgical referral (4% vs 16% with placebo); either drug alone did not help.
- Still failing: surgery, with VATS preferred over thoracotomy.
- Avoid single-agent tPA or DNase, and streptokinase, which did not reduce death or surgery in MIST1 (454 patients).
The pneumonia itself: community-acquired pneumonia breakdown.
Thoracentesis: who, how and what to send
- Who: almost every new effusion of uncertain cause at least 10 mm thick on ultrasound, CT or a decubitus film. Symmetric bilateral heart failure effusions without fever or chest pain get diuresis first; tap if they persist 3 days or more (Merck).
- How: ultrasound-guided in all cases, with the needle over the upper edge of the rib to avoid the neurovascular bundle along each rib's lower edge.
- What to send: protein and LDH (with serum values), glucose, cell count and differential, Gram stain and culture (BTS: plain and blood culture bottles); add pH if infection is possible, 25-50 mL for cytology if cancer is suspected, and ADA, amylase or lipids as needed.
- How much: a therapeutic tap usually removes about 1-1.5 L. Some clinicians cap it at 1.5 L in 24 hours; Merck sets no fixed limit but stops for chest tightness, chest pain or severe coughing. Re-expansion pulmonary edema is rare, unpredictable and potentially life threatening.
- Complications: pneumothorax, infection, re-expansion pulmonary edema or hypotension, hemothorax, liver or spleen puncture, vasovagal syncope. No routine chest x-ray is needed afterward if the patient is well.
USMLE traps
| Trap | What is actually true |
|---|---|
| "All three criteria must be met for an exudate" | Any one is enough |
| "Use the patient's serum LDH for the two-thirds rule" | Two-thirds of the laboratory's ULN; the patient's serum LDH belongs only in the ratio |
| "Heart failure on diuretics with an exudate needs a cancer workup" | Check the albumin gradient first (above 1.2 g/dL = transudate) |
| "Bilateral means transudate, unilateral means exudate" | About 1 in 5 heart failure effusions is one-sided; cancer, SLE and pulmonary embolism can be bilateral |
| "A transudate rules out cancer" | 1-10% of malignant effusions are transudates by Light's criteria |
| "Low pH means empyema" | Also esophageal rupture, rheumatoid effusion, cancer, TB; heparin or lidocaine in the syringe lowers it falsely |
| "Wait for frank pus before placing a tube" | pH 7.2 or lower, glucose below 60 mg/dL, positive Gram stain or culture, or loculations already mean drain |
| "Milky fluid is always chylothorax" | Pseudochylothorax has high cholesterol and crystals; about 15% of chylothoraces have triglycerides below 110 mg/dL, and chylomicrons settle it |
Three more practice vignettes
Vignette 1: the diuretic trap. A 74-year-old woman with heart failure with reduced ejection fraction has had 5 days of IV furosemide; her orthopnea is better, but a right effusion persists and is tapped. Pleural fluid: protein 3.5 g/dL, albumin 1.8 g/dL, LDH 120 U/L, glucose 105 mg/dL, lymphocytes 60%. Serum: protein 6.8 g/dL, albumin 3.4 g/dL, LDH 210 U/L (ULN 220 U/L). Which finding best shows that this effusion is a transudate?
A. Pleural fluid glucose of 105 mg/dL. B. A serum-minus-pleural albumin gradient of 1.6 g/dL. C. A pleural fluid-to-serum LDH ratio of 0.57. D. The right-sided location. E. Lymphocyte-predominant fluid.
Answer: B. The protein ratio is 0.51, an exudate by a hair: the classic diuretic pattern. The albumin gradient above 1.2 g/dL reclassifies it as a transudate, and the protein gradient (3.3 g/dL) agrees, so keep treating the heart failure. A: a normal glucose fits most exudates too. C: a negative LDH criterion cannot cancel a positive protein criterion. D: laterality does not decide. E: lymphocytes are nonspecific; BTS lists heart failure itself among causes of lymphocytic effusions.
Vignette 2: the pneumonia that will not settle. A 58-year-old man with right lower lobe pneumonia is still febrile after 3 days of ceftriaxone and azithromycin. Ultrasound shows a moderate right effusion with thin septations. Thoracentesis yields cloudy, non-purulent fluid: pH 7.08, glucose 40 mg/dL, LDH 1,350 U/L, 85% neutrophils, negative Gram stain. What is the most appropriate next step?
A. Small-bore chest tube drainage, continuing antibiotics. B. Broader antibiotics and a repeat tap in 48 hours. C. Intrapleural streptokinase. D. Intrapleural tPA alone. E. Immediate VATS decortication.
Answer: A. A pH below 7.2 and a glucose below 60 mg/dL make this a complicated parapneumonic effusion (ACCP category 3); BTS 2023 advises a small-bore drain. B: antibiotics alone do not clear an infected, acidic pleural space, and delay worsens outcomes (ERS/ESTS 2023). C: streptokinase did not reduce death or surgery (MIST1). D: tPA alone was no better than placebo (MIST2); tPA plus DNase is the step after a drain stops draining. E: surgery is for failure of tube drainage, not first-line.
Vignette 3: the lymphocytic exudate. A 27-year-old man who moved from a country with a high TB burden a year ago has 5 weeks of fever, weight loss and right pleuritic pain. Chest x-ray shows a moderate right effusion and clear lungs. The straw-colored fluid is an exudate with 88% lymphocytes, ADA 85 U/L, a negative AFB smear and negative cytology. His tuberculin skin test is negative. What is the best way to confirm the diagnosis?
A. Repeat the pleural fluid AFB smear. B. Pleural biopsy for histology and mycobacterial culture. C. Accept the negative skin test as excluding TB. D. Serum NT-proBNP. E. Pleural fluid triglycerides.
Answer: B. A lymphocytic exudate with an ADA above 40 U/L makes tuberculous pleuritis most likely, and BTS 2023 strongly recommends tissue sampling for culture and drug sensitivity; biopsy histology plus culture confirms up to 90% (Porcel and Light). A: fluid smears are rarely positive (about 5%), because TB pleuritis is mainly a hypersensitivity reaction. C: about a third of patients have a negative skin test. D: NT-proBNP is for suspected heart failure. E: triglycerides are for milky fluid. More practice on the Pulmonology hub.
Key takeaways
- Light's criteria: exudate if protein ratio above 0.5, LDH ratio above 0.6, or pleural LDH above two-thirds of the laboratory's ULN for serum LDH; any one is enough.
- Transudate = systemic problem (heart failure, cirrhosis, nephrotic syndrome); exudate = pleural or lymphatic problem (pneumonia, cancer, pulmonary embolism, TB).
- Heart failure on diuretics with a borderline exudate: an albumin gradient above 1.2 g/dL or protein gradient above 3.1 g/dL calls it a transudate.
- Drain a parapneumonic effusion for pH 7.2 or lower, glucose below 60 mg/dL, positive Gram stain or culture, loculations or pus: small-bore tube, then tPA plus DNase, then VATS.
- Lymphocytes: TB (ADA above 40 U/L; confirm with pleural biopsy) or cancer (cytology positive in only about half). Triglycerides above 110 mg/dL: chylothorax.
Sources
- BTS Guideline for Pleural Disease (Roberts ME, et al.) — British Thoracic Society/Thorax (2023)
- Pleural Effusion — Merck Manual Professional Edition (2025)
- How To Do Thoracentesis — Merck Manual Professional Edition (2025)
- Esophageal Rupture — Merck Manual Professional Edition (2026)
- Porcel JM, Light RW. Diagnostic Approach to Pleural Effusion in Adults — American Family Physician (2006)
- Shen-Wagner J, et al. Pleural Effusion: Diagnostic Approach in Adults — American Family Physician (2023)
- Pleural Effusion — StatPearls, NCBI Bookshelf (2024)
- Chylothorax — StatPearls, NCBI Bookshelf (2024)
- Maldonado F, et al. Pleural Fluid Characteristics of Chylothorax — Mayo Clinic Proceedings (2009)
- Sundaralingam A, et al. Diagnostics in Pleural Disease — Diagnostics (2020)
- Light RW. The Light Criteria: The Beginning and Why They Are Useful 40 Years Later — Clinics in Chest Medicine (2013)
- Bielsa S, et al. Solving the Light's Criteria Misclassification Rate of Cardiac and Hepatic Transudates — Respirology (2012)
- Wijayaratne T, et al. Cardiac Related Pleural Effusions: A Narrative Review — Journal of Thoracic Disease (2024)
- Wilkins H, et al. Hepatic Hydrothorax — Journal of Thoracic Disease (2024)
- Colice GL, et al. Medical and Surgical Treatment of Parapneumonic Effusions: An Evidence-Based Guideline — Chest (2000)
- Colice GL, Idell S. Counterpoint: Should Fibrinolytics Be Routinely Administered Intrapleurally for Management of a Complicated Parapneumonic Effusion? No — Chest (2014)
- Bedawi EO, et al. ERS/ESTS Statement on the Management of Pleural Infection in Adults — European Respiratory Journal (2023)
- Rahman NM, et al. Intrapleural Use of Tissue Plasminogen Activator and DNase in Pleural Infection — New England Journal of Medicine (2011)
- Maskell NA, et al. U.K. Controlled Trial of Intrapleural Streptokinase for Pleural Infection — New England Journal of Medicine (2005)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
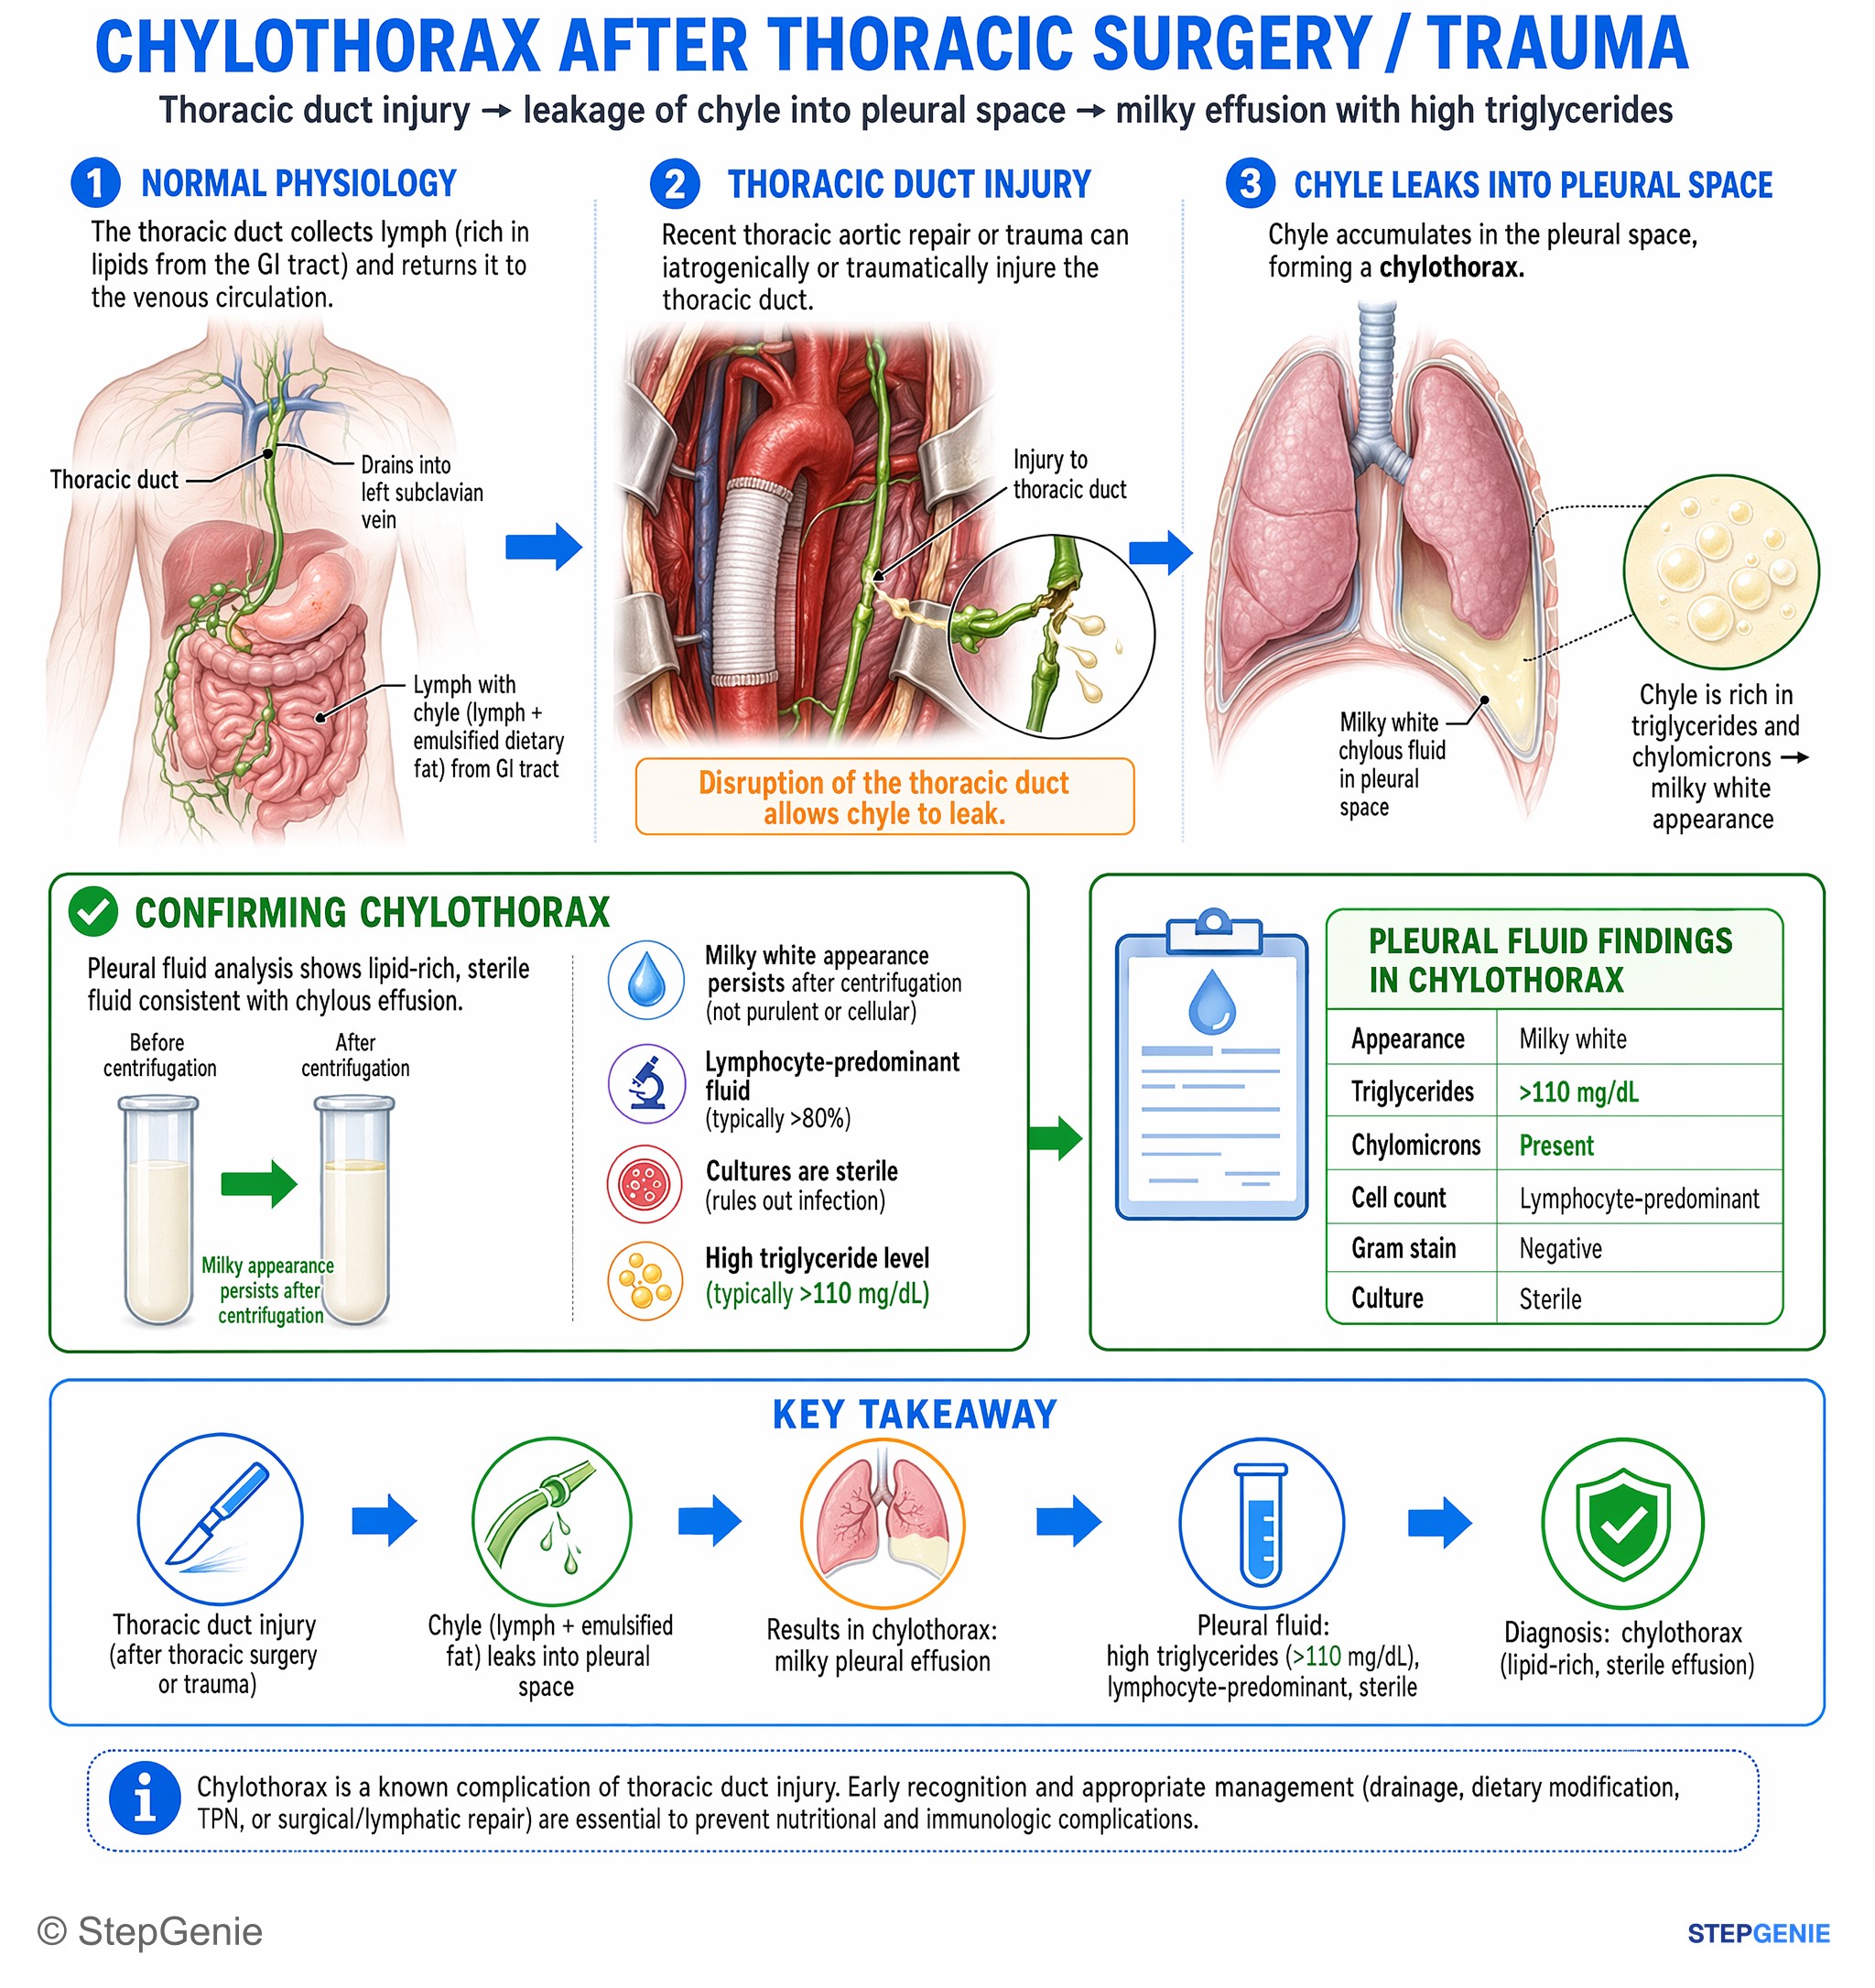
Chylothorax from thoracic duct injury → milky pleural effusion with high triglycerides, lymphocyte-predominant, sterile fluid after…
USMLE Step 1Frequently Asked Questions
What are Light's criteria for pleural effusion?
Light's criteria classify a pleural effusion as an exudate if any one of three findings is present: a pleural fluid-to-serum protein ratio above 0.5, a pleural fluid-to-serum LDH ratio above 0.6, or a pleural fluid LDH above two-thirds of the laboratory's upper limit of normal for serum LDH. If none is present, the effusion is a transudate. The criteria catch nearly all exudates but label about 20 to 25 percent of transudates as exudates.
What is the difference between a transudative and an exudative pleural effusion?
A transudate forms when systemic forces push fluid across a healthy pleura: high hydrostatic pressure in heart failure, low oncotic pressure in nephrotic syndrome or hypoalbuminemia, or ascites crossing the diaphragm in cirrhosis. An exudate forms when the pleura itself is inflamed, infected or infiltrated, or when lymphatic drainage is blocked, as in pneumonia, cancer, tuberculosis and pulmonary embolism. Transudates are managed by treating the underlying condition, while exudates need a search for the specific cause.
What are the most common causes of an exudative pleural effusion?
Parapneumonic effusion from bacterial pneumonia is the most common cause of an exudate. Other common causes are cancer (most often lung cancer, breast cancer or lymphoma), pulmonary embolism, viral infection and tuberculosis. Less common causes include rheumatoid arthritis, lupus, pancreatitis, esophageal rupture, chylothorax, coronary artery bypass surgery, benign asbestos effusion and drugs such as tyrosine kinase inhibitors, amiodarone and nitrofurantoin. Cell counts, glucose, pH, cytology and adenosine deaminase help separate them.
Why can a heart failure pleural effusion look like an exudate?
Diuretics are thought to remove water from the effusion faster than protein, so protein and LDH concentrate, and about 20 percent of heart failure effusions meet Light's exudate criteria after diuresis. When the picture is clearly heart failure but the fluid is only a borderline exudate, calculate a gradient: a serum albumin minus pleural albumin above 1.2 g/dL (more sensitive in a 2012 study) or a serum protein minus pleural protein above 3.1 g/dL favors a transudate.
When does a parapneumonic effusion need a chest tube?
Drainage is needed for frank pus, a positive Gram stain or culture, loculations, an effusion filling at least half the hemithorax, a pleural fluid pH below 7.2, or a glucose below 60 mg/dL when pH is unavailable. The 2023 British Thoracic Society guideline drains at a pH of 7.2 or lower and measures LDH when the pH is between 7.2 and 7.4. A small-bore tube comes first, then intrapleural tPA plus DNase, then VATS surgery.
Which pleural fluid findings point to tuberculosis or cancer?
Both usually cause a lymphocyte-predominant exudate. An adenosine deaminase above 40 U/L in a lymphocytic exudate makes tuberculous pleuritis most likely, but fluid smears are rarely positive, and the 2023 British Thoracic Society guideline prefers pleural tissue for culture. Malignant effusions, most often from lung cancer, breast cancer or lymphoma, may be bloody and tend to recur. Cytology is positive in only about half to 60 percent of cases, so a negative result does not exclude cancer.