Cor pulmonale is right ventricular (RV) hypertrophy, dilation and eventually failure caused by pulmonary hypertension from a lung disorder or chronic hypoxia, not from left heart, congenital or valvular disease; COPD is the most common cause. The mechanism is chronic alveolar hypoxia (plus hypercapnia, loss of capillary bed and polycythemia) driving pulmonary vasoconstriction and arteriolar remodeling, which raises pulmonary vascular resistance (PVR): WHO group 3 pulmonary hypertension, now defined as a mean pulmonary artery pressure (mPAP) >20 mm Hg at rest (2022 ESC/ERS). Look for a loud P2, parasternal heave, tricuspid regurgitation, JVD, hepatomegaly and edema, right axis deviation on ECG and a pressure-loaded RV on echo. Treat the lung disease and the hypoxemia (long-term oxygen), use diuretics cautiously, and don't reach for PAH drugs in COPD.
The vignette
A 66-year-old man with a 50-pack-year smoking history has 6 months of worsening exertional dyspnea, fatigue and leg swelling. He has had a productive cough most days for years. Pulse is 98/min, respirations 22/min, blood pressure 128/76 mm Hg and SpO2 87% on room air. He has a barrel chest, prolonged expiration and scattered wheezes without crackles. The jugular venous pressure is elevated with prominent v waves. There is a left parasternal heave, a loud P2 and a holosystolic murmur at the left lower sternal border. The liver is enlarged, and there is pitting edema to the mid-shins. Arterial blood gas on room air: PaO2 52 mm Hg, PaCO2 50 mm Hg. Hematocrit is 56%. Post-bronchodilator FEV1/FVC is 0.48. ECG shows right axis deviation, R > S in V1 and peaked P waves in lead II. Echocardiography shows a dilated, hypertrophied right ventricle, a flattened interventricular septum, peak tricuspid regurgitation velocity 3.6 m/s, left ventricular ejection fraction 60% and no intracardiac shunt. Which mechanism best explains his right heart findings?
A. Alveolar hypoxia causing pulmonary arteriolar vasoconstriction and remodeling B. Left ventricular dysfunction raising pulmonary venous pressure C. Organized thromboemboli obstructing the pulmonary arteries D. A germline BMPR2 mutation causing pulmonary arterial smooth-muscle proliferation E. Reversal of a long-standing left-to-right intracardiac shunt F. Acute massive pulmonary embolism
Answer: A, hypoxic vasoconstriction and remodeling
This is cor pulmonale from COPD. He has an obstructive pattern (FEV1/FVC 0.48; see the FEV1/FVC cheat sheet), chronic hypoxemia and hypercapnia, secondary polycythemia, signs of pulmonary hypertension (loud P2, parasternal heave, a fast tricuspid jet) and right heart failure (JVD with v waves, hepatomegaly, edema), all with a normal left ventricle. Chronic alveolar hypoxia constricts the pulmonary arterioles; over years their muscular walls thicken and remodel, so PVR stays high and the RV hypertrophies against the load, then dilates and fails. Treating early matters, before these structural changes become irreversible.
Why every other answer is wrong
- B. Left ventricular dysfunction: this is group 2 pulmonary hypertension, and left heart failure is the most common cause of right heart failure overall. But cor pulmonale by definition excludes RV failure from left heart disease, his ejection fraction is 60% and there are no crackles. Group 2 is post-capillary, with a pulmonary artery wedge pressure (PAWP) >15 mm Hg. Compare the patterns in left vs right heart failure.
- C. Organized thromboemboli: chronic thromboembolic pulmonary hypertension (CTEPH, group 4) follows unresolved emboli. It matters because it is potentially curable (pulmonary endarterectomy), so unexplained pulmonary hypertension gets a V/Q scan. Here there is a clear lung cause and no history of PE.
- D. BMPR2 mutation: heritable pulmonary arterial hypertension (PAH, group 1); BMPR2 is the most common heritable cause. PAH is diagnosed only after left heart, lung and thromboembolic causes are excluded, and it doesn't fit a heavy smoker with airflow obstruction and hypercapnia.
- E. Reversed left-to-right shunt: Eisenmenger physiology is PAH associated with congenital heart disease (group 1), with cyanosis once the shunt reverses (see the Eisenmenger syndrome question). Congenital heart disease is excluded from the definition of cor pulmonale, and his echo shows no shunt.
- F. Acute massive PE: the classic cause of acute cor pulmonale: sudden dyspnea, hypotension and an acutely dilated RV. His 6-month course, RV hypertrophy and polycythemia point to a chronic process, because hypertrophy reflects long-standing pressure overload (PE review: PE memory palace).
What counts as cor pulmonale
Merck defines it as RV enlargement and eventual failure secondary to a lung disorder that causes pulmonary hypertension, explicitly excluding RV enlargement from LV failure, congenital heart disease or acquired valve disease. It accounts for an estimated 6-7% of adult heart disease in the US (StatPearls).
| Timing | Causes |
|---|---|
| Acute | Massive pulmonary embolism; ventilator-induced lung injury in ARDS |
| Chronic: airways and parenchyma | COPD (most common), interstitial lung disease and pulmonary fibrosis, cystic fibrosis, loss of lung tissue after surgery or trauma |
| Chronic: ventilation | Obesity hypoventilation, obstructive sleep apnea, kyphoscoliosis, neuromuscular respiratory disease |
| Chronic: vessels | Chronic unresolved pulmonary emboli, pulmonary veno-occlusive disease, systemic sclerosis |
Pathophysiology: from hypoxic lung to failing right ventricle
- Hypoxic pulmonary vasoconstriction. Locally it diverts blood away from poorly ventilated alveoli to keep V/Q matched (see dead space vs shunt). When hypoxia is chronic and global, the whole pulmonary bed constricts; hypercapnia adds to it.
- Remodeling. Chronic vasoconstriction drives smooth-muscle proliferation and medial hypertrophy in small pulmonary arteries, with changes in nitric oxide, endothelin-1 and growth factors.
- Lost capillary bed. Emphysema destroys alveolar walls and the capillaries in them.
- Polycythemia. Hypoxia raises the hematocrit, and the thicker blood adds resistance.
- The RV gives way. Pressure overload → RV hypertrophy → dilation → tricuspid regurgitation → high right atrial pressure → systemic venous congestion (JVD, hepatomegaly, ascites, edema).
The hemodynamic anchor is . In cor pulmonale, PVR is high and PAWP is normal (pre-capillary pulmonary hypertension).
Pulmonary hypertension: the 2022 definition and the five groups
| Profile | mPAP | PAWP | PVR |
|---|---|---|---|
| Pulmonary hypertension | >20 mm Hg at rest | ||
| Pre-capillary (expected in cor pulmonale) | >20 mm Hg | ≤15 mm Hg | >2 Wood units |
| Isolated post-capillary (left heart disease) | >20 mm Hg | >15 mm Hg | ≤2 Wood units |
| Combined pre- and post-capillary | >20 mm Hg | >15 mm Hg | >2 Wood units |
Exam lore vs current definition: older sources and many question banks use the previous definition, mPAP ≥25 mm Hg (StatPearls' 2023 cor pulmonale chapter still describes catheterization showing an mPAP "above 25 mmHg"). The 2022 ESC/ERS guideline lowered it to >20 mm Hg. Right heart catheterization is the gold standard; on echo, a peak tricuspid regurgitation velocity >2.8 m/s may suggest pulmonary hypertension but can't confirm or exclude it.
| Group | Name | Examples |
|---|---|---|
| 1 | Pulmonary arterial hypertension | Idiopathic, heritable (BMPR2), drugs and toxins, connective tissue disease, HIV, portal hypertension, congenital heart disease, schistosomiasis |
| 2 | Left heart disease | Systolic or diastolic LV dysfunction, valve disease; the most common cause of pulmonary hypertension |
| 3 | Lung disease and/or hypoxia | COPD/emphysema, interstitial lung disease, mixed obstructive-restrictive disease, hypoventilation syndromes, hypoxia without lung disease (high altitude), developmental lung disorders |
| 4 | Pulmonary artery obstruction | CTEPH, other obstructions |
| 5 | Unclear or multifactorial | Hemolytic anemias including sickle cell disease, myeloproliferative disorders, sarcoidosis, chronic kidney disease |
Lung disease, especially COPD, is the second most common cause of pulmonary hypertension after left heart disease (ESC/ERS).
Exam, ECG, x-ray and echo findings
| Test | What to look for |
|---|---|
| Symptoms | Exertional dyspnea and fatigue (almost all patients with pulmonary hypertension), exertional chest discomfort, light-headedness or syncope, leg swelling, a sense of fullness in the abdomen or neck |
| Exam | Loud P2, left parasternal heave, holosystolic tricuspid regurgitation murmur, right-sided S3 or S4, JVD with prominent v waves, enlarged (sometimes pulsatile) liver, ascites, pitting edema |
| ECG | Right axis deviation, R > S in V1, RV hypertrophy, peaked P waves in lead II (P pulmonale, from right atrial enlargement); S1Q3T3 can appear (ECG basics: how to read an ECG) |
| Chest x-ray | Enlarged hilar pulmonary arteries that prune quickly toward the periphery; the RV filling the anterior (retrosternal) airspace on the lateral view; hyperinflation if COPD |
| Echo | Dilated, hypertrophied RV; flattened septum with paradoxical motion; TAPSE <1.6 cm and pericardial effusion signal RV systolic dysfunction and a worse prognosis; often limited by hyperinflated lungs |
| Labs | BNP or NT-proBNP (supports the diagnosis and tracks response), polycythemia, hypoxemia with or without hypercapnia |
| Confirmation | Right heart catheterization: mPAP >20 mm Hg, PAWP ≤15 mm Hg, PVR >2 Wood units |
Treatment: fix the lung and the oxygen first
- Treat the underlying disease. For group 3, management of the lung disorder is the primary treatment.
- Oxygen. It relieves hypoxic vasoconstriction and improves cardiac output. GOLD 2026: long-term oxygen may improve survival in severe resting chronic hypoxemia: PaO2 ≤55 mm Hg, or <60 mm Hg if there is cor pulmonale or secondary polycythemia; it is not prescribed routinely for moderate desaturation. The patient in the vignette (PaO2 52 mm Hg, hematocrit 56%) qualifies.
- Diuretics, cautiously. Loop diuretics relieve edema, but the failing RV depends on preload, and small decreases in preload can cause hypotension (Merck).
- Digoxin. Only a modest effect on the failing RV, and the evidence is weak without LV dysfunction; not a first-line answer.
- Pulmonary vasodilators. Not typically indicated for cor pulmonale from chronic lung disease, and there is no conclusive evidence for them in COPD. In pulmonary hypertension due to interstitial lung disease (PH-ILD), endothelin receptor antagonists and riociguat are generally contraindicated because of more adverse events; the exception is inhaled treprostinil, which improves exercise capacity and is FDA-approved for PH-ILD (WHO group 3).
- By group, for contrast: group 1 gets PAH therapy (calcium channel blockers only if vasoreactive); group 2, treatment of the left heart disease; group 4, pulmonary endarterectomy if operable, or balloon angioplasty or riociguat if not.
How USMLE tests it
| Stem clue | Think | Key next fact |
|---|---|---|
| Heavy smoker, FEV1/FVC <0.7, hypoxemia, edema, loud P2, normal LV | Cor pulmonale (group 3) | Treat COPD; oxygen if PaO2 ≤55 mm Hg (or <60 with cor pulmonale) |
| Obesity, daytime sleepiness, hypercapnia, RV failure | Hypoventilation syndrome (group 3) | Polysomnography |
| Sudden dyspnea and hypotension after surgery or immobility, dilated RV | Acute cor pulmonale from massive PE | Treat the PE |
| Persistent dyspnea months after a PE | CTEPH (group 4) | V/Q scan; endarterectomy |
| Young adult, normal lungs and LV, exertional syncope, loud P2 | PAH (group 1) | Right heart catheterization with vasoreactivity testing |
| Orthopnea, crackles, low ejection fraction, PAWP >15 | Group 2 | Treat the left heart failure |
| Known VSD, new cyanosis and clubbing | Eisenmenger (group 1) | Shunt reversal |
Key takeaways
- Cor pulmonale = RV hypertrophy, dilation and failure from pulmonary hypertension due to lung disease or hypoxia, never from left heart, congenital or valve disease.
- COPD is the most common cause; acute cor pulmonale is classically massive PE.
- Mechanism: chronic hypoxic vasoconstriction + arteriolar remodeling (plus capillary loss and polycythemia) → ↑ PVR with normal PAWP.
- Pulmonary hypertension = mPAP >20 mm Hg at rest (2022 ESC/ERS; older sources say ≥25); pre-capillary adds PAWP ≤15 mm Hg and PVR >2 Wood units. Confirm with right heart catheterization.
- Clues: loud P2, parasternal heave, TR murmur, JVD with v waves, hepatomegaly, edema; ECG right axis deviation, R > S in V1, peaked P in lead II.
- Treat the lung and the hypoxemia (long-term oxygen for PaO2 ≤55 mm Hg, or <60 mm Hg with cor pulmonale), diurese gently, and avoid PAH drugs in COPD.
Sources
- Right Heart Failure and Cor Pulmonale — Merck Manual Professional Edition (2025)
- Cor Pulmonale — StatPearls, NCBI Bookshelf (2023)
- Pulmonary Hypertension — Merck Manual Professional Edition (2025)
- 2022 ESC/ERS Guidelines for the diagnosis and treatment of pulmonary hypertension — European Respiratory Journal (2023)
- Chronic Obstructive Pulmonary Disease (COPD) — Merck Manual Professional Edition (2026)
- Pocket Guide to COPD Diagnosis, Management and Prevention: 2026 Report — Global Initiative for Chronic Obstructive Lung Disease (2025)
- 2026 GOLD Report — Global Initiative for Chronic Obstructive Lung Disease (2025)
- Tyvaso (treprostinil) inhalation solution label — DailyMed, US National Library of Medicine (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
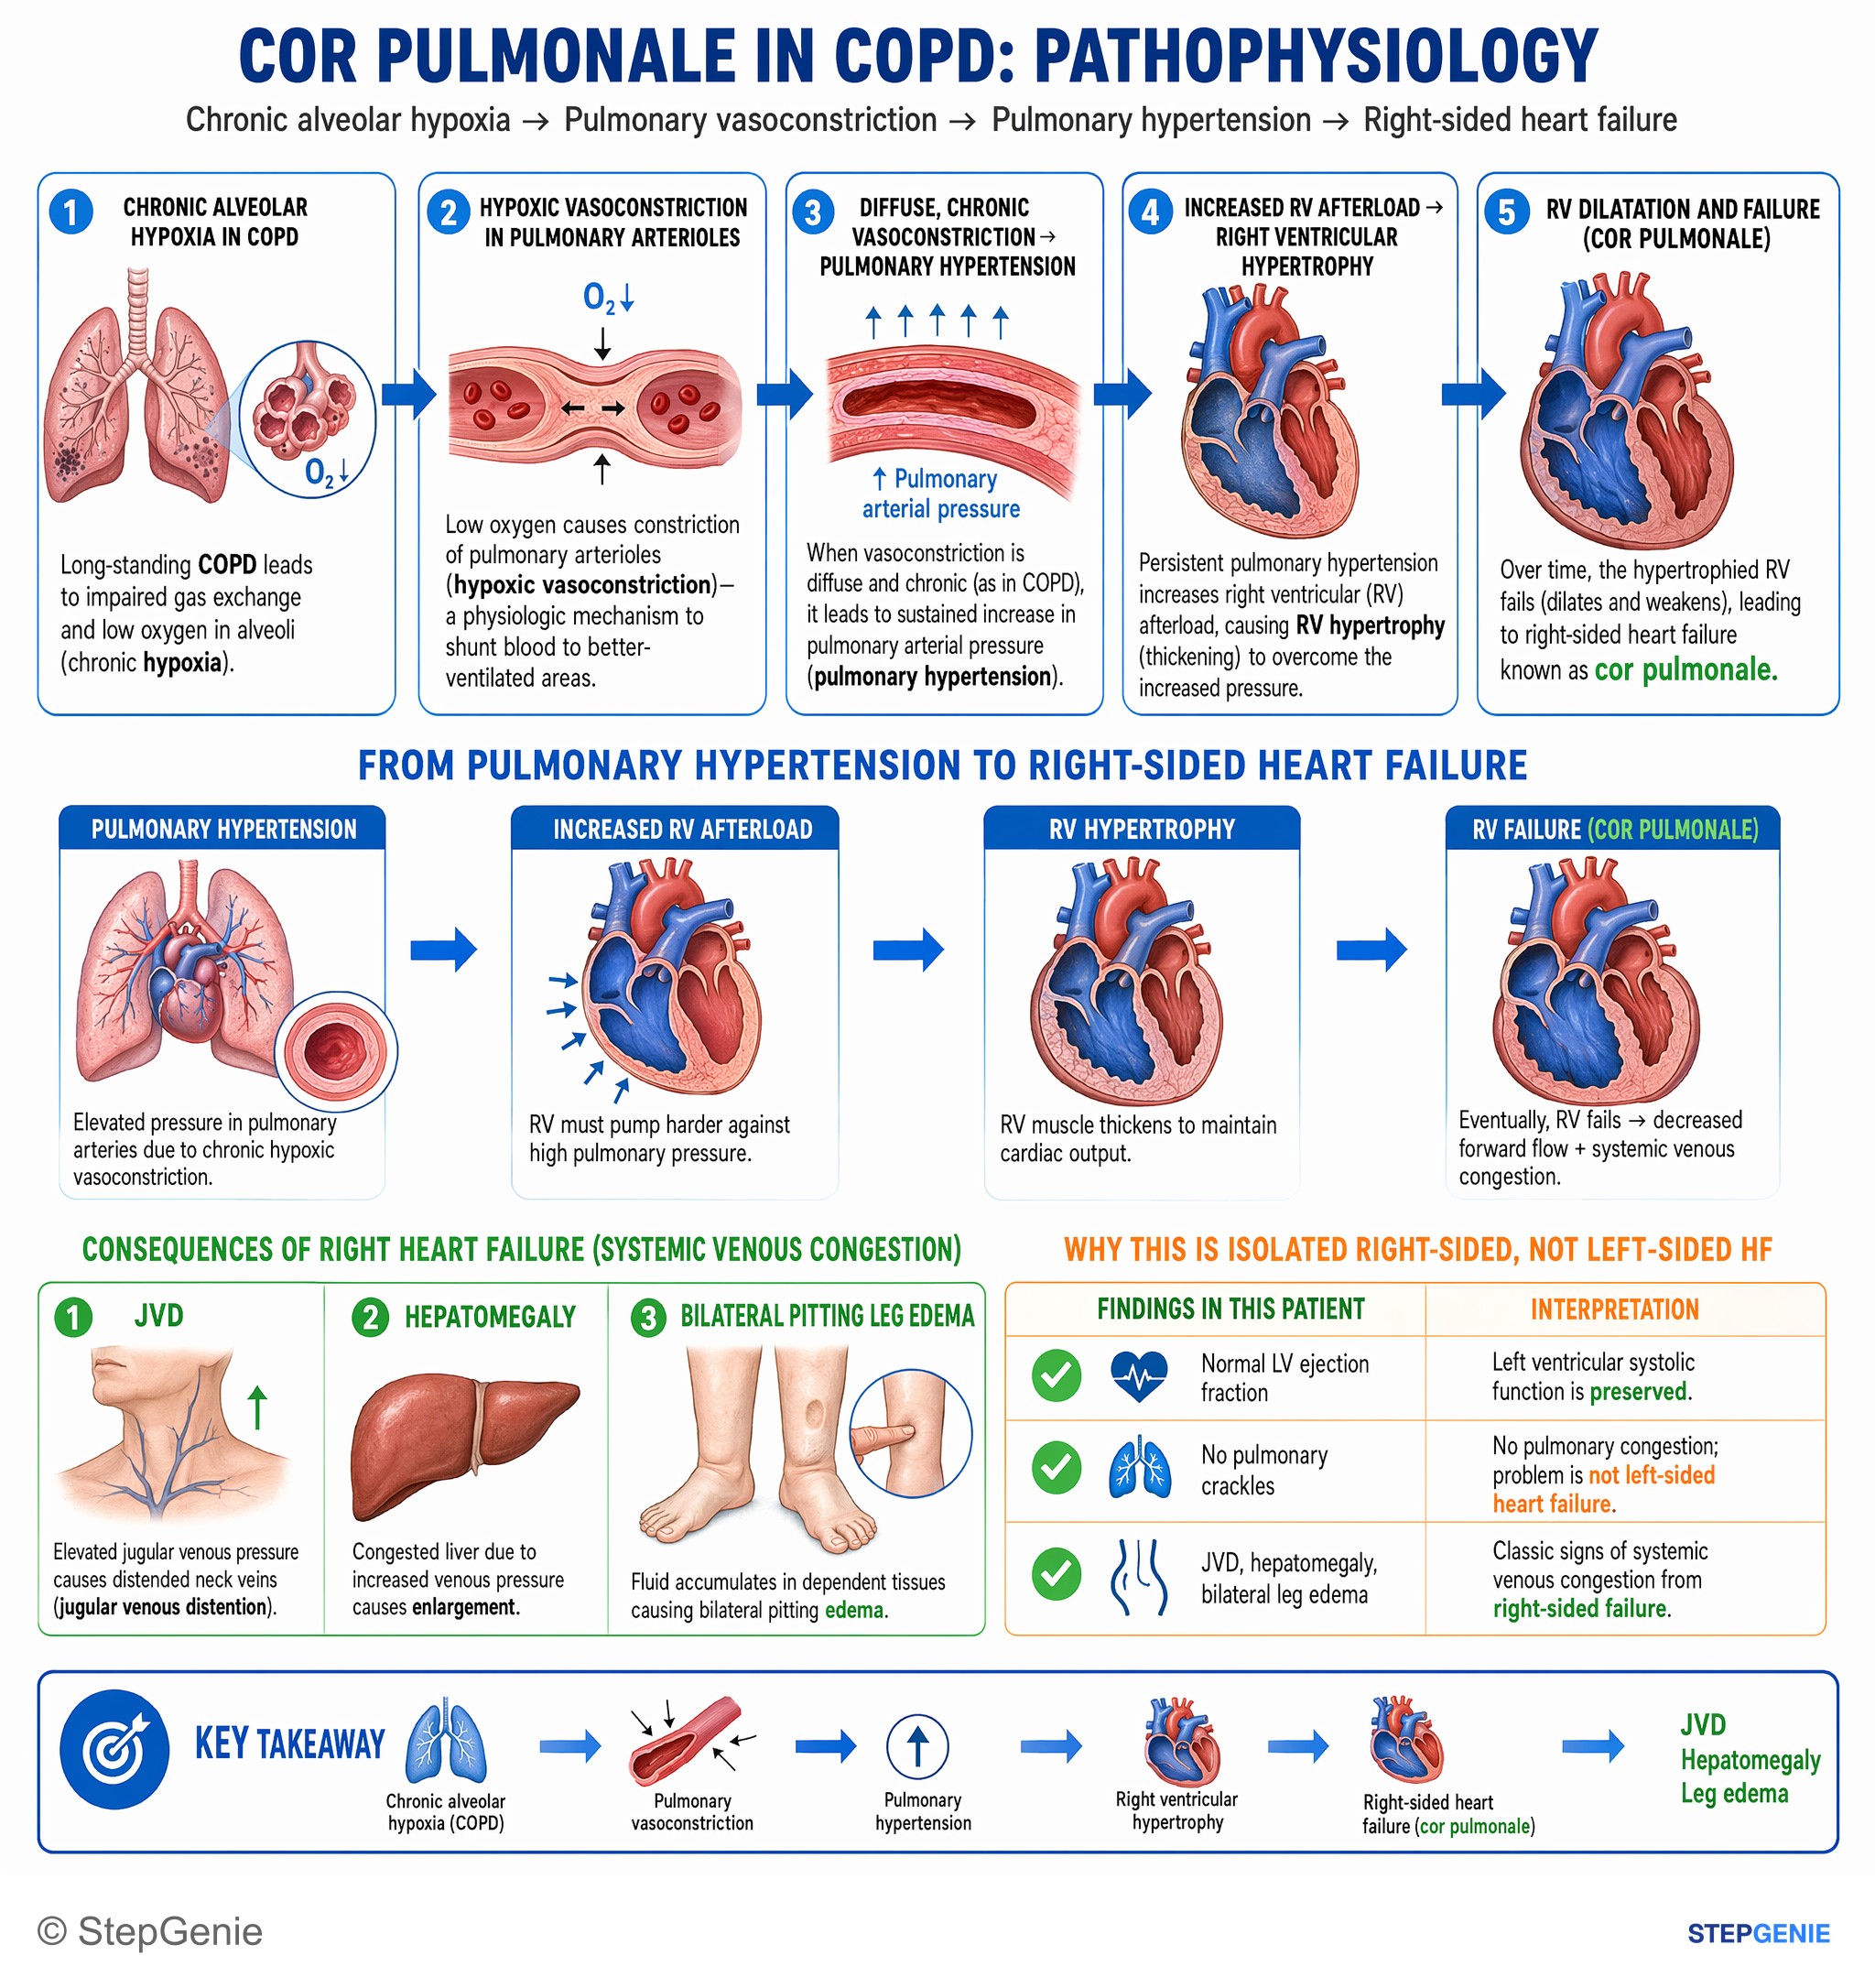
Cor pulmonale from COPD: chronic alveolar hypoxia → pulmonary vasoconstriction → pulmonary hypertension → right-sided heart failure with…
USMLE Step 1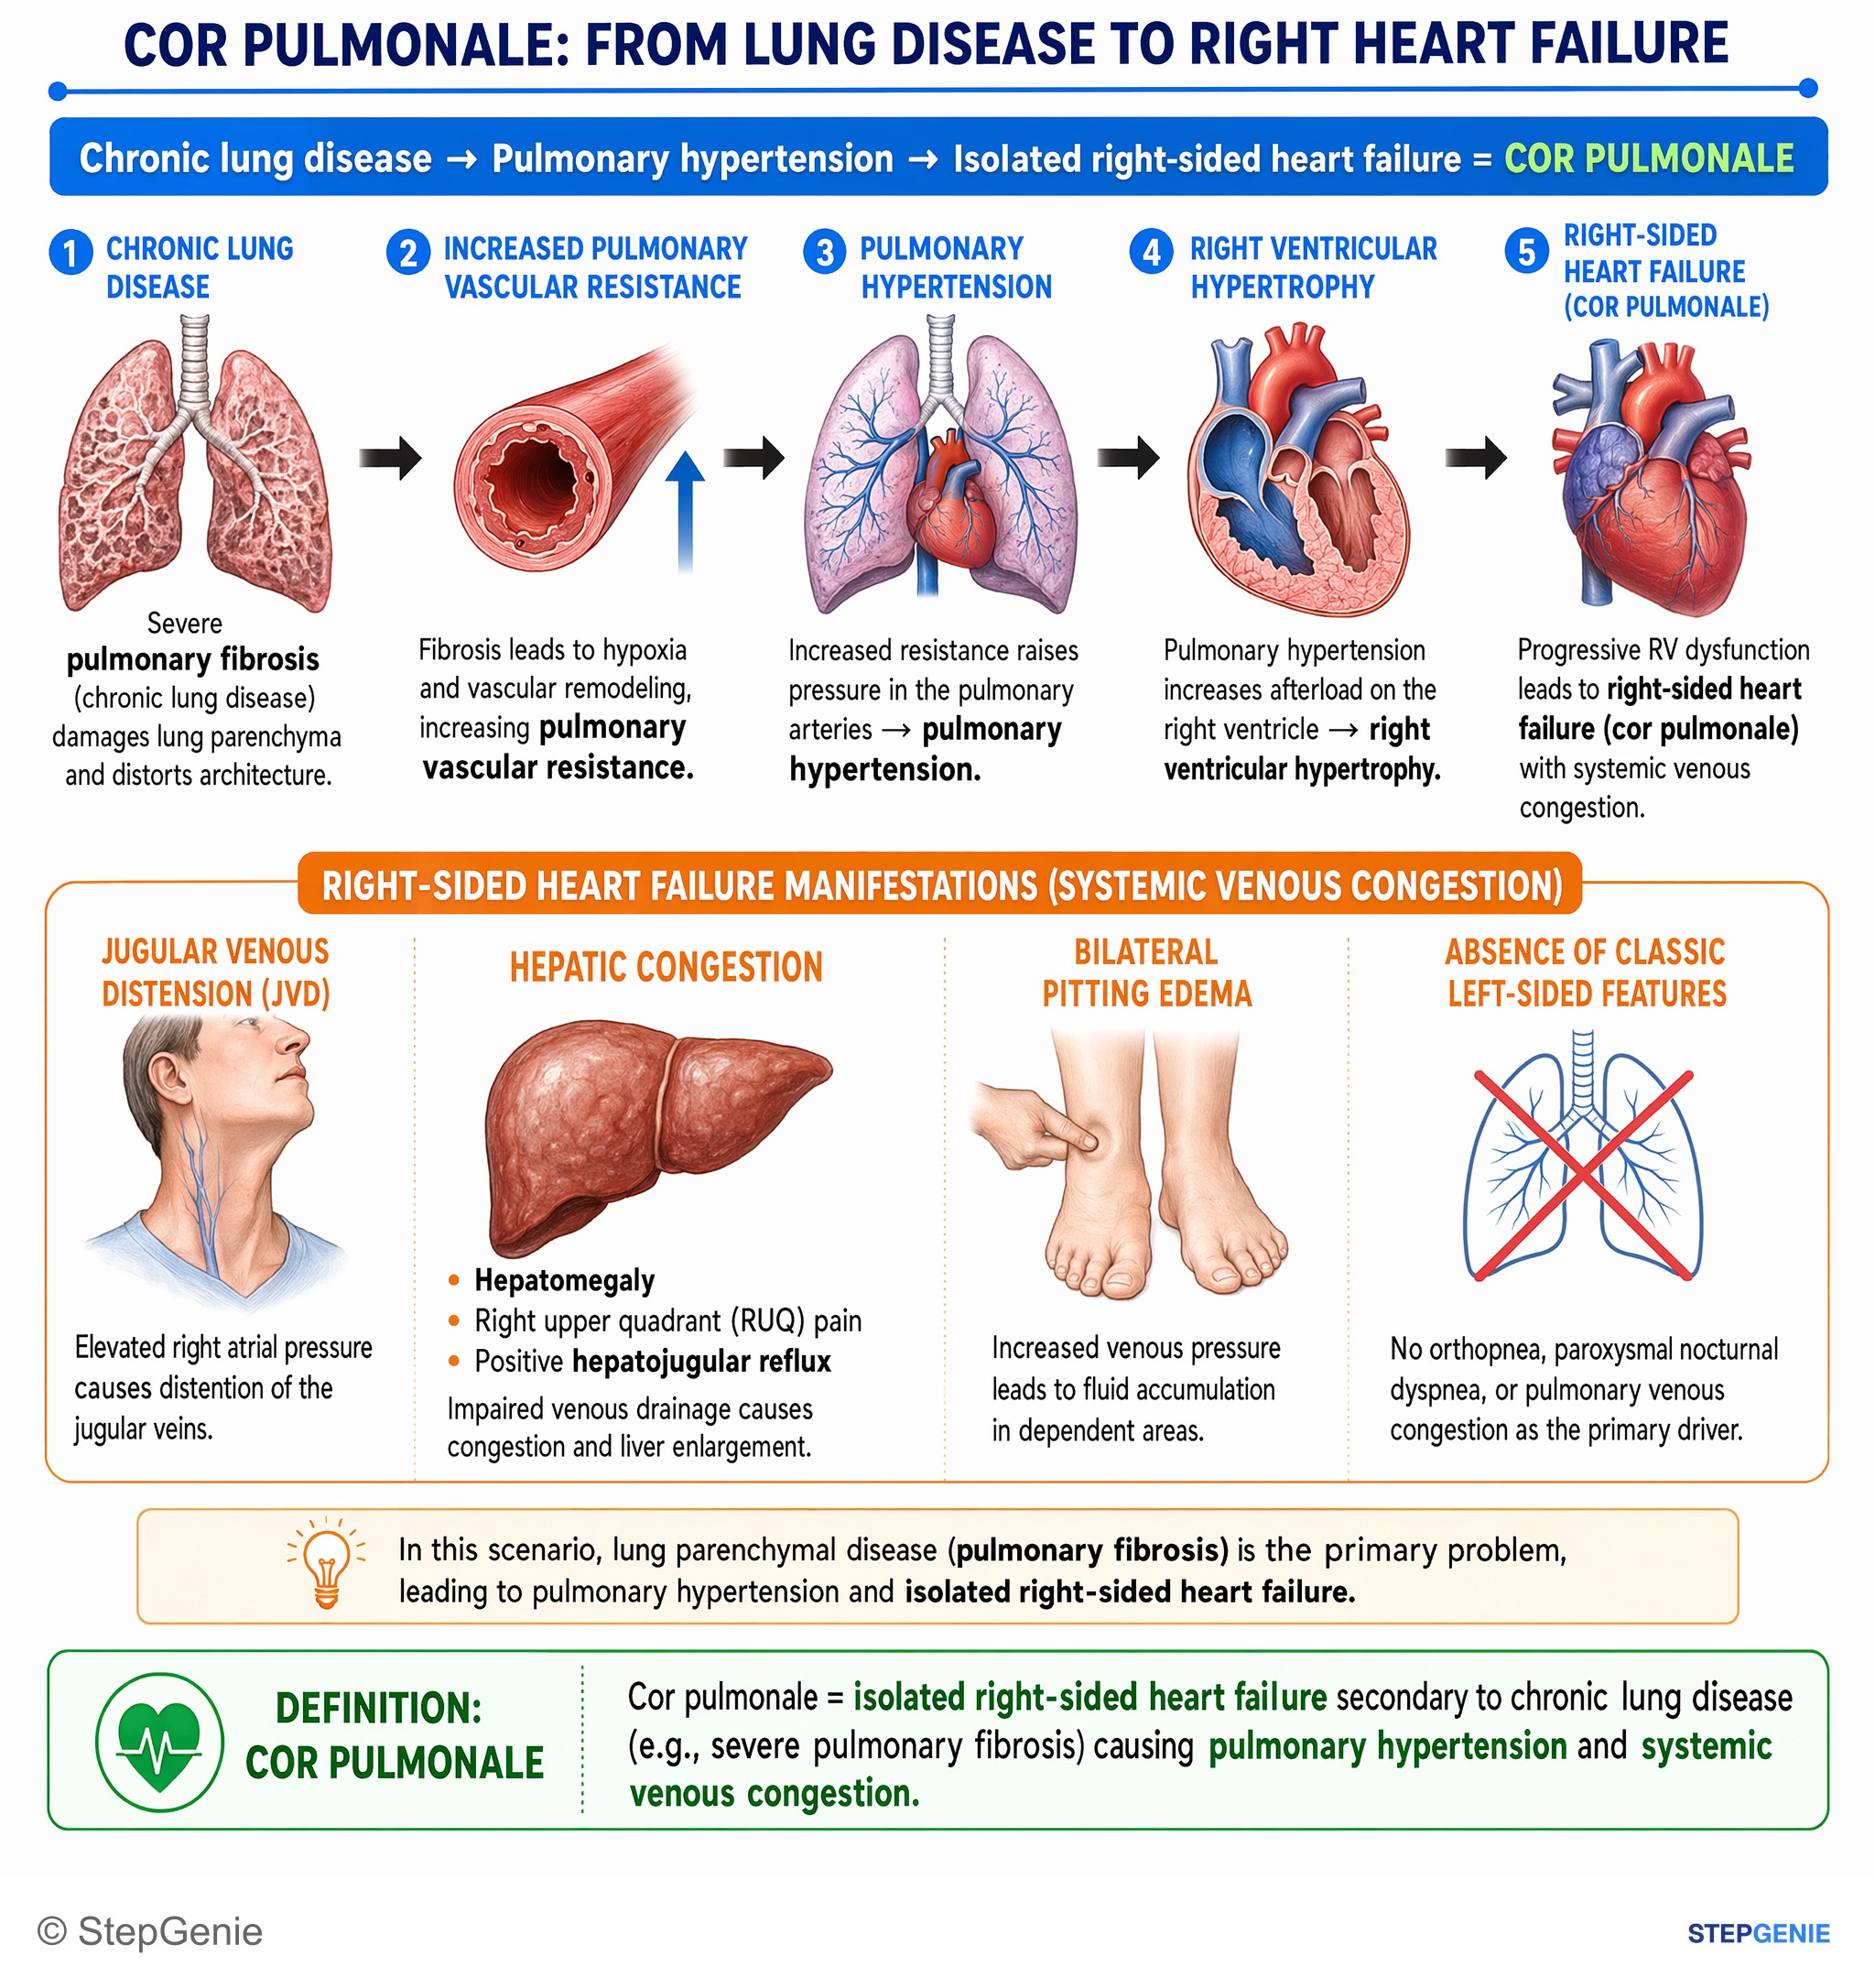
Cor pulmonale = isolated right-sided heart failure secondary to chronic lung disease (e.g., severe pulmonary fibrosis) causing pulmonary…
USMLE Step 2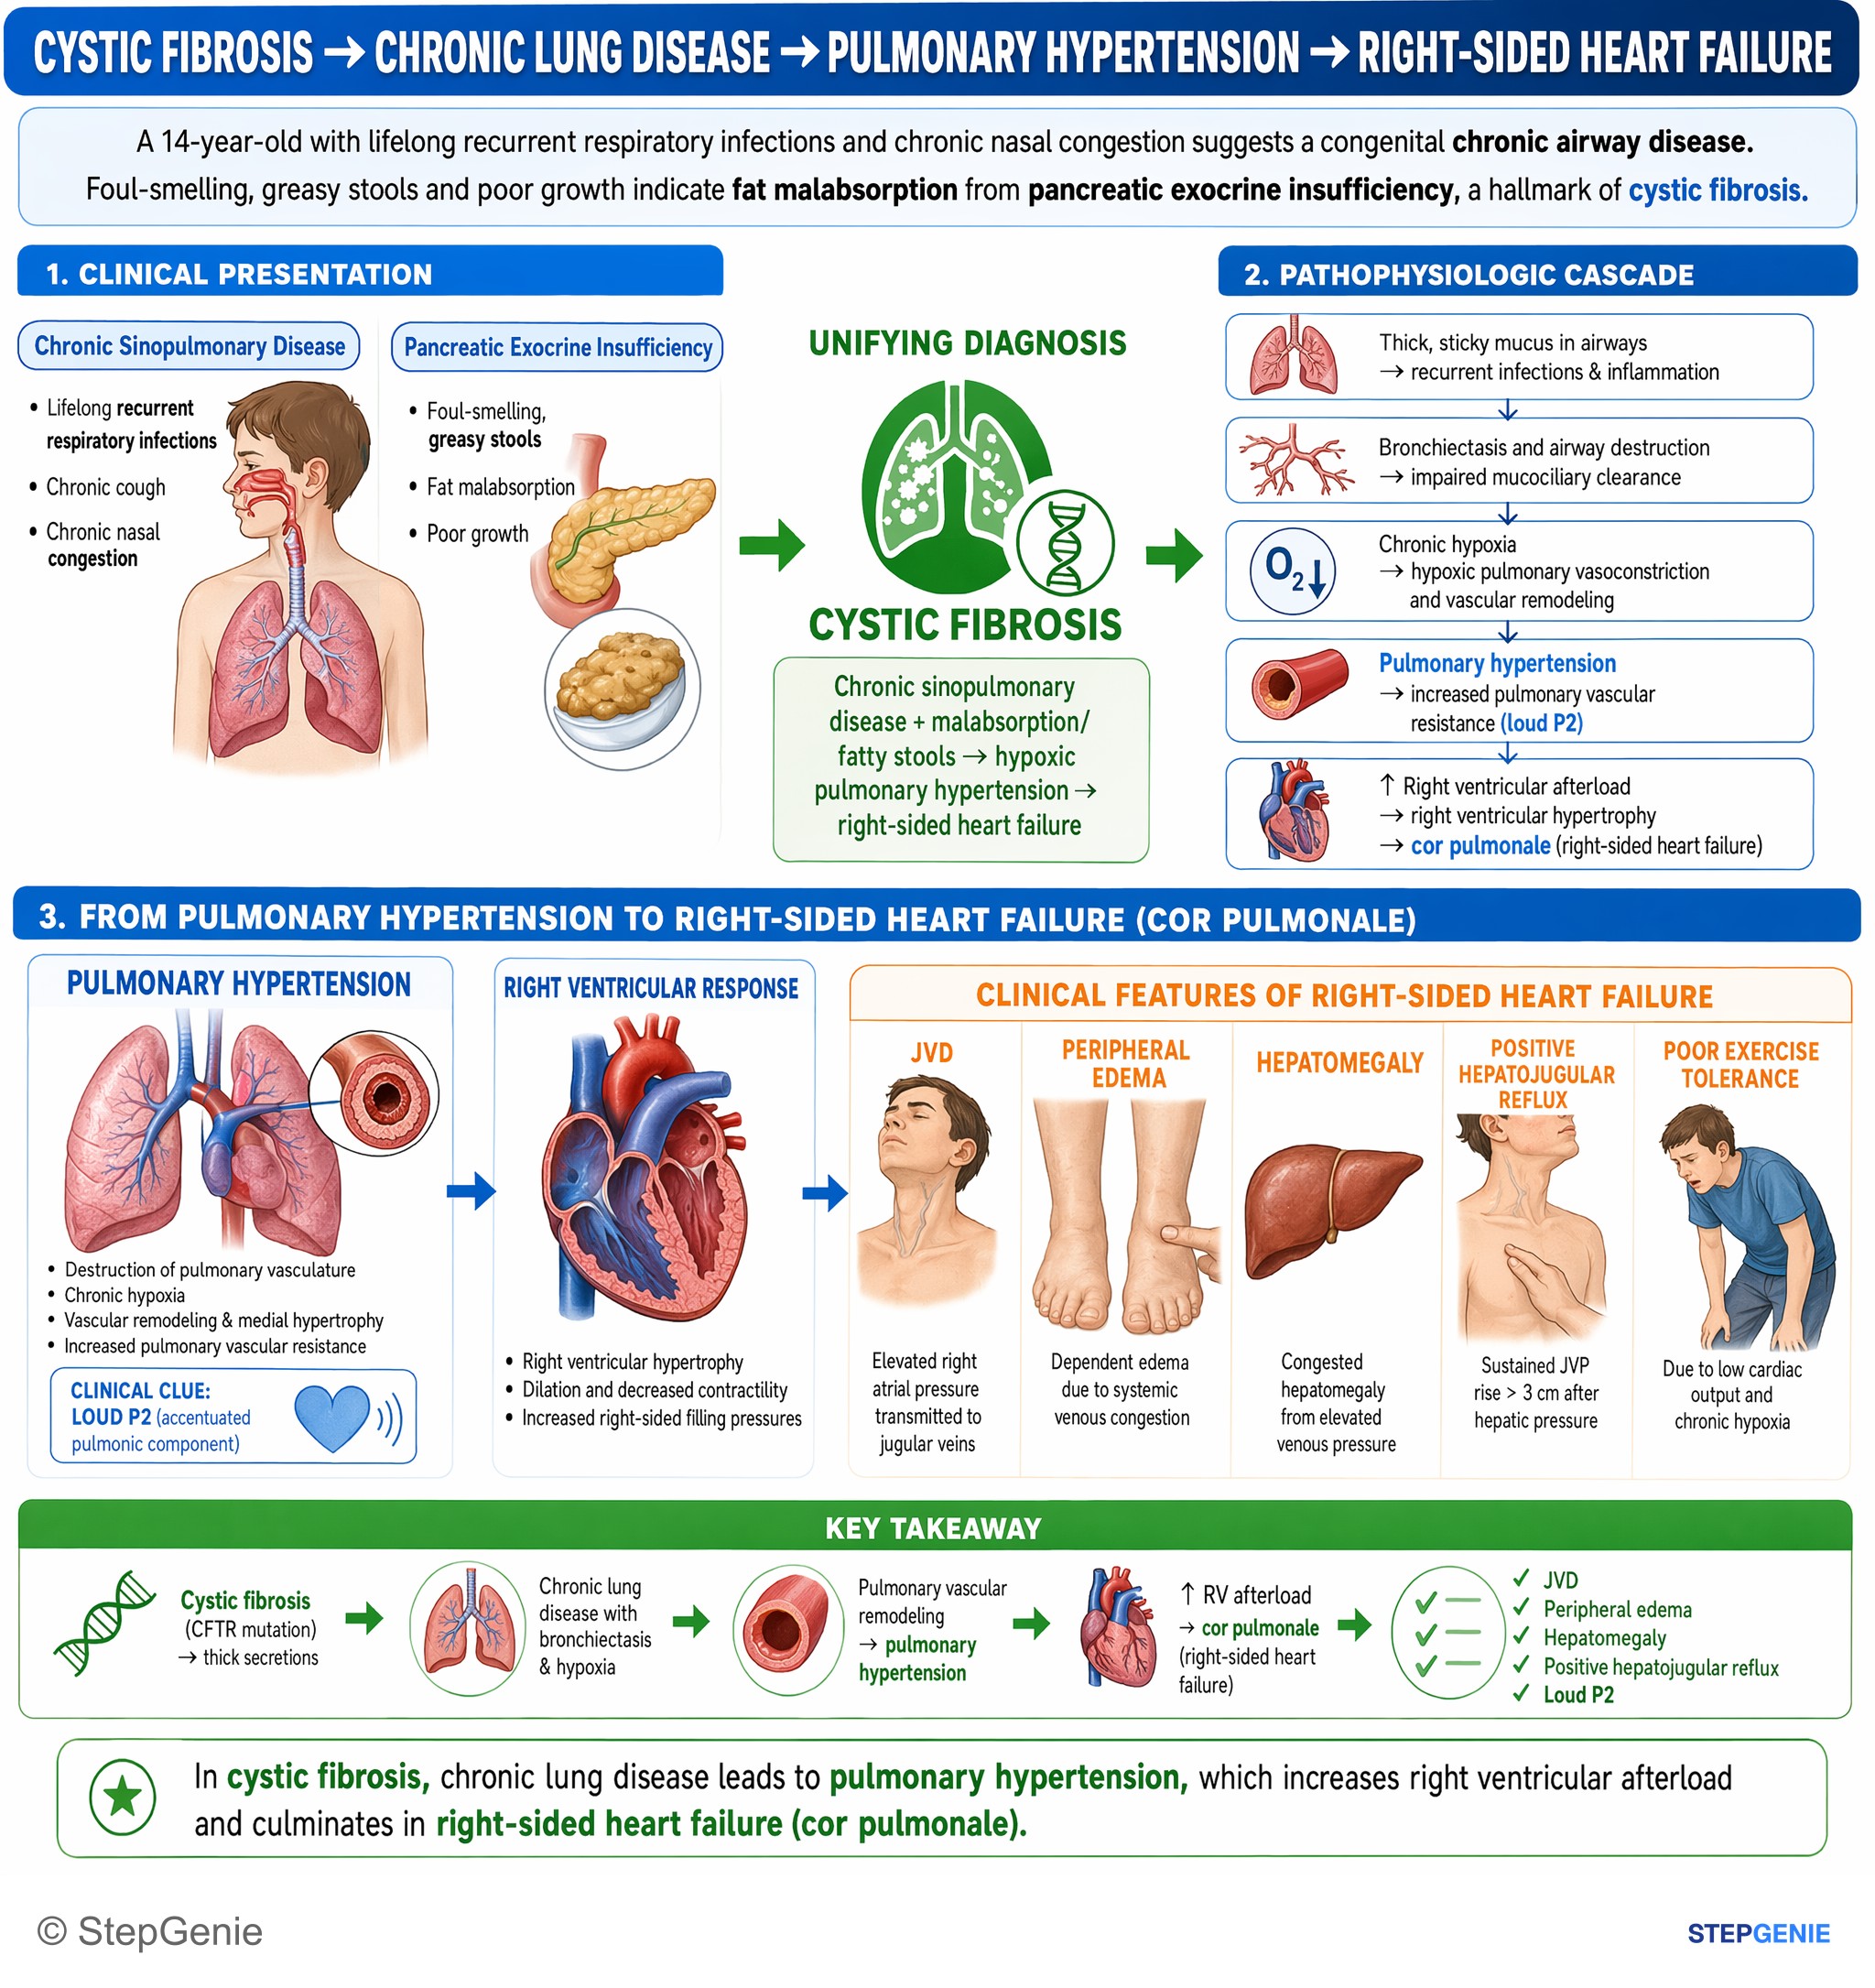
Cystic fibrosis → chronic sinopulmonary disease + malabsorption/fatty stools → hypoxic pulmonary hypertension → right-sided heart failure…
USMLE Step 2Frequently Asked Questions
What is cor pulmonale?
Cor pulmonale is enlargement of the right ventricle, by hypertrophy and dilation, and eventually right heart failure, caused by pulmonary hypertension that results from a lung disorder or chronic hypoxia. By definition it excludes right ventricular failure caused by left heart failure, congenital heart disease or acquired valve disease. Chronic cor pulmonale is most often due to COPD; acute cor pulmonale is classically caused by a massive pulmonary embolism.
How does COPD cause cor pulmonale?
Chronic alveolar hypoxia in COPD triggers hypoxic pulmonary vasoconstriction throughout the lungs, and hypercapnia adds to it. Over time the small pulmonary arteries remodel, with smooth-muscle proliferation and medial hypertrophy. Emphysema also destroys capillary bed, and hypoxia-driven polycythemia thickens the blood. Together these raise pulmonary vascular resistance, so the right ventricle hypertrophies against the higher pressure, then dilates and fails, producing JVD, hepatomegaly and edema.
What are the ECG findings in cor pulmonale?
The ECG shows signs of right ventricular hypertrophy and right atrial enlargement: right axis deviation, a dominant R wave with R greater than S in lead V1, and peaked P waves in lead II, called P pulmonale. An S1Q3T3 pattern can also appear. Echocardiography, which can be limited by hyperinflated lungs, shows right ventricular strain and suggests pulmonary hypertension; right heart catheterization is needed to confirm it.
What is the current definition of pulmonary hypertension?
The 2022 ESC/ERS guidelines define pulmonary hypertension as a mean pulmonary artery pressure above 20 mm Hg at rest, measured by right heart catheterization. Pre-capillary pulmonary hypertension, the pattern seen in cor pulmonale, also requires a pulmonary artery wedge pressure of 15 mm Hg or less and a pulmonary vascular resistance above 2 Wood units. Older sources and many question banks still use the previous threshold of 25 mm Hg or more.
What is WHO group 3 pulmonary hypertension?
Group 3 is pulmonary hypertension associated with lung disease and/or hypoxia. It includes COPD and emphysema, interstitial lung disease, mixed obstructive and restrictive disease, hypoventilation syndromes, hypoxia without lung disease such as living at high altitude, and developmental lung disorders. It is the group behind most chronic cor pulmonale. Treatment focuses on the lung disease and oxygen; pulmonary vasodilators lack conclusive evidence in COPD, and inhaled treprostinil is FDA-approved for pulmonary hypertension due to interstitial lung disease.
How is cor pulmonale treated?
Treatment targets the cause: optimize the underlying lung disease and correct hypoxemia. In COPD, long-term oxygen may improve survival when resting PaO2 is 55 mm Hg or lower, or below 60 mm Hg with cor pulmonale or secondary polycythemia. Loop diuretics relieve edema but must be used cautiously because the failing right ventricle depends on preload. Digoxin has only a modest effect, and pulmonary vasodilators are not typically indicated in COPD-related cor pulmonale.