Chest tubes are one of those “sounds straightforward” interventions that become tricky the moment you’re staring at five answer choices that are all plausible. On USMLE-style questions, the real test isn’t “have you heard of a chest tube?”—it’s whether you can match the pathology + stability + imaging to the right pleural intervention (or no tube at all).
Tag: Pulmonary > Pulmonary Vascular & Critical Care
The Vignette (Q-bank style)
A 27-year-old man is brought to the ED after a motorcycle crash. He is anxious and dyspneic. Vitals: T 36.8°C, HR 132/min, BP 84/52 mm Hg, RR 32/min, SpO₂ 86% on nonrebreather. Exam shows tracheal deviation to the left, distended neck veins, and absent breath sounds on the right with hyperresonance to percussion.
Which of the following is the most appropriate next step?
A. Obtain a portable chest x-ray
B. Needle decompression followed by chest tube placement
C. Noninvasive positive-pressure ventilation (BiPAP)
D. IV furosemide
E. Therapeutic thoracentesis
The Correct Answer: B. Needle decompression followed by chest tube placement
This is classic tension pneumothorax: obstructive shock physiology (hypotension, tachycardia), unilateral absent breath sounds + hyperresonance, JVD, and mediastinal shift (tracheal deviation away from affected side).
Why this is correct
- Unstable patient + suspected tension pneumothorax = treat immediately.
- Don’t wait for imaging. The diagnosis is clinical.
- Needle decompression is the immediate temporizing maneuver.
- Then place a tube thoracostomy (chest tube) for definitive management.
Where to decompress (high-yield)
Two commonly tested acceptable sites:
- 2nd intercostal space, midclavicular line (classic teaching)
- 4th or 5th intercostal space, anterior to midaxillary line (increasingly recommended due to more reliable anatomy)
Chest tube placement (high-yield)
- “Safe triangle”: lateral chest wall around the 4th–5th intercostal space, anterior/midaxillary line
- Remember: intercostal neurovascular bundle runs inferior to each rib, so go over the top of the rib.
The Core Concept: When do you actually need a chest tube?
Chest tube (tube thoracostomy) indications you should know cold
| Condition | Typical management | Chest tube? |
|---|---|---|
| Tension pneumothorax | Needle decompression → chest tube | Yes (after needle) |
| Large pneumothorax (symptomatic or large on imaging) | Chest tube or pigtail catheter | Often yes |
| Traumatic pneumothorax | Chest tube (esp if on positive pressure ventilation) | Yes |
| Hemothorax | Chest tube (drain + quantify bleeding) | Yes |
| Empyema / complicated parapneumonic effusion | Chest tube drainage + antibiotics | Yes |
| Malignant pleural effusion (recurrent) | Thoracentesis → consider indwelling catheter/pleurodesis | Sometimes |
One-liner to remember
Air under pressure or blood/pus in the pleural space → chest tube.
Why Every Distractor Is Wrong (and what it’s trying to teach)
A. Obtain a portable chest x-ray
Why it’s tempting: Pneumothorax is often confirmed on CXR.
Why it’s wrong here: This patient is hemodynamically unstable with classic signs of tension pneumothorax. Imaging delays life-saving treatment.
USMLE rule:
- Stable pneumothorax? Imaging first is reasonable.
- Unstable with suspected tension? Treat first.
C. Noninvasive positive-pressure ventilation (BiPAP)
Why it’s tempting: Hypoxic and dyspneic? Support ventilation.
Why it’s dangerous/wrong: Positive pressure can worsen a pneumothorax and can rapidly convert a simple pneumothorax into tension pneumothorax by forcing more air into the pleural space.
High-yield pitfall:
- In suspected pneumothorax (especially trauma), avoid NIPPV until you’ve addressed the pleural air problem.
D. IV furosemide
Why it’s tempting: Dyspnea + hypoxia + “critical care vibes” makes people think pulmonary edema.
Why it’s wrong: No crackles, no S3, no orthopnea history, and the exam screams obstructive shock, not cardiogenic fluid overload. Also, diuresis would worsen hypotension.
Pattern recognition:
- Cardiogenic pulmonary edema: crackles, S3, hypertension or “warm/wet,” CXR congestion.
- Tension pneumothorax: unilateral absent breath sounds, hyperresonance, JVD, hypotension.
E. Therapeutic thoracentesis
Why it’s tempting: “Drain the pleural space” sounds right.
Why it’s wrong: Thoracentesis is for pleural effusions, not pneumothorax in an unstable trauma patient.
Know the division:
- Thoracentesis = diagnostic/therapeutic removal of fluid (effusion).
- Chest tube/pigtail = ongoing drainage of air (pneumothorax) or blood/pus (hemothorax/empyema), especially when large, ongoing, or complicated.
Rapid-Fire High-Yield Pearls (USMLE-friendly)
Tension pneumothorax: clinical diagnosis
- Key findings: hypotension, JVD, tracheal deviation away, absent breath sounds, hyperresonance
- Mechanism: one-way valve → rising intrathoracic pressure → ↓ venous return → obstructive shock
Simple pneumothorax vs tension pneumothorax
| Feature | Simple pneumothorax | Tension pneumothorax |
|---|---|---|
| Hemodynamics | Usually stable | Unstable (shock) |
| Tracheal deviation | Usually none | Yes (late but classic) |
| Next best step | Oxygen ± aspiration/chest tube depending size | Needle decompression immediately |
Hemothorax clues
- Dullness to percussion (fluid), decreased breath sounds
- CXR: pleural fluid level
- Chest tube drains and measures bleeding
- Massive hemothorax often defined as >1500 mL immediate output or >200 mL/hr ongoing → surgical evaluation
Empyema / complicated parapneumonic effusion
- Think: fever, pleuritic pain, pneumonia not improving
- Pleural fluid: low pH (<7.2), low glucose, high LDH, loculations
- Management: antibiotics + chest tube (often with fibrinolytics or surgery if loculated)
Exam Strategy: How to pick “chest tube” under pressure
Ask yourself three questions:
-
Is the patient unstable (shock/respiratory failure) with unilateral findings?
- If yes and consistent with tension pneumothorax → needle decompression → chest tube.
-
Is the pleural problem air vs fluid?
- Air (pneumo): pigtail/chest tube if large/symptomatic/trauma.
- Blood/pus: chest tube.
-
Is this an effusion that needs sampling first?
- Stable effusion → diagnostic thoracentesis (unless obvious CHF responding to diuresis).
Takeaway
Chest tube questions reward precision: what’s in the pleural space (air vs fluid), how sick is the patient, and what’s the safest immediate move. In an unstable trauma patient with signs of tension pneumothorax, the right answer isn’t “confirm”—it’s decompress now, tube next.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
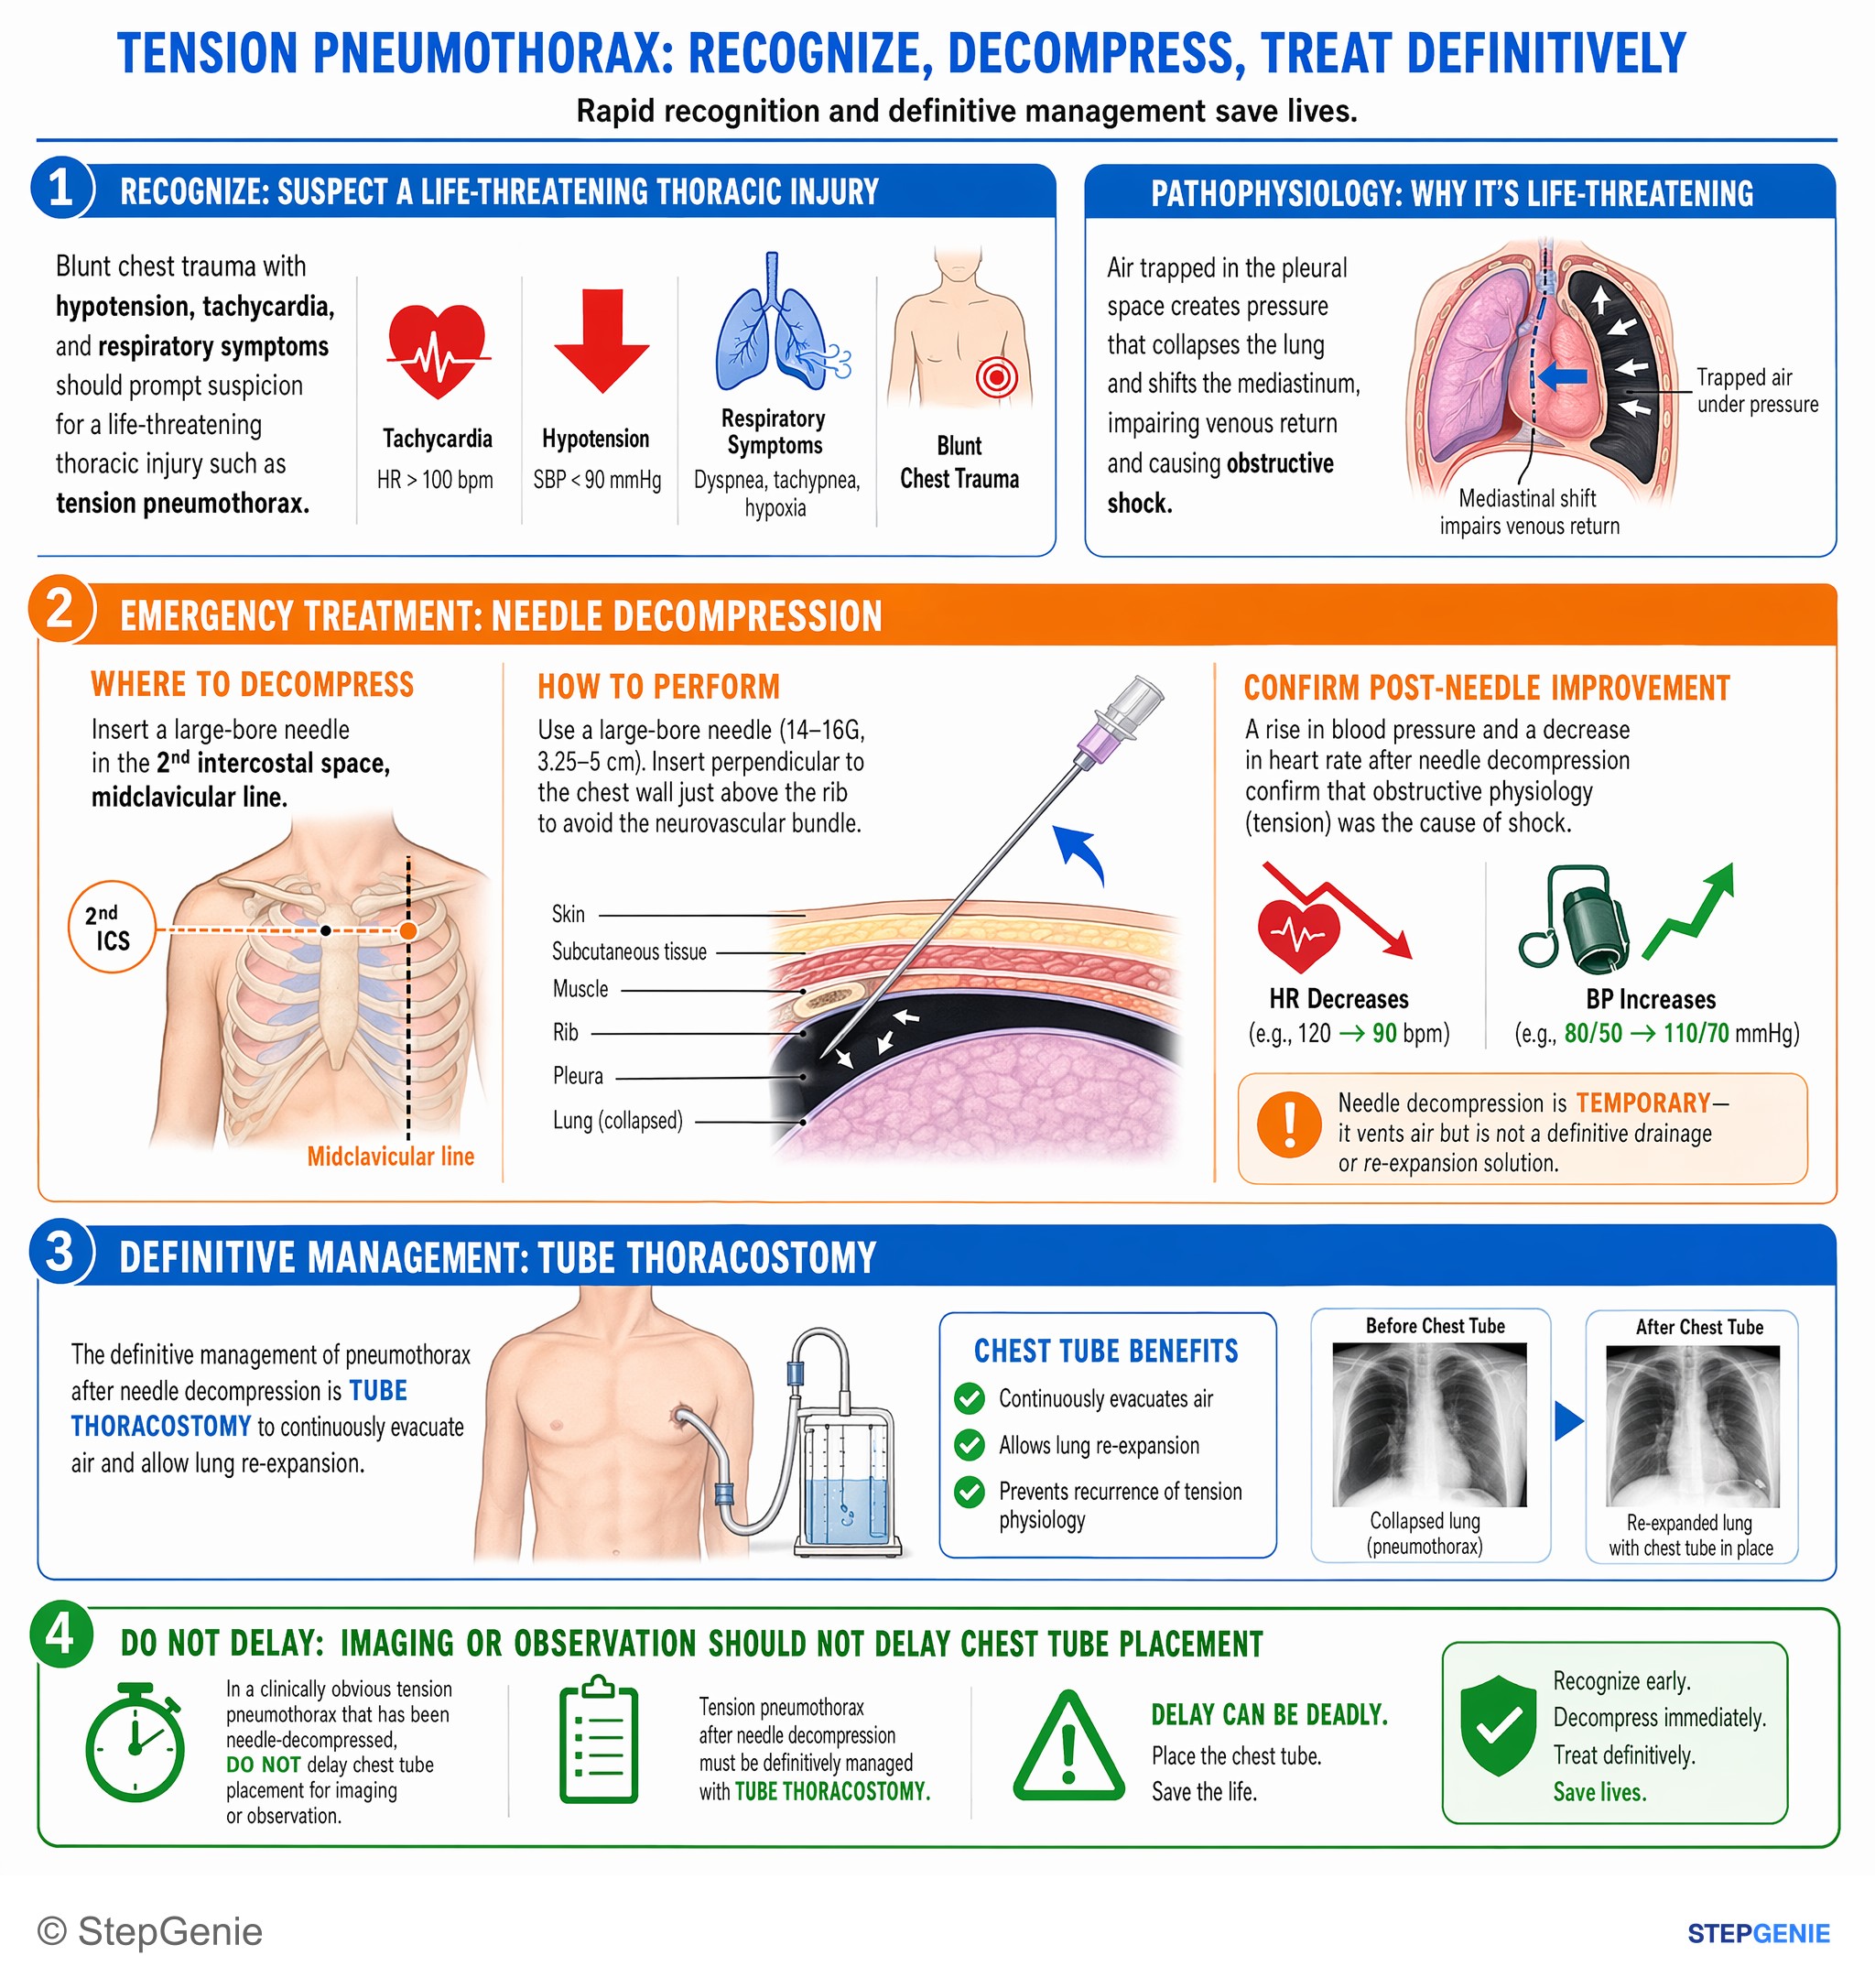
Tension pneumothorax after needle decompression must be definitively managed with tube thoracostomy; do not delay for imaging or…
USMLE Step 2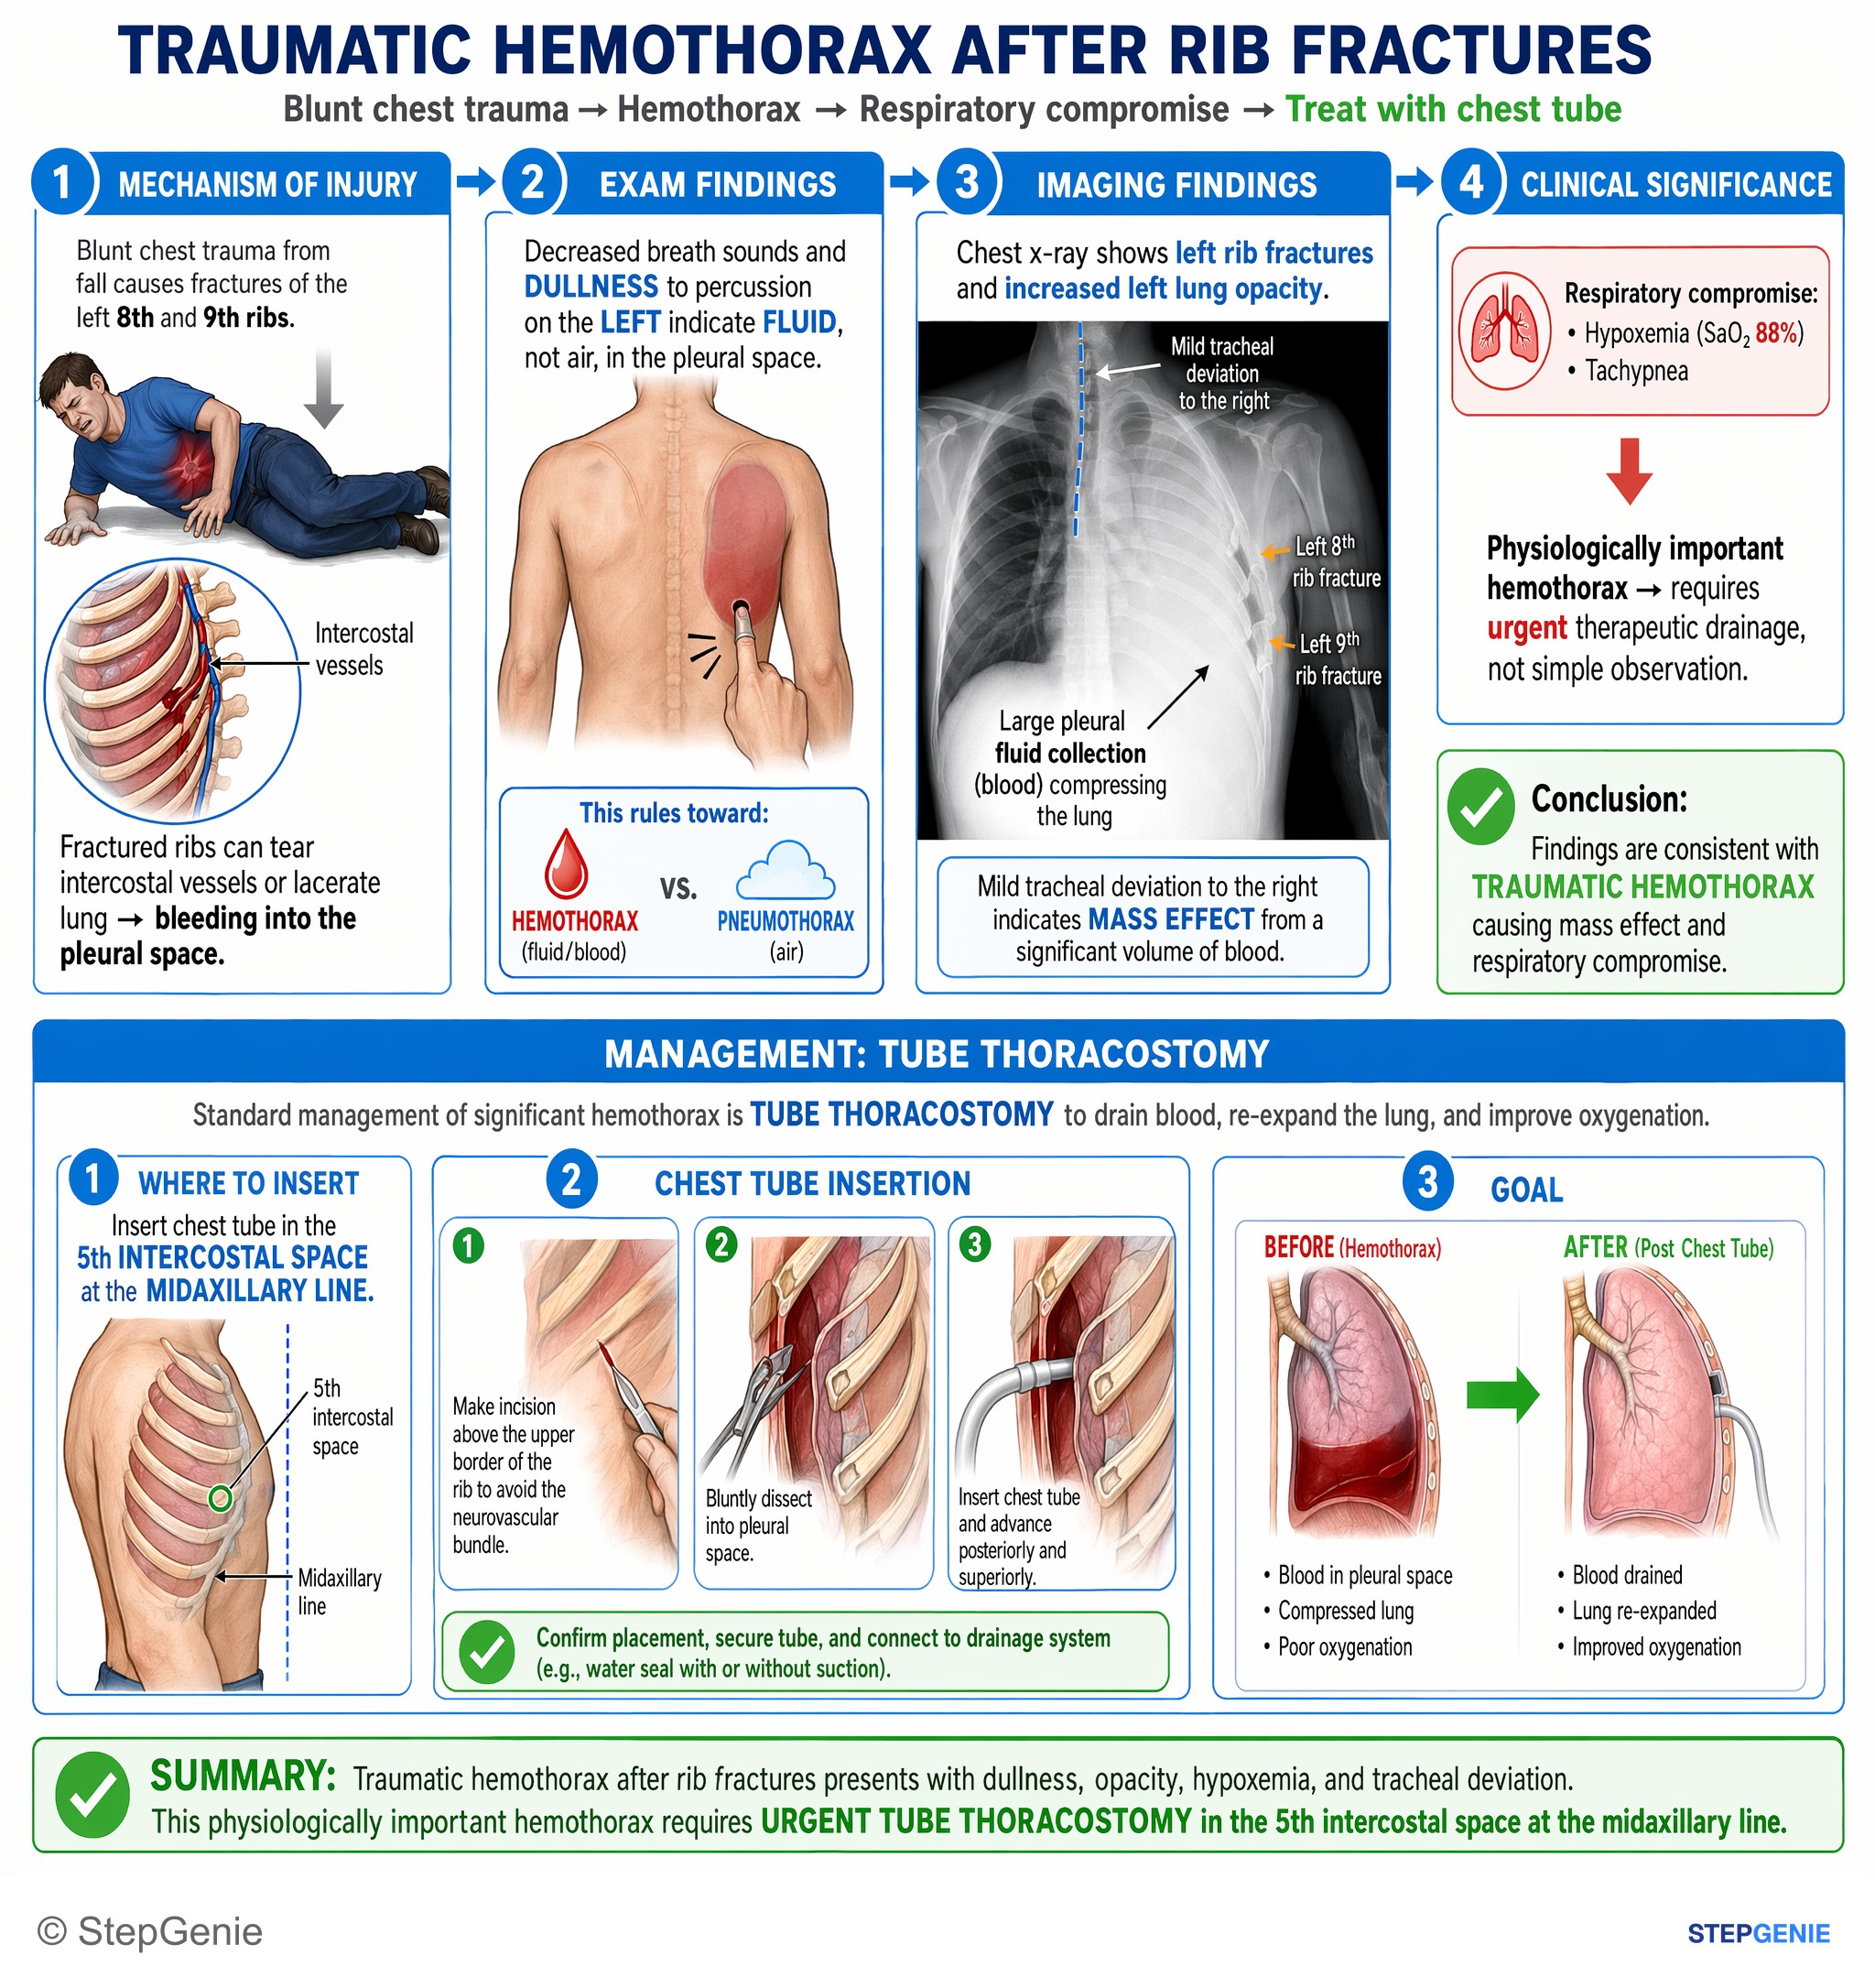
Traumatic hemothorax after rib fractures → hypoxemia, dullness, opacity, tracheal deviation → manage with tube thoracostomy (5th…
USMLE Step 2Frequently Asked Questions
What is the next step for suspected tension pneumothorax in an unstable trauma patient?
The next step is immediate needle decompression followed by chest tube placement. An unstable patient with hypotension, tachycardia, unilateral absent breath sounds, hyperresonance, jugular venous distention, and tracheal deviation has a clinical picture of tension pneumothorax. Because this causes obstructive shock, treatment should not wait for imaging, and tube thoracostomy is the definitive management after decompression.
Why shouldn’t you get a chest x-ray before treating tension pneumothorax?
You should not get a chest x-ray first because tension pneumothorax is a clinical diagnosis in an unstable patient. When hypotension and classic exam findings suggest obstructive shock from pleural air under pressure, imaging delays life-saving treatment. Imaging is reasonable for a stable pneumothorax, but if the patient is unstable and tension is suspected, you treat first with decompression.
How do you tell tension pneumothorax from simple pneumothorax on exam?
Tension pneumothorax is distinguished by hemodynamic instability and obstructive shock physiology. A simple pneumothorax is usually hemodynamically stable, whereas tension pneumothorax causes hypotension and can show jugular venous distention and tracheal deviation away from the affected side. Both can have absent breath sounds, but hyperresonance plus shock findings should push you toward tension pneumothorax and immediate decompression.
Why is BiPAP dangerous in suspected pneumothorax?
BiPAP is dangerous because positive pressure can worsen a pneumothorax by forcing more air into the pleural space. In a patient with suspected pneumothorax, especially after trauma, noninvasive positive-pressure ventilation can rapidly convert a simple pneumothorax into tension pneumothorax. That is why the pleural air problem should be addressed first rather than giving NIPPV.
When do you need a chest tube instead of thoracentesis?
You need a chest tube when the pleural space contains air under pressure or ongoing blood or pus, while thoracentesis is used for pleural fluid removal. Chest tubes are indicated for tension pneumothorax, many large or traumatic pneumothoraces, hemothorax, and empyema or complicated parapneumonic effusion. Thoracentesis is for pleural effusions, so it is not the right procedure for an unstable trauma patient with pneumothorax.