The countercurrent multiplier is how the loop of Henle builds a salty renal medulla: the thick ascending limb pumps NaCl out through NKCC2 but is impermeable to water, the thin descending limb lets water leave, and flow in opposite directions multiplies this small difference into a gradient from about 300 mOsm/kg at the corticomedullary border to about 1,200 mOsm/kg at the papillary tip. The vasa recta (the countercurrent exchanger) preserve that gradient, urea recycling deepens it, and ADH lets the collecting duct use it by inserting aquaporin-2 channels, producing concentrated urine. Loop diuretics, Bartter syndrome, sickle cell disease or trait and medullary washout all impair concentrating ability.
The whole system on one line each
| Job | Structure | How | Without it |
|---|---|---|---|
| Create the gradient | Loop of Henle (countercurrent multiplier) | Active NaCl reabsorption in the water-tight TAL plus water exit from the descending limb, multiplied by opposing flow | No hypertonic medulla (loop diuretics, Bartter) |
| Deepen it | Inner medullary collecting duct and urea transporters | Urea recycling, increased by ADH | Weaker inner medullary gradient |
| Preserve it | Vasa recta (countercurrent exchanger) | Slow flow in hairpin capillaries trades solute and water passively | Washout (sickling in the vasa recta) |
| Use it | Collecting duct with ADH | V2 receptor signaling inserts AQP2; water follows the gradient | Large volumes of dilute urine (diabetes insipidus) |
Segment-by-segment cheat sheet
| Segment | Water permeable? | What moves | Key proteins | Tubular fluid |
|---|---|---|---|---|
| Thin descending limb | Yes | Water leaves into the salty interstitium; urea enters | Aquaporin-1; UT-A urea transporters | Becomes hypertonic, up to about 1,200 mOsm/kg at the hairpin |
| Thin ascending limb | No | NaCl leaves | — | Starts to dilute |
| Thick ascending limb (TAL) | No | Na⁺, K⁺ and 2 Cl⁻ reabsorbed; the lumen-positive voltage drives Mg²⁺ and Ca²⁺ between cells | NKCC2 (loop diuretic target), basolateral Na⁺/K⁺-ATPase | Diluting segment: about 100 mOsm/kg by the top |
| Early distal convoluted tubule | Low | NaCl reabsorbed | NCC (thiazide target) | Diluted further |
| Collecting duct | With ADH (low without it) | Water leaves with ADH; urea leaves the inner medullary duct with ADH | V2 receptor, AQP2; UT-A1 and UT-A3 | Dilute without ADH; concentrated with ADH |
Juxtamedullary nephrons have loops of varying length, some reaching very deep into the medulla; cortical nephrons have short loops that barely enter it, if at all. The end of the TAL also carries the macula densa, the NaCl sensor of the juxtaglomerular apparatus.
How the multiplier works in 4 steps
- TAL pumps NaCl out, water stays in. The interstitium becomes hypertonic while the tubular fluid becomes hypotonic. This small horizontal difference is the "single effect."
- The descending limb equilibrates. Water leaves the water-permeable descending limb into the salty interstitium, so the fluid inside becomes hypertonic.
- Flow pushes it deeper. New isotonic fluid enters from the proximal tubule and moves the concentrated fluid toward the hairpin.
- Repeat along the loop. The single effect stacks up vertically: about 300 mOsm/kg near the cortex, about 1,200 mOsm/kg at the papillary tip.
Remember it as "salt out going up, water out going down."
Numbers to know
| Value | About |
|---|---|
| Plasma and cortical interstitium | 280-300 mOsm/kg |
| Papillary tip (deep inner medulla) | 1,200 mOsm/kg |
| Fluid leaving the TAL | 100 mOsm/kg (hypotonic) |
| Healthy maximal urine after dehydration | Over 700-800 mOsm/kg (Merck); the ceiling is set by the papillary tip |
| Maximally dilute urine | Under 100 mOsm/kg |
| Maximal urine output of normal kidneys | Up to about 25 L/day |
Free water clearance ties it together: CH2O = V − Cosm, where Cosm = (Uosm × V) ÷ Posm. It is positive when urine is dilute (no ADH) and negative when urine is concentrated (ADH present).
Urea recycling
- Urea accumulates in the inner medullary interstitium and helps raise its osmolality.
- With ADH, urea leaves the inner medullary collecting duct through the facilitated transporters UT-A1 and UT-A3 (passive transport down its gradient, not a pump), builds up in the interstitium, and re-enters the thin descending limb (UT-A) and the vasa recta (UT-B).
- Evidence: mice lacking UT-A1 and UT-A3 have markedly reduced concentrating ability, and loss of vascular UT-B cuts it by about 25%.
Vasa recta: the countercurrent exchanger
- Hairpin capillaries parallel the loops. Descending vasa recta pick up Na⁺ and urea and lose water; ascending vasa recta do the reverse, so solute is recycled rather than carried away.
- Flow must be slow: rapid flow would carry off Na⁺ and urea and wash out the gradient.
- Multiplier vs exchanger: the loop creates the gradient with active transport; the vasa recta preserve it passively.
ADH: using the gradient
- ADH (arginine vasopressin) binds V2 receptors on collecting duct principal cells, which leads to insertion of AQP2 water channels into the apical membrane; water then moves down the medullary gradient. When fluid intake is adequate, less AVP is released and AQP2 is removed.
- ADH also increases urea transport in the inner medullary collecting duct, deepening the gradient.
- Updated names (Merck 2026): central diabetes insipidus is now arginine vasopressin deficiency (AVP-D), and nephrogenic DI is arginine vasopressin resistance (AVP-R). Desmopressin raises urine osmolality by 50-100% or more in AVP-D but by less than 50 mOsm/kg in AVP-R. See central vs nephrogenic diabetes insipidus and ADH and water balance.
What breaks the system
| Cause | Where it breaks | Clue |
|---|---|---|
| Loop diuretics | Block NKCC2 in the TAL, so medullary hypertonicity is not built | Large-volume diuresis; hypokalemia; more calcium and magnesium in the urine (loop diuretics) |
| Bartter syndrome | Inherited TAL transport defect (SLC12A1/NKCC2, KCNJ1/ROMK and related genes; usually autosomal recessive) | "Built-in loop diuretic": salt and potassium wasting, hypokalemic metabolic alkalosis, high renin and aldosterone, normal or low blood pressure, high urine calcium; antenatal forms cause polyhydramnios |
| Sickle cell disease and trait | Sickling in the slow, hypoxic, hyperosmotic vasa recta destroys countercurrent exchange and long loops | Hyposthenuria (common even in trait), self-limited hematuria (usually from the left kidney), papillary necrosis (less common in trait) |
| Primary polydipsia | Chronic high water intake lowers medullary tonicity (washout) | Cannot concentrate maximally even after water restriction (SIADH vs psychogenic polydipsia) |
| AVP resistance | Collecting duct ignores ADH: AVPR2 variants (X-linked, the most common inherited form) or rare AQP2 variants (autosomal), lithium, hypercalcemia, sickle cell nephropathy, possibly chronic hypokalemia | Dilute urine despite circulating ADH; minimal desmopressin response |
| AVP deficiency | Too little ADH: damage to the hypothalamic supraoptic and paraventricular nuclei (where ADH is made) or the pituitary stalk; the posterior pituitary only stores and releases it | Dilute urine that concentrates after desmopressin |
Loop vs thiazide: concentrating vs diluting
| Loop diuretic (TAL) | Thiazide (early DCT) | |
|---|---|---|
| Effect on the medullary gradient | Flattened | Spared |
| What is impaired | Ability to concentrate urine | Ability to dilute urine |
| Hyponatremia | Much less common | Classic, especially in older patients |
This is why thiazides, not loop diuretics, are the classic cause of drug-induced hyponatremia: the gradient stays intact, so ADH can still pull water back while sodium is lost. More in the thiazide mnemonic.
How USMLE tests it
- "Which segment is impermeable to water but reabsorbs NaCl?" The TAL, the diluting segment.
- "Which segment equilibrates with the interstitium?" The thin descending limb (aquaporin-1).
- Multiplier vs exchanger: loop of Henle creates, vasa recta preserve.
- Urea is recycled by facilitated transporters, not actively pumped.
- Lithium causes AVP resistance; in AVP resistance, thiazides, amiloride or NSAIDs can help.
- Sickle cell trait plus inability to concentrate urine points to the vasa recta.
Practice question
A 20-year-old man with sickle cell trait has noticed for several months that he passes large volumes of urine and wakes at night to void; he drinks more because he is thirsty. Last year he had one self-limited episode of painless gross hematuria. Serum sodium is 141 mEq/L, and glucose and calcium are normal. After overnight fluid restriction his urine is less concentrated than expected, and it does not concentrate further after desmopressin. Which of the following best explains his inability to concentrate urine?
A. Sickling in the vasa recta, destroying medullary countercurrent exchange B. Deficient vasopressin release from the posterior pituitary C. Inherited loss of NKCC2 function in the thick ascending limb D. Medullary washout from habitual excessive water drinking E. Osmotic diuresis from glycosuria
Answer: A. The medulla is hypoxic and hyperosmotic and its blood flow is slow, an ideal setting for sickling. Damage to the vasa recta and long loops of Henle destroys countercurrent exchange, so even people with sickle cell trait commonly develop hyposthenuria. Self-limited hematuria (usually from the left kidney) is another known renal feature of sickle cell trait.
- B: AVP deficiency would raise urine osmolality by 50-100% or more after desmopressin; he did not respond.
- C: Bartter syndrome causes salt and potassium wasting with hypokalemic metabolic alkalosis and high renin and aldosterone, and its antenatal forms appear before birth; nothing in this stem points to it, and it would not explain the hematuria.
- D: long-standing polydipsia does blunt maximal concentration, but here thirst follows the urine losses, and the sickle cell trait and hematuria point to medullary damage.
- E: glucose is normal, so there is no glycosuria driving an osmotic diuresis.
Key takeaways
- TAL: salt out, no water (NKCC2), the diluting segment. Descending limb: water out (aquaporin-1).
- The multiplier creates a gradient from about 300 to about 1,200 mOsm/kg; the vasa recta preserve it; ADH uses it through V2 receptors and AQP2.
- Urea recycling (UT-A1 and UT-A3, increased by ADH) deepens the inner medullary gradient.
- Loop diuretics flatten the gradient and impair concentration; thiazides impair dilution, which is why they cause hyponatremia.
- Sickle cell trait and disease cause hyposthenuria through vasa recta sickling.
- Central DI is now AVP deficiency, and nephrogenic DI is AVP resistance (lithium, hypercalcemia, X-linked AVPR2).
Sources
- Tubular Reabsorption (25.6) — OpenStax Anatomy and Physiology 2e
- Loop of Henle: textbook excerpts — ScienceDirect Topics (Elsevier)
- Urea Transporter: textbook excerpts — ScienceDirect Topics (Elsevier)
- Loop Diuretic Agent: excerpts incl. Hyponatremia in Acute Decompensated Heart Failure (JACC 2015) — ScienceDirect Topics (Elsevier)
- Sickle Cell Nephropathy: textbook excerpts incl. Comprehensive Clinical Nephrology — ScienceDirect Topics (Elsevier)
- Arginine Vasopressin Resistance (Nephrogenic Diabetes Insipidus) — Merck Manual Professional Edition (2026)
- Arginine Vasopressin Deficiency (Central Diabetes Insipidus) — Merck Manual Professional Edition (2026)
- Hyponatremia — Merck Manual Professional Edition (2025)
- Sickle Cell Disease — Merck Manual Professional Edition (2026)
- Bartter Syndrome — StatPearls, NCBI Bookshelf (2026)
- Hypokalemia — Merck Manual Professional Edition (2025)
- AQP2 Gene — MedlinePlus Genetics (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
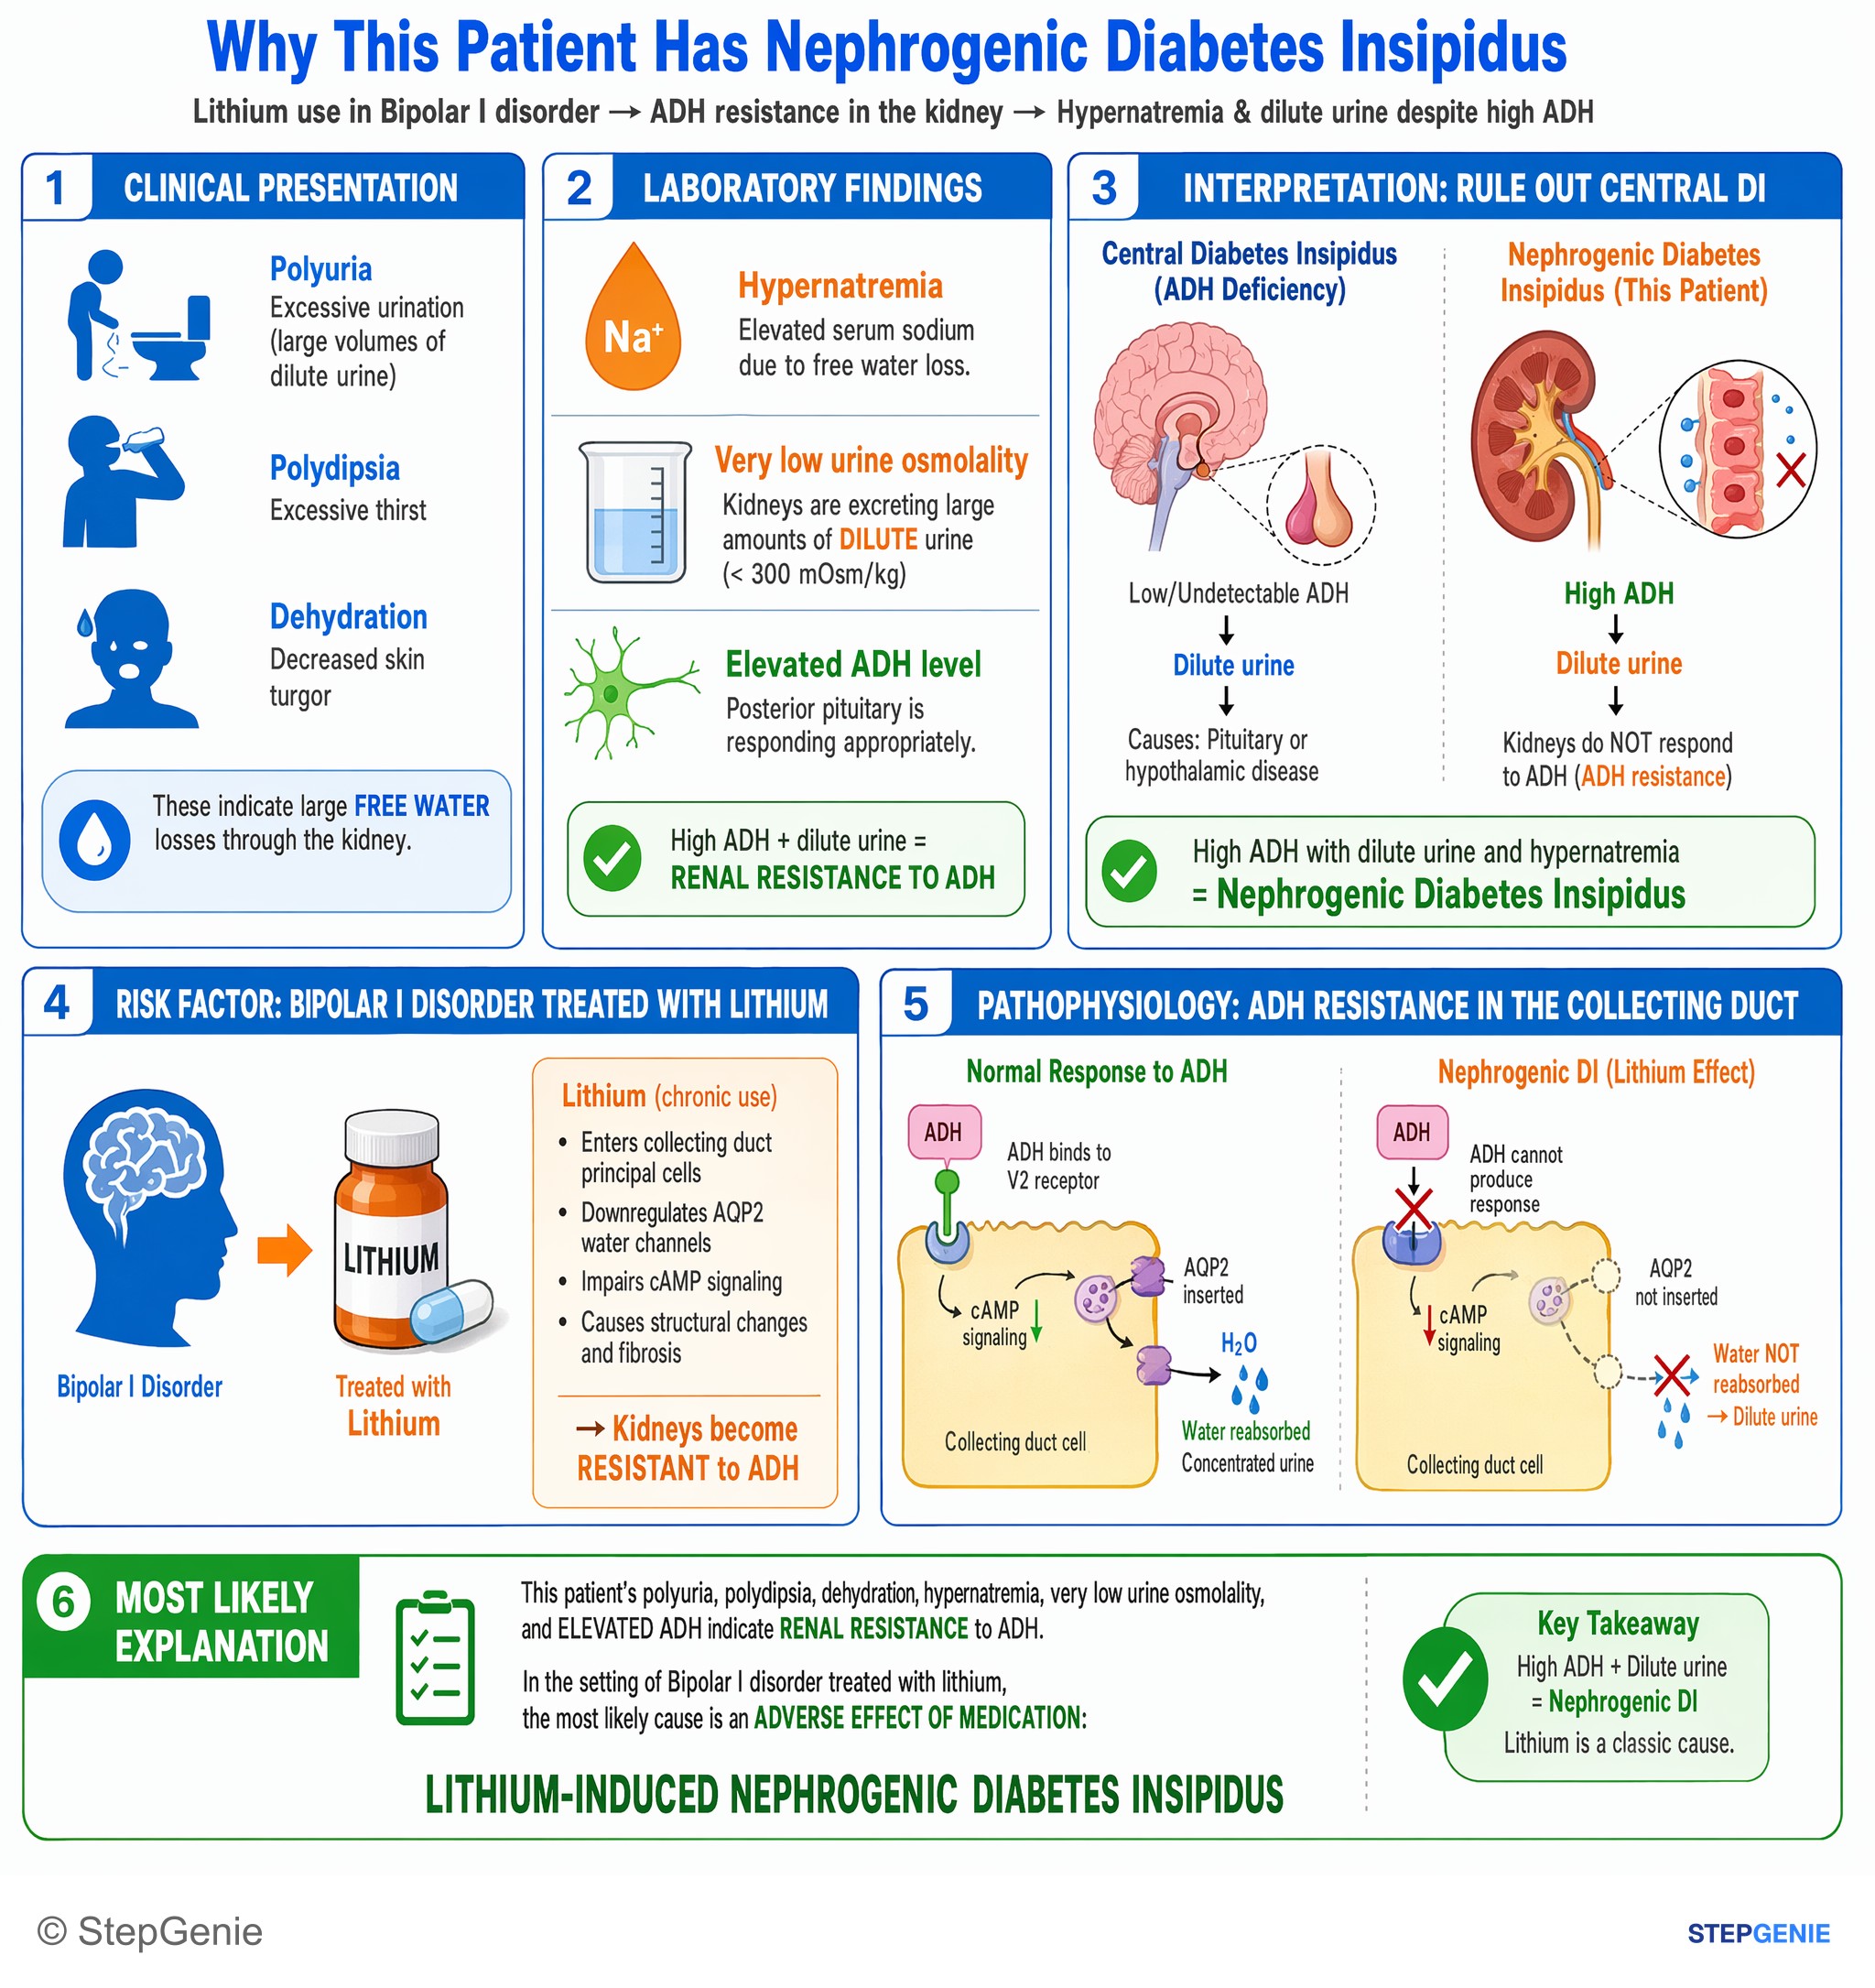
Nephrogenic diabetes insipidus from chronic lithium use in bipolar I: kidneys become ADH-resistant → hypernatremia + low urine osmolality…
USMLE Step 1Frequently Asked Questions
What is the countercurrent multiplier?
The countercurrent multiplier is the mechanism by which the loop of Henle builds an osmotic gradient in the renal medulla. The thick ascending limb actively reabsorbs NaCl through NKCC2 but is impermeable to water, and the thin descending limb lets water leave into the salty interstitium. Because fluid flows in opposite directions in the two limbs, this small difference is multiplied along the loop, giving a gradient from about 300 mOsm/kg near the cortex to about 1,200 mOsm/kg at the papillary tip.
What is the difference between the countercurrent multiplier and the countercurrent exchanger?
The countercurrent multiplier is the loop of Henle, which creates the medullary gradient using active NaCl transport in the water-impermeable thick ascending limb. The countercurrent exchanger is the vasa recta, the hairpin capillaries that preserve the gradient passively: descending vessels pick up sodium and urea and lose water, and ascending vessels do the reverse. Their slow blood flow keeps solute from being washed out of the medulla.
Why is the thick ascending limb called the diluting segment?
The thick ascending limb reabsorbs sodium, potassium and chloride through the NKCC2 cotransporter but has no water channels, so salt leaves the tubule while water stays behind. The tubular fluid becomes hypotonic, about 100 mOsm/kg by the top of the limb, even as the reabsorbed salt makes the surrounding medulla hypertonic. Its lumen-positive voltage also drives calcium and magnesium reabsorption between cells, which is why loop diuretics increase their excretion.
How does ADH concentrate urine?
ADH, also called arginine vasopressin, binds V2 receptors on collecting duct principal cells, which leads to insertion of aquaporin-2 water channels into the apical membrane. Water then moves out of the collecting duct down the medullary gradient that the countercurrent multiplier built, producing small volumes of concentrated urine. ADH also increases urea transport through UT-A1 and UT-A3 in the inner medullary collecting duct, which deepens the inner medullary gradient. Without ADH, the collecting duct stays relatively impermeable to water and the urine is dilute.
Why do thiazides cause hyponatremia more often than loop diuretics?
Loop diuretics block NKCC2 in the thick ascending limb, which prevents the medullary gradient from forming, so the kidney cannot concentrate urine and free water is lost along with salt. Thiazides block NaCl reabsorption in the early distal convoluted tubule, a cortical segment, which impairs the kidney's ability to dilute urine while leaving the medullary gradient intact, so ADH can still retain water. Merck notes that loop diuretics much less commonly cause hyponatremia, and older patients are especially susceptible to thiazide-induced hyponatremia.
Why does sickle cell trait cause hyposthenuria?
The renal medulla is relatively hypoxic and hyperosmotic, and its blood flow is slow, which makes the vasa recta an ideal place for red cells to sickle. Repeated sickling damages the vasa recta and long loops of Henle, destroying countercurrent exchange in the inner medulla, so the kidney cannot concentrate urine normally. This hyposthenuria is common even in sickle cell trait, which can also cause self-limited hematuria (usually from the left kidney) and, less often than in sickle cell disease, papillary necrosis.