Deep vein thrombosis (DVT) is one of those “simple-sounding” diagnoses that shows up everywhere on Step 1 because it links basic pathophysiology (Virchow triad) to real clinical consequences (pulmonary embolism). If you can quickly recognize who’s at risk, what’s happening in the vessel wall, and how to diagnose and treat it, you’ll score easy points across pulm/critical care, heme/onc, OB, and surgery questions.
Big Picture: What is DVT and why does it matter?
Deep vein thrombosis is a thrombus in the deep venous system, most commonly in the lower extremities (e.g., popliteal, femoral, iliac veins). The main danger is embolization to the lungs → pulmonary embolism (PE).
Step framing: DVT is a venous clot → think stasis + hypercoagulability, not plaque rupture.
High-Yield Definition (Step-ready)
- DVT: clot in deep veins (not superficial thrombophlebitis)
- Most common site: lower extremities
- Clinical significance: source of pulmonary emboli
- Clot type: red (RBC-rich) thrombus due to slower venous flow
Pathophysiology: Virchow Triad (Core mechanism)
Nearly every DVT question is secretly asking: which leg of Virchow triad is at play?
Virchow triad
- Stasis
- Endothelial injury
- Hypercoagulability
| Virchow component | What it means | Classic Step triggers |
|---|---|---|
| Stasis | Slow venous flow → clotting factors accumulate | Immobilization, prolonged travel, CHF, stroke with paresis |
| Endothelial injury | Vessel wall disruption exposes pro-thrombotic subendothelium | Surgery (esp ortho/hip), trauma, central venous catheters |
| Hypercoagulability | Increased tendency to clot | Cancer, pregnancy/postpartum, OCPs/estrogen, inherited thrombophilias |
First Aid cross-reference: Pathology (Thrombosis & Embolism) → Virchow triad and DVT/PE associations.
Hypercoagulability: High-yield inherited thrombophilias
These show up as “young patient with recurrent clots” or “clot after minor trigger.”
Factor V Leiden (most common inherited thrombophilia)
- Mutation makes factor V resistant to inactivation by protein C
- ↑ risk of DVT
- Often presents with recurrent venous thromboses
- Labs: can have normal PT/PTT; diagnosed with APC resistance assays/genetics
Prothrombin gene mutation (G20210A)
- ↑ prothrombin → ↑ thrombin → ↑ clotting
- Venous thrombosis risk
Protein C or Protein S deficiency
- Normally: Protein C (activated by thrombin-thrombomodulin) inactivates factors Va and VIIIa
- Deficiency → venous thrombosis
- Classic board tie-in: warfarin skin necrosis (see treatment section)
Antithrombin deficiency
- Antithrombin inhibits thrombin (IIa) and Xa
- Deficiency → hypercoagulable
- Heparin works by activating antithrombin → deficiency can cause heparin resistance
First Aid cross-reference: Heme/Onc (Coagulation disorders) → Factor V Leiden, protein C/S deficiency, antithrombin deficiency.
Acquired hypercoagulability: Don’t miss these Step favorites
Malignancy (Trousseau syndrome)
- Migratory thrombophlebitis / recurrent thrombosis
- Often mucin-producing adenocarcinomas (e.g., pancreas)
Antiphospholipid syndrome (APS)
- Arterial and venous thrombosis + pregnancy morbidity
- Labs: “paradoxical” ↑ PTT but clots (lupus anticoagulant)
- Can cause DVT → PE
Nephrotic syndrome
- Loss of antithrombin III in urine → hypercoagulable → venous thrombosis (incl. renal vein thrombosis)
Pregnancy / postpartum & estrogen (OCPs)
- Increased clotting factors; venous stasis in pregnancy also contributes
First Aid cross-reference: Heme/Onc + Repro → APS; pregnancy hypercoagulability.
Clinical Presentation: What does DVT look like?
Typical symptoms/signs
- Unilateral leg swelling
- Pain, tenderness (often calf)
- Warmth, erythema
- Pitting edema
- Dilated superficial veins may be seen
Important Step nuance
- Many DVTs are clinically silent.
- Homan sign (calf pain with dorsiflexion) is not reliable (low sensitivity/specificity). If it appears in an answer choice, it’s often a trap unless the stem is clearly old-school.
If they suddenly develop…
- Dyspnea, pleuritic chest pain, hemoptysis, syncope → think PE from DVT until proven otherwise
Diagnosis: How to approach on exams (and in real life)
Use pretest probability (Wells) + D-dimer + ultrasound
Core Step algorithm:
- Low pretest probability → D-dimer
- If negative: DVT unlikely
- If positive: do compression ultrasound
- High pretest probability → compression ultrasound first
- If negative but still high suspicion: repeat ultrasound or further imaging depending on scenario
Tests you need to know
D-dimer
- High sensitivity, low specificity
- Elevated in:
- DVT/PE
- infection, inflammation, trauma
- pregnancy
- malignancy
- postop state
- Best used to rule out DVT in low-risk patients
Compression ultrasound (duplex ultrasonography)
- First-line diagnostic test for suspected lower-extremity DVT
- Looks for noncompressible vein (key phrase)
Venography
- Historically “gold standard” but rarely used now (invasive)
First Aid cross-reference: Pulmonary (PE) + Path (Thromboembolism) → D-dimer and imaging logic is commonly implied.
Treatment: Anticoagulation is the main event
Initial management
Most uncomplicated DVTs get therapeutic anticoagulation.
Common options:
- DOACs (e.g., apixaban, rivaroxaban) for many patients
- Heparin (unfractionated or LMWH) often used initially in hospitalized/high-risk scenarios
- Warfarin for selected situations (e.g., certain valvular conditions; also historically common)
Mechanism tie-ins (Step 1):
- Heparin/LMWH → activate antithrombin → inhibit IIa and Xa (LMWH more Xa-selective)
- Warfarin → inhibits vitamin K epoxide reductase → ↓ factors II, VII, IX, X, and protein C & S
Warfarin skin necrosis (classic board concept)
- Warfarin initially drops protein C faster than procoagulant factors → transient hypercoagulable state
- Can cause skin necrosis
- Prevention: bridge with heparin when starting warfarin for acute thrombosis
Duration (testable generalities)
- Provoked DVT (e.g., surgery, immobilization): often shorter course
- Unprovoked or recurrent DVT: longer-term anticoagulation considered
- Cancer-associated thrombosis: anticoagulation strategy tailored; higher recurrence risk
(Exact durations vary by guideline and stem context—Step questions usually test the concept of provoked vs unprovoked and recurrence risk.)
When to consider an IVC filter (high-yield indication)
Inferior vena cava (IVC) filter is considered when:
- Anticoagulation is contraindicated (e.g., active major bleeding, very high bleeding risk)
- Or recurrent PE/DVT despite adequate anticoagulation (less common)
Concept: An IVC filter prevents PE, but does not treat the existing clot and may increase long-term DVT risk.
Complications: What Step wants you to anticipate
Pulmonary embolism (PE)
- Most feared acute complication
- Can cause hypoxemia, tachycardia, pleuritic chest pain, and in massive PE: hypotension/obstructive shock
Post-thrombotic syndrome
- Chronic venous insufficiency after DVT
- Leg swelling, pain, heaviness, skin changes, venous stasis ulcers
Phlegmasia cerulea dolens (rare but high yield)
- Massive iliofemoral DVT → severe swelling, cyanosis, pain
- Threatens limb viability (compartment-like physiology)
DVT vs Superficial thrombophlebitis (quick comparison)
| Feature | DVT | Superficial thrombophlebitis |
|---|---|---|
| Location | Deep veins (femoral/popliteal/iliac) | Superficial veins |
| PE risk | Yes (major concern) | Usually low (but can extend) |
| Diagnosis | Compression ultrasound | Often clinical ± ultrasound |
| Treatment | Anticoagulation | NSAIDs, compression; anticoagulate if extension/high risk |
High-Yield Associations & Rapid-Fire Facts (Step 1 gold)
- Venous clots: stasis, hypercoagulability, RBC-rich “red” thrombi
- Immobility + cancer + surgery + pregnancy/estrogen = classic DVT risk stack
- D-dimer: sensitive, not specific → best to rule out in low-risk
- Ultrasound finding: noncompressible vein
- Factor V Leiden: resistance to protein C → recurrent DVT
- APS: ↑ PTT but thrombosis; pregnancy loss
- Nephrotic syndrome: loss of antithrombin III → thrombosis
- Warfarin: early drop in protein C → transient hypercoagulable state → skin necrosis unless bridged
First Aid Cross-References (where this lives conceptually)
Use these as “anchors” while you review:
- Pathology (Thrombosis & Embolism): Virchow triad; red vs white thrombi; embolization
- Pulmonary (Pulmonary embolism): DVT as the source; D-dimer logic; imaging approach
- Heme/Onc (Coagulation disorders): Factor V Leiden; protein C/S deficiency; antithrombin; APS
- Repro: pregnancy/OCP hypercoagulability
(Section titles may vary slightly by edition, but these topics consistently appear in those chapters.)
Mini–Self-Check (3 classic vignettes)
-
Post-op patient with unilateral swollen tender calf → next best test?
Compression ultrasound (high pretest probability) -
Young patient with recurrent DVTs and normal PT/PTT → likely cause?
Factor V Leiden (APC resistance) -
Patient started on warfarin for DVT without bridge develops painful skin lesions/necrosis → mechanism?
Rapid protein C depletion → transient hypercoagulability
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
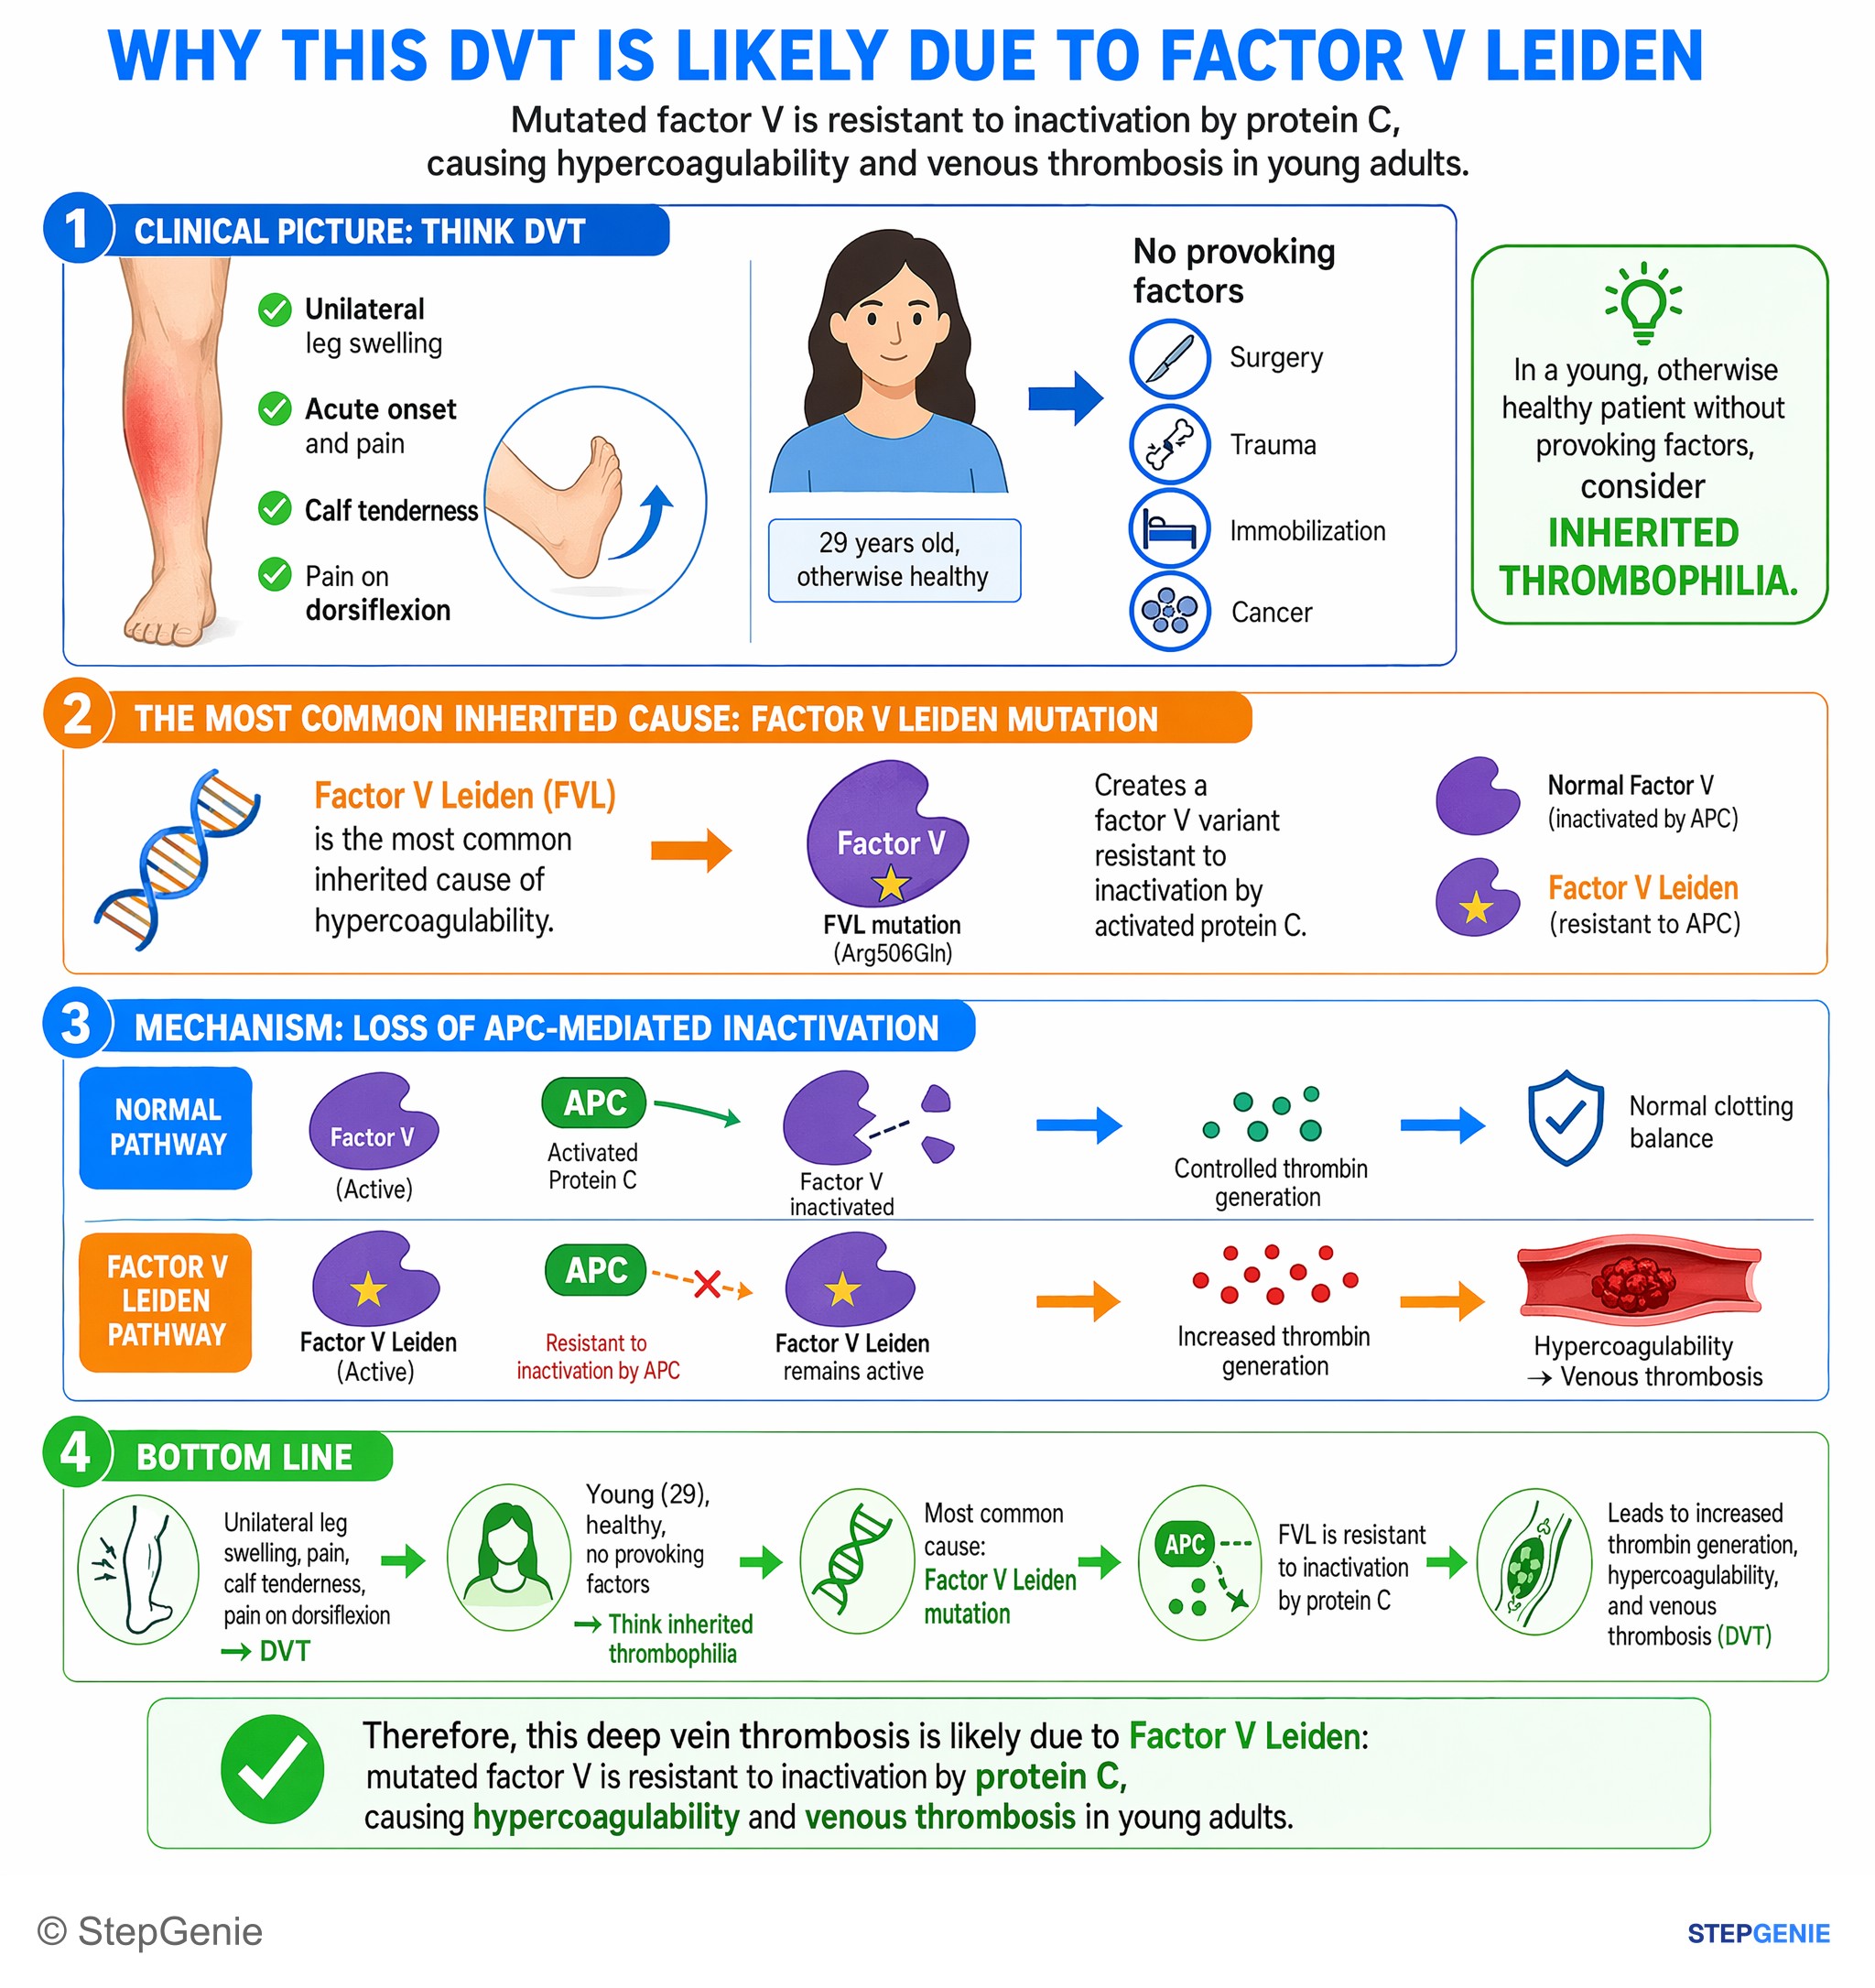
Deep vein thrombosis due to Factor V Leiden: mutated factor V is resistant to inactivation by protein C, causing hypercoagulability and…
USMLE Step 2Frequently Asked Questions
Why is deep vein thrombosis dangerous if the clot is in the leg?
Deep vein thrombosis is dangerous because it can embolize to the lungs and cause a pulmonary embolism. A DVT is a thrombus in the deep venous system, most often in the lower extremities such as the popliteal, femoral, or iliac veins. Its major clinical significance is that part of the clot can break off, travel through the venous circulation, and obstruct pulmonary vessels.
What causes a DVT on Step 1?
A DVT is classically caused by Virchow triad: stasis, endothelial injury, and hypercoagulability. Stasis comes from slow venous flow, such as immobilization, prolonged travel, CHF, or stroke with paresis. Endothelial injury occurs with surgery, trauma, or central venous catheters. Hypercoagulability is seen with cancer, pregnancy or postpartum state, estrogen use, and inherited thrombophilias like Factor V Leiden.
How do you diagnose suspected lower-extremity DVT on an exam question?
The key diagnostic approach is pretest probability plus D-dimer and compression ultrasound. In a low-pretest-probability patient, start with D-dimer; a negative result makes DVT unlikely, while a positive result should be followed by compression ultrasound. In a high-pretest-probability patient, go straight to compression ultrasound first. The classic ultrasound clue is a noncompressible vein.
Is D-dimer good for ruling in DVT?
No, D-dimer is mainly useful for ruling out DVT in low-risk patients, not for ruling it in. It has high sensitivity but low specificity, so many conditions can elevate it, including infection, inflammation, trauma, pregnancy, malignancy, and the postoperative state. That is why a positive D-dimer does not confirm DVT and usually needs follow-up imaging such as compression ultrasound.
What symptoms should make you think a DVT has turned into a pulmonary embolism?
Sudden dyspnea, pleuritic chest pain, hemoptysis, or syncope should make you think of pulmonary embolism from a DVT. Typical DVT symptoms include unilateral leg swelling, pain, warmth, erythema, pitting edema, and sometimes dilated superficial veins, but many DVTs are clinically silent. If respiratory symptoms suddenly appear in that setting, PE should be suspected until proven otherwise.