The juxtaglomerular apparatus (JGA) is the kidney's built-in sensor where a nephron's own tubule touches its glomerulus. It has three parts: the macula densa (tubular cells that sense NaCl), the juxtaglomerular (granular) cells in the afferent arteriole wall (modified smooth muscle cells that secrete renin), and the extraglomerular mesangial (lacis) cells between them. High NaCl at the macula densa triggers ATP and adenosine release, which constricts the afferent arteriole and lowers GFR (tubuloglomerular feedback); high NaCl delivery also suppresses renin. Low NaCl, low renal perfusion pressure and beta-1 sympathetic stimulation all increase renin release.
The JGA comparison table
| Macula densa | Juxtaglomerular (granular) cells | Extraglomerular mesangial (lacis) cells | |
|---|---|---|---|
| Where | Specialized patch of tubular epithelium where the end of the thick ascending limb meets the distal convoluted tubule, pressed against its own glomerulus | Wall (tunica media) of the afferent arteriole at the glomerular entrance | Between the macula densa and the arterioles, outside the glomerulus |
| Cell type | Epithelial (tubular) cells | Modified smooth muscle cells | Mesangial-type support cells |
| Senses | Luminal NaCl delivery (and flow), via the Na-K-2Cl cotransporter (NKCC2) | Afferent arteriolar pressure (intrarenal baroreceptor) and beta-1 sympathetic input; respond to macula densa signals | Relay position; the bases of macula densa cells interdigitate with them |
| Releases | High NaCl: ATP and adenosine. Low NaCl: PGE2 (COX-2) and nitric oxide (nNOS) | Renin (stored in granules) | No hormone of exam importance |
| Net effect | Tubuloglomerular feedback keeps GFR and distal delivery stable; tunes renin | Starts the renin-angiotensin-aldosterone system | Part of the signaling bridge |
| Classic exam clue | "Which cells sense NaCl?" NSAIDs blunt its prostaglandin signal | "Which cells secrete renin?" Beta-blockers lower renin; renal artery stenosis raises it | Named in JGA diagrams |
Location wording varies. Some texts place the macula densa in the terminal thick ascending limb, others at the start of the distal convoluted tubule, and StatPearls spans both. Either way, it sits at the TAL-DCT junction, right next to the vascular pole of its own glomerulus.
High vs low NaCl at the macula densa
| High NaCl delivery (GFR too high) | Low NaCl delivery (GFR or volume too low) | |
|---|---|---|
| Macula densa signal | ATP and adenosine | PGE2 and NO |
| Afferent arteriole | Constricts | Dilates |
| GFR | Falls back toward normal | Rises back toward normal |
| Renin | Suppressed | Released |
| Logic | "Too much is reaching me: filter less" | "Too little is reaching me: filter more and retain salt" |
Think of the macula densa as a downstream quality check: the NaCl reaching it reflects how much was filtered upstream. That is why the response targets the afferent arteriole, the inflow to the same glomerulus. Nitric oxide counterbalances the constriction by relaxing the afferent arteriole.
Renin release: what turns it up and down
Renin is an aspartyl protease that converts angiotensinogen to angiotensin I, the rate-limiting step of the RAAS. ACE then makes angiotensin II, which constricts blood vessels (including both glomerular arterioles), raises sympathetic outflow, and stimulates aldosterone and vasopressin release. Aldosterone drives Na⁺ reabsorption and K⁺ excretion. The full cascade is in the RAAS question breakdown.
| Renin goes UP | Renin goes DOWN |
|---|---|
| Low renal perfusion pressure sensed by JG cells (hypovolemia, blood loss, renal artery stenosis) | High afferent arteriolar pressure |
| Low NaCl delivery to the macula densa (PGE2, NO) | High NaCl delivery to the macula densa |
| Sympathetic beta-1 stimulation via the renal nerves | Beta-blockers |
| Loss of angiotensin II negative feedback (ACE inhibitors, ARBs) | Angiotensin II (negative feedback) |
| Loop diuretics acting at the macula densa | NSAIDs (no prostaglandin signal) |
Tubuloglomerular feedback vs myogenic autoregulation
Two local mechanisms keep renal blood flow and GFR steady when blood pressure changes; both act on the afferent arteriole.
| Myogenic mechanism | Tubuloglomerular feedback | |
|---|---|---|
| Sensor | Smooth muscle of the afferent arteriole itself | Macula densa |
| Trigger | Stretch from higher pressure | Higher NaCl and flow at the end of the loop |
| Response | Afferent smooth muscle contracts | ATP and adenosine constrict the afferent arteriole |
| Extra role | — | The same sensor also tunes renin release |
Pressure ranges and the efferent side of the story are in renal blood flow autoregulation. Strong sympathetic activity constricts the afferent arterioles and cuts renal blood flow.
Drugs and diseases that work through the JGA
| Drug or condition | What happens at the JGA | Exam consequence |
|---|---|---|
| NSAIDs | Block the prostaglandins that dilate the afferent arteriole and signal renin release | AKI when renal perfusion depends on prostaglandins (dehydration, heart failure, CKD, liver disease, older age, diuretics, ACE inhibitors or ARBs); hyperkalemia from hyporeninemic hypoaldosteronism |
| ACE inhibitors, ARBs | Less angiotensin II action (ACE inhibitors lower its level; ARBs block its AT1 receptor), so less efferent constriction and no negative feedback, so plasma renin rises | GFR can fall sharply when kidney function depends on the RAAS, as in renal artery stenosis, CKD, severe heart failure or volume depletion; hyperkalemia (ACE inhibitors vs ARBs) |
| Beta-blockers | Block beta-1 receptors on JG cells | Lower renin release, a possible contributor to their antihypertensive effect |
| Loop diuretics | Block NKCC2, the transporter the macula densa uses to sense NaCl; luminal bumetanide increases renin secretion experimentally | Renin rises; the same NKCC2 blockade flattens the medullary gradient (countercurrent multiplier) |
| SGLT2 inhibitors | Less proximal Na⁺ reabsorption, so more Na⁺ reaches the distal tubule and macula densa | Lower intraglomerular pressure, which the FDA label says is believed to reflect increased tubuloglomerular feedback |
| Renal artery stenosis | JG cells of the affected kidney sense low perfusion and release renin | Secondary hyperaldosteronism with high renin; resistant or abruptly worsening hypertension, flash pulmonary edema; a systolic-diastolic abdominal bruit is almost pathognomonic but often absent (renal artery stenosis) |
| Primary aldosteronism | Aldosterone is autonomous, so volume expansion suppresses renin | Low renin, high aldosterone; Merck's screening cut-off is an aldosterone-to-renin ratio over 20 (ng/dL per ng/mL/hour), with assay-dependent variation |
Renal artery stenosis in one line: atherosclerosis causes about 80% (more common in men over 50; proximal third of the renal artery) and fibromuscular dysplasia about 20% (younger patients, usually women; distal two-thirds of the main renal artery and its branches).
How USMLE tests the JGA
- "Which cells secrete renin?" JG (granular) cells of the afferent arteriole, not the macula densa.
- "Which cells sense NaCl?" The macula densa, not the JG cells (they sense pressure and beta-1 input).
- Wrong arteriole: tubuloglomerular feedback and the myogenic reflex act on the afferent arteriole; angiotensin II blockade relaxes the efferent one.
- Direction errors: more NaCl at the macula densa means less renin and lower GFR; less NaCl means more renin and afferent dilation.
- Renin sorts hyperaldosteronism: high renin plus high aldosterone = secondary (for example renal artery stenosis); low renin plus high aldosterone = primary (Conn syndrome).
- Hyperkalemia stems: an older patient with CKD on an ACE inhibitor who starts daily ibuprofen and develops high potassium = hyporeninemic hypoaldosteronism plus RAAS blockade.
Practice question
A 61-year-old man with type 2 diabetes, hypertension and albuminuric chronic kidney disease takes lisinopril. Dapagliflozin is added, and over the next weeks his urine albumin excretion falls. Which of the following best explains the drop in intraglomerular pressure caused by the new drug?
A. Adenosine-mediated constriction of the afferent arteriole B. Dilation of the efferent arteriole from reduced angiotensin II C. Increased renin release from juxtaglomerular cells D. Prostaglandin-mediated dilation of the afferent arteriole E. Blockade of beta-1 receptors on juxtaglomerular cells
Answer: A. SGLT2 inhibition leaves more sodium (with chloride) in the tubule, so more NaCl reaches the macula densa. The macula densa reads this as "filtration is too high" and releases ATP and adenosine, which constrict the afferent arteriole and lower glomerular pressure. The dapagliflozin label says its lowering of intraglomerular pressure is believed to be mediated by increased tubuloglomerular feedback.
- B: reducing angiotensin II relaxes the efferent arteriole. That is how lisinopril lowers glomerular pressure, and it is why ACE inhibitors can drop GFR when renal function depends on the RAAS, but it is not dapagliflozin's mechanism.
- C: extra NaCl at the macula densa suppresses renin; renin rises with low NaCl, low perfusion pressure or beta-1 stimulation.
- D: prostaglandin-mediated afferent dilation is the low-NaCl response (the one NSAIDs remove); it would raise glomerular pressure.
- E: beta-1 blockade on JG cells is how beta-blockers lower renin; dapagliflozin does not block beta receptors.
Key takeaways
- JGA = macula densa + JG (granular) cells + extraglomerular mesangial cells, where a nephron's TAL-DCT junction touches its own afferent arteriole.
- Macula densa senses NaCl through NKCC2; JG cells secrete renin and sense afferent pressure and beta-1 input.
- High NaCl → ATP and adenosine → afferent constriction → lower GFR (tubuloglomerular feedback); high NaCl also means less renin.
- Low NaCl → PGE2 and NO → renin release and afferent dilation.
- Renin rises with low perfusion pressure, low macula densa NaCl, beta-1 stimulation, ACE inhibitors and ARBs, and loop diuretics; it falls with angiotensin II, beta-blockers and NSAIDs.
- NSAIDs cause hyporeninemic hypoaldosteronism (hyperkalemia) and AKI in prostaglandin-dependent kidneys.
- SGLT2 inhibitors lower glomerular pressure, believed to be through increased tubuloglomerular feedback.
Sources
- Biochemistry, Renin — StatPearls, NCBI Bookshelf (2023)
- Regulation of Renal Blood Flow (25.7) — OpenStax Anatomy and Physiology 2e
- Endocrine Regulation of Kidney Function (25.8) — OpenStax Anatomy and Physiology 2e
- Macula Densa: textbook excerpts incl. Seldin and Giebisch's The Kidney — ScienceDirect Topics (Elsevier)
- Hypertension — Merck Manual Professional Edition (2026)
- Renovascular Hypertension — Merck Manual Professional Edition (2025)
- Primary Aldosteronism — Merck Manual Professional Edition (2026)
- Celebrex (celecoxib) prescribing information — DailyMed, NLM (2024)
- Zestril (lisinopril) prescribing information — DailyMed, NLM (2024)
- Cozaar (losartan) prescribing information — DailyMed, NLM (2025)
- Inderal LA (propranolol) prescribing information — DailyMed, NLM (2026)
- Farxiga (dapagliflozin) prescribing information — DailyMed, NLM (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
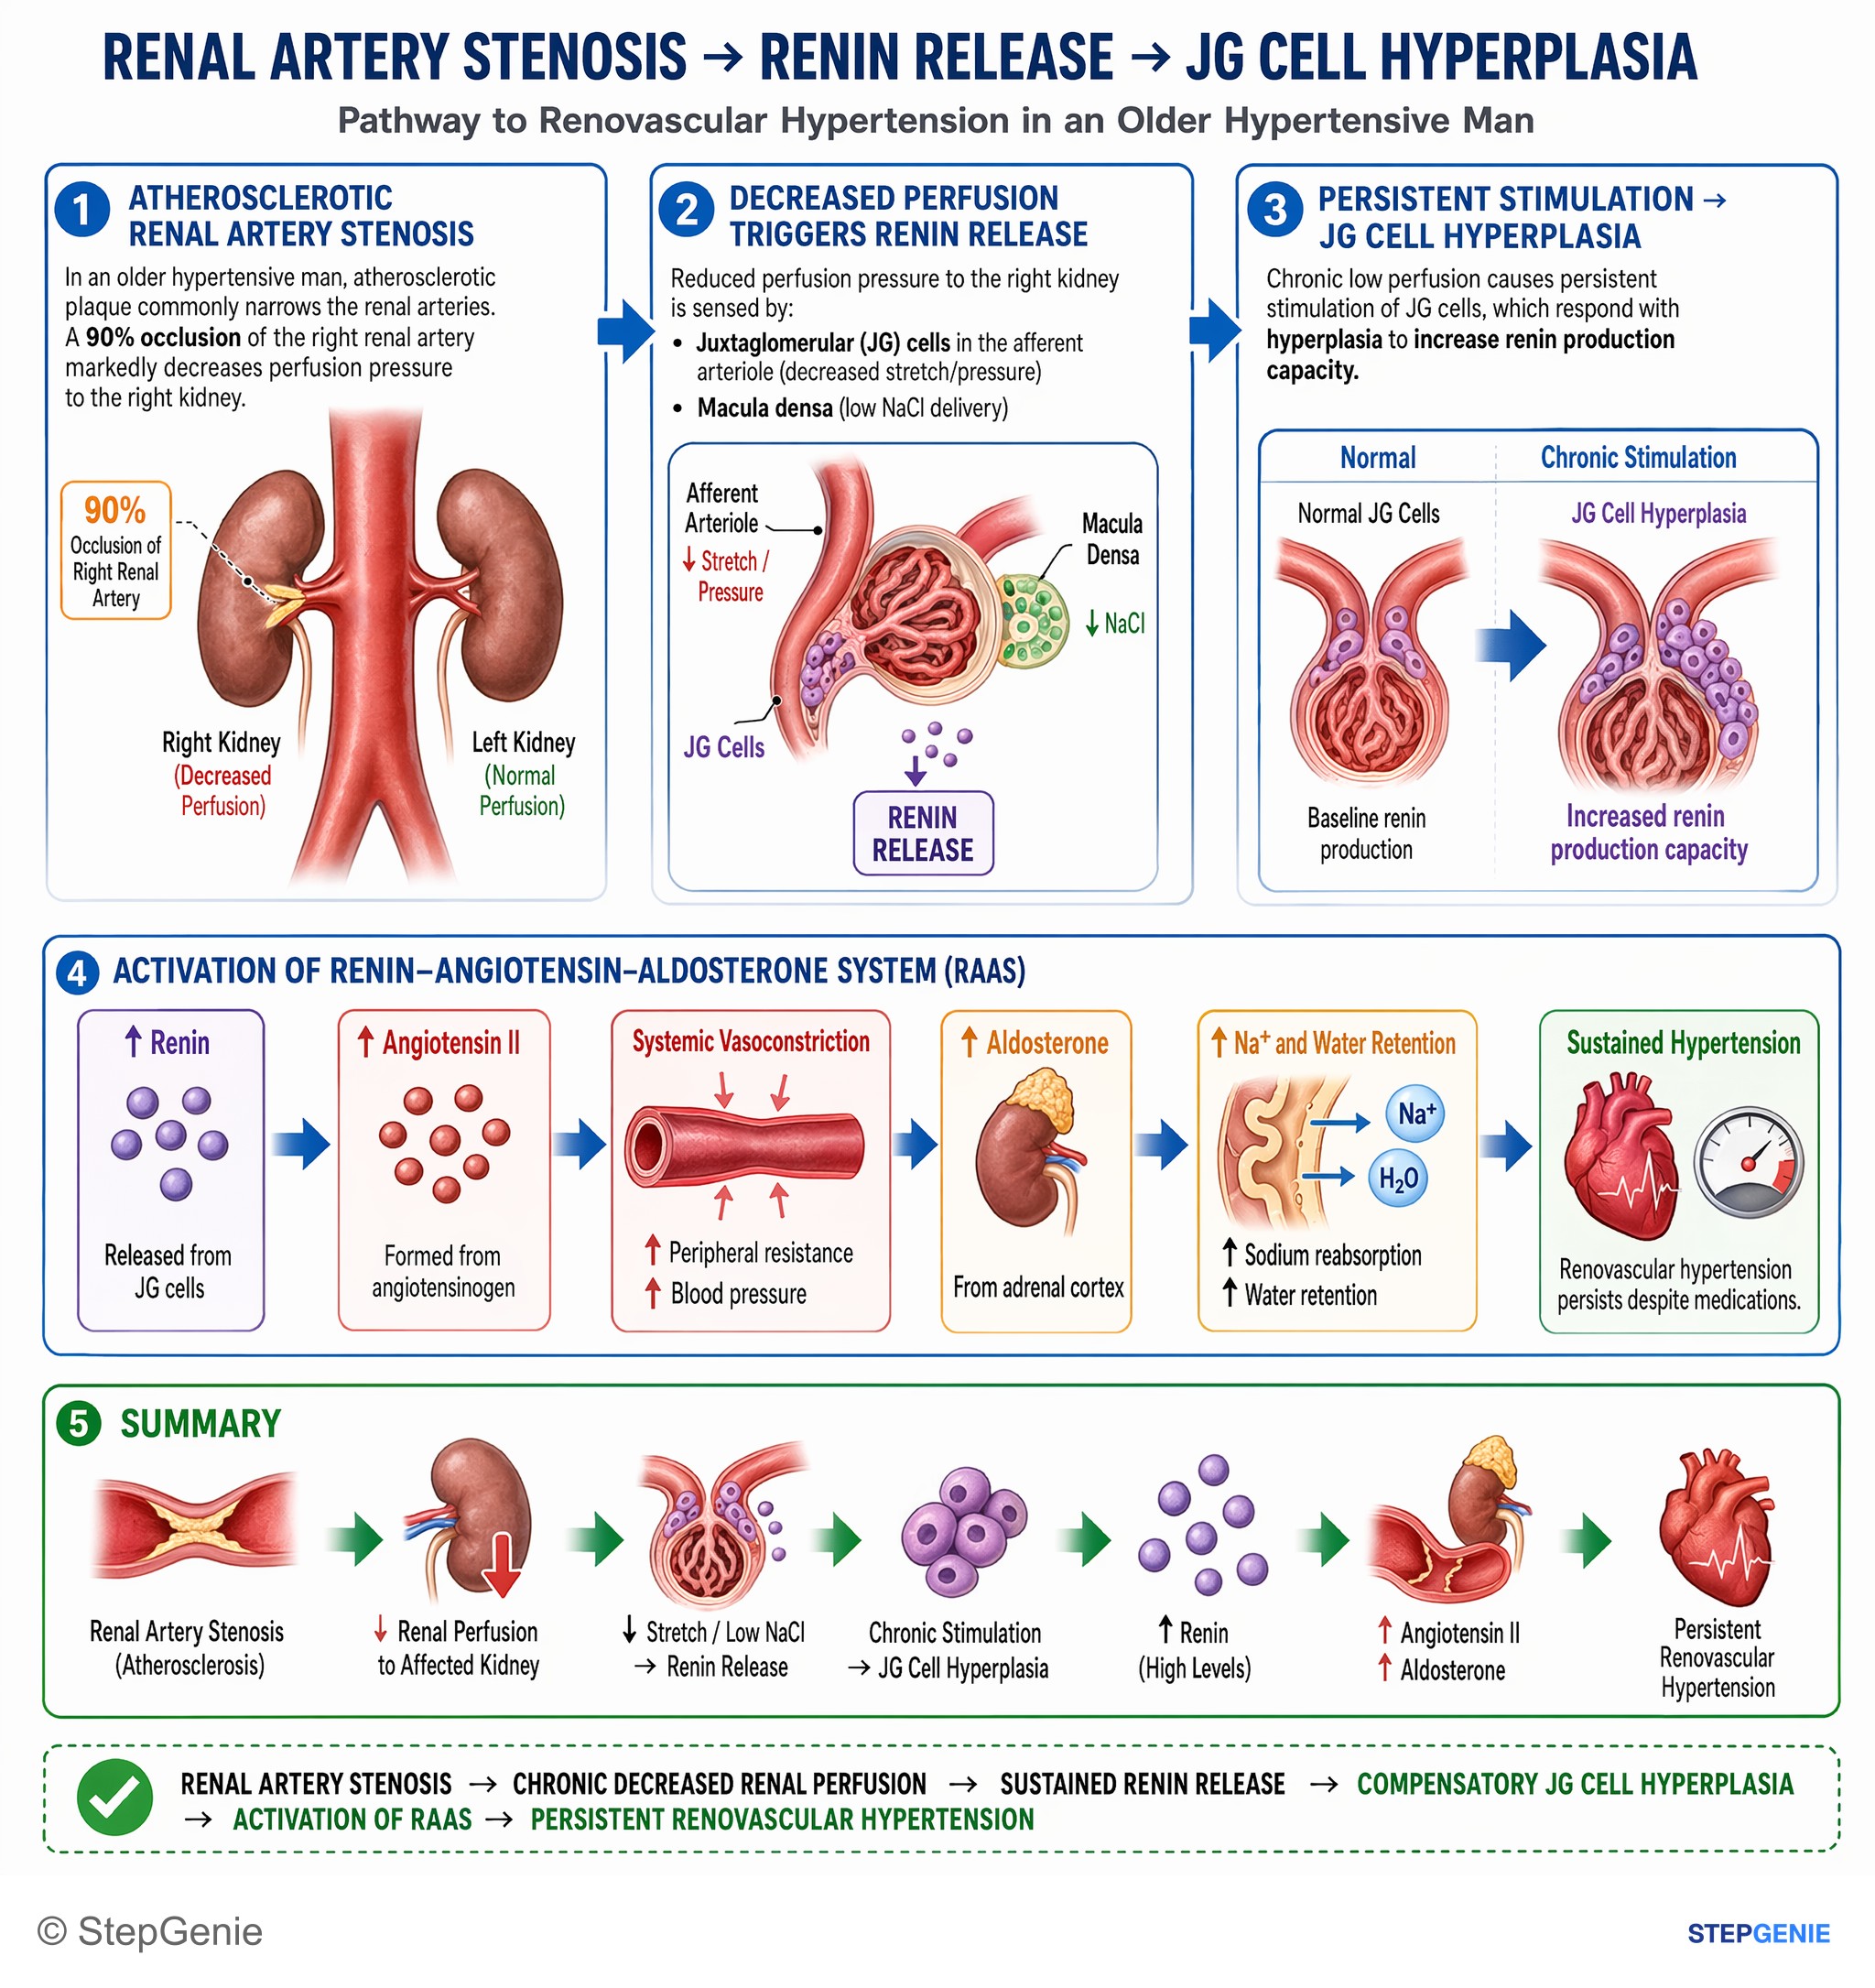
Renal artery stenosis → chronic decreased renal perfusion → sustained renin release → compensatory juxtaglomerular cell hyperplasia in the…
USMLE Step 1Frequently Asked Questions
What are the three parts of the juxtaglomerular apparatus?
The juxtaglomerular apparatus has three parts. The macula densa is a patch of specialized tubular cells at the junction of the thick ascending limb and distal convoluted tubule that senses NaCl. The juxtaglomerular, or granular, cells are modified smooth muscle cells in the wall of the afferent arteriole that secrete renin. The extraglomerular mesangial, or lacis, cells sit between them. All three lie where a nephron's tubule touches the vascular pole of its own glomerulus.
What does the macula densa sense and what does it release?
The macula densa senses the NaCl delivered to the end of the loop of Henle, using the Na-K-2Cl cotransporter (NKCC2), as a readout of upstream filtration. When NaCl delivery is high, it releases ATP and adenosine, which constrict the afferent arteriole and lower GFR, and renin release is suppressed. When NaCl delivery is low, it releases prostaglandin E2 and nitric oxide, which stimulate renin release from juxtaglomerular cells and relax the afferent arteriole.
What stimulates renin release from juxtaglomerular cells?
Three main signals increase renin release: low renal perfusion pressure sensed by the juxtaglomerular cells themselves, low NaCl delivery to the macula densa, and sympathetic stimulation of beta-1 receptors. ACE inhibitors and ARBs also raise renin by removing angiotensin II negative feedback, and loop diuretics raise it by blocking NaCl sensing at the macula densa. Angiotensin II, high NaCl delivery, beta-blockers and NSAIDs lower renin release.
What is tubuloglomerular feedback?
Tubuloglomerular feedback is a local loop that keeps each nephron's GFR stable. If GFR rises, more NaCl reaches the macula densa, which releases ATP and adenosine to constrict the afferent arteriole of the same glomerulus, bringing GFR back down; if GFR falls, the afferent arteriole relaxes. It works alongside the myogenic response of the afferent arteriole, and SGLT2 inhibitors are thought to lower intraglomerular pressure by strengthening it.
How do NSAIDs affect the juxtaglomerular apparatus?
NSAIDs block prostaglandin synthesis, removing a signal that dilates the afferent arteriole and stimulates renin release. In people whose kidneys depend on prostaglandins to maintain blood flow, such as those with dehydration, heart failure, chronic kidney disease, liver disease or older age, or those taking diuretics, ACE inhibitors or ARBs, this can cause acute kidney injury. NSAIDs can also cause hyperkalemia through a hyporeninemic hypoaldosteronism state, even with normal kidney function.
How do SGLT2 inhibitors act on the juxtaglomerular apparatus?
SGLT2 inhibitors such as dapagliflozin block sodium and glucose reabsorption in the proximal tubule, so more sodium reaches the distal nephron and the macula densa. The macula densa responds as if filtration were too high, triggering afferent arteriolar constriction through tubuloglomerular feedback. The dapagliflozin label says the resulting fall in intraglomerular pressure is believed to be mediated by this increased tubuloglomerular feedback, one proposed way these drugs protect the kidney.