ADH questions are the kind that look “simple” until your brain mixes up water vs sodium, osmolarity vs volume, and serum vs urine. Here’s a quick, shareable acronym trick that locks the whole ADH/water-balance story into place—plus the high-yield USMLE facts that ride along with it.
The Acronym Trick: ADH = “Adds DiHydration”
One-liner
ADH “adds dihydration” by inserting Aquaporin-2 in the collecting duct → you reabsorb free water → urine becomes concentrated.
Visual (mental image)
Picture ADH as a bouncer at the collecting duct who opens “A2 doors” (Aquaporin-2) so water can slip back into the blood, leaving less water in the urine.
A2 = Aquaporin-2 = ADH effect
(If you remember only one thing: ADH → AQP2 → water reabsorption)
The 4-Box ADH Snapshot (Memorize This Table)
| Variable | With High ADH | With Low ADH |
|---|---|---|
| Collecting duct water permeability | ↑ (AQP2 inserted) | ↓ (AQP2 removed) |
| Urine osmolarity | ↑ (concentrated) | ↓ (dilute) |
| Urine volume | ↓ | ↑ |
| Serum osmolarity | ↓ (water retained) | ↑ (water lost) |
High-yield translation:
- ADH ON → concentrate urine, conserve water
- ADH OFF → dilute urine, dump water
Where ADH Works (USMLE Favorite)
Primary site: Collecting duct principal cells
- ADH binds V2 receptor (Gs) on basolateral membrane
- ↑ cAMP → AQP2 inserted into the apical membrane
- Water then exits basolaterally via AQP3/4 (constitutively present)
Micro-pearls:
- V2 = kidney water (collecting duct)
- V1 = vasoconstriction (more on that below)
What Triggers ADH Release? (Two Big Inputs)
1) Osmolarity (most sensitive)
- ↑ plasma osmolality → hypothalamic osmoreceptors → ↑ ADH
- Even small changes in osmolality can move ADH a lot.
2) Effective circulating volume (most urgent when severe)
- ↓ volume/pressure → baroreceptors (carotid sinus/aortic arch) → ↑ ADH
- When volume is very low, the body prioritizes perfusion—even if it worsens osmolality.
Board-style takeaway:
Severe hypovolemia can cause high ADH even with low plasma osmolality.
ADH Does More Than Water: The “Urea + Vessels” Add-ons
Urea recycling (helps concentrate urine)
ADH increases urea permeability in the inner medullary collecting duct, strengthening the medullary gradient. This is part of why ADH makes urine really concentrated.
Vasoconstriction via V1 (especially at high levels)
- V1 receptor (Gq) → vasoconstriction
- Clinically relevant: very high ADH (or analogs) can support BP.
High-Yield Clinical Patterns You’ll Be Asked to Recognize
Central vs nephrogenic diabetes insipidus (DI)
Core idea: DI = can’t concentrate urine → polyuria + dilute urine
| Condition | ADH level | Urine osm | Response to desmopressin |
|---|---|---|---|
| Central DI (↓ ADH production) | ↓ | ↓ | Urine osm ↑ (improves) |
| Nephrogenic DI (kidney unresponsive) | ↑ | ↓ | Minimal/no change |
Classic causes (Step-style):
- Central DI: head trauma, neurosurgery, pituitary issues
- Nephrogenic DI: lithium, demeclocycline, hypercalcemia, hypokalemia
SIADH
Core idea: too much ADH → water retention → hyponatremia + low serum osmolality
Typical findings:
- Low serum Na+, low serum osmolality
- Inappropriately concentrated urine (urine osm not maximally dilute)
- Urine Na+ often elevated (due to mild volume expansion → natriuresis)
Common associations:
- Small cell lung carcinoma (ectopic ADH)
- CNS pathology, pulmonary disease
- SSRIs, carbamazepine, cyclophosphamide (drug triggers)
Rapid-Fire Mnemonics (Shareable)
1) “ADH Adds Aquaporin-2”
- ADH → AQP2 insertion → water reabsorption → concentrated urine
2) “DI = Dilute Inside (urine)”
- Diabetes insipidus → huge volume of dilute urine
3) “SIADH = Soaked In ADH”
- Too much ADH → water retained → hyponatremia
Quick Practice: 3 One-Liners (Test Yourself)
- High ADH → low urine volume, high urine osm, lower serum osm
- Low ADH → high urine volume, low urine osm, higher serum osm
- Desmopressin improves urine concentration in central DI, not nephrogenic DI
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
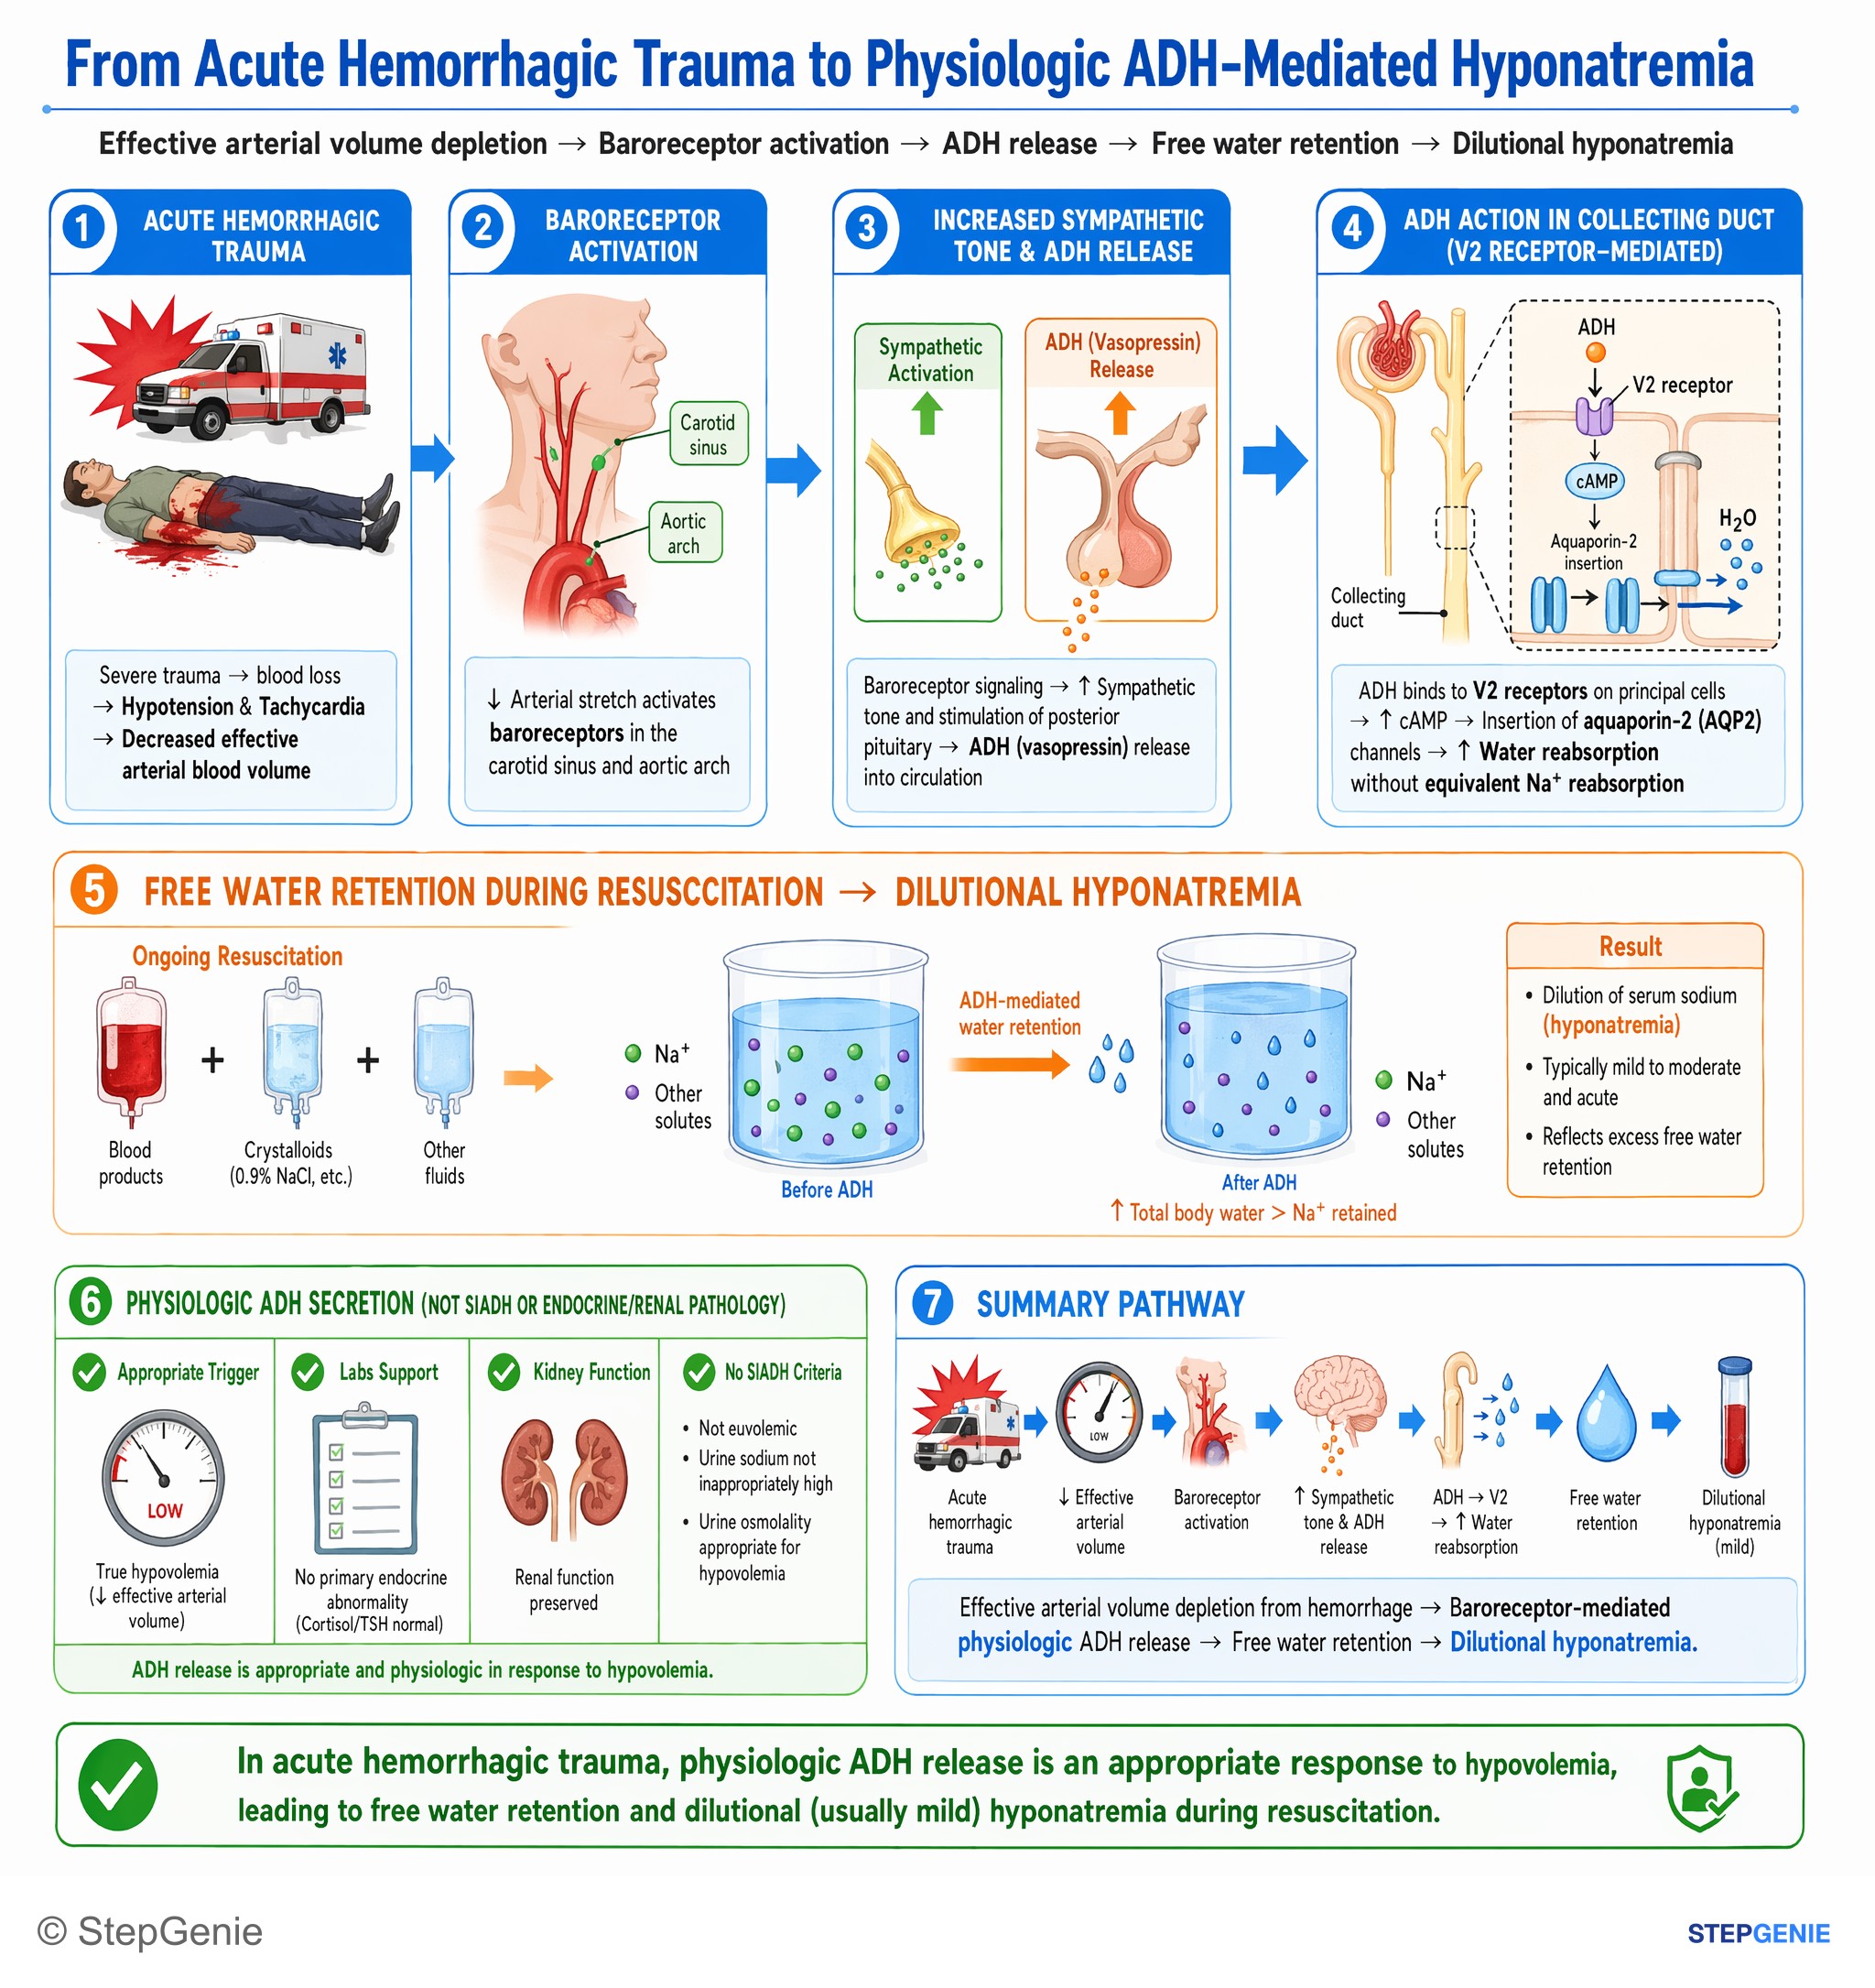
Acute hemorrhagic trauma → effective arterial volume depletion → baroreceptor-mediated physiologic ADH release → free water retention →…
USMLE Step 1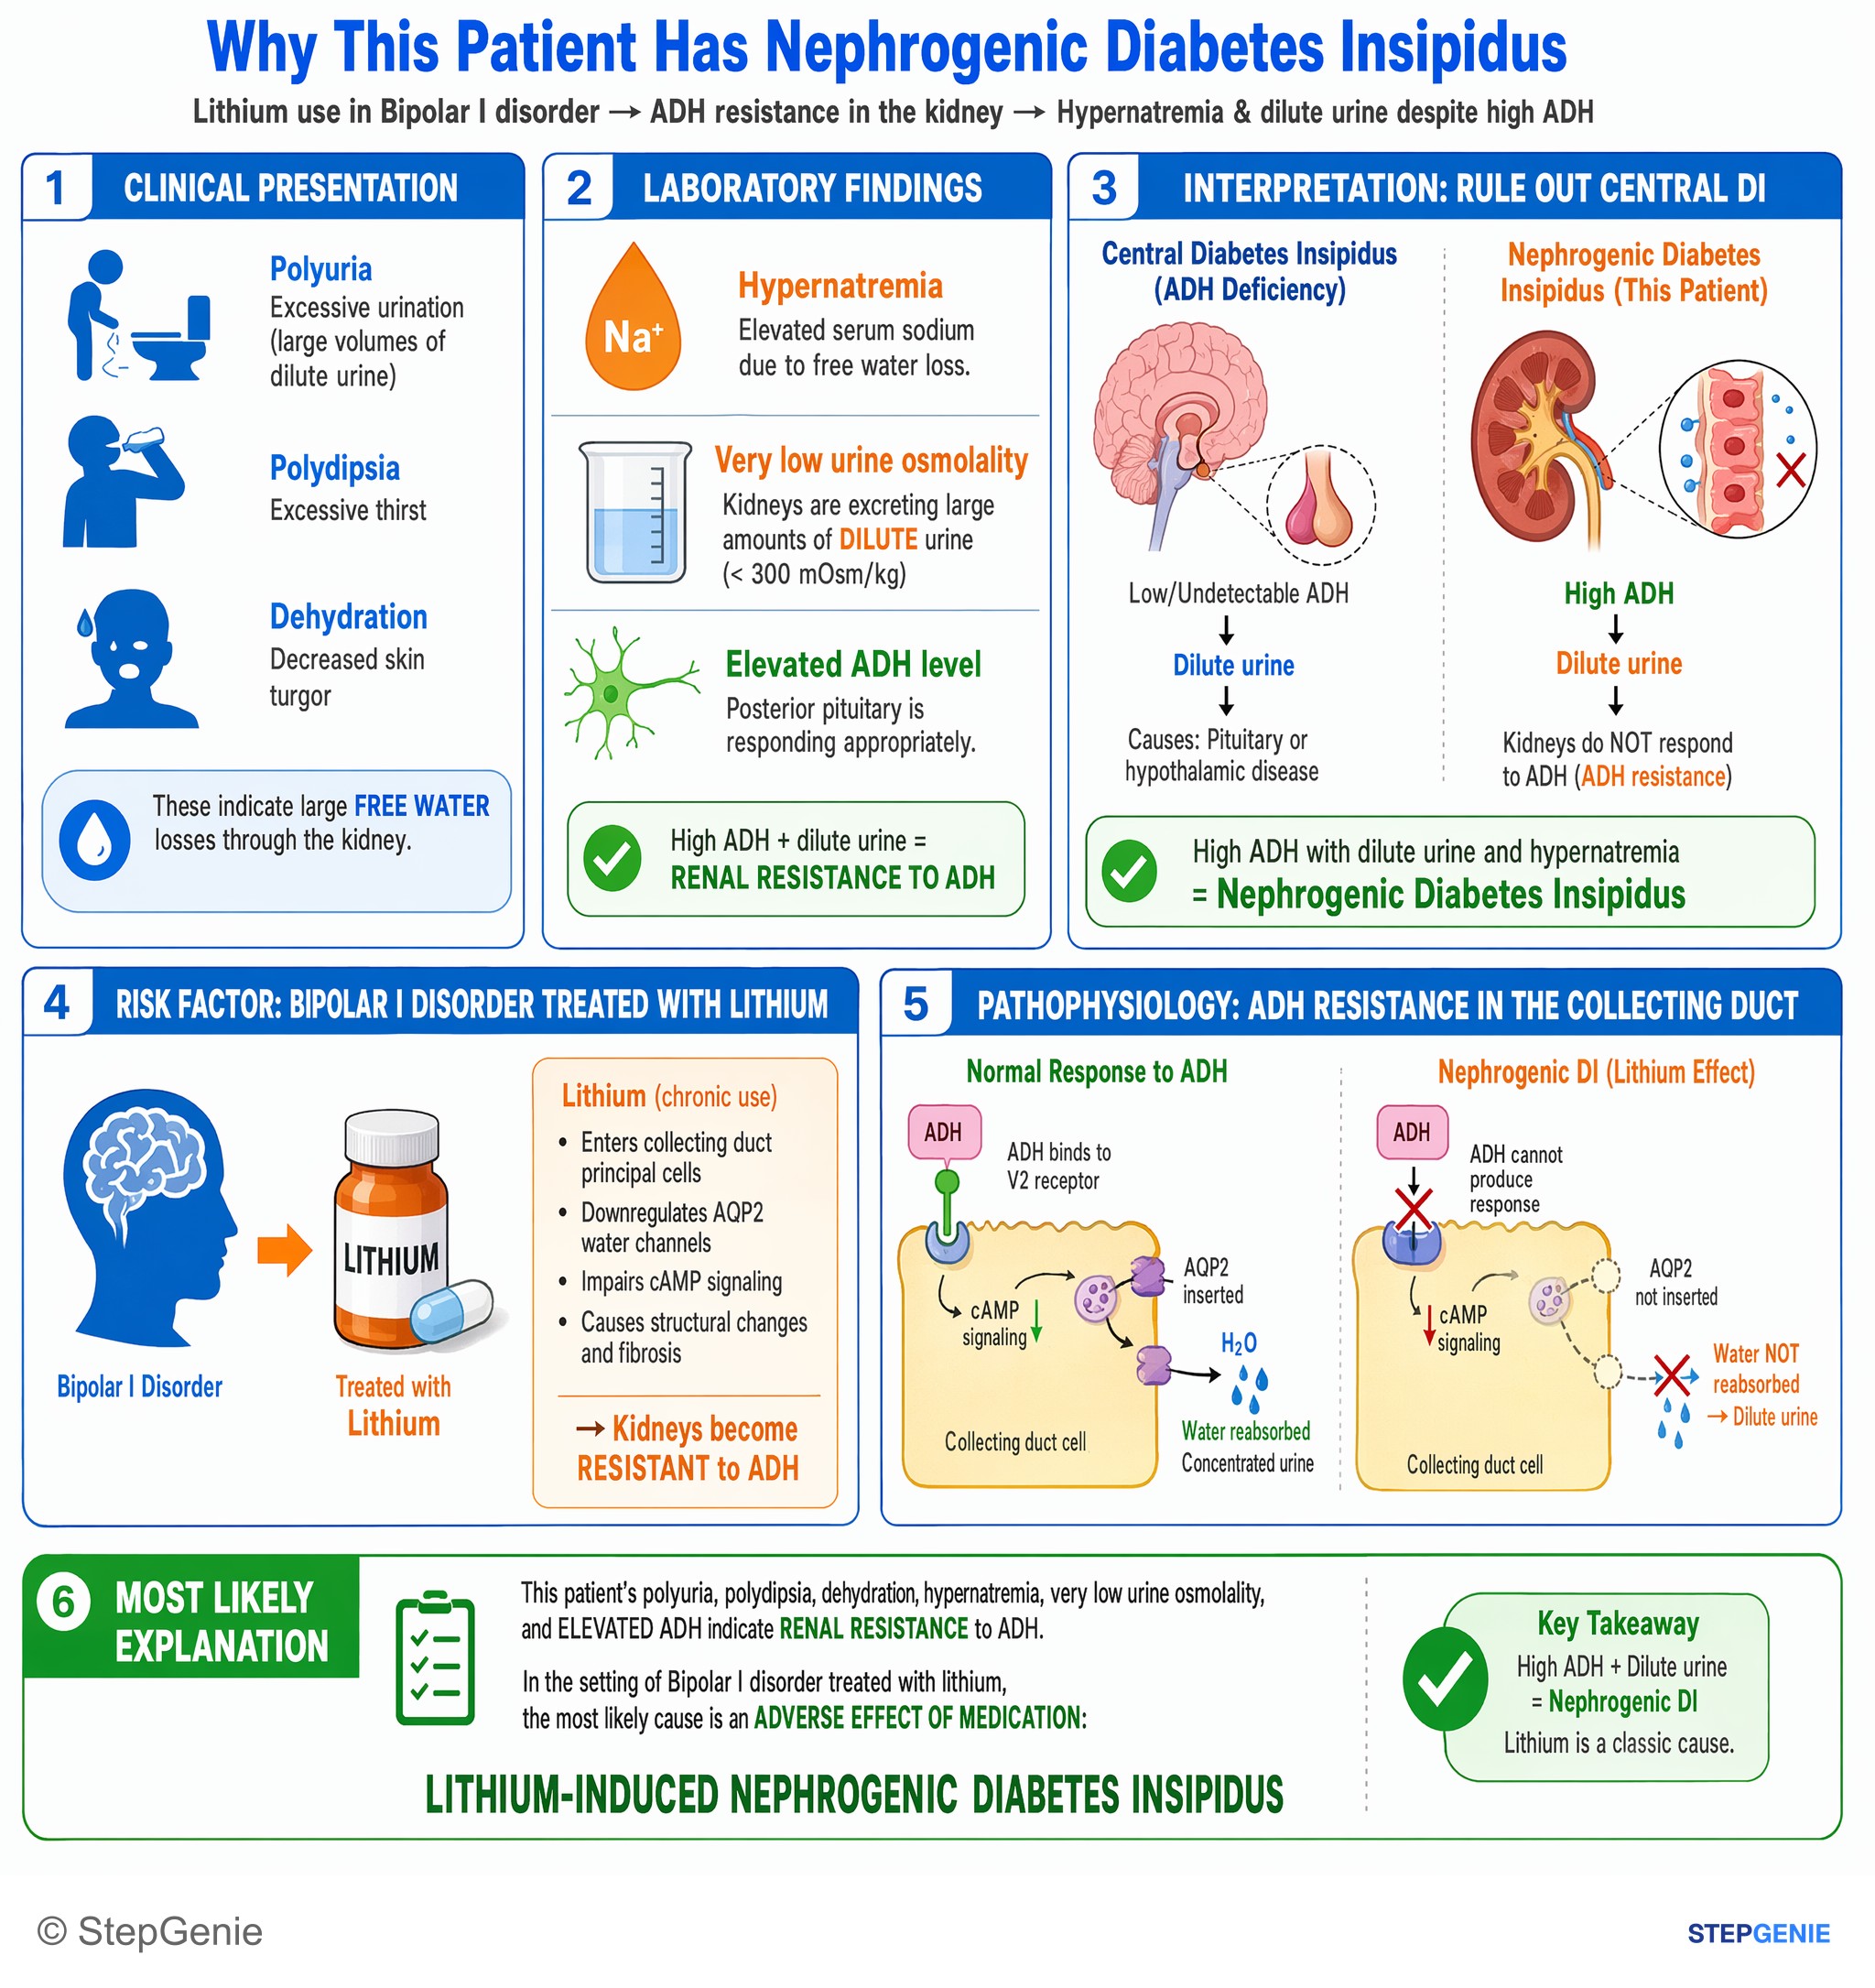
Nephrogenic diabetes insipidus from chronic lithium use in bipolar I: kidneys become ADH-resistant → hypernatremia + low urine osmolality…
USMLE Step 1Frequently Asked Questions
How does ADH make urine more concentrated?
ADH makes urine more concentrated by inserting Aquaporin-2 channels into collecting duct principal cells, which increases water reabsorption. It binds the V2 receptor on the basolateral membrane, raises cAMP, and places AQP2 in the apical membrane. Water then moves back into the blood, so less water stays in the urine, urine osmolarity rises, and urine volume falls.
What happens to urine volume, urine osmolarity, and serum osmolarity when ADH is high?
High ADH causes low urine volume, high urine osmolarity, and lower serum osmolarity. The key reason is that ADH increases collecting duct water permeability by inserting AQP2, so the kidney reabsorbs more free water. That conserves water and concentrates the urine, while retained water lowers serum osmolarity.
What triggers ADH release the most?
The most sensitive trigger for ADH release is increased plasma osmolality. Hypothalamic osmoreceptors respond even to small changes in osmolality and can markedly increase ADH. Low effective circulating volume also raises ADH through baroreceptors in the carotid sinus and aortic arch, and in severe hypovolemia this volume signal can dominate even if plasma osmolality is low.
How do you tell central diabetes insipidus from nephrogenic diabetes insipidus?
You distinguish central from nephrogenic diabetes insipidus by the desmopressin response and the underlying ADH status. Both cause polyuria with dilute urine because the patient cannot concentrate urine. In central DI, ADH production is low and desmopressin increases urine osmolarity. In nephrogenic DI, ADH is high because the kidney is unresponsive, so desmopressin causes minimal or no change.
Why does SIADH cause hyponatremia with concentrated urine?
SIADH causes hyponatremia with concentrated urine because excess ADH retains water while still making the collecting duct reabsorb water efficiently. That added water lowers serum sodium and serum osmolality, but the urine remains inappropriately concentrated instead of becoming maximally dilute. Urine sodium is often elevated as mild volume expansion promotes natriuresis.