Atypical pneumonia is pneumonia caused by organisms that a Gram stain and routine culture miss and that beta-lactams don't treat. The classic trio is Mycoplasma pneumoniae, Chlamydia pneumoniae and Legionella pneumophila; respiratory viruses and animal-borne infections (psittacosis, Q fever, tularemia, hantavirus) are the look-alikes. These pneumonias are often clinically indistinguishable from typical pneumonia, so exam stems hand you an exposure plus an extrapulmonary clue: a dorm student with cold agglutinins (Mycoplasma), a hotel guest with diarrhea, confusion and hyponatremia (Legionella), a parrot owner (C. psittaci). Treat with a macrolide, doxycycline or a respiratory fluoroquinolone, and remember that the Legionella urinary antigen detects only L. pneumophila serogroup 1.
What makes a pneumonia "atypical"
- The organism defines it, not the X-ray. Mycoplasma has no cell wall (hard to see on Gram stain, inherently resistant to beta-lactams); C. pneumoniae grows only inside host cells; Legionella needs selective media such as buffered charcoal yeast extract (BCYE) agar.
- How common: atypical bacteria cause about 3-11% of community-acquired pneumonia (CAP), viruses up to 30% (Merck).
- Exam lore vs reality: the classic stem is "walking pneumonia" with an X-ray that looks worse than the patient, but Merck notes that chlamydial and mycoplasmal pneumonias are often clinically indistinguishable from other pneumonias, which is one reason most empiric CAP regimens include atypical coverage (amoxicillin alone for healthy outpatients is the exception).
The visual hack: map where the patient breathed it in
Picture a small town. Each building is one organism; the stem tells you which building the patient walked out of.
| Picture this | Organism | Clinching clue | Test / drug |
|---|---|---|---|
| College dorm, barracks, summer camp | Mycoplasma pneumoniae | Child or young adult, weeks of dry cough, cold agglutinin hemolysis, rash or mucositis | NAAT (PCR) / macrolide; doxycycline or fluoroquinolone in adults |
| Hoarse family at the school gate | Chlamydia pneumoniae | Laryngitis, pharyngitis, a cough that lingers for weeks | NAAT / azithromycin; doxycycline or fluoroquinolone |
| Hotel hot tub, cruise ship, cooling tower | Legionella pneumophila | Older smoker, high fever, diarrhea, confusion, hyponatremia, raised AST/ALT | Urine antigen plus lower respiratory culture or PCR / levofloxacin or azithromycin |
| Pet shop parrot cage | Chlamydia psittaci | Abrupt fever, headache, dry cough, pulse-temperature dissociation, splenomegaly | PCR or serology / doxycycline |
| Lambing or calving barn | Coxiella burnetii (Q fever) | Dust from birth products; prolonged fever, low platelets, high liver enzymes | Serology, PCR in week 1 / doxycycline |
| Rabbit carcass, tick or deer fly | Francisella tularensis | Pneumonic tularemia: pleuritic pain, hilar nodes, effusion | Culture, PCR, serology / gentamicin (first if severe), ciprofloxacin, levofloxacin or doxycycline |
| Dusty cabin with mouse droppings | Hantavirus | Flu-like illness, then pulmonary edema and shock | IgM ELISA, PCR / supportive care, ECMO |
| Nursery, infant aged 1-3 months | Chlamydia trachomatis | Usually afebrile, staccato cough, tachypnea, eosinophilia | Nasopharyngeal testing / oral erythromycin or azithromycin |
| Winter waiting room | Influenza, RSV, other viruses | Season, myalgias, positive viral PCR | Rapid molecular test / oseltamivir for influenza |
Two-step rule: first ask "does this look atypical?", then "where was the air?". The exposure usually decides the answer before the labs do.
The core trio side by side
| Mycoplasma pneumoniae | Chlamydia pneumoniae | Legionella pneumophila | |
|---|---|---|---|
| Organism | No cell wall | Obligate intracellular | Gram-negative rod living in freshwater amebas |
| Spread | Droplets; crowded settings | Droplets and fomites | Inhaled warm-water aerosols; not person to person |
| Incubation | 1-4 weeks | 3-4 weeks | 2-10 days |
| Typical host | Children (including under 5), students, recruits | School-age children, young adults; reinfection in older adults | Age 50 or older, smokers, chronic lung disease, immunosuppression |
| Signature clue | Cold agglutinins, rash or mucositis | Usually mild; sometimes laryngitis or pharyngitis; cough lasting weeks | GI symptoms, confusion, hyponatremia, relative bradycardia |
| Best test | NAAT (serology lacks specificity) | NAAT | Urine antigen plus culture or PCR of sputum or BAL |
| Treatment | Macrolide; doxycycline; fluoroquinolone (adults) | Azithromycin; doxycycline; fluoroquinolone | Respiratory fluoroquinolone or azithromycin |
C. pneumoniae is the quiet one: mostly mild, with outbreaks in families, dorms and military camps, and in vitro resistance to penicillin, ampicillin and sulfa drugs (CDC). Older texts call it Chlamydophila; see the Chlamydophila pneumoniae cheat sheet.
Mycoplasma pneumoniae: no wall, cold agglutinins
- No cell wall → beta-lactams fail. The classic stem is a teenager who did not improve on amoxicillin. More hooks are in the Mycoplasma pneumoniae acronym.
- Who: most common in children; outbreaks in colleges, military training and detention facilities. CDC reported a large rise in 2024, including in young children.
- Disease: tracheobronchitis, pharyngitis or pneumonia (unilateral or bilateral bronchopneumonia), asthma flares, lasting weeks to months. Outside the lungs: hemolytic anemia, encephalitis, arthralgias and reactive infectious mucocutaneous eruption (RIME).
- Cold agglutinins: IgM against the I antigen; the direct antiglobulin test is positive for C3, negative for IgG. EBV (anti-i) and idiopathic disease do the same, so this supports Mycoplasma rather than proving it. Bullous myringitis is the classic exam link, but Merck lists viral and S. pneumoniae causes too.
- Diagnosis and treatment: NAAT is preferred (CDC). Macrolide for children and adults, doxycycline for older children and adults, fluoroquinolone for adults. Macrolide resistance has stayed under 10% in the US; if a patient isn't improving on a macrolide, switch (for example, to doxycycline).
Legionella: water, weird labs and the urine antigen trap
- Source: grows in warm water (77-104°F) biofilms and is inhaled from showers, hot tubs, decorative fountains and cooling towers; essentially no person-to-person spread. Pontiac fever is the mild, self-limited flu-like form without pneumonia.
- Clues: high fever, headache or confusion, watery diarrhea, relative bradycardia; labs show hyponatremia, hypophosphatemia and raised aminotransferases; X-ray shows patchy, rapidly progressive, asymmetric infiltrates.
- The urine antigen trap: 60-95% sensitive and over 98% specific from about day 3, but it detects only L. pneumophila serogroup 1, which causes 65-90% of cases (Merck). CDC advises ordering both the antigen and a culture or molecular test of a lower respiratory specimen. Blood cultures are unreliable. ATS/IDSA (2019) suggests antigen testing only in severe CAP or with an outbreak or recent travel.
- Treatment: a respiratory fluoroquinolone (levofloxacin or moxifloxacin, 7-14 days) is Merck's preferred regimen; azithromycin (5-10 days) also works. Case fatality is about 10%, about 25% if healthcare-associated (CDC). Work through a case in the Legionella pneumophila question breakdown.
Viruses and zoonoses: the look-alikes
Viruses cause up to 30% of CAP. ATS/IDSA (2019) recommends a rapid influenza molecular test when influenza is circulating and antiviral treatment such as oseltamivir for influenza-positive CAP regardless of symptom duration. A positive viral test doesn't automatically mean no antibiotics: the 2025 ATS update suggests withholding them only for outpatients without comorbidities. IDSA did not endorse that guideline, mainly over its advice to treat virus-positive outpatients with comorbidities and nonsevere inpatients. Details: the viral pneumonia mnemonic.
- Psittacosis: inhaled dust from dried droppings or secretions of infected birds (pet shops, poultry plants); incubation 5-14 days. Doxycycline, because macrolide failures are reported; macrolides for children and pregnancy.
- Q fever: Coxiella is shed in the placenta, amniotic fluid, milk, urine and feces of goats, sheep and cattle; expect prolonged fever, low platelets, a normal white count and raised liver enzymes. Under 5% develop chronic Q fever, mostly endocarditis that routine blood cultures miss. Acute disease: doxycycline for 14 days.
- Pneumonic tularemia: follows inhaling F. tularensis (dust or aerosols) or spread from untreated tularemia of another form. CDC's 2025 recommendations make ciprofloxacin, levofloxacin, gentamicin and doxycycline first-line, prefer an aminoglycoside first in severe illness and rule out doxycycline alone for severe disease. Streptomycin, the classic review-book answer, still works but is now a third-tier drug (more adverse effects than gentamicin, limited US availability).
- Hantavirus pulmonary syndrome: deer mouse urine, droppings or saliva; fatal in nearly 4 in 10; no specific antiviral, so supportive care and ECMO.
- Bird exposure has three classic answers: psittacosis (infection; doxycycline), histoplasmosis (fungus in soil heavy with bird or bat droppings; Ohio and Mississippi River valleys) and bird fancier's lung, a hypersensitivity pneumonitis with fever and dyspnea 4-8 hours after exposure and no infection.
Empiric treatment: where atypical coverage fits
Empiric regimens still come from the 2019 ATS/IDSA guideline:
| Setting | Regimen | Covers atypicals? |
|---|---|---|
| Outpatient, no comorbidities | Amoxicillin 1 g three times daily, or doxycycline 100 mg twice daily, or a macrolide (only where pneumococcal macrolide resistance is under 25%) | Not amoxicillin alone |
| Outpatient with comorbidities (chronic heart, lung, liver or kidney disease, diabetes, alcoholism, cancer, asplenia) | Amoxicillin-clavulanate or cefpodoxime/cefuroxime plus a macrolide or doxycycline, or a respiratory fluoroquinolone alone | Yes |
| Inpatient, nonsevere | Beta-lactam (ampicillin-sulbactam, ceftriaxone, cefotaxime or ceftaroline) plus a macrolide, or a respiratory fluoroquinolone alone | Yes |
| Inpatient, severe | Beta-lactam plus a macrolide or plus a respiratory fluoroquinolone | Yes |
- Add MRSA or Pseudomonas coverage for prior respiratory isolation of that organism. After recent hospitalization with IV antibiotics plus locally validated risk factors, add it empirically in severe CAP, but in nonsevere CAP obtain cultures and add it only if they are positive. Procalcitonin doesn't decide whether to start antibiotics.
- 2025 ATS update: stable outpatients and nonsevere inpatients can stop at 3-4 days (minimum 3); severe CAP gets at least 5; suspected Legionella or other intracellular organisms, S. aureus, Pseudomonas, empyema or abscess may need longer. Corticosteroids: recommended against in nonsevere CAP, suggested in severe CAP (not influenza). Practice in the community-acquired pneumonia question breakdown.
How USMLE tests it
- "Not better on amoxicillin" in a young patient: Mycoplasma; switch to azithromycin or doxycycline.
- Negative Legionella urine antigen: doesn't rule it out; send a lower respiratory culture or PCR.
- Pneumonia plus diarrhea, confusion and a sodium of 128: Legionella, not small cell carcinoma with SIADH.
- Afebrile infant aged 1-3 months, staccato cough, eosinophils ≥400/mm³: C. trachomatis; erythromycin for 14 days or azithromycin for 3 days (watch for pyloric stenosis under 6 weeks); treat the mother and her partners.
Practice question
A 58-year-old man who smokes has had fever, dry cough, watery diarrhea and confusion for 4 days. A week ago he stayed at a hotel and used its hot tub. Temperature is 39.7°C (103.5°F) and pulse is 84/min. Serum sodium is 127 mEq/L and AST is 110 U/L. Chest X-ray shows patchy right lower lobe infiltrates. A sputum Gram stain shows many neutrophils and few organisms. The Legionella urinary antigen test is negative. Which test is most likely to establish the diagnosis?
A. Blood cultures on routine media B. Cold agglutinin titer C. Culture of a lower respiratory specimen on buffered charcoal yeast extract agar D. Paired serology for Chlamydia psittaci E. Repeat Legionella urinary antigen in 48 hours
Answer: C. Hot tub exposure, diarrhea, confusion, hyponatremia, raised AST and relative bradycardia (pulse 84/min at 39.7°C) point to Legionnaires' disease. The urine antigen detects only L. pneumophila serogroup 1, so a negative result leaves other serogroups and species. CDC pairs it with culture on selective media (BCYE) or a molecular test of a lower respiratory specimen; PCR would be an equally good answer. Start levofloxacin or azithromycin without waiting for the result.
- A: Legionella doesn't grow on routine media, and blood cultures are unreliable for it.
- B: cold agglutinins suggest Mycoplasma, are nonspecific, and don't fit a water exposure with hyponatremia.
- D: psittacosis needs bird exposure, and paired serology answers only weeks later.
- E: by day 4 the antigen test is already in its sensitive window; repeating it still can't detect non-serogroup 1 infection.
Key takeaways
- Atypical = missed by Gram stain and routine culture, not treated by beta-lactams.
- Ask where the air came from: dorm (Mycoplasma), hot tub (Legionella), parrot (psittacosis), birthing barn (Q fever), rabbit or tick (tularemia), mouse droppings (hantavirus).
- Mycoplasma: no cell wall, IgM anti-I cold agglutinins, NAAT, macrolide first; US macrolide resistance under 10%.
- Legionella: diarrhea, confusion, hyponatremia; the urine antigen detects only serogroup 1, so pair it with culture or PCR.
- Guidelines: regimens from ATS/IDSA 2019; the 2025 ATS update shortens therapy for stable nonsevere CAP and suggests steroids in severe CAP.
Sources
- Diagnosis and Treatment of Adults with Community-acquired Pneumonia: Executive Summary — ATS/IDSA (2019)
- Diagnosis and Management of Community-acquired Pneumonia: An Official ATS Clinical Practice Guideline — American Journal of Respiratory and Critical Care Medicine (2025)
- Why IDSA Did Not Endorse the Community-Acquired Pneumonia Guidelines 2025 Update — Clinical Infectious Diseases (2026)
- Community-Acquired Pneumonia — Merck Manual Professional Edition (2026)
- Legionella Infections — Merck Manual Professional Edition (2024)
- Legionella: Fact Sheet for Clinicians — CDC (2025)
- Clinical Care of M. pneumoniae Infection — CDC (2026)
- Clinical Features of M. pneumoniae Infection — CDC (2026)
- Clinical Overview of C. pneumoniae Infection — CDC (2026)
- Clinical Overview of Psittacosis — CDC (2026)
- Clinical Signs and Symptoms of Q Fever — CDC (2025)
- Tularemia Antimicrobial Treatment and Prophylaxis: CDC Recommendations for Naturally Acquired Infections and Bioterrorism Response, United States, 2025 — MMWR Recommendations and Reports (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
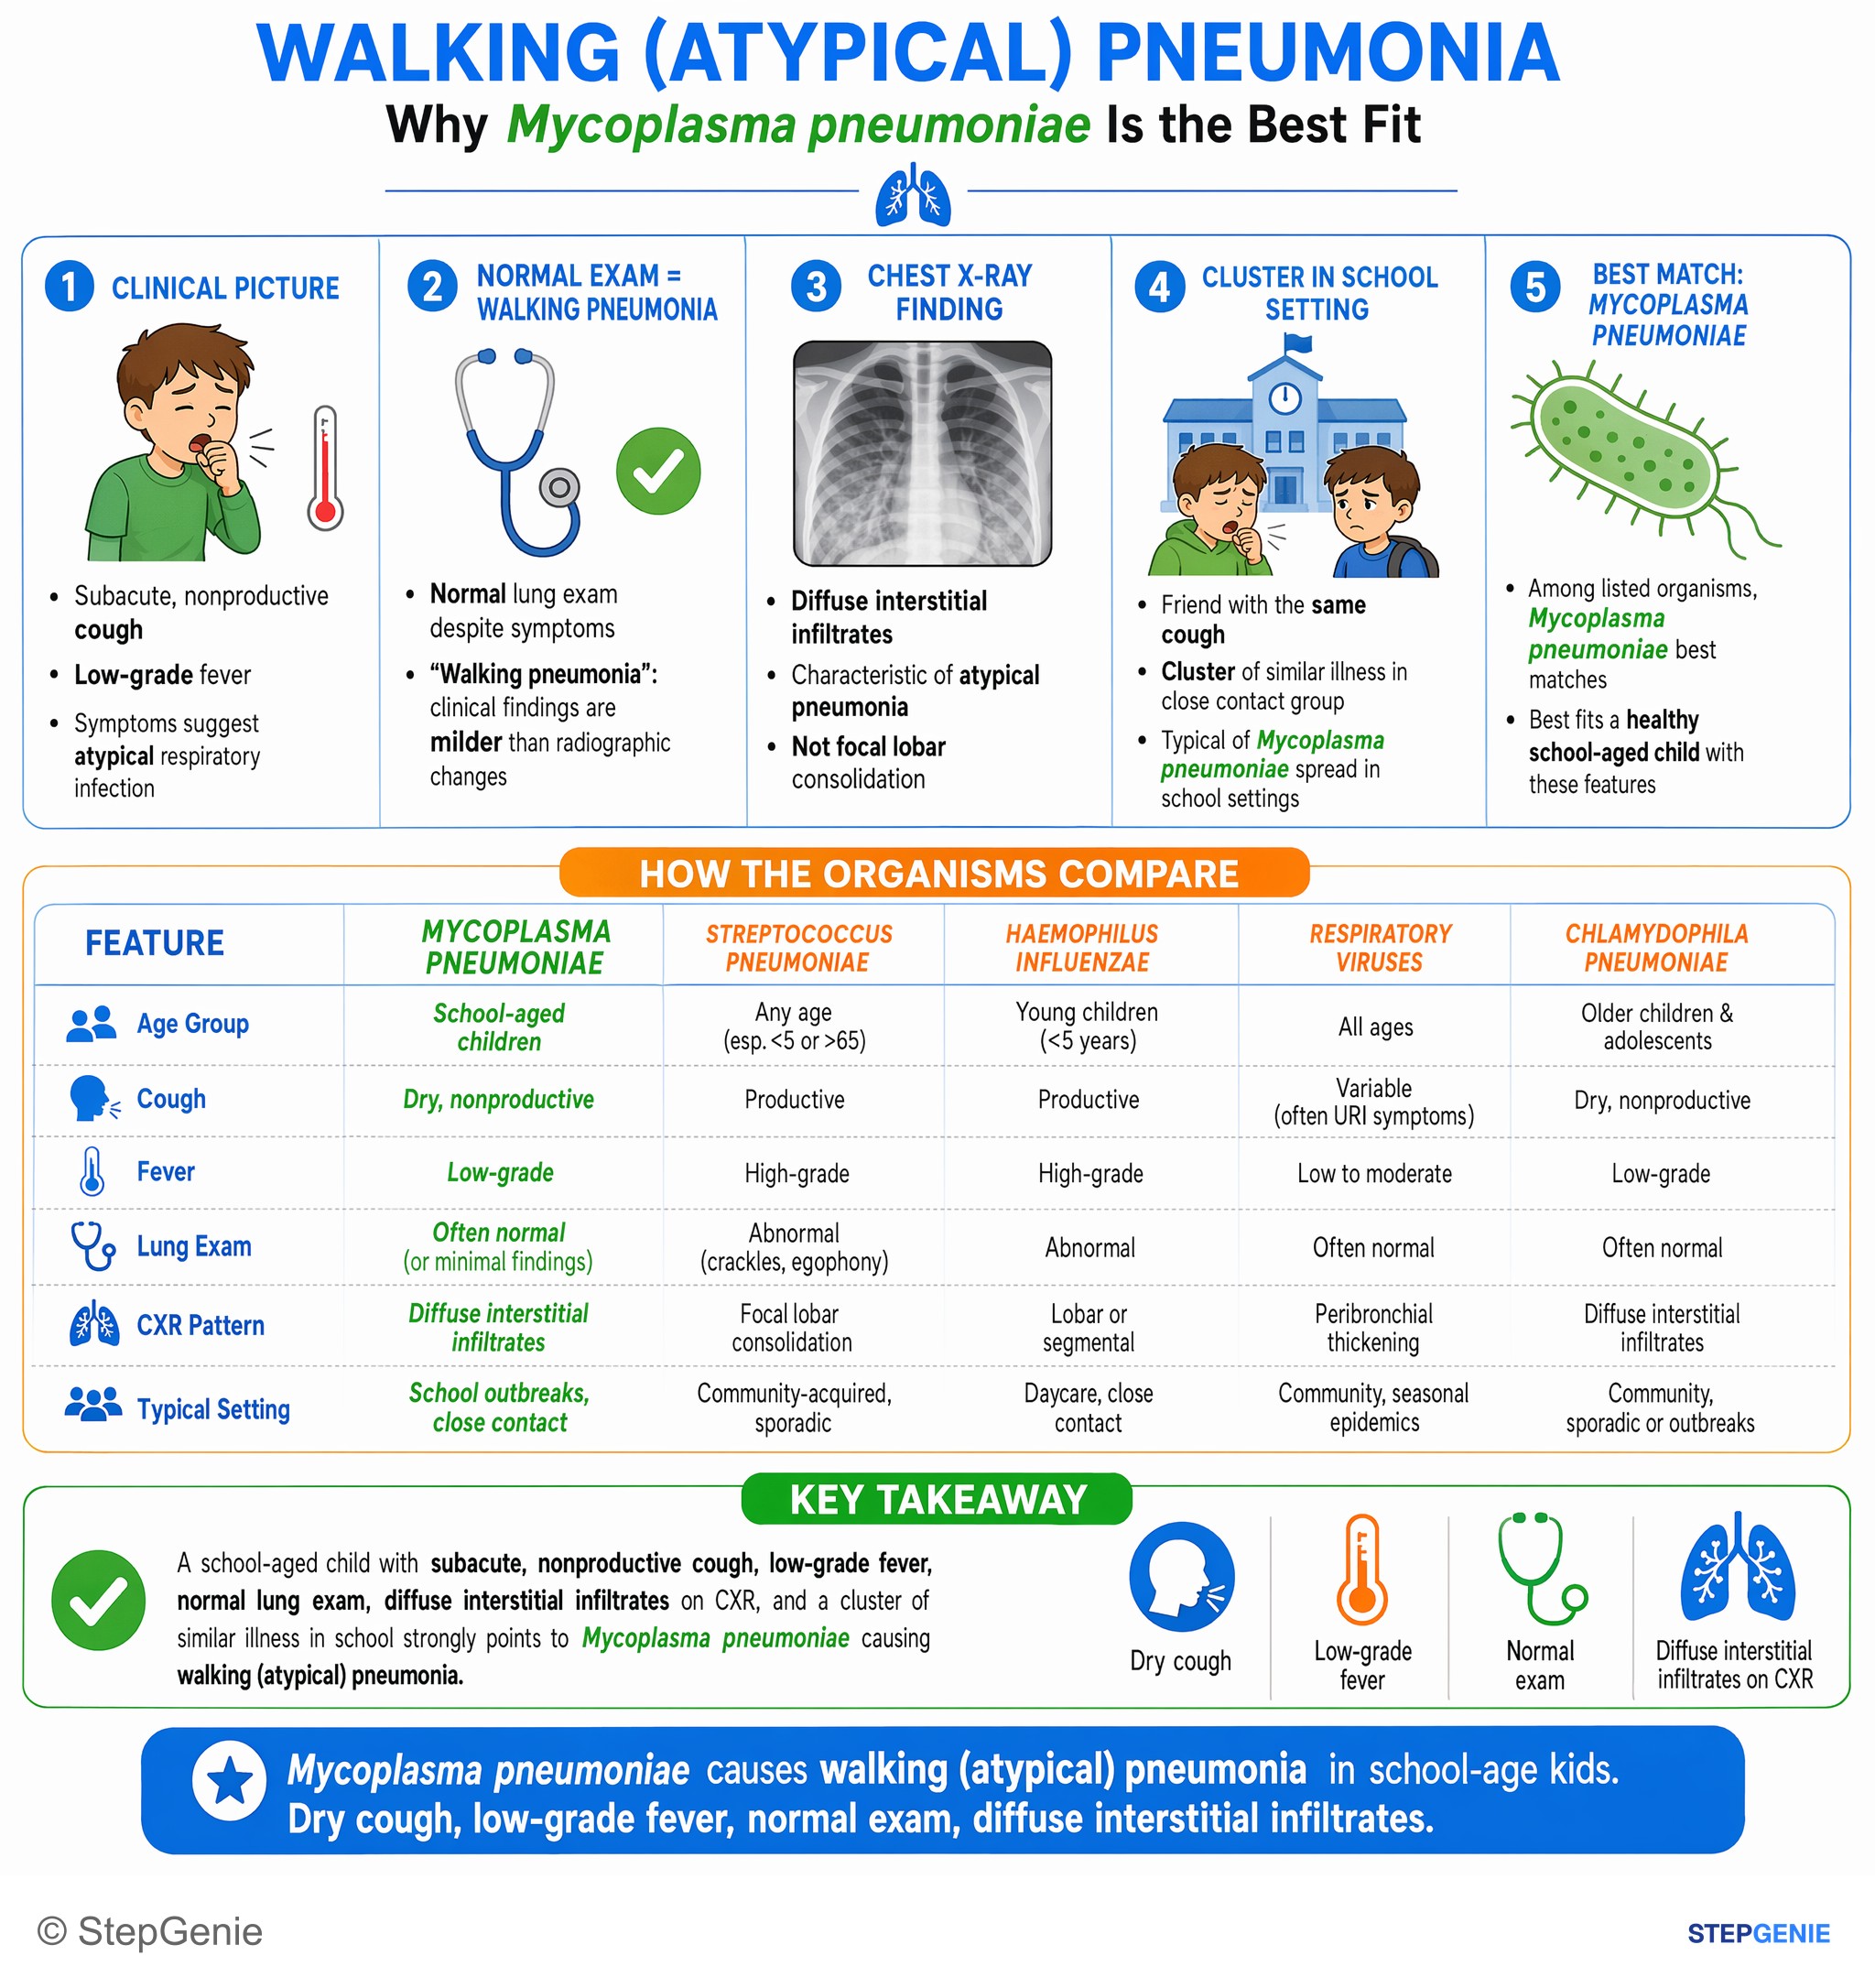
Mycoplasma pneumoniae causes walking (atypical) pneumonia in school-age kids: dry cough, low-grade fever, normal exam, diffuse…
USMLE Step 1
Legionella pneumophila causes severe pneumonia with GI symptoms, confusion, and hyponatremia; it is isolated on charcoal yeast extract…
USMLE Step 1Frequently Asked Questions
What organisms cause atypical pneumonia?
The classic atypical bacteria are Mycoplasma pneumoniae, Chlamydia pneumoniae and Legionella pneumophila. Together they cause roughly 3 to 11 percent of community-acquired pneumonia, while respiratory viruses cause up to 30 percent. Animal-borne look-alikes include Chlamydia psittaci from birds, Coxiella burnetii (Q fever) from livestock birth products, Francisella tularensis from rabbits, ticks and deer flies, and hantavirus from deer mouse droppings. In infants aged 1 to 3 months, Chlamydia trachomatis causes a usually afebrile pneumonia with a staccato cough.
Why don't beta-lactams work for atypical pneumonia?
Penicillins and cephalosporins act on the bacterial cell wall. Mycoplasma pneumoniae has no cell wall, so it is inherently resistant, and Chlamydia and Legionella live inside host cells, where these drugs are not effective. Atypical pneumonia is therefore treated with a macrolide such as azithromycin, a tetracycline such as doxycycline, or a respiratory fluoroquinolone such as levofloxacin. A classic exam stem is a young adult whose cough and fever did not improve on amoxicillin.
Does a negative Legionella urinary antigen test rule out Legionnaires' disease?
No. The urinary antigen test detects only Legionella pneumophila serogroup 1, which causes about 65 to 90 percent of cases, so infection with other serogroups or species gives a negative result. Its sensitivity is also imperfect, about 60 to 95 percent from roughly day 3 of illness. CDC advises pairing the urine antigen with a culture on selective media or a molecular test of a lower respiratory specimen such as sputum or bronchoalveolar lavage fluid. Blood cultures are unreliable for Legionella.
What are cold agglutinins in Mycoplasma pneumonia?
Cold agglutinins are IgM autoantibodies, usually against the I antigen on red cells, that bind and fix complement at temperatures below body temperature. After Mycoplasma infection they can cause an acute, usually self-limited hemolytic anemia. The direct antiglobulin test is positive for C3 and negative for IgG. Cold agglutinins also follow Epstein-Barr virus infection (often anti-i) and occur in idiopathic cold agglutinin disease, so they support but do not prove Mycoplasma. NAAT is the preferred diagnostic test.
What is the treatment for Legionella and Mycoplasma pneumonia?
Legionnaires' disease is treated with a respiratory fluoroquinolone such as levofloxacin or moxifloxacin for 7 to 14 days, or azithromycin for 5 to 10 days. Mycoplasma pneumonia is treated with a macrolide in children and adults, with doxycycline in older children and adults, or a fluoroquinolone in adults. Macrolide resistance in Mycoplasma has stayed under 10 percent in the United States, and CDC suggests an alternative such as doxycycline if a patient is not improving on a macrolide.
How do you tell psittacosis, Q fever and tularemia apart?
Use the exposure. Psittacosis follows contact with birds such as parrots, parakeets or poultry and causes fever, headache, dry cough and sometimes pulse-temperature dissociation; treat with doxycycline. Q fever follows inhaled dust from the birth products of goats, sheep or cattle and causes prolonged fever, low platelets and raised liver enzymes; treat with doxycycline. Pneumonic tularemia follows inhaling Francisella tularensis in dust or aerosols, for example from infected rabbits, or spread from tularemia caught from ticks, deer flies or animal handling; CDC's 2025 first-line drugs are ciprofloxacin, levofloxacin, gentamicin and doxycycline, with an aminoglycoside preferred in severe illness.