You’re cruising through your pulmonary infections questions when a classic “immunocompromised + hypoxia” vignette shows up—and suddenly every answer choice looks plausible. Pneumocystis jirovecii pneumonia (PJP) is one of those USMLE staples where the correct answer is high-yield, but the real score boost comes from knowing why the distractors are wrong (and what diagnosis they do represent).
The Vignette (Classic Q-Bank Style)
A 34-year-old man with HIV presents with 2 weeks of progressive dyspnea, nonproductive cough, and low-grade fever. He is not on antiretroviral therapy. Exam shows tachypnea and diffuse crackles. Pulse oximetry is 90% on room air. CXR shows bilateral diffuse interstitial infiltrates. LDH is elevated. CD4 count is 120 cells/mm³.
Most likely diagnosis?
A. Pneumocystis jirovecii pneumonia
B. Reactivation tuberculosis
C. Histoplasmosis
D. CMV pneumonitis
E. Legionella pneumonia
Step-by-Step: Why the Correct Answer Is PJP
✅ A. Pneumocystis jirovecii pneumonia — Correct
Why it fits:
- HIV with CD4 < 200 (biggest board-relevant risk factor)
- Subacute onset (days to weeks), not a sudden lobar consolidation picture
- Nonproductive cough + dyspnea + fever
- Diffuse bilateral interstitial/ground-glass pattern (often described as “hazy” or “ground-glass”)
- Elevated LDH (nonspecific but classically associated)
- Hypoxemia is often out of proportion to auscultation findings
Diagnostic confirmation (high-yield):
- Induced sputum or BAL with silver stain (Gomori methenamine silver) showing cup-shaped cysts
- Many stems now mention (1→3)-β-D-glucan as supportive (fungal cell wall component; not specific)
Treatment (Step 2 favorite):
- TMP-SMX is first-line
- Add corticosteroids if significant hypoxemia:
- Indication commonly tested as PaO₂ < 70 mmHg on room air or A–a gradient ≥ 35
- Alternatives (if sulfa allergy): pentamidine, atovaquone, or clindamycin + primaquine (varies by severity)
Prophylaxis (Step 1 + Step 2):
- TMP-SMX prophylaxis when CD4 < 200
- Also when oropharyngeal candidiasis is present (even if CD4 isn’t provided), depending on question style
Imaging + Buzzwords You Should Recognize Instantly
| Feature | PJP |
|---|---|
| Typical patient | HIV/AIDS, transplant, chronic steroids |
| Symptom tempo | Subacute (1–3 weeks) |
| Cough | Nonproductive |
| CXR | Bilateral diffuse interstitial infiltrates |
| CT | Ground-glass opacities |
| Labs | ↑ LDH (nonspecific) |
| Diagnosis | BAL/induced sputum + silver stain |
| Treatment | TMP-SMX ± steroids |
Board trap: Normal or near-normal lung exam does not rule out severe PJP.
Now the Real Money: Why Each Distractor Is Wrong (and What It Actually Is)
❌ B. Reactivation tuberculosis
Why it’s tempting: HIV patient with fever and cough.
Why it’s wrong here:
- Reactivation TB classically shows apical disease and cavitation (or nodular infiltrates) rather than diffuse interstitial ground-glass.
- Symptoms often include night sweats, weight loss, hemoptysis—more “B symptom” heavy.
- TB is often more productive than PJP and tends not to present with classic elevated LDH framing.
What would push you toward TB:
- Upper lobe cavitary lesions
- Acid-fast bacilli on sputum, positive NAAT
- Exposure history, incarceration, homelessness
❌ C. Histoplasmosis
Why it’s tempting: Opportunistic infection in immunocompromised.
Why it’s wrong here:
- Histoplasma is tied to Ohio/Mississippi River valleys and exposure to bat/bird droppings (caves, chicken coops).
- Imaging more often shows focal infiltrates, mediastinal/hilar lymphadenopathy, or disseminated disease patterns—not the prototypical diffuse ground-glass interstitial picture of PJP.
What would push you toward Histoplasma:
- Geography + exposure
- Urine antigen positivity (high-yield in disseminated disease)
- Dissemination clues: hepatosplenomegaly, pancytopenia, mucosal ulcers
❌ D. CMV pneumonitis
Why it’s tempting: Severe immunosuppression + pulmonary symptoms.
Why it’s wrong here:
- CMV pneumonitis is more classically seen in transplant patients and advanced AIDS with very low CD4 (often < 50).
- HIV patients with CD4 < 50 more commonly get CMV retinitis (floaters, blurry vision) and systemic illness.
- Radiology can be diffuse, but question stems usually include very low CD4, systemic CMV clues, or biopsy findings.
What would push you toward CMV:
- CD4 < 50
- Retinitis symptoms or exam findings
- Biopsy showing owl’s eye intranuclear inclusions
- Treatment: ganciclovir/valganciclovir (boards love this pairing)
❌ E. Legionella pneumonia
Why it’s tempting: Atypical pneumonia can cause diffuse findings and hypoxemia.
Why it’s wrong here:
- Legionella is typically acute and often more toxic-appearing.
- Key board clues are GI symptoms (diarrhea), hyponatremia, confusion, and exposure to water sources (hotel, cruise ship, cooling towers).
- Imaging is usually patchy/unilateral or lobar/bronchopneumonia—not the classic HIV + CD4 < 200 + ground-glass setup.
What would push you toward Legionella:
- High fever + diarrhea + hyponatremia
- Urine antigen test
- Treatment: azithromycin or fluoroquinolone
High-Yield “Answer Choice Differentiators” (Quick Pattern Recognition)
If the stem says…
- CD4 < 200 + subacute dyspnea + dry cough + diffuse ground-glass → PJP
- CD4 < 50 + retinitis or “owl eye” inclusions → CMV
- Apical cavitation + chronic constitutional symptoms → Reactivation TB
- Ohio/Mississippi River valleys + bat/bird droppings + urine antigen → Histoplasma
- Diarrhea + hyponatremia + hotel/cruise + urine antigen → Legionella
USMLE-Style “Next Best Step” Add-On (Common Follow-Up)
If the question pivots to management:
- Start empiric TMP-SMX if clinical suspicion is high (don’t wait if unstable).
- Check oxygenation:
- If PaO₂ < 70 or A–a ≥ 35, add prednisone (or IV steroids if severe).
- Confirm diagnosis with induced sputum or BAL.
And if they ask prevention:
- TMP-SMX prophylaxis when CD4 < 200
- Discontinue prophylaxis after immune recovery on ART (commonly when CD4 > 200 for ≥ 3 months—varies slightly by guideline wording, but the exam usually emphasizes the threshold and ART response concept)
Takeaway: The Question Isn’t Just “What Is It?”—It’s “What Else Could It Be?”
PJP is a diagnosis you should be able to call in under 10 seconds when you see:
- HIV + CD4 < 200
- Subacute dyspnea
- Nonproductive cough
- Diffuse interstitial/ground-glass
- Elevated LDH
- Hypoxemia
But the real Q-bank win is knowing that the distractors aren’t random—they’re a checklist of neighboring look-alikes you’re expected to separate using CD4 thresholds, symptom tempo, exposures, imaging pattern, and signature labs.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
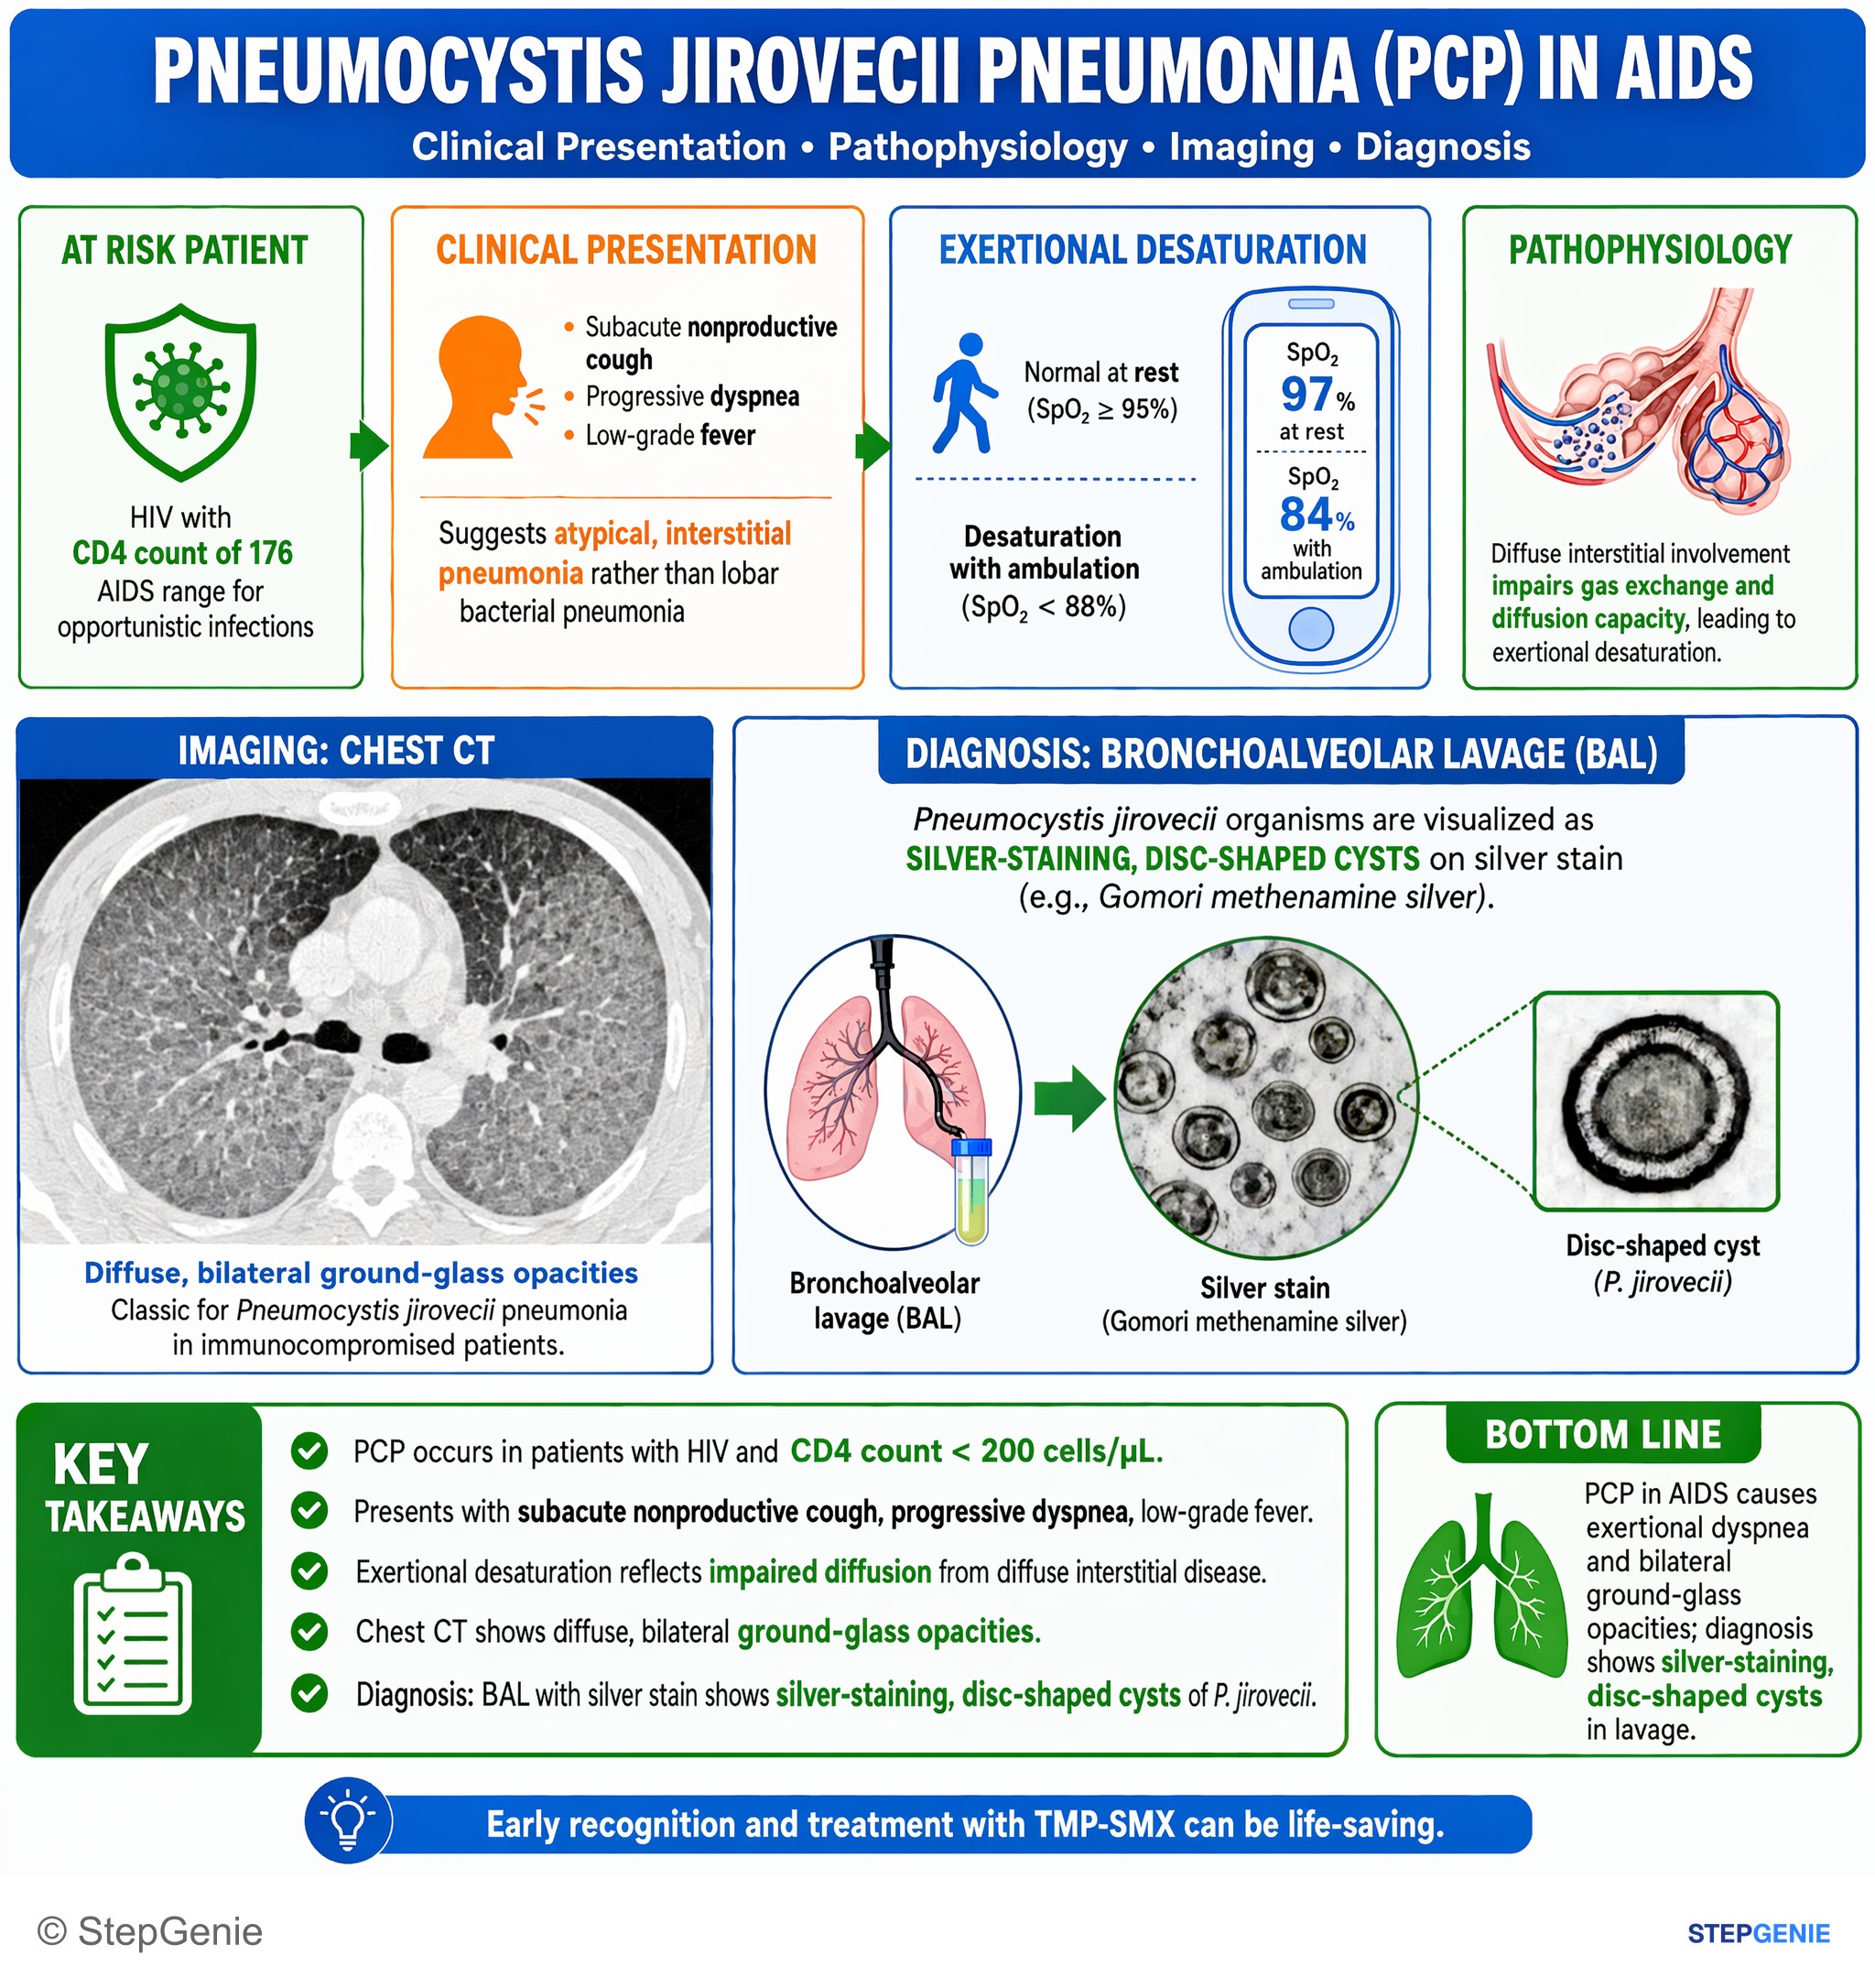
Pneumocystis jirovecii pneumonia (PCP) in AIDS causes exertional dyspnea and bilateral ground-glass opacities; diagnosis shows…
USMLE Step 1Frequently Asked Questions
What clues point to Pneumocystis jirovecii pneumonia instead of another pulmonary infection in an HIV patient?
Pneumocystis jirovecii pneumonia is suggested by HIV with CD4 below 200 plus subacute dyspnea, nonproductive cough, low-grade fever, hypoxemia, and bilateral diffuse interstitial or ground-glass infiltrates. Elevated LDH is a classic supportive clue, though nonspecific. A normal or near-normal lung exam does not rule it out, because hypoxemia can be out of proportion to auscultation findings.
How is Pneumocystis jirovecii pneumonia confirmed on exams and in question stems?
Pneumocystis jirovecii pneumonia is confirmed with induced sputum or bronchoalveolar lavage showing cup-shaped cysts on Gomori methenamine silver stain. Many question stems also mention a positive (1→3)-β-D-glucan as supportive evidence. That marker reflects a fungal cell wall component, but it is not specific, so the silver stain findings are the classic diagnostic clue.
What is the first-line treatment for Pneumocystis jirovecii pneumonia, and when do you add steroids?
The first-line treatment is TMP-SMX. Corticosteroids are added when there is significant hypoxemia, commonly tested as a PaO2 less than 70 mmHg on room air or an A–a gradient of at least 35. If a patient cannot take sulfa drugs, alternatives mentioned include pentamidine, atovaquone, or clindamycin plus primaquine, depending on severity.
How do you tell Pneumocystis jirovecii pneumonia from reactivation TB on a test question?
Pneumocystis jirovecii pneumonia usually causes a subacute illness with dry cough and diffuse bilateral interstitial or ground-glass infiltrates, whereas reactivation TB classically causes apical disease with cavitation or nodular infiltrates. TB also leans more toward chronic constitutional symptoms such as night sweats, weight loss, and hemoptysis, and sputum studies may show acid-fast bacilli or a positive NAAT.
How do you distinguish Pneumocystis jirovecii pneumonia from CMV pneumonitis, histoplasmosis, and Legionella?
Use the associated clues. CMV pneumonitis is more associated with transplant patients or advanced AIDS with very low CD4 counts, often below 50, and may come with retinitis or owl’s eye inclusions. Histoplasmosis points to Ohio or Mississippi River valley exposure, bat or bird droppings, urine antigen positivity, and possible dissemination. Legionella is more acute and classically features diarrhea, hyponatremia, confusion, water-source exposure, and a positive urine antigen.