A lung abscess is a necrotizing lung infection that leaves a circumscribed, pus-filled cavity. The classic cause is aspiration of oral secretions by someone with impaired consciousness (alcohol or drug intoxication, seizures, anesthesia) or poor dentition, so mixed oral anaerobes (Peptostreptococcus, Fusobacterium, Prevotella, Bacteroides) dominate. The exam picture is an indolent illness (weeks to months) with fever, cough and foul-smelling sputum, and a chest x-ray showing a cavity with an air-fluid level in a dependent segment: the posterior segment of an upper lobe or the superior segment of a lower lobe, more often on the right. First-line therapy today is a beta-lactam/beta-lactamase inhibitor such as ampicillin-sulbactam; clindamycin, the classic exam answer, is now rarely used because of C. difficile risk and resistance. Antibiotics continue for 3-6 weeks or longer, until the x-ray clears, and only a minority need drainage or surgery.
The Q-bank vignette
A 52-year-old man is brought to the emergency department with 2 weeks of fever, productive cough and right-sided pleuritic chest pain. His sputum and breath smell foul. He drinks heavily and was found "passed out" after a binge about 3 weeks ago. Temperature is 38.9°C (102°F). He has poor dentition with gingivitis, and crackles are heard over the right posterior chest. WBC count is 16,500/mm³. Chest x-ray shows a 5-cm thick-walled cavity with an air-fluid level, surrounded by consolidation, in the superior segment of the right lower lobe; there is no pleural effusion.
Which of the following is the most likely diagnosis?
A. Lung abscess caused by aspirated oral flora
B. Lobar pneumonia caused by Streptococcus pneumoniae
C. Reactivation pulmonary tuberculosis
D. Cavitating squamous cell carcinoma
E. Pulmonary infarction from a pulmonary embolus
F. Empyema
G. Necrotizing Staphylococcus aureus pneumonia after influenza
H. Septic pulmonary emboli from tricuspid endocarditis
I. Granulomatosis with polyangiitis
Answer: A. Lung abscess from aspiration
Three findings lock it in:
- Aspiration risk: binge drinking with loss of consciousness, plus gingivitis (periodontal disease supplies the anaerobes).
- Foul (putrid) sputum and breath: the signature of anaerobic infection.
- A cavity with an air-fluid level in a dependent segment: the superior segment of a lower lobe is dependent when a person lies on their back. The air-fluid level appears when the abscess ruptures into a bronchus: pus is coughed up and air replaces it.
Why every other choice is wrong
- B. Pneumococcal lobar pneumonia: comes on over hours to days with lobar consolidation and responds quickly to standard therapy; it is not the 2-week illness with putrid sputum and a cavity. Review the community-acquired pneumonia breakdown.
- C. Reactivation TB: favors the lung apices and evolves over weeks to months with chronic cough, night sweats and weight loss; the sputum is not putrid. When the story fits (exposure, HIV, homelessness), isolate the patient and send sputum for AFB smear, NAAT and culture. See primary vs reactivation TB.
- D. Cavitating carcinoma: an excavating bronchial carcinoma (classically squamous cell carcinoma in a smoker) mimics an abscess, and an obstructing tumor can cause one. Suspect cancer when the cavity has no surrounding consolidation, there is no fever, or the lesion does not respond to antibiotics; bronchoscopy settles it.
- E. Pulmonary infarction: sudden dyspnea and pleuritic pain with a pleural-based, wedge-shaped opacity (Hampton hump), not putrid sputum or a fluid-filled cavity. CT pulmonary angiography is the test.
- F. Empyema: frank pus in the pleural space, not in the lung. Expect a pleural collection, often loculated; drainage is needed for pus, pleural fluid pH below 7.20, glucose below 60 mg/dL, a positive Gram stain or culture, or loculations. About 10% of lung abscesses extend into the pleura and cause one. See the empyema tips.
- G. Staphylococcal necrotizing pneumonia: follows influenza or affects hospitalized patients, and the patient is acutely ill within days. S. aureus can form lung abscesses that rapidly progress to pneumatoceles and empyema, and community-acquired MRSA causes severe necrotizing pneumonia; treat MRSA with vancomycin or linezolid. Nothing here suggests influenza.
- H. Septic pulmonary emboli: blood-borne, so expect multiple nodules or abscesses rather than one dependent cavity, in a person who injects drugs, with a tricuspid regurgitation murmur and positive blood cultures (S. aureus is the classic organism). Multiple abscesses call for an echocardiogram. See the infective endocarditis breakdown.
- I. Granulomatosis with polyangiitis: multiple lung nodules that may cavitate, plus sinusitis, epistaxis or a saddle nose, glomerulonephritis (hematuria, red cell casts) and c-ANCA against PR3. There is no infectious story. See the GPA guide.
Who aspirates, and where it lands
Risk factors (Merck, StatPearls):
- Impaired consciousness: alcohol or drug intoxication, sedatives and opioids, general anesthesia, seizures.
- Impaired swallowing or protection of the airway: stroke and other neurologic disease, esophageal or laryngeal disorders, vomiting.
- Dental disease: gingivitis and poor oral hygiene supply the anaerobic inoculum.
- Secondary abscesses: bronchial obstruction (carcinoma, foreign body), immunosuppression (advanced HIV, transplant), blood-borne seeding (septic emboli, right-sided endocarditis), and direct spread from an empyema or mediastinal abscess.
Gravity decides the segment:
| Position during aspiration | Dependent segments |
|---|---|
| Lying on the back (supine) | Posterior segments of the upper lobes, superior segments of the lower lobes |
| Upright | Basal segments of the lower lobes (also the middle lobe and lingula) |
Positional pattern per Radiopaedia; Merck's classic sites in a recumbent patient are the posterior segments of the upper lobes and the superior or lateral basal segments of the lower lobes. Aspirated material reaches the right lung more often because the right main bronchus is wider, shorter and more vertical, and StatPearls lists the posterior segment of the right upper lobe, the middle lobe and the superior segment of the right lower lobe as the commonest abscess sites.
Microbiology
| Organism | When to think of it |
|---|---|
| Oral anaerobes: Peptostreptococcus, Fusobacterium, Prevotella, Bacteroides | Aspiration, dental disease, putrid sputum, indolent course: the most common cause |
| Streptococci | Often mixed with the anaerobes |
| Staphylococcus aureus, including MRSA | After influenza, in hospitalized patients, or from septic emboli |
| Klebsiella pneumoniae | Necrotizing pneumonia with abscess and empyema, classically in alcohol use disorder or diabetes (see the Klebsiella breakdown) |
| Pseudomonas and other gram-negative rods | Immunocompromised patients (the most common cause in this group) |
| Nocardia, mycobacteria, fungi | Also immunocompromised patients |
Expectorated sputum is contaminated by mouth anaerobes, so sputum anaerobic cultures are not useful. Send a Gram stain, aerobic sputum culture and blood cultures; bronchoscopic samples are better for anaerobic culture (Merck).
Diagnosis
- Chest x-ray: consolidation with a single cavity containing an air-fluid level in a dependent segment.
- CT chest: when the cavity is not clear on the radiograph, a mass is suspected, or an abscess must be told apart from an empyema or an infected bulla.
- Bronchoscopy: to exclude cancer or a foreign body, find unusual organisms, and evaluate immunocompromised patients or those who fail to improve.
- Echocardiography when there are multiple abscesses, to look for endocarditis.
Treatment
- First line: a beta-lactam/beta-lactamase inhibitor, such as IV ampicillin-sulbactam (Merck).
- Alternatives: a carbapenem (imipenem-cilastatin) or ceftriaxone plus metronidazole; for penicillin allergy, moxifloxacin, or levofloxacin plus metronidazole. Add vancomycin or linezolid for MRSA. Less ill patients can take oral amoxicillin-clavulanate or moxifloxacin.
- Clindamycin: the classic exam answer, but Merck says it is "rarely used now" because of C. difficile infection and resistance; StatPearls keeps it as an option for penicillin allergy.
- Not metronidazole alone: the flora is polymicrobial, so monotherapy is not adequate (StatPearls).
- Duration: until the chest x-ray shows complete resolution or a small, stable scar, generally 3-6 weeks or longer (Merck).
- Slow response is expected, but no defervescence or clinical improvement after 7-10 days should prompt a search for resistant or unusual organisms, airway obstruction (cancer, foreign body) or a noninfectious cause.
- Drainage is the exception: percutaneous catheter drainage for some subpleural abscesses, drainage of any accompanying empyema, and surgery (usually lobectomy) in about 10% who do not respond (Merck). Abscesses larger than 6 cm are less likely to resolve with antibiotics alone (StatPearls). Chest physiotherapy and postural drainage are no longer routinely recommended because pus can spill into other airways.
Next-step question: the patient in the vignette is admitted. What is the most appropriate initial treatment?
A. IV ampicillin-sulbactam
B. Oral metronidazole alone
C. Oral azithromycin alone
D. Urgent lobectomy
E. Isoniazid, rifampin, pyrazinamide and ethambutol
Answer: A. A beta-lactam/beta-lactamase inhibitor covers the mixed oral anaerobes and streptococci. B misses part of the polymicrobial flora. C is an outpatient community-acquired pneumonia option, not a lung abscess regimen. D is reserved for the roughly 10% who fail antibiotics. E treats tuberculosis, which nothing here suggests; start it only if the clinical picture or AFB testing points to TB.
Lung abscess vs look-alikes
| Condition | Imaging | Key clue |
|---|---|---|
| Lung abscess | Single thick-walled cavity with an air-fluid level in a dependent segment | Aspiration risk, putrid sputum, indolent course |
| Empyema | Pleural collection, often loculated | Pus in the pleural space; needs drainage |
| Reactivation TB | Apical cavitation | Weeks to months of cough, night sweats, weight loss; exposure risk |
| Cavitating carcinoma | Cavity, often without surrounding consolidation | Smoker, no fever, no response to antibiotics |
| Septic emboli | Multiple nodules or abscesses | Injection drug use, tricuspid endocarditis |
| GPA | Multiple nodules that may cavitate | Sinusitis, saddle nose, glomerulonephritis, c-ANCA |
| S. aureus necrotizing pneumonia | Abscesses, pneumatoceles, empyema | After influenza; rapid, severe course |
| Pulmonary infarction | Pleural-based wedge (Hampton hump) | Sudden dyspnea, risk factors for clots |
How USMLE tests lung abscess
- Alcohol, seizure, stroke, anesthesia or bad teeth + foul sputum + cavity with an air-fluid level = aspiration lung abscess.
- Location: supine aspiration → posterior upper lobe or superior lower lobe segments; upright → basal segments; right more often than left.
- Organisms: mixed oral anaerobes; think S. aureus after influenza and Klebsiella in alcohol use disorder.
- Treatment: ampicillin-sulbactam now; clindamycin is the older answer; never metronidazole alone.
- No response in 7-10 days, no fever, or a cavity without consolidation → bronchoscopy for cancer or a foreign body.
- Multiple cavities + injection drug use → septic emboli; cavities + sinus disease + glomerulonephritis → GPA.
Key takeaways
- Lung abscess = necrotizing infection with a pus-filled cavity, usually from aspirated oral anaerobes.
- Risk factors: impaired consciousness (alcohol, seizures, sedation), dysphagia and dental disease.
- Classic imaging: a single cavity with an air-fluid level in a dependent segment (posterior upper lobe, superior lower lobe), more often on the right.
- Foul-smelling sputum = anaerobes; expectorated sputum is useless for anaerobic culture.
- Treat with ampicillin-sulbactam (alternatives: carbapenem, ceftriaxone plus metronidazole, moxifloxacin) for 3-6 weeks or longer, until the x-ray clears.
- Drainage or surgery only for nonresponders, very large abscesses or an accompanying empyema.
- Look-alikes: empyema, cavitary TB, cavitating squamous cell carcinoma, septic emboli, GPA.
Sources
- Lung Abscess — Merck Manual Professional Edition (2025)
- Lung Abscess — StatPearls, NCBI Bookshelf (2024)
- Aspiration Pneumonitis and Pneumonia — Merck Manual Professional Edition (2024)
- Aspiration pneumonia — Radiopaedia (2024)
- Anatomy, Thorax, Bronchial — StatPearls, NCBI Bookshelf (2023)
- Pleural Effusion — Merck Manual Professional Edition (2025)
- Tuberculosis (TB) — Merck Manual Professional Edition (2026)
- Pulmonary Embolism (PE) — Merck Manual Professional Edition (2026)
- Staphylococcal Infections — Merck Manual Professional Edition (2025)
- Infective Endocarditis — Merck Manual Professional Edition (2025)
- Granulomatosis With Polyangiitis (GPA) — Merck Manual Professional Edition (2025)
- Klebsiella, Enterobacter, and Serratia Infections — Merck Manual Professional Edition (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
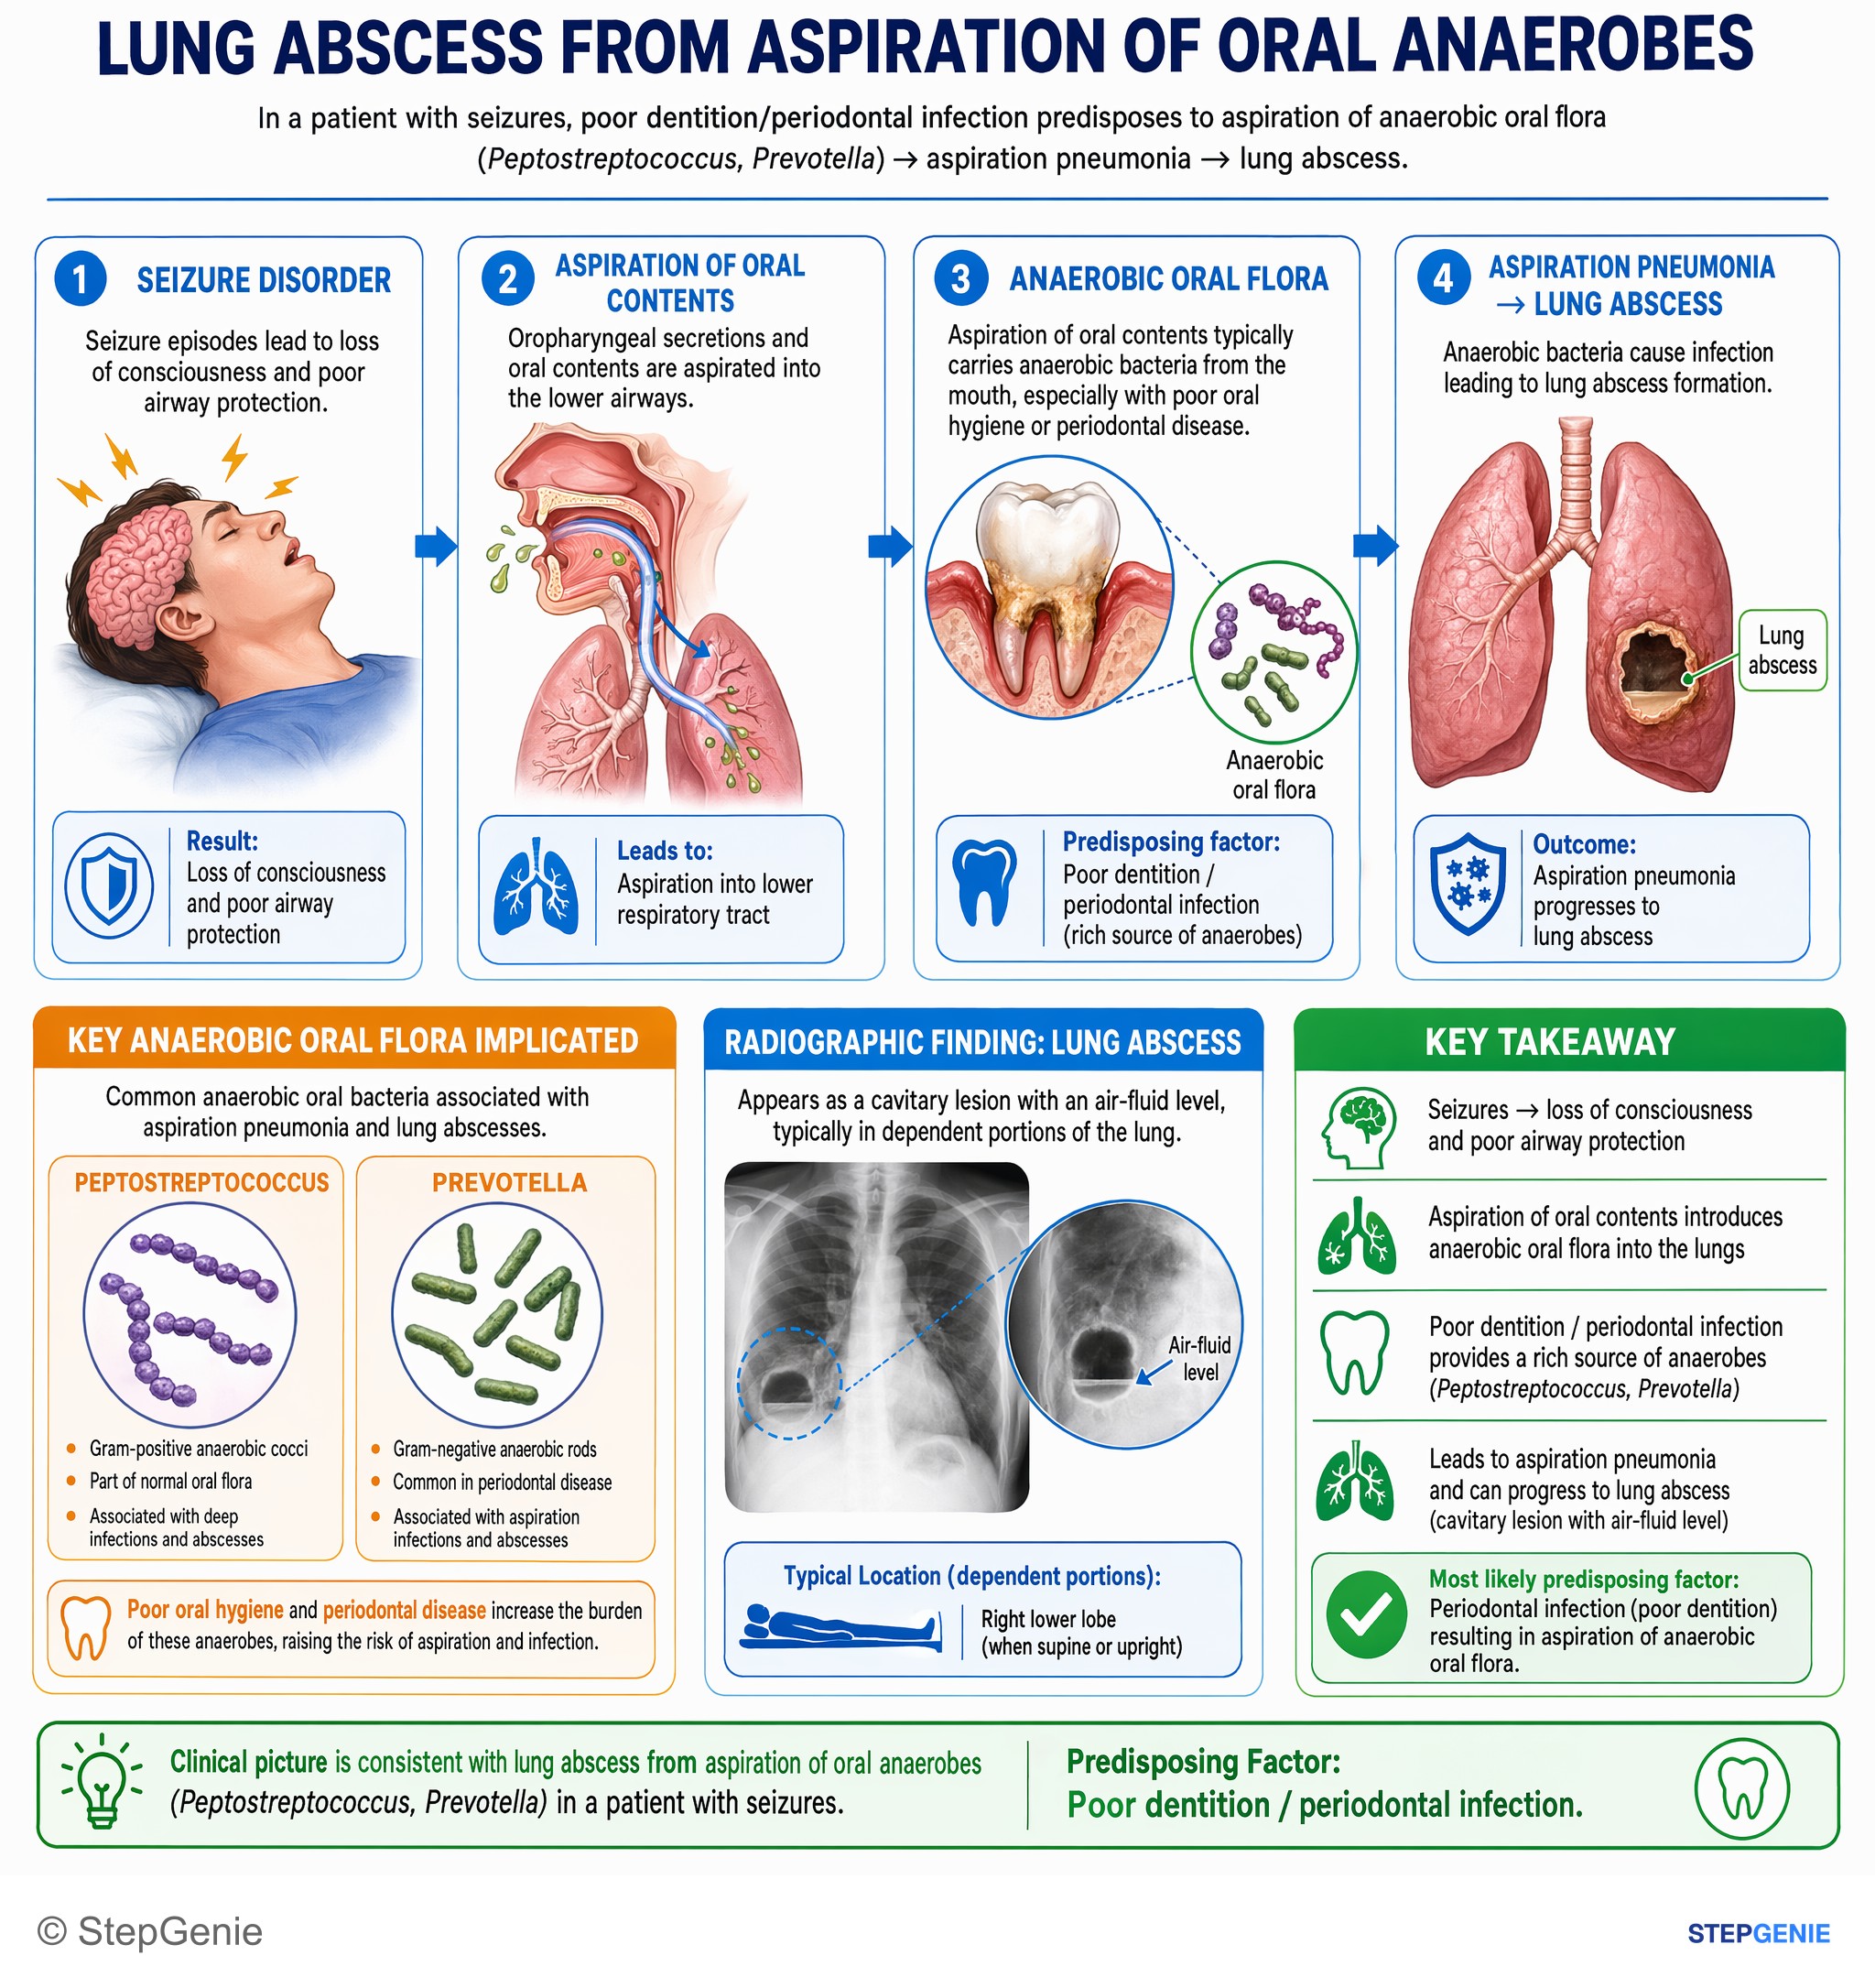
Lung abscess from aspiration of oral anaerobes (Peptostreptococcus, Prevotella) in a patient with seizures; predisposing factor is poor…
USMLE Step 1Frequently Asked Questions
What causes a lung abscess?
Most lung abscesses follow aspiration of oral secretions by people with impaired consciousness (alcohol or drug intoxication, sedatives, anesthesia, seizures), trouble swallowing or poor dental hygiene. The aspirated mouth flora, mainly anaerobes such as Peptostreptococcus, Fusobacterium, Prevotella and Bacteroides mixed with streptococci, cause a necrotizing infection that forms a pus-filled cavity. Secondary abscesses come from bronchial obstruction by cancer or a foreign body, immunosuppression, septic emboli from right-sided endocarditis, or spread from an empyema.
Where do aspiration lung abscesses usually occur?
They form in the lung segments that are lowest (dependent) at the moment of aspiration. When a person aspirates lying on their back, material falls into the posterior segments of the upper lobes and the superior segments of the lower lobes; when upright, it falls mainly into the basal segments of the lower lobes. The right lung is involved more often because the right main bronchus is wider, shorter and more vertical. A cavity with an air-fluid level in one of these segments is the classic exam finding.
What is the first-line antibiotic for a lung abscess?
Current first-line therapy is a beta-lactam/beta-lactamase inhibitor such as IV ampicillin-sulbactam, which covers mixed oral anaerobes and streptococci. Alternatives include a carbapenem, ceftriaxone plus metronidazole, or moxifloxacin for penicillin allergy, with vancomycin or linezolid added for MRSA. Clindamycin was the classic choice but is now rarely used because of C. difficile risk and resistance, and metronidazole alone is not adequate. Treatment usually lasts 3 to 6 weeks or longer, until the chest x-ray clears.
How is a lung abscess different from empyema?
A lung abscess is a pus-filled cavity inside the lung tissue, usually after aspiration, and most heal with several weeks of antibiotics alone. An empyema is frank pus in the pleural space, between the lung and the chest wall, and it must be drained by thoracentesis or a chest tube in addition to antibiotics. On imaging an empyema is a pleural collection, often loculated, while an abscess is a cavity within the lung; CT helps when the chest x-ray is unclear. About 10% of lung abscesses spread to cause an empyema.
When does a lung abscess need drainage or surgery?
Rarely. Most lung abscesses drain through a bronchus and heal with 3 to 6 weeks or more of antibiotics. Percutaneous catheter drainage can help some subpleural abscesses, any accompanying empyema must be drained, and surgery, usually lobectomy, is needed in about 10% of patients who do not respond. Abscesses larger than about 6 cm are less likely to resolve with antibiotics alone. No improvement after 7 to 10 days should prompt a search for resistant organisms, airway obstruction or cancer.
How do you tell a lung abscess from cavitary TB or lung cancer?
Lung abscess is favored by aspiration risk, foul-smelling sputum, fever and a single cavity with an air-fluid level and surrounding consolidation in a dependent segment. Reactivation TB favors the lung apices and develops over weeks to months with night sweats and weight loss; sputum AFB smear, NAAT and culture confirm it. A cavitating carcinoma, classically squamous cell carcinoma in a smoker, is suggested by a cavity without surrounding consolidation, no fever or no response to antibiotics, and is evaluated with bronchoscopy.