Drug-induced lung disease is a spectrum, not one disorder: more than 150 drugs can cause interstitial pneumonitis or fibrosis, organizing pneumonia, bronchospasm, cough, noncardiogenic pulmonary edema, pleural effusion, eosinophilic infiltrates, hemorrhage or pulmonary vascular disease. The exam pairs to know are amiodarone (pneumonitis, peak onset 6-12 months), bleomycin (pneumonitis progressing to fibrosis; DLCO monitoring, high oxygen worsens it), busulfan (late fibrosis), methotrexate (hypersensitivity-type pneumonitis), nitrofurantoin (acute eosinophilic reaction or chronic fibrosis), checkpoint inhibitors (immune pneumonitis), ACE inhibitors (dry cough), aspirin/NSAIDs (AERD) and nonselective beta-blockers (bronchospasm). The diagnosis rests on timing, pattern and exclusion of infection, heart failure and cancer; treatment starts with stopping the drug.
The vignette
A 68-year-old man has 3 months of progressive exertional dyspnea and a dry cough. He has atrial fibrillation and heart failure with reduced ejection fraction. Medications are amiodarone 400 mg daily (started 9 months ago), lisinopril (6 years), metoprolol succinate, furosemide and apixaban. He has never smoked.
Temperature is 37.7°C (99.9°F), pulse 64/min, blood pressure 124/76 mm Hg and SpO₂ 90% on room air. There are fine bibasilar crackles, no wheezes, no JVD and no edema. NT-proBNP is at his usual baseline. Chest CT shows bilateral peripheral ground-glass and reticular opacities with patchy consolidation; the unenhanced images show increased attenuation of the liver. Compared with tests done before amiodarone, PFTs show FVC 68% of predicted (was 85%), FEV₁/FVC 0.82 and DLCO 42% of predicted (was 75%).
Which of the following best explains his findings?
A. Amiodarone pulmonary toxicity B. ACE inhibitor-induced cough C. Beta-blocker-induced bronchospasm D. Cardiogenic pulmonary edema E. Idiopathic pulmonary fibrosis
Answer and why A is right
A. Amiodarone pulmonary toxicity. Every clue lines up:
- Timing: onset can be days to a decade into therapy, but peaks at 6-12 months and is somewhat dose-related; he is at 9 months on 400 mg/day.
- Syndrome: the label describes cough and progressive dyspnea with functional, radiographic and pathologic evidence of lung injury, as hypersensitivity pneumonitis (including eosinophilic pneumonia) or interstitial/alveolar pneumonitis. Low-grade fever does not argue against it.
- Physiology: restriction (falling FVC, normal FEV₁/FVC) with a large DLCO drop from baseline, the reason baseline PFTs with DLCO are required.
- Imaging: patchy ground-glass, reticular and consolidative opacities; high attenuation of the liver (and thyroid) on unenhanced CT reflects iodine-rich amiodarone deposits.
- Stakes: rates as high as 17% in some series, fatal in about 10% of cases.
Next steps: stop amiodarone and choose another antiarrhythmic, exclude infection and heart failure, and treat significant disease with glucocorticoids (the label suggests prednisone 40-60 mg/day tapered over several weeks; courses are often prolonged). Because amiodarone's half-life is 15-142 days, toxicity can persist for weeks after stopping.
Why every other answer is wrong
B. ACE inhibitor-induced cough. ACE is the same enzyme as kininase, which degrades bradykinin; accumulated bradykinin is thought to drive a dry, persistent, often nocturnal cough in up to 20% of North American and European patients (up to 40% in Asian populations). It usually starts within days to months of beginning the drug, so a cough first appearing 6 years in would be atypical, and it does not cause crackles, opacities, restriction or a low DLCO. The test is stopping the drug; the fix is an ARB (see the ACE inhibitor vs ARB mnemonic).
C. Beta-blocker-induced bronchospasm. Beta-blockade produces obstruction: wheeze and a low FEV₁/FVC. His ratio is 0.82 and he has no wheeze. The risk is mainly with nonselective agents (propranolol, nadolol, carvedilol, sotalol, even timolol eye drops); cardioselective metoprolol, atenolol and bisoprolol are preferred, though selectivity falls at higher doses.
D. Cardiogenic pulmonary edema. Tempting in a patient with HFrEF, but there is no JVD, edema or rise in natriuretic peptide, and the slow 3-month course with high-attenuation liver points elsewhere. In heart failure on amiodarone, always rule out edema before blaming the drug, and vice versa.
E. Idiopathic pulmonary fibrosis. IPF is a diagnosis of exclusion; a drug that causes pneumonitis must be ruled out first. Its HRCT pattern is usual interstitial pneumonia (subpleural, basal reticulation with honeycombing and traction bronchiectasis) that evolves over years, not ground-glass and consolidation over months.
Drug-pattern table: the pairs to memorize
| Drug | Main lung pattern | Timing and risk factors | Exam clue and action |
|---|---|---|---|
| Amiodarone | Interstitial or alveolar pneumonitis, organizing pneumonia, fibrosis, nodules; ARDS after surgery | Peak 6-12 months; can occur at low dose | Baseline CXR and PFTs with DLCO; history, exam and CXR every 3-6 months; stop, prednisone |
| Bleomycin | Pneumonitis progressing to pulmonary fibrosis in some | Total dose over 400 units, age over 70, renal impairment; high FiO₂ | Lungs and skin lack bleomycin hydrolase; monitor DLCO; keep FiO₂ near room air in surgery |
| Busulfan | "Busulfan lung": bronchopulmonary dysplasia with fibrosis | Rare; 8 months to 10 years after starting | Low DLCO; exclude infection and leukemic infiltrates; poor prognosis |
| Methotrexate | Acute or chronic interstitial (hypersensitivity-type) pneumonitis | Occurs even at weekly rheumatoid arthritis doses (about 1% in trials) | Dry cough, dyspnea, fever; exclude Pneumocystis and other infections; withhold or stop |
| Nitrofurantoin | Acute hypersensitivity pneumonitis; chronic interstitial pneumonitis or fibrosis | Acute: first week. Chronic: 6 months or more of continuous use (UTI prophylaxis), often older adults | Acute: fever, eosinophilia, infiltrates or effusion, dramatic recovery. Chronic: insidious, may be permanent |
| Checkpoint inhibitors (pembrolizumab, nivolumab) | Immune-mediated pneumonitis | 3.4% with pembrolizumab; more after thoracic radiation | Grade 2: withhold, prednisone 1-2 mg/kg/day. Grade 3-4: stop permanently |
| ACE inhibitors | Dry cough; angioedema | Cough: days to months after starting | Normal CXR and PFTs; switch to an ARB |
| Aspirin and COX-1 NSAIDs (AERD) | Bronchospasm with nasal congestion | Asthma plus nasal polyps | Avoid COX-1 inhibitors; leukotriene modifiers; aspirin desensitization |
| Nonselective beta-blockers | Bronchospasm | Asthma or bronchospastic COPD | Relative contraindication in asthma, eye drops included; use cardioselective agents cautiously |
Other patterns on Merck's list: noncardiogenic pulmonary edema (heroin, methadone, cocaine, hydrochlorothiazide, gemcitabine), pleural effusion (amiodarone, bromocriptine, methotrexate, nitrofurantoin), pulmonary vascular disease (fenfluramine, phentermine) and parenchymal hemorrhage (anticoagulants). For side effects beyond the lung, see high-yield drug side effects.
High-yield details by drug
- Bleomycin (ABVD for Hodgkin lymphoma, BEP for testicular cancer): pulmonary toxicity in about 10% of patients and death from fibrosis in about 1%. The earliest symptom is dyspnea and the earliest sign fine crackles. The label recommends chest x-rays every 1-2 weeks and, if DLCO is used, monthly DLCO, stopping the drug when DLCO "falls below 30% to 35% of the pretreatment value." Bleomycin-exposed lungs are injured by oxygen at concentrations usually considered safe, so FiO₂ is kept near 25% during and after surgery. It is cleared mainly by the kidneys, so renal impairment raises exposure.
- Busulfan: symptoms (insidious cough, dyspnea, low-grade fever) appear 8 months to 10 years after starting, after an average of 4 years of therapy. Treatment is unsatisfactory, and most patients have died within 6 months of diagnosis in reported series.
- Nitrofurantoin: the classic two faces. Acute: fever, chills, cough, chest pain, dyspnea, infiltrates or effusion and eosinophilia in the first week, reversing quickly when the drug is stopped. Chronic: diffuse interstitial pneumonitis or fibrosis after 6 months or more, with little fever; the longer it goes unrecognized, the less it reverses.
- Methotrexate: the label warns of acute or chronic interstitial pneumonitis, including irreversible or fatal cases, and of opportunistic infections such as Pneumocystis pneumonia, so a febrile pneumonitis on methotrexate needs an infection workup (see Pneumocystis jirovecii). Do not confuse it with inhaled-antigen hypersensitivity pneumonitis.
- Immune checkpoint inhibitors: steroids continue until grade 1 or less, then taper over at least a month; resume only after recovery, and permanently stop for grade 3-4 pneumonitis.
- AERD (Samter triad): asthma, chronic rhinosinusitis with nasal polyps, and respiratory reactions to aspirin and other COX-1 inhibitors; about 9% of adults with asthma and 30% of those with asthma and nasal polyps. The classic mechanism is a shift of arachidonic acid metabolism toward leukotrienes (AAAAI notes the exact cause is not known). Safe analgesics: low-dose acetaminophen or a COX-2 inhibitor such as celecoxib.
- Beta-blockers: cardioselectivity is relative and dose-dependent; a calcium channel blocker is preferred over a beta-blocker for angina in a patient with bronchospastic disease.
How USMLE tests it
- Name the pattern first. Restriction with a low DLCO means parenchymal disease; a low FEV₁/FVC means airway disease (refresh the FEV₁/FVC cheat sheet); a dry cough with normal tests points to ACE inhibitors.
- Then the timeline. Hours to days (NSAID-triggered bronchospasm in AERD, acute nitrofurantoin reaction in week 1), days to months (ACE inhibitor cough), months (amiodarone, peak 6-12 months), 6 months to years (chronic nitrofurantoin after 6 months or more of use; busulfan after an average of 4 years of therapy).
- Exclude the mimics. Infection (especially on methotrexate or steroids), heart failure, lymphangitic cancer and radiation pneumonitis.
- Stop the drug and watch. Merck: the diagnosis rests on the response to withdrawal (and rechallenge, if practical). Glucocorticoids are added for significant amiodarone or checkpoint-inhibitor pneumonitis.
- Monitoring questions: amiodarone means baseline CXR, PFTs with DLCO, thyroid and liver tests (see antiarrhythmics class I-IV); bleomycin means serial chest films or DLCO and low FiO₂. Merck notes that the benefit of routine screening is unproven, but the labels still call for it.
Key takeaways
- Drug-induced lung disease = timing + pattern + exclusion; stop the drug first.
- Amiodarone: pneumonitis peaking at 6-12 months, restriction with a falling DLCO, high-attenuation liver on CT; baseline CXR and PFTs with DLCO, then history, exam and CXR every 3-6 months.
- Bleomycin: dose-related pneumonitis and fibrosis (over 400 units, age over 70, renal impairment); monitor DLCO; avoid high FiO₂.
- Busulfan: late fibrosis. Methotrexate: hypersensitivity-type pneumonitis; rule out Pneumocystis. Nitrofurantoin: acute eosinophilic reaction in week 1 or chronic fibrosis after 6 months.
- Checkpoint inhibitors: grade 2 pneumonitis = hold and steroids; grade 3-4 = stop permanently.
- Airway reactions: ACE inhibitor cough (bradykinin, switch to ARB), AERD (asthma, polyps, NSAIDs), nonselective beta-blockers (bronchospasm, including timolol drops).
- For anything rarer, check the Pneumotox database.
Sources
- Drug-Induced Pulmonary Disease — Merck Manual Professional Edition (2025)
- Amiodarone — Pneumotox, The Drug-Induced Respiratory Disease Website (2026)
- PACERONE (amiodarone) tablets label — DailyMed (2025)
- Bleomycin for Injection label — DailyMed (2024)
- MYLERAN (busulfan) tablets label — DailyMed (2025)
- MACROBID (nitrofurantoin) capsules label — DailyMed (2025)
- TREXALL (methotrexate) tablets label — DailyMed (2026)
- KEYTRUDA (pembrolizumab) label — DailyMed (2026)
- Medications for Hypertension — Merck Manual Professional Edition (2025)
- Cough in Adults — Merck Manual Professional Edition (2025)
- Asthma — Merck Manual Professional Edition (2026)
- Aspirin-Exacerbated Respiratory Disease (AERD) — American Academy of Allergy, Asthma & Immunology (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
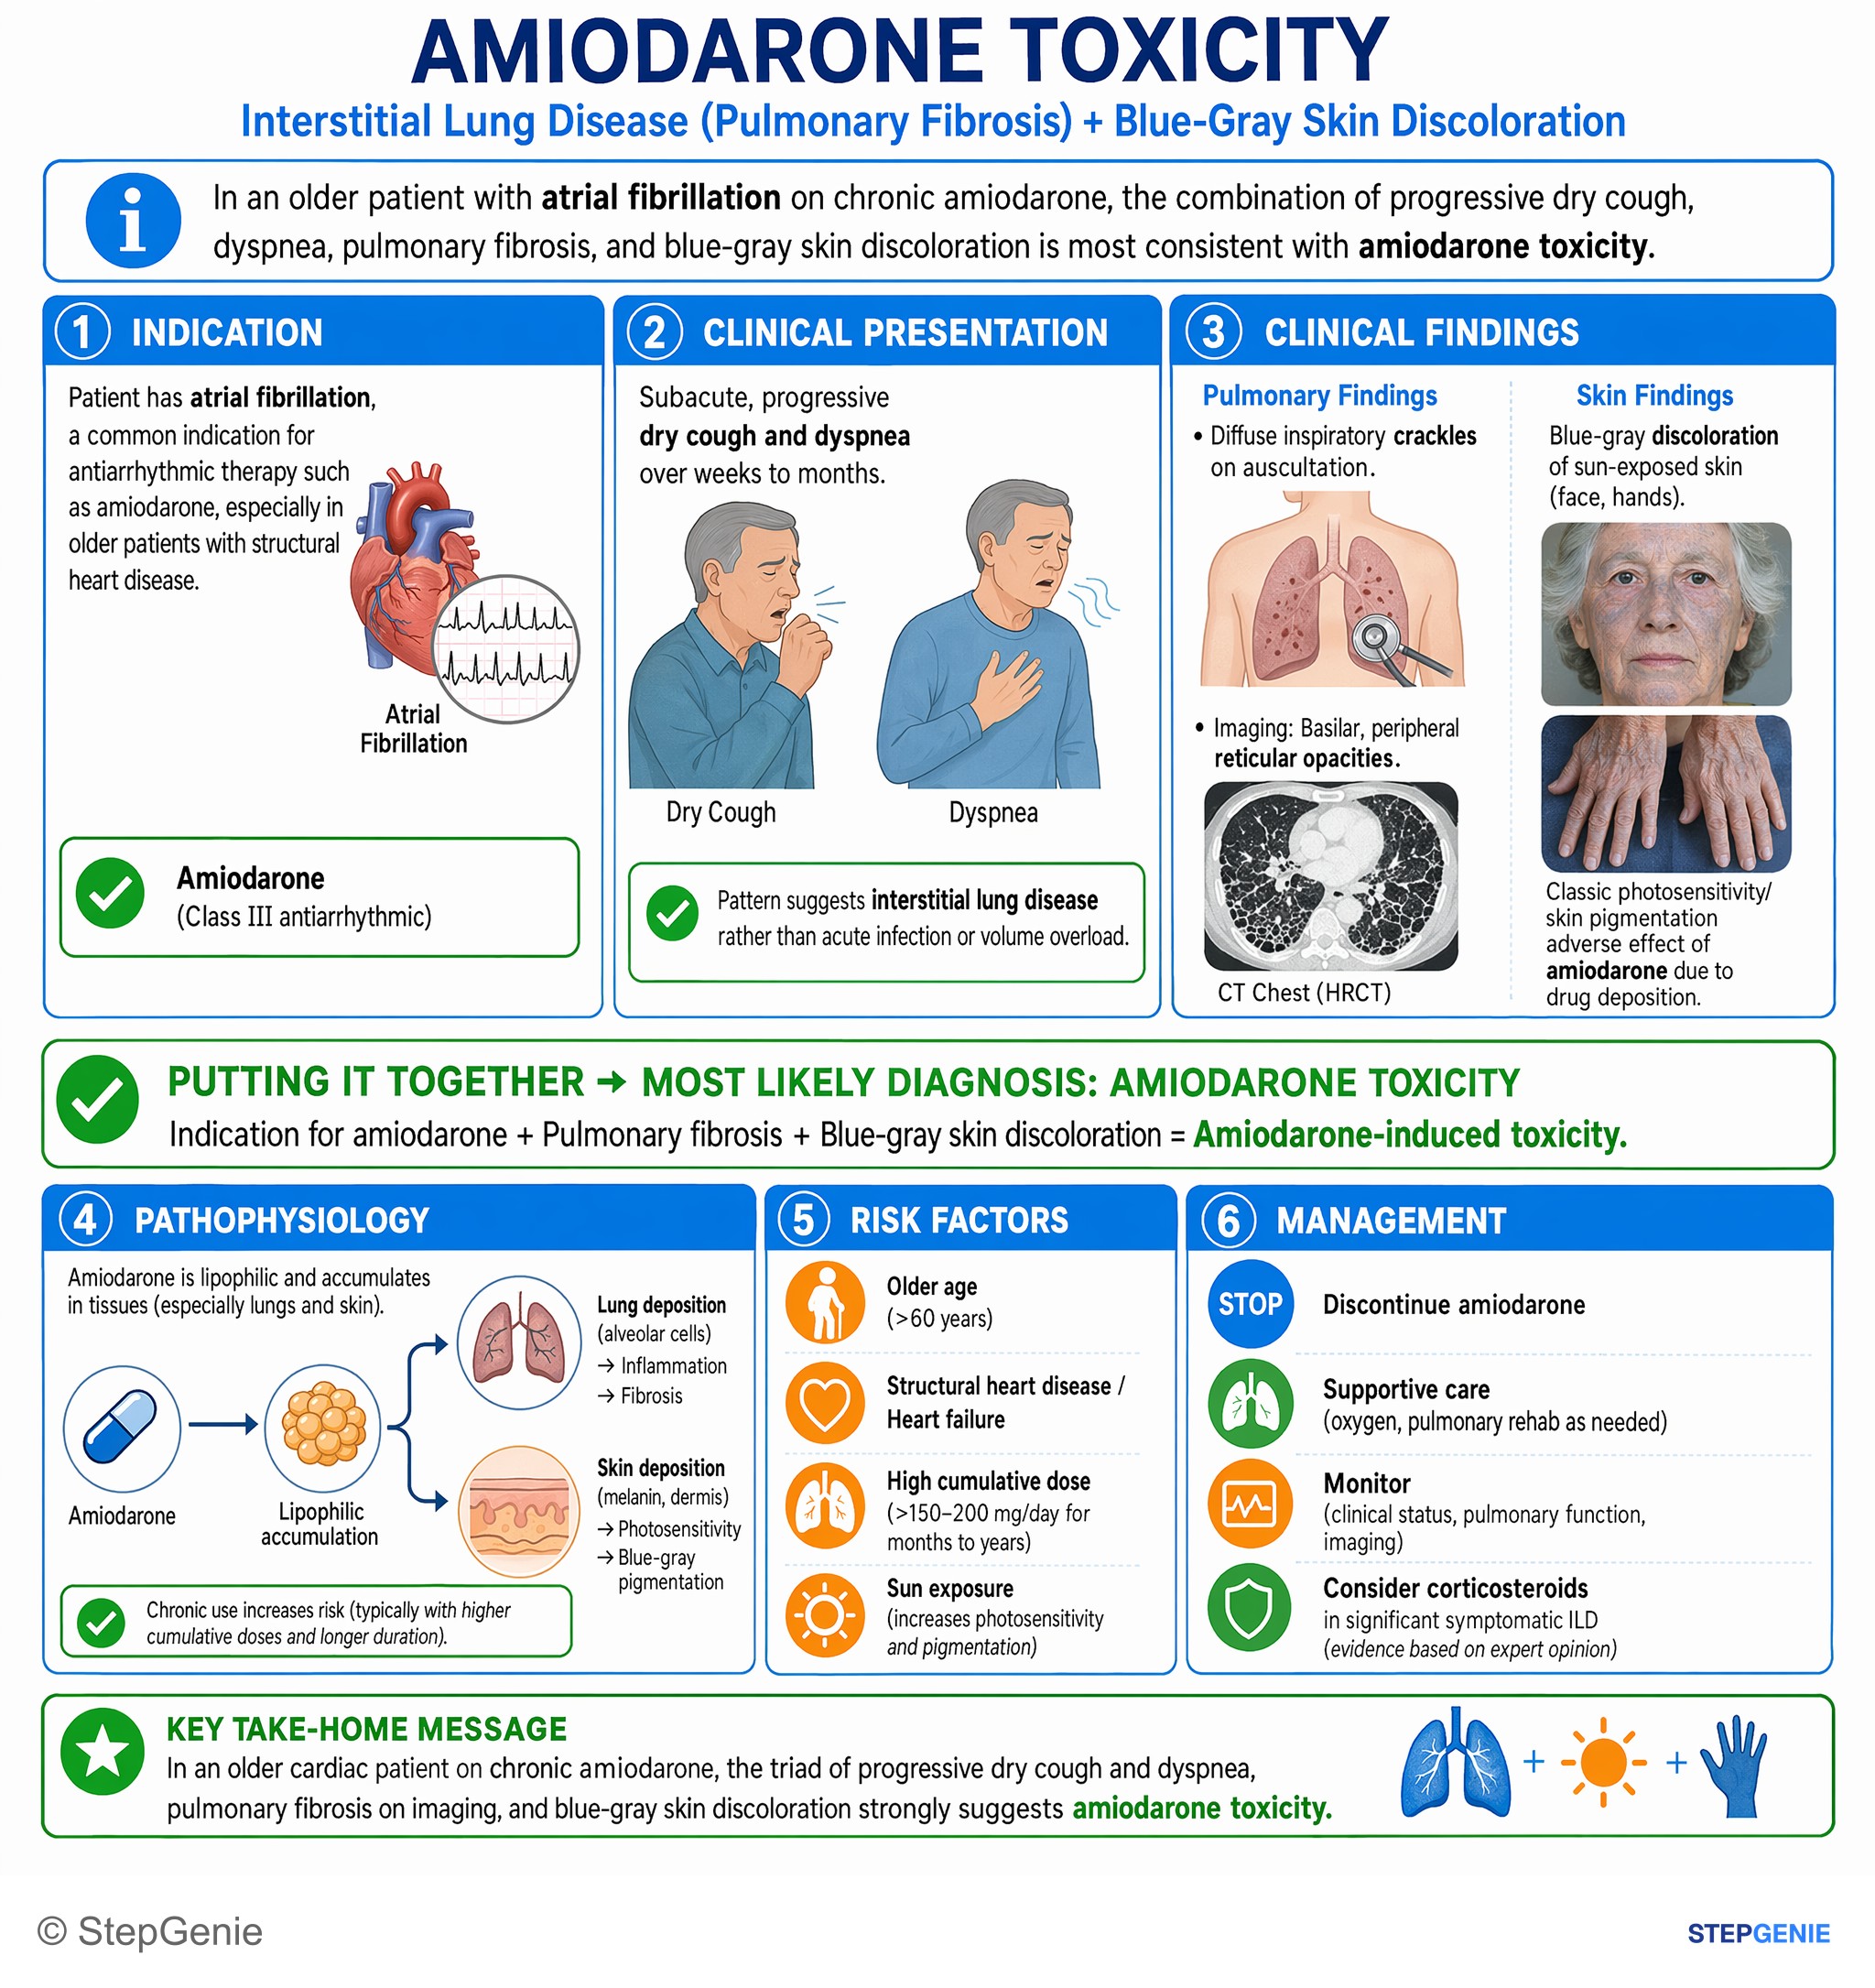
Amiodarone-induced interstitial lung disease with blue-gray skin discoloration: chronic use → pulmonary fibrosis + photosensitivity/skin…
USMLE Step 1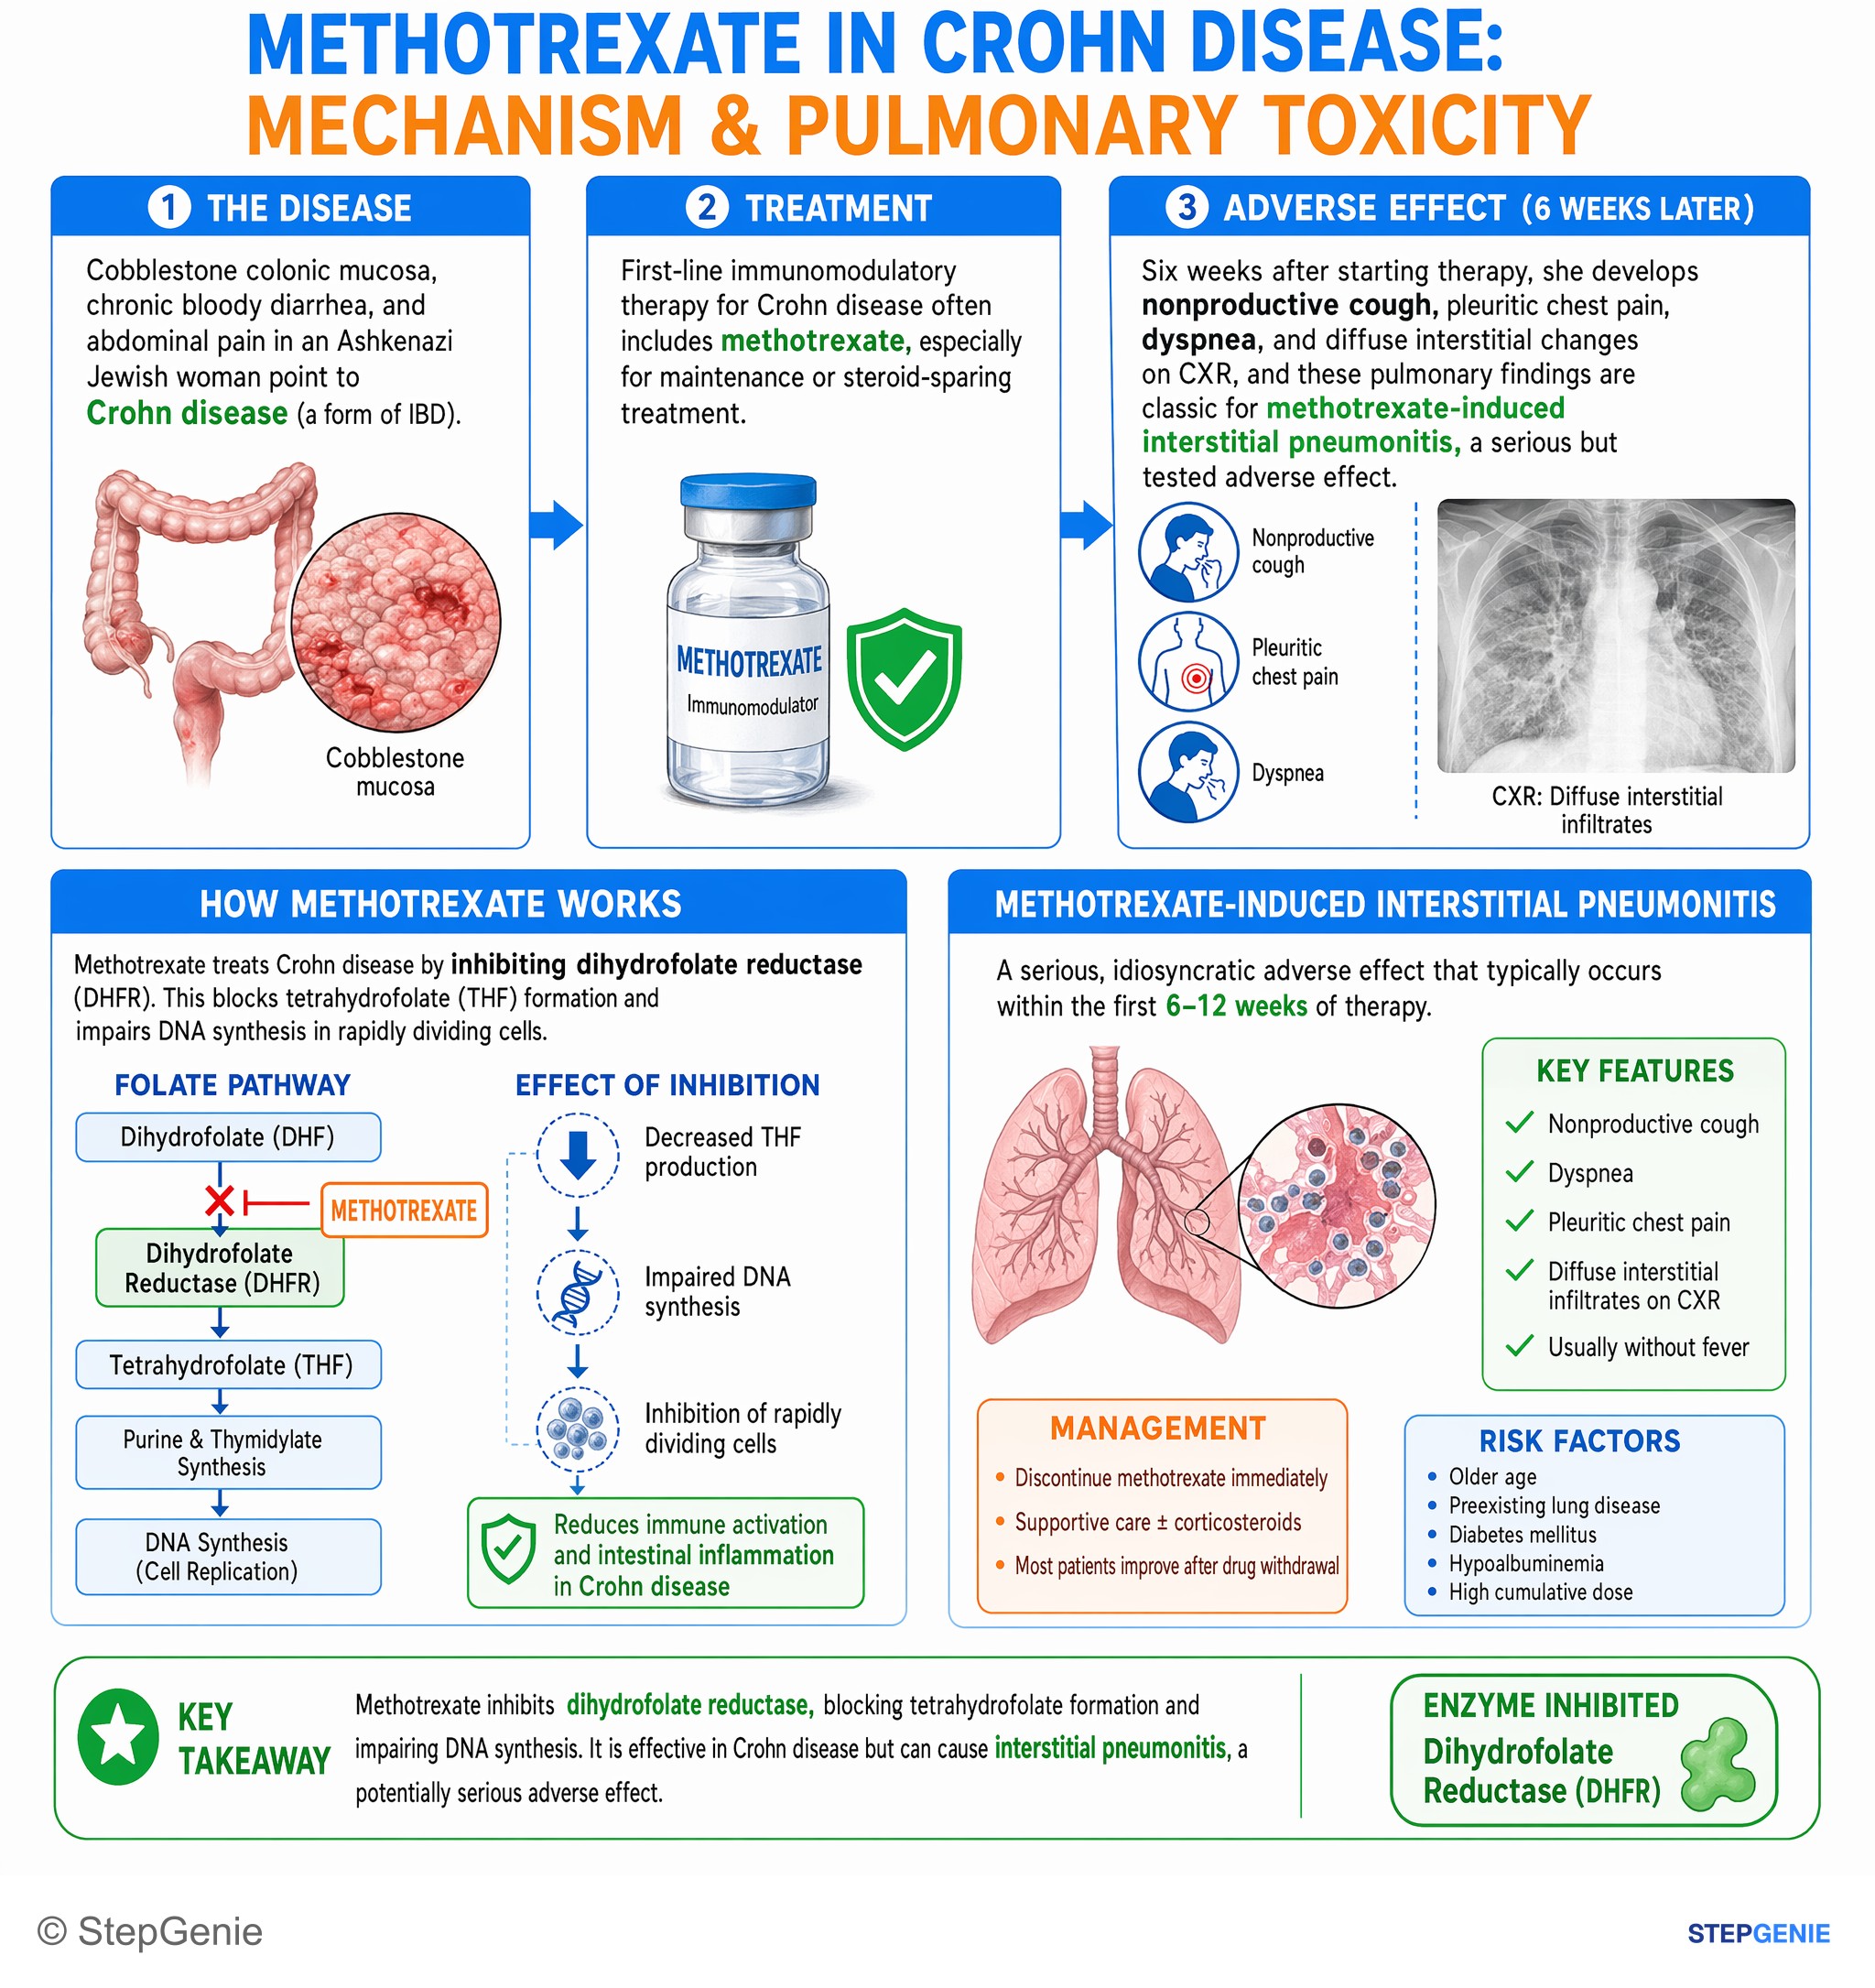
Methotrexate treats Crohn disease by inhibiting dihydrofolate reductase; can cause pulmonary toxicity (nonproductive cough, dyspnea…
USMLE Step 1Frequently Asked Questions
Which drugs cause pulmonary fibrosis?
The classic exam list is bleomycin, busulfan, amiodarone, methotrexate and nitrofurantoin. Bleomycin causes dose-related pneumonitis that can progress to fibrosis, especially above 400 units total, after age 70 or with renal impairment. Busulfan causes a rare, late fibrosis, often years into therapy. Amiodarone and methotrexate mainly cause pneumonitis that can scar, and nitrofurantoin causes chronic interstitial pneumonitis or fibrosis after six months or more of continuous use. Checkpoint inhibitors and cyclophosphamide are also on Merck's list.
How does amiodarone pulmonary toxicity present?
It usually presents as cough and progressive dyspnea, sometimes with low-grade fever, malaise or pleuritic pain, most often 6 to 12 months into therapy, although it can appear within days or after years and even at low doses. Imaging shows patchy ground-glass, reticular or consolidative opacities, and unenhanced CT may show a high-attenuation liver and thyroid. Pulmonary function tests show restriction with a falling DLCO. Treatment is stopping amiodarone and, for significant disease, a prolonged course of glucocorticoids.
What monitoring is needed for amiodarone and bleomycin lung toxicity?
For amiodarone, the label calls for a baseline chest x-ray and pulmonary function tests including diffusion capacity, then history, examination and chest x-ray every 3 to 6 months or whenever symptoms occur, plus thyroid and liver tests. For bleomycin, the label recommends chest x-rays every 1 to 2 weeks and, if DLCO is used, monthly measurements, stopping the drug when DLCO falls below 30% to 35% of the pretreatment value. Patients who have had bleomycin should receive FiO2 near room air during surgery.
How do acute and chronic nitrofurantoin lung reactions differ?
The acute reaction is a hypersensitivity pneumonitis that usually appears in the first week of treatment, with fever, chills, cough, chest pain, dyspnea, infiltrates or pleural effusion, and eosinophilia; it reverses, often dramatically, when the drug is stopped. The chronic reaction develops insidiously after six months or more of continuous use, typically long-term UTI prophylaxis in older adults, with dyspnea, cough and diffuse interstitial pneumonitis or fibrosis but little fever, and it may leave permanent damage.
What is aspirin-exacerbated respiratory disease?
Aspirin-exacerbated respiratory disease, or Samter triad, combines asthma, chronic rhinosinusitis with nasal polyps, and respiratory reactions such as bronchospasm and nasal congestion after aspirin or other COX-1 inhibiting NSAIDs. It affects about 9% of adults with asthma and 30% of those with asthma and nasal polyps. Classic teaching links it to a shift in arachidonic acid metabolism toward leukotrienes. Management is NSAID avoidance, low-dose acetaminophen or celecoxib for pain, inhaled steroids, leukotriene modifiers and, in some patients, aspirin desensitization.
How is checkpoint inhibitor pneumonitis managed?
Immune-mediated pneumonitis occurs in about 3.4% of patients on pembrolizumab and is more common after thoracic radiation. For grade 2 pneumonitis the drug is withheld and prednisone 1 to 2 mg/kg/day or equivalent is given until improvement to grade 1 or less, followed by a taper over at least a month; treatment may resume after recovery. Grade 3 or 4 pneumonitis means permanent discontinuation. As with any suspected drug-induced pneumonitis, infection should be excluded.