An aspergilloma is a fungus ball colonizing a pre-existing lung cavity (classically an old tuberculosis cavity) in a patient who is not immunocompromised: it looks like a round mass with a rim of air inside the cavity, causes hemoptysis or nothing at all, and is resected if it bleeds. Invasive aspergillosis is angioinvasive infection in an immunocompromised host (prolonged neutropenia, transplant, high-dose glucocorticoids, chronic granulomatous disease) with nodules and a halo sign on CT, and the IDSA 2016 guideline recommends voriconazole as primary therapy. ABPA is a hypersensitivity reaction in asthma or cystic fibrosis (high IgE, eosinophilia, mucus plugs, bronchiectasis) treated with glucocorticoids, with itraconazole to spare steroids.
The Q-bank vignette
A 54-year-old man treated for pulmonary tuberculosis 10 years ago has coughed up blood-streaked sputum on several occasions over 3 months. He is afebrile and has no weight loss. Chest CT shows a round, solid mass inside a thick-walled right upper lobe cavity, separated from the cavity wall by a crescent of air. Serum Aspergillus IgG is elevated.
Most likely diagnosis? Aspergilloma (fungus ball).
Why it's an aspergilloma
- What it is: a mass of tangled hyphae, fibrin and few inflammatory cells sitting inside a cavity, usually without invading the wall. IDSA treats a single aspergilloma as one form of chronic pulmonary aspergillosis (CPA) with a favorable prognosis.
- The host: someone with a structural cavity (old TB is the classic stem; bronchiectasis, tumors and other destructive lung diseases also qualify) who is not immunosuppressed.
- The symptom: often none; otherwise cough and hemoptysis, which can be severe. Fever and weight loss argue for something else.
- The image: a roughly spherical shadow with surrounding air inside a cavity.
- The confirmation: Aspergillus IgG. Serum galactomannan is a poor test here (sensitive in only about 38% of aspergilloma cases in the study IDSA cites).
The four Aspergillus lung syndromes side by side
| Feature | Aspergilloma | Chronic cavitary pulmonary aspergillosis | Invasive aspergillosis | ABPA |
|---|---|---|---|---|
| Host | Old cavity, not immunocompromised | Underlying lung disease, no or minimal immunocompromise | Prolonged neutropenia, stem cell or organ transplant, high-dose glucocorticoids, CGD, advanced HIV | Asthma or cystic fibrosis |
| Mechanism | Fungus ball colonizing a cavity | Slowly progressive cavitation over at least 3 months; fibrosis is an end stage | Angioinvasion: infarction, hemorrhage, dissemination | Hypersensitivity (types I, III and IV); fungus stays in the airway lumen |
| Symptoms | None, cough or hemoptysis | Weight loss, fatigue, productive cough, hemoptysis; often mistaken for TB | Cough, pleuritic chest pain, hemoptysis, dyspnea; can progress to respiratory failure | Asthma flares, brown mucus plugs, wheeze |
| Imaging | Round fungal ball with a rim of air in a cavity | New or enlarging cavities, pericavitary infiltrates, pleural thickening, sometimes a fungal ball | Nodules, halo sign; air crescent later, with neutrophil recovery | Fleeting infiltrates, "finger-in-glove" mucoid impaction, bronchiectasis |
| Key test | Aspergillus IgG | Aspergillus IgG (most sensitive test) | CT; galactomannan in serum or BAL fluid; biopsy | Total IgE and Aspergillus-specific IgE; skin test; eosinophilia |
| Treatment | Observe if asymptomatic and stable; resect if symptomatic | At least 6 months of oral itraconazole or voriconazole if symptomatic or progressing | Voriconazole; alternatives liposomal amphotericin B or isavuconazole | Glucocorticoids; itraconazole to cut steroid use |
Imaging signs that separate them
- Halo sign: a nodule larger than 1 cm surrounded by ground-glass opacity, which reflects hemorrhage around an angioinvasive lesion. It is seen particularly in neutropenic patients with invasive aspergillosis.
- Air crescent in invasive disease: a later sign of invasive mold infection, often appearing as the neutrophil count recovers.
- Air around a fungus ball: in an aspergilloma the air rims a ball inside a cavity that was already there. Same crescent shape, different story; read the host.
- Reverse halo sign: more often associated with mucormycosis than with aspergillosis.
Why every other answer choice is wrong
Invasive aspergillosis. Tempting because Aspergillus plus hemoptysis sounds invasive. Wrong here because the patient is not immunocompromised and has a pre-existing cavity with a ball in it. Pick it when a neutropenic patient (for example, during leukemia induction) or a transplant recipient on high-dose steroids has fever, pleuritic pain and a nodule with a halo; CT is recommended whenever it is suspected, even if the chest radiograph looks normal.
Chronic cavitary pulmonary aspergillosis (CCPA). The closest cousin. Pick it when the patient has at least 3 months of symptoms such as weight loss, fatigue and productive cough, with new cavities, pericavitary infiltrates or pleural thickening on serial imaging. Our patient has no systemic symptoms and a single cavity containing a ball, which fits a single aspergilloma.
Allergic bronchopulmonary aspergillosis. A hypersensitivity reaction, not a cavity problem. Pick it for an asthmatic or cystic fibrosis patient with worsening exacerbations, brown mucus plugs, fleeting infiltrates, bronchiectasis, peripheral eosinophilia and a very high IgE. The airway disease is reviewed in the bronchiectasis Q-bank breakdown.
Reactivation tuberculosis. The history of TB and the upper lobe make it tempting, but reactivation brings fever, night sweats and weight loss, apical infiltrates or cavitary lesions and acid-fast bacilli in sputum, not a separate ball inside a clean old cavity. Hemoptysis after TB can come from the fungus growing in the leftover cavity. Compare the TB patterns in the primary vs reactivation tuberculosis Q-bank.
Mucormycosis. Also an angioinvasive mold, but in a different host: diabetic ketoacidosis, deferoxamine therapy, neutropenia or transplant. Tissue shows broad, ribbon-like, nonseptate hyphae with right-angle branching (Aspergillus has septate hyphae with acute-angle branching). Voriconazole has no activity against it; treatment is liposomal amphotericin B plus surgical debridement.
Cavitary lung cancer. Hemoptysis plus a cavity keeps cancer on the list, and rarely a necrotic cancer becomes infected with Aspergillus and mimics CPA. A discrete ball with a rim of air in a long-standing post-TB cavity, with positive Aspergillus IgG, points to aspergilloma.
Management by syndrome
The recommendations below follow the IDSA 2016 aspergillosis guideline unless noted.
- Single aspergilloma: observe if asymptomatic with no increase in cavity size over 6–24 months. Resect if symptomatic, especially with significant hemoptysis, unless surgery is contraindicated. Systemic antifungals penetrate the ball poorly and are not the treatment; perioperative antifungals are given only if spillage during surgery is a concern.
- Hemoptysis in CPA: oral tranexamic acid, bronchial artery embolization for significant bleeding, and antifungals to prevent recurrence.
- CCPA: at least 6 months of oral itraconazole or voriconazole for symptomatic or progressive disease; posaconazole is third line.
- Invasive aspergillosis: start voriconazole early, while the workup is under way; alternatives are liposomal amphotericin B and isavuconazole. Echinocandins are not recommended as primary monotherapy. Treat for at least 6–12 weeks and reduce immunosuppression when possible. Head-to-head trials have found posaconazole and isavuconazole as effective as voriconazole, with fewer adverse effects.
- Prevention: posaconazole prophylaxis during prolonged neutropenia (for example, acute myeloid leukemia) and in stem cell recipients with graft-versus-host disease; recombinant interferon-γ prophylaxis in chronic granulomatous disease, covered in the CGD overview.
- ABPA: systemic glucocorticoids are the mainstay of treatment; IDSA suggests adding itraconazole, with drug-level monitoring, for patients who remain symptomatic despite steroids or to reduce steroid use.
Exam traps
- Same fungus, four diseases: decide by the host first (cavity, immunosuppression, or asthma/CF), then by the image.
- Galactomannan helps diagnose invasive disease in patients with hematologic cancers or stem cell transplants; it is insensitive for aspergilloma and CPA, where Aspergillus IgG is the test.
- Air crescent in a neutropenic patient who is recovering is part of invasive aspergillosis, not a new aspergilloma.
- Voriconazole side effects: transient visual disturbances, hepatotoxicity, photosensitivity (with skin cancer risk on long-term use), hallucinations and QT prolongation.
- Voriconazole does not treat mucormycosis; a mold infection that breaks through voriconazole should raise that possibility.
- Antifungals don't dissolve a fungus ball; a bleeding aspergilloma needs embolization or surgery.
Worked example: the neutropenic version
Vignette. A 48-year-old woman is 12 days into induction chemotherapy for acute myeloid leukemia and has had an absolute neutrophil count below 100/µL for 10 days. Despite broad-spectrum antibiotics she has fever, pleuritic chest pain and scant hemoptysis. Chest CT shows a 2-cm nodule surrounded by ground-glass opacity. BAL galactomannan is positive. What is the most appropriate treatment?
Answer: Voriconazole (IDSA 2016 primary therapy), with liposomal amphotericin B or isavuconazole as alternatives.
Why the distractors fail: surgical resection is the answer for a bleeding aspergilloma in a cavity, not for angioinvasive disease; prednisone is for ABPA and would worsen invasive infection; fluconazole has no useful mold activity; and an echinocandin alone is not recommended as primary therapy.
Key takeaways
- Aspergilloma: fungus ball in an old cavity, non-immunocompromised host, hemoptysis; observe or resect.
- CCPA: at least 3 months of symptoms and progressive cavities; Aspergillus IgG; at least 6 months of an oral azole.
- Invasive aspergillosis: neutropenia or transplant, halo sign, galactomannan; voriconazole (IDSA 2016).
- ABPA: asthma or CF, high IgE, eosinophilia, mucus plugs; glucocorticoids, plus itraconazole to spare steroids.
- Hyphae: Aspergillus septate with acute-angle branching; Mucorales broad, nonseptate, right-angle branching.
Sources
- Practice Guidelines for the Diagnosis and Management of Aspergillosis: 2016 Update — Infectious Diseases Society of America
- Aspergillosis — Merck Manual Professional Edition
- Allergic Bronchopulmonary Aspergillosis (ABPA) — Merck Manual Professional Edition
- Mucormycosis — Merck Manual Professional Edition
- Tuberculosis (TB) — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
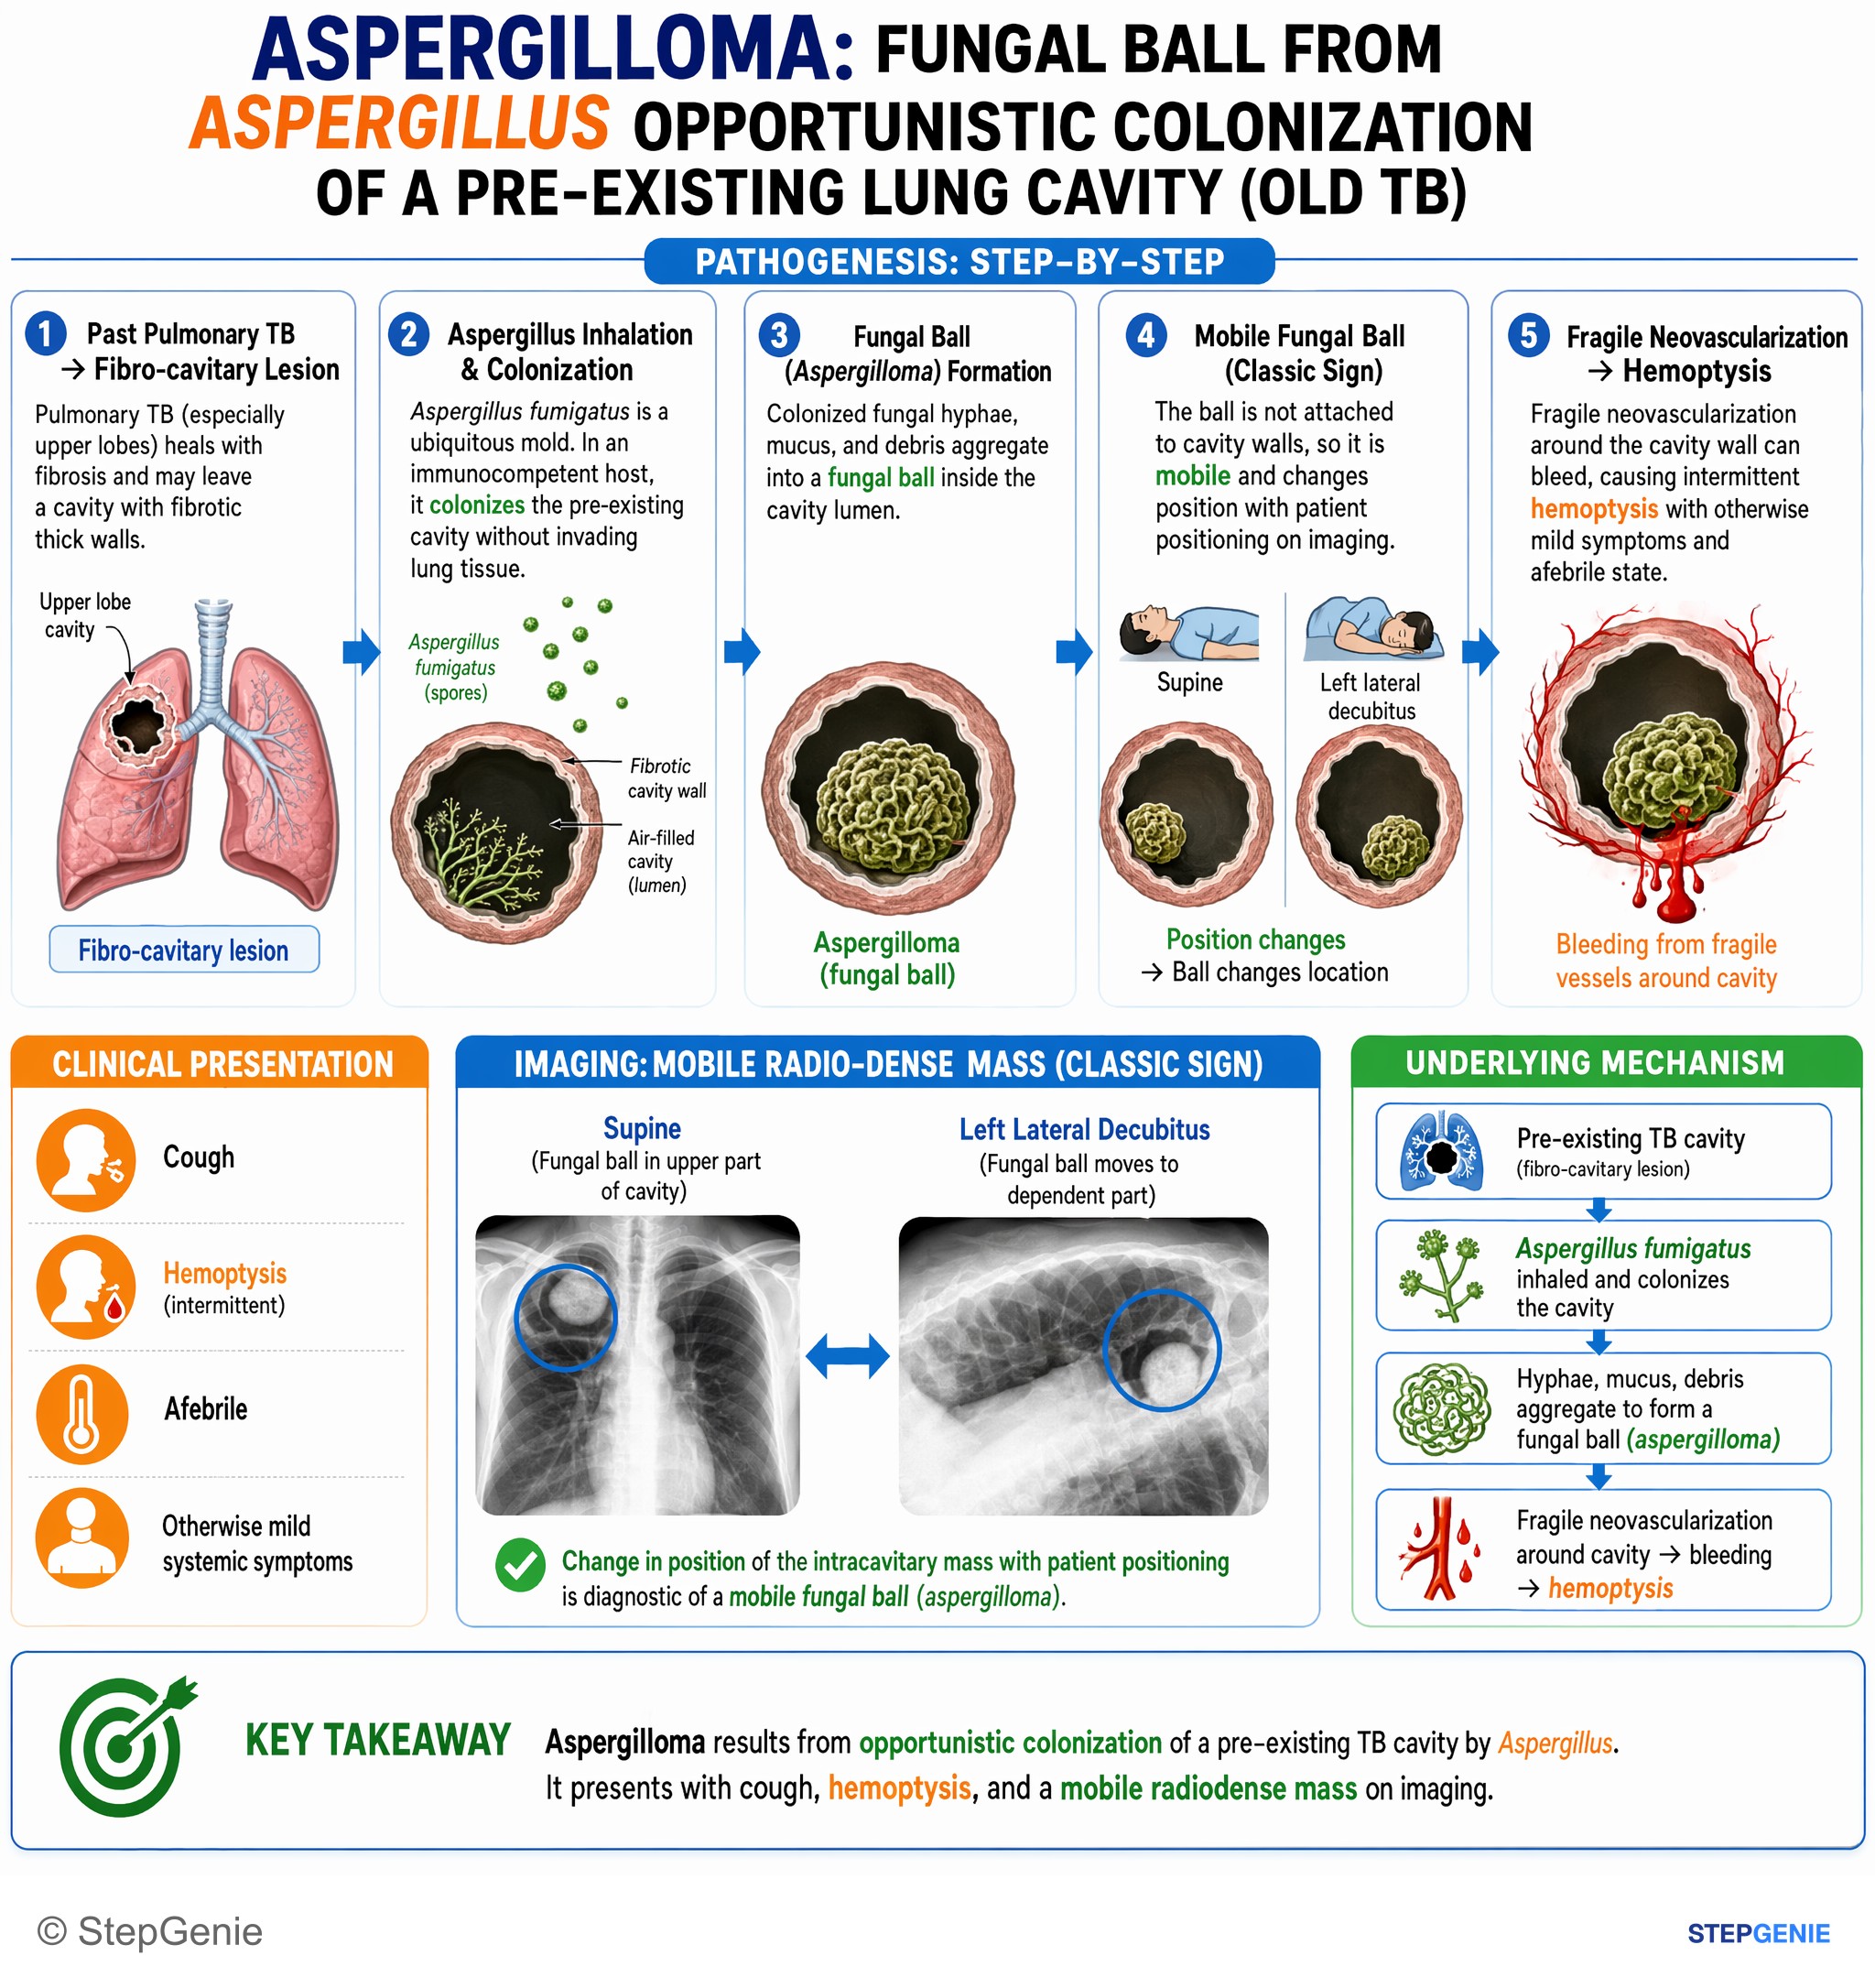
Aspergilloma: fungal ball from Aspergillus opportunistic colonization of a pre-existing lung cavity (old TB); causes cough, hemoptysis…
USMLE Step 1Frequently Asked Questions
What is the difference between aspergilloma and invasive aspergillosis?
An aspergilloma is a noninvasive fungus ball growing inside a pre-existing lung cavity, usually after tuberculosis, in someone who is not immunocompromised; it causes hemoptysis or no symptoms. Invasive aspergillosis is angioinvasive infection in an immunocompromised host, such as a patient with prolonged neutropenia or a transplant, and shows nodules with a halo sign on CT. An aspergilloma is observed or resected, whereas invasive disease needs antifungal therapy, with voriconazole first line.
What is the treatment for aspergilloma?
Under the IDSA 2016 guideline, an asymptomatic single aspergilloma whose cavity does not grow over 6 to 24 months is observed, while a symptomatic one, especially with significant hemoptysis, is surgically resected if there are no contraindications. Systemic antifungals penetrate the fungus ball poorly. In chronic pulmonary aspergillosis, hemoptysis is managed with tranexamic acid, bronchial artery embolization and antifungal therapy to prevent recurrence.
What does the halo sign mean in aspergillosis?
The halo sign is a nodule larger than 1 cm surrounded by ground-glass opacity, which reflects hemorrhage around an angioinvasive fungal lesion. It is seen particularly in neutropenic patients with invasive pulmonary aspergillosis. An air crescent tends to appear later, often as the neutrophil count recovers, while a reverse halo sign is more often associated with mucormycosis than with aspergillosis.
How is ABPA diagnosed and treated?
ABPA is suspected in a patient with asthma or cystic fibrosis who has frequent exacerbations, brown mucus plugs, fleeting infiltrates, bronchiectasis or eosinophilia. Elevated total IgE and Aspergillus-specific IgE establish the diagnosis, supported by a positive skin test and Aspergillus IgG. Systemic glucocorticoids are the mainstay, and itraconazole is added to reduce steroid use or for disease that persists despite steroids.
Why is voriconazole the drug of choice for invasive aspergillosis?
The IDSA 2016 guideline gives voriconazole a strong recommendation, based on high-quality evidence, as primary therapy for invasive pulmonary aspergillosis, with liposomal amphotericin B or isavuconazole as alternatives and treatment for at least 6 to 12 weeks. Voriconazole can cause visual disturbances, hepatotoxicity, photosensitivity and QT prolongation, and it has no activity against mucormycosis.