Pulmonary embolism (PE) is one of those USMLE “blink and you miss it” diagnoses: the patient looks like a lot of other things (pneumonia, panic attack, MI), but the correct next step depends on recognizing the pattern fast. A memory palace makes PE stick because you can walk through the pathophys + diagnosis + treatment in one mental scene.
The Memory Palace: “The Lung Airport Security Checkpoint”
Picture the pulmonary vasculature as an airport where blood is trying to board oxygen flights. A clot (embolus) is a suspicious suitcase that jams security, backs up the line, and triggers alarms throughout the terminal.
Room 1 — The Gate Jam (What PE is)
At the security gate, a big suitcase blocks the main lane: embolus obstructs a pulmonary artery → perfusion drops to ventilated alveoli.
One-liner: PE causes a V/Q mismatch with increased dead space (ventilation without perfusion).
- Ventilation: present
- Perfusion: decreased/absent
- Result: hypoxemia + tachypnea
Room 2 — The Alarm Panel (Classic presentation)
Above the gate is a flashing red sign: “SUDDEN”.
Think: sudden onset dyspnea, pleuritic chest pain, tachypnea, tachycardia.
High-yield extras:
- Hemoptysis = suggests pulmonary infarction (more likely with smaller emboli + limited collateral flow)
- Syncope or hypotension = think massive PE with obstructive shock
- Fever can happen (don’t get baited into pneumonia)
Mini-table: “What symptom points where?”
| Finding | Think |
|---|---|
| Sudden dyspnea + pleuritic CP | PE until proven otherwise |
| Hypotension + JVD + clear lungs | Massive PE (obstructive shock) |
| Hemoptysis + pleuritic pain | Pulmonary infarct (often peripheral) |
Room 3 — The “Risk Factor Baggage Claim”
At baggage claim, you see suitcases labeled with PE risk factors. This is where USMLE loves to hide the answer.
“The 3 Suitcase Labels”
- Stasis (long flight/immobility, stroke, heart failure, hospitalization)
- Endothelial injury (surgery, trauma)
- Hypercoagulable state (cancer, pregnancy, OCPs, Factor V Leiden, antiphospholipid syndrome)
One-liner: PE risk factors = Virchow triad.
High-yield: DVT origin
- Most PEs come from proximal lower extremity DVTs (popliteal/femoral/iliac) rather than distal calf veins.
Room 4 — The “Gas Exchange Billboard” (ABG + physiology)
There’s a big billboard displaying blood gases:
ABG pattern you should expect
- Respiratory alkalosis early: hyperventilation →
- Hypoxemia:
- Increased A–a gradient (key testable concept)
One-liner: PE typically causes hypoxemia + respiratory alkalosis + increased A–a gradient.
High-yield physiology:
- PE decreases perfusion → some alveoli become dead space
- Hypoxemia triggers hyperventilation
- The body may also shunt blood to better-perfused units, worsening mismatch
Room 5 — The “ECG Security Camera” (EKG + CXR)
You check the security footage.
ECG: what’s actually high-yield
Most common: sinus tachycardia.
Classic board-famous but less sensitive:
- S1Q3T3 (deep S in I, Q wave + inverted T in III) = acute right heart strain
- Right axis deviation, RBBB, T-wave inversions in right precordials (V1–V4) can show strain
CXR: often unimpressive
- Can be normal
- May show atelectasis or small pleural effusion
“Classic” signs you might see in question stems:
- Hampton hump: wedge-shaped infarct near pleura
- Westermark sign: regional oligemia (decreased vascular markings)
One-liner: Normal CXR + hypoxemia + pleuritic pain = PE is climbing the list.
Room 6 — The “Right Ventricle Panic Room” (Massive PE)
Behind a locked door is the right ventricle (RV) sweating.
What massive PE does
Large clot → abrupt pulmonary vascular resistance → acute RV dilation/strain → decreased LV preload → hypotension.
One-liner: Massive PE = obstructive shock from acute RV failure.
High-yield bedside clue:
- Clear lungs + hypotension + JVD = obstructive physiology (massive PE, tamponade, tension PTX)
Room 7 — The Testing Hallway: Choosing the right next step
This is the “don’t lose points” corridor. The best test depends on stability and pretest probability.
Step 1: Is the patient hemodynamically unstable?
- Unstable (hypotension/shock):
- If PE suspected → bedside echo (look for RV strain)
- Often proceed to urgent reperfusion treatment if high suspicion
- Stable: use pretest probability tools + targeted testing
Step 2: Stable patient—use pretest probability
Common exam flow:
- Low probability + PERC negative → no testing
- Low/intermediate probability → D-dimer
- High probability → go straight to CT pulmonary angiography (CTPA) (don’t waste time with D-dimer)
Quick “D-dimer truth”
- Great for ruling out in low/intermediate risk when negative
- Not specific: elevated in inflammation, pregnancy, cancer, post-op, etc.
Imaging choices (high-yield)
| Test | Best when | Key notes |
|---|---|---|
| CTPA | Most stable patients | First-line imaging in many settings |
| V/Q scan | Pregnancy, contrast allergy, renal failure | Best if normal CXR; “high probability” supports PE |
| Compression ultrasound | DVT suspected; can support PE diagnosis | If proximal DVT found, treat as VTE |
Room 8 — The Treatment Lounge (What to do now)
Immediate management (most suspected/confirmed PEs)
- Anticoagulate (unless contraindicated)
- Heparin products (e.g., UFH/LMWH) initially; DOACs commonly used outpatient depending on scenario
One-liner: PE treatment = anticoagulation; add thrombolysis or thrombectomy if massive/unstable.
When to give thrombolysis?
- Massive PE with hemodynamic instability (shock/hypotension) → systemic thrombolysis (if no major contraindications)
- “Submassive” PE (RV strain but normotensive) → individualized; often anticoagulation ± catheter-directed options depending on bleeding risk and severity
IVC filter: the board-style indication
- Acute VTE + absolute contraindication to anticoagulation (or recurrent VTE despite adequate anticoagulation)
The Visual Mnemonic (Shareable)
“PE = Airport Security JAM”
- Suitcase blocks gate → ↓ perfusion → dead space
- Alarms blare → sudden dyspnea + pleuritic pain + tachycardia
- Baggage labels → Virchow triad
- Gas billboard → resp alkalosis + ↑A–a gradient
- Security camera → sinus tachy (± S1Q3T3)
- RV panic room → massive PE = obstructive shock
- Testing hallway → unstable? echo; stable? D-dimer/CTPA
- Treatment lounge → anticoagulation; thrombolysis if massive
Rapid-Fire USMLE High-Yield Pearls
- Most common ECG: sinus tachycardia
- ABG: respiratory alkalosis + hypoxemia + increased A–a gradient
- Path: PE = V/Q mismatch (dead space)
- Most PEs come from proximal DVTs
- Massive PE: hypotension from acute RV failure
- Negative D-dimer is most useful in low/intermediate risk patients
- Pregnancy/contrast contraindication: consider V/Q scan (especially with normal CXR)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
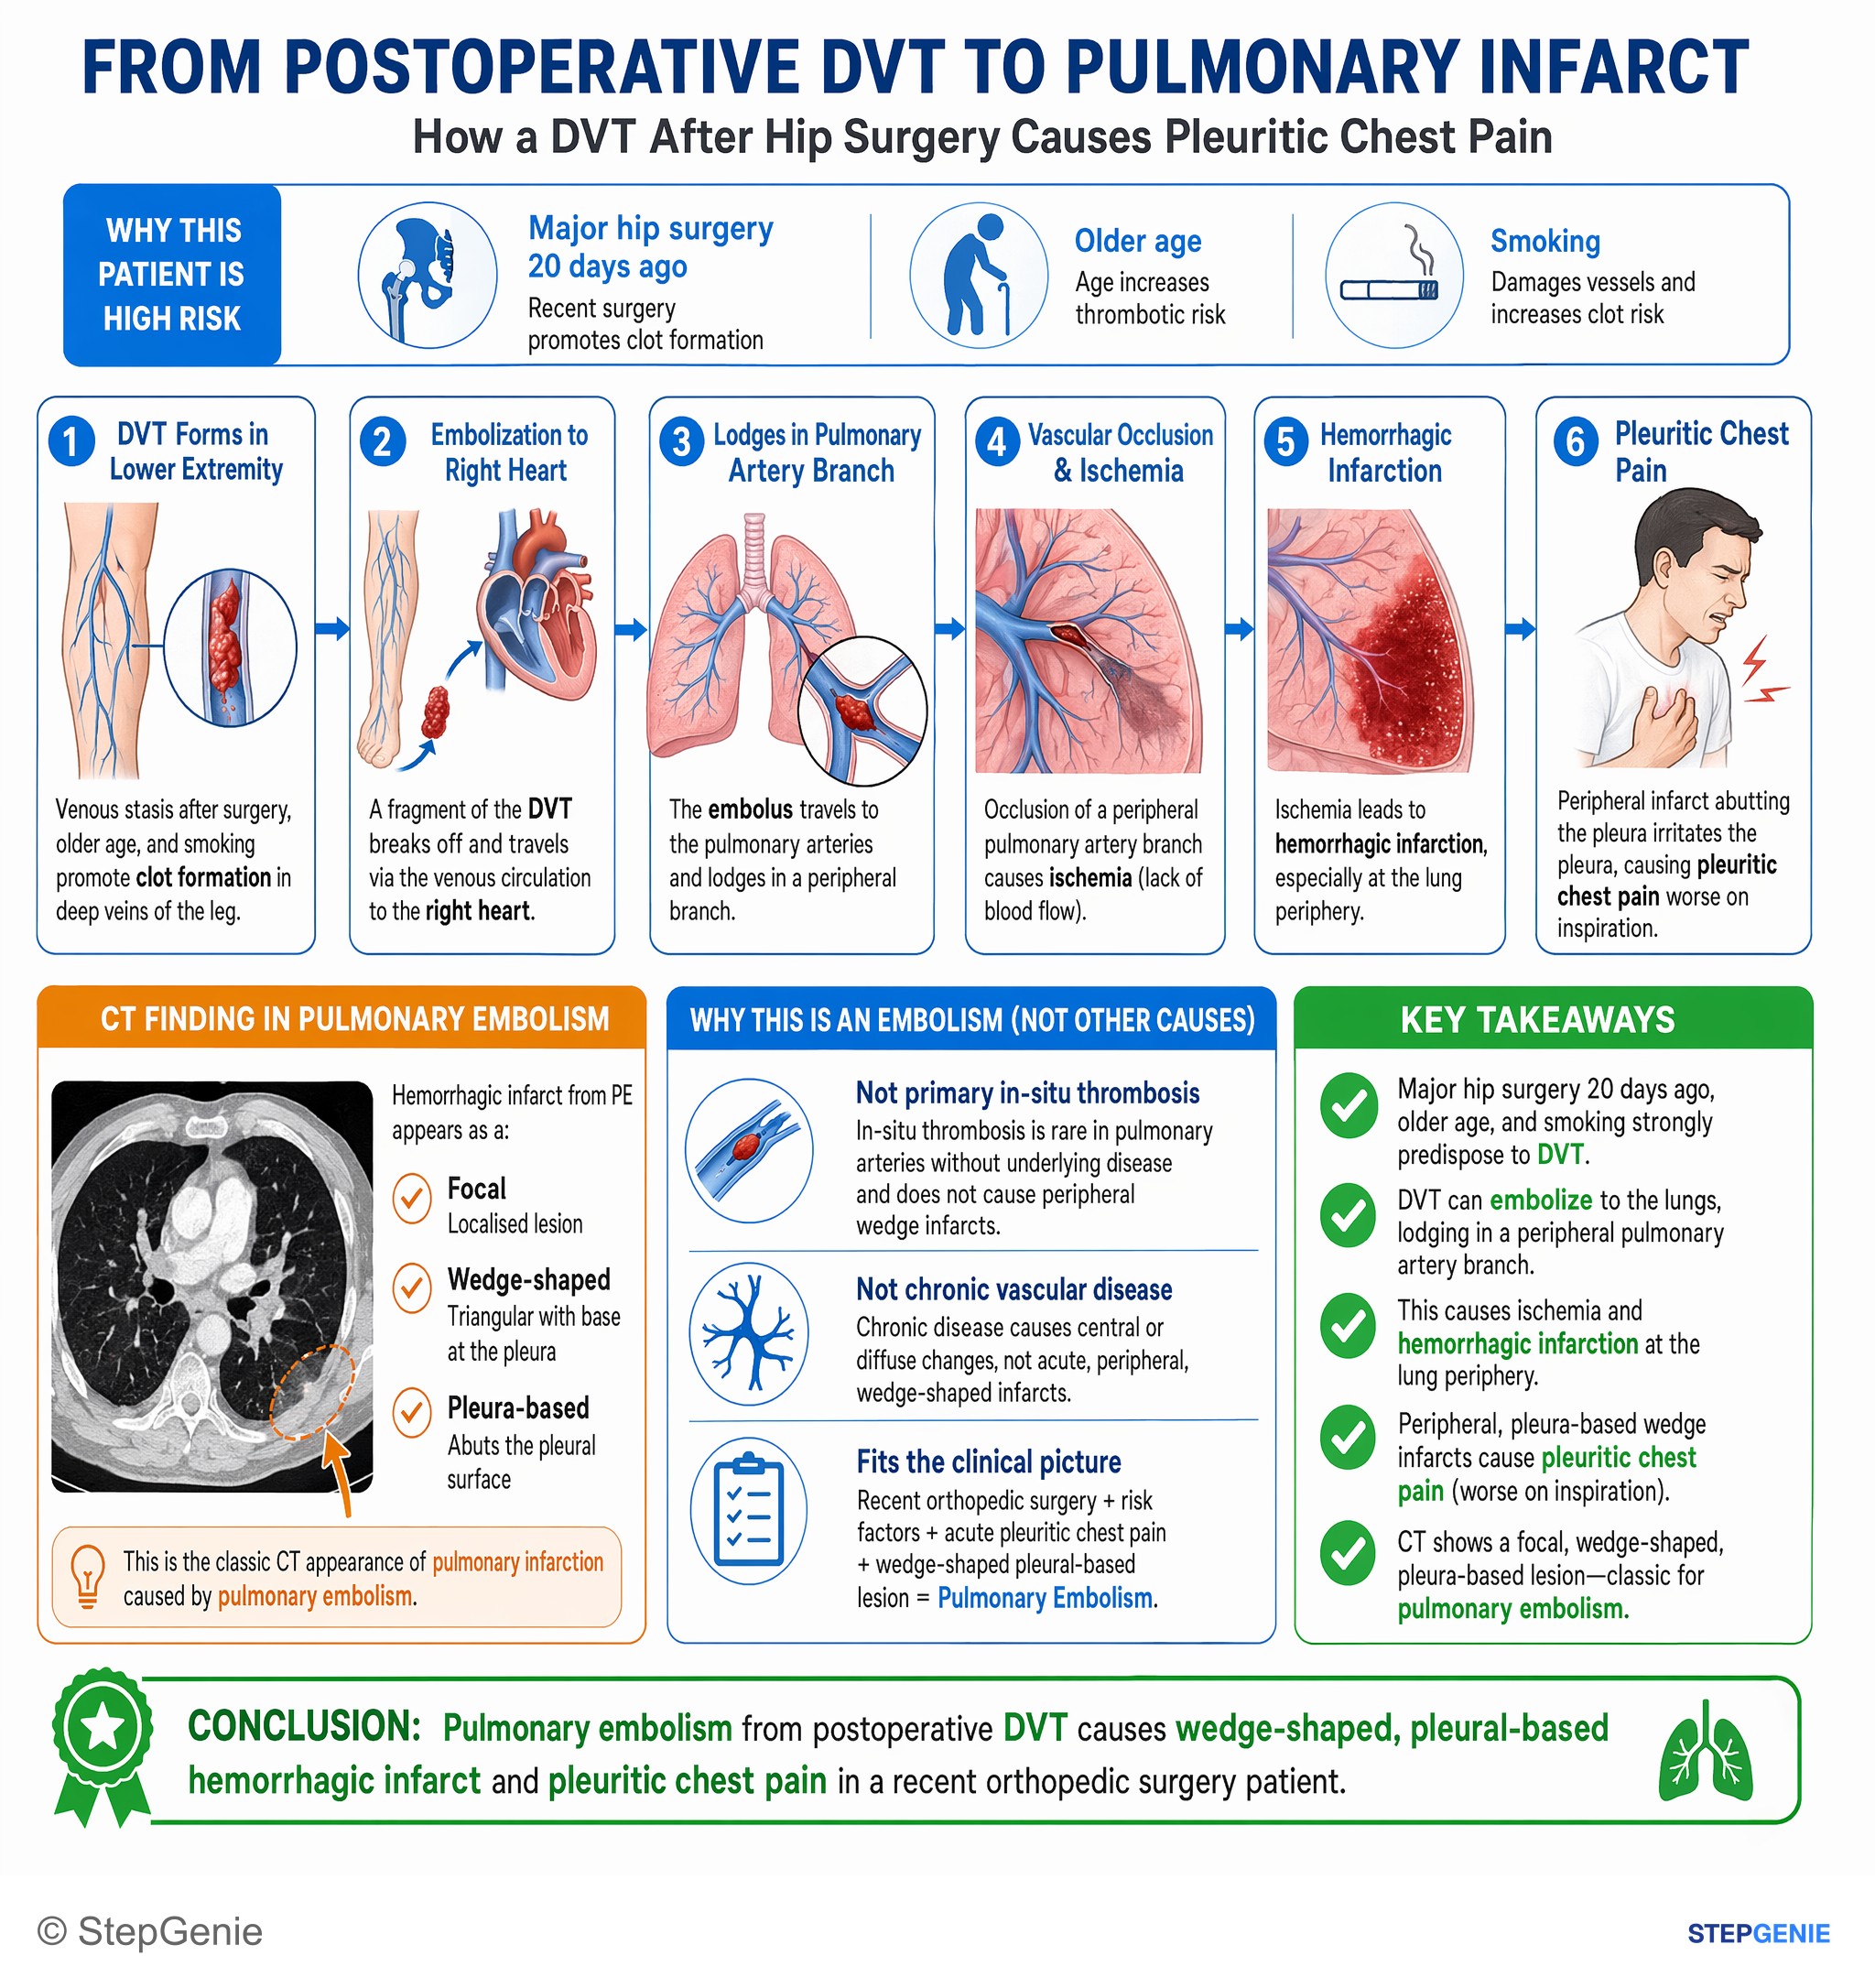
Pulmonary embolism from postoperative DVT causes wedge-shaped, pleural-based hemorrhagic infarct and pleuritic chest pain in a recent…
USMLE Step 1Frequently Asked Questions
Why does pulmonary embolism cause hypoxemia and tachypnea?
Pulmonary embolism causes hypoxemia and tachypnea because an embolus obstructs a pulmonary artery, reducing perfusion to alveoli that are still being ventilated. This creates a V/Q mismatch with increased dead space, meaning ventilation is present but perfusion is decreased or absent. The resulting hypoxemia triggers hyperventilation, so patients often develop tachypnea and an early respiratory alkalosis with a low PaCO2.
What symptoms should make you think of pulmonary embolism instead of pneumonia or panic attack?
Sudden dyspnea, pleuritic chest pain, tachypnea, and tachycardia should make you think strongly of pulmonary embolism. Hemoptysis suggests pulmonary infarction, while syncope or hypotension points toward massive PE with obstructive shock. Fever can also occur in PE, so it should not automatically push you toward pneumonia. A normal chest x-ray with hypoxemia and pleuritic pain also makes PE more likely.
How do you recognize massive pulmonary embolism on exam?
Massive pulmonary embolism is suggested by hypotension or shock, especially when it appears with jugular venous distension and clear lungs. A large clot abruptly raises pulmonary vascular resistance, causing acute right ventricular dilation and strain, which then reduces left ventricular preload and leads to hypotension. This is obstructive shock from acute right heart failure, so syncope, hemodynamic instability, and bedside signs of right-sided strain are major clues.
What is the best next test for suspected pulmonary embolism?
The best next test depends on hemodynamic stability and pretest probability. In an unstable patient with suspected PE, bedside echocardiography is used to look for right ventricular strain and urgent reperfusion treatment may follow if suspicion is high. In stable patients, low or intermediate probability generally leads to D-dimer testing, while high probability should go straight to CT pulmonary angiography rather than wasting time with D-dimer.
What is the first-line treatment for pulmonary embolism, and when do you give thrombolysis?
The first-line treatment for most suspected or confirmed pulmonary emboli is anticoagulation, unless it is contraindicated. Initial therapy commonly uses heparin products such as unfractionated heparin or low-molecular-weight heparin, and DOACs are often used in outpatient management depending on the situation. Thrombolysis or thrombectomy is added for massive or unstable PE, particularly when there is hemodynamic instability such as shock or hypotension.