A ton of pulmonary “gimme” questions aren’t really about memorizing facts—they’re about knowing what each answer choice is trying to bait you into confusing. Surfactant is a classic example: it’s easy to recall “made by type II pneumocytes,” but Step questions love testing mechanism (surface tension), timing (fetal lung development), and consequences (atelectasis vs edema vs shunt). Let’s break it down like a Q-bank explanation where every distractor teaches something.
Clinical Vignette (Q-Bank Style)
A 29-year-old G1P0 at 30 weeks gestation presents in preterm labor. She delivers a premature infant who develops progressive respiratory distress shortly after birth. The baby has tachypnea, nasal flaring, grunting, and intercostal retractions. Pulse oximetry shows hypoxemia. A chest radiograph demonstrates diffuse reticulogranular (“ground-glass”) opacities with air bronchograms.
Which of the following best explains the primary pathophysiology of this infant’s condition?
A. Decreased pulmonary compliance due to increased alveolar surface tension
B. Destruction of alveolar walls due to increased elastase activity
C. Decreased diffusing capacity due to thickening of the alveolar-capillary membrane
D. Increased airway resistance due to loss of radial traction on small airways
E. Increased pulmonary capillary hydrostatic pressure causing alveolar transudate
Correct Answer: A. Decreased pulmonary compliance due to increased alveolar surface tension
This is neonatal respiratory distress syndrome (NRDS) from surfactant deficiency, classically in premature infants.
What surfactant normally does (the Step 1 version)
Surfactant (mostly dipalmitoylphosphatidylcholine—DPPC—and phosphatidylglycerol) reduces surface tension at the air–liquid interface in alveoli.
Why that matters physiologically
By lowering surface tension, surfactant:
- Increases lung compliance → less work required to inflate lungs
- Prevents alveolar collapse (atelectasis), especially at end-expiration
- Stabilizes small alveoli (prevents emptying into larger alveoli)
A key relationship tested on Step is Laplace’s law:
- = pressure needed to keep alveolus open
- = surface tension
- = radius
If surfactant is low → increases → small alveoli (small ) require much higher pressure to stay open → collapse → atelectasis → hypoxemia and respiratory distress.
Pathology + imaging tie-in (Step 2–friendly)
Surfactant deficiency causes alveolar collapse and epithelial injury, leading to hyaline membrane formation (fibrin-rich exudate + necrotic debris). The CXR description (ground-glass + air bronchograms) is classic.
High-yield management hooks
- Antenatal corticosteroids (e.g., betamethasone) → accelerate type II pneumocyte maturation and surfactant production
- Exogenous surfactant can be administered after birth
- Support with oxygen/CPAP as needed (be mindful of oxygen toxicity risks in premies)
Distractor Autopsy: Why the Other Answer Choices Are Wrong (and What They’re Testing)
B. Destruction of alveolar walls due to increased elastase activity
This is pointing to emphysema, especially α1-antitrypsin deficiency (uninhibited elastase) or smoking-related protease/antiprotease imbalance.
Clues you’d expect instead:
- Adult with progressive dyspnea, hyperinflation, barrel chest
- ↓ DLCO in emphysema (especially panacinar/centrilobular)
- CXR: hyperlucency, flattened diaphragm
Why it’s wrong here: NRDS is a compliance/surface tension problem from surfactant deficiency, not alveolar wall destruction.
C. Decreased diffusing capacity due to thickening of the alveolar-capillary membrane
This is aiming for interstitial lung disease/pulmonary fibrosis: thickened alveolar walls impair diffusion.
Clues you’d expect instead:
- Older patient, dry cough, progressive dyspnea
- Restrictive pattern: ↓ TLC, ↓ FVC, normal/↑ FEV1/FVC
- ↓ DLCO (diffusion impairment)
- Imaging: reticular opacities, honeycombing (depending on cause)
Why it’s wrong here: NRDS is primarily alveolar collapse from high surface tension, not thickened diffusion barrier as the initiating problem.
D. Increased airway resistance due to loss of radial traction on small airways
This is another emphysema-flavored distractor. In emphysema, destruction of alveolar septa reduces radial traction, so small airways collapse during expiration → airflow obstruction.
Clues you’d expect instead:
- Obstructive PFTs: ↓ FEV1/FVC, ↑ TLC, ↑ RV
- Prolonged expiration, wheeze (variable)
Why it’s wrong here: NRDS presents at birth and is driven by alveoli failing to stay open, not dynamic small-airway collapse from loss of tethering.
E. Increased pulmonary capillary hydrostatic pressure causing alveolar transudate
This describes cardiogenic pulmonary edema (left-sided heart failure) with increased hydrostatic pressure pushing fluid into alveoli.
Clues you’d expect instead:
- Adult with orthopnea, PND, JVD, S3, peripheral edema
- CXR: Kerley B lines, perihilar “bat wing” edema, pleural effusions
- Often improved with diuretics and afterload reduction
Why it’s wrong here: NRDS isn’t caused by fluid overload into alveoli; it’s surfactant deficiency → atelectasis.
The “Surfactant” Core Facts That Show Up Again and Again
Where it’s made
- Type II pneumocytes
- Also responsible for regeneration of alveolar epithelium after injury
Timing + fetal testing (high yield)
Surfactant production increases late in gestation.
| Concept | What to remember for Step |
|---|---|
| Maturity marker | Lecithin:sphingomyelin (L:S) ratio ≥ 2 suggests fetal lung maturity |
| Another maturity marker | Phosphatidylglycerol (PG) presence supports maturity |
| Big risk factor | Prematurity (esp. <34 weeks) |
| Maternal diabetes | Delays surfactant maturation → increases NRDS risk |
Consequences of low surfactant (memorize this chain)
↓ surfactant → ↑ surface tension → ↓ compliance → atelectasis → V/Q mismatch (shunt physiology) → hypoxemia
Rapid-Fire Exam Pearls (the stuff that wins points)
- Surfactant increases compliance by lowering surface tension. If a stem says “stiff lungs” in a preterm neonate, think surfactant deficiency.
- Ground-glass opacities + air bronchograms in a premature newborn = classic NRDS.
- Antenatal steroids are a common “what is the next best step?” answer because they upregulate surfactant.
- Maternal diabetes is a favorite twist: fetal hyperinsulinemia antagonizes cortisol effects → delayed surfactant production.
- If the question pivots to Laplace’s law, remember: smaller radius alveoli need disproportionately more pressure if surface tension is high.
Bottom Line
In surfactant deficiency, the primary problem is increased alveolar surface tension, causing alveolar collapse and decreased compliance—not airway obstruction, not diffusion barrier thickening, not hydrostatic edema, and not elastase-mediated destruction. The distractors aren’t random; they’re a checklist of other “hypoxemia + respiratory distress” mechanisms you should be able to separate on sight.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
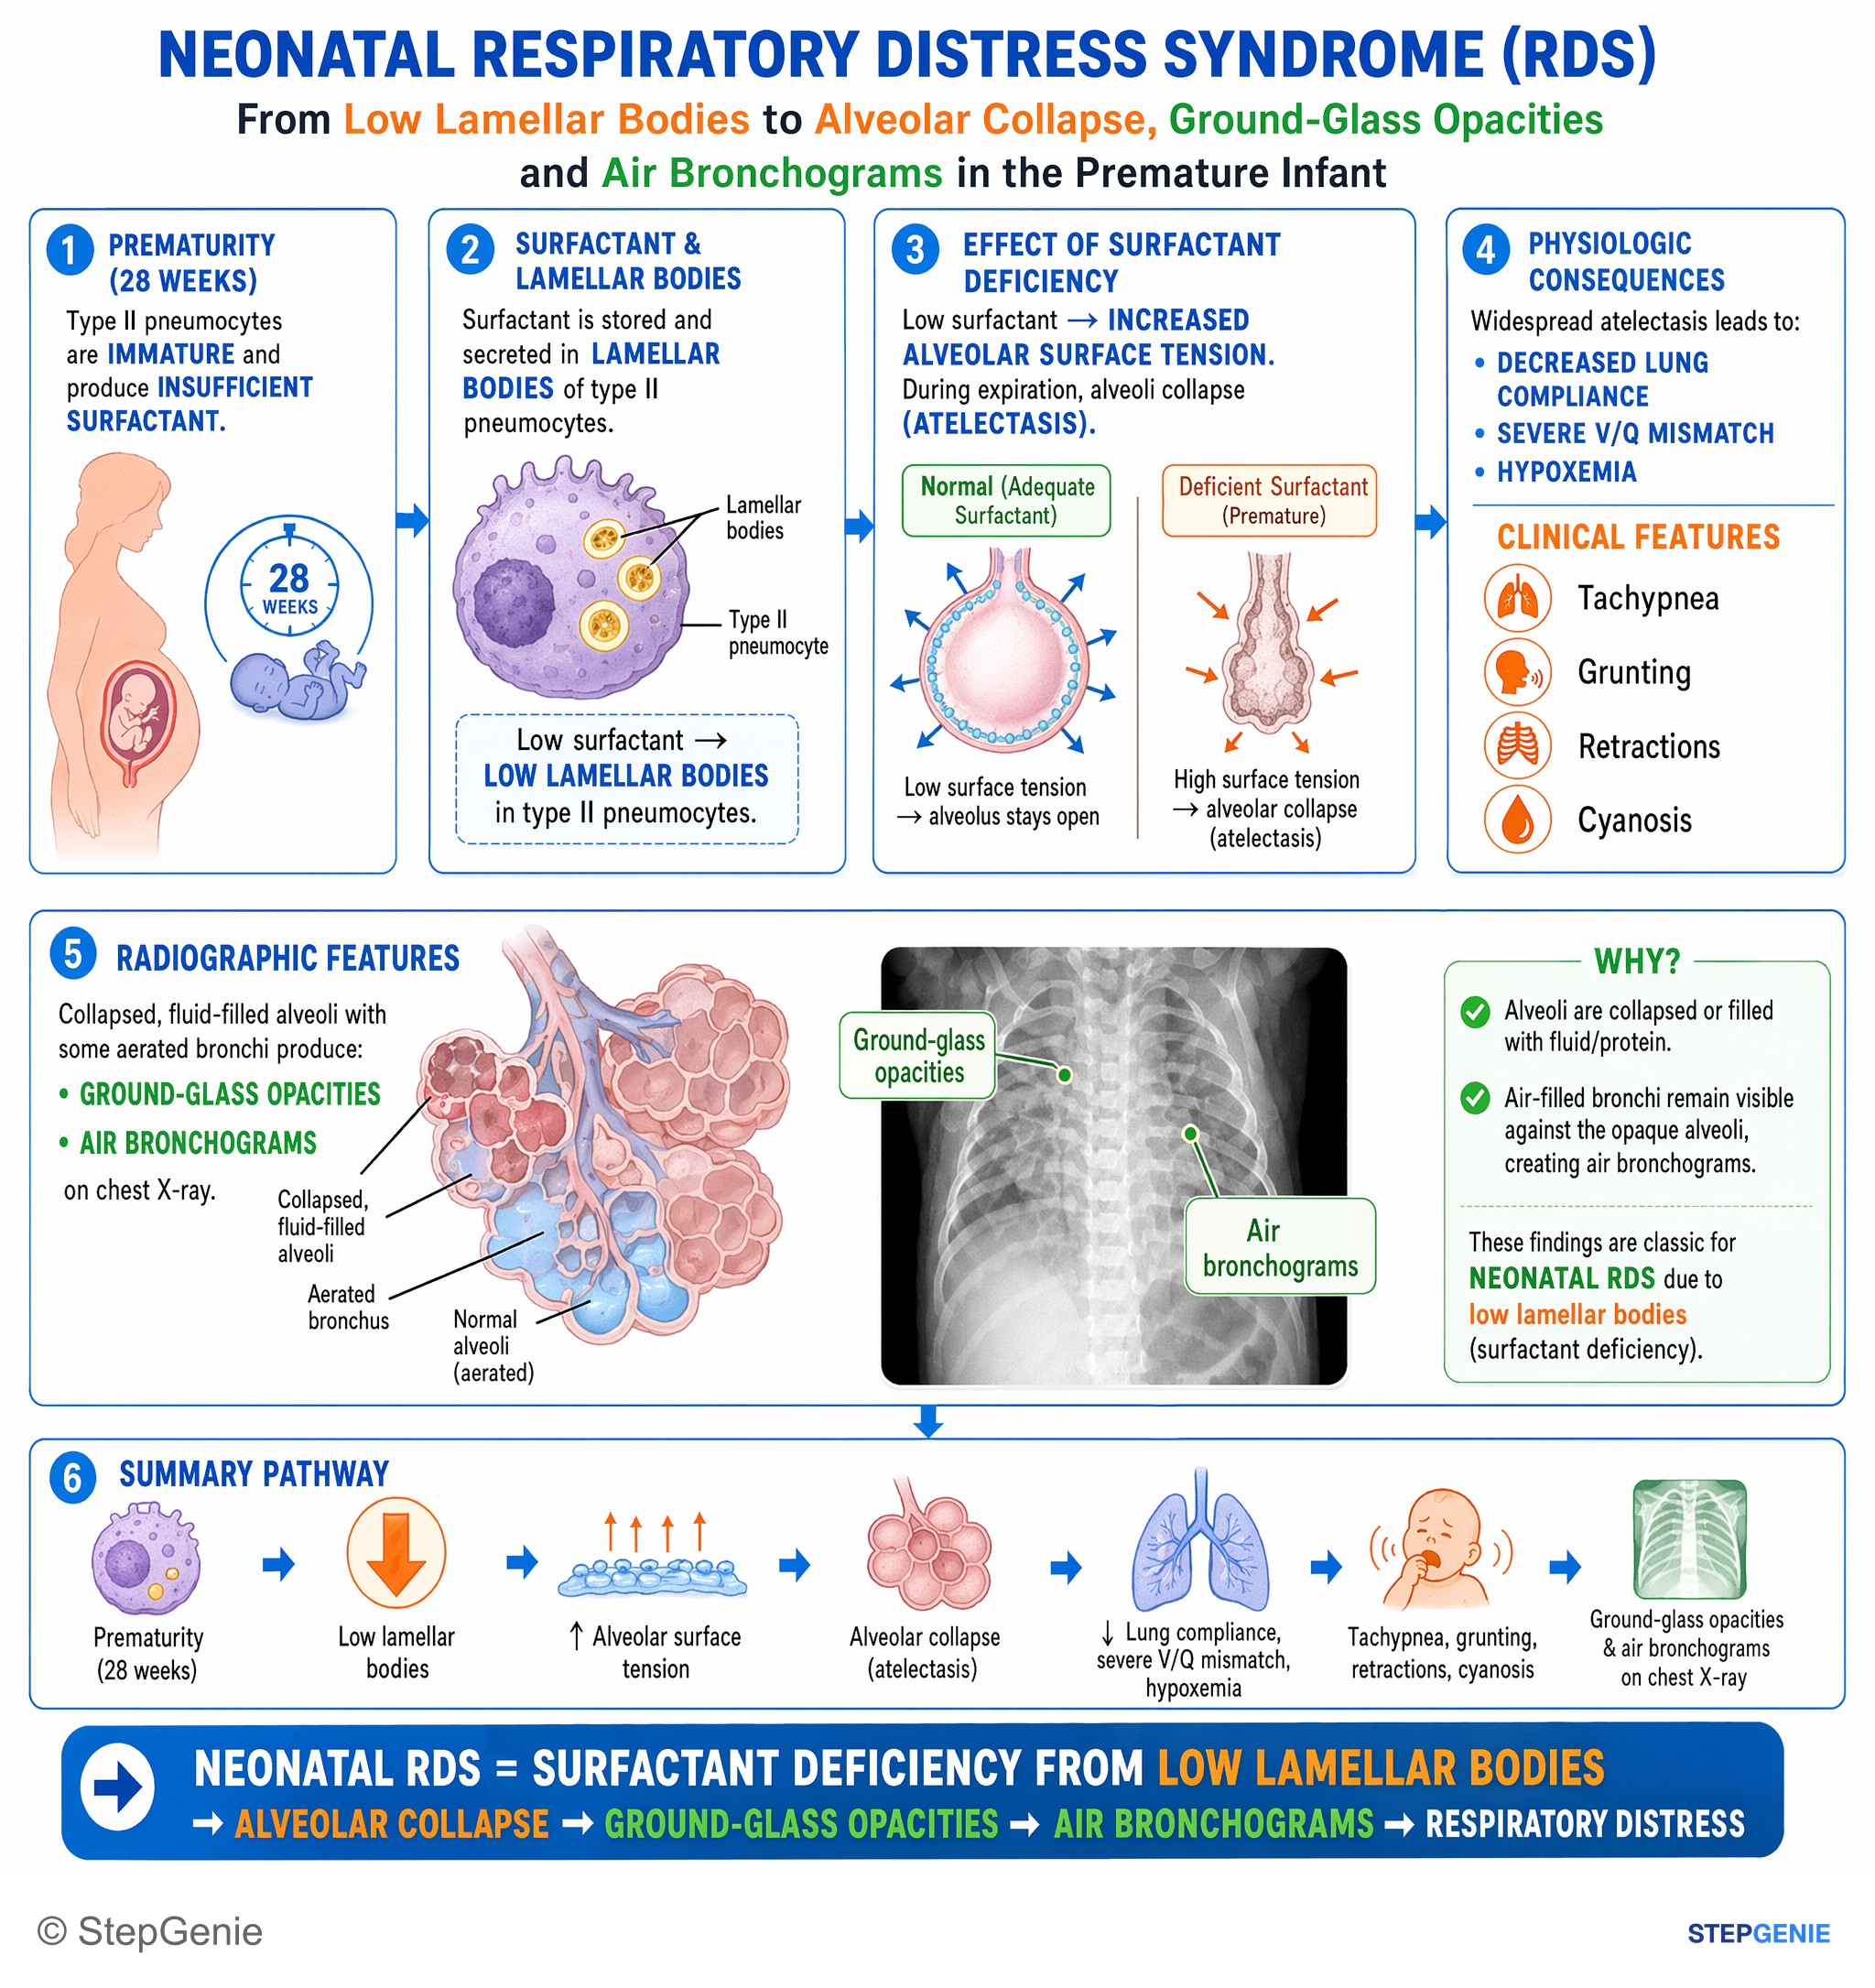
Neonatal respiratory distress syndrome from surfactant deficiency due to low lamellar bodies → alveolar collapse, ground-glass opacities…
USMLE Step 1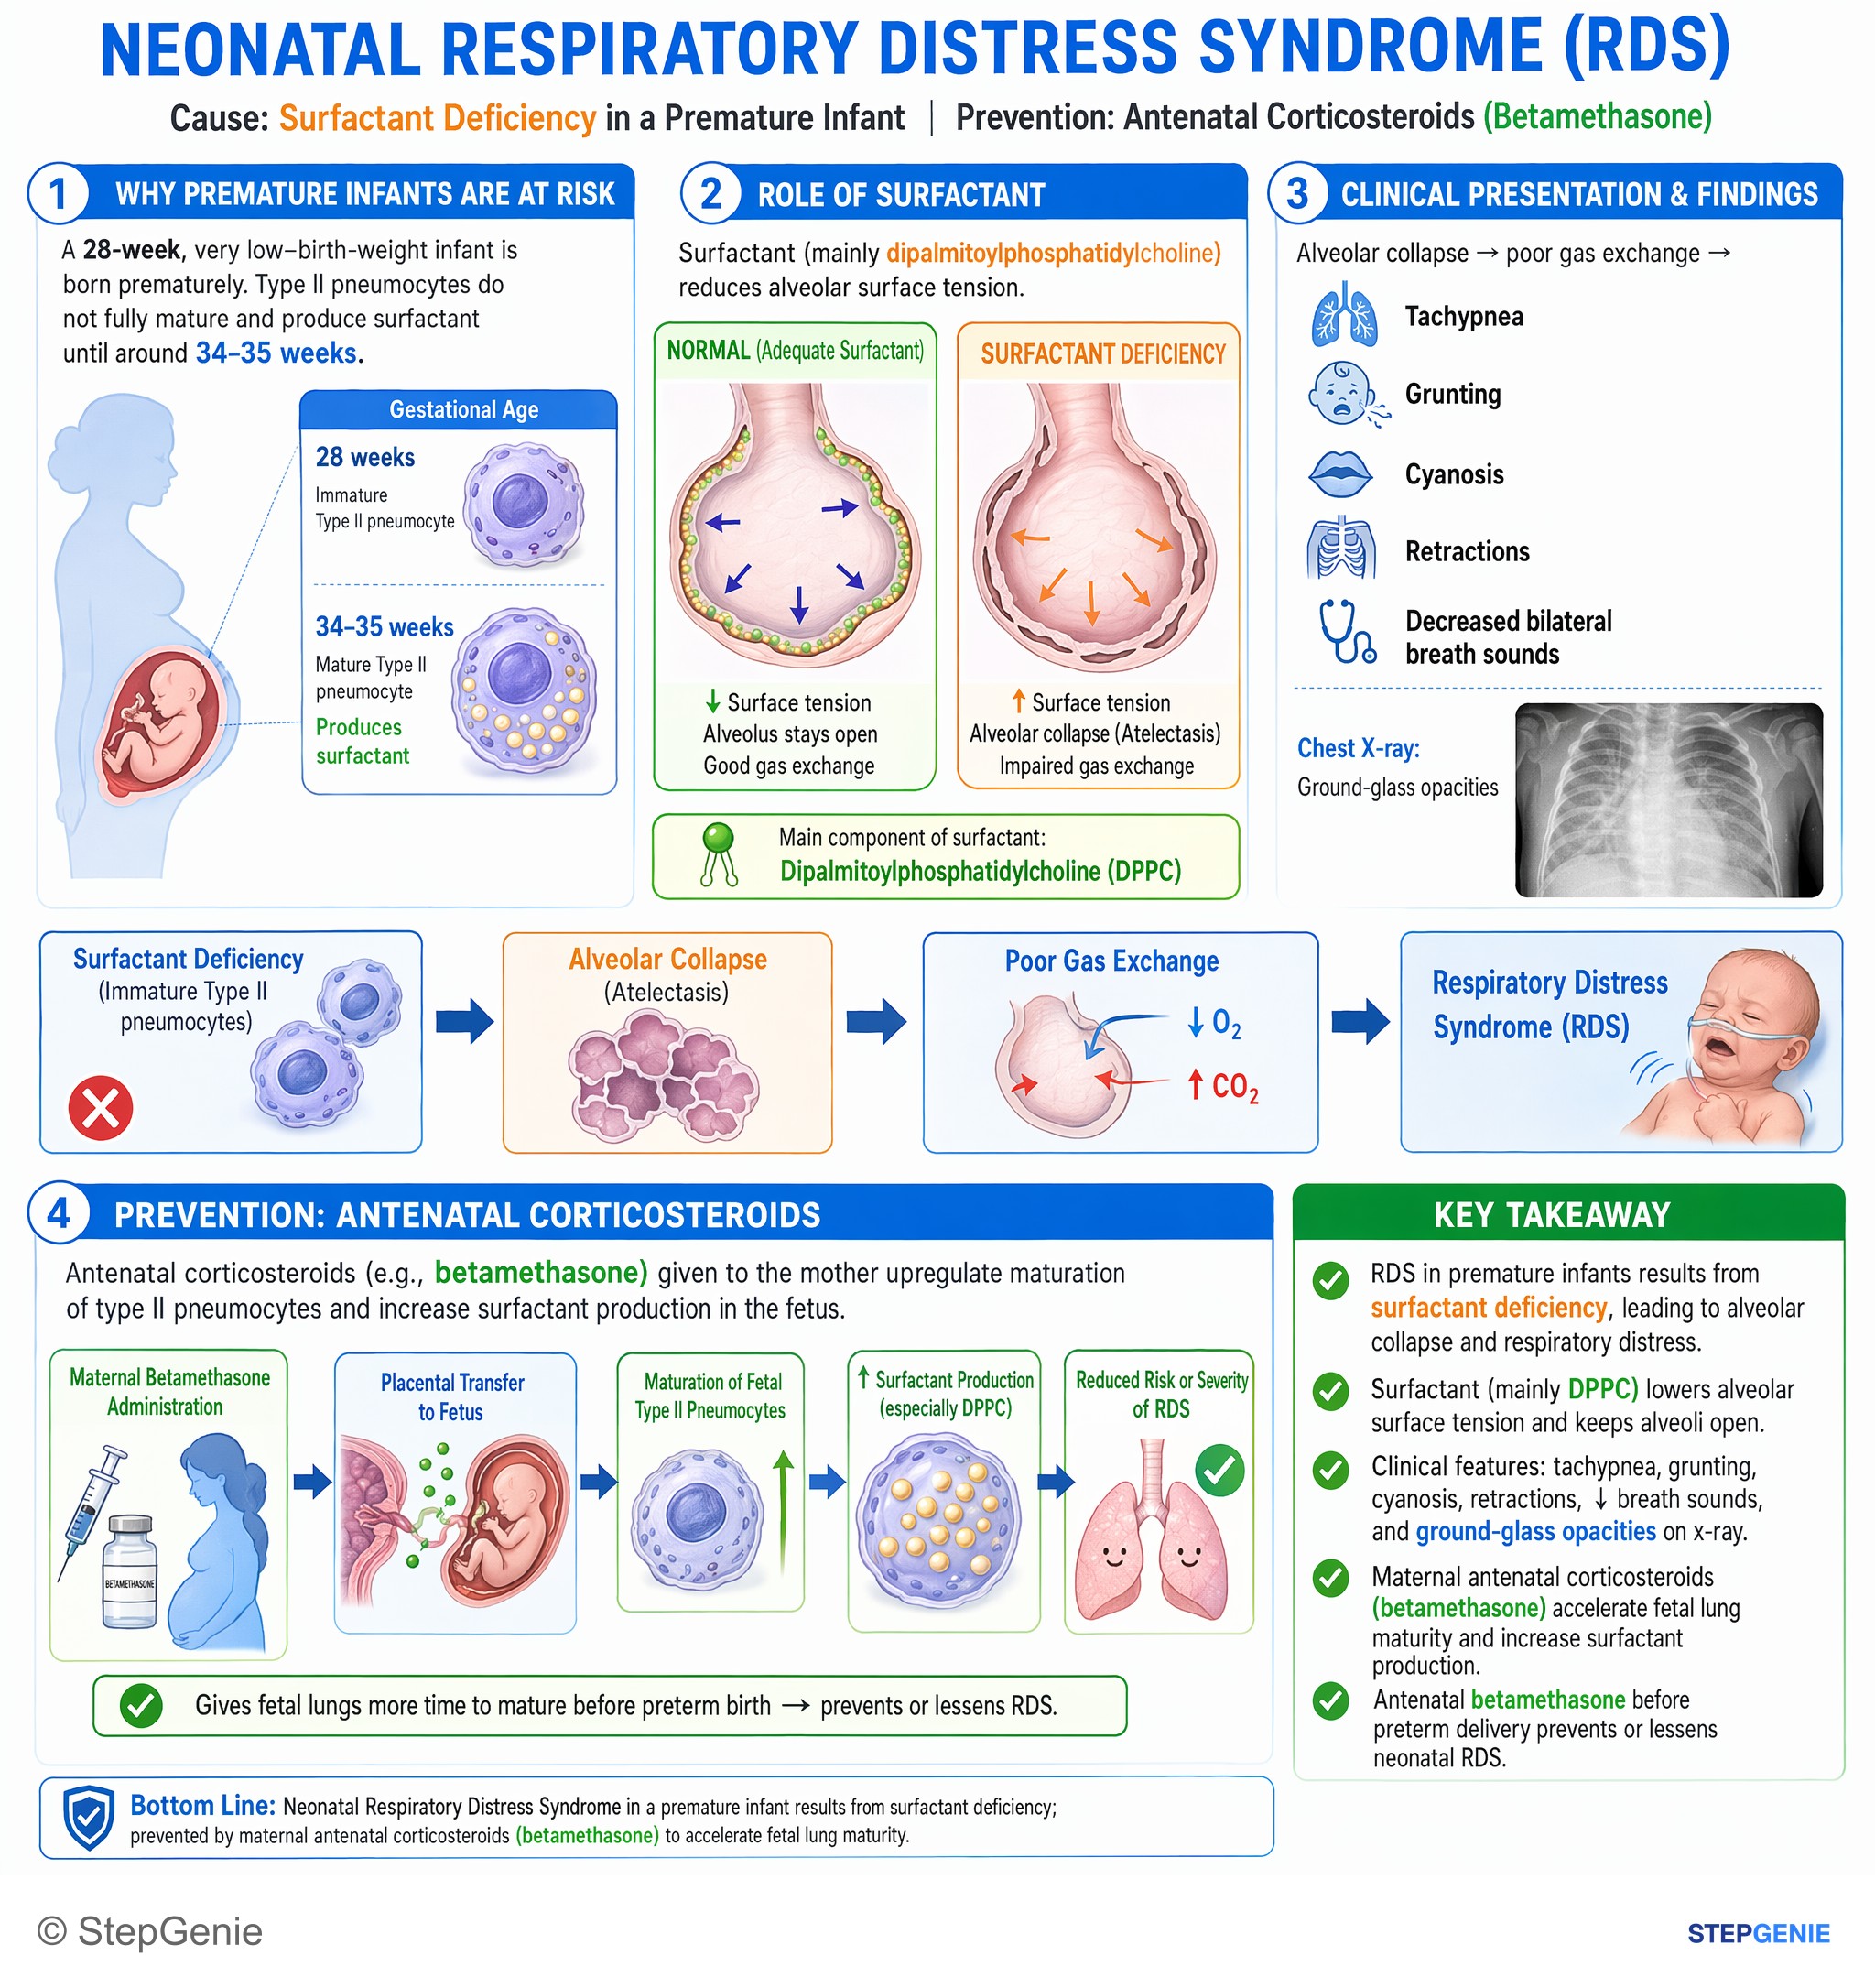
Neonatal respiratory distress syndrome in a premature infant results from surfactant deficiency; prevented by maternal antenatal…
USMLE Step 2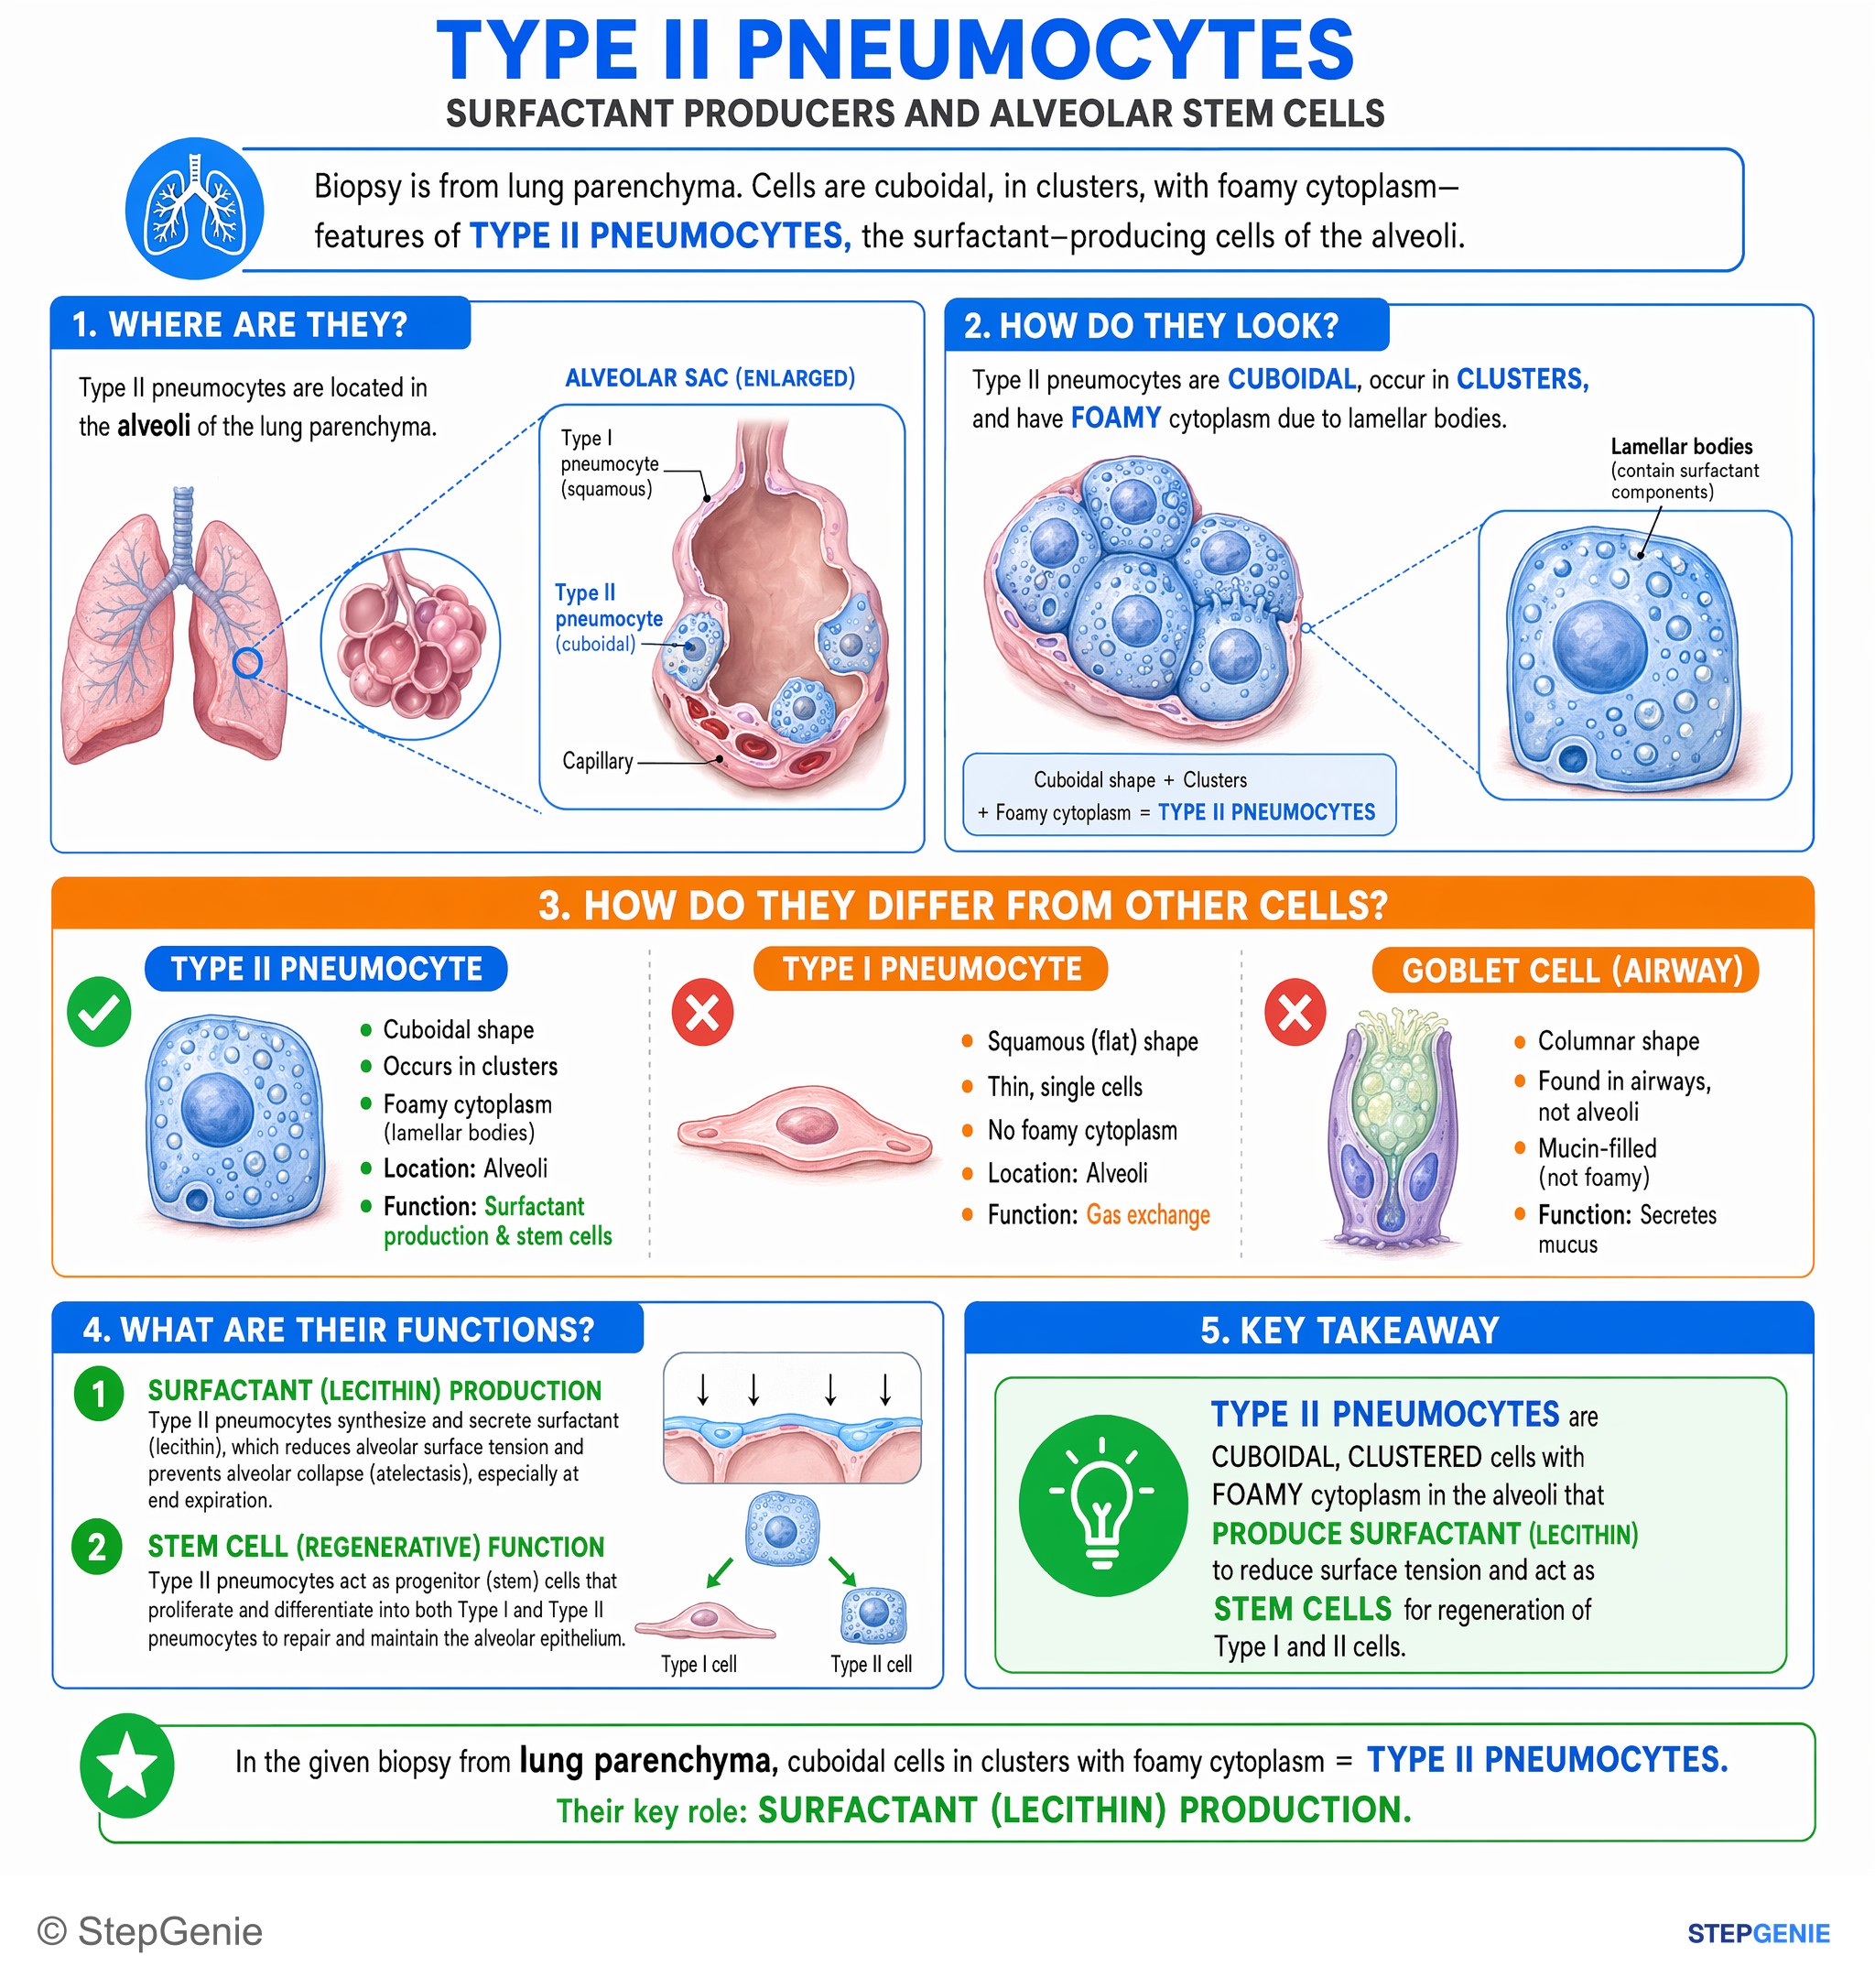
Type II pneumocytes are cuboidal cells with foamy cytoplasm that produce surfactant (lecithin) to reduce alveolar surface tension and…
USMLE Step 1Frequently Asked Questions
Why does surfactant deficiency cause atelectasis and respiratory distress in premature infants?
Surfactant deficiency causes alveolar collapse by increasing surface tension and lowering lung compliance. Surfactant normally reduces surface tension at the air–liquid interface, which makes the lungs easier to inflate and helps keep alveoli open at end-expiration. When surfactant is low, small alveoli require much higher pressure to stay open, so they collapse, leading to atelectasis, hypoxemia, and respiratory distress.
What chest x-ray finding is classic for neonatal respiratory distress syndrome?
The classic chest radiograph finding in neonatal respiratory distress syndrome is diffuse reticulogranular ground-glass opacities with air bronchograms. This pattern fits surfactant deficiency in a premature infant with respiratory distress. The underlying problem is alveolar collapse with epithelial injury, which can also lead to hyaline membrane formation made of fibrin-rich exudate and necrotic debris.
How do you tell neonatal respiratory distress syndrome from emphysema in answer choices?
Neonatal respiratory distress syndrome is a surfactant deficiency problem causing decreased compliance from increased alveolar surface tension, whereas emphysema involves destruction of alveolar walls. Emphysema clues include an adult with progressive dyspnea, hyperinflation, barrel chest, decreased DLCO, hyperlucency, or flattened diaphragms. In contrast, neonatal respiratory distress syndrome presents at birth in a premature infant with alveolar collapse and respiratory distress.
What is the role of antenatal steroids and exogenous surfactant in neonatal respiratory distress syndrome?
Antenatal corticosteroids accelerate type II pneumocyte maturation and increase surfactant production, which helps reduce the risk or severity of neonatal respiratory distress syndrome. After birth, exogenous surfactant can be given as treatment. These therapies target the core defect, because the disorder is caused by inadequate surfactant in premature infants rather than fluid overload, fibrosis, or emphysematous destruction.
What fetal lung maturity markers are high-yield for surfactant questions?
The key fetal lung maturity markers are an L:S ratio of at least 2 and the presence of phosphatidylglycerol. Surfactant production increases late in gestation, so these findings support fetal lung maturity. Prematurity is a major risk factor for neonatal respiratory distress syndrome, especially before 34 weeks, because immature lungs are more likely to have insufficient surfactant.