COPD questions on a Q-bank are rarely testing whether you “know COPD.” They’re testing whether you can prove it from the vignette—and then disprove the tempting alternatives. The fastest way to climb your pulmonary score is to treat every answer choice like it’s there for a reason.
Tag: Pulmonary > Obstructive Lung Disease
The Vignette (Q-bank style)
A 62-year-old man comes to clinic for progressive shortness of breath for 5 years. He has a 45–pack-year smoking history. He has a chronic productive cough most mornings and reports needing “antibiotics a couple times each winter.” On exam, he has diffuse wheezes and rhonchi. His lips are slightly cyanotic. He has bilateral ankle edema. Room-air pulse oximetry is 88%. Pulmonary function testing shows an obstructive pattern with decreased FEV/FVC and increased TLC. Chest radiograph shows increased bronchovascular markings and mild cardiomegaly.
Question: Which underlying change most likely explains this patient’s primary disease process?
Answer choices:
A. Destruction of alveolar septa with loss of elastic recoil
B. Goblet cell hyperplasia in the bronchi with increased mucus production
C. Noncaseating granulomas in the interstitium and hilar lymph nodes
D. Bronchial hyperresponsiveness with reversible airway obstruction
E. Diffuse alveolar damage with hyaline membrane formation
Step 1: Lock in the Diagnosis From the Vignette
This is COPD, and specifically chronic bronchitis–predominant COPD.
Clues pointing to chronic bronchitis:
- Chronic productive cough (“most mornings”) + recurrent “winter antibiotics” (infectious exacerbations)
- Hypoxemia (SpO 88%) and cyanosis
- Peripheral edema → suggests cor pulmonale (pulmonary HTN → right heart strain)
- CXR: increased bronchovascular markings (a “dirty chest” look), cardiomegaly can appear with cor pulmonale (classically you’ll hear RV changes)
Remember the classic definition: chronic bronchitis = productive cough for ≥3 months in each of 2 consecutive years (after excluding other causes).
Correct Answer: B. Goblet cell hyperplasia in the bronchi with increased mucus production
Why B is correct (what’s actually happening)
Chronic bronchitis is driven by irritant-induced airway inflammation (often cigarette smoke) causing:
- Mucous gland enlargement and goblet cell hyperplasia
- Excess mucus → airway plugging + impaired clearance
- Chronic inflammation → airway wall thickening and narrowing
High-yield pathology hook: Reid Index
The Reid index measures the thickness of the mucous gland layer relative to total bronchial wall thickness.
- Normal: ~< 40%
- Chronic bronchitis: > 50%
If you see “Reid index increased,” think chronic bronchitis immediately.
High-yield physiology link
Mucus plugging + airway wall thickening → ventilation/perfusion mismatch with low V/Q regions → hypoxemia early.
This is why chronic bronchitis patients more often trend toward:
- Hypoxemia, hypercapnia
- Pulmonary vasoconstriction → pulmonary HTN → cor pulmonale
Now the Real Test: Why Every Distractor Is Wrong (and what it would mean)
A. Destruction of alveolar septa with loss of elastic recoil
This is emphysema.
How emphysema differs in vignettes:
- Often dyspnea predominates over cough/sputum (“pink puffer” stereotype)
- Barrel chest, pursed-lip breathing, accessory muscle use
- CXR: hyperinflation, flattened diaphragms, decreased vascular markings, blebs/bullae
- Path: enlarged air spaces distal to terminal bronchioles + alveolar wall destruction
Board-relevant mechanism:
- Loss of elastic recoil → air trapping and dynamic airway collapse during expiration (especially with increased intrathoracic pressure)
Classic risk factor pair you must know:
- Smoking → centriacinar emphysema (upper lobes)
- -antitrypsin deficiency → panacinar emphysema (lower lobes, younger patient, can have liver disease)
Why it’s not A here: the vignette is dominated by productive cough, infections, hypoxemia, and cor pulmonale—more chronic bronchitis.
C. Noncaseating granulomas in the interstitium and hilar lymph nodes
This is sarcoidosis.
What sarcoid usually looks like:
- Young/middle-aged adult, often systemic symptoms
- Bilateral hilar lymphadenopathy
- Restrictive lung disease findings on PFTs (↓TLC, normal/high FEV/FVC)
- Can present with: erythema nodosum, uveitis, facial nerve palsy, hypercalcemia
Why it’s not C:
- This vignette has an obstructive pattern and classic COPD risk factor (smoking) + chronic cough with sputum.
- Sarcoid is not primarily a “smoker’s chronic productive cough” disease.
D. Bronchial hyperresponsiveness with reversible airway obstruction
This is asthma.
Asthma hallmarks USMLE loves:
- Reversible obstruction: FEV increases after bronchodilator
- Often episodic symptoms (wheezing, nighttime cough)
- Associated with atopy, eczema, allergic rhinitis (especially in younger patients)
- Path: eosinophils, Charcot-Leyden crystals, Curschmann spirals (classic Step 1 tie-ins)
Why it’s not D:
- COPD is typically less reversible and progressively worsening.
- Chronic bronchitis features mucus gland/goblet cell changes rather than purely bronchial hyperreactivity.
- The clinical story is long-standing, smoking-linked, with cor pulmonale/hypoxemia.
Exam trap: COPD can improve a bit with bronchodilators, but it’s not the dramatic reversibility typical of asthma.
E. Diffuse alveolar damage with hyaline membrane formation
This is ARDS.
ARDS is:
- Acute onset respiratory failure after a major insult (sepsis, pancreatitis, trauma, aspiration)
- Severe hypoxemia refractory to oxygen therapy
- CXR: diffuse bilateral opacities (“white-out”)
- Path: hyaline membranes (protein-rich edema fluid + necrotic debris) lining alveoli
Why it’s not E:
- This is chronic, progressive disease over years with obstructive PFTs—nothing about an acute precipitating event.
COPD “Emphysema vs Chronic Bronchitis” — Rapid Comparison Table
| Feature | Chronic Bronchitis | Emphysema |
|---|---|---|
| Core problem | Mucus + airway inflammation | Alveolar wall destruction |
| Key symptom | Chronic productive cough | Progressive dyspnea |
| Hypoxemia/hypercapnia | Early (low V/Q) | Later (more dead space) |
| Infections | Common | Less prominent |
| PFTs | Obstructive; may have ↓DLCO (variable) | Obstructive + ↓DLCO (classic) |
| CXR | “Dirty chest,” ↑bronchovascular markings | Hyperinflation, ↓vascular markings, flattened diaphragm, bullae |
| Cor pulmonale | More common | Can occur later |
| Path buzzword | Reid index ↑ | Elastic recoil ↓, septal destruction |
High-Yield COPD Physiology You’ll Actually Use on Test Day
1) PFT pattern (obstructive)
- FEV ↓
- FVC normal/↓
- FEV/FVC ↓
- TLC ↑ (air trapping)
- RV ↑
2) DLCO (diffusing capacity)
- Emphysema: DLCO ↓ (less alveolar surface area)
- Chronic bronchitis: DLCO often normal (alveoli intact)
3) Oxygen therapy complication
In COPD patients with chronic CO retention, oxygen can worsen hypercapnia due to:
- V/Q mismatch (loss of hypoxic vasoconstriction in poorly ventilated areas)
- Haldane effect (oxygenated Hb carries less CO)
Boards love to frame this as: “PaCO rises after high-flow O.” The correct move clinically is titrate oxygen (often target SpO around 88–92% in known CO retainers), not “never give oxygen.”
Micro + Exacerbations: A Common Q-bank Twist
Chronic bronchitis patients get infectious COPD exacerbations with increased sputum volume/purulence and worsening dyspnea. Common pathogens:
- Haemophilus influenzae
- Moraxella catarrhalis
- Streptococcus pneumoniae
- Severe disease/bronchiectasis: Pseudomonas
If the stem says “increased purulent sputum + fever,” think exacerbation on top of baseline COPD—and don’t let that distract you from the underlying chronic pathology.
Takeaway: The “Answer Choice Matters” Framework
When you see COPD:
- Decide phenotype (chronic bronchitis vs emphysema) using symptoms + CXR.
- Map to path:
- Chronic bronchitis → goblet cell hyperplasia, Reid index ↑
- Emphysema → alveolar septal destruction, elastic recoil ↓, DLCO ↓
- Eliminate distractors by asking: does this sound obstructive vs restrictive, chronic vs acute, reversible vs irreversible?
Do that consistently, and COPD questions stop feeling like trivia and start feeling like pattern recognition you can defend.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
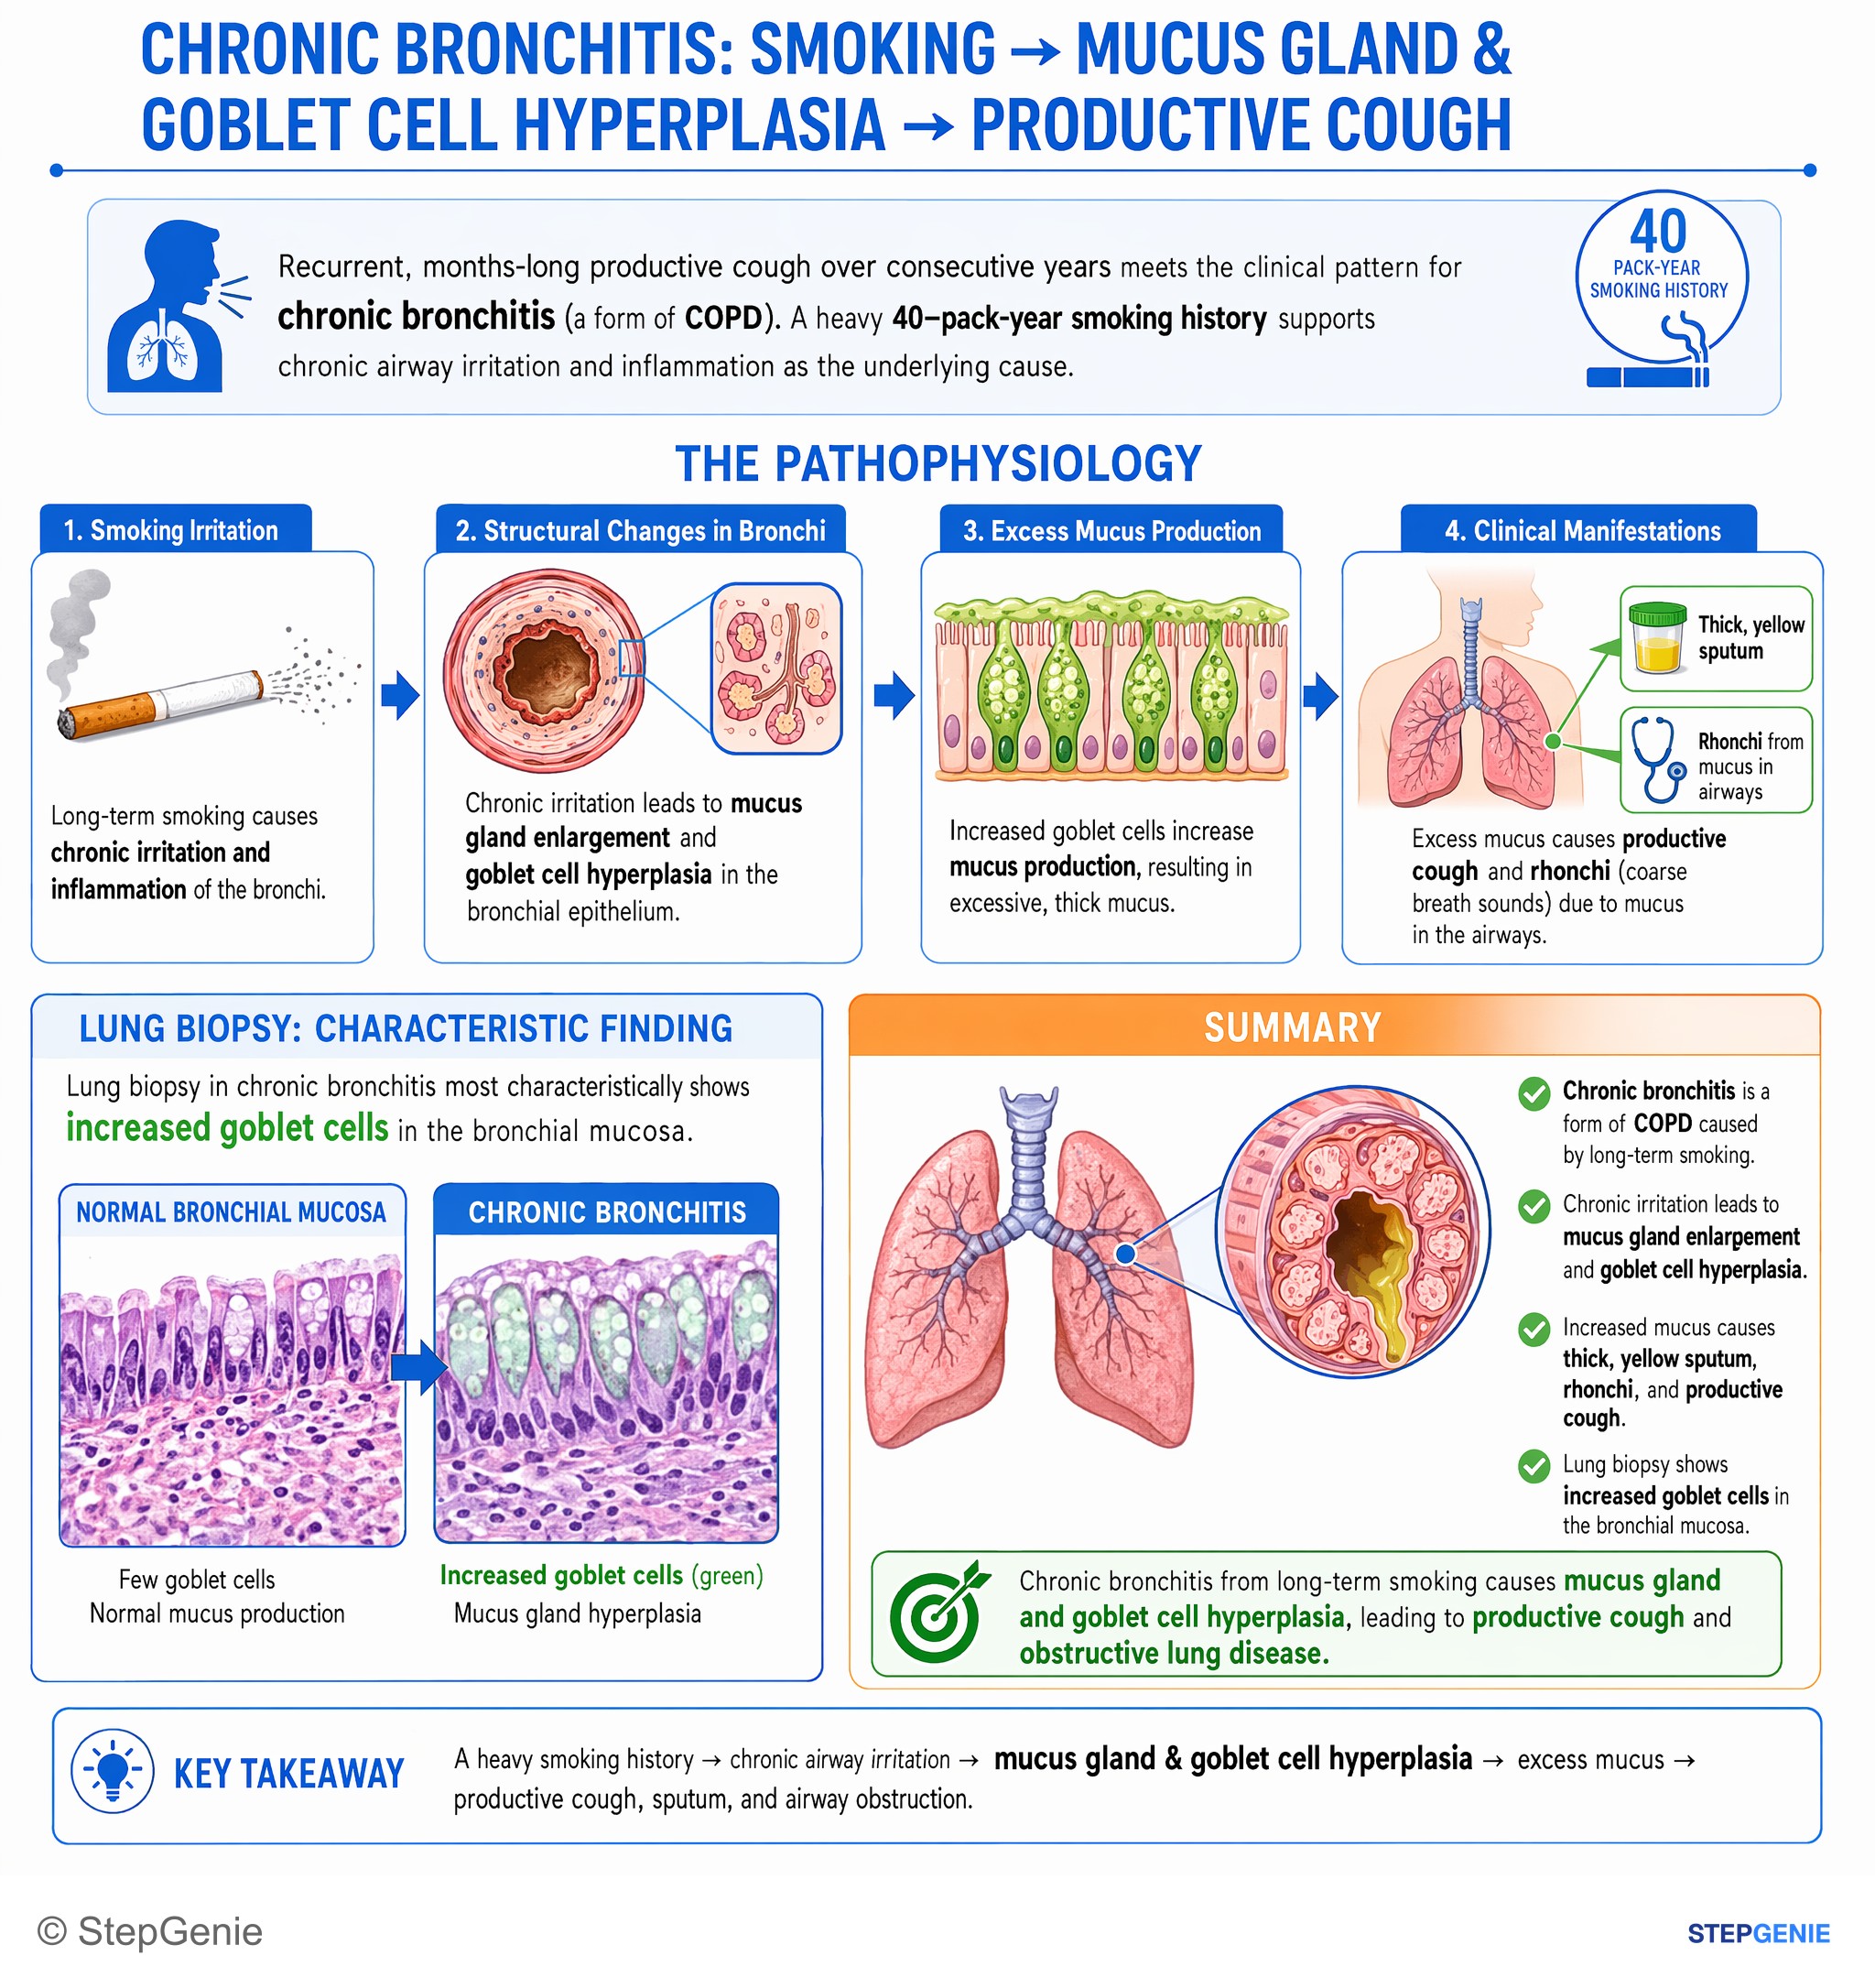
Chronic bronchitis from long-term smoking causes mucus gland and goblet cell hyperplasia, leading to productive cough and obstructive lung…
USMLE Step 1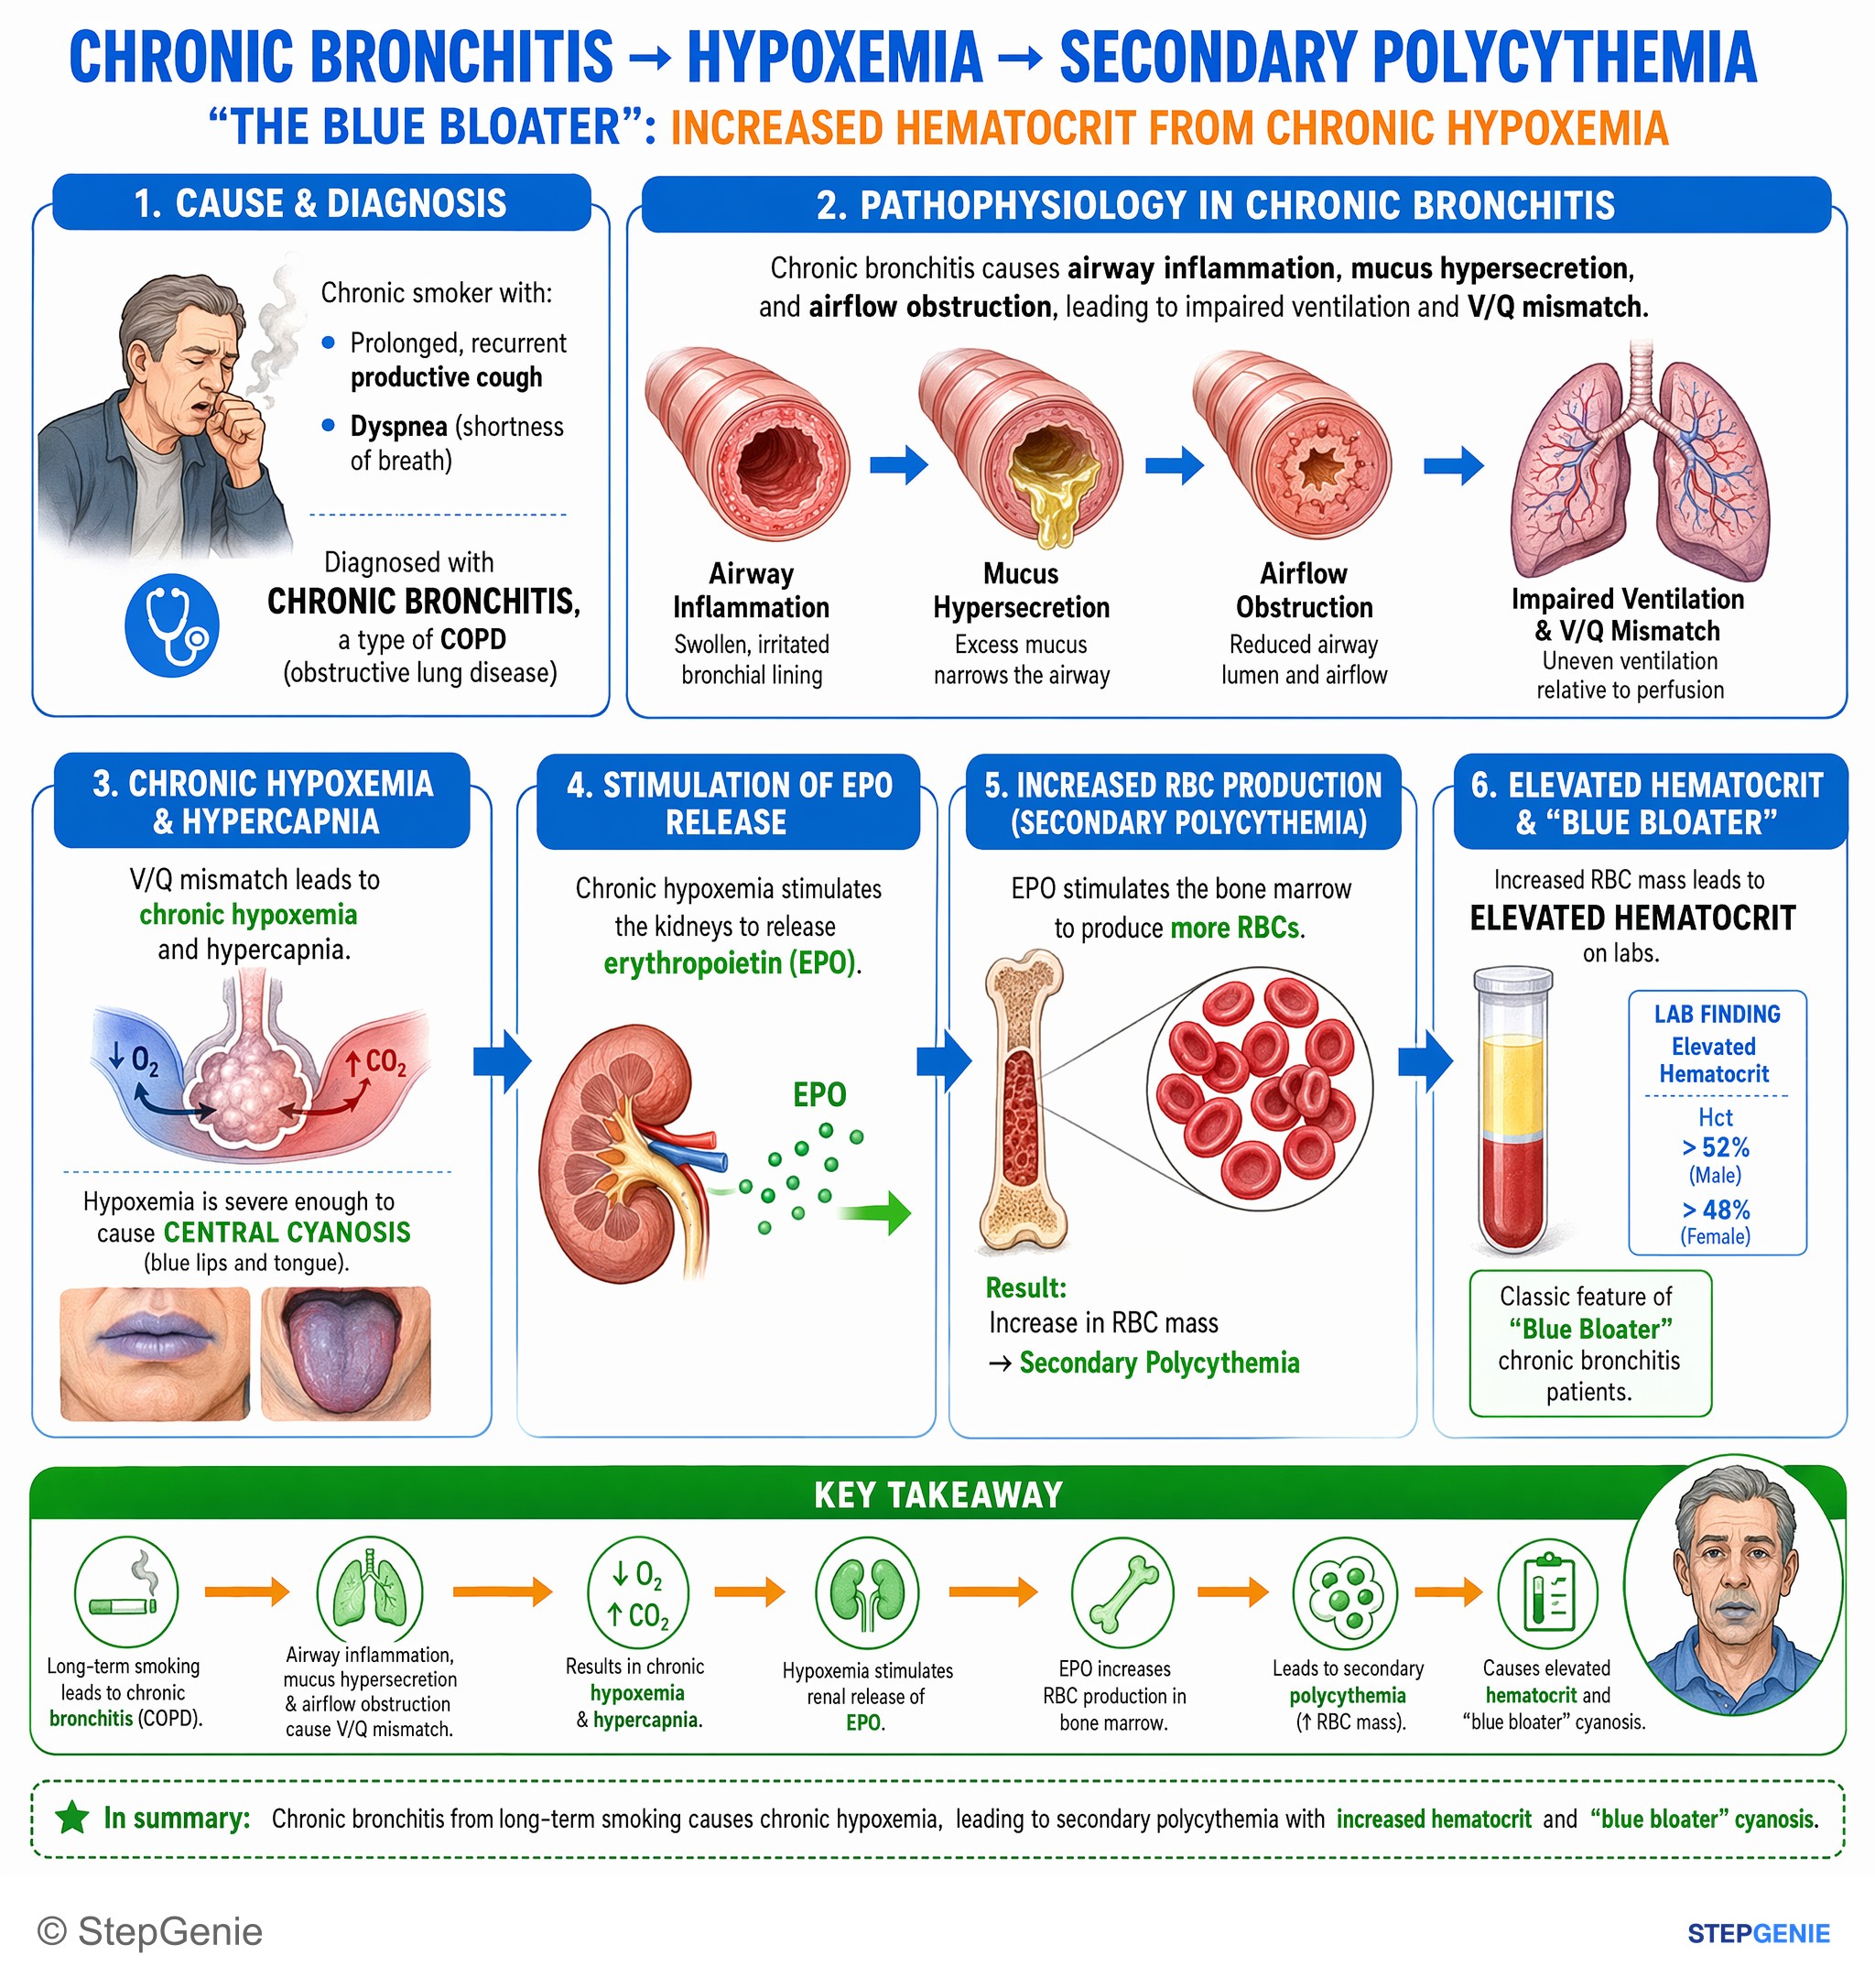
Chronic bronchitis from long-term smoking causes chronic hypoxemia → secondary polycythemia with increased hematocrit and “blue bloater”…
USMLE Step 1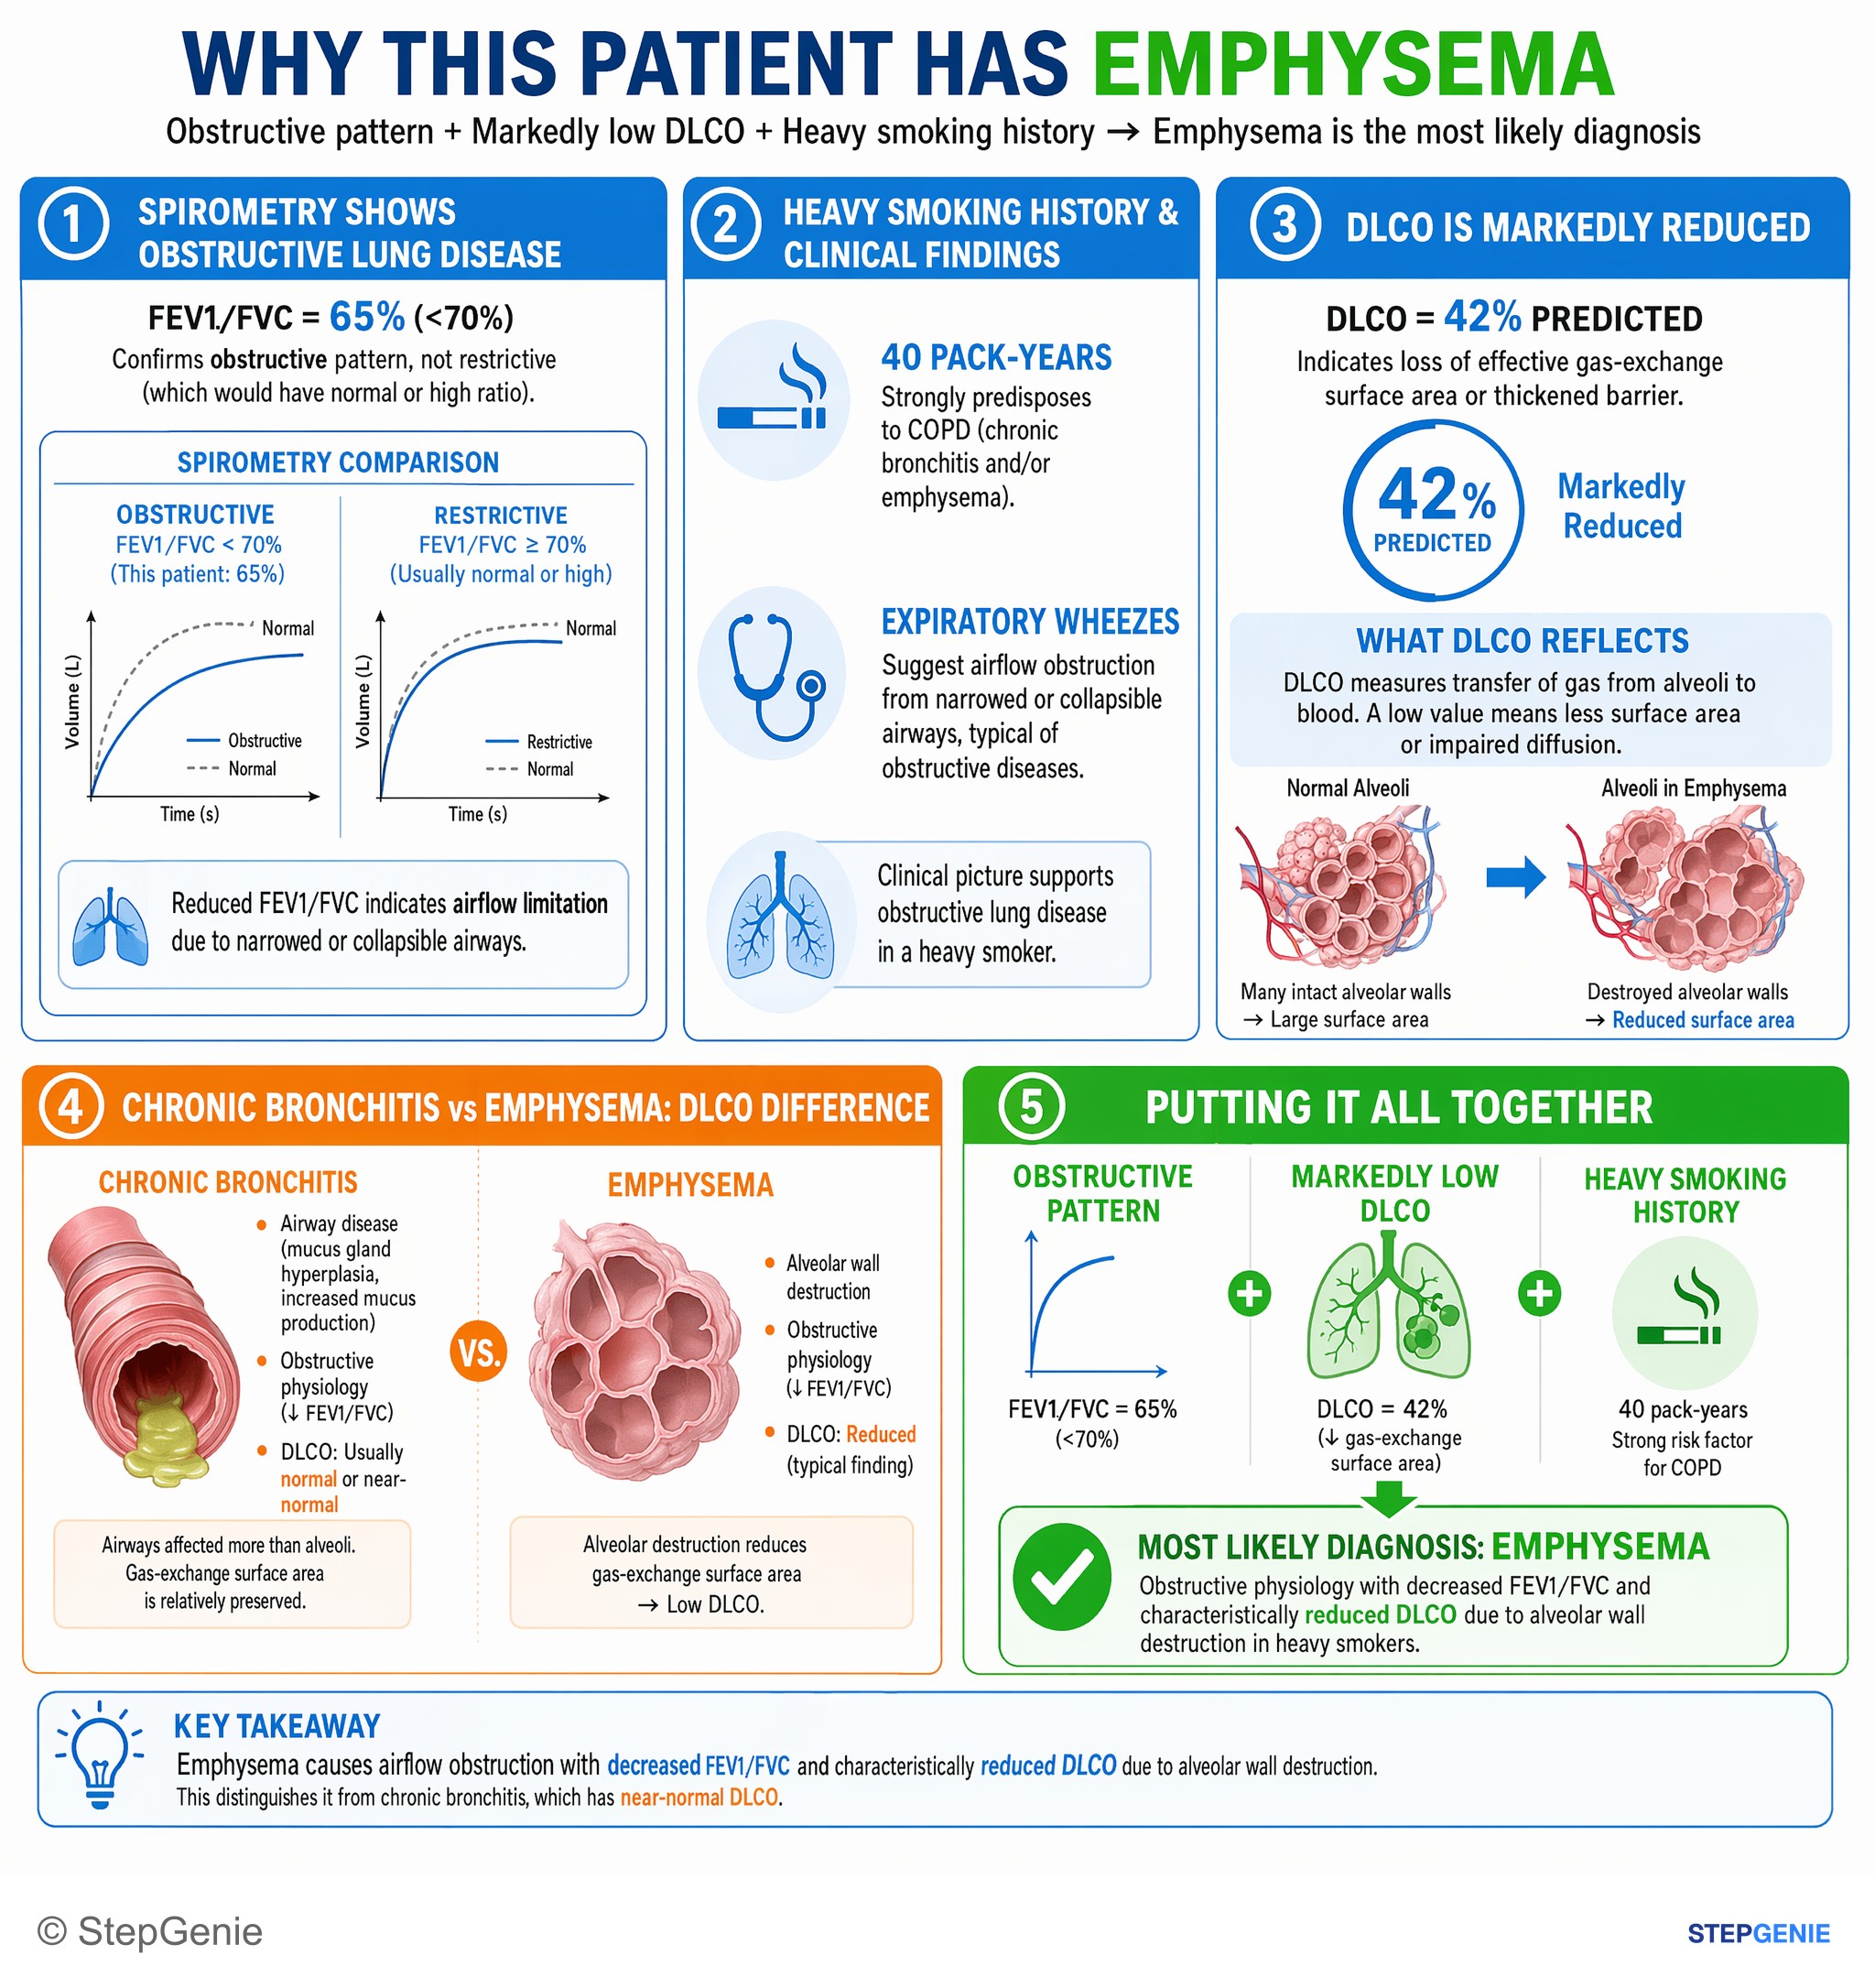
Emphysema causes obstructive physiology with decreased FEV1/FVC and characteristically reduced DLCO due to alveolar wall destruction in…
USMLE Step 2Frequently Asked Questions
How do you tell chronic bronchitis from emphysema in a COPD vignette?
Chronic bronchitis is suggested by productive cough, recurrent infections, hypoxemia, cyanosis, and signs of cor pulmonale, whereas emphysema more often presents with dyspnea predominating over cough and sputum. Chronic bronchitis also has increased bronchovascular markings on chest radiograph, while emphysema classically shows hyperinflation, flattened diaphragms, decreased vascular markings, and blebs or bullae.
Why does chronic bronchitis cause hypoxemia and cor pulmonale?
Chronic bronchitis causes hypoxemia because excess mucus and airway wall thickening create low ventilation/perfusion regions. Irritant-induced airway inflammation leads to mucus plugging and narrowed airways, which impair ventilation. The resulting hypoxemia can trigger pulmonary vasoconstriction, leading to pulmonary hypertension and right heart strain, which explains cor pulmonale and findings such as peripheral edema.
What underlying pathologic change explains chronic bronchitis?
The key underlying change in chronic bronchitis is goblet cell hyperplasia in the bronchi with increased mucus production. Cigarette smoke and other irritants drive airway inflammation, causing mucous gland enlargement, excess mucus, and chronic airway wall thickening. This leads to airway plugging, impaired clearance, and the obstructive physiology seen on pulmonary function testing.
What is the Reid index, and why is it high-yield for chronic bronchitis?
The Reid index is the thickness of the mucous gland layer relative to the total bronchial wall thickness, and it is increased in chronic bronchitis. A normal value is less than about 40%, while chronic bronchitis is greater than 50%. If a question says the Reid index is increased, that is a classic pathology clue pointing directly to chronic bronchitis.
How do you rule out asthma, sarcoidosis, and ARDS when the answer is chronic bronchitis?
Chronic bronchitis is favored when the vignette shows smoking-related, progressive, less reversible obstructive disease with productive cough, hypoxemia, and cor pulmonale. Asthma is typically reversible and often episodic, sarcoidosis usually causes restrictive findings with bilateral hilar lymphadenopathy, and ARDS is an acute respiratory failure syndrome after a major insult with diffuse bilateral opacities and hyaline membrane formation.