Bronchiectasis is one of those “pattern recognition” diagnoses that can feel easy—until a question stem forces you to separate it from COPD, asthma, TB, and cystic fibrosis in 30 seconds. The key is to know what must be true (chronic productive cough + recurrent infections + airway dilation) and why the distractors are tempting but wrong.
Q-Bank-Style Clinical Vignette
A 46-year-old woman presents with daily productive cough for 2 years. She reports large amounts of foul-smelling sputum, intermittent fevers, and two pneumonias in the past year requiring antibiotics. She has no smoking history. Exam shows digital clubbing and coarse crackles at the lung bases that partially clear with coughing. A chest CT shows dilated airways with thickened bronchial walls and “tram-track” opacities.
Which of the following is the most likely underlying pathophysiology?
A. Destruction of alveolar walls with airspace enlargement
B. Chronic bronchial dilation due to persistent infection and inflammation
C. Bronchial smooth muscle hypertrophy with reversible airflow obstruction
D. Caseating granulomatous inflammation of the upper lobes
E. Defective CFTR leading to dehydrated airway surface liquid and mucus plugging
Correct Answer: B. Chronic bronchial dilation due to persistent infection and inflammation
Why this is bronchiectasis
Bronchiectasis is permanent abnormal dilation of bronchi and bronchioles due to chronic inflammation and repeated infections, which destroy elastic and muscular components of the airway wall.
Clues in the stem:
- Chronic productive cough with copious, foul-smelling sputum (classic)
- Recurrent infections (pneumonias, fevers)
- Crackles that may improve with cough (secretions in dilated airways)
- Digital clubbing (common in bronchiectasis; uncommon in uncomplicated chronic bronchitis/asthma)
- CT: tram-tracks, airway wall thickening, dilation (often described with signet ring sign)
High-yield pathophys snapshot
- Cycle: infection → inflammation → airway wall destruction → impaired clearance → more infection
- Most commonly associated organisms (classically tested):
- H influenzae, S pneumoniae, Staph aureus
- Pseudomonas (especially with cystic fibrosis or advanced disease)
Imaging pearls (USMLE-friendly)
- High-resolution CT is the best diagnostic test.
- Findings: bronchial dilation, lack of tapering, bronchial wall thickening
- “Signet ring sign”: dilated bronchus larger than accompanying pulmonary artery.
Common causes to have on reflex
Bronchiectasis is a final common pathway; questions often ask you to identify the underlying driver.
| Category | High-yield examples | Tip-off clues |
|---|---|---|
| Post-infectious | Severe pneumonia, pertussis, measles | History of serious childhood/lower resp infections |
| CF / impaired mucociliary clearance | Cystic fibrosis, primary ciliary dyskinesia | CF: pancreatic issues; PCD: sinusitis + infertility |
| Airway obstruction | Tumor, foreign body | Focal bronchiectasis, localized wheeze |
| Immunodeficiency | CVID, hypogammaglobulinemia | Recurrent sinopulmonary infections |
| Allergic | ABPA (Aspergillus) | Asthma + eosinophilia + high IgE; central bronchiectasis |
Systematic Distractor Breakdown: Why Every Other Choice Is Wrong
A. Destruction of alveolar walls with airspace enlargement
This describes emphysema, not bronchiectasis.
Why it’s tempting: Both are obstructive and can present with dyspnea.
Why it’s wrong here:
- Emphysema = alveolar wall destruction → decreased elastic recoil, air trapping
- Typical features: minimal sputum, barrel chest, weight loss, smoking or A1AT risk
- CT would show hyperlucency/blebs, not airway dilation with thick walls
- Clubbing is not a classic emphysema hallmark
Step takeaway: If the question is screaming copious purulent sputum + recurrent infections, think bronchiectasis, not emphysema.
C. Bronchial smooth muscle hypertrophy with reversible airflow obstruction
This describes asthma.
Why it’s tempting: Obstructive disease + cough is common.
Why it’s wrong here:
- Asthma cough is often dry or with scant sputum (unless severe)
- Hallmarks: episodic symptoms, triggers, nocturnal symptoms, atopy
- Pathology: goblet cell hyperplasia, subepithelial fibrosis, smooth muscle hypertrophy, Curschmann spirals, Charcot-Leyden crystals
- Imaging: typically normal or hyperinflation; not “tram-tracks” bronchial dilation
Step takeaway: Asthma is reversible bronchoconstriction; bronchiectasis is irreversible airway dilation from chronic damage.
D. Caseating granulomatous inflammation of the upper lobes
This points to reactivation tuberculosis (or certain endemic fungi), not bronchiectasis.
Why it’s tempting: Chronic cough + recurrent symptoms can trigger “TB reflex.”
Why it’s wrong here:
- TB classically causes:
- Upper lobe involvement
- Night sweats, weight loss
- Hemoptysis can occur (also seen in bronchiectasis), but the imaging and sputum story differ
- CT description here is of bronchial dilation, not cavitary lesions
- Bronchiectasis can be post-infectious after TB, but the stem’s CT is directly describing bronchiectasis as the primary finding.
Step takeaway: TB = granulomas/cavitation; bronchiectasis = dilated bronchi with chronic purulent sputum.
E. Defective CFTR leading to dehydrated airway surface liquid and mucus plugging
This describes cystic fibrosis—a cause of bronchiectasis, but not the best answer to the pathophysiology described.
Why it’s tempting: CF is a classic association with bronchiectasis and Pseudomonas.
Why it’s wrong here (as the “most likely”):
- The patient is 46 with no provided CF features (pancreatic insufficiency, recurrent childhood infections, infertility, nasal polyps)
- In classic USMLE stems, CF is usually telegraphed:
- Chronic sinopulmonary disease since childhood
- Steatorrhea, failure to thrive, fat-soluble vitamin deficiency
- Male infertility (CBAVD)
- The stem asks for the pathophysiology of the airway abnormality, which is chronic infection/inflammation destroying airway walls.
Step takeaway: CFTR mutation is upstream; bronchiectasis is the downstream airway remodeling.
High-Yield Bronchiectasis Facts (Rapid Review)
Core triad
- Chronic productive cough
- Recurrent respiratory infections
- Permanent bronchial dilation on CT
Physical exam and symptoms
- Coarse crackles, rhonchi, wheeze
- Digital clubbing
- Hemoptysis can occur (inflamed, friable airways)
Pulmonary function tests (PFTs)
- Obstructive pattern: decreased
- Often increased residual volume from air trapping in severe disease
Complications to remember
- Massive hemoptysis (bronchial arteries are high-pressure)
- Pulmonary hypertension/cor pulmonale in advanced disease
- Colonization with Pseudomonas (worse prognosis)
Mini Algorithm: How to Recognize Bronchiectasis in a Stem
- Big sputum (daily, copious, purulent/foul) + recurrent antibiotics
- CT says “dilated bronchi,” “tram-tracks,” or “signet ring”
- Look for an underlying cause clue (CF, ABPA, immunodeficiency, obstruction, prior severe infections)
One-Liner Memory Hook
Bronchiectasis = “broken bronchi”: chronic infection and inflammation break the airway walls, leaving permanently dilated, mucus-filled tubes that keep getting infected.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
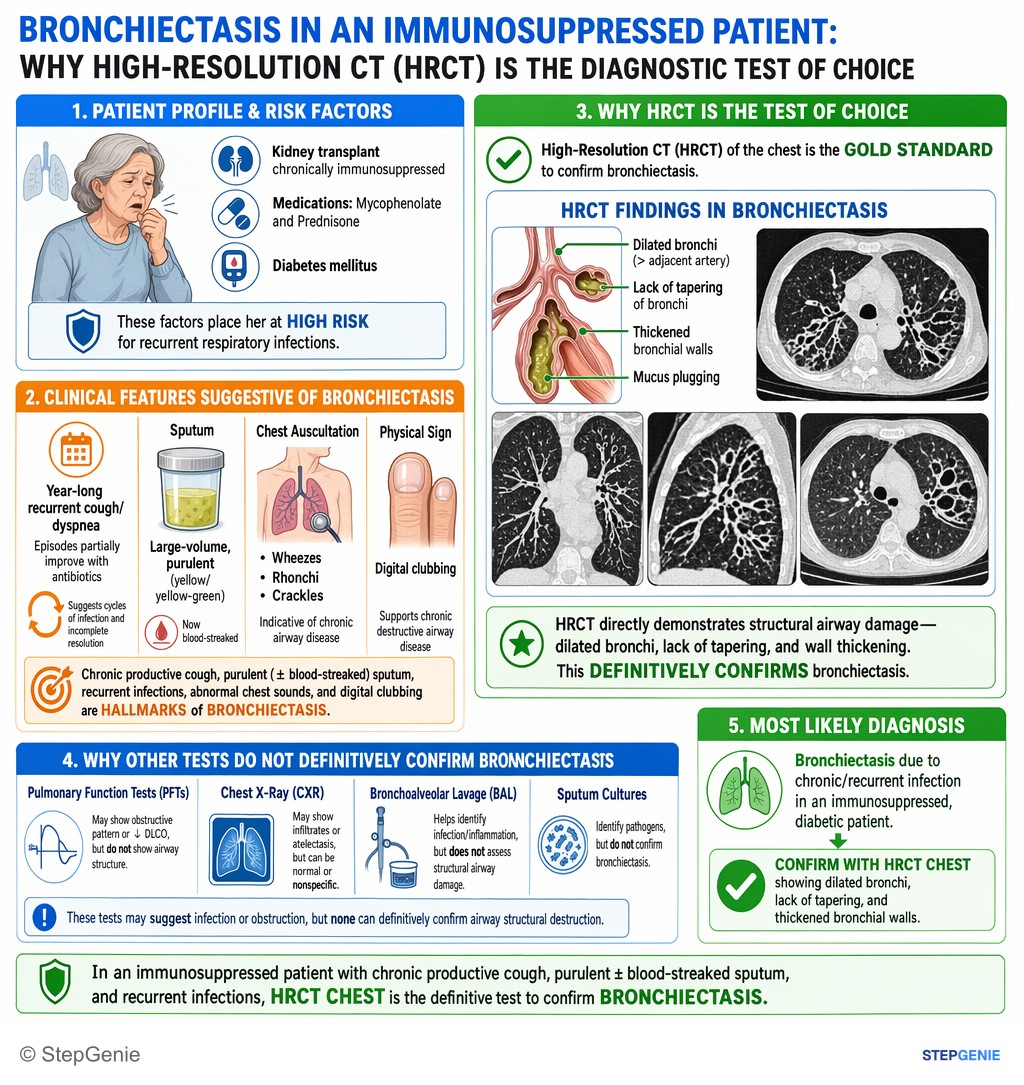
Bronchiectasis from chronic/recurrent infection in an immunosuppressed patient is best confirmed with high-resolution CT showing airway…
USMLE Step 2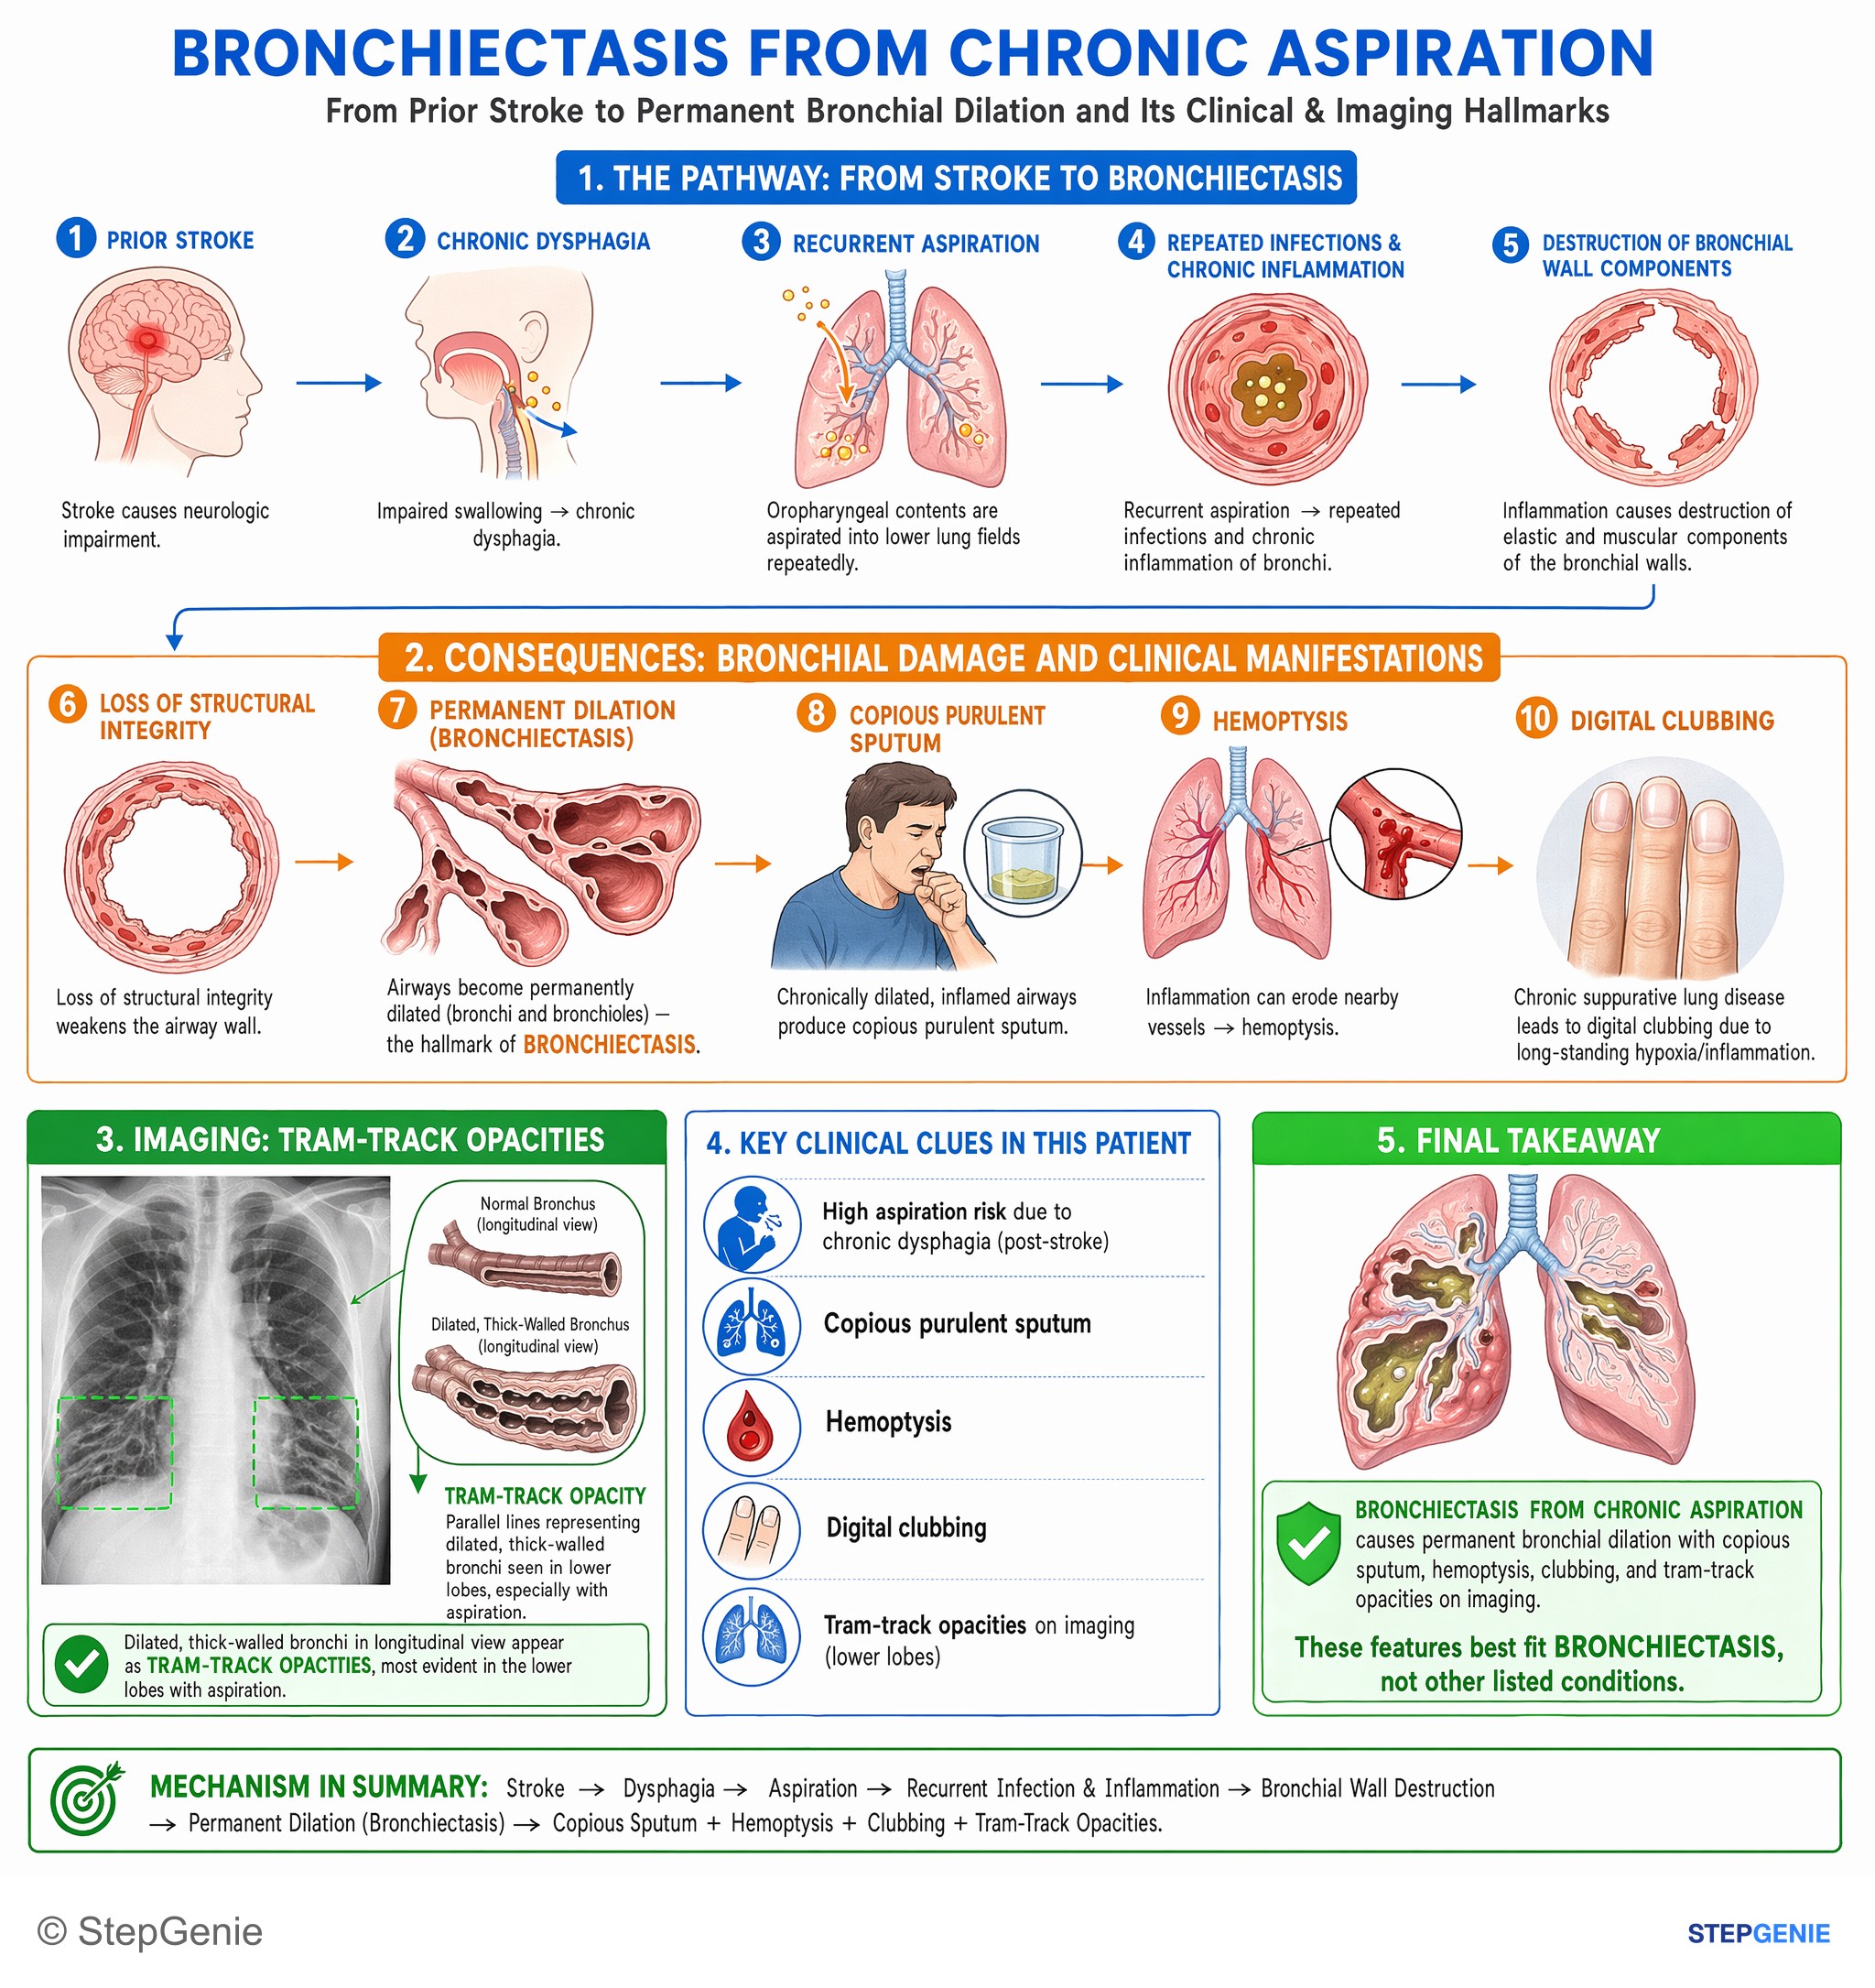
Bronchiectasis from chronic aspiration causes permanent bronchial dilation with copious sputum, hemoptysis, clubbing, and tram-track…
USMLE Step 2
Bronchiectasis: chronic productive cough with large volumes of purulent sputum, recurrent infections, and airway wall thickening/irregular…
USMLE Step 2Frequently Asked Questions
What findings make bronchiectasis the most likely diagnosis on a pulmonary question stem?
Bronchiectasis is most likely when a stem combines chronic productive cough, recurrent infections, and airway dilation on imaging. Classic clues include copious foul-smelling sputum, intermittent fevers, repeated pneumonias, coarse crackles that can improve with coughing, and digital clubbing. Chest CT supports the diagnosis when it shows dilated airways, thickened bronchial walls, tram-track opacities, or a signet ring sign.
Why does bronchiectasis cause recurrent infections and lots of purulent sputum?
Bronchiectasis causes recurrent infection because chronic inflammation and repeated infections permanently damage and dilate the bronchi and bronchioles. This destroys elastic and muscular components of the airway wall, impairs mucus clearance, and sets up a self-perpetuating cycle of infection, inflammation, airway wall destruction, and more infection. The result is chronic productive cough with copious, often foul-smelling sputum.
How do you tell bronchiectasis from emphysema or asthma on exam questions?
Bronchiectasis is distinguished by irreversible airway dilation with copious purulent sputum and recurrent infections, whereas emphysema and asthma have different core patterns. Emphysema is alveolar wall destruction with airspace enlargement, typically causing minimal sputum and CT hyperlucency or blebs rather than thick-walled dilated airways. Asthma causes reversible airflow obstruction with episodic symptoms, often dry cough, and imaging that is usually normal or hyperinflated rather than tram-track bronchial dilation.
What is the best diagnostic test for bronchiectasis and what does it show?
High-resolution CT is the best diagnostic test for bronchiectasis. It typically shows bronchial dilation, lack of normal tapering, and bronchial wall thickening. USMLE-style descriptions may mention tram-track opacities or the signet ring sign, where the dilated bronchus is larger than the accompanying pulmonary artery. These findings help separate bronchiectasis from other obstructive lung diseases.
How do you tell primary bronchiectasis from cystic fibrosis as an answer choice?
Cystic fibrosis can cause bronchiectasis, but it is not always the best answer when the question asks for the immediate pathophysiology shown in the stem. The direct process in bronchiectasis is chronic bronchial dilation from persistent infection and inflammation. CF becomes more likely when there are supporting clues such as pancreatic issues, recurrent childhood infections, or other signs of impaired mucociliary clearance.