You’re cruising through a pulmonary Q-bank block, and suddenly a “young COPD” vignette pops up. You recognize alpha-1 antitrypsin (A1AT) deficiency… but the answer choices are all plausible. This is exactly where Step questions are made: not just spotting the diagnosis, but proving why everything else is wrong.
Tag: Pulmonary > Obstructive Lung Disease
The Clinical Vignette (Classic Q-Bank Style)
A 34-year-old man comes to clinic for progressive dyspnea and chronic cough. He has had two hospitalizations for COPD exacerbations in the past year. He smoked briefly in college but quit 10 years ago (5 pack-years total). On exam, he is thin and tachypneic with decreased breath sounds. Pulmonary function testing shows an obstructive pattern. A chest CT demonstrates panacinar emphysema most prominent in the lower lobes. Labs show mildly elevated AST/ALT.
Question: What is the underlying pathophysiology?
The Correct Answer: Alpha-1 Antitrypsin Deficiency
What’s happening?
A1AT deficiency causes unopposed elastase activity, leading to progressive destruction of alveolar walls.
- A1AT is produced in the liver
- Its main job in the lung: inhibit neutrophil elastase
- Without it: elastase breaks down elastin in alveolar septa → emphysema
High-yield hallmarks (USMLE loves these)
Think A1AT when you see:
- Early-onset emphysema (often <45)
- Emphysema in a minimal/absent smoking history
- Basilar (lower lobe) predominant disease
- Panacinar emphysema pattern
- Evidence of liver disease (hepatitis, cirrhosis)
- Sometimes: necrotizing panniculitis (rare but board-favorite)
Why lower lobes?
Perfusion is higher at the bases → more inflammatory cell trafficking → more elastase burden → more damage when A1AT is missing.
Genetics + liver tie-in
Most severe phenotypes involve misfolded A1AT accumulating in hepatocytes (classically PiZZ).
| Feature | Lung | Liver |
|---|---|---|
| Mechanism | Low A1AT → ↑ elastase activity | Misfolded A1AT trapped in ER |
| Result | Emphysema (panacinar, lower lobes) | Hepatitis, cirrhosis, ↑ risk HCC |
Diagnosis & management (testable)
- Serum A1AT level: decreased
- Phenotyping/genotyping: confirms subtype
- Treatment:
- Smoking cessation (huge)
- COPD inhaler therapy as needed
- IV A1AT augmentation for select patients
- Liver transplant can be curative for hepatic disease (restores normal A1AT production)
Why Every Other Answer Choice Is Wrong (Systematic Distractor Takedown)
Below are common distractors used in A1AT vignettes—and the single feature that should make you reject them.
Distractor 1: Centriacinar (Centrilobular) Emphysema from Smoking
Why it’s tempting: Obstructive PFTs + emphysema = “smoker’s COPD.”
Why it’s wrong here:
- Smoking-associated emphysema is centriacinar and upper-lobe predominant
- This patient has panacinar + lower lobes and minimal smoking history
USMLE memory hook:
- Smoking → centriacinar → upper lobes
- A1AT → panacinar → lower lobes
Distractor 2: Chronic Bronchitis (Reid Index Increased)
Why it’s tempting: COPD exacerbations, cough.
Why it’s wrong here:
- Chronic bronchitis is defined clinically by productive cough ≥3 months in 2 consecutive years
- CT clue in vignette is emphysema pattern (alveolar destruction), not mucus gland hypertrophy
- Chronic bronchitis is more associated with:
- cyanosis (“blue bloater”)
- rhonchi/wheezing
- increased sputum
- pulmonary hypertension/cor pulmonale
High-yield pathology: Increased Reid index = thickened mucous gland layer.
Distractor 3: Asthma (Reversible Bronchoconstriction; Eosinophils; Curschmann Spirals)
Why it’s tempting: Obstructive PFTs in a young person.
Why it’s wrong here:
- Asthma is typically episodic with triggers and shows reversibility on spirometry
- CT in asthma doesn’t classically show emphysema distribution patterns like panacinar lower-lobe destruction
- No atopic history, nocturnal symptoms, or allergen trigger pattern is provided
Boards love these asthma buzzwords:
- Eosinophils, Charcot-Leyden crystals, Curschmann spirals
- Thickened basement membrane, smooth muscle hypertrophy
Distractor 4: Bronchiectasis (Dilated Airways from Chronic Infection)
Why it’s tempting: Recurrent hospitalizations + cough.
Why it’s wrong here:
- Bronchiectasis = permanent airway dilation, classically with:
- copious purulent sputum
- recurrent infections
- hemoptysis
- CT would show “tram tracks”/signet ring changes, not emphysema predominance patterns
High-yield associations:
- CF, primary ciliary dyskinesia, ABPA, immunodeficiency, post-infectious
Distractor 5: Pulmonary Fibrosis / Restrictive Disease (↓ TLC, “Velcro” Crackles)
Why it’s tempting: Progressive dyspnea.
Why it’s wrong here:
- Vignette explicitly gives obstructive physiology
- Fibrosis is restrictive: ↓ TLC, ↓ FVC, normal/high FEV1/FVC
- Exam would suggest fine inspiratory crackles rather than decreased breath sounds from hyperinflation
Distractor 6: Pulmonary Hypertension as the Primary Problem
Why it’s tempting: Dyspnea + chronic lung disease.
Why it’s wrong here:
- Pulmonary HTN is often a complication of COPD, not the core mechanism
- The stem gives you the primary anatomic diagnosis: emphysema with a specific distribution pattern (panacinar, basilar)
Quick “Step-Style” Comparison Table
| Condition | Pattern | Typical Patient | Key Clue |
|---|---|---|---|
| A1AT deficiency | Panacinar, lower lobes | Young, minimal smoking; ± liver disease | Early emphysema + ↑ LFTs |
| Smoking COPD emphysema | Centriacinar, upper lobes | Heavy smoker | Upper-lobe emphysema |
| Chronic bronchitis | Airway disease (not alveoli) | Smoker | Productive cough; ↑ Reid index |
| Asthma | Reversible obstruction | Atopy, episodic | Eosinophils, triggers, reversibility |
| Bronchiectasis | Dilated bronchi | Chronic infections | Copious sputum, hemoptysis |
| Pulmonary fibrosis | Restrictive | Variable | ↓ TLC, crackles, honeycombing |
Ultra High-Yield Takeaways (What You Should Recall in 10 Seconds)
- A1AT deficiency = unopposed elastase → emphysema
- Panacinar + lower lobes = A1AT deficiency
- Centriacinar + upper lobes = smoking
- A1AT deficiency also causes liver disease (misfolded protein accumulates in hepatocytes)
- In young “COPD” patients with little smoking history: always consider A1AT
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
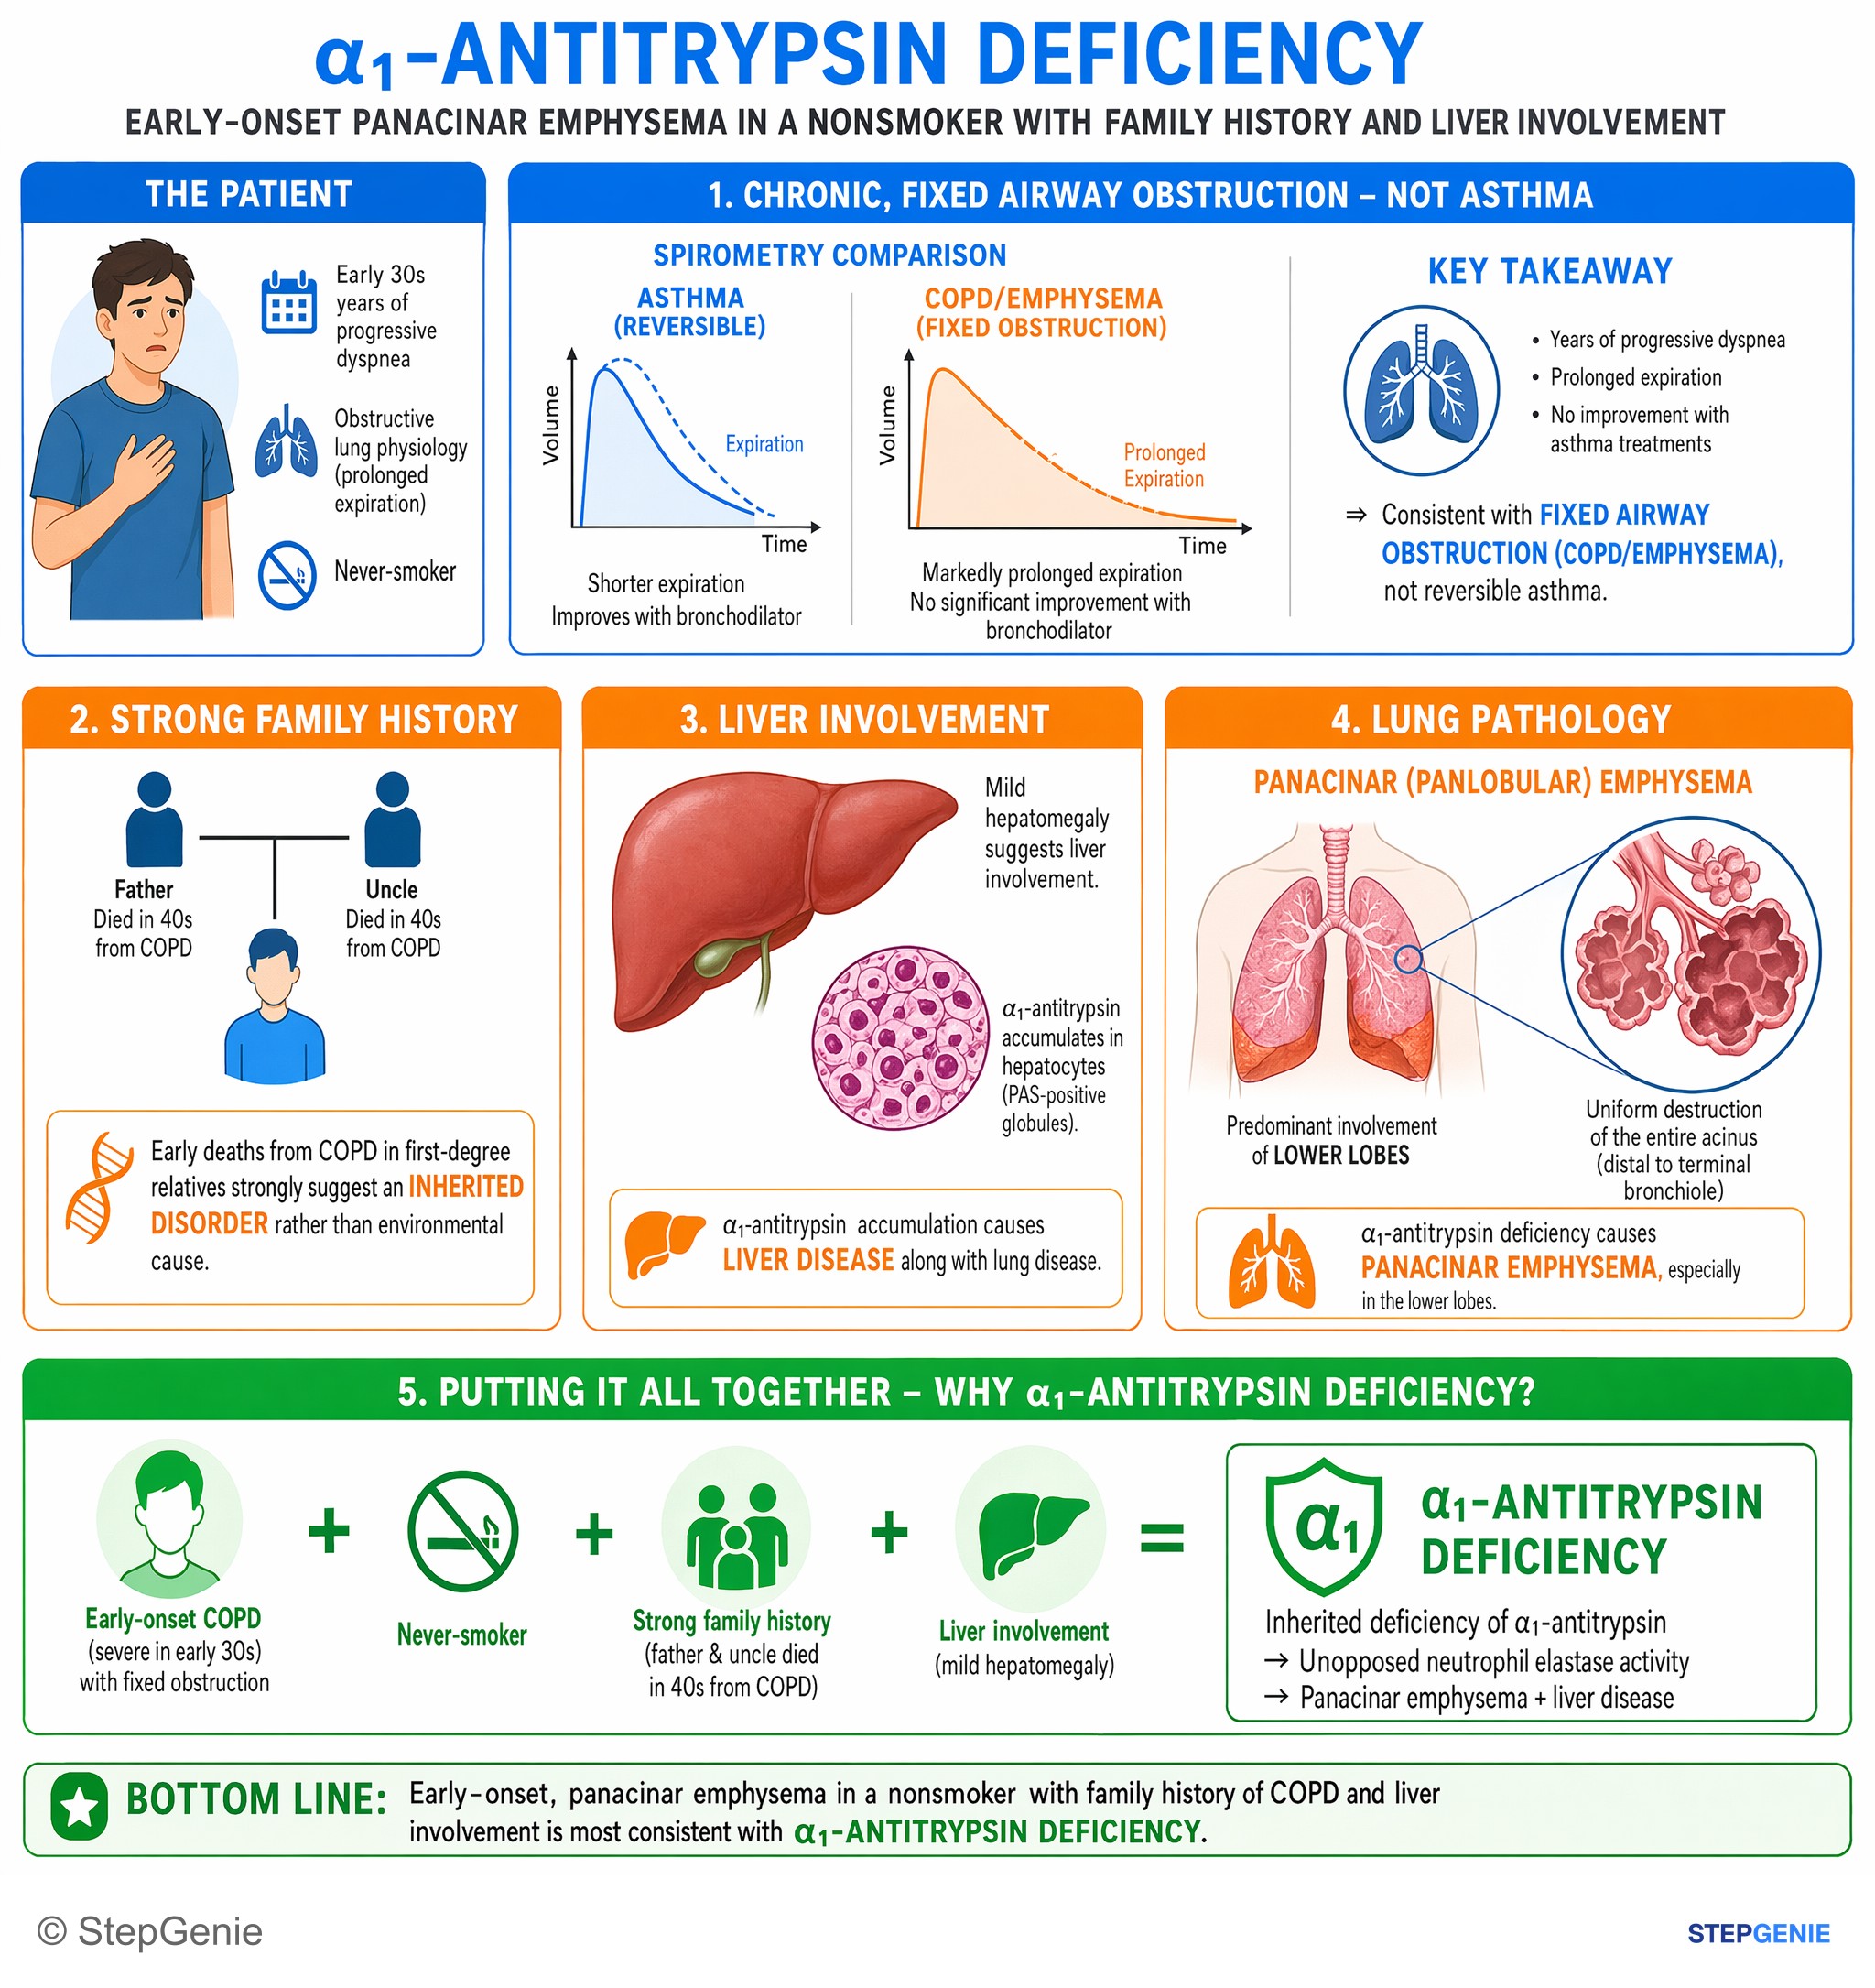
α1-antitrypsin deficiency → early-onset panacinar emphysema in a nonsmoker with family history of COPD and liver involvement.
USMLE Step 2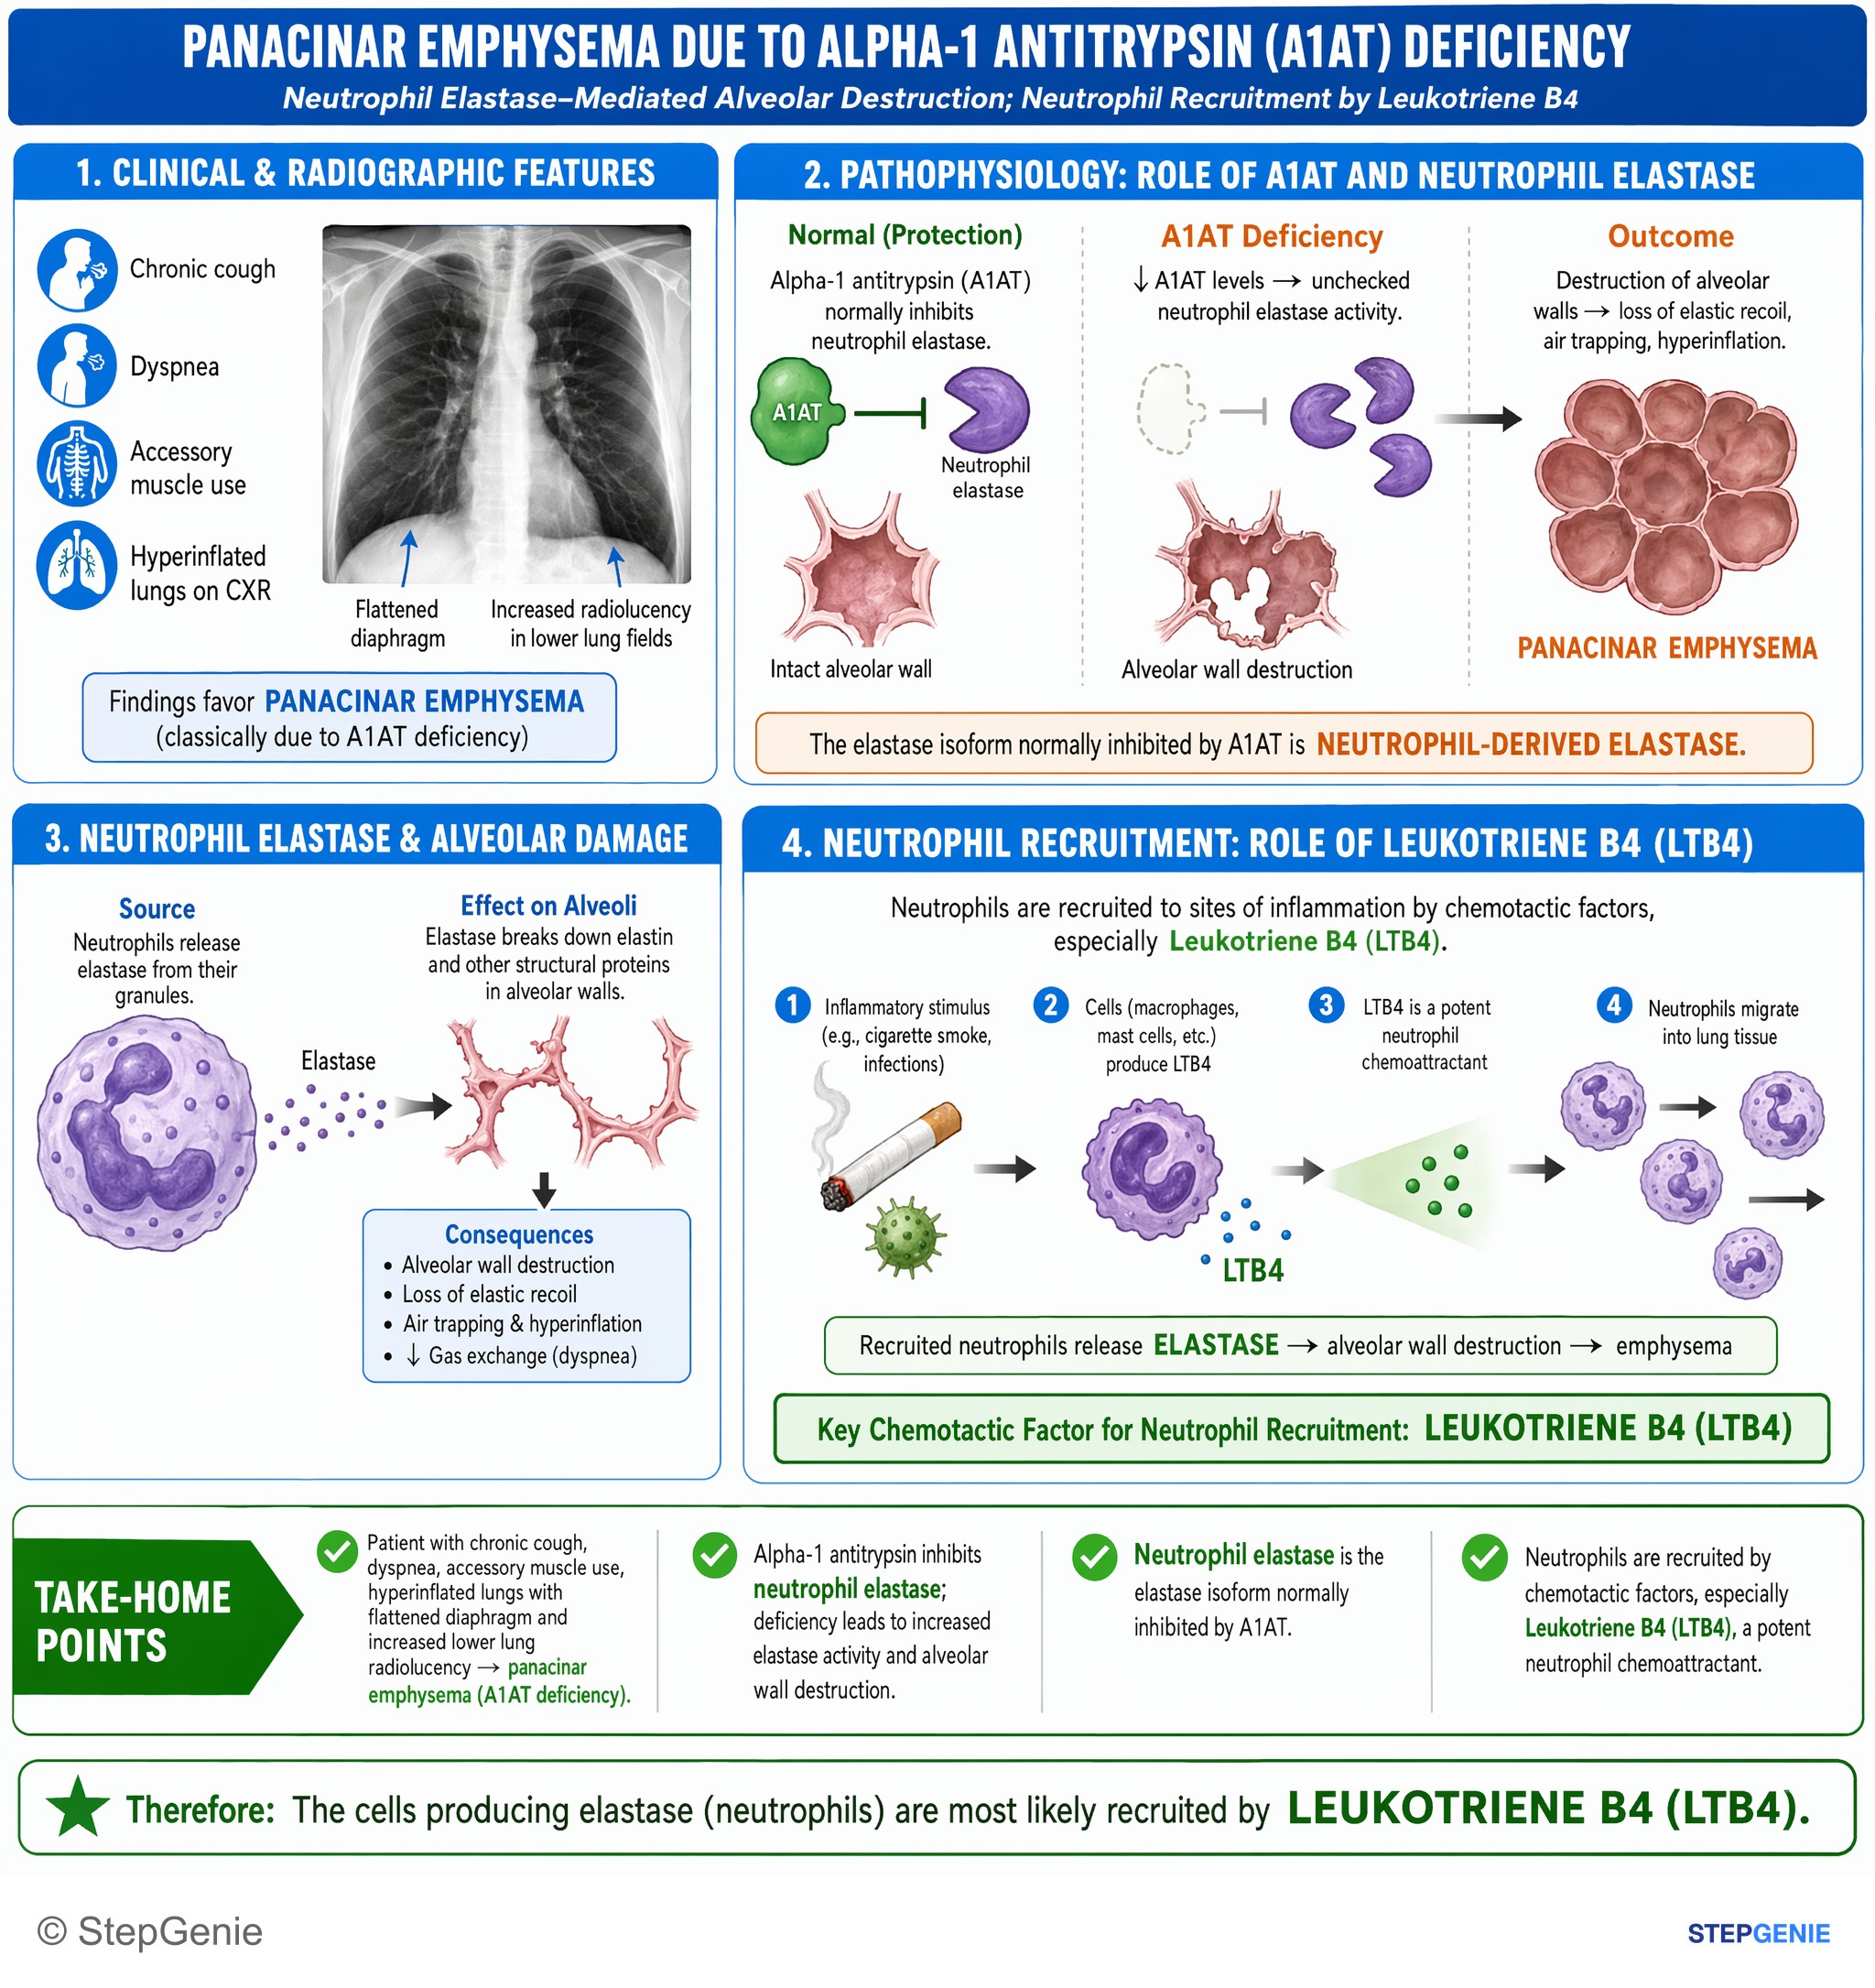
Panacinar emphysema due to A1AT deficiency involves neutrophil elastase–mediated destruction; LTB4 is a key neutrophil chemoattractant.
USMLE Step 1Frequently Asked Questions
Why does alpha-1 antitrypsin deficiency cause emphysema?
Alpha-1 antitrypsin deficiency causes emphysema because it leads to unopposed neutrophil elastase activity in the lungs. Alpha-1 antitrypsin is made in the liver and normally inhibits elastase. When it is deficient, elastase breaks down elastin in the alveolar septa, causing progressive destruction of alveolar walls and producing emphysema, classically with a panacinar pattern.
How do you tell alpha-1 antitrypsin deficiency emphysema from smoking-related emphysema?
The key distinction is that alpha-1 antitrypsin deficiency causes panacinar emphysema that is most prominent in the lower lobes, often in a younger patient with little or no smoking history. Smoking-related emphysema is typically centriacinar and upper-lobe predominant. A vignette describing early-onset COPD with minimal smoking exposure and basilar emphysema should point toward alpha-1 antitrypsin deficiency.
Why are the lower lobes more affected in alpha-1 antitrypsin deficiency?
The lower lobes are more affected because perfusion is higher at the lung bases, which increases inflammatory cell trafficking there. That creates a greater elastase burden in the lower lobes. When alpha-1 antitrypsin is missing, there is less protection against neutrophil elastase, so the increased elastase activity causes more damage in the basilar regions.
Why can alpha-1 antitrypsin deficiency cause elevated liver enzymes along with lung disease?
Alpha-1 antitrypsin deficiency can affect both the lungs and liver because the abnormal protein is produced in the liver and may misfold and accumulate in hepatocytes. The lung problem comes from low circulating alpha-1 antitrypsin and increased elastase activity, while the liver problem comes from misfolded protein trapped in the endoplasmic reticulum, leading to hepatitis or cirrhosis and mildly elevated AST and ALT.
How is alpha-1 antitrypsin deficiency diagnosed and treated?
Diagnosis starts with a decreased serum alpha-1 antitrypsin level, and phenotyping or genotyping is used to confirm the subtype. Management includes smoking cessation, which is especially important, along with COPD inhaler therapy as needed. Select patients may receive IV alpha-1 antitrypsin augmentation, and liver transplant can be curative for hepatic disease because it restores normal alpha-1 antitrypsin production.