The FEV1/FVC ratio is the share of the forced vital capacity (FVC) that a patient blows out in the first second (FEV1), and a low ratio means airflow obstruction. The ERS/ATS 2022 interpretation standard defines obstruction as a ratio below the lower limit of normal (LLN, the 5th percentile, a z-score below −1.645), while GOLD 2026 still diagnoses COPD with a post-bronchodilator ratio below 0.70. A normal or high ratio with a low FVC only suggests restriction: a total lung capacity (TLC) below the LLN confirms it, and a low ratio plus a low TLC is a mixed defect. DLCO then names the cause: low in emphysema and interstitial lung disease, normal in chronic bronchitis and in chest wall or neuromuscular restriction, and normal or high in asthma.
The one-page cheat sheet
| Measure | Obstructive | Restrictive | Mixed | Non-specific pattern |
|---|---|---|---|---|
| FEV1/FVC | Low (below LLN; GOLD: below 0.70 after bronchodilator) | Normal or high | Low | Normal |
| FEV1 | Low | Low, in proportion to volume | Low | Low (FEV1 and/or FVC) |
| FVC | Normal or low | Low | Normal or low | Low or normal |
| TLC | Normal or high (hyperinflation) | Low (below LLN): the defining test | Low | Normal |
| RV | Normal or high (air trapping) | Low | Varies | Not defining |
Add DLCO to name the disease
| Condition | Pattern | TLC | DLCO | Clue in the stem |
|---|---|---|---|---|
| Asthma | Obstructive, reversible | Normal (high during attacks) | Normal or high | Episodic wheeze, large bronchodilator response |
| Chronic bronchitis | Obstructive | Normal or high | Normal | Productive cough at least 3 months a year for 2 years in a row |
| Emphysema | Obstructive | High | Low | Smoker, barrel chest, hyperinflated chest x-ray |
| Interstitial lung disease (IPF, sarcoidosis, hypersensitivity pneumonitis, asbestosis and other pneumoconioses) | Restrictive | Low | Low | Fine crackles, exertional desaturation |
| Chest wall or obesity (kyphoscoliosis, morbid obesity) | Restrictive | Low | Normal | Deformity, high BMI |
| Neuromuscular weakness (ALS, Guillain-Barré, myasthenia gravis) | Restrictive | Low | Normal | Weak cough, low maximal inspiratory and expiratory pressures |
| Pulmonary vascular disease (chronic PE, pulmonary hypertension) | Often normal spirometry | Normal | Low | Isolated low DLCO |
| Alveolar hemorrhage, polycythemia | Varies | Varies | High | Hemoptysis; high hematocrit |
What FEV1, FVC and the ratio mean
- FVC is the most air a patient can forcibly exhale after a maximal breath in; FEV1 is the volume exhaled in the first second, the most reproducible flow measurement and the one used to grade obstruction.
- Obstruction comes from a narrowed lumen (secretions, tumor), a thickened or constricted wall (smooth muscle, edema) or lost elastic recoil (emphysema). FEV1 falls more than FVC, so the ratio drops, and incomplete emptying traps air, raising RV and often TLC.
- Restriction comes from stiff lungs (fibrosis), a stiff or heavy chest wall (kyphoscoliosis, obesity, pleural disease), weak inspiratory muscles or lost lung tissue (lobectomy). FEV1 and FVC fall together, and the extra elastic recoil of fibrotic lungs holds the airways open, so the ratio stays normal or rises.
- Memory hook: FVC is the size of the room; FEV1 is how much of it empties into the hallway in one second. Obstruction is a narrow hallway (low ratio); restriction is a small room (normal or high ratio).
LLN vs the fixed 0.70 cut-off
The normal ratio falls with age. Merck lists expected FEV1/FVC values of about 85% at 8-19 years, 80% at 20-39, 75% at 40-59 and 70% at 60-80, so one fixed cut-off mislabels people at both ends of life.
- ERS/ATS 2022: obstruction = FEV1/FVC below the LLN (5th percentile of a healthy reference population; z-score below −1.645). The standard strongly discourages the fixed 0.70 ratio and the 80%-of-predicted cut-offs.
- GOLD 2026: COPD requires a post-bronchodilator FEV1/FVC below 0.70 in the right clinical setting. GOLD keeps the fixed ratio for simplicity, accepting possible over-diagnosis in older adults and under-diagnosis in about 1% of young adults (under age 50, compare with the LLN or z-score). Confirm a ratio of 0.60-0.80 on a separate occasion; a pre-bronchodilator test without obstruction can exclude COPD unless suspicion is very high.
- Exam framing: most stems still use "FEV1/FVC below 0.70 = obstruction"; if a report gives the LLN or a z-score, use it.
Grading severity: by FEV1, not by the ratio
| System | Measure | Mild | Moderate | Severe | Very severe |
|---|---|---|---|---|---|
| GOLD (COPD, ratio below 0.70) | Post-bronchodilator FEV1, % predicted | 80% or more (GOLD 1) | 50-79% (GOLD 2) | 30-49% (GOLD 3) | Below 30% (GOLD 4) |
| ERS/ATS 2022 (any impairment) | z-score | −1.65 to −2.5 | −2.51 to −4.0 | Below −4.1 | No fourth level |
Confirming restriction: measure TLC
Spirometry cannot measure RV (the air that never leaves the lungs), so it cannot measure TLC. Body plethysmography is the more accurate method when air is trapped; helium dilution and nitrogen washout underestimate volumes in severe obstruction.
- Restriction = TLC below the LLN (many textbooks still write TLC below 80% of predicted). Early restriction can show only a low RV.
- A low FVC with a low ratio is not automatically mixed. In obstruction, trapped air raises RV and shrinks FVC ("pseudo-restriction"). A normal or high TLC means pure obstruction (as does an FVC that rises to the LLN or above after a bronchodilator); a low TLC means a mixed defect.
- Non-specific pattern: low FEV1 and/or FVC, normal ratio, normal TLC; it can reflect reduced effort, restriction or early small-airway disease (ERS/ATS 2022). Without TLC, this preserved-ratio pattern is called PRISm (GOLD: post-bronchodilator ratio 0.70 or more, FEV1 below 80% predicted); about 20-30% later develop obstruction.
- Refresh the lung volumes and capacities and compliance vs elastance.
DLCO: the tiebreaker
DLCO measures how well inhaled carbon monoxide crosses into red cells, so it depends on the area and thickness of the alveolar-capillary membrane and on pulmonary capillary blood volume. Beyond the table:
- Low also with anemia (corrects when adjusted for hemoglobin) and after lung resection. An isolated low DLCO suggests pulmonary vascular disease, early interstitial lung disease or anemia.
- Normal in pleural effusion and other extraparenchymal restriction: the alveoli and capillaries are healthy.
- High also in asthma and left-to-right intracardiac shunts; in alveolar hemorrhage, red cells in the alveoli bind carbon monoxide.
Bronchodilator response: 10% of predicted vs 12% and 200 mL
- ERS/ATS 2022: a positive response is a rise in FEV1 or FVC of more than 10% of the patient's predicted value, calculated as (post − pre) ÷ predicted × 100.
- Classic exam rule (ATS/ERS 2005): a rise of at least 12% and at least 200 mL from baseline in FEV1 or FVC, still the usual Step answer.
- Why it changed: dividing by a very low baseline inflates the percentage. If FEV1 rises from 1.20 L to 1.45 L with a predicted value of 3.00 L, that is +250 mL and +21% from baseline (positive by the old rule) but only 8.3% of predicted (not positive by ERS/ATS 2022).
- Meaning: a large response supports asthma, but COPD can respond too; GOLD 2026 says reversibility neither separates COPD from asthma nor predicts long-term treatment response.
Flow-volume loops: small airways vs upper airway
| Loop | Shape | Classic causes |
|---|---|---|
| Obstructive | Scooped-out (concave) expiratory limb | COPD, asthma |
| Restrictive | Small loop, normal shape; flow is high for the lung volume | Interstitial lung disease, kyphoscoliosis |
| Fixed upper airway obstruction | Both limbs flattened into a box | Tracheal stenosis, goiter |
| Variable extrathoracic obstruction | Inspiratory limb flattened; expiration normal | Vocal fold paralysis, vocal fold dysfunction |
| Variable intrathoracic obstruction | Expiratory plateau (flat, not scooped) | Tracheomalacia |
During forced inspiration, pressure inside the extrathoracic airway drops and a floppy segment is sucked inward; during forced expiration, high pleural pressure squeezes a floppy intrathoracic segment. Extrathoracic flattens inspiration, intrathoracic flattens expiration, fixed flattens both.
Stepwise interpretation flowchart
- Check quality. Fast start, no cough, smooth curve, full exhalation and repeatable efforts. Poor effort lowers both FEV1 and FVC and can mimic restriction.
- Is FEV1/FVC below the LLN (or below 0.70 in a classic stem or for GOLD)?
- Yes = obstruction. Grade it by FEV1, test the bronchodilator response, and if FVC is also low, measure TLC: normal or high = air trapping; low = mixed.
- No: go to step 3.
- Is FVC low?
- No = normal spirometry. If asthma is still suspected, do a methacholine challenge (a fall in FEV1 of 20% or more supports airway hyperresponsiveness).
- Yes = possible restriction: measure TLC. Low = restriction; normal = non-specific pattern. (Without TLC, a preserved ratio with a low FEV1 is called PRISm.)
- Add DLCO (table above): obstruction + low DLCO = emphysema; restriction + low DLCO = interstitial lung disease; restriction + normal DLCO = chest wall, obesity or neuromuscular disease.
- Look at the loop if the stem mentions stridor, a goiter or "asthma" that never responds to inhalers (vocal fold dysfunction mimics asthma).
Worked examples (illustrative numbers)
| Results | Read | Why |
|---|---|---|
| 79-year-old: FEV1/FVC 0.68, z-score −0.9 | Normal | Above the LLN; the fixed 0.70 cut-off would over-call obstruction |
| 28-year-old with cough: FEV1/FVC 0.71, z-score −1.8 | Obstruction | Below the LLN even though it is above 0.70 |
| FEV1/FVC 0.86, FVC 60%, TLC below LLN, DLCO 45% | Parenchymal restriction | Interstitial lung disease such as IPF or asbestosis |
Practice question
A 63-year-old man with a 45-pack-year smoking history has 2 years of progressive exertional dyspnea with little sputum. He is thin, with a barrel chest, distant breath sounds and a prolonged expiratory phase. Pulmonary function testing shows:
| Test | Result |
|---|---|
| FEV1 (post-bronchodilator) | 45% of predicted |
| FVC (post-bronchodilator) | 72% of predicted |
| FEV1/FVC (post-bronchodilator) | 0.48 (below the LLN) |
| FEV1 change after albuterol | +60 mL (2% of predicted) |
| TLC | 128% of predicted |
| RV | 190% of predicted |
| DLCO (hemoglobin normal) | 42% of predicted |
| Flow-volume loop | Concave expiratory limb, normal inspiratory limb |
Which of the following best explains these findings?
A. Interstitial fibrosis with decreased lung compliance B. Loss of elastic recoil and alveolar surface area C. Reversible bronchial smooth muscle constriction D. Mucus gland hyperplasia with intact alveoli E. Respiratory muscle weakness F. Fixed narrowing of the trachea G. Normal age-related decline H. Submaximal effort during testing
Answer: B. A ratio of 0.48 is obstruction, a TLC of 128% is hyperinflation (so the low FVC is trapped air, not restriction), an RV of 190% is air trapping, and a low DLCO with a normal hemoglobin means lost alveolar-capillary surface: emphysema. The concave expiratory limb fits small airways collapsing on expiration, the tiny bronchodilator response fits fixed obstruction, and a post-bronchodilator FEV1 of 45% is GOLD 3 (severe). Review the COPD Q-bank breakdown, and think of alpha-1 antitrypsin deficiency when emphysema appears in a young nonsmoker.
- A: fibrosis is restrictive (normal or high ratio, low TLC); only the low DLCO matches.
- C: asthma shows reversibility and a normal or high DLCO; here the response is 2% of predicted and the DLCO is low.
- D: chronic bronchitis is obstruction with a chronic productive cough and a normal DLCO, because the alveoli are intact.
- E: neuromuscular weakness is restrictive: low TLC, normal ratio, normal DLCO, low maximal respiratory pressures.
- F: fixed tracheal narrowing flattens both loop limbs into a box; it does not raise TLC or lower DLCO.
- G: the normal ratio falls to about 0.70 by age 60-80, but 0.48 with an FEV1 of 45% and a low DLCO is disease.
- H: poor effort gives non-repeatable curves that underestimate FEV1 and FVC, but it cannot push TLC above normal or explain the emphysema signs on examination.
How USMLE tests it
- Classic pairs: emphysema vs chronic bronchitis = low vs normal DLCO; fibrosis vs obesity or ALS = low vs normal DLCO.
- Traps: low FEV1 and FVC are not restriction until TLC is low; asthma between attacks can have normal spirometry (methacholine next); stridor or a box-shaped loop is upper airway obstruction, not COPD.
Key takeaways
- FEV1/FVC below the LLN = obstruction (ERS/ATS 2022); GOLD 2026 still uses a post-bronchodilator ratio below 0.70 for COPD, which can over-call obstruction in older adults.
- Restriction needs a low TLC. A low FVC with a normal ratio is a clue; a low FVC with a low ratio may be air trapping.
- Mixed = low ratio + low TLC; non-specific = low FEV1 and/or FVC with a normal ratio and normal TLC (PRISm when TLC is not measured).
- DLCO: low in emphysema, interstitial lung disease and vascular disease; normal in chronic bronchitis and extraparenchymal restriction; normal or high in asthma.
- Bronchodilator response: more than 10% of predicted FEV1 or FVC (ERS/ATS 2022); classic exam rule at least 12% and 200 mL.
Sources
- Airflow, Lung Volumes, and Flow-Volume Loop — Merck Manual Professional Edition (2026)
- Measurement of Gas Exchange (DLCO) — Merck Manual Professional Edition (2026)
- Tests of Respiratory Muscle Function — Merck Manual Professional Edition (2026)
- ERS/ATS Technical Standard on Interpretive Strategies for Routine Lung Function Tests — European Respiratory Journal (2022)
- 2026 GOLD Report and Pocket Guide — Global Initiative for Chronic Obstructive Lung Disease (2026)
- Chronic Obstructive Pulmonary Disease (COPD) — Merck Manual Professional Edition (2026)
- Asthma — Merck Manual Professional Edition (2026)
- A Stepwise Approach to the Interpretation of Pulmonary Function Tests — American Family Physician (2014)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
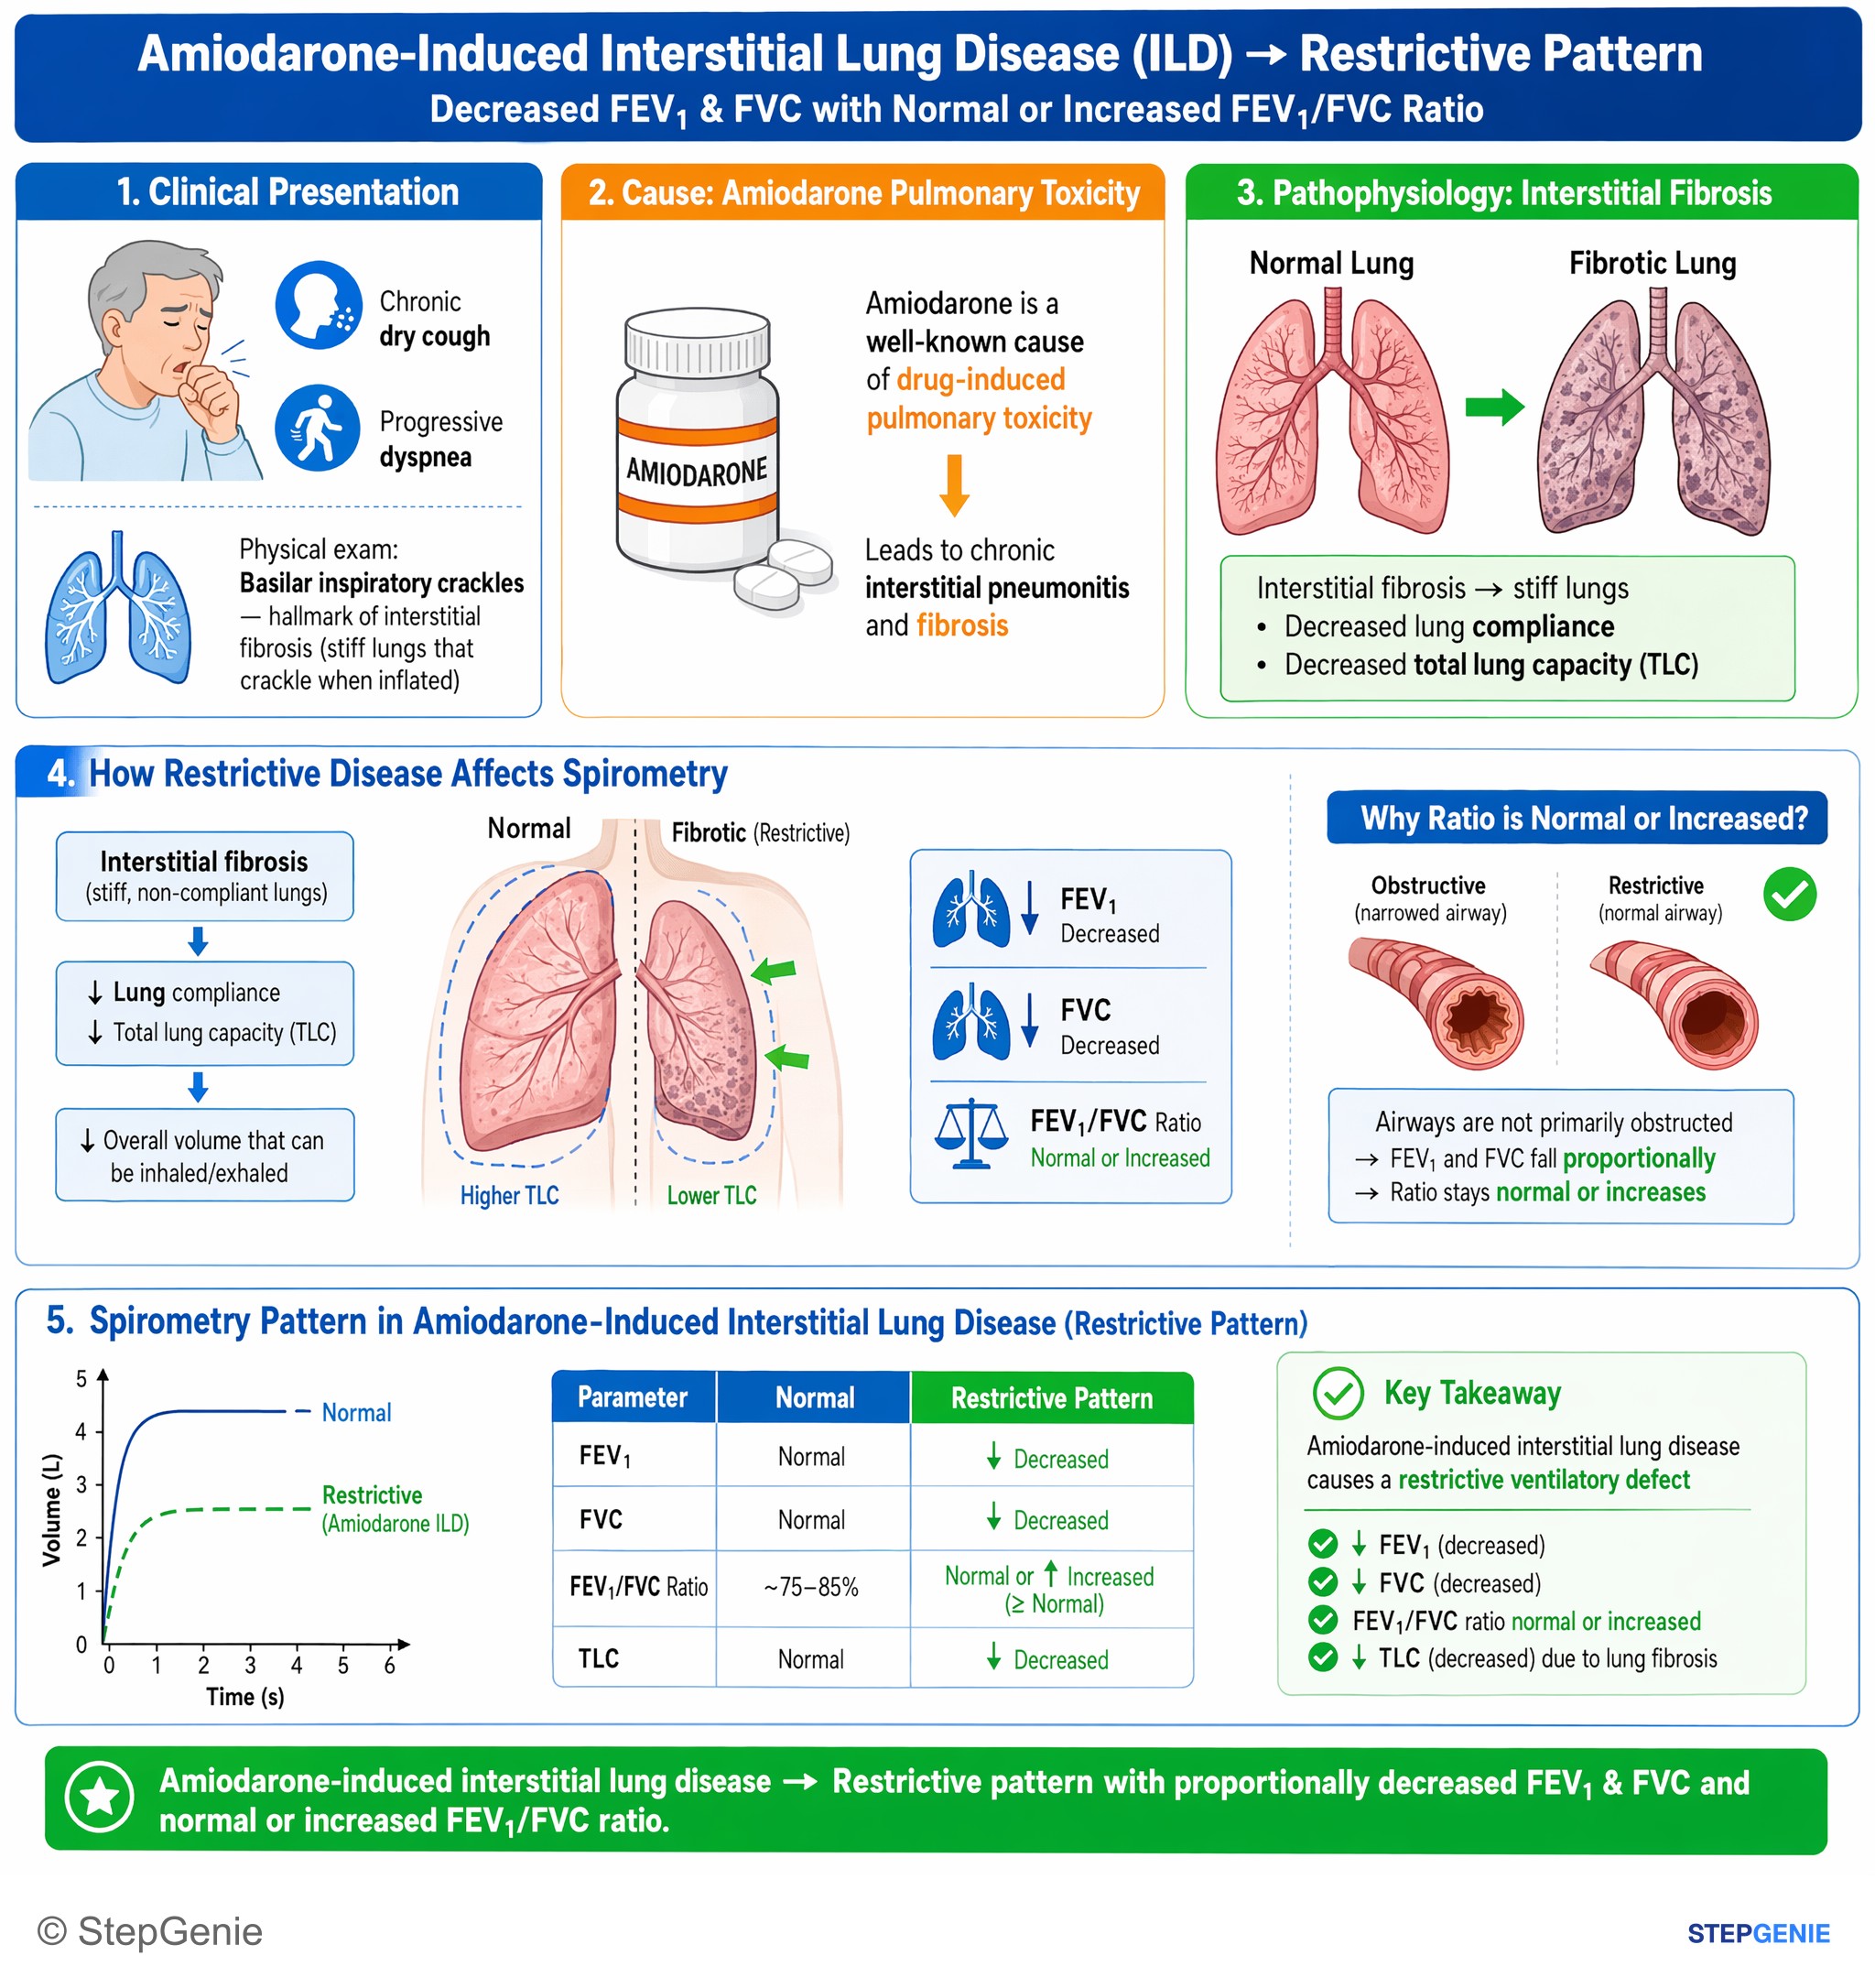
Amiodarone-induced interstitial lung disease causes a restrictive pattern with proportionally decreased FEV1 & FVC and normal or increased…
USMLE Step 1Frequently Asked Questions
What does a low FEV1/FVC ratio mean?
A low FEV1/FVC ratio means airflow obstruction: the patient exhales a smaller than normal share of the forced vital capacity in the first second. The 2022 ERS/ATS standard defines it as a ratio below the lower limit of normal, the 5th percentile for age, sex and height. Common causes are COPD, asthma, bronchiectasis and cystic fibrosis. Severity is graded by the FEV1, not by the ratio, and lung volumes and DLCO help identify the cause.
Is an FEV1/FVC ratio below 0.70 always COPD?
No. GOLD 2026 diagnoses COPD with a post-bronchodilator FEV1/FVC below 0.70 plus compatible symptoms and exposures, but a low ratio also occurs in asthma and other obstructive diseases. Because the normal ratio falls with age, the fixed 0.70 cut-off can over-diagnose obstruction in older adults and miss some young adults, which is why the ERS/ATS 2022 standard prefers the lower limit of normal. GOLD advises confirming the result on a separate occasion when the ratio is between 0.60 and 0.80.
How do you tell obstructive from restrictive lung disease on PFTs?
Start with the FEV1/FVC ratio. A low ratio means obstruction. A normal or high ratio with a low FVC suggests restriction, but restriction is confirmed only when total lung capacity is below the lower limit of normal on lung volume testing. If the ratio is low and TLC is also low, the defect is mixed. If TLC is normal or high despite a low FVC, the low FVC reflects air trapping from obstruction rather than restriction.
What is a significant bronchodilator response on spirometry?
The 2022 ERS/ATS standard defines a positive bronchodilator response as an increase in FEV1 or FVC of more than 10 percent of the patient's predicted value. The older ATS/ERS 2005 rule, still common on exams, requires an increase of at least 12 percent and at least 200 mL from baseline. A large response supports asthma, but COPD can respond too, and GOLD notes that reversibility does not reliably distinguish COPD from asthma.
What does DLCO tell you in obstructive and restrictive lung disease?
DLCO measures gas transfer across the alveolar-capillary membrane. In obstruction, a low DLCO points to emphysema, a normal DLCO fits chronic bronchitis, and a normal or high DLCO fits asthma. In restriction, a low DLCO points to interstitial lung disease, while a normal DLCO suggests a chest wall, obesity or neuromuscular cause. An isolated low DLCO with normal spirometry suggests pulmonary vascular disease, early interstitial lung disease or anemia.
How do flow-volume loops show upper airway obstruction?
A fixed upper airway obstruction, such as tracheal stenosis or a goiter, flattens both the inspiratory and expiratory limbs into a box shape. A variable extrathoracic obstruction, such as vocal fold paralysis or vocal fold dysfunction, flattens only the inspiratory limb. A variable intrathoracic obstruction, such as tracheomalacia, flattens the expiratory limb. Small-airway obstruction in COPD or asthma instead produces a scooped-out, concave expiratory limb.