CADET, face Right is a mnemonic for what shifts the oxygen-hemoglobin dissociation curve to the right: more CO2, Acid (H+), 2,3-DPG (2,3-BPG), Exercise and Temperature. A right shift raises the P50 (normally about 27 mm Hg) and helps tissues unload O2; the opposite changes, fetal hemoglobin, carbon monoxide and methemoglobin shift it left.
For any curve question, ask two things: did the curve move (affinity, read from the P50), and did the amount of O2 in the blood change (content)? Carbon monoxide does both, anemia only lowers content, and cyanide does neither: cells simply can't use the O2 they receive.
CADET, face Right: the right-shift mnemonic
Each letter lowers hemoglobin's O2 affinity when it rises. Whether you learned it as "face right" or "turn right," the letters are the same.
| Letter | Stands for | Why affinity falls | Where you see it |
|---|---|---|---|
| C | CO2 ↑ | CO2 forms carbonic acid; it also has a smaller direct effect | Active tissue, hypoventilation |
| A | Acid (H+ ↑, pH ↓) | Protons favor the low-affinity T state (Bohr effect) | Lactic acid, any acidosis |
| D | 2,3-DPG (2,3-BPG) ↑ | Binds deoxyhemoglobin's central cavity and stabilizes the T state | Chronic hypoxia, pyruvate kinase deficiency |
| E | Exercise | Brings heat, CO2 and lactic acid together | Working skeletal muscle |
| T | Temperature ↑ | Heat favors O2 release | Fever, active tissue |
Flip every arrow for the left shifters: less CO2 (hyperventilation), alkalosis, less 2,3-BPG (stored blood) and cold. Then add three the mnemonic can't cover: fetal hemoglobin (HbF), carbon monoxide and methemoglobin. A hook for that side: Left = Lower P50 = Loves O2 (holds on to it).
The oxygen-hemoglobin dissociation curve: shape, P50 and key numbers
The curve plots hemoglobin O2 saturation (the percentage of binding sites occupied) against PO2. It is sigmoid because binding is cooperative: deoxyhemoglobin sits mostly in the low-affinity T (tense) state, and each O2 that binds shifts the other subunits toward the high-affinity R (relaxed) state, so the next binds more easily; unloading works in reverse. Hemoglobin's Hill coefficient is about 2.6; a coefficient of 1 (no cooperativity) gives a hyperbolic curve like myoglobin's. The same T/R logic governs allosteric regulation of enzymes.
| PO2 | Saturation | Why it matters |
|---|---|---|
| About 100 mm Hg (arterial, sea level) | 96-98% | Flat top: loading is protected, and more PO2 adds mainly dissolved O2 |
| 60 mm Hg | About 90% | The usual hypoxemia cut-off; below it saturation falls steeply |
| 40 mm Hg (mixed venous) | About 75% | At rest, tissues use only part of the O2 delivered |
| 26-27 mm Hg (P50) | 50% | The standard measure of affinity |
- P50 is the PO2 at which hemoglobin is 50% saturated: 27 mm Hg in Merck, about 26 mm Hg in a European Respiratory Society review. Higher P50 = right shift = lower affinity; lower P50 = left shift = higher affinity.
- Plateau vs steep part: flat at lung PO2, so a modest fall in alveolar PO2 barely changes saturation; steep at tissue PO2, so a small fall releases a lot of O2.
- Content is mostly hemoglobin: only about 1.5% of blood O2 is dissolved, and resting tissues extract only about 20-25% of what is delivered.
Left vs right shift: what changes, and what it does to loading and unloading
| Right shift | Left shift | |
|---|---|---|
| P50 | Higher | Lower |
| O2 affinity | Lower | Higher |
| Unloading in tissues | Easier | Harder |
| Loading in the lungs | Little change at a normal alveolar PO2 | Easier, which matters when alveolar PO2 is low |
| Causes | ↑ CO2, ↑ H+, ↑ 2,3-BPG, ↑ temperature, exercise; HbS; pyruvate kinase deficiency | ↓ CO2, alkalosis, ↓ 2,3-BPG (stored blood), hypothermia; HbF, CO, methemoglobin, Hb Barts |
| Typical stem | Febrile, acidotic or exercising patient | Neonate, house fire, benzocaine or dapsone, stored-blood transfusion |
Why direction matters. Arterial blood sits on the flat top of the curve, so a right shift costs little loading at a normal alveolar PO2 but releases more O2 at tissue PO2. When alveolar PO2 is very low, loading moves onto the steep part and a left shift becomes protective: that is how fetal blood loads O2 at the placenta, and why the alkalosis-driven left shift near Everest's summit helps climbers.
High altitude: the classic timeline and the in vivo twist
- Hours: hypoxia drives hyperventilation and respiratory alkalosis, a left-shifting influence (see respiratory acidosis and alkalosis).
- Days: alkalosis stimulates red cell 2,3-BPG synthesis; the classic teaching is a right shift by day 2 or 3. The kidneys excrete bicarbonate, and pH tends to normalize within days.
- Weeks: erythropoietin raises red cell mass.
- What studies found: after 4 days at a simulated 3,500 m, 2,3-BPG rose but the P50 at each subject's own PCO2 was unchanged (26.4 vs 26.1 mm Hg); other moderate-altitude studies found shifts in either direction. On the 1981 Everest expedition, estimated in vivo P50 was 27.6 mm Hg at 6,300 m (28.1 at sea level), 24.9 at 8,050 m and 19.4 on the summit in one climber: at extreme altitude alkalosis wins, and the left shift protects arterial saturation.
Stored blood
Red cells stored more than 7 days lose 2,3-BPG (none is left after 10 days), so they hold O2 more tightly; in one surgical study, units stored a mean of 24 days had about 90% less 2,3-BPG and a 30% lower P50. Recovery after transfusion takes 12-24 hours per Merck, but up to 3 days in that study. It seems to matter clinically only in infant exchange transfusion, sickle cell disease with acute chest syndrome or stroke, and some severe heart failure.
Bohr effect, Haldane effect and 2,3-BPG
- Bohr effect: more CO2 and H+ lower hemoglobin's O2 affinity, so O2 comes off where metabolism is high. The CO2 effect works mostly through the acid it generates (CO2 + H2O ⇌ H2CO3 ⇌ H+ + HCO3−), which ties the curve to acid-base physiology.
- Haldane effect (the CO2 side of the same coin): at the same PCO2, deoxygenated blood carries more CO2 than oxygenated blood, because deoxyhemoglobin forms more carbaminohemoglobin and buffers H+ better. In the lungs, O2 binding makes hemoglobin give up CO2 and H+.
- 2,3-BPG comes from red cell glycolysis, binds deoxyhemoglobin in the central cavity and stabilizes the T state. It rises with chronic hypoxia and in pyruvate kinase deficiency, falls in stored blood, and binds HbF weakly.
Memory line: Bohr = CO2 and H+ push O2 off hemoglobin; Haldane = O2 pushes CO2 off hemoglobin.
Fetal hemoglobin, myoglobin and abnormal hemoglobins
| Molecule | Curve | P50 | Exam point |
|---|---|---|---|
| HbA (α2β2) | Sigmoid | 26-27 mm Hg | The reference curve |
| HbF (α2γ2) | Sigmoid, left-shifted | About 19 mm Hg | Binds 2,3-BPG weakly; pulls O2 from maternal blood |
| Myoglobin | Hyperbolic, left of HbA | Lower than HbA | One subunit, no cooperativity; stores O2 in muscle |
| Hb Barts (γ4) | Far left (very high affinity) | Lower than HbA | All four alpha genes deleted (alpha thalassemia): hydrops fetalis |
| HbS | Right-shifted | Higher than HbA | Polymerizes when deoxygenated |
| High-affinity variants | Left-shifted | Lower than HbA | Tissue hypoxia drives polycythemia (low-affinity variants: anemia) |
- HbF loads O2 at a placental PO2 of about 20 mm Hg on the fetal side (35-50 mm Hg in maternal placental blood). Hydroxyurea raises HbF in sickle cell disease, which helps prevent sickling (see sickle cell disease).
- Voxelotor raised hemoglobin's O2 affinity (a deliberate left shift) to inhibit HbS polymerization; it was withdrawn from the market in September 2024 after postmarketing trials showed more vaso-occlusive crises and deaths than placebo.
- HbF and CO: fetal hemoglobin binds CO more avidly, and fetal carboxyhemoglobin can keep rising after the mother's level stabilizes, one reason pregnancy lowers the threshold for hyperbaric O2.
Shift vs content: PaO2, saturation and the oxygen content equation
The most-missed idea: PaO2, saturation and O2 content are three different variables. PaO2 is the tension of dissolved O2 (it drives saturation), saturation is the percentage of hemoglobin sites carrying O2, and content is the total O2 per deciliter of blood:
Sources give the constant as 1.34 to 1.39 mL O2 per g Hb: 1.39 is the ideal stoichiometric value, 1.34 the measured one. With Hb 15 g/dL, SaO2 0.98 and PaO2 100 mm Hg, CaO2 ≈ 19.7 + 0.3 = 20 mL/dL. Halve the hemoglobin and content roughly halves, while PaO2 and SaO2 stay normal. Delivery is DO2 = cardiac output × CaO2 (× 10 for mL/min), normally about 1,000 mL/min against a consumption of about 250 mL/min.
Hypoxemia vs hypoxia: hypoxemia is a low PaO2 (usually below 60 mm Hg, or SpO2 below 90%); hypoxia means tissues get or use too little O2 for their needs, which anemia, low cardiac output or cyanide can cause despite a normal PaO2. Causes of a low PaO2: dead space vs shunt.
| PaO2 | Pulse oximetry | O2 content | Curve | Clue | |
|---|---|---|---|---|---|
| Hypoxemia | ↓ | ↓ | ↓ | 2,3-BPG may rise over days | Improves with O2 unless a shunt |
| Anemia | Normal | Normal | ↓ | No primary shift | Low mixed venous saturation |
| Carbon monoxide | Normal | Normal or falsely high | ↓ | Left | Fire, heater or exhaust |
| Methemoglobin | Normal | About 85%, not fixed by O2 | ↓ | Left | Oxidant drug; chocolate-brown blood |
| Cyanide | Normal | Normal | Normal | Not a hemoglobin problem | High venous O2, lactic acidosis |
Carbon monoxide poisoning: left shift plus lost carrying capacity
CO binds hemoglobin with about 200-250 times the affinity of O2 (Merck gives 210). It occupies binding sites, so content falls; it makes the remaining sites hold O2 more tightly (left shift, with a less sigmoid curve); and it inhibits cytochrome c oxidase in the electron transport chain.
- Clues: headache is most common, then dizziness, weakness and nausea; suspect it when several people from one heated home have flu-like symptoms. Delayed neurologic sequelae can appear 2-40 days later.
- Diagnosis: PaO2 is normal, pulse oximetry reads normal or high because it can't tell carboxyhemoglobin from oxyhemoglobin, and the saturation calculated on a standard blood gas looks normal too. Measure carboxyhemoglobin by co-oximetry; a venous sample is fine. ACEP (2017) advises against diagnosing CO toxicity with noninvasive pulse CO-oximetry. Levels fall quickly once O2 starts, so a low level after an ambulance ride doesn't exclude poisoning. In moderate to severe cases, get an ECG and cardiac biomarkers.
- Treatment: remove the source and give 100% O2 by nonrebreather mask, intubating if needed. The carboxyhemoglobin half-life is about 4-6 hours on room air, 60-90 minutes on 100% O2 and 20-30 minutes with hyperbaric O2.
- Hyperbaric O2 is selective, not routine. ACEP's 2025 policy makes only a Level C recommendation: selected symptomatic patients may benefit, depending on severity and how far away a chamber is. One double-blind trial found fewer cognitive sequelae at 6 weeks (25% vs 46%), but a Cochrane review concluded the trials do not establish benefit. Usual reasons for a hyperbaric consult: loss of consciousness, neurologic or cardiovascular findings, severe acidosis, carboxyhemoglobin above 25% and pregnancy.
- House fires bring cyanide too. Suspect it when the patient is more obtunded than the carboxyhemoglobin explains, doesn't improve with O2, or has lactic acidosis with a narrow arteriovenous O2 difference. Give hydroxocobalamin, but draw the carboxyhemoglobin sample first, because hydroxocobalamin can distort co-oximetry.
Methemoglobinemia: the pulse oximeter stuck near 85%
Methemoglobin has its iron oxidized from Fe2+ to Fe3+. It can't carry O2, and it shifts the curve of the remaining hemoglobin left. Cytochrome b5 reductase normally keeps levels below 1%.
- Causes: benzocaine and other local anesthetics, dapsone (see dermatitis herpetiformis), nitrites and nitrates (infants given well water, "poppers"), nitroglycerin, nitroprusside, primaquine, sulfonamides and aniline dyes. Congenital forms: cytochrome b5 reductase deficiency and hemoglobin M.
- By level: cyanosis from about 10%, chocolate-brown blood from about 15%, headache and anxiety near 20%, confusion at 30-50%, then seizures, arrhythmias and coma; above 70% is often fatal.
- Oximetry: a standard two-wavelength pulse oximeter reads about 85% once methemoglobin reaches 30-35%, often 75-90% despite supplemental O2. PaO2 is normal and the saturation calculated from it is falsely normal; the difference is the saturation gap (more than 5% suggests an abnormal hemoglobin). Co-oximetry confirms.
- Treatment: stop the drug (often enough) and give O2. Methylene blue is indicated for symptoms or levels above about 20-30%; the label dose is 1 mg/kg IV, repeated once after an hour if the level stays above 30% or symptoms persist. It works only after NADPH-dependent reduction to leukomethylene blue, and that NADPH comes from G6PD in the pentose phosphate pathway.
- The G6PD caveat: the FDA label lists G6PD deficiency as a contraindication (severe hemolysis, and the drug may not work). StatPearls (2025) calls its use controversial but not absolutely contraindicated: many G6PD-deficient patients keep enough enzyme activity to respond, so it should be given cautiously, not withheld. Classic teaching follows the label: avoid it in known G6PD deficiency; alternatives include exchange transfusion, hyperbaric O2 and, less reliably, ascorbic acid. See G6PD deficiency.
- Label warnings: serotonin syndrome with SSRIs, SNRIs, MAO inhibitors and opioids (boxed warning), and falsely low pulse oximeter readings from the dye itself.
Classic graph questions
- Which curve is myoglobin? The hyperbolic one, left of hemoglobin. Fetal blood? Sigmoid, left of the adult curve, P50 near 19 mm Hg. Exercising muscle, fever or acidosis? The curve to the right.
- When the y-axis is O2 content, not saturation: anemia lowers the plateau without moving the P50 (plot saturation instead, and the anemic and normal curves overlap); polycythemia raises it. CO lowers the plateau and moves the curve left, making it less sigmoid.
- An arrow on the steep part: a small fall in PO2 releases a lot of O2. On the plateau: a modest fall in alveolar PO2 barely changes arterial saturation.
USMLE traps: classic teaching vs current evidence
| Trap | What's actually true |
|---|---|
| "Altitude shifts the curve right" | 2,3-BPG rises, but alkalosis offsets it: in vivo P50 changes little at moderate altitude (studies disagree on direction) and falls at extreme altitude. Classic teaching stresses the 2,3-BPG rise |
| Normal pulse oximetry rules out CO poisoning | It reads normal or high; measure carboxyhemoglobin by co-oximetry |
| A pulse CO-oximeter can confirm CO toxicity | ACEP advises against using it for diagnosis |
| Every CO patient needs hyperbaric O2 | Everyone gets 100% O2; hyperbaric O2 is for selected patients (ACEP Level C) |
| Cherry-red skin is the CO sign | Rare; don't rely on it |
| Anemia shifts the curve | No primary shift: content falls, PaO2 and SaO2 stay normal; chronic anemia can raise 2,3-BPG (compensatory right shift) |
| High-flow O2 makes COPD patients hypercapnic by removing "hypoxic drive" | Mainly by worsening V/Q matching (hypoxic vasoconstriction is released), with the Haldane effect explaining about 25% of the rise; titrate to SpO2 88-92% |
More breathing physiology is on the Pulmonology hub.
Worked USMLE-style vignettes
Vignette 1: the house fire. A 24-year-old man is brought to the emergency department after being rescued from a house fire. He is confused and reports headache and nausea. Temperature is 37°C (98.6°F), pulse 110/min, blood pressure 122/70 mm Hg and respirations 18/min. Pulse oximetry reads 99% on room air, and arterial PaO2 is 95 mm Hg. Co-oximetry shows carboxyhemoglobin 28%. Which best describes the change in his oxygen-hemoglobin dissociation curve?
A. Right shift with decreased P50 B. Left shift with decreased P50 C. Right shift with increased P50 D. No shift; decreased hemoglobin concentration only E. Left shift with increased P50
Answer: B. CO occupies heme sites (lowering content) and shifts the curve left: affinity rises and the P50 falls. The normal PaO2 and 99% reading are the trap. He needs 100% O2 now; confusion and a level above 25% make him a hyperbaric candidate, and the fire raises the question of cyanide.
- A and E: internally inconsistent: a right shift always raises the P50, a left shift always lowers it.
- C: a real pattern (fever, acidosis, exercise), but nothing here lowers affinity.
- D: describes simple anemia, which lowers content without a shift.
Vignette 2: the 85% that won't budge. A 62-year-old man becomes cyanotic 20 minutes after benzocaine throat spray for a transesophageal echocardiogram. Pulse oximetry reads 85% and doesn't change on 100% O2. Arterial PaO2 is 410 mm Hg with a calculated saturation of 99%, and the blood looks chocolate-brown. What is the most likely cause?
A. Right-to-left shunt B. Carbon monoxide poisoning C. Methemoglobinemia D. Severe anemia E. Cyanide toxicity
Answer: C. Benzocaine oxidizes heme iron to Fe3+. The oximeter is pinned near 85% while the PaO2-based saturation is falsely normal: a saturation gap. Co-oximetry confirms it, and methylene blue is the treatment if he is symptomatic or the level is high, though the label contraindicates it in known G6PD deficiency.
- A: a shunt would lower the PaO2, which is very high here.
- B: CO makes the oximeter read normal or high, not low.
- D: anemia leaves pulse oximetry normal.
- E: cyanide leaves saturation normal; the problem is O2 use, not carriage.
Vignette 3: the anemia that's better tolerated. A 19-year-old woman with chronic hemolytic anemia from pyruvate kinase deficiency has hemoglobin 8 g/dL but plays college soccer with less fatigue than her physician expected. Which change in her red cells best explains this?
A. Decreased 2,3-BPG with a left shift B. Increased 2,3-BPG with a right shift C. Increased fetal hemoglobin with a left shift D. Increased arterial O2 content E. Decreased P50
Answer: B. Red cell 2,3-BPG is raised in pyruvate kinase deficiency. It stabilizes the T state, raises the P50 and shifts the curve right, so her tissues unload more O2 from each deciliter of blood.
- A: the stored-blood pattern, which makes unloading harder.
- C: more HbF would raise affinity and hinder unloading.
- D: with hemoglobin 8 g/dL, her content is lower.
- E: a lower P50 means a left shift.
Key takeaways
- CADET, face Right: more CO2, acid, 2,3-BPG, exercise and heat shift the curve right, raise the P50 (about 27 mm Hg) and favor unloading.
- Left shifters: alkalosis, low CO2, cold, low 2,3-BPG, HbF, CO and methemoglobin; they help loading but hinder unloading.
- Three variables: CaO2 = 1.34 × Hb × SaO2 + 0.003 × PaO2 (constant 1.34-1.39); anemia lowers content only.
- CO: normal PaO2 and pulse oximetry, low content, left shift; co-oximetry; 100% O2 for all, hyperbaric O2 for selected patients.
- Methemoglobin: pulse oximetry near 85% with a saturation gap; methylene blue, with G6PD deficiency the classic caution.
- Altitude: 2,3-BPG rises within days, but alkalosis offsets it in vivo; at extreme altitude the curve ends up left-shifted.
Sources
- Physiology, Oxyhemoglobin Dissociation Curve — StatPearls, NCBI Bookshelf (2023)
- Partial Pressure of Oxygen — StatPearls, NCBI Bookshelf (2026)
- Physiology, Oxygen Transport — StatPearls, NCBI Bookshelf (2022)
- Physiology, Bohr Effect — StatPearls, NCBI Bookshelf (2023)
- Physiology, Carbon Dioxide Transport — StatPearls, NCBI Bookshelf (2023)
- Physiology, Fetal Hemoglobin — StatPearls, NCBI Bookshelf (2023)
- Biochemistry, Myoglobin — StatPearls, NCBI Bookshelf (2023)
- Pyruvate Kinase Deficiency — StatPearls, NCBI Bookshelf (2023)
- Carbon Monoxide Poisoning — StatPearls, NCBI Bookshelf (2026)
- Methemoglobinemia — StatPearls, NCBI Bookshelf (2025)
- Sickle Cell Anemia — StatPearls, NCBI Bookshelf (2023)
- Measurement of Gas Exchange — Merck Manual Professional Edition (2026)
- Carbon Monoxide Poisoning — Merck Manual Professional Edition (2025)
- Smoke Inhalation — Merck Manual Professional Edition (2026)
- Complications of Transfusion — Merck Manual Professional Edition (2026)
- Acute Altitude Illness — Merck Manual Professional Edition (2026)
- Collins JA, et al. Relating Oxygen Partial Pressure, Saturation and Content — Breathe (2015)
- New Clinical Policy for Adult Patients with Acute Carbon Monoxide Poisoning — ACEP Now (2025)
- ACEP Clinical Policy on Acute Carbon Monoxide Poisoning — ACEP Now (2017)
- Weaver LK, et al. Hyperbaric Oxygen for Acute Carbon Monoxide Poisoning — N Engl J Med (2002)
- Buckley NA, et al. Hyperbaric Oxygen for Carbon Monoxide Poisoning — Cochrane Database Syst Rev (2011)
- Winslow RM, Samaja M, West JB. Red Cell Function at Extreme Altitude on Mount Everest — J Appl Physiol (1984)
- Balaban DY, et al. The In-Vivo Oxyhaemoglobin Dissociation Curve at Sea Level and High Altitude — Respir Physiol Neurobiol (2013)
- Woyke S, et al. A New Approach to Haemoglobin Oxygen Affinity Research at High Altitude — Eur J Appl Physiol (2025)
- Scott AV, et al. 2,3-Diphosphoglycerate Concentrations in Autologous Salvaged Versus Stored Red Blood Cells and in Surgical Patients After Transfusion — Anesth Analg (2016)
- Abdo WF, Heunks LM. Oxygen-Induced Hypercapnia in COPD: Myths and Facts — Crit Care (2012)
- Grewal A. Anaemia and Pregnancy: Anaesthetic Implications — Indian J Anaesth (2010)
- PROVAYBLUE (Methylene Blue) Injection Label — DailyMed (2025)
- Voluntary Withdrawal of Oxbryta (Voxelotor) From the Market — FDA (2024)
- OXBRYTA (Voxelotor) Prescribing Information — FDA (2019)
- 22.5 Transport of Gases — OpenStax Anatomy and Physiology 2e (2022)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
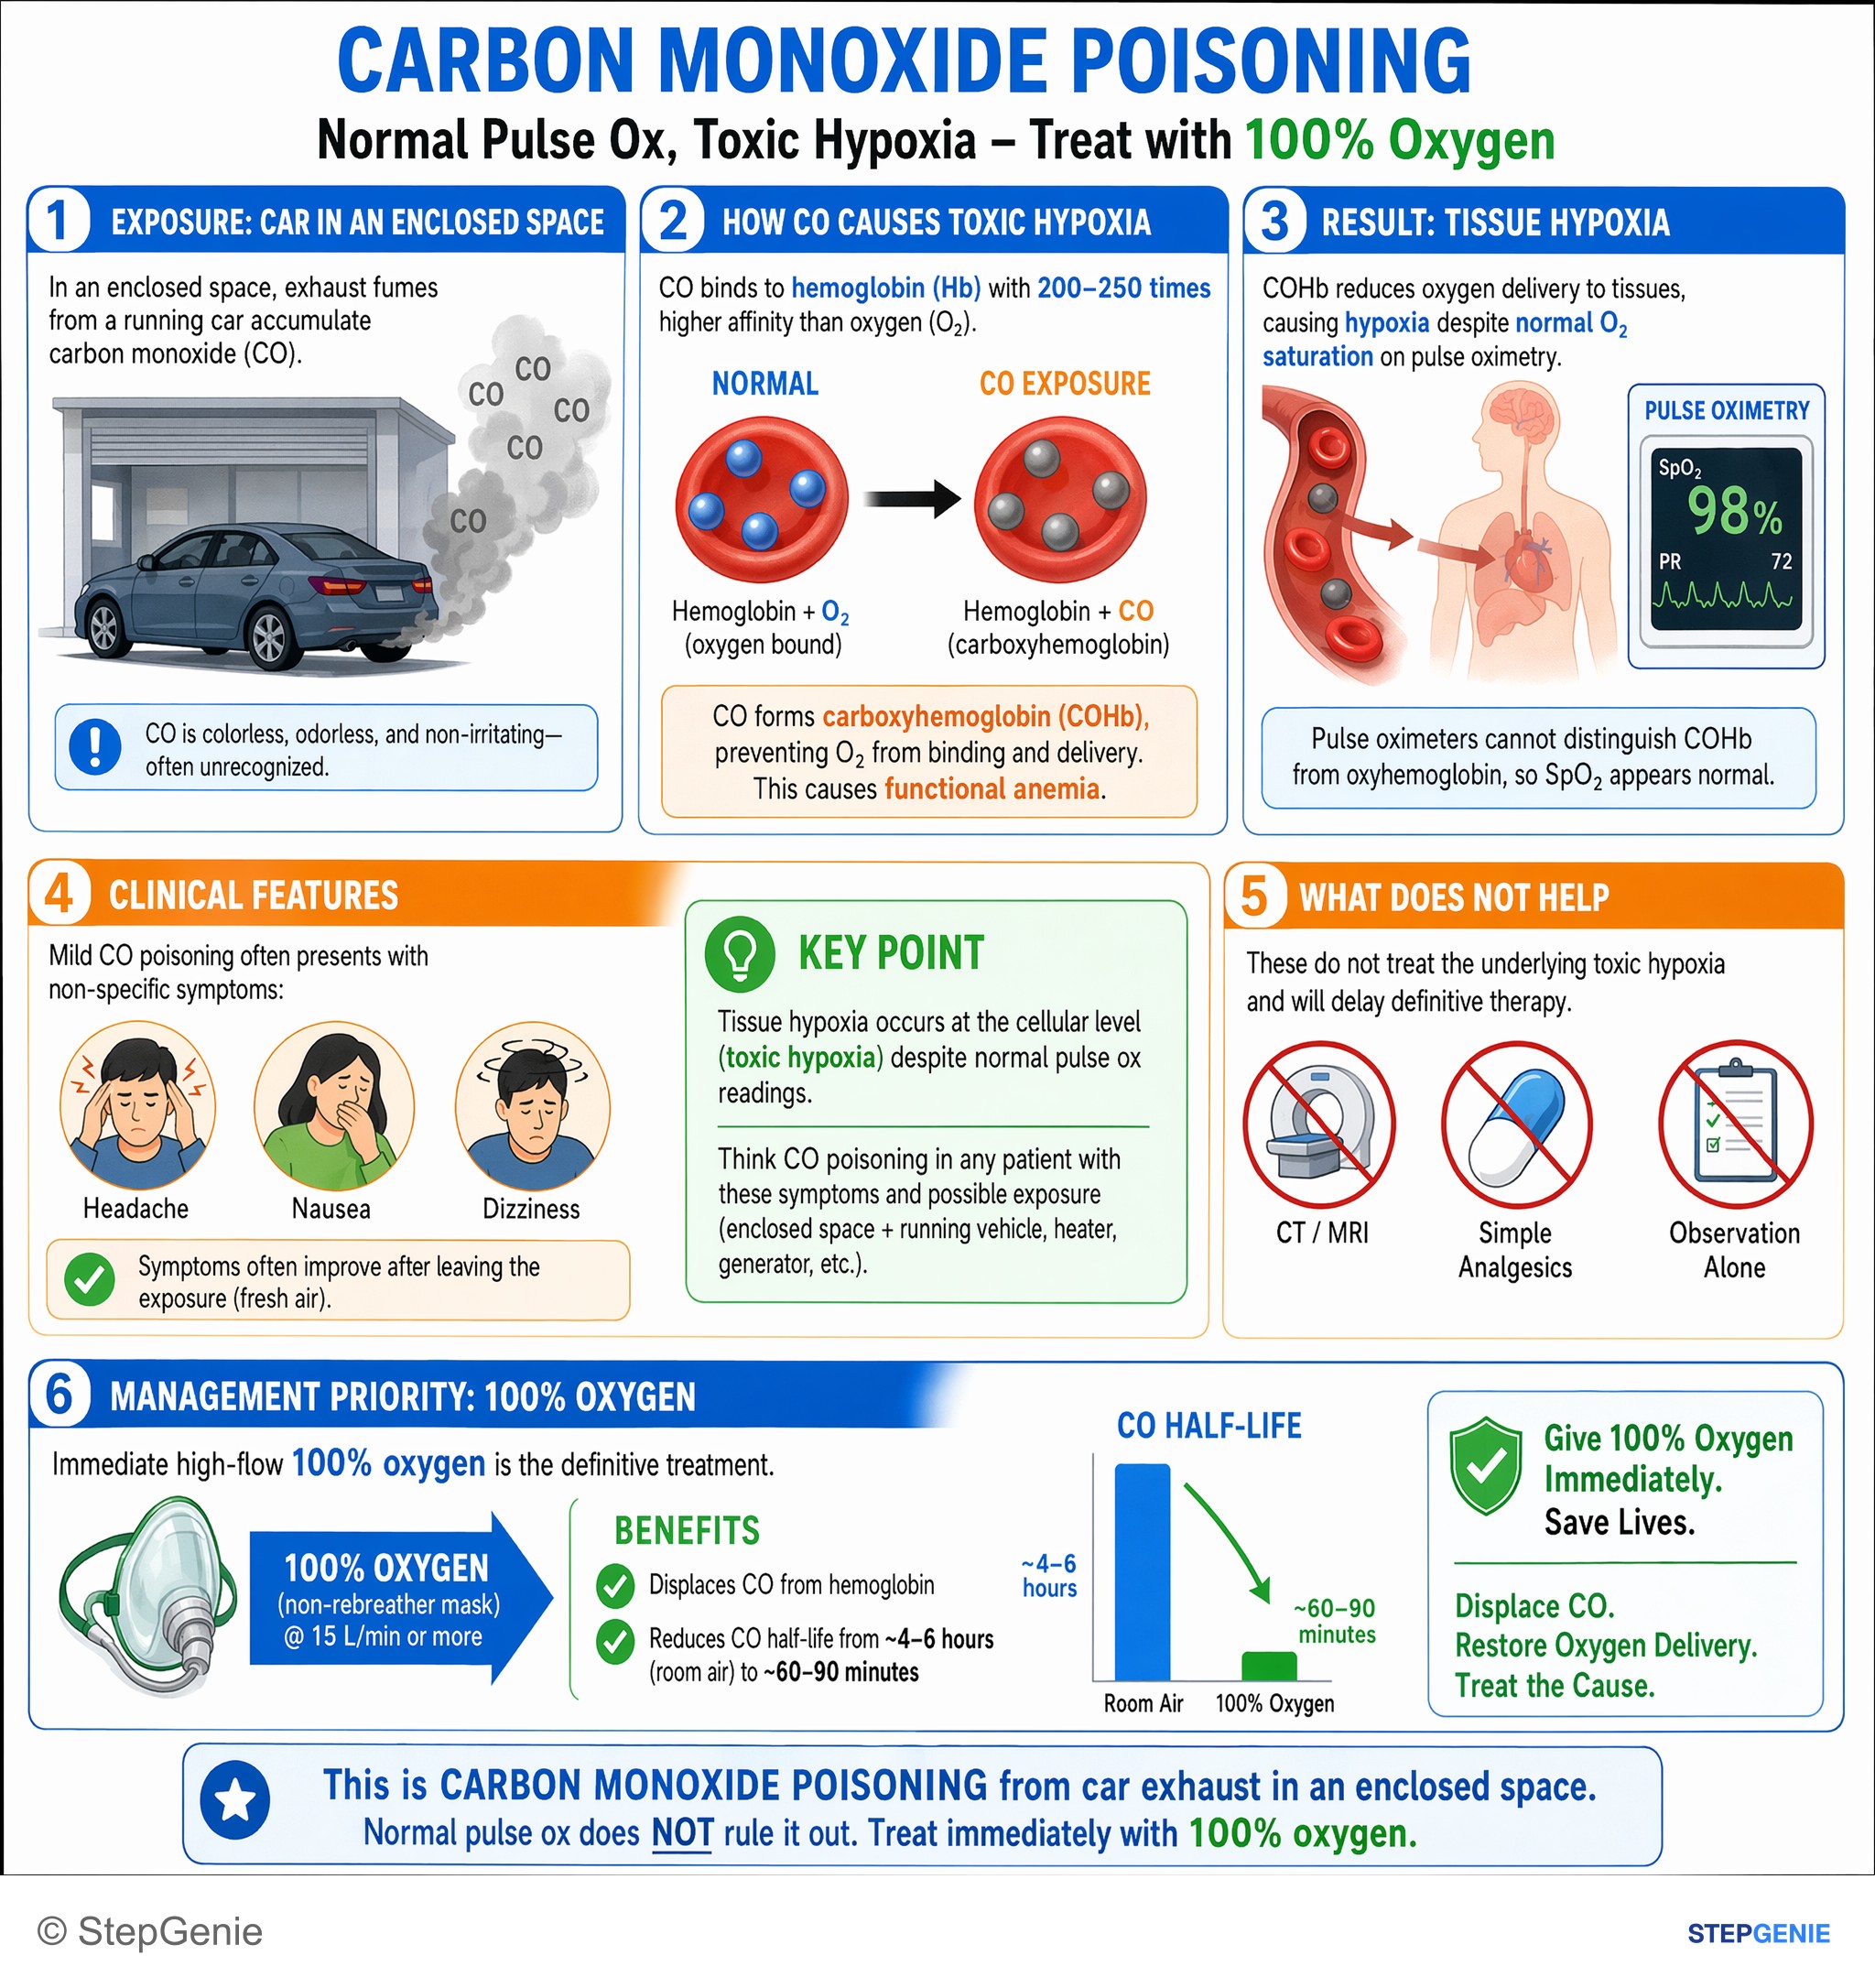
Carbon monoxide poisoning from car exhaust in enclosed space; normal pulse ox; treat immediately with 100% oxygen to displace CO from…
USMLE Step 2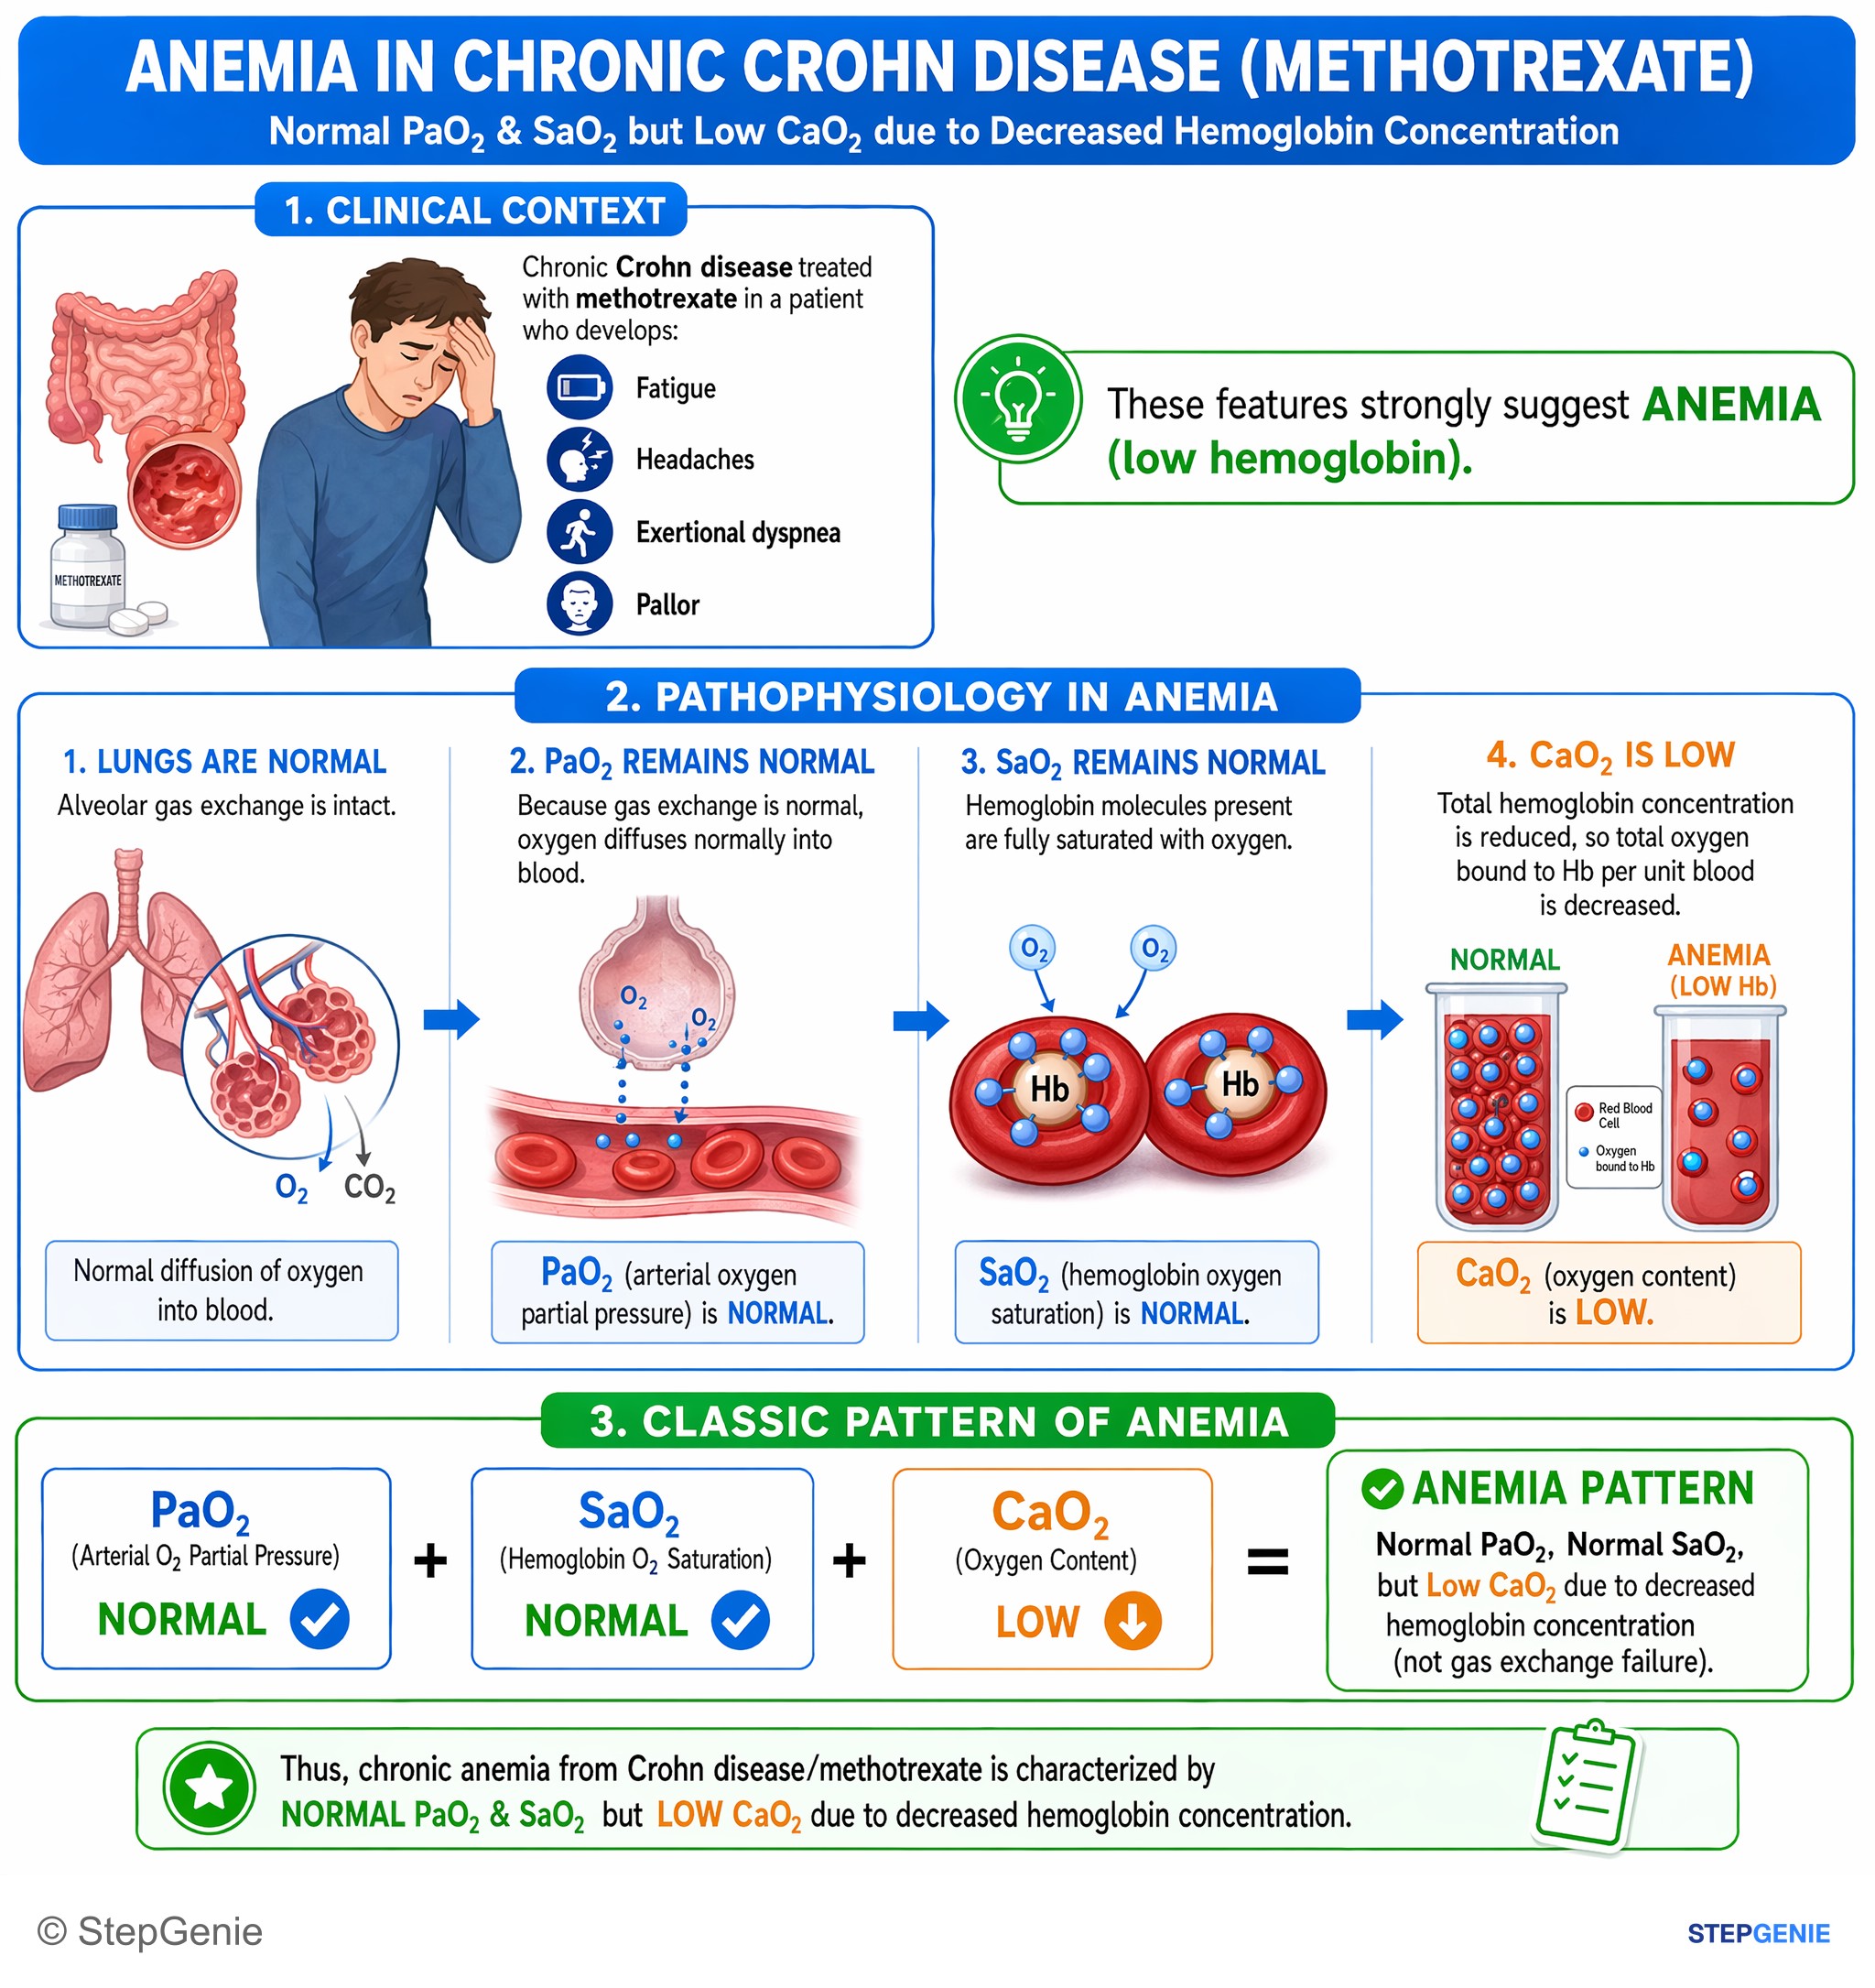
Chronic anemia from Crohn disease/methotrexate: normal PaO2 & SaO2 but low CaO2 due to decreased hemoglobin concentration.
USMLE Step 1Frequently Asked Questions
What does CADET, face Right stand for?
CADET, face Right lists the changes that shift the oxygen-hemoglobin dissociation curve to the right when they increase: CO2, Acid (hydrogen ions, lower pH), DPG (2,3-diphosphoglycerate, also called 2,3-BPG), Exercise and Temperature. Each lowers hemoglobin's oxygen affinity and raises the P50, so tissues unload more oxygen. Reverse the changes (less CO2, alkalosis, low 2,3-BPG, cold) and the curve shifts left; fetal hemoglobin, carbon monoxide and methemoglobin also shift it left.
What does the oxygen-hemoglobin dissociation curve show, and why is it sigmoid?
It plots hemoglobin oxygen saturation against the partial pressure of oxygen. The S shape comes from cooperative binding: deoxyhemoglobin sits mostly in the low-affinity tense state, and each oxygen that binds shifts the other subunits toward the high-affinity relaxed state. The flat top protects loading in the lungs, while the steep middle lets tissues take off a lot of oxygen for a small fall in PO2. Myoglobin, with one subunit, has a hyperbolic curve.
What is the difference between a left shift and a right shift of the curve?
A right shift means lower oxygen affinity: the P50 rises and hemoglobin releases oxygen more easily in tissues. More CO2, acid, 2,3-BPG, heat and exercise cause it. A left shift means higher affinity and a lower P50: hemoglobin loads oxygen well but releases it less readily. Alkalosis, low CO2, cold, low 2,3-BPG as in stored blood, fetal hemoglobin, carbon monoxide and methemoglobin shift the curve left.
What is the normal P50 of hemoglobin?
The P50 is the partial pressure of oxygen at which hemoglobin is 50 percent saturated. In adults it is about 26 to 27 mm Hg; Merck gives 27. A higher P50 signals a right shift and lower affinity, and a lower P50 a left shift and higher affinity. Fetal hemoglobin has a P50 of about 19 mm Hg, and red cells stored for weeks can have a P50 about 30 percent lower than fresh cells.
What happens to the curve in carbon monoxide poisoning?
Carbon monoxide binds hemoglobin with about 200 to 250 times the affinity of oxygen. It lowers oxygen content and shifts the curve to the left, so the oxygen still bound is released less readily. PaO2 stays normal and pulse oximetry reads normal or falsely high, so carboxyhemoglobin must be measured by co-oximetry. Everyone gets 100 percent oxygen; hyperbaric oxygen is for selected patients, such as those with loss of consciousness, severe symptoms or pregnancy.
Does high altitude shift the oxygen-hemoglobin curve to the right?
Classically, yes: hypoxia triggers hyperventilation and respiratory alkalosis, and within a few days red cell 2,3-BPG rises, which shifts the curve right when measured at standard pH. In the body, though, the alkalosis largely cancels that effect. A 2025 chamber study found the P50 at subjects' own PCO2 unchanged after 4 days at a simulated 3,500 m, and at extreme altitude on Everest the curve was left-shifted, which protects arterial saturation.