You’re cruising through a cardio pharm block and hit a question that looks like it’s about “which diuretic?”—but it’s really about mechanism, electrolytes, hemodynamics, and side effects. Loop diuretics are a USMLE staple because they show up in CHF, pulmonary edema, hypercalcemia, and drug toxicity vignettes—and the distractors are almost always “near-miss” diuretics or RAAS drugs with overlapping clinical uses.
Tag: Cardiovascular > Cardiac Pharmacology
The Clinical Vignette (Q-bank style)
A 68-year-old man with a history of systolic heart failure (HFrEF) and hypertension presents with acute shortness of breath. He is tachypneic and hypoxic. Exam shows diffuse crackles, elevated JVP, and 2+ pitting edema. Chest X-ray demonstrates pulmonary edema. He is given an IV medication that leads to rapid symptomatic improvement. Shortly afterward, labs show:
- Na⁺ 138 mEq/L
- K⁺ 2.9 mEq/L
- Cl⁻ 96 mEq/L
- HCO₃⁻ 34 mEq/L
- Mg²⁺ low
Which drug was most likely administered?
Answer choices:
A. Furosemide
B. Hydrochlorothiazide
C. Spironolactone
D. Acetazolamide
E. Mannitol
Step-by-step: Why the Correct Answer is Furosemide (A)
The clinical “tell”
This is acute decompensated heart failure with pulmonary edema. The phrase “IV medication” + “rapid symptomatic improvement” is a classic clue for IV loop diuretics.
Mechanism (must-know)
Loop diuretics (furosemide, bumetanide, torsemide, ethacrynic acid) inhibit the:
- Na⁺-K⁺-2Cl⁻ (NKCC2) cotransporter in the thick ascending limb of the loop of Henle.
This segment is water-impermeable and is a huge driver of medullary hypertonicity. Blocking NKCC2 causes powerful natriuresis/diuresis → decreased intravascular volume.
The lab pattern
Loop diuretics commonly cause:
- Hypokalemic metabolic alkalosis
- Here: K⁺ low and HCO₃⁻ high
- Hypomagnesemia
- Increased Ca²⁺ excretion (loops “lose Ca²⁺”)
The immediate hemodynamic benefit
A classic high-yield pearl: IV loop diuretics also cause venodilation (via prostaglandins) → reduced preload quickly, which helps pulmonary edema even before major diuresis kicks in.
USMLE tie-in: If they mention NSAID use blunting the effect, that’s because NSAIDs ↓ prostaglandins → ↓ loop diuretic efficacy.
High-yield Loop Diuretic Facts (memorize-friendly)
Core effects
- ↑ Na⁺, K⁺, Cl⁻, Mg²⁺ excretion
- ↑ Ca²⁺ excretion (treat hypercalcemia)
- ↑ urine output (most potent diuretics)
Indications you’ll see in vignettes
- Acute pulmonary edema (IV)
- CHF with volume overload
- Edema (cirrhosis, nephrotic syndrome)
- Hypercalcemia
- Sometimes for HTN when GFR is low (thiazides less effective)
Toxicities (the “OHH DANG” set)
| Adverse effect | Why it happens / clue |
|---|---|
| Ototoxicity | dose-related; more likely with aminoglycosides |
| Hypokalemia | increased distal Na⁺ delivery → ↑ K⁺ secretion |
| Hypomagnesemia | loss of lumen-positive potential |
| Dehydration | overdiuresis |
| Allergy (sulfa) | furosemide/bumetanide/torsemide are sulfonamides |
| Nephritis (AIN) | uncommon but tested |
Ethacrynic acid is the loop diuretic to remember when they say: “severe sulfa allergy.” (Also ototoxic.)
Now Destroy the Distractors (B–E)
B. Hydrochlorothiazide — tempting, but wrong for acute pulmonary edema
Why it might lure you: thiazides are diuretics used for hypertension and mild edema.
Why it’s wrong here:
- Thiazides are less potent and not the go-to for acute pulmonary edema.
- Mechanism: blocks Na⁺/Cl⁻ cotransporter in the distal convoluted tubule.
High-yield contrast: loops vs thiazides
- Loops: “lose Ca²⁺” (↑ Ca²⁺ excretion)
- Thiazides: “save Ca²⁺” (↓ Ca²⁺ excretion) → can cause hypercalcemia
Thiazide side effects you should recognize:
- Hyponatremia
- Hypokalemic metabolic alkalosis (yes, also!)
- HyperGLUC: HyperGlycemia, HyperLipidemia, HyperUricemia, HyperCalcemia
So if the vignette screamed recurrent calcium kidney stones and they want prevention: that’s when HCTZ becomes attractive.
C. Spironolactone — wrong timeline and wrong electrolyte direction
Why it might lure you: it’s used in HF, improves mortality, and is a “diuretic.”
Why it’s wrong here:
- Not used for rapid symptom relief in acute pulmonary edema.
- Causes hyperkalemia (this patient has hypokalemia).
- Much weaker diuresis than loops.
Mechanism:
- Aldosterone receptor antagonist in the collecting duct → ↓ ENaC and Na⁺ reabsorption → ↓ K⁺/H⁺ secretion.
USMLE HF pearl:
- Spironolactone/eplerenone are mortality-benefit drugs in HFrEF (along with ACEi/ARB/ARNI, beta blockers, SGLT2 inhibitors, hydralazine/isosorbide dinitrate in select patients).
- Tested adverse effect: gynecomastia (spironolactone); eplerenone is more selective.
D. Acetazolamide — wrong acid-base pattern
Why it might lure you: it’s a diuretic and changes bicarbonate.
Why it’s wrong here:
- Acetazolamide causes metabolic acidosis (loss of HCO₃⁻), not alkalosis.
- It’s not the go-to for pulmonary edema volume removal.
Mechanism:
- Carbonic anhydrase inhibitor in the proximal tubule → ↓ HCO₃⁻ reabsorption → alkaline urine, acidic blood.
Classic indications:
- Altitude sickness
- Glaucoma
- Idiopathic intracranial hypertension
- Metabolic alkalosis correction (sometimes)
Side effects to recall:
- NAGMA metabolic acidosis
- Hypokalemia
- Kidney stones (↑ urine pH)
- Sulfa allergy risk
E. Mannitol — would worsen pulmonary edema
Why it might lure you: osmotic diuretic, increases urine output.
Why it’s wrong here:
- Mannitol initially expands intravascular volume by pulling water into the bloodstream → can worsen pulmonary edema and CHF.
- It’s used more for reducing intracranial pressure and intraocular pressure.
Mechanism:
- Osmotic diuretic filtered at the glomerulus, not reabsorbed → holds water in the tubule.
Board-style contraindication clue:
- If the patient has CHF or pulmonary edema, mannitol is dangerous.
The “Answer Choice Matters” Takeaways (what to remember on test day)
If you see acute pulmonary edema in CHF
Think:
- IV loop diuretic (e.g., furosemide) for rapid decongestion
- Expect hypokalemic metabolic alkalosis and hypomagnesemia
If you see recurrent calcium stones
Think:
- Thiazide (↓ urinary Ca²⁺)
If you see HFrEF mortality benefit + hyperK risk
Think:
- Spironolactone/eplerenone
If you see altitude sickness / glaucoma / IIH
Think:
- Acetazolamide (metabolic acidosis)
If you see increased ICP but NOT CHF
Think:
- Mannitol (watch for pulmonary edema)
Rapid-Fire Table: Diuretics at a Glance (USMLE favorite)
| Drug class | Site | Acid-base | K⁺ effect | Signature clinical clue |
|---|---|---|---|---|
| Loop (furosemide) | Thick ascending limb (NKCC2) | Metabolic alkalosis | ↓ K⁺ | Pulmonary edema, hypercalcemia, ototoxicity |
| Thiazide (HCTZ) | DCT (Na⁺/Cl⁻) | Metabolic alkalosis | ↓ K⁺ | Hypercalcemia, gout, hyperglycemia |
| K⁺-sparing (spironolactone) | Collecting duct | Mild acidosis tendency | ↑ K⁺ | Gynecomastia, mortality benefit in HFrEF |
| CA inhibitor (acetazolamide) | PCT | Metabolic acidosis | ↓ K⁺ | Altitude sickness, glaucoma, kidney stones |
| Osmotic (mannitol) | PCT/descending limb | Variable | Variable | ↑ ICP/IOP; worsens CHF/pulm edema |
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
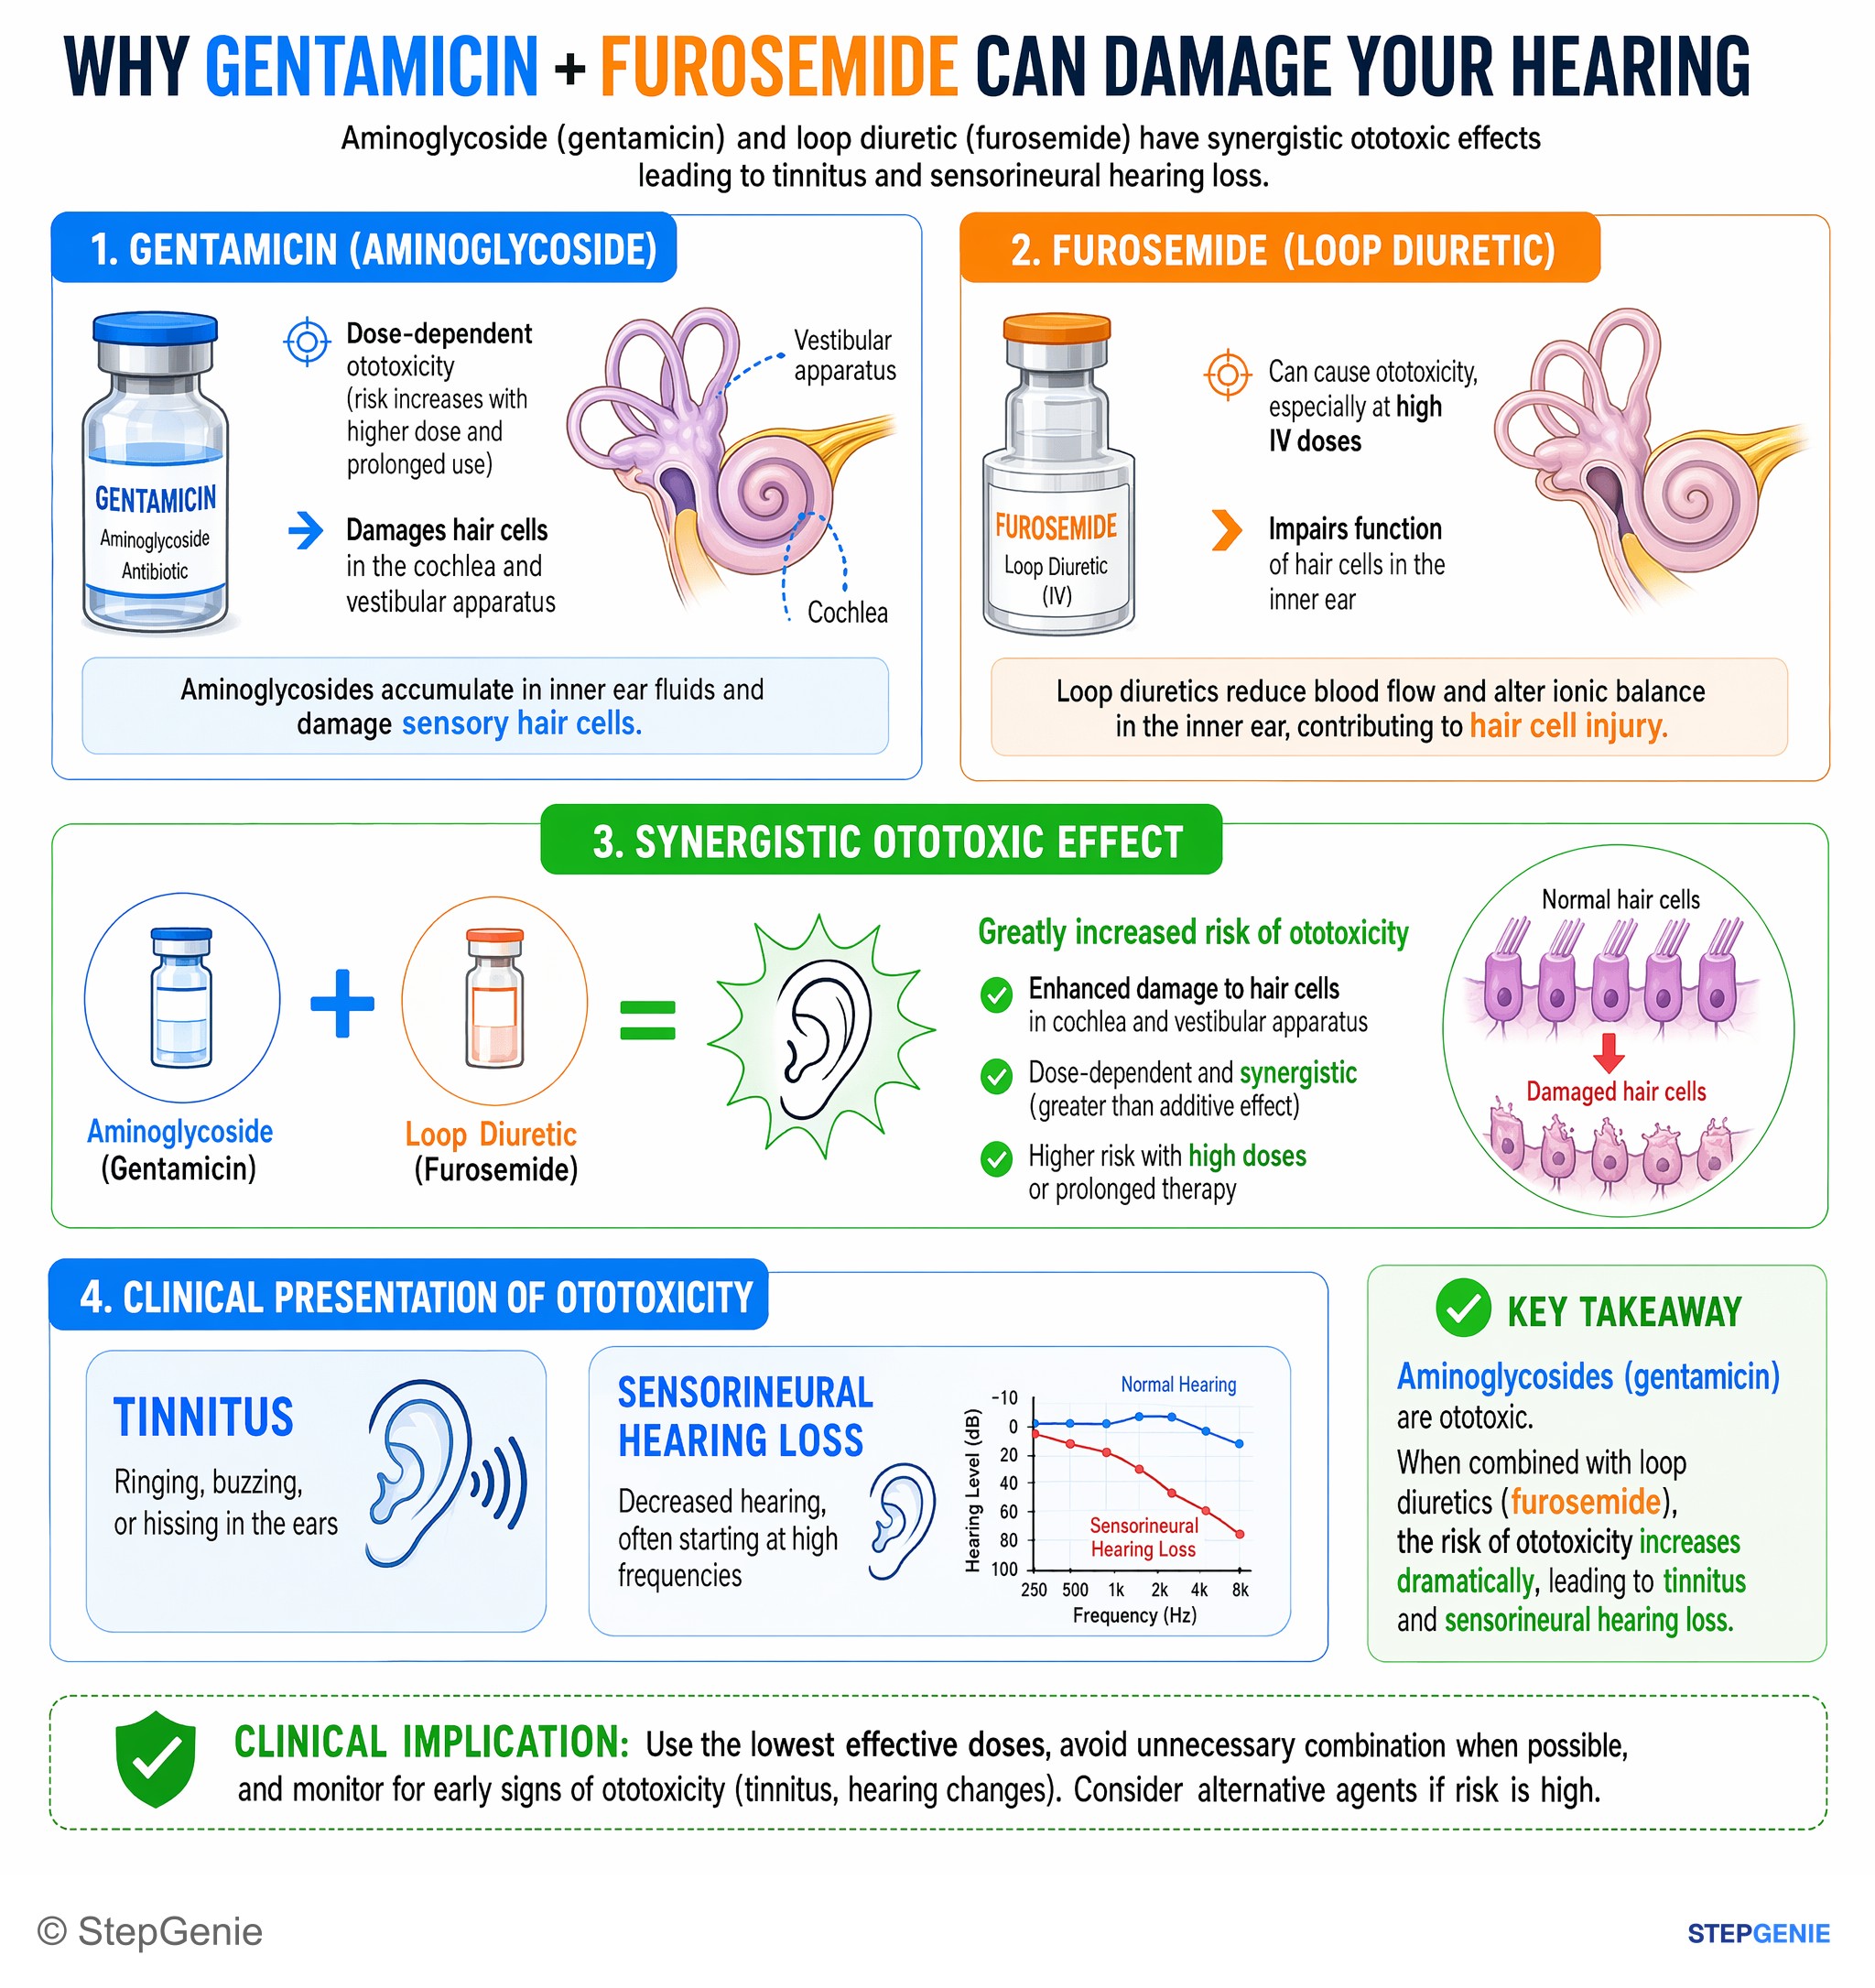
Aminoglycosides (gentamicin) are ototoxic, especially when combined with loop diuretics (furosemide), causing tinnitus and sensorineural…
USMLE Step 1Frequently Asked Questions
What diuretic is most likely given IV for rapid relief of acute pulmonary edema in HFrEF?
Furosemide is the most likely drug. In a patient with acute decompensated heart failure, pulmonary edema, diffuse crackles, elevated JVP, and rapid improvement after an IV medication, the classic choice is an IV loop diuretic. Loop diuretics are the go-to agents for acute pulmonary edema because they produce powerful diuresis and quickly reduce preload.
How do loop diuretics cause hypokalemic metabolic alkalosis and low magnesium?
Loop diuretics commonly cause hypokalemic metabolic alkalosis and hypomagnesemia. They inhibit the Na+-K+-2Cl- cotransporter in the thick ascending limb, increasing sodium delivery downstream and promoting potassium loss. They also increase magnesium excretion. In a vignette, low potassium, high bicarbonate, and low magnesium after a potent diuretic strongly point to a loop diuretic effect.
Why do IV loop diuretics improve pulmonary edema so quickly?
IV loop diuretics improve pulmonary edema quickly because they reduce preload even before full diuresis occurs. A classic high-yield point is that they cause venodilation through prostaglandins, which lowers venous return and helps relieve pulmonary congestion rapidly. This is why an IV loop can produce early symptomatic benefit in acute decompensated heart failure.
How do you tell loop diuretics from thiazides on a USMLE question?
A key distinction is calcium handling and clinical use. Loop diuretics increase calcium excretion, while thiazides decrease calcium excretion and can cause hypercalcemia. Loops are also more potent and are used for acute pulmonary edema, whereas hydrochlorothiazide is less potent and not the go-to drug for rapid relief in that setting. Both can cause hypokalemic metabolic alkalosis, so calcium clues help separate them.
Why is mannitol the wrong answer in a patient with CHF and pulmonary edema?
Mannitol is wrong because it can worsen pulmonary edema and heart failure. Although it is an osmotic diuretic that increases urine output, it initially expands intravascular volume by pulling water into the bloodstream. In a patient who already has CHF and pulmonary edema, that volume shift can aggravate congestion rather than provide the rapid relief expected from a loop diuretic.