Antiplatelet drugs prevent arterial, platelet-rich thrombi by blocking one step of platelet activation. Aspirin irreversibly inhibits platelet cyclooxygenase (COX-1), stopping thromboxane A2 (TXA2) production for the platelet's 7-10-day life; P2Y12 inhibitors block ADP signaling (clopidogrel and prasugrel are irreversible prodrugs, while ticagrelor and IV cangrelor act directly and reversibly); GP IIb/IIIa inhibitors block the final fibrinogen bridge; dipyridamole and cilostazol inhibit phosphodiesterase; and vorapaxar blocks the platelet thrombin receptor (PAR-1). In acute coronary syndrome (ACS), the default is dual antiplatelet therapy (DAPT: aspirin plus a P2Y12 inhibitor) for at least 12 months unless bleeding risk is high, with ticagrelor or prasugrel preferred over clopidogrel when PCI is done (2025 ACC/AHA). Classic exam twists: CYP2C19 poor metabolizers and omeprazole blunt clopidogrel, prasugrel is out after a stroke or TIA, ticagrelor causes dyspnea, and cilostazol is out in heart failure.
The vignette
A 59-year-old man with hypertension and hyperlipidemia has 45 minutes of substernal chest pressure radiating to his left arm. ECG shows new horizontal ST depression in V4-V6, and his high-sensitivity troponin is rising. He has asthma and nasal polyps, and 2 years ago he needed intubation for bronchospasm that began an hour after he took ibuprofen. A heparin infusion and a high-intensity statin are started, and coronary angiography is planned. Which drug should he receive now to inhibit his platelets?
A. Aspirin B. Clopidogrel C. Warfarin D. Eptifibatide E. Dipyridamole F. Cilostazol
Answer: B, clopidogrel, and why every choice matters
ST depression with a rising troponin is an NSTEMI, which normally gets DAPT. But asthma + nasal polyps + severe bronchospasm after an NSAID is AERD (Samter triad), a reaction to COX-1-inhibiting drugs, so aspirin can't simply be given. A P2Y12 inhibitor still blocks ADP-driven platelet activation, and the 2025 ACC/AHA ACS guideline recommends one for every ACS patient, with a loading dose as early as possible when aspirin can't be taken at presentation.
Current-guideline footnote: for patients who report aspirin hypersensitivity, the same guideline prefers aspirin desensitization whenever possible, so DAPT can still be used, and it prefers ticagrelor or prasugrel over clopidogrel when PCI is done. Clopidogrel is the only P2Y12 inhibitor offered here, and it is the classic exam answer for "aspirin can't be used."
- A. Aspirin: first-line in every ACS (162-325 mg chewed, non-enteric-coated, then 75-100 mg daily), but in AERD a dose can trigger life-threatening bronchospasm. Supervised desensitization is the route back to daily aspirin, not an untested dose in the emergency department.
- C. Warfarin: an anticoagulant (vitamin K antagonist), not an antiplatelet; it has no role in treating an acute ACS, and he is already anticoagulated with heparin. See the anticoagulants breakdown.
- D. Eptifibatide: a GP IIb/IIIa inhibitor. The 2025 guideline says these drugs should not be given routinely in ACS (no ischemic benefit, more bleeding); they are reasonable only during PCI with a large thrombus burden, no-reflow or slow flow.
- E. Dipyridamole: a phosphodiesterase inhibitor that raises adenosine; it is used with aspirin to prevent recurrent stroke and IV for stress testing, where it can provoke coronary steal. No ACS role.
- F. Cilostazol: a PDE3 inhibitor for intermittent claudication; no ACS role, and contraindicated in heart failure of any severity.
Where each drug hits the platelet
- Adhesion: after vessel injury, von Willebrand factor anchors to exposed collagen and binds platelet GP Ib/IX.
- Activation: COX turns arachidonic acid into TXA2 (blocked by aspirin); released ADP acts on P2Y12 receptors (blocked by clopidogrel, prasugrel, ticagrelor, cangrelor); thrombin acts on PAR-1 (blocked by vorapaxar). Raising platelet cAMP damps activation (dipyridamole, cilostazol).
- Aggregation: fibrinogen links GP IIb/IIIa receptors on neighboring platelets, the final common pathway (blocked by eptifibatide and tirofiban).
Drill the steps with the platelet plug mnemonic.
Antiplatelet mechanism table
| Drug | Target | Binding | Main uses | Key adverse effects and cautions |
|---|---|---|---|---|
| Aspirin | COX-1 → no TXA2 | Irreversible | ACS; secondary prevention after MI, stroke or TIA | GI bleeding; AERD; Reye syndrome in children with viral illness; tinnitus in overdose |
| Clopidogrel | P2Y12 | Irreversible; prodrug (CYP2C19) | ACS (with fibrinolysis, or if ticagrelor/prasugrel can't be used); recent MI, stroke, PAD | Bleeding; poor effect in CYP2C19 poor metabolizers; omeprazole interaction; TTP has been reported |
| Prasugrel | P2Y12 | Irreversible; prodrug (mainly CYP3A4, CYP2B6) | ACS managed with PCI | Bleeding; contraindicated after stroke or TIA |
| Ticagrelor | P2Y12 | Reversible; direct-acting | ACS or prior MI; minor stroke or high-risk TIA | Dyspnea; bleeding; ventricular pauses; contraindicated after intracranial hemorrhage |
| Cangrelor | P2Y12 | Reversible; IV | PCI in P2Y12-naive patients | Bleeding; effect gone within about an hour |
| Eptifibatide, tirofiban | GP IIb/IIIa | Reversible; IV | During PCI for large thrombus, no-reflow or slow flow (not routine) | Bleeding; acute profound thrombocytopenia |
| Dipyridamole | PDE; adenosine uptake | Reversible | With aspirin after stroke or TIA; IV stress testing | Headache; coronary steal |
| Cilostazol | PDE3 | Reversible | Intermittent claudication | Contraindicated in heart failure; headache, diarrhea, palpitations |
| Vorapaxar | PAR-1 | Reversible, but half-life about 8 days | Prior MI or PAD, added to aspirin and/or clopidogrel | Contraindicated after stroke, TIA or intracranial hemorrhage |
Aspirin: what gets tested
- AERD (Samter triad): asthma, chronic rhinosinusitis with nasal polyps and reactions to aspirin and other COX-1-inhibiting NSAIDs, from dysregulated arachidonic acid metabolism. NSAIDs trigger attacks in about 9% of all people with asthma and up to 30% of those with nasal polyps. For pain, acetaminophen or a COX-2-selective drug such as celecoxib can be used; desensitization lets patients take daily aspirin.
- Reye syndrome: acute encephalopathy with fatty liver in people under 18; aspirin during a viral illness such as influenza or varicella raises the risk up to 20-fold. Kawasaki disease is the classic pediatric exception.
- Overdose: tinnitus, nausea, vomiting and hyperventilation; respiratory alkalosis first, then metabolic acidosis.
P2Y12 inhibitors side by side
| Clopidogrel | Prasugrel | Ticagrelor | Cangrelor | |
|---|---|---|---|---|
| Route | Oral, daily | Oral, daily | Oral, twice daily | IV; half-life 3-6 minutes |
| Stop before surgery | 5 days | At least 7 days | 5 days | Platelet function back within 1 hour |
| Signature warning | Boxed: reduced effect in CYP2C19 poor metabolizers (two nonfunctional alleles); consider another P2Y12 inhibitor | Boxed: bleeding; never after stroke or TIA; generally not at age ≥75 (unless diabetes or prior MI); not before urgent CABG; weight <60 kg adds bleeding risk | Dyspnea (14-21% in trials); ventricular pauses; aspirin 75-100 mg daily; avoid strong CYP3A inhibitors and inducers | Clopidogrel or prasugrel given during the infusion won't work until the next dose; give them after it stops (ticagrelor can be given during) |
- Prasugrel 5 mg: the label suggests this maintenance dose below 60 kg; the 2025 ACS guideline also allows it, with caution, at 75 or older.
- Clopidogrel and PPIs: avoid omeprazole and esomeprazole, which significantly reduce clopidogrel's antiplatelet activity; dexlansoprazole, lansoprazole and pantoprazole affect it less (PPIs, CYP450 inhibitors).
- Other clopidogrel facts: opioids delay and reduce its absorption; TTP, sometimes fatal and sometimes after less than 2 weeks of use, needs urgent plasma exchange (TTP vs HUS).
- Ticagrelor's boxed warning is bleeding: don't start it before urgent CABG, and if possible manage bleeding without stopping it, because stopping raises the risk of cardiovascular events.
GP IIb/IIIa, PDE inhibitors and vorapaxar
- GP IIb/IIIa inhibitors (eptifibatide, tirofiban): IV, reversible; stop fibrinogen and von Willebrand factor from binding the receptor; PCI bailout only (see choice D). Stop eptifibatide and heparin for acute profound thrombocytopenia; eptifibatide is contraindicated in dialysis-dependent patients. Abciximab, the classic exam name, has no current US label on DailyMed.
- Dipyridamole: blocks adenosine uptake and inhibits PDE, raising platelet cAMP and cGMP. Given as aspirin 25 mg/extended-release dipyridamole 200 mg twice daily after stroke or TIA; headache is common. That aspirin dose may be inadequate for cardiac indications.
- Cilostazol: PDE3 inhibitor; more cAMP in platelets and vessels means less aggregation plus vasodilation, which lengthens walking distance in claudication (response in 2-4 weeks, up to 12). Boxed warning: contraindicated in heart failure of any severity, because PDE3 inhibitors reduced survival in class III-IV heart failure. Dose: 100 mg twice daily on an empty stomach; 50 mg twice daily with strong or moderate CYP3A4 inhibitors or with CYP2C19 inhibitors.
- Vorapaxar: reversible PAR-1 antagonist whose 8-day half-life makes it effectively irreversible. Contraindicated with prior stroke, TIA or intracranial hemorrhage; avoid with warfarin or other anticoagulants.
Who gets which antiplatelet
| Setting | Plan (USMLE level) |
|---|---|
| ACS treated with PCI | Aspirin + ticagrelor or prasugrel; clopidogrel if they are unavailable, not tolerated or contraindicated |
| STEMI treated with fibrinolysis | Aspirin + clopidogrel, given with the fibrinolytic |
| After ACS | DAPT for ≥12 months unless bleeding risk is high; to cut bleeding, switch to ticagrelor alone ≥1 month after PCI (if tolerating ticagrelor DAPT), or consider de-escalating to clopidogrel after 1 month |
| Also needs an oral anticoagulant (e.g., AF) | Stop aspirin 1-4 weeks after PCI; continue the anticoagulant + a P2Y12 inhibitor, preferably clopidogrel |
| Minor (non-disabling) ischemic stroke or high-risk TIA | Short-term DAPT (the 2026 AHA/ASA guideline prefers it to thrombolysis for non-disabling deficits): aspirin + clopidogrel within 24 hours for 21 days (Merck), or aspirin + ticagrelor up to 30 days if NIHSS ≤5 or high-risk TIA (label); then one agent |
| Long term after noncardioembolic stroke or TIA | Aspirin, clopidogrel, or aspirin-extended-release dipyridamole; no long-term DAPT |
| Symptomatic PAD | Aspirin or clopidogrel; cilostazol for claudication (unless heart failure) |
Atrial fibrillation-related stroke needs anticoagulation, not antiplatelets. For the full ACS pathway, see STEMI vs NSTEMI management.
DAPT, bleeding and the PPI question
- Bleeding, sometimes fatal, is the main serious risk of every antiplatelet, and combining two raises it.
- The 2025 ACS guideline recommends a PPI for patients on antiplatelet therapy who are at risk of GI bleeding; with clopidogrel, choose pantoprazole over omeprazole or esomeprazole.
How USMLE tests it
| Stem clue | Answer |
|---|---|
| Stent thrombosis on clopidogrel; genotype shows two loss-of-function CYP2C19 alleles | Switch to another P2Y12 inhibitor (prasugrel or ticagrelor) |
| Clopidogrel started alongside omeprazole | Less active metabolite; use pantoprazole |
| ACS + prior stroke or TIA | Avoid prasugrel |
| Mild new dyspnea after starting DAPT for ACS, normal exam | Ticagrelor (usually mild to moderate; often resolves on continued treatment) |
| Anemia with schistocytes, low platelets and confusion soon after starting clopidogrel | TTP: urgent plasma exchange |
| Claudication in a patient with heart failure | Cilostazol is contraindicated |
| Wheezing after aspirin in a patient with nasal polyps | AERD: COX-1 inhibition |
Key takeaways
- Aspirin: irreversible COX-1 → no TXA2; first-line in ACS unless AERD or true allergy (then desensitize if possible, and load the P2Y12 inhibitor early).
- P2Y12 inhibitors: clopidogrel and prasugrel are irreversible prodrugs; ticagrelor is reversible, direct-acting and twice daily; cangrelor is IV with offset in about an hour.
- Clopidogrel traps: CYP2C19 poor metabolizers (boxed warning), omeprazole/esomeprazole, TTP.
- Prasugrel: never after stroke or TIA; generally avoided at 75 or older (5 mg with caution if used). Ticagrelor: dyspnea, aspirin ≤100 mg, contraindicated after intracranial hemorrhage.
- GP IIb/IIIa inhibitors are PCI bailout drugs, not routine; watch for thrombocytopenia.
- Cilostazol treats claudication but is contraindicated in heart failure; vorapaxar is contraindicated after stroke, TIA or intracranial hemorrhage.
- ACS: DAPT ≥12 months by default; prasugrel or ticagrelor with PCI, clopidogrel with fibrinolysis; PPI if GI bleeding risk.
Sources
- 2025 ACC/AHA/ACEP/NAEMSP/SCAI Guideline for the Management of Patients With Acute Coronary Syndromes — JACC (2025)
- Plavix (clopidogrel) tablets: prescribing information — DailyMed, NLM (2025)
- Effient (prasugrel) tablets: prescribing information — DailyMed, NLM (2022)
- Brilinta (ticagrelor) tablets: prescribing information — DailyMed, NLM (2026)
- Kengreal (cangrelor) for injection: prescribing information — DailyMed, NLM (2025)
- Cilostazol tablets: prescribing information — DailyMed, NLM (2022)
- Zontivity (vorapaxar) tablets: prescribing information — DailyMed, NLM (2022)
- Eptifibatide injection: prescribing information — DailyMed, NLM (2024)
- Aspirin and extended-release dipyridamole capsules: prescribing information — DailyMed, NLM (2021)
- Asthma (aspirin-exacerbated respiratory disease) — Merck Manual Professional Edition (2025)
- Ischemic Stroke — Merck Manual Professional Edition (2026)
- Top Things to Know: 2026 Guideline for the Early Management of Patients With Acute Ischemic Stroke — American Heart Association (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
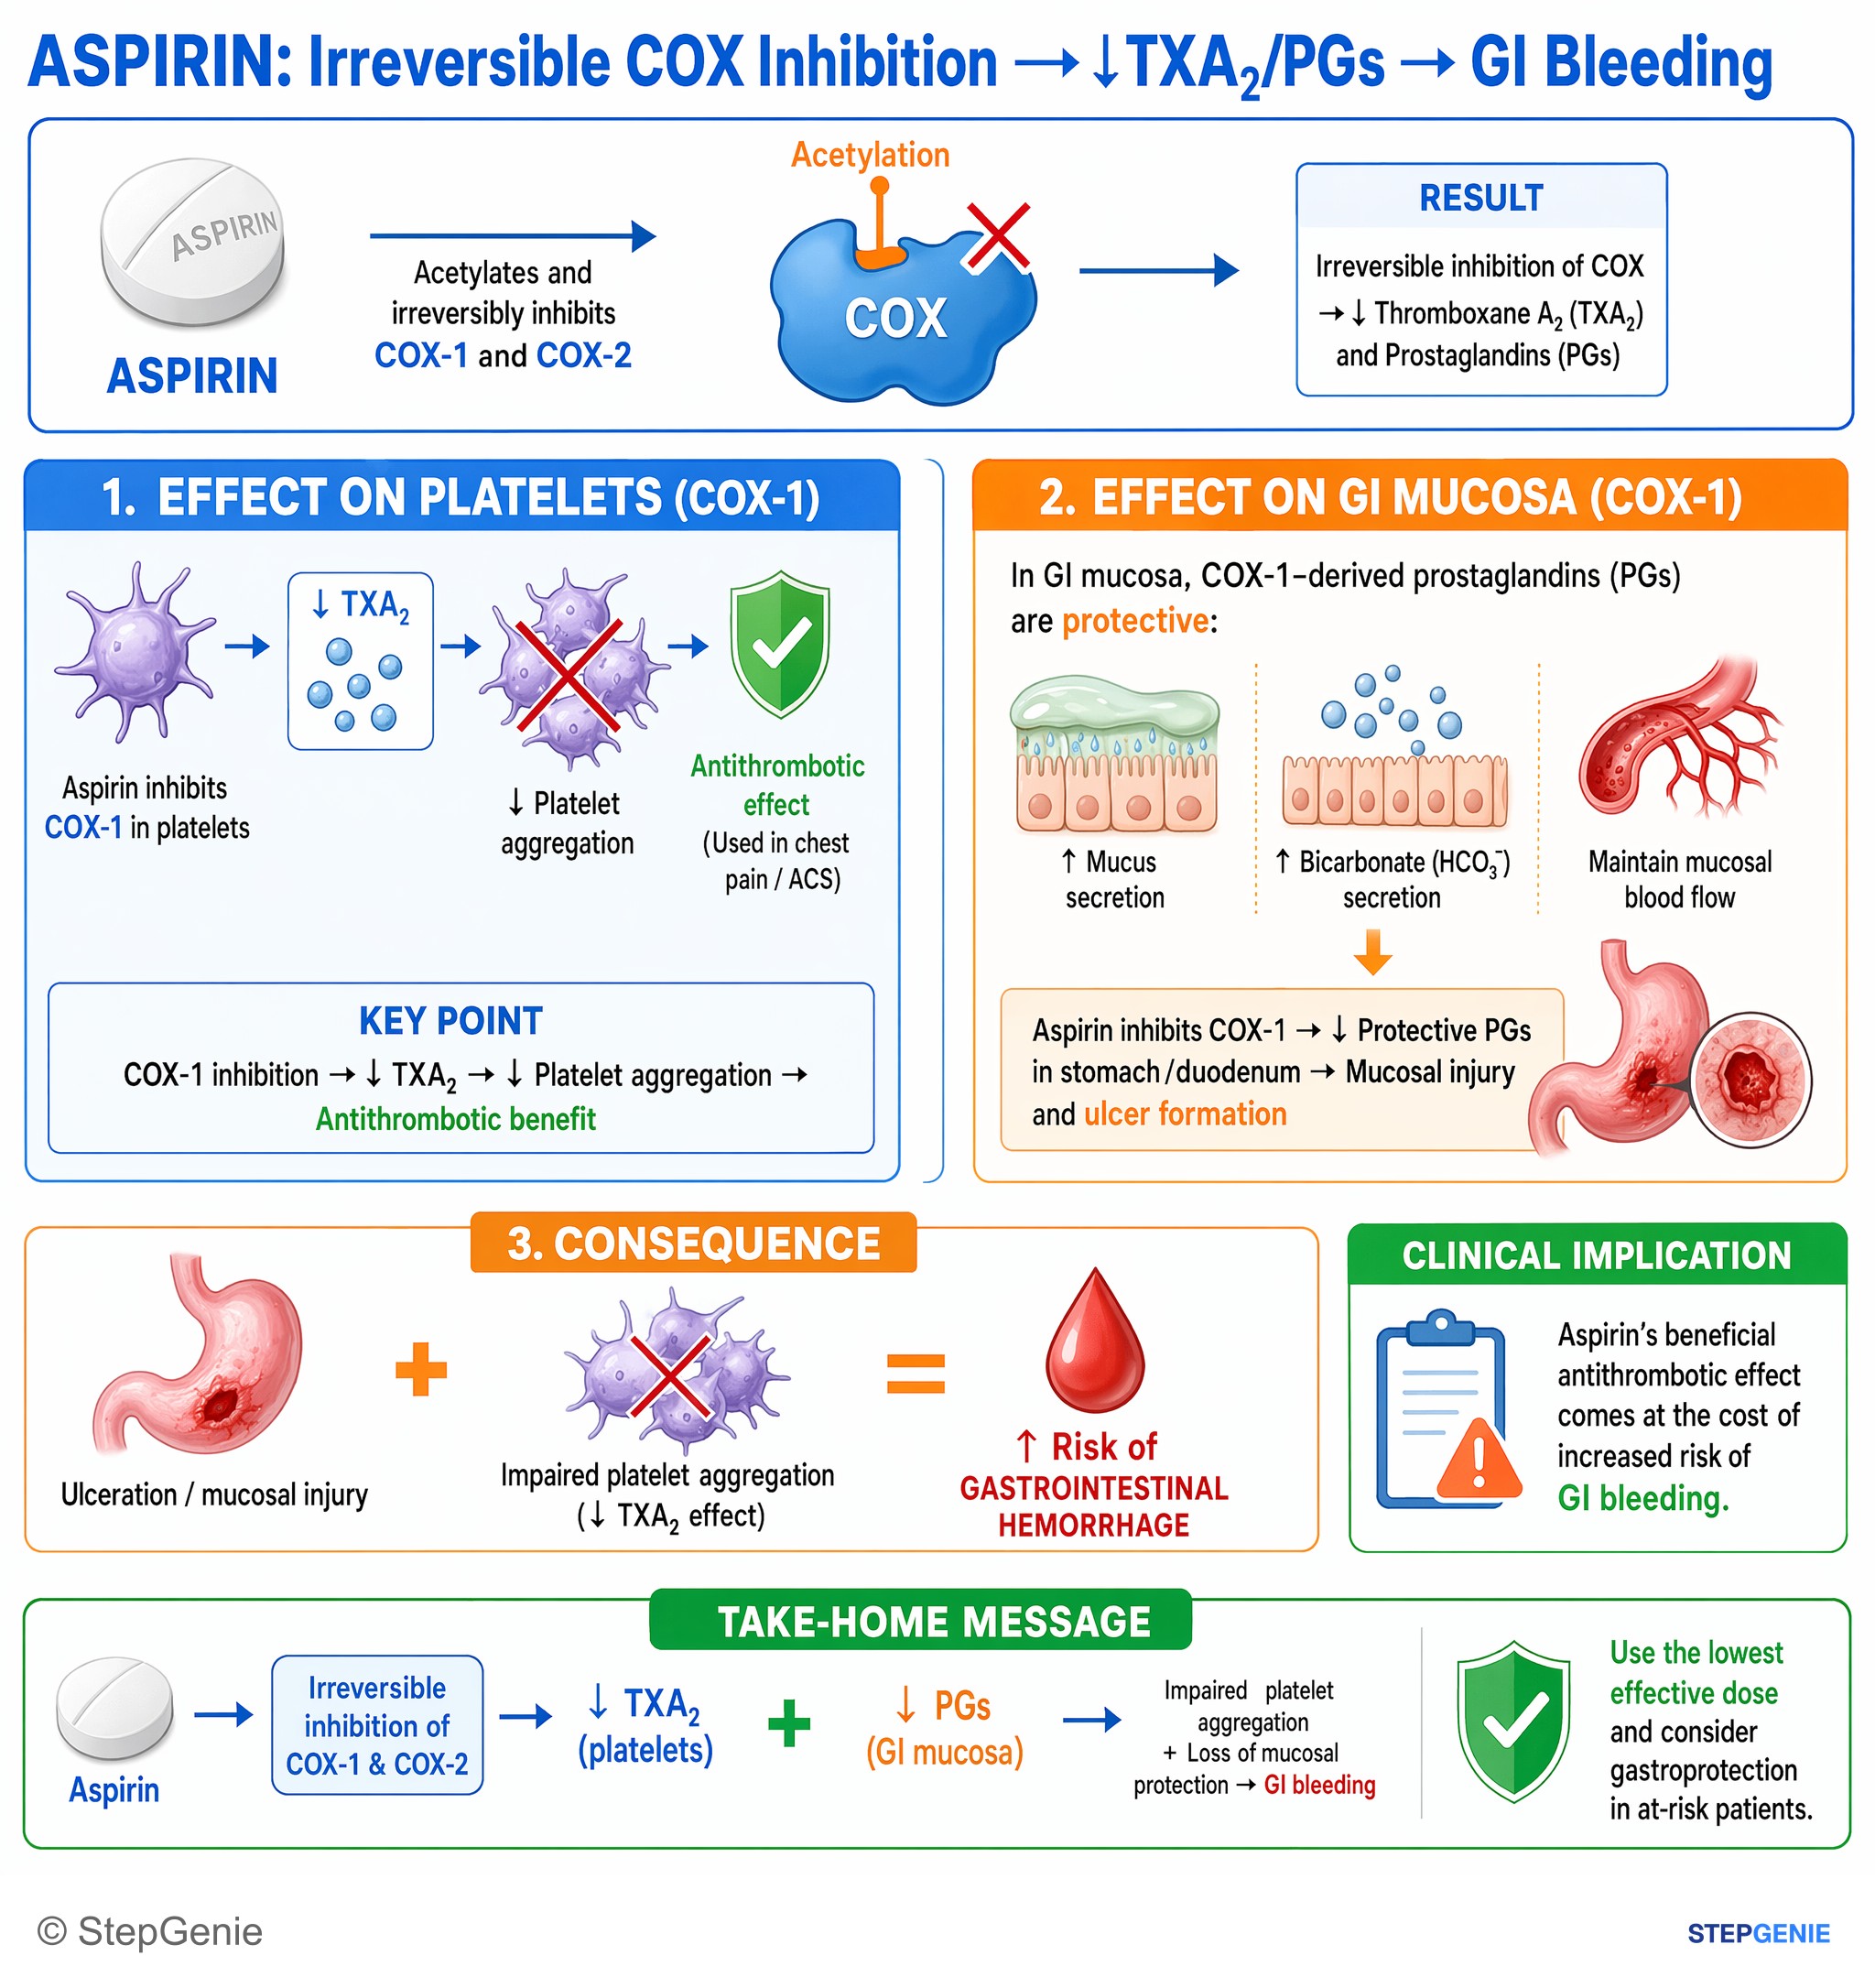
Aspirin irreversibly inhibits COX → ↓TXA2/PGs, impairing platelet aggregation and mucosal protection, causing GI bleeding as a key adverse…
USMLE Step 1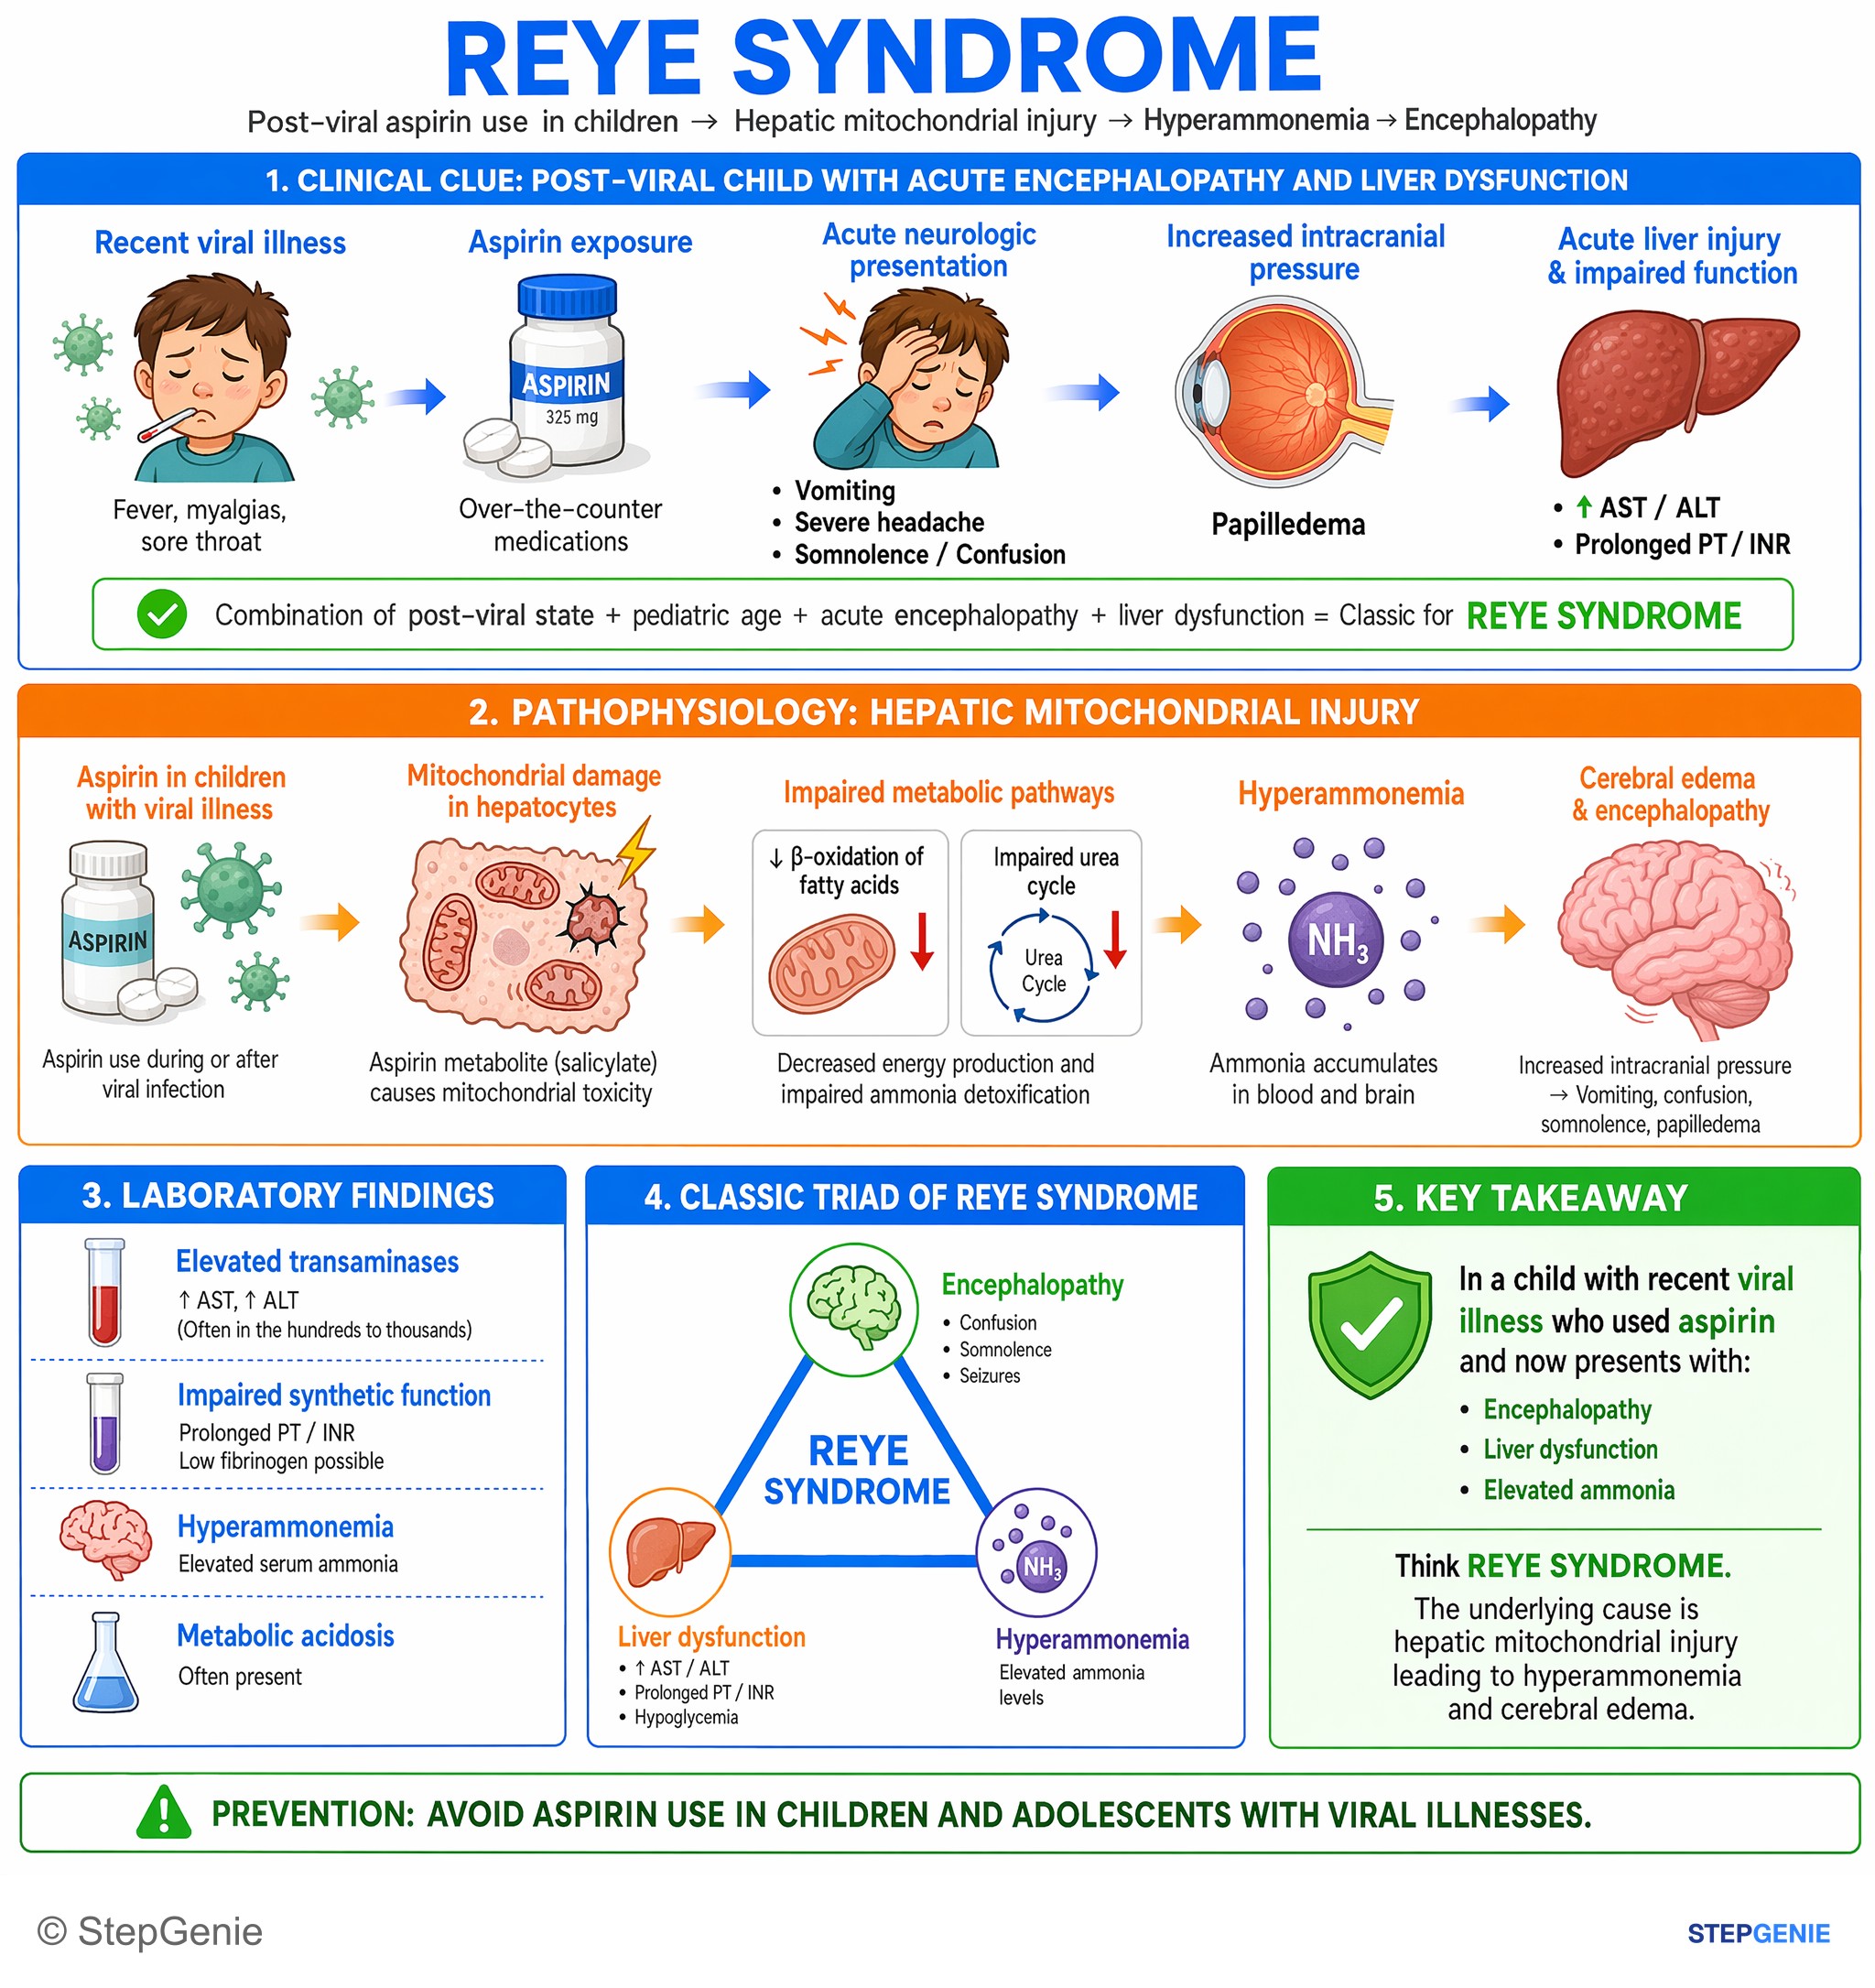
Reye syndrome: post-viral aspirin use → hepatic mitochondrial dysfunction → hyperammonemia, elevated transaminases, encephalopathy…
USMLE Step 1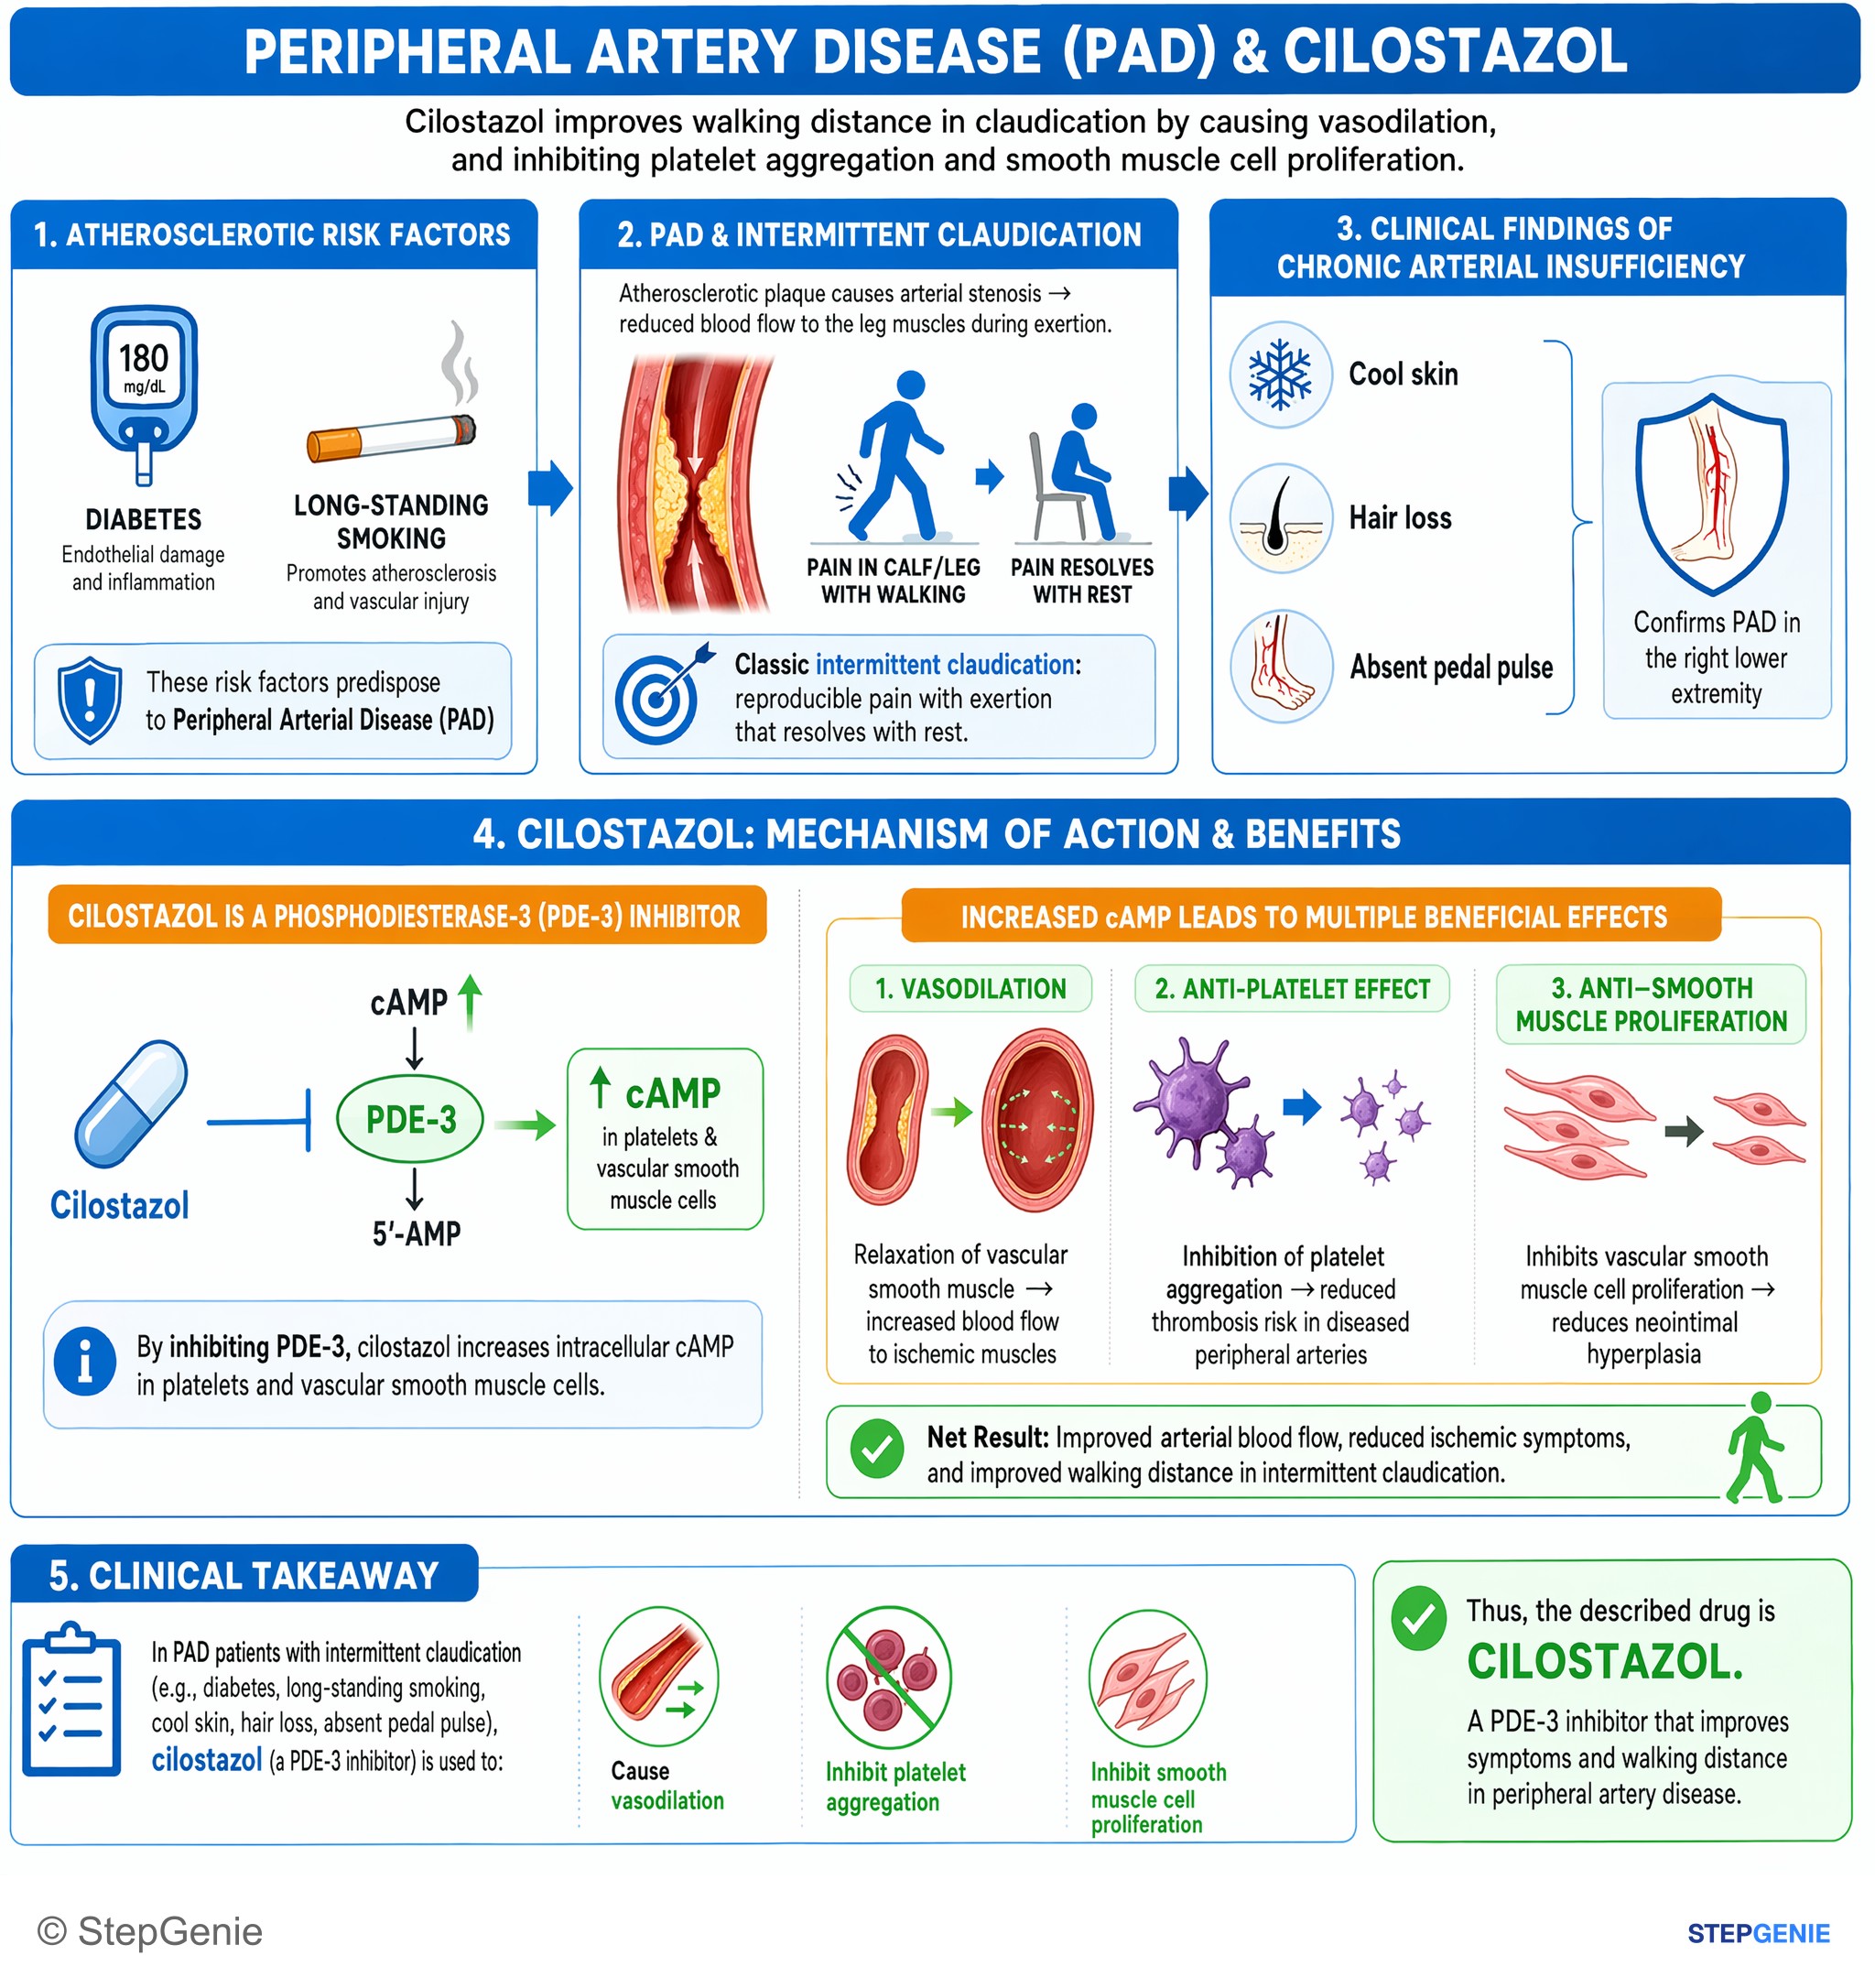
Peripheral artery disease causing claudication is treated with cilostazol, a PDE-3 inhibitor that causes vasodilation and inhibits…
USMLE Step 1Frequently Asked Questions
What is the difference between aspirin and clopidogrel?
Aspirin irreversibly inhibits platelet cyclooxygenase (COX-1), so platelets stop making thromboxane A2. Clopidogrel is a prodrug, activated mainly by CYP2C19, whose active metabolite irreversibly blocks the platelet P2Y12 ADP receptor. Both effects last for the rest of the platelet's life, about 7 to 10 days. They are combined as dual antiplatelet therapy after acute coronary syndrome and stenting, and clopidogrel can be used alone when aspirin cannot be tolerated.
Which antiplatelet drugs are reversible?
Ticagrelor (oral, twice daily) and cangrelor (IV, with platelet function back within about an hour) block the P2Y12 receptor reversibly. Eptifibatide and tirofiban reversibly block GP IIb/IIIa, and dipyridamole and cilostazol are reversible phosphodiesterase inhibitors. Aspirin, clopidogrel and prasugrel are irreversible, so their effect lasts for the platelet's lifespan. Vorapaxar binds reversibly, but its half-life of about 8 days makes it effectively irreversible.
Why is prasugrel contraindicated after a stroke or TIA?
In patients with a history of stroke or transient ischemic attack, prasugrel led to worse net clinical outcomes, including more strokes and intracranial hemorrhages than clopidogrel, so the label lists prior stroke or TIA as a contraindication and the 2025 ACC/AHA guideline says it should not be given. The label also advises against it at age 75 or older unless the patient has diabetes or a prior MI and suggests 5 mg below 60 kg; the guideline allows a cautious 5 mg dose at 75 or older. Stop it at least 7 days before surgery.
Why should omeprazole be avoided with clopidogrel?
Clopidogrel must be converted to its active metabolite, principally by CYP2C19. Omeprazole and esomeprazole inhibit CYP2C19 and significantly reduce clopidogrel's antiplatelet activity, so the label says to avoid them. When a proton pump inhibitor is needed, as it is for patients at risk of GI bleeding on antiplatelet therapy, pantoprazole, lansoprazole or dexlansoprazole affect clopidogrel less. The same pathway explains the boxed warning for CYP2C19 poor metabolizers.
How long is dual antiplatelet therapy given after an acute coronary syndrome?
The 2025 ACC/AHA guideline makes at least 12 months of aspirin plus a P2Y12 inhibitor the default after an acute coronary syndrome for patients not at high bleeding risk, with ticagrelor or prasugrel preferred over clopidogrel when PCI is done. To lower bleeding, patients tolerating ticagrelor-based therapy can switch to ticagrelor alone 1 month or more after PCI, and de-escalation to clopidogrel after 1 month may be reasonable. Patients who also need an oral anticoagulant stop aspirin 1 to 4 weeks after PCI and keep a P2Y12 inhibitor, preferably clopidogrel.
What are the main side effects of ticagrelor?
Bleeding is the boxed warning, and ticagrelor is contraindicated after intracranial hemorrhage or with active bleeding. Dyspnea occurred in 14 to 21 percent of trial patients and is usually mild to moderate. Ventricular pauses and central sleep apnea have also been reported. It is given with aspirin no higher than 100 mg daily, because higher aspirin doses appear to reduce its effectiveness, and strong CYP3A inhibitors or inducers should be avoided.