You’re cruising through a Q-bank when a familiar anticoagulant vignette pops up—and suddenly every option looks kind of right. The trick isn’t just knowing what heparin, warfarin, and DOACs do; it’s recognizing what the question is actually testing (onset, monitoring, antidotes, pregnancy, renal clearance, bridging, and key contraindications). Let’s walk through a classic scenario the way Step questions want you to think: pick the best answer and actively eliminate every distractor.
Tag: Cardiovascular > Cardiac Pharmacology
The Vignette (Q-bank style)
A 72-year-old man with hypertension and nonvalvular atrial fibrillation is started on an anticoagulant to reduce his stroke risk. He has stage 4 chronic kidney disease (eGFR 22 mL/min/1.73 m²). Two weeks later he presents with a gastrointestinal bleed. His medication list includes metoprolol and the new anticoagulant. The team wants an agent with predictable anticoagulation that is safe in severe CKD and has a reliable reversal strategy.
Which medication was most appropriate to start initially?
A. Apixaban
B. Dabigatran
C. Enoxaparin
D. Rivaroxaban
E. Warfarin
Stepwise Approach: What are they testing?
The question is not “what treats Afib?”—it’s testing:
- Nonvalvular Afib anticoag options
- Renal clearance differences among DOACs
- When warfarin is preferred
- Reversal agents and predictability/monitoring
- LMWH pitfalls in renal failure
Correct Answer: E. Warfarin
Why warfarin wins here
In severe CKD (eGFR ~22), many DOACs become risky due to accumulation and bleeding. While apixaban is sometimes used in CKD with dose adjustment, classic USMLE logic is:
- Warfarin is preferred when:
- Severe renal impairment (especially when DOAC dosing is uncertain or contraindicated)
- Mechanical heart valves (DOACs are not indicated)
- Moderate-to-severe mitral stenosis (“valvular Afib”)
- Need for measurable anticoagulation effect (INR) and well-established reversal
High-yield warfarin facts (the stuff they love to test)
- MOA: inhibits vitamin K epoxide reductase ↓ γ-carboxylation of II, VII, IX, X and proteins C and S
- Monitoring: PT/INR
- Onset: delayed (because it affects synthesis, not activity)
- Early hypercoagulability: due to rapid drop in protein C → can cause warfarin skin necrosis
- Bridge with heparin when initiating for acute thrombosis or high-risk scenarios
- Teratogenic: contraindicated in pregnancy (fetal bone/cartilage abnormalities, hemorrhage)
- Reversal (bleeding):
- Vitamin K (slow)
- 4-factor PCC (fast, preferred for major bleeding)
- FFP is older/less efficient than PCC
Now, Destroy the Distractors (why each answer choice matters)
A. Apixaban (Factor Xa inhibitor) — tempting, but CKD complicates it
Why people pick it:
- DOACs are first-line for nonvalvular Afib in many patients
- No routine monitoring, predictable dosing
- Compared with other DOACs, apixaban is often perceived as “most kidney-friendly”
Why it’s not best here (USMLE framing):
- In advanced CKD, DOAC pharmacokinetics and bleeding risk become a major issue.
- Test writers often expect: severe CKD → choose warfarin.
Key apixaban pearls
- MOA: direct Factor Xa inhibitor
- Monitoring: none routinely
- Reversal: andexanet alfa (Factor Xa “decoy”)
- Adverse effect: bleeding (especially GI)
If the vignette emphasized normal renal function + desire to avoid INR checks, apixaban would be a top choice.
B. Dabigatran (Direct thrombin inhibitor) — the renal clearance trap
Why it’s wrong:
- Dabigatran is significantly renally cleared → accumulation in CKD → higher bleeding risk.
High-yield dabigatran facts
- MOA: direct thrombin (Factor IIa) inhibitor
- Reversal: idarucizumab (monoclonal antibody fragment)
- Classic adverse effect: dyspepsia + bleeding
- Step pattern: If you see CKD + dabigatran, think avoid (or dose adjust; many questions simplify to “contraindicated/high risk”).
C. Enoxaparin (LMWH) — good drug, wrong setting
Why it’s wrong here:
- LMWH is renally cleared and can accumulate in CKD → bleeding.
- Also, for long-term stroke prevention in Afib, LMWH is usually not the go-to outpatient maintenance choice.
High-yield heparin vs LMWH
- Unfractionated heparin (UFH):
- Faster on/off, preferred in severe CKD and inpatient settings when you want quick titration
- Monitoring: aPTT
- Reversal: protamine sulfate
- LMWH (enoxaparin):
- More predictable dosing, less HIT than UFH
- Renal clearance → caution/avoid in severe CKD
- Often used in DVT/PE treatment or bridging (in appropriate renal function)
If option “unfractionated heparin” were here and the question asked about an inpatient bridge or acute clot with severe CKD, UFH would jump up the list.
D. Rivaroxaban (Factor Xa inhibitor) — similar to apixaban, often more renal concern
Why it’s wrong:
- Like other DOACs, rivaroxaban has renal elimination and is often avoided or dose-limited in advanced CKD.
- Also associated with GI bleeding risk in some comparisons—exact nuance varies, but the testable point is renal clearance and DOAC use limitations.
High-yield rivaroxaban facts
- MOA: Factor Xa inhibitor
- Monitoring: none routinely
- Reversal: andexanet alfa (for Xa inhibitors)
“Big Picture” Table: Anticoagulants at a Glance (USMLE style)
| Drug/Class | Target | Lab Monitoring | Onset | Key Uses | Key Adverse Effects | Reversal |
|---|---|---|---|---|---|---|
| UFH | Activates antithrombin → inhibits IIa, Xa | aPTT | Rapid | DVT/PE tx, ACS, bridge; preferred in severe CKD | Bleeding, HIT, osteoporosis | Protamine sulfate |
| LMWH (enoxaparin) | Antithrombin → mostly Xa | None (± anti-Xa) | Rapid | DVT/PE tx/prophylaxis; bridging | Bleeding, lower HIT risk; accumulates in CKD | Partial protamine effect |
| Warfarin | ↓ Vit K-dependent factors II, VII, IX, X; ↓ C, S | PT/INR | Delayed | Afib (esp CKD/valvular), VTE long-term | Bleeding, skin necrosis, teratogen | Vitamin K, 4F-PCC |
| Dabigatran | Direct IIa inhibitor | None | Rapid | Afib, VTE | Bleeding, dyspepsia; renal clearance | Idarucizumab |
| Apixaban/Rivaroxaban | Direct Xa inhibitors | None | Rapid | Afib, VTE | Bleeding; caution in CKD | Andexanet alfa |
High-Yield “Answer Choice Triggers” You Should Recognize
If you see pregnancy
- Use heparin/LMWH (do not cross placenta)
- Avoid warfarin (teratogenic)
If you see mechanical heart valve
- Choose warfarin (DOACs are not indicated)
If you see need for immediate anticoagulation
- Choose heparin (UFH/LMWH) → works fast
- Remember warfarin is delayed and needs bridging in many high-risk starts
If you see HIT
- Stop heparin/LMWH
- Use a non-heparin anticoagulant (classically argatroban or bivalirudin; also fondaparinux sometimes shows up)
If you see major bleeding + warfarin
- 4-factor PCC + vitamin K
If you see major bleeding + dabigatran
- Idarucizumab
If you see major bleeding + Xa inhibitor
- Andexanet alfa (or PCC depending on institutional protocols; USMLE loves andexanet)
How to Think Like the Test Writer (Quick Algorithm)
- Identify indication: Afib stroke prevention vs acute DVT/PE vs ACS.
- Check the “deal-breakers”:
- Pregnant? → heparin/LMWH
- Mechanical valve / mitral stenosis? → warfarin
- Severe CKD? → warfarin (or UFH inpatient); be cautious with DOACs/LMWH
- If warfarin is started: remember bridge and protein C drop concepts.
- If bleeding occurs: pick the correct reversal.
Takeaway
In this vignette, warfarin is the best initial anticoagulant because severe CKD makes DOAC/LMWH choices less safe and less predictable—and warfarin has a well-established monitoring and reversal framework. On Step exams, you score points not by vaguely recognizing drug classes, but by matching patient-specific constraints (kidney function, pregnancy, valve status, urgency) to the one anticoagulant that cleanly fits.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
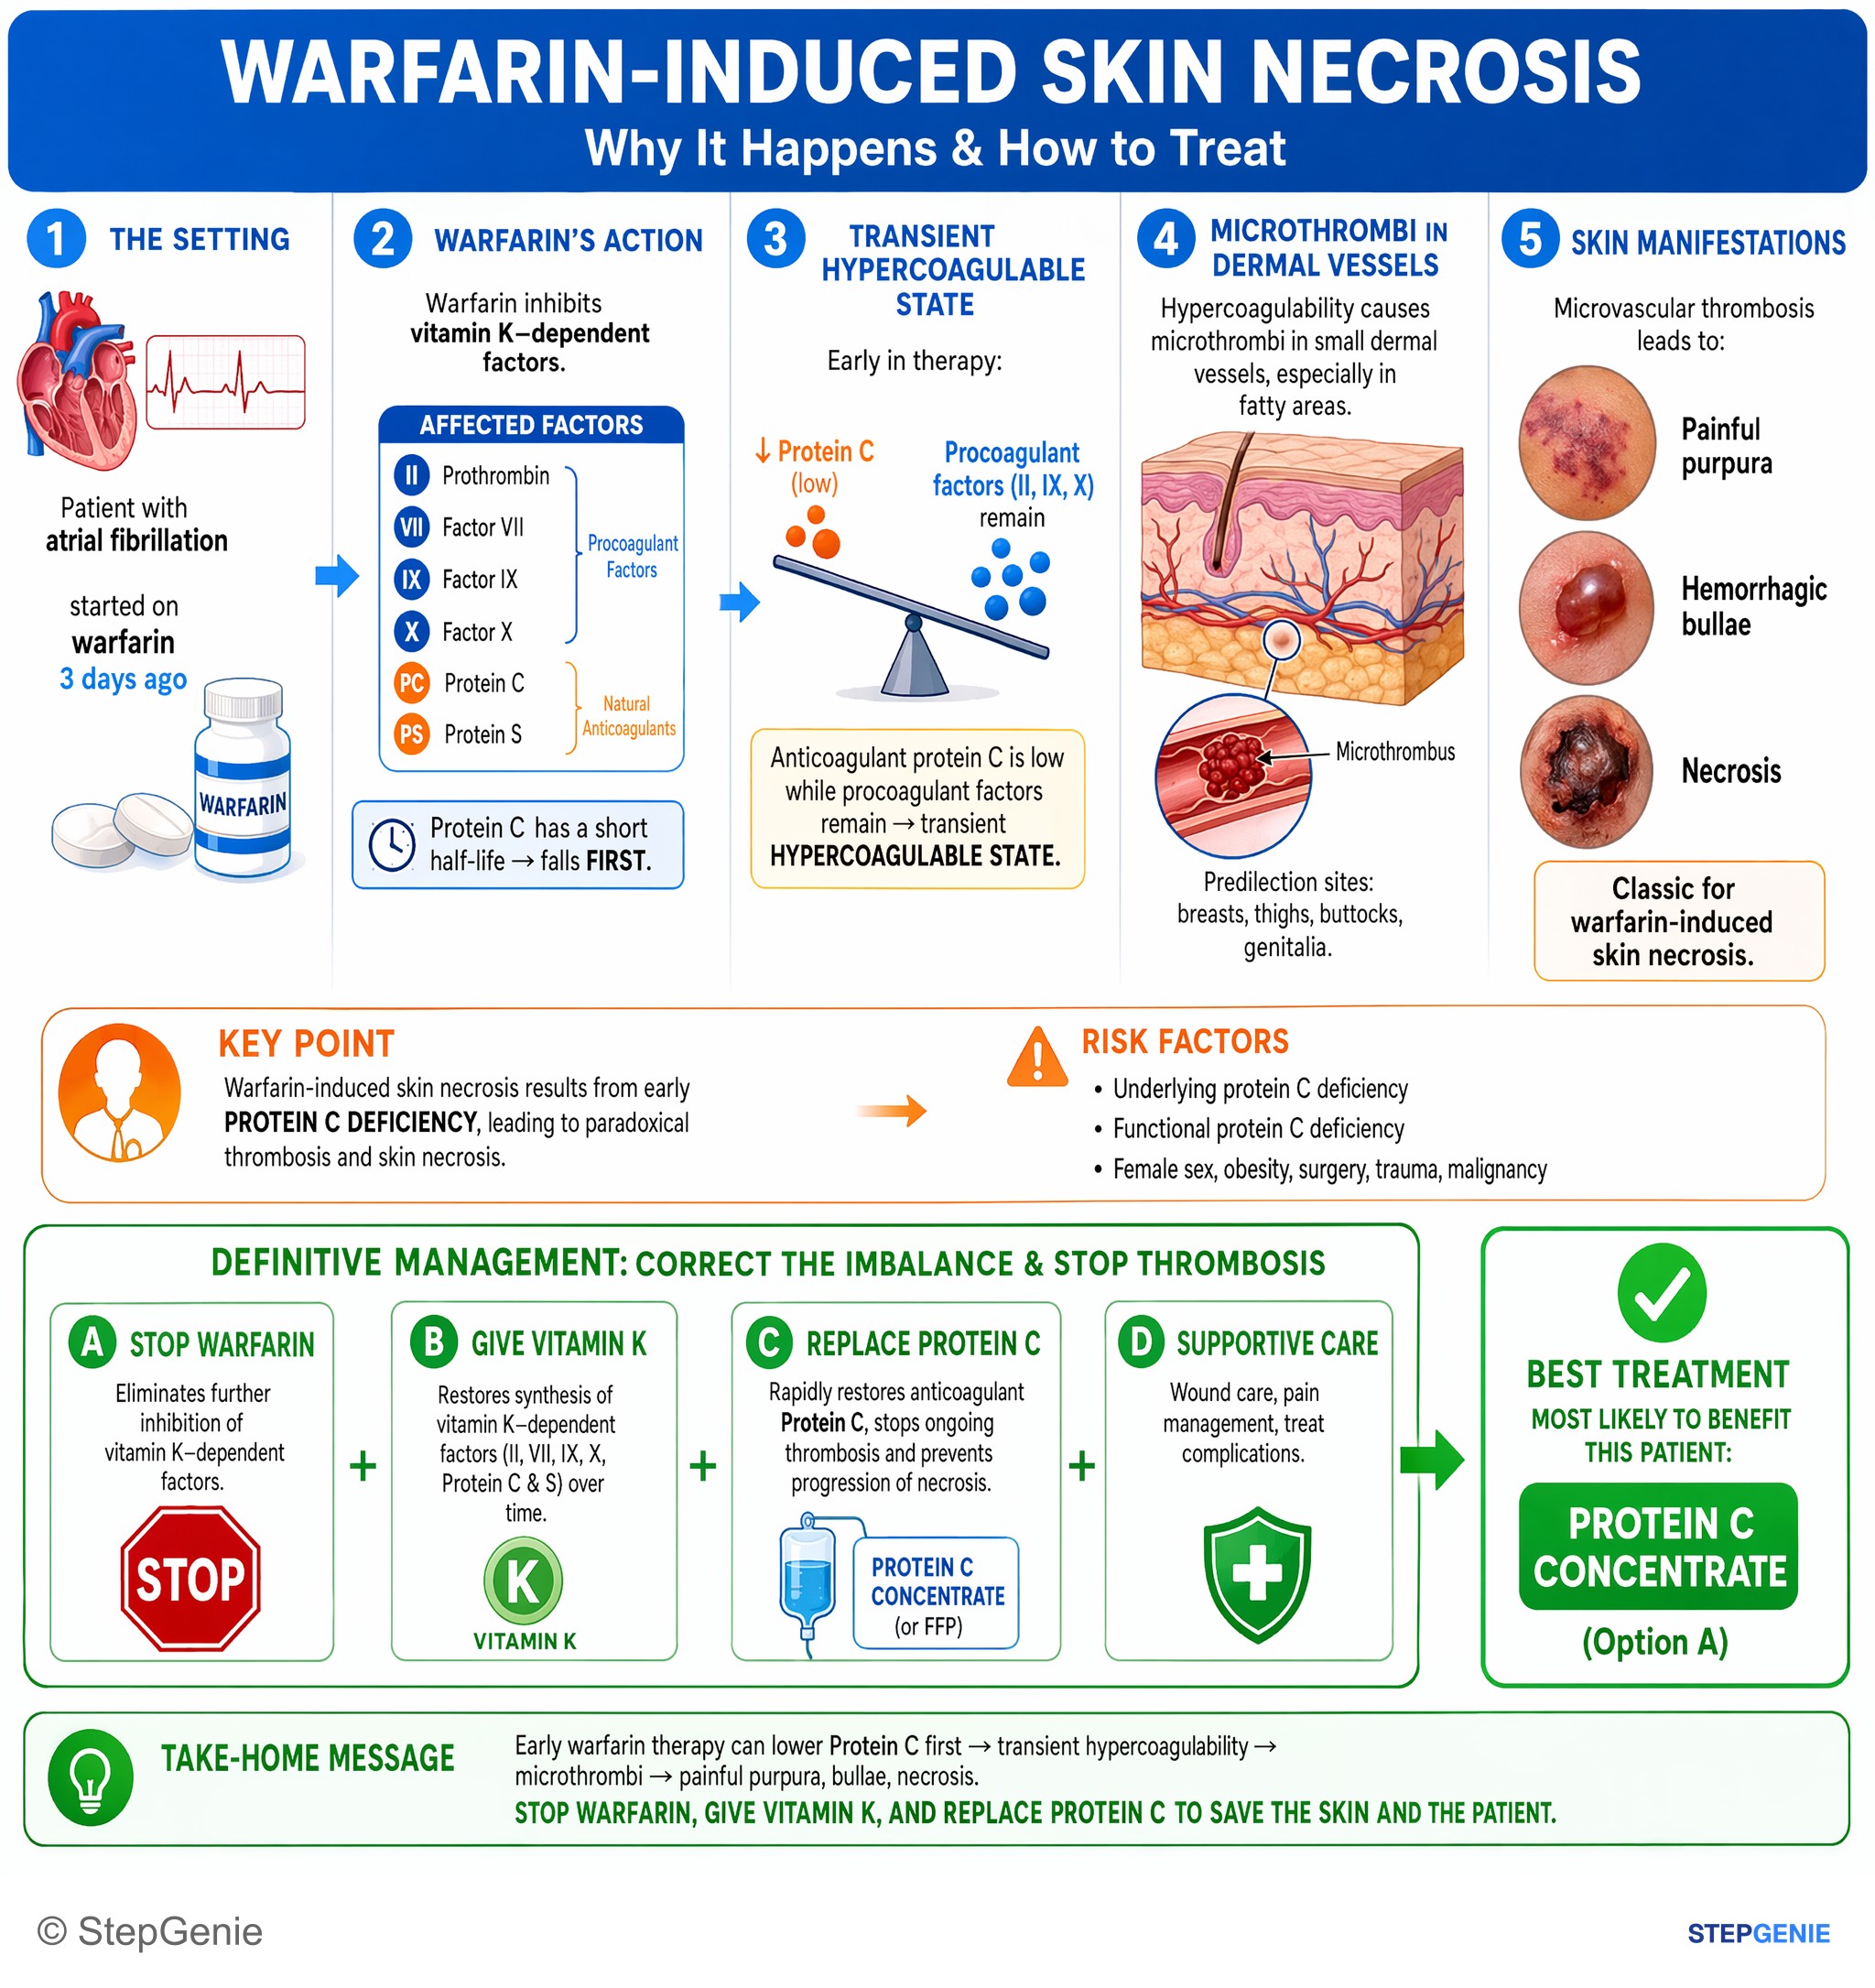
Warfarin-induced skin necrosis from early protein C deficiency → paradoxical thrombosis and skin necrosis; treat by replacing protein C…
USMLE Step 2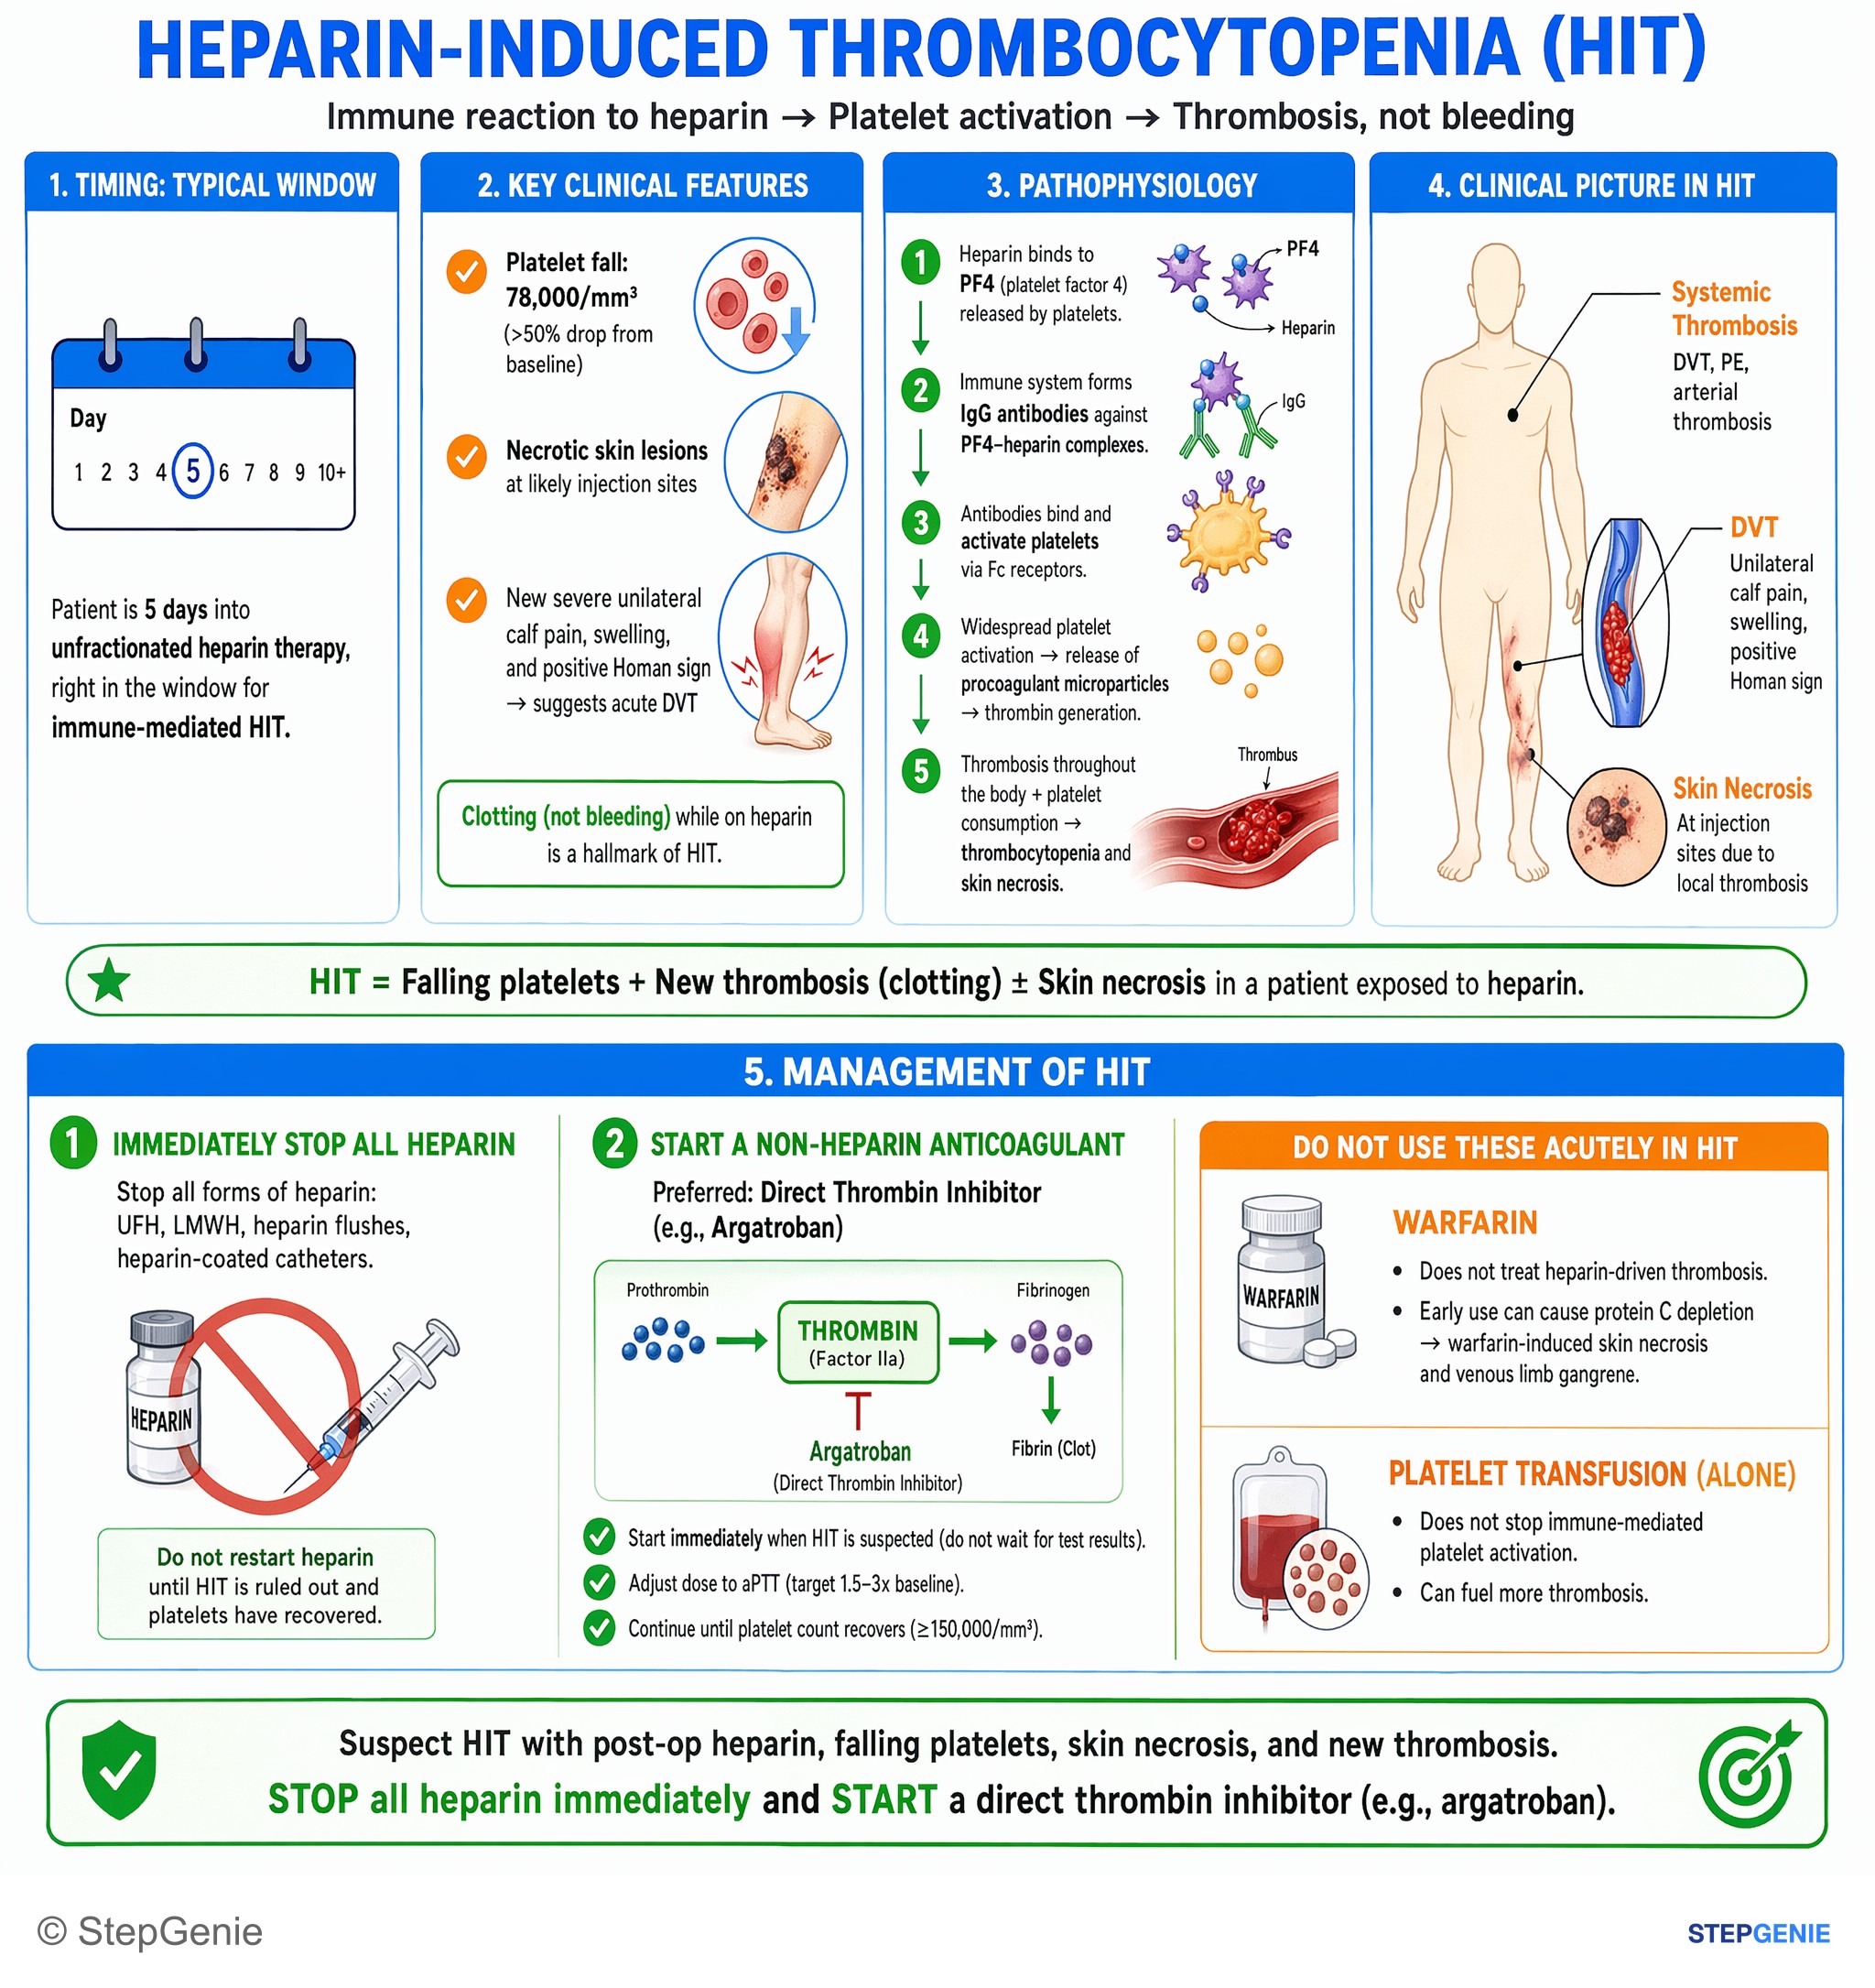
Heparin-induced thrombocytopenia: post-op heparin, falling platelets, skin necrosis, new thrombosis → stop heparin and start direct…
USMLE Step 2Frequently Asked Questions
Why is warfarin preferred over DOACs in severe CKD for atrial fibrillation?
Warfarin is preferred because severe CKD raises the risk that many DOACs will accumulate and cause bleeding. In advanced renal impairment, classic USMLE logic favors warfarin when DOAC dosing is uncertain or contraindicated. Warfarin also gives a measurable anticoagulation effect with PT/INR and has a well-established reversal strategy, making it a more controllable option when renal function is poor.
How do you tell dabigatran from apixaban or rivaroxaban on a pharmacology question?
Dabigatran is the direct thrombin inhibitor, while apixaban and rivaroxaban are direct factor Xa inhibitors. Dabigatran is also the classic renal-clearance trap because it is significantly renally cleared and can accumulate in CKD, increasing bleeding risk. Its specific reversal agent is idarucizumab, whereas the factor Xa inhibitors are reversed with andexanet alfa.
What makes enoxaparin a bad answer choice in severe CKD?
Enoxaparin is a poor choice in severe CKD because it is renally cleared and can accumulate, which increases bleeding risk. It is also usually not the preferred long-term outpatient maintenance drug for stroke prevention in atrial fibrillation. By contrast, unfractionated heparin is preferred in severe CKD when rapid titration is needed, especially in inpatient or bridging settings.
Why do Step questions care so much about warfarin monitoring, onset, and bridging?
These details explain why warfarin behaves differently from heparin and DOACs. Warfarin inhibits vitamin K epoxide reductase, so its onset is delayed because it affects clotting factor synthesis rather than existing factor activity. It is monitored with PT/INR, and it can cause early hypercoagulability from a rapid drop in protein C, so heparin bridging is used in acute thrombosis or other high-risk situations.
What is the major bleeding reversal strategy for warfarin?
Major warfarin bleeding is reversed most rapidly with 4-factor PCC, while vitamin K provides slower reversal. This reliable and well-established reversal strategy is one reason warfarin remains important when predictable management of bleeding matters. FFP can also be used, but it is described as an older and less efficient option than PCC.