A hypertensive emergency is severe hypertension (often defined as at least 180 mm Hg systolic and/or 120 mm Hg diastolic) with new or worsening target-organ damage: hypertensive encephalopathy, optic disc edema, acute kidney injury, acute coronary syndrome, acute pulmonary edema, aortic dissection or eclampsia. The organ damage, not the number, defines it. Treat it in an ICU with a short-acting, titratable IV drug (nicardipine, clevidipine and labetalol are typical) and lower pressure gradually: by about 20-25% (mean arterial pressure) over the first 1-2 hours, then toward about 160/100 mm Hg over the next 2-6 hours, and to normal over the following 24-48 hours (Merck; StatPearls). Aortic dissection is the main exception (beta-blocker first, systolic pressure to 120 mm Hg or lower quickly). Severe hypertension without acute organ damage, the old "hypertensive urgency," is not an emergency: the 2025 AHA/ACC guideline says to evaluate and treat it (in nonpregnant adults) as an outpatient, starting, restarting or intensifying oral medication in a timely way.
The Q-bank question
A 47-year-old man who stopped his antihypertensive medications 3 months ago is brought to the emergency department with 2 days of worsening headache, vomiting and blurred vision; this morning he became confused. Blood pressure is 236/138 mm Hg in both arms and pulse 94/min. He is disoriented but has no focal neurologic deficits. Funduscopy shows bilateral optic disc edema with flame-shaped hemorrhages and cotton-wool spots. Noncontrast head CT shows no hemorrhage. The ECG shows left ventricular hypertrophy without acute ST changes, troponin is normal, serum creatinine is 1.1 mg/dL, and a urine drug screen is negative.
Which of the following is the most appropriate next step in management?
A. Oral clonidine, then discharge with clinic follow-up in 1 week B. IV nicardipine infusion in the ICU, lowering mean arterial pressure by about 20-25% over the first 1-2 hours C. IV nitroprusside titrated to bring blood pressure to 120/80 mm Hg within the first hour D. Sublingual immediate-release nifedipine E. IV esmolol titrated to bring systolic pressure below 120 mm Hg as fast as possible
Answer: B. Headache, vomiting, confusion and optic disc edema with a pressure of 236/138 mm Hg is hypertensive encephalopathy, a hypertensive emergency. He needs ICU monitoring and a titratable IV agent. Nicardipine is a dihydropyridine calcium channel blocker that acts mainly as a vasodilator; it is started at 5 mg/h and increased by 2.5 mg/h every 5-15 minutes, up to 15 mg/h. His mean arterial pressure (MAP = diastolic + one-third of the pulse pressure) is about 171 mm Hg, so a 20-25% reduction means a MAP of roughly 128-137 mm Hg over the first 1-2 hours, not a normal reading.
Why every other answer is wrong
- A. Oral clonidine and discharge. Oral drugs and outpatient follow-up are right for severe hypertension without acute organ damage, not for encephalopathy. Oral clonidine cannot be titrated minute to minute (pressure falls within 30-60 minutes and bottoms out at 2-4 hours), drowsiness affects about a third of patients and clouds the neurologic exam, and stopping it abruptly can cause a rapid rebound rise in pressure, rarely with encephalopathy, stroke or death.
- C. Nitroprusside to 120/80 within the hour. The drug is potent and titratable, and Merck still names it among typical first-line drugs (while advising against it when alternatives are available), but the target is the error. Dropping a chronically hypertensive patient to "normal" in an hour risks ischemic stroke, MI and kidney injury; the label's boxed warning says precipitous falls can cause irreversible ischemic injury or death. Nitroprusside also produces cyanide (infusions above 2 mcg/kg/min generate it faster than the body clears it), lets thiocyanate accumulate in renal impairment, and can raise intracranial pressure. Merck notes higher mortality with nitroprusside than with clevidipine, nitroglycerin or nicardipine.
- D. Immediate-release nifedipine. The capsule label says it should not be used for the acute reduction of blood pressure: given orally or sublingually it has caused profound hypotension, MI and death. (Oral immediate-release nifedipine is an option for acute severe hypertension in pregnancy, a different setting.)
- E. Esmolol to a systolic pressure under 120 mm Hg. That is the aortic dissection regimen. Equal arm pressures and a picture of encephalopathy give no reason to suspect dissection, and forcing pressure that low, that fast, risks cerebral hypoperfusion. See aortic dissection, Stanford A vs B.
Emergency vs severe hypertension without organ damage
| Hypertensive emergency | Severe hypertension without acute organ damage | |
|---|---|---|
| Blood pressure | Often 180/120 mm Hg or higher; can be lower if a normotensive person's BP rises suddenly | Above 180/120 mm Hg |
| Target-organ damage | New or worsening | None |
| Where | ICU | Outpatient (2025 AHA/ACC guideline) |
| Drugs | Short-acting, titratable IV infusion | Oral: start, restart or intensify |
| Speed | MAP down about 20-25% in 1-2 hours, then gradual | Gradual, with close outpatient follow-up |
In hospital, asymptomatic markedly raised pressure may reflect measurement problems or temporary, reversible factors. A 2024 AHA scientific statement on acute care addresses this; according to AAFP's 2026 summary of it, such pressure often does not need to be treated, and medication changes are best made in outpatient primary care.
Target-organ damage: what to look for
| Organ | Finding | First test |
|---|---|---|
| Brain | Encephalopathy: headache, vomiting, confusion, seizures, transient cortical blindness; stroke or hemorrhage | Head CT for any neurologic finding |
| Eyes | Flame-shaped hemorrhages, cotton-wool spots, exudates; optic disc edema (papilledema) is part of the severe retinopathy usually seen with hypertensive encephalopathy | Funduscopy |
| Heart | Acute coronary syndrome; acute LV failure with pulmonary edema | ECG, troponin |
| Aorta | Dissection: abrupt tearing or ripping chest or interscapular pain, pulse deficits, arm BP difference | CT angiography (or TEE) |
| Kidneys | Acute kidney injury, hematuria, proteinuria; fibrinoid necrosis of renal arterioles is the classic pathology | Creatinine, urinalysis |
| Pregnancy | Preeclampsia or eclampsia | BP, urine protein, labs |
Merck's core workup is an ECG, urinalysis, electrolytes and creatinine, plus head CT for neurologic findings.
Why encephalopathy happens. Cerebral arterioles normally constrict as pressure rises, keeping brain flow constant. Above a MAP of about 160 mm Hg (lower in a previously normotensive person whose pressure rises suddenly), they give way and dilate, plasma leaks out, and cerebral edema follows. That same baseline dependence is why the rate of rise matters as much as the number, and why a chronically hypertensive brain is put at risk by a sudden drop to "normal." The kidney uses the same idea: see renal blood flow autoregulation.
The IV drug toolbox
| Drug | How it works | Use it for | Watch out for |
|---|---|---|---|
| Nicardipine | Dihydropyridine CCB, mainly a vasodilator | Most emergencies except acute heart failure; often used postoperatively and in pregnancy | Tachycardia, headache, flushing, phlebitis; caution with myocardial ischemia; contraindicated in advanced aortic stenosis |
| Clevidipine | Ultra-short-acting dihydropyridine CCB | Most emergencies; lower mortality than nitroprusside | Contraindicated with soy or egg allergy, defective lipid metabolism, severe aortic stenosis; caution in acute heart failure |
| Labetalol | Alpha-1 and beta blocker (mostly beta when IV) | Most emergencies except acute LV failure; pregnancy | Avoid in asthma; heart block, orthostatic hypotension |
| Esmolol | Short-acting beta-blocker | Aortic dissection, perioperative | Hypotension |
| Nitroglycerin | Nitrate vasodilator | Myocardial ischemia, heart failure with pulmonary edema | Headache, tachycardia, tolerance with prolonged use |
| Nitroprusside | Arterial and venous dilator | Mostly hypertensive acute decompensated heart failure (also encephalopathy, and dissection after beta-blockade); Merck advises against it when alternatives exist | Cyanide and thiocyanate toxicity, precipitous hypotension; caution with raised ICP or azotemia |
| Hydralazine | Direct arteriolar dilator | Eclampsia | Reflex tachycardia, aggravates angina |
| Fenoldopam | Dopamine-1 agonist (renal vasodilation, natriuresis) | Still in Merck's table and exam lists, but every US product is listed as discontinued (Drugs@FDA) | Tachycardia, flushing, hypokalemia; raises intraocular pressure in glaucoma |
| Phentolamine | Alpha blocker | Confirmed pheochromocytoma (rarely used otherwise) | Tachycardia, flushing, headache |
| Enalaprilat | IV ACE inhibitor | Acute LV failure | Precipitous fall in high-renin states; avoid in acute MI and pregnancy |
Match the emergency to the drug
- Hypertensive encephalopathy: nicardipine, clevidipine or labetalol; lower MAP by about 20-25%.
- Aortic dissection: IV beta-blocker first (esmolol, labetalol or metoprolol) to a heart rate of 60-80/min and systolic pressure of 120 mm Hg or lower; add a vasodilator such as nitroprusside only after beta-blockade, because reflex sympathetic activation increases aortic shear stress.
- Acute coronary syndrome or acute pulmonary edema: IV nitroglycerin. Avoid hydralazine (it aggravates angina) and labetalol in acute LV failure.
- Preeclampsia or eclampsia: IV labetalol or hydralazine, or oral immediate-release nifedipine, plus magnesium sulfate to prevent seizures; ACE inhibitors are contraindicated in pregnancy because they can injure or kill the fetus, especially with second- and third-trimester exposure. More in preeclampsia and eclampsia.
- Cocaine toxicity: benzodiazepines first, then IV nitrates, nicardipine or phentolamine for persistent hypertension; beta-blockers are contraindicated.
- Pheochromocytoma crisis: phentolamine (alpha blockade first); see the pheochromocytoma mnemonic.
- Acute stroke: follows stroke-specific blood pressure rules; see stroke management.
How USMLE tests it
- Look past the number. 220/130 with no symptoms and a normal workup is not an emergency; 190/115 with confusion and papilledema is.
- "Lower it by how much?" About 20-25% in the first 1-2 hours. Normalizing within an hour is wrong, except in aortic dissection.
- IV and titratable vs oral. Emergency means an IV infusion in the ICU; oral agents belong to severe hypertension without organ damage.
- Immediate-release nifedipine for a hypertensive crisis is always wrong outside pregnancy.
- Nitroprusside clues: rising dose requirements, then metabolic acidosis, agitation or seizures during a long or high-dose infusion suggest cyanide toxicity; thiocyanate accumulates in kidney failure.
- Drug-patient mismatches: labetalol in asthma, clevidipine with an egg or soy allergy, nicardipine or clevidipine with severe aortic stenosis, beta-blockers in cocaine toxicity, and vasodilator before beta-blocker in dissection.
- Rebound hypertension after abruptly stopping clonidine is a classic cause of a hypertensive crisis.
Key takeaways
- Hypertensive emergency = severe BP plus new or worsening target-organ damage; the organ findings, not the number, decide.
- ICU and a titratable IV drug: nicardipine, clevidipine or labetalol for most cases.
- Lower MAP by about 20-25% over 1-2 hours, then toward 160/100 mm Hg over 2-6 hours and to normal over 24-48 hours.
- Aortic dissection: beta-blocker first, systolic pressure 120 mm Hg or lower, heart rate 60-80/min.
- Severe hypertension without organ damage: outpatient oral therapy (2025 AHA/ACC guideline).
- Never use immediate-release nifedipine to drop BP acutely; nitroprusside carries cyanide and thiocyanate risk.
Sources
- Hypertensive Emergencies — Merck Manual Professional Edition (2026)
- 2025 High Blood Pressure Guideline: Top Things to Know — American Heart Association Professional Heart Daily (2025)
- Management of Elevated Blood Pressure in Acute Care: Statement From the American Heart Association — American Family Physician (2026)
- Hypertensive Emergency — StatPearls, NCBI Bookshelf (2023)
- Aortic Dissection — Merck Manual Professional Edition (2024)
- Cocaine — Merck Manual Professional Edition (2026)
- Nipride RTU (Sodium Nitroprusside) Injection: Prescribing Information — DailyMed, NLM (2018)
- Nicardipine Hydrochloride Injection: Prescribing Information — DailyMed, NLM (2025)
- Cleviprex (Clevidipine) Injectable Emulsion: Prescribing Information — DailyMed, NLM (2022)
- Nifedipine Capsules: Prescribing Information — DailyMed, NLM (2018)
- Clonidine Hydrochloride Tablets: Prescribing Information — DailyMed, NLM (2022)
- Corlopam (Fenoldopam Mesylate): Drugs@FDA Application Overview — US Food and Drug Administration
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
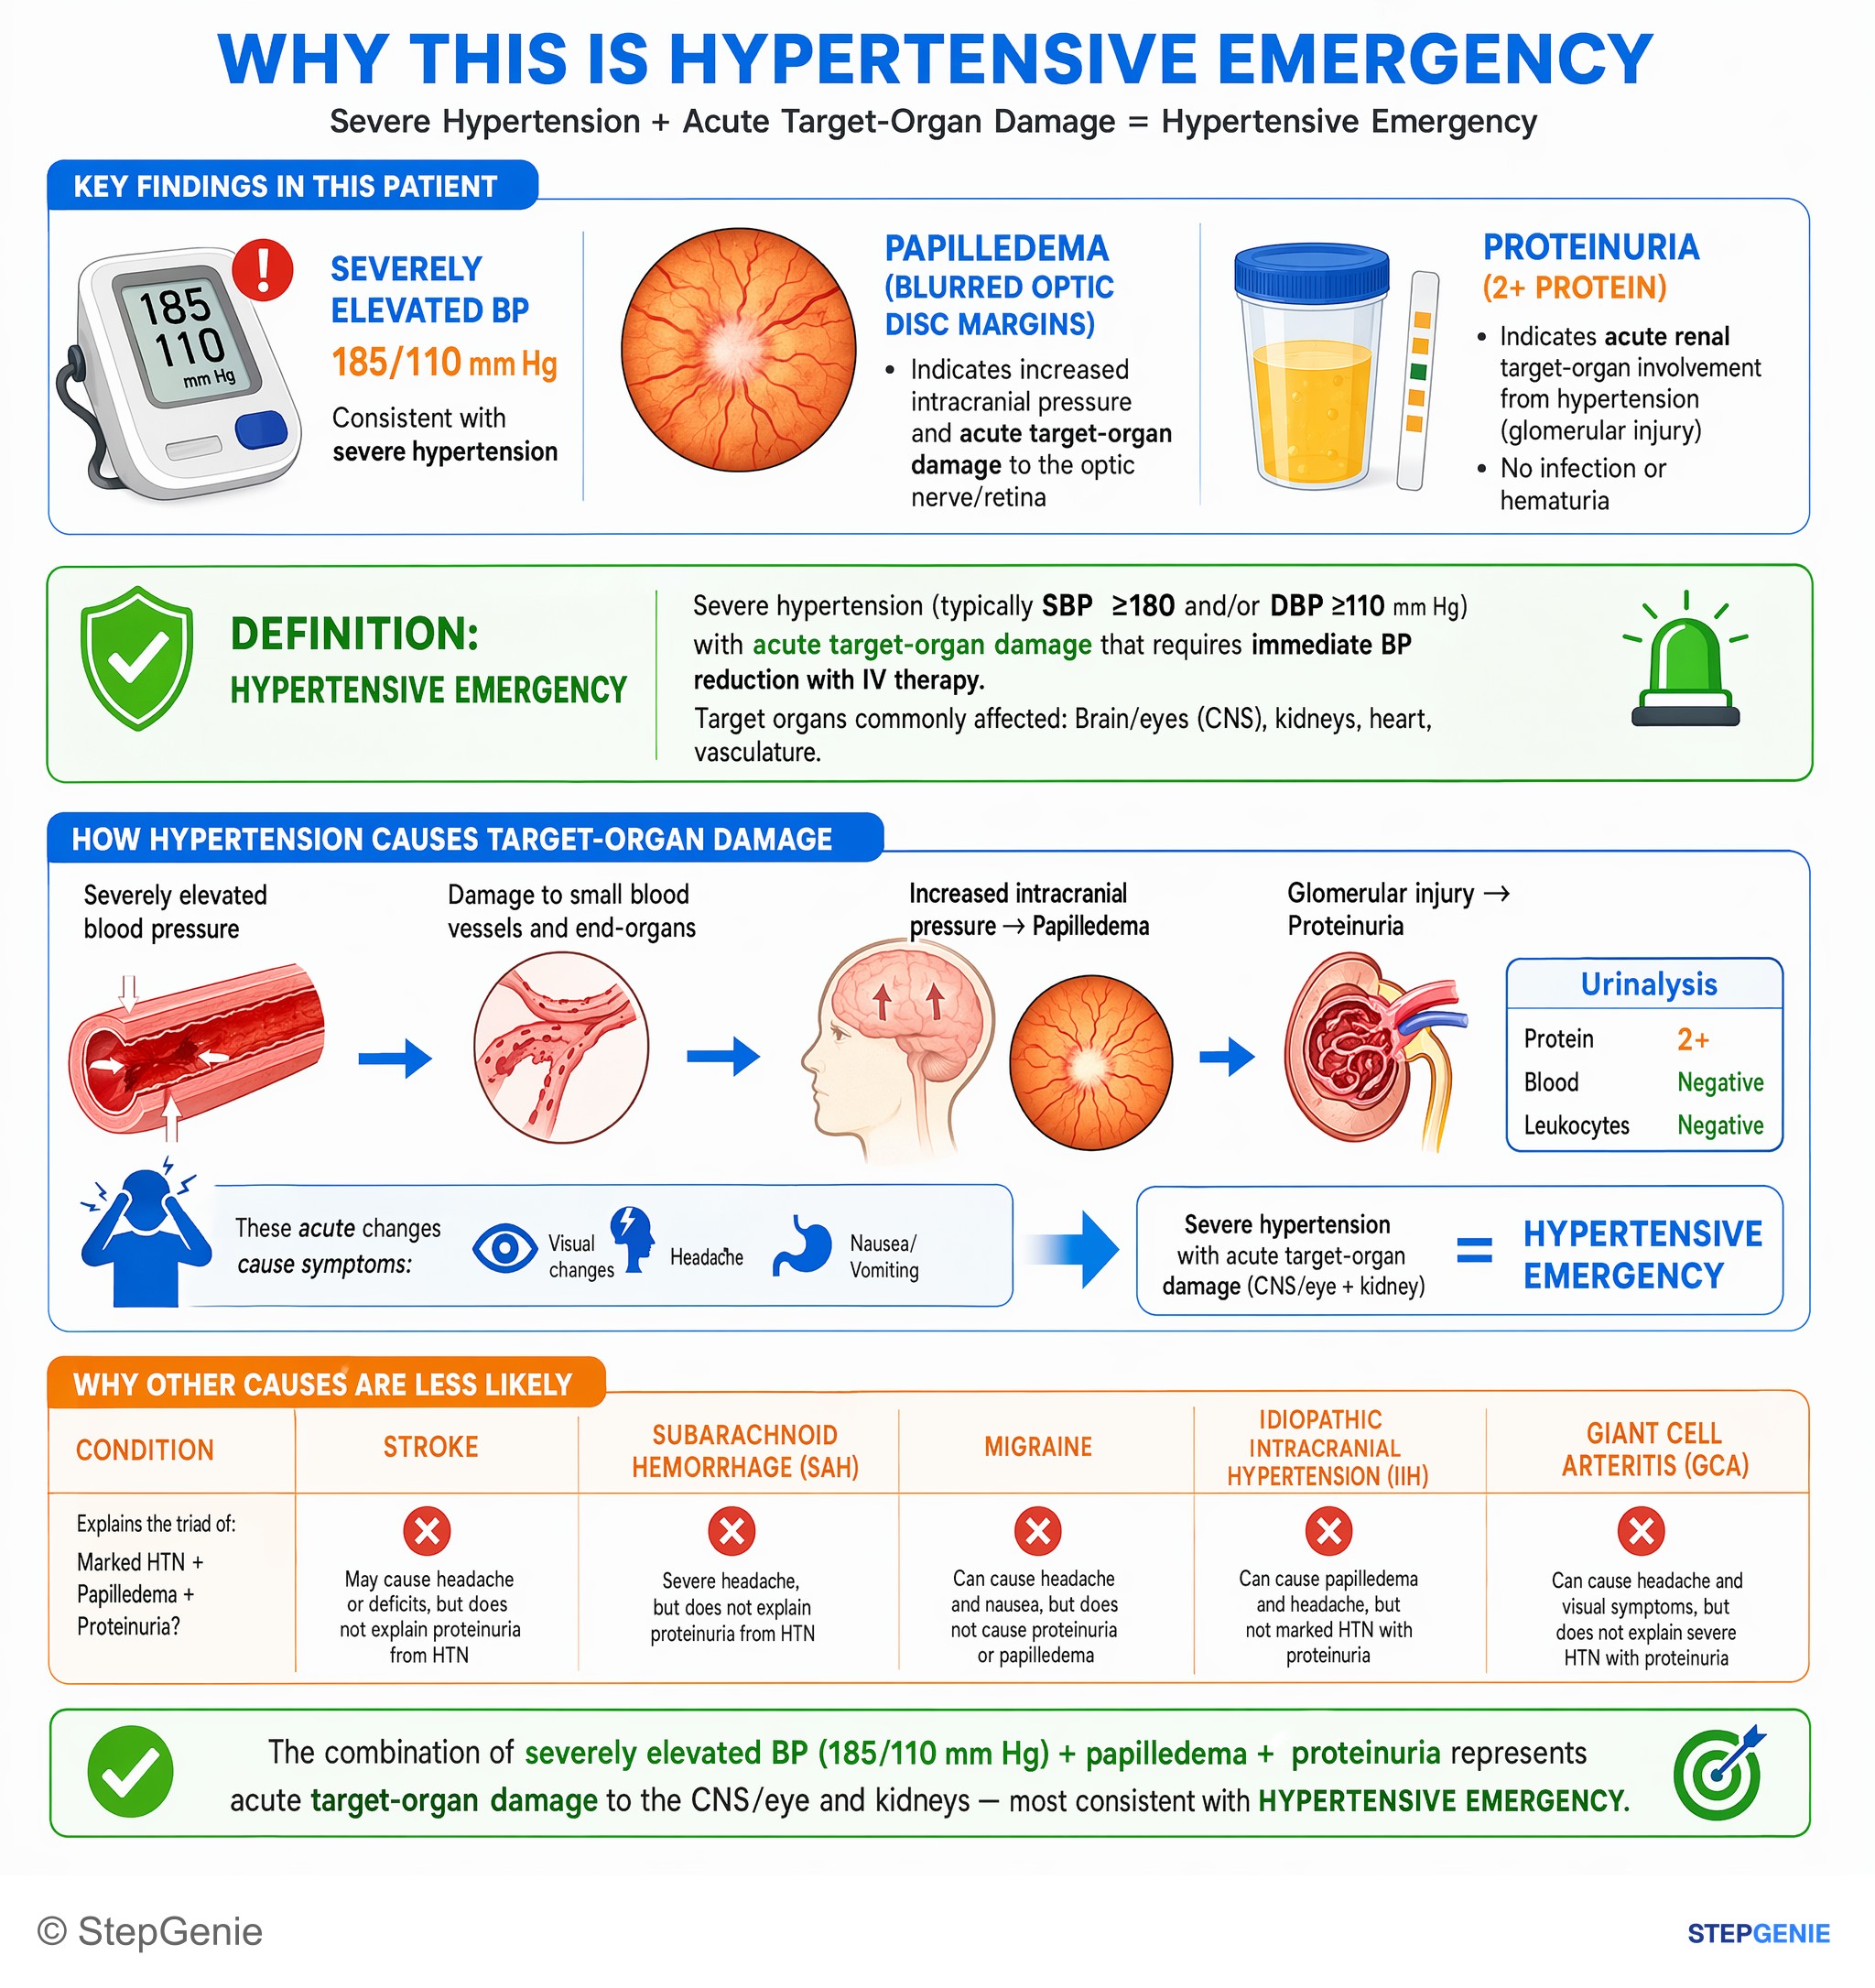
Hypertensive emergency: severe hypertension with acute target-organ damage (papilledema, proteinuria) causing headache, visual changes…
USMLE Step 2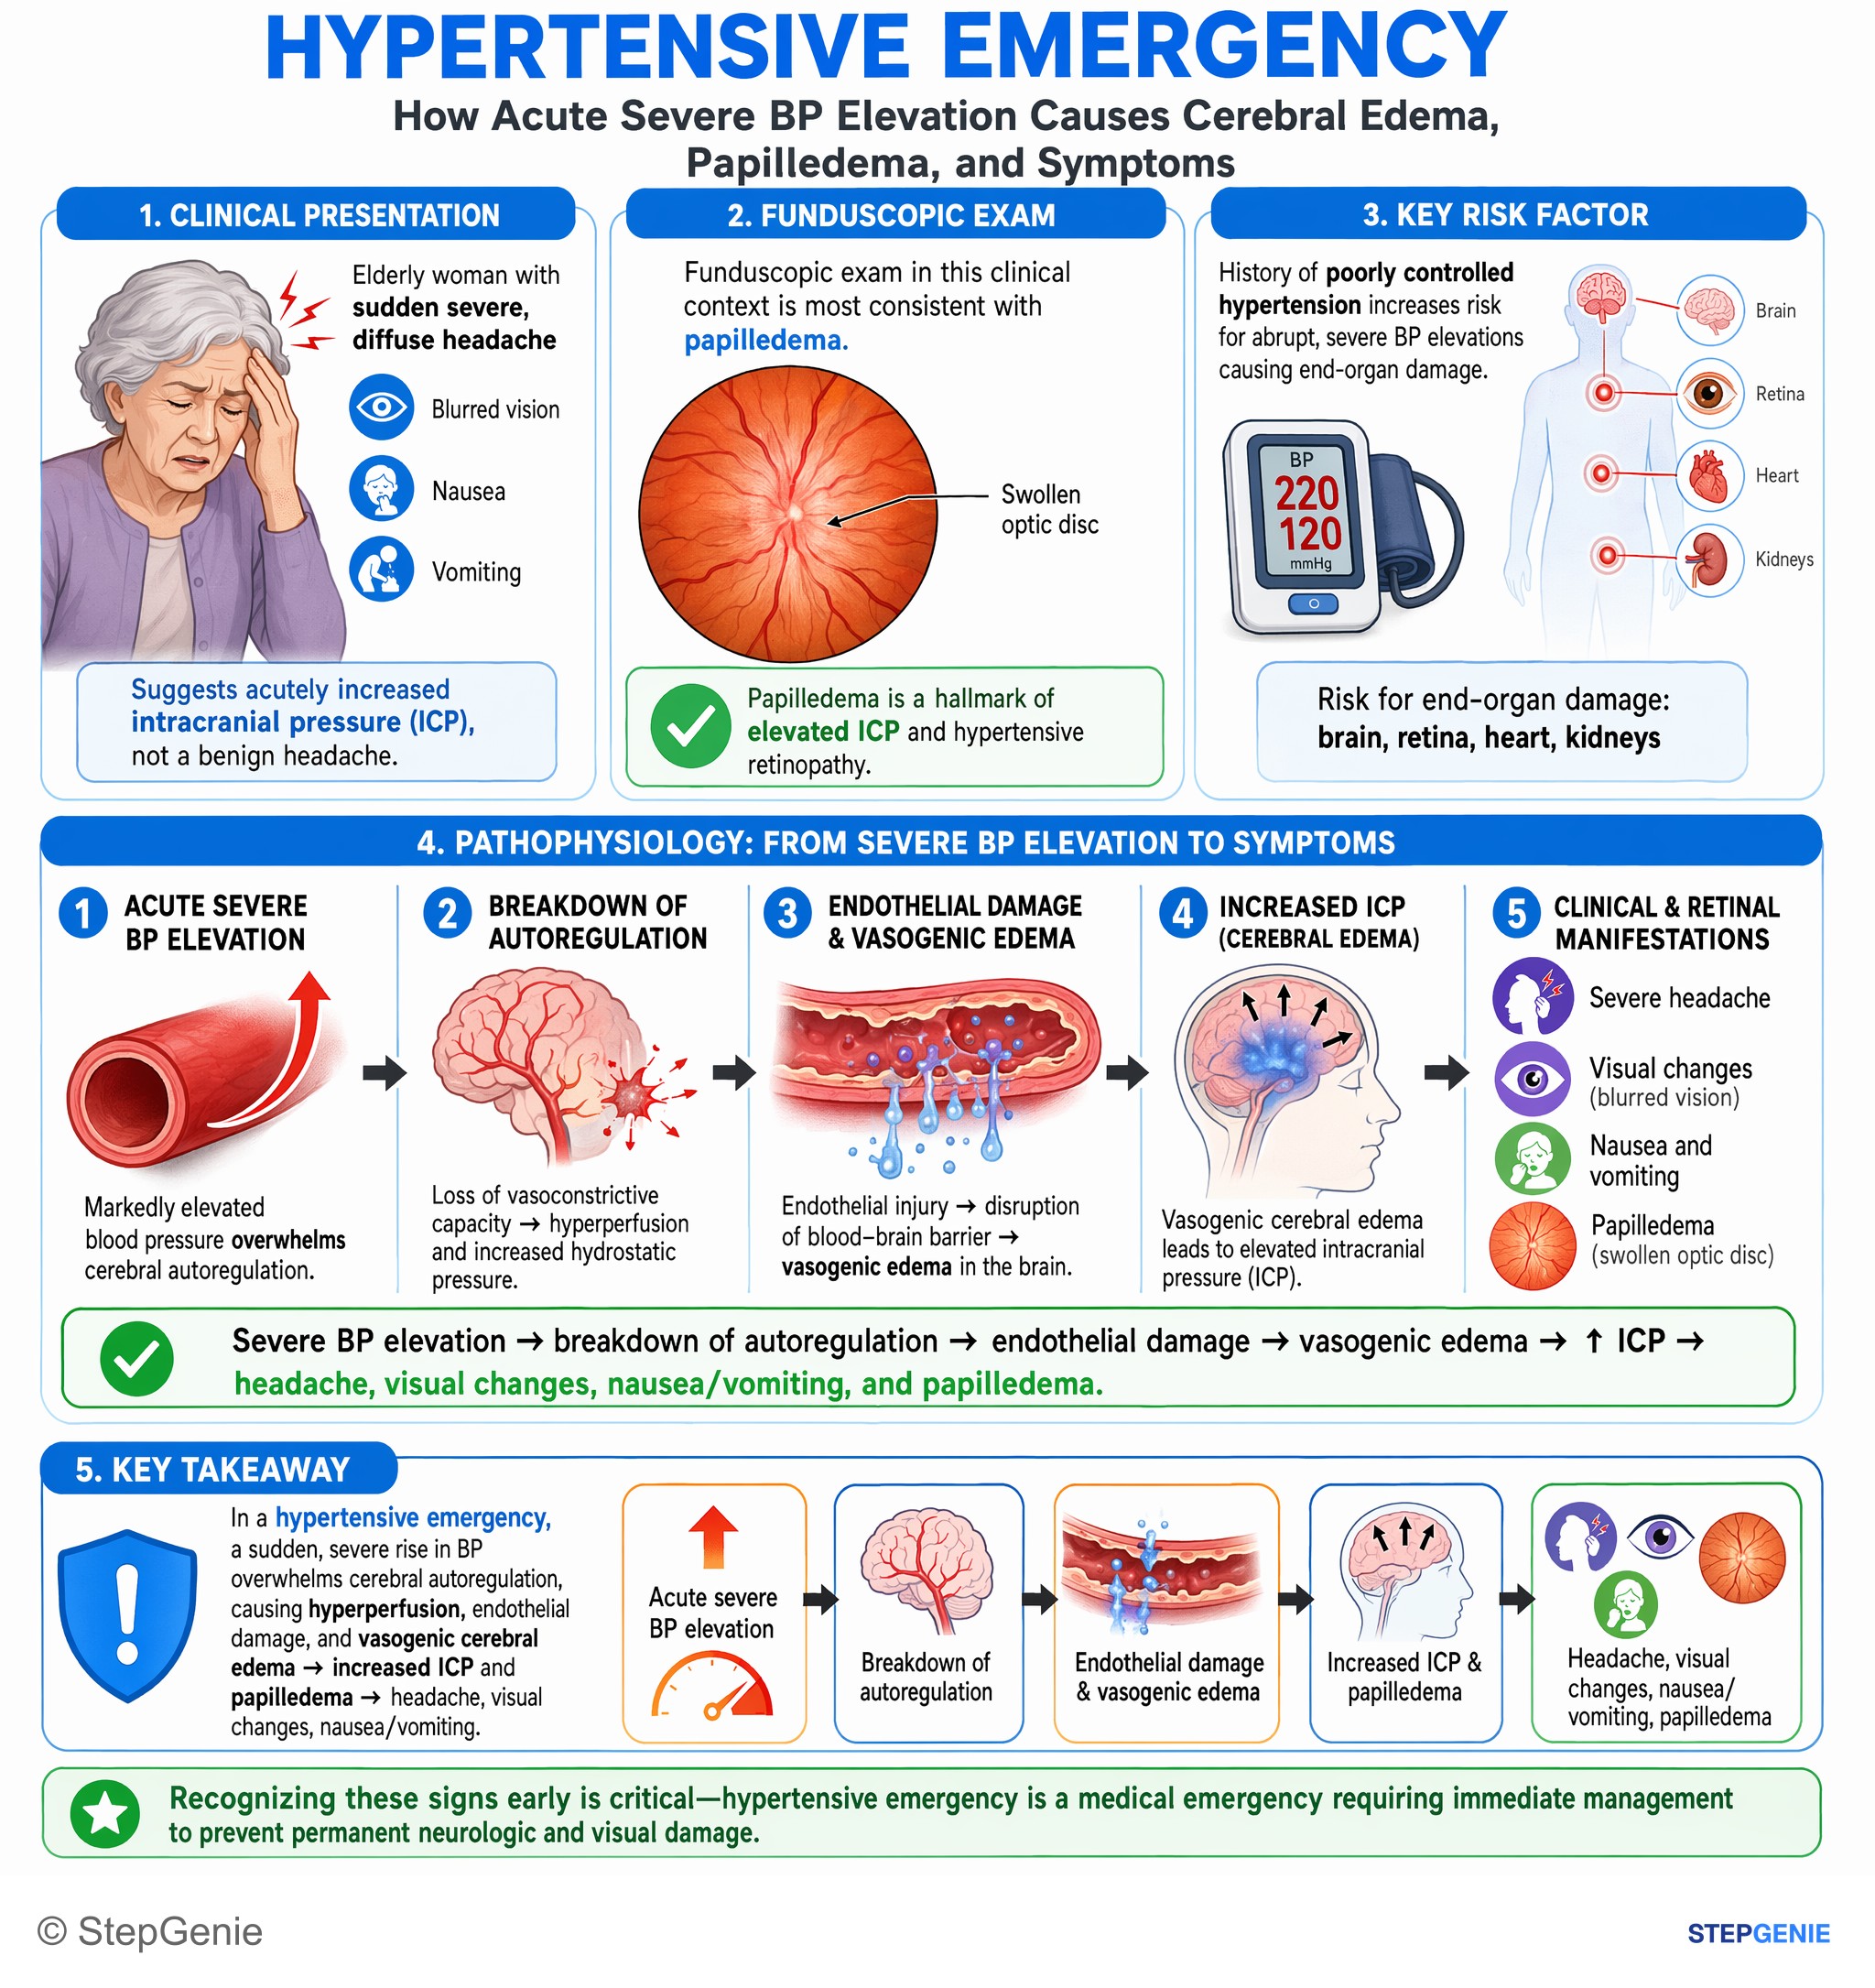
Hypertensive emergency causes acute severe BP elevation → breakdown of autoregulation → cerebral edema and papilledema with headache…
USMLE Step 1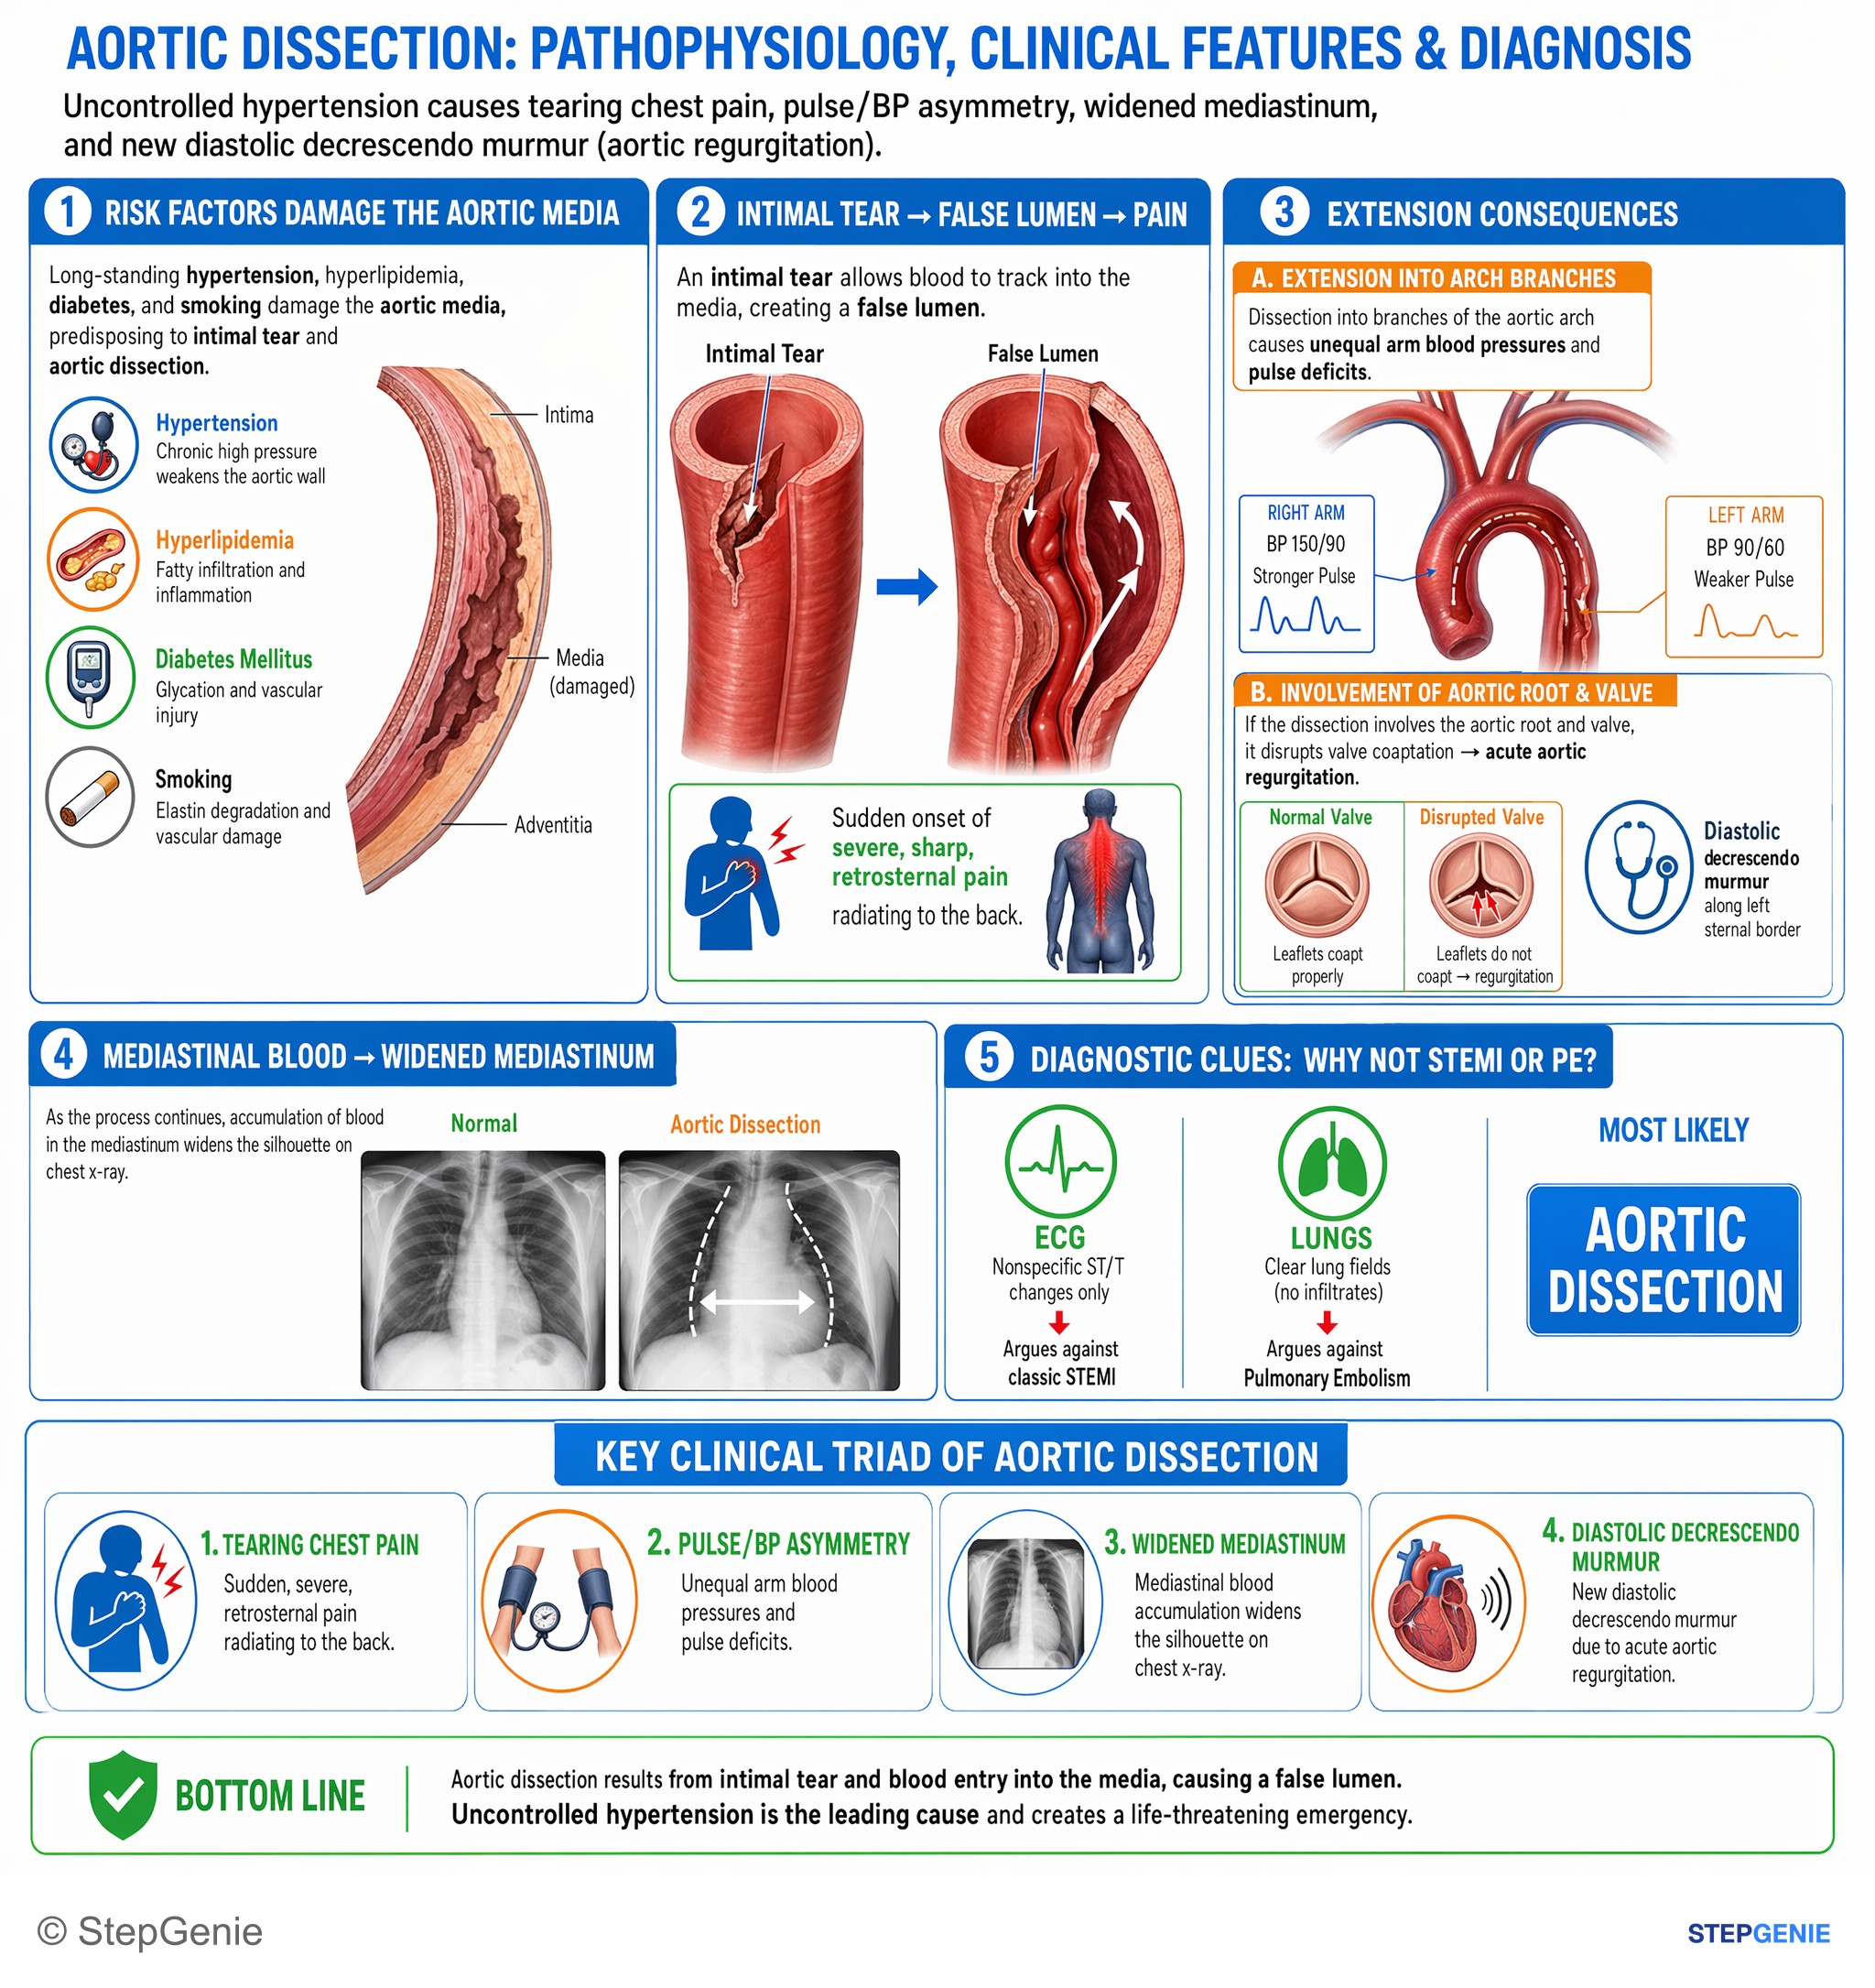
Aortic dissection from uncontrolled hypertension causes tearing chest pain, pulse/BP asymmetry, widened mediastinum, and new diastolic…
USMLE Step 2Frequently Asked Questions
What is the difference between hypertensive emergency and hypertensive urgency?
Both involve severe hypertension, often at least 180/120 mm Hg. A hypertensive emergency also has new or worsening target-organ damage, such as encephalopathy, optic disc edema, acute kidney injury, acute coronary syndrome, pulmonary edema, aortic dissection or eclampsia, and is treated in an ICU with IV drugs. Without acute organ damage it is severe hypertension, formerly called hypertensive urgency, and the 2025 AHA/ACC guideline advises outpatient evaluation and timely oral medication for nonpregnant adults.
How fast should blood pressure be lowered in a hypertensive emergency?
Gradually. A common approach is to lower mean arterial pressure by about 20 to 25% over the first 1 to 2 hours, then toward about 160/100 mm Hg over the next 2 to 6 hours, and to normal over the following 24 to 48 hours. Dropping pressure to normal quickly can cause ischemic injury to the brain, heart or kidneys. Aortic dissection is the main exception: systolic pressure is brought to 120 mm Hg or lower quickly, with a beta-blocker given first.
What is the drug of choice for hypertensive emergency?
There is no single drug for every case; the choice depends on the organ involved. Short-acting, titratable IV agents such as nicardipine, clevidipine and labetalol suit most hypertensive emergencies, including encephalopathy. Aortic dissection calls for an IV beta-blocker such as esmolol first, myocardial ischemia and pulmonary edema for nitroglycerin, eclampsia for hydralazine or labetalol with magnesium sulfate, pheochromocytoma for phentolamine, and cocaine toxicity for benzodiazepines first, with beta-blockers avoided.
Why is nitroprusside used less often in hypertensive emergency?
Nitroprusside works almost instantly and is easy to titrate, but its boxed warning covers precipitous drops in blood pressure and dose-related cyanide production. Infusions above 2 mcg/kg/min generate cyanide faster than the body can clear it, thiocyanate accumulates in kidney failure, and the drug can raise intracranial pressure. The Merck Manual notes higher mortality with nitroprusside than with clevidipine, nitroglycerin or nicardipine, advises against it when other options are available, and suggests clevidipine may be preferred for most hypertensive emergencies.
Why is immediate-release nifedipine not used for hypertensive crisis?
Given orally or sublingually, immediate-release nifedipine can lower blood pressure abruptly and unpredictably, and there are well-documented reports of profound hypotension, myocardial infarction and death when it was used this way. Its label states that the capsules should not be used for the acute reduction of blood pressure. The exception is pregnancy, where oral immediate-release nifedipine is one of the options for acute severe hypertension.
What are the signs of hypertensive encephalopathy?
Hypertensive encephalopathy causes headache, vomiting, blurred vision and confusion, and can progress to seizures, transient cortical blindness or focal deficits. Funduscopy typically shows optic disc edema with flame-shaped hemorrhages and cotton-wool spots. It happens when pressure exceeds the brain's autoregulatory limit, about a mean arterial pressure of 160 mm Hg in many patients and lower after a sudden rise in someone previously normotensive, so vessels dilate, plasma leaks and the brain swells. Head CT excludes hemorrhage.