Hypertension questions love to look “routine”… until one tiny clue flips the diagnosis from essential (primary) HTN to a secondary cause you’re expected to catch. The difference isn’t just academic—Step-style vignettes often hinge on why each wrong answer is wrong. Let’s walk through a classic Q-bank scenario and then dissect every distractor like you would on test day.
Clinical Vignette (Q-bank style)
A 34-year-old woman comes to clinic for repeated elevated blood pressure readings noted at a workplace health fair. She feels well. BP today is 168/104 mm Hg in both arms. BMI is 23 kg/m². She does not smoke. No medications or supplements. Physical exam shows a soft abdominal bruit. Basic metabolic panel shows: Na 141 mEq/L, K 3.1 mEq/L, Cl 101 mEq/L, HCO₃ 28 mEq/L, BUN 12 mg/dL, creatinine 0.8 mg/dL. Urinalysis is normal.
Which of the following is the most likely cause of her hypertension?
A. Essential (primary) hypertension
B. Coarctation of the aorta
C. Pheochromocytoma
D. Primary hyperaldosteronism (Conn syndrome)
E. Renal artery stenosis due to fibromuscular dysplasia
The Correct Answer: E. Renal artery stenosis due to fibromuscular dysplasia
This vignette is built around a few high-yield “secondary HTN” flags:
Why this is renal artery stenosis (FMD)
- Young woman (<40) with severe HTN (stage 2 range)
- Abdominal bruit (renal artery stenosis clue)
- Hypokalemia (secondary hyperaldosteronism via RAAS)
- Normal creatinine and urinalysis (no intrinsic nephritic/nephrotic picture)
Pathophysiology (what the test wants you to think)
Renal hypoperfusion (from renal artery stenosis) → increased renin → increased angiotensin II → increased aldosterone → sodium retention + potassium wasting.
- Expect high renin and high aldosterone in renovascular HTN.
- The hypokalemia here fits mineralocorticoid effect (aldosterone-driven K⁺ secretion).
High-yield diagnosis/management pearls
- Fibromuscular dysplasia (FMD): classically affects young women, involves renal and carotid arteries, and shows a “string of beads” appearance on imaging.
- Screening/diagnosis: often CTA or MRA (renal artery imaging). Duplex ultrasound can be used depending on setting.
- Treatment: BP control (often needs RAAS blockade with caution) and sometimes angioplasty (especially in FMD).
USMLE trap to remember: ACE inhibitors can increase creatinine in renal artery stenosis, especially bilateral disease or solitary kidney stenosis (drop in GFR due to loss of efferent arteriolar constriction).
Essential vs Secondary Hypertension: How to Decide Fast
Essential (primary) hypertension
- Most common (~90–95% of cases)
- Usually gradual onset (middle age and up), often associated with:
- obesity, high sodium diet
- family history
- metabolic syndrome
When to suspect secondary hypertension (high-yield triggers)
- Age <30 with no risk factors
- Abrupt onset or rapid worsening
- Resistant HTN (uncontrolled on 3 meds, including a diuretic)
- Hypokalemia without diuretics
- Episodic symptoms (palpitations, sweating, headaches)
- Abdominal bruit
- End-organ damage out of proportion to duration
Distractor Breakdown: Why Each Wrong Answer Is Wrong (and when it would be right)
A. Essential (primary) hypertension — Wrong here
Essential HTN is a diagnosis of exclusion. This patient has multiple secondary clues:
- young
- severe
- abdominal bruit
- hypokalemia
When essential HTN is most likely:
- Middle-aged patient, gradual rise in BP
- No specific endocrine/renal clues
- Normal potassium and no bruits
- Risk factors (obesity, family history, high sodium intake)
B. Coarctation of the aorta — Wrong here
Coarctation is a classic Step diagnosis but has a very specific physical exam pattern.
What you’d expect in coarctation:
- Upper extremity HTN with lower extremity hypotension
- Delayed/weak femoral pulses (radiofemoral delay)
- Possible rib notching on CXR (collateral intercostal arteries)
- Often diagnosed in childhood/young adulthood; associated with bicuspid aortic valve and Turner syndrome
Why it doesn’t fit:
- BP is elevated in both arms, but there’s no mention of leg BP differences or diminished femoral pulses
- Hypokalemia is not a classic coarctation clue
C. Pheochromocytoma — Wrong here
Pheochromocytoma is a catecholamine-secreting tumor (adrenal medulla) that produces a distinctive symptom cluster.
Classic presentation:
- Episodic headaches
- Sweating
- Palpitations
- Paroxysmal HTN (can be sustained too), pallor, tremor
- Diagnosis: plasma free metanephrines or 24-hour urine metanephrines
Why it doesn’t fit:
- She feels well—no episodic sympathetic surges described
- Abdominal bruit + hypokalemia points much more strongly to RAAS-mediated disease than catecholamines
Test-day nuance: Pheochromocytoma can cause hyperglycemia (catecholamine-driven), but it does not typically cause isolated hypokalemia via aldosterone.
D. Primary hyperaldosteronism (Conn syndrome) — Tempting, but wrong here
Conn syndrome causes autonomous aldosterone secretion → HTN + hypokalemia + metabolic alkalosis.
Classic labs:
- Low renin
- High aldosterone
- Elevated aldosterone-to-renin ratio (ARR)
Why it’s not the best answer here:
- The abdominal bruit strongly suggests renovascular disease.
- In renovascular HTN: renin is high (kidney senses low perfusion).
- In Conn: renin is suppressed due to volume expansion.
When Conn syndrome is correct:
- HTN + hypokalemia without diuretic use
- No bruit
- Consider adrenal adenoma or bilateral adrenal hyperplasia
- Confirmatory testing: salt loading (per question style) and imaging after biochemical diagnosis
Quick Comparison Table: High-Yield Secondary HTN Patterns
| Condition | Key Clues | Renin | Aldosterone | Other High-Yield Notes |
|---|---|---|---|---|
| Renal artery stenosis (FMD) | Young woman, abdominal bruit, sudden/severe HTN | ↑ | ↑ | “String of beads,” may respond to angioplasty |
| Renal artery stenosis (atherosclerosis) | Older man, PAD/CAD risk, abdominal bruit | ↑ | ↑ | ACEi/ARB can ↑Cr (esp bilateral) |
| Primary hyperaldosteronism | HTN + hypoK, metabolic alkalosis | ↓ | ↑ | ARR elevated; adrenal adenoma/hyperplasia |
| Pheochromocytoma | Episodic HA/sweats/palpitations | — | — | ↑ metanephrines; treat with alpha-blockade first |
| Coarctation | Arm HTN, weak femoral pulses, leg hypoTN | ↑ (variable) | ↑ (variable) | Rib notching; Turner, bicuspid AV |
“Why Every Answer Choice Matters”: Your Test-Day Algorithm
When you see hypertension, force yourself to scan for secondary clues before settling on essential HTN:
- Age + severity: young with stage 2 HTN → think secondary
- Electrolytes: hypokalemia → think aldosterone (primary vs secondary)
- Symptoms: episodic adrenergic spells → pheo
- Exam: abdominal bruit → renovascular; pulse/BP discrepancy → coarctation
- Medication/substances (common Step add-ons): NSAIDs, OCPs, steroids, stimulants, licorice
High-Yield Takeaways (what to memorize)
- Most HTN is essential, but Step questions are often secondary because clues are embedded.
- Renal artery stenosis:
- High renin + high aldosterone
- Abdominal bruit
- FMD in young women; atherosclerosis in older patients
- Primary hyperaldosteronism:
- Low renin + high aldosterone
- Hypokalemia and metabolic alkalosis are classic
- Pheochromocytoma: episodic catecholamine symptoms; diagnose with metanephrines; treat with alpha-blockade first
- Coarctation: upper > lower extremity BP + delayed femoral pulses
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
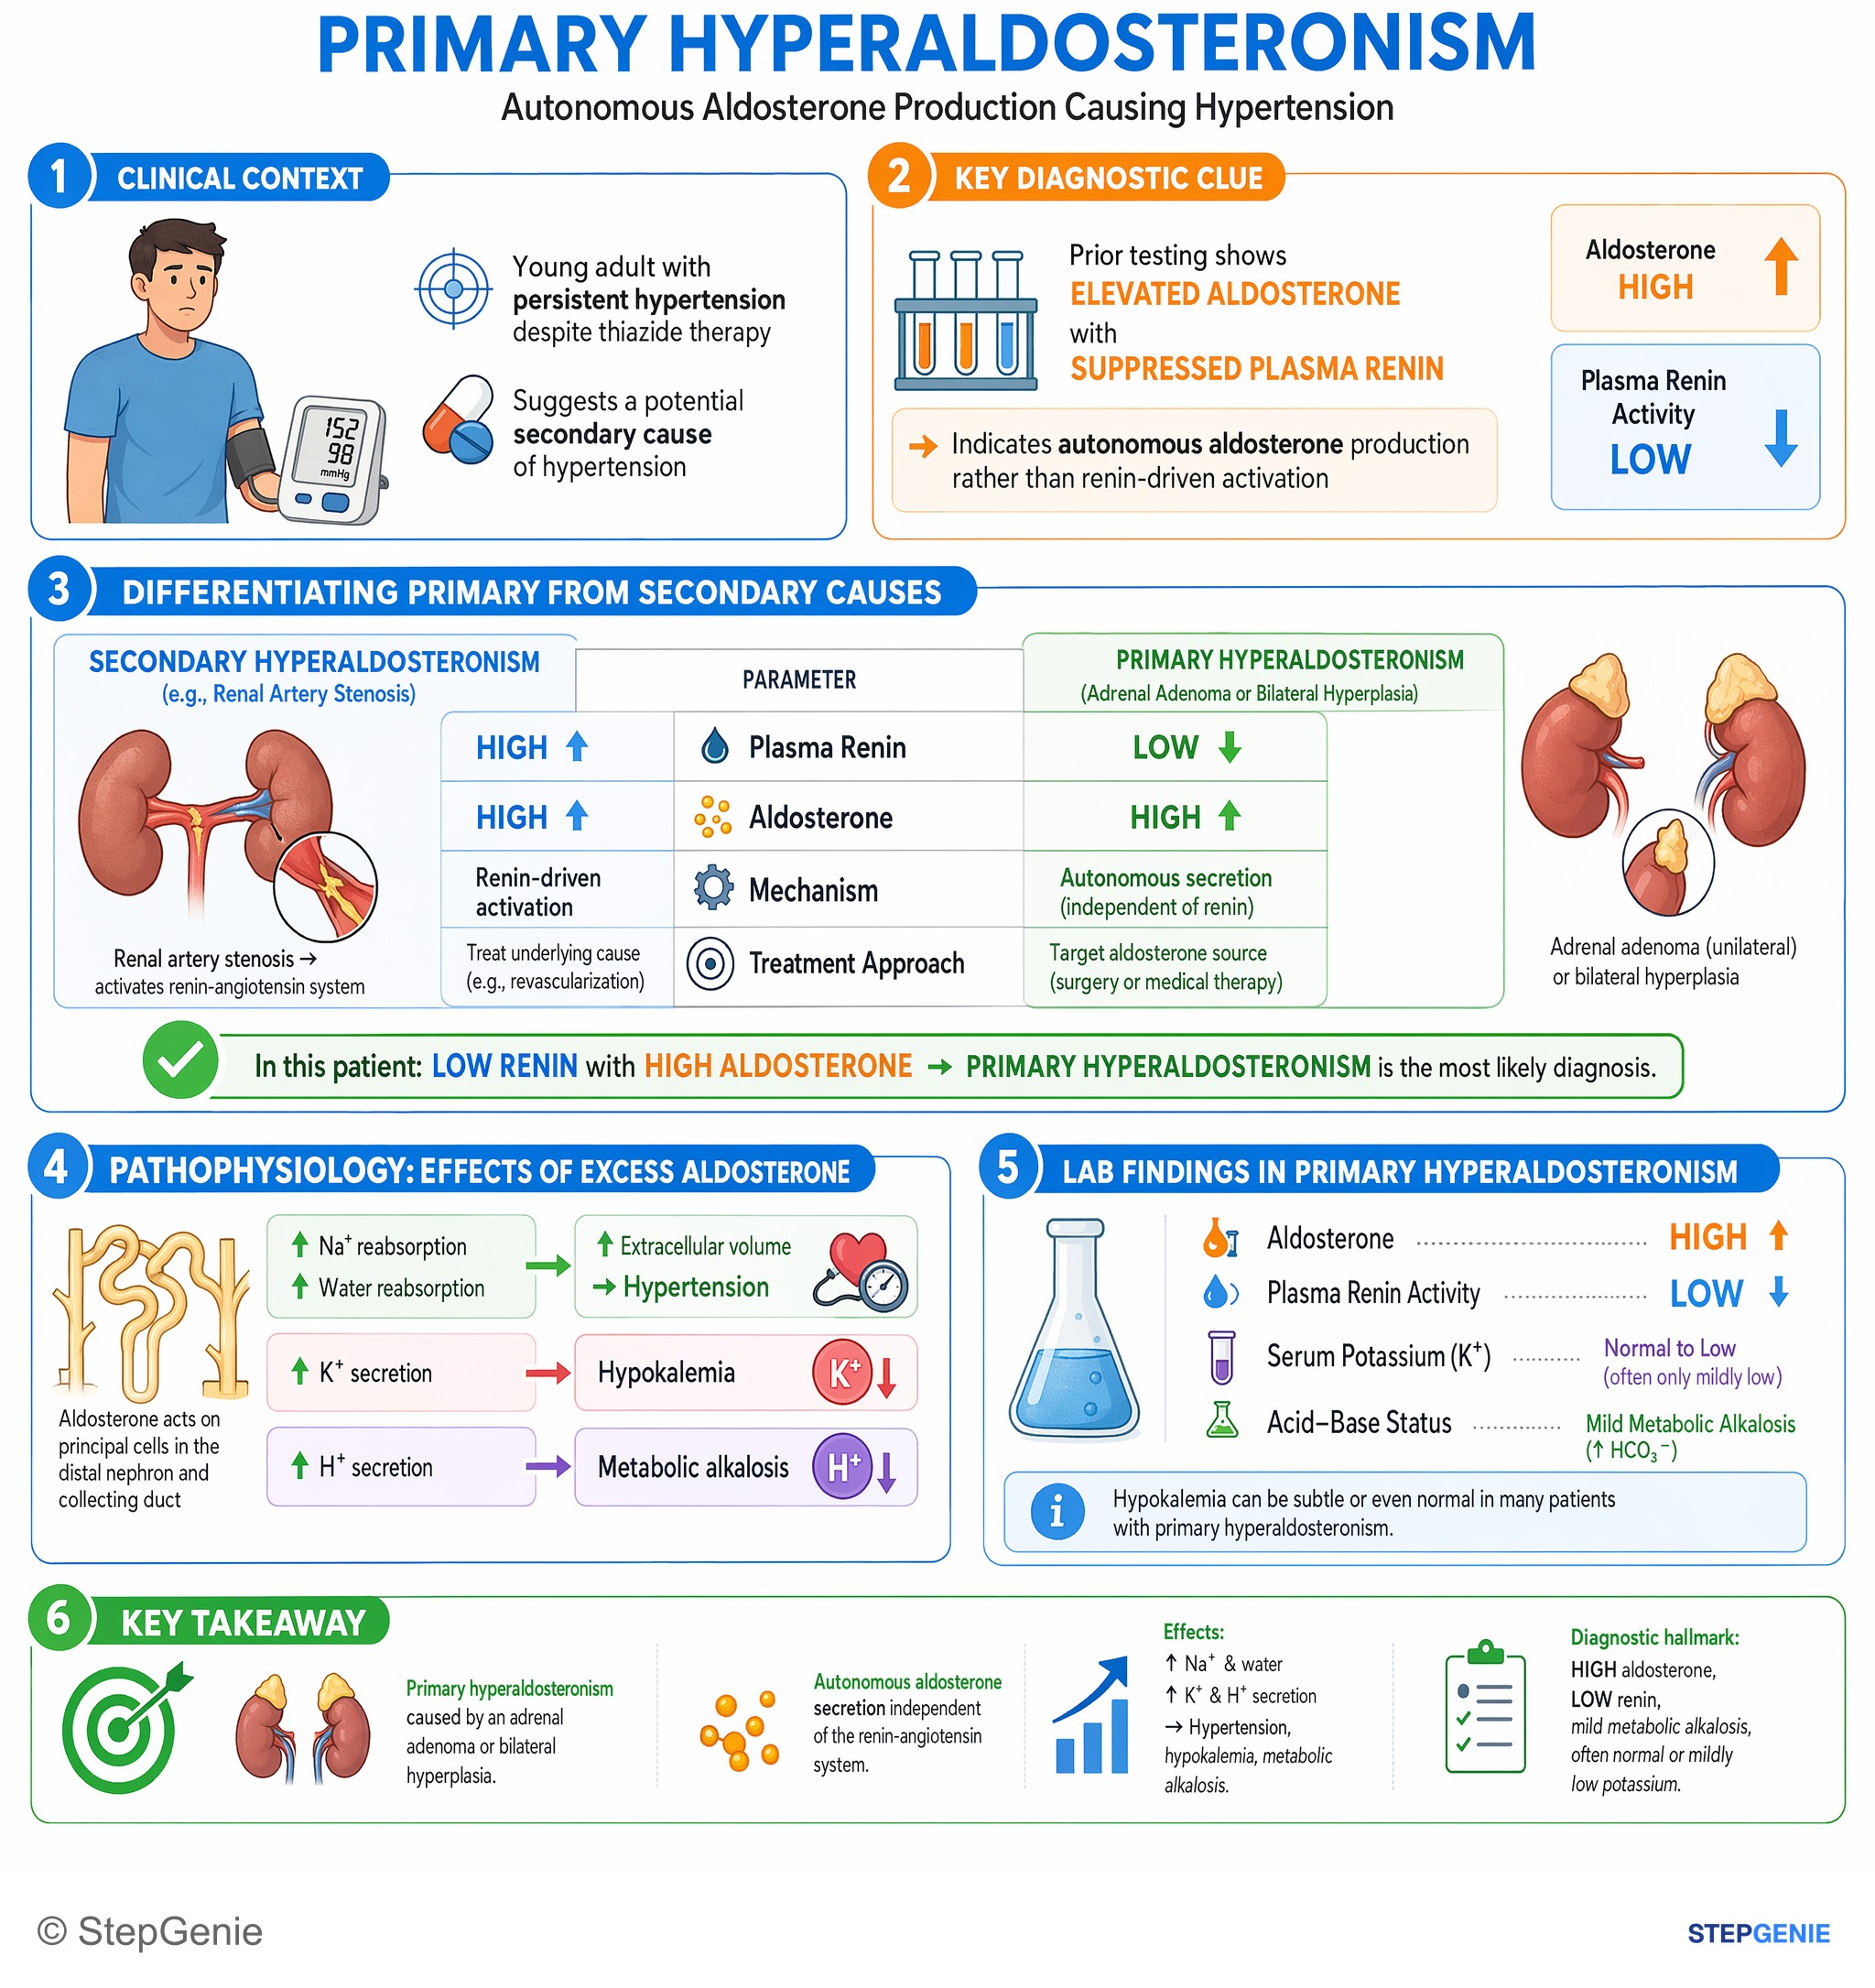
Primary hyperaldosteronism: autonomous aldosterone → hypertension with high aldosterone, low renin, mild metabolic alkalosis, often only…
USMLE Step 1Frequently Asked Questions
How do you tell renal artery stenosis from essential hypertension in a young patient with high blood pressure?
Renal artery stenosis is more likely when severe hypertension appears in a young patient and is accompanied by specific secondary clues such as an abdominal bruit and hypokalemia without diuretic use. Essential hypertension is usually a diagnosis of exclusion, tends to have a more gradual onset in middle age, and is more often associated with obesity, family history, high sodium intake, or metabolic syndrome rather than bruits or low potassium.
Why does renal artery stenosis due to fibromuscular dysplasia cause hypokalemia?
Renal artery stenosis causes hypokalemia by activating the renin-angiotensin-aldosterone system. Reduced renal perfusion increases renin, which raises angiotensin II and then aldosterone. The aldosterone effect leads to sodium retention and potassium wasting, so renovascular hypertension typically has high renin and high aldosterone. In a young woman with severe hypertension and an abdominal bruit, that pattern strongly supports fibromuscular dysplasia.
How do you tell renovascular hypertension from primary hyperaldosteronism on a vignette?
The key difference is the renin level and the presence of renovascular clues. Renovascular hypertension causes high renin and high aldosterone because the kidney senses low perfusion, while primary hyperaldosteronism causes high aldosterone with suppressed renin due to volume expansion. An abdominal bruit strongly points toward renovascular disease, whereas Conn syndrome is more likely when hypertension and hypokalemia occur without a bruit.
What clues point to fibromuscular dysplasia as the cause of secondary hypertension?
Fibromuscular dysplasia is suggested by a young woman with severe hypertension, an abdominal bruit, and hypokalemia from secondary hyperaldosteronism. It classically affects young women, commonly involves the renal and carotid arteries, and can show a string-of-beads appearance on imaging. CTA or MRA is often used for diagnosis, and treatment may include blood pressure control and sometimes angioplasty.
Why isn’t pheochromocytoma or coarctation the best answer in this hypertension vignette?
Pheochromocytoma is less likely because its classic presentation is episodic headaches, sweating, palpitations, and sympathetic surges, which are absent here. Coarctation is less likely because it typically causes upper-extremity hypertension with lower-extremity hypotension and delayed or weak femoral pulses. In contrast, an abdominal bruit plus hypokalemia fits a renin-angiotensin-aldosterone–mediated renovascular process much better.