Ebstein anomaly is apical (downward) displacement of the septal and posterior (inferior) tricuspid leaflets into the right ventricle, which "atrializes" part of the RV and causes tricuspid regurgitation (TR). The classic stem is a cyanotic newborn (right-to-left shunting through a patent foramen ovale or ASD, because right atrial pressure is high) with a holosystolic murmur at the left lower sternal border, a widely split S1, massive "box-shaped" cardiomegaly, tall P waves and right bundle branch block, and a mother who took lithium. Older children and adults present with WPW (right-sided accessory pathways) and atrial arrhythmias. Lithium's link to cardiac defects holds up but is far smaller than old registry data suggested: in a 2017 US cohort of 1.3 million pregnancies, first-trimester exposure raised cardiac malformations from 1.15% to 2.41% (adjusted risk ratio 1.65).
The Q-bank vignette
A 2-day-old boy born at 39 weeks becomes cyanotic. Oxygen saturation is 78% on room air and 84% on 100% oxygen. His mother has bipolar I disorder and took a mood stabilizer throughout pregnancy. He has a widely split S1 with a loud second component, a grade 3/6 holosystolic murmur at the left lower sternal border, and a liver edge 3 cm below the right costal margin. Chest x-ray shows massive, globular cardiomegaly with reduced pulmonary vascular markings. The ECG shows tall P waves in leads II and V1 and a right bundle branch block pattern.
Which of the following best describes the underlying defect?
- A. Apical displacement of the septal and posterior tricuspid leaflets with atrialization of the right ventricle
- B. Absence of the tricuspid valve with a hypoplastic right ventricle
- C. Anterior deviation of the infundibular septum with a large malalignment VSD
- D. Aorta arising from the right ventricle and pulmonary artery from the left ventricle
- E. A defect in the fossa ovalis region of the atrial septum
Answer: A, Ebstein anomaly. TR explains the murmur, liver congestion and huge right atrium; the high RA pressure pushes deoxygenated blood across the foramen ovale, so oxygen barely helps. The "mood stabilizer" is the lithium clue.
Why the findings fit: anatomy to exam clue
| Finding in the stem | Mechanism |
|---|---|
| Cyanosis, little response to oxygen | RA pressure exceeds LA pressure, so blood shunts right to left through a PFO or ASD |
| Holosystolic murmur, left lower sternal border | Tricuspid regurgitation through the malformed valve |
| Widely split S1, loud second component ("sail sound") | Delayed closure of the large, sail-like anterior tricuspid leaflet |
| Massive cardiomegaly ("box-shaped" or "wall-to-wall" heart) | Huge right atrium plus the atrialized portion of the RV |
| Tall P waves in II and V1 (giant "Himalayan" P waves in some) | Right atrial enlargement |
| Right bundle branch block, first-degree AV block | Delayed RV activation; slow conduction through the enlarged atrium |
| Delta wave, short PR, SVT | Accessory pathways, usually right-sided and sometimes multiple |
| Hepatomegaly, edema | Right-sided heart failure from TR |
| Cyanosis worst in the first days of life | High newborn pulmonary vascular resistance limits forward flow from the small functional RV (in severe cases the pulmonary valve does not open at all: "functional pulmonary atresia"); it eases as resistance falls |
The anatomy in one line: the tricuspid leaflets, mainly the septal and posterior ones, fail to delaminate from the RV wall, so the functional valve orifice sits deep in the ventricle. The anterior leaflet keeps its normal annular attachment but is large and redundant. Everything between the true annulus and the displaced leaflets behaves like atrium. Echocardiography makes the diagnosis: apical displacement of the septal leaflet of at least 8 mm/m² plus an elongated, sail-like anterior leaflet.
Ebstein vs the look-alikes
| Lesion | Core anatomy | Heart sounds and murmur | ECG | Chest x-ray |
|---|---|---|---|---|
| Ebstein anomaly | Displaced septal and posterior tricuspid leaflets; atrialized RV | Widely split S1; holosystolic TR murmur at the left lower sternal border | Tall P waves, RBBB, first-degree AV block; WPW in some | Massive, globular (box-shaped) heart |
| Tricuspid atresia | No tricuspid valve; hypoplastic RV; needs an ASD plus a VSD or PDA | Single S1; VSD murmur | Left axis deviation and LVH | Normal or slightly enlarged heart, reduced pulmonary markings |
| Tetralogy of Fallot | Anterior deviation of the conal septum: VSD, RV outflow obstruction, overriding aorta, RVH | Harsh systolic ejection murmur at the left upper sternal border; single S2 | RVH, right axis deviation | Boot-shaped heart |
| D-transposition | Aorta from the RV, pulmonary artery from the LV; parallel circulations | Often no murmur; single loud S2 | Right axis deviation, RVH, or normal for age | Egg on a string |
| Secundum ASD | Defect in the fossa ovalis | Fixed, widely split S2; ejection murmur at the upper left sternal border | Right axis deviation, rSR′ in V1 | Enlarged RA and RV, prominent pulmonary artery, increased pulmonary markings |
Why every other answer choice is wrong
- B, tricuspid atresia: also cyanosis with an obligatory right-to-left atrial shunt, but S1 is single (there is no tricuspid valve to close) and the ECG shows left axis deviation with LVH, because the left ventricle does all the work. The heart is not massively enlarged.
- C, tetralogy of Fallot: the murmur is a harsh ejection murmur at the upper left sternal border from RV outflow obstruction, the heart is boot-shaped rather than massively enlarged, and the ECG shows RV hypertrophy. Hypercyanotic "tet" spells peak at 2–4 months of age.
- D, D-transposition: profound cyanosis within hours of birth with an otherwise unremarkable exam, a single loud S2 and often no murmur. It needs prostaglandin E1, sometimes balloon atrial septostomy, then the arterial switch in the first week.
- E, secundum ASD: a left-to-right shunt, so no cyanosis in a newborn. It splits S2 (fixed), not S1, and makes a flow murmur at the upper left sternal border. Cyanosis appears only if shunt reversal develops years later, as in Eisenmenger syndrome. Here the atrial opening is only the escape valve for high RA pressure.
Murmur location, timing and maneuvers for all of these are compared in the heart murmurs USMLE table.
Lithium and Ebstein anomaly: how big is the risk?
- Where the scare came from: 1970s reports from the voluntary International Register of Lithium Babies suggested Ebstein anomaly was about 400 times more common after prenatal lithium exposure. Voluntary registries of this kind most likely overestimated the risk.
- The landmark cohort (Patorno et al., NEJM 2017; 1,325,563 pregnancies, 663 first-trimester lithium exposures): cardiac malformations occurred in 2.41% of exposed vs 1.15% of unexposed infants (adjusted RR 1.65, 95% CI 1.02–2.68). Risk rose with dose (RR 3.22 above 900 mg/day). Right ventricular outflow tract obstruction defects, the group that includes Ebstein anomaly, occurred in 0.60% vs 0.18%, and none of the exposed cases was coded specifically as Ebstein anomaly.
- Later data point the same way: a 2020 meta-analysis found a pooled odds ratio of 1.86 for cardiac malformations, and experts summarizing the evidence describe a modest relative increase with a low absolute risk.
- The FDA label says the increased risk of cardiac malformations is likely small, though the data are insufficient to establish a drug-associated risk, and advises considering fetal echocardiography at 16–20 weeks after first-trimester exposure.
- For the exam: lithium is still the teratogen paired with Ebstein anomaly. In counseling, the risk is weighed against the high relapse risk of stopping lithium. Lithium's other toxicities are in the lithium guide.
Arrhythmias: WPW and beyond
- Pre-excitation is more common in Ebstein anomaly than in any other congenital heart disease. Merck puts WPW at about 20% of patients; other estimates range widely (MedlinePlus: 5–25%). Pathways are usually right-sided (septal and posterior), and 13–33% of patients have more than one pathway (one review).
- Atrial arrhythmias are common in adults: in one series of 682 patients, 18% had atrial fibrillation and 21% atrial flutter or atrial tachycardia.
- The PR interval can go either way: prolonged (first-degree AV block, reported in 42% in one review) from slow conduction through the huge atrium, or short with a delta wave when a pathway pre-excites the ventricle.
- Treatment: catheter ablation of accessory pathways; pre-excited atrial fibrillation follows the usual WPW rules.
Management
- Severely cyanotic newborn: prostaglandin E1 keeps the ductus arteriosus open (supplying pulmonary blood flow) until pulmonary vascular resistance falls and the small functional RV can take over. Some need a Blalock-Thomas-Taussig shunt or more complex surgery.
- Symptoms, worsening TR or enlarging right heart after early infancy: surgical repair, often the cone reconstruction of the tricuspid valve, closing any atrial defect at the same time. Some patients need tricuspid valve replacement.
- Cyanosis with only modest valve dysfunction: transcatheter closure of the atrial communication.
- Arrhythmias: ablation of accessory pathways.
Key takeaways
- Anatomy: septal and posterior tricuspid leaflets displaced toward the apex, atrialized RV, TR, huge right atrium.
- Cyanosis comes from right-to-left shunting through a PFO or ASD driven by high RA pressure; it can improve as newborn pulmonary resistance falls.
- Exam clues: widely split S1, holosystolic TR murmur at the left lower sternal border, box-shaped heart, tall P waves, RBBB.
- Associations: WPW with right-sided (sometimes multiple) pathways, atrial arrhythmias, ASD/PFO, pulmonary stenosis, and maternal lithium.
- Lithium risk is modest: cardiac malformations about 2.4% vs 1.2% (adjusted RR 1.65) in a 1.3-million-pregnancy cohort, not the old 400-fold estimate; consider fetal echocardiography after first-trimester exposure.
- Versus tricuspid atresia: single S1 and left axis deviation with LVH.
Sources
- Ebstein Anomaly — Merck Manual Professional Edition
- Ebstein anomaly — MedlinePlus Medical Encyclopedia (2026)
- Dalakoti M, et al. Electrocardiography findings and clinical presentation in Ebstein's anomaly — Singapore Medical Journal (2019)
- Hsiung I, et al. Electrophysiologic Considerations in Adult Patients with Ebstein's Anomaly — Journal of Personalized Medicine (2024)
- Lithium carbonate prescribing information, section 8.1 Pregnancy — DailyMed
- Lithium During Pregnancy and Risk of Cardiovascular Malformations (Patorno et al., NEJM 2017) — MGH Center for Women's Mental Health (2017)
- Lithium Use in Pregnancy and the Risk of Adverse Perinatal Outcomes — MGH Center for Women's Mental Health (2026)
- Tricuspid Atresia — Merck Manual Professional Edition
- Tetralogy of Fallot — Merck Manual Professional Edition
- Transposition of the Great Arteries (TGA) — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
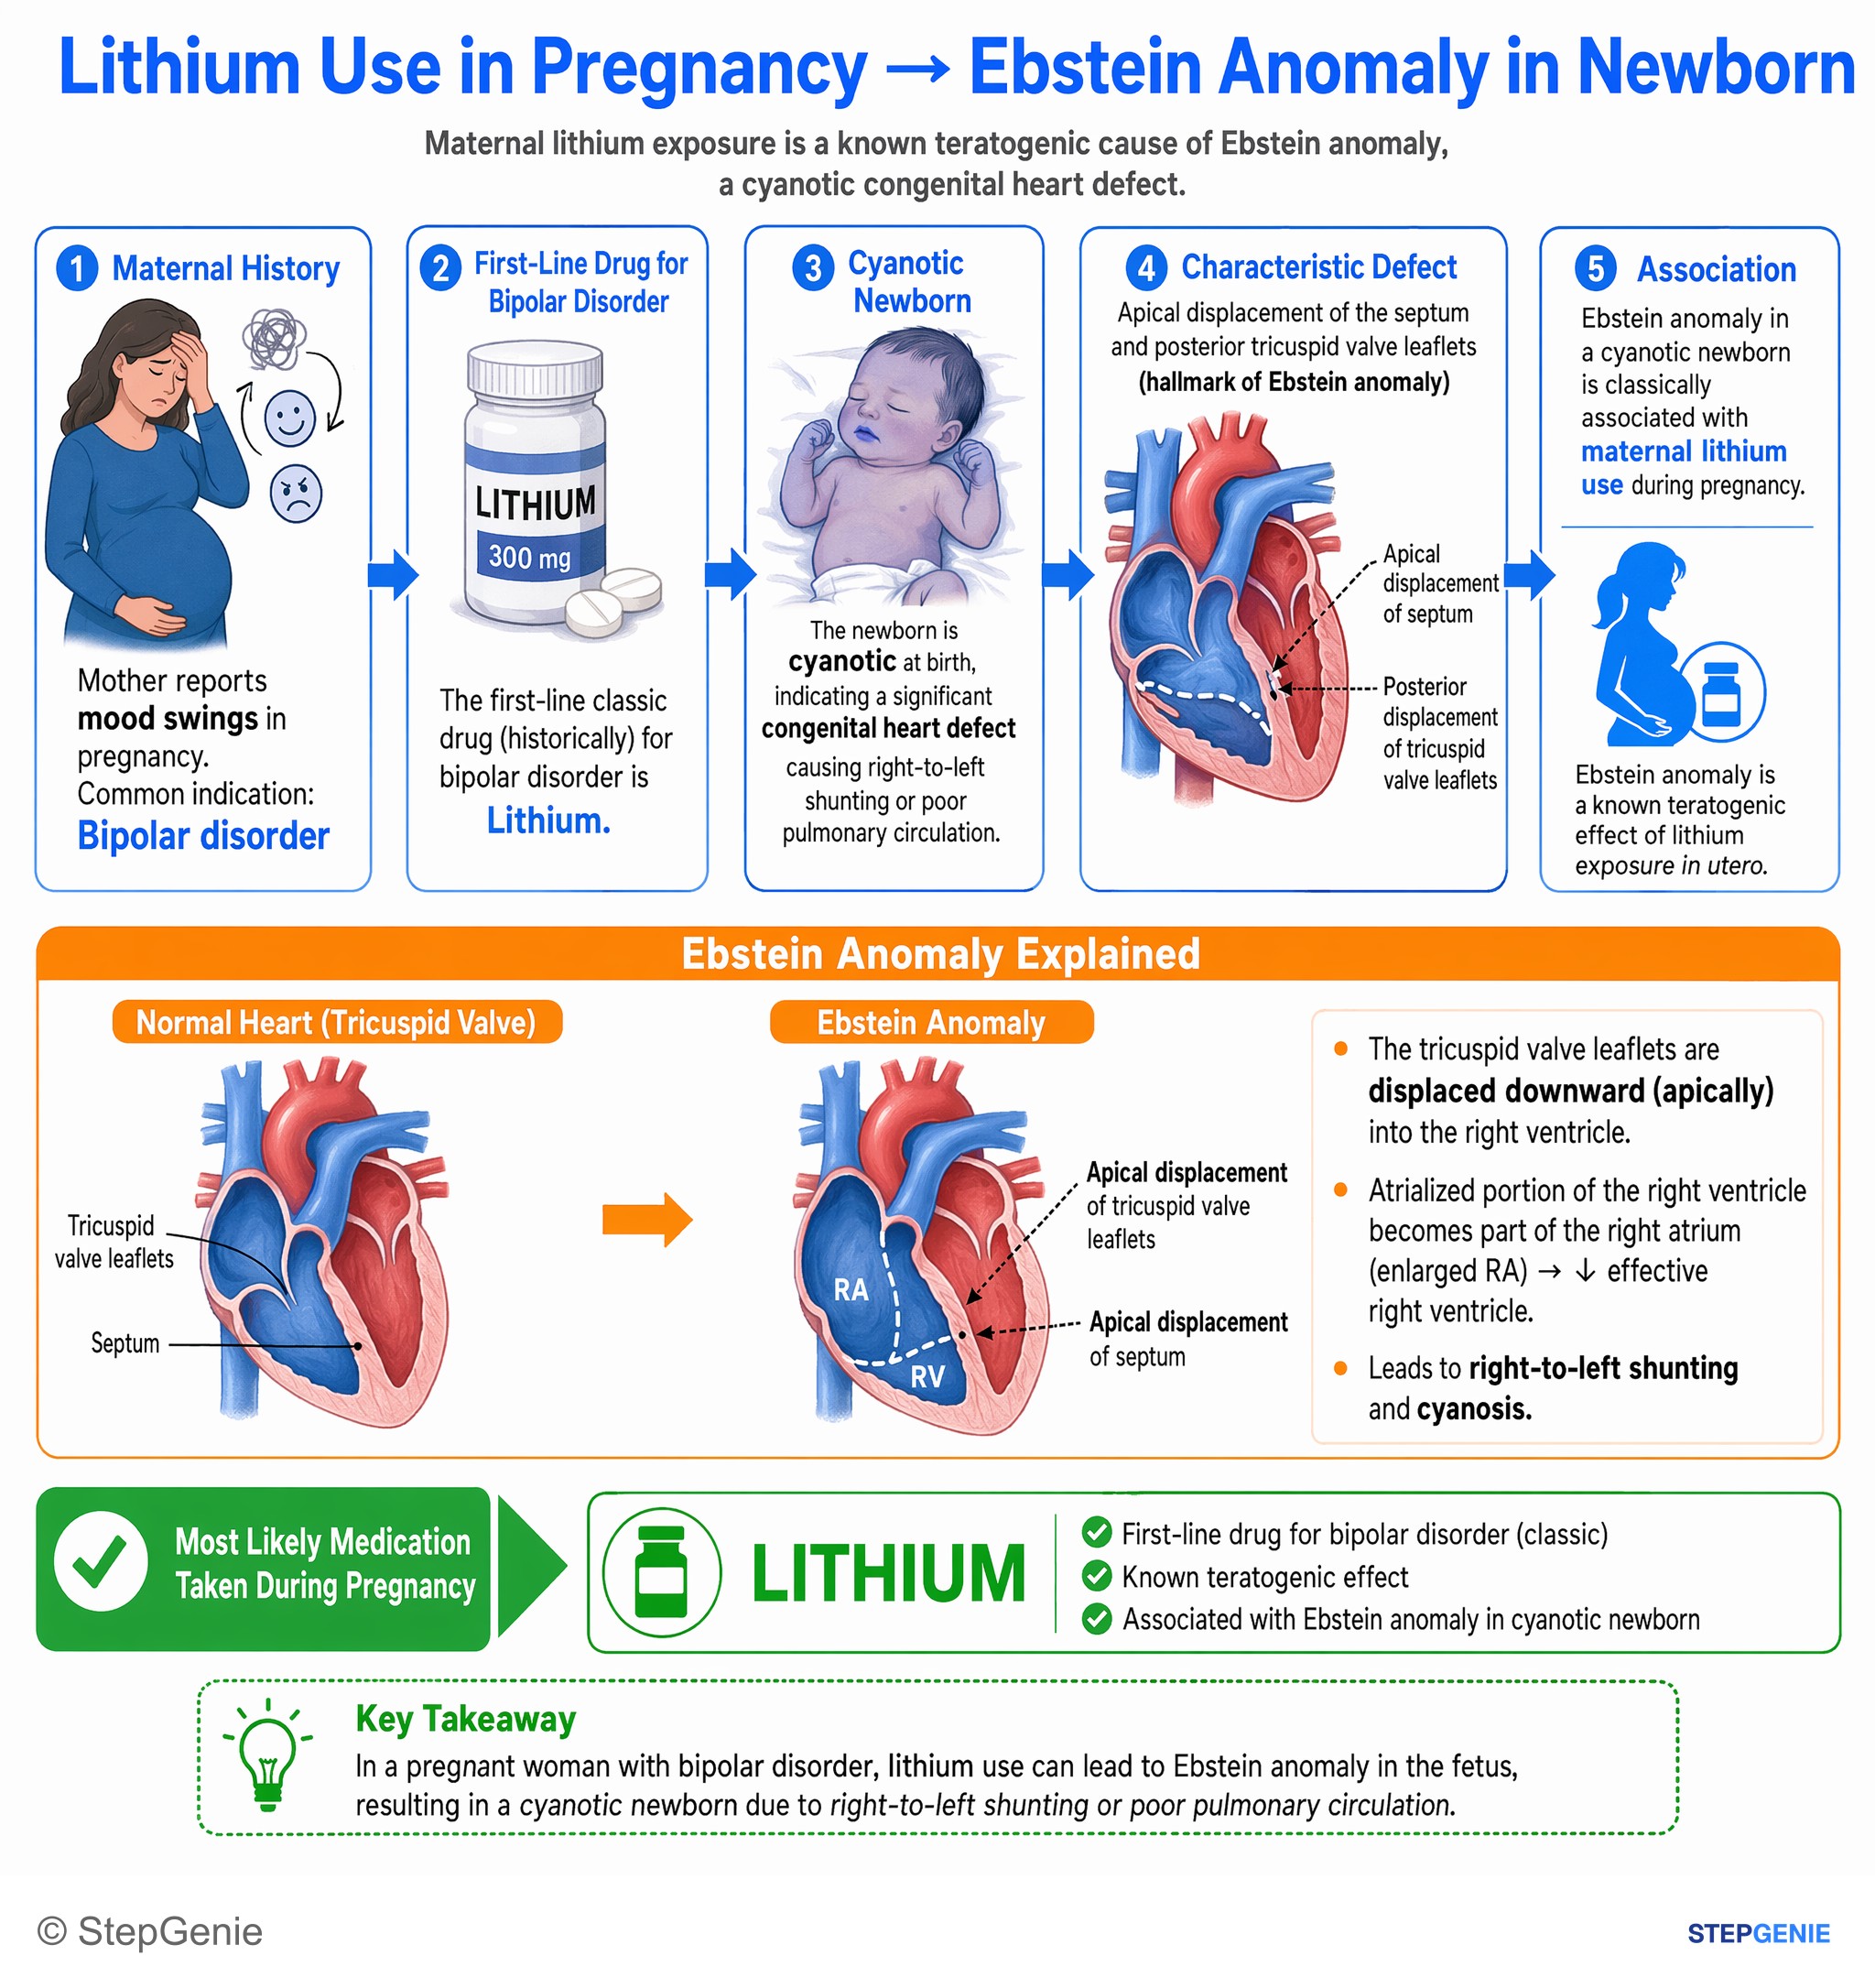
Ebstein anomaly (apical displacement of tricuspid valve) in a cyanotic newborn is classically associated with maternal lithium use during…
USMLE Step 1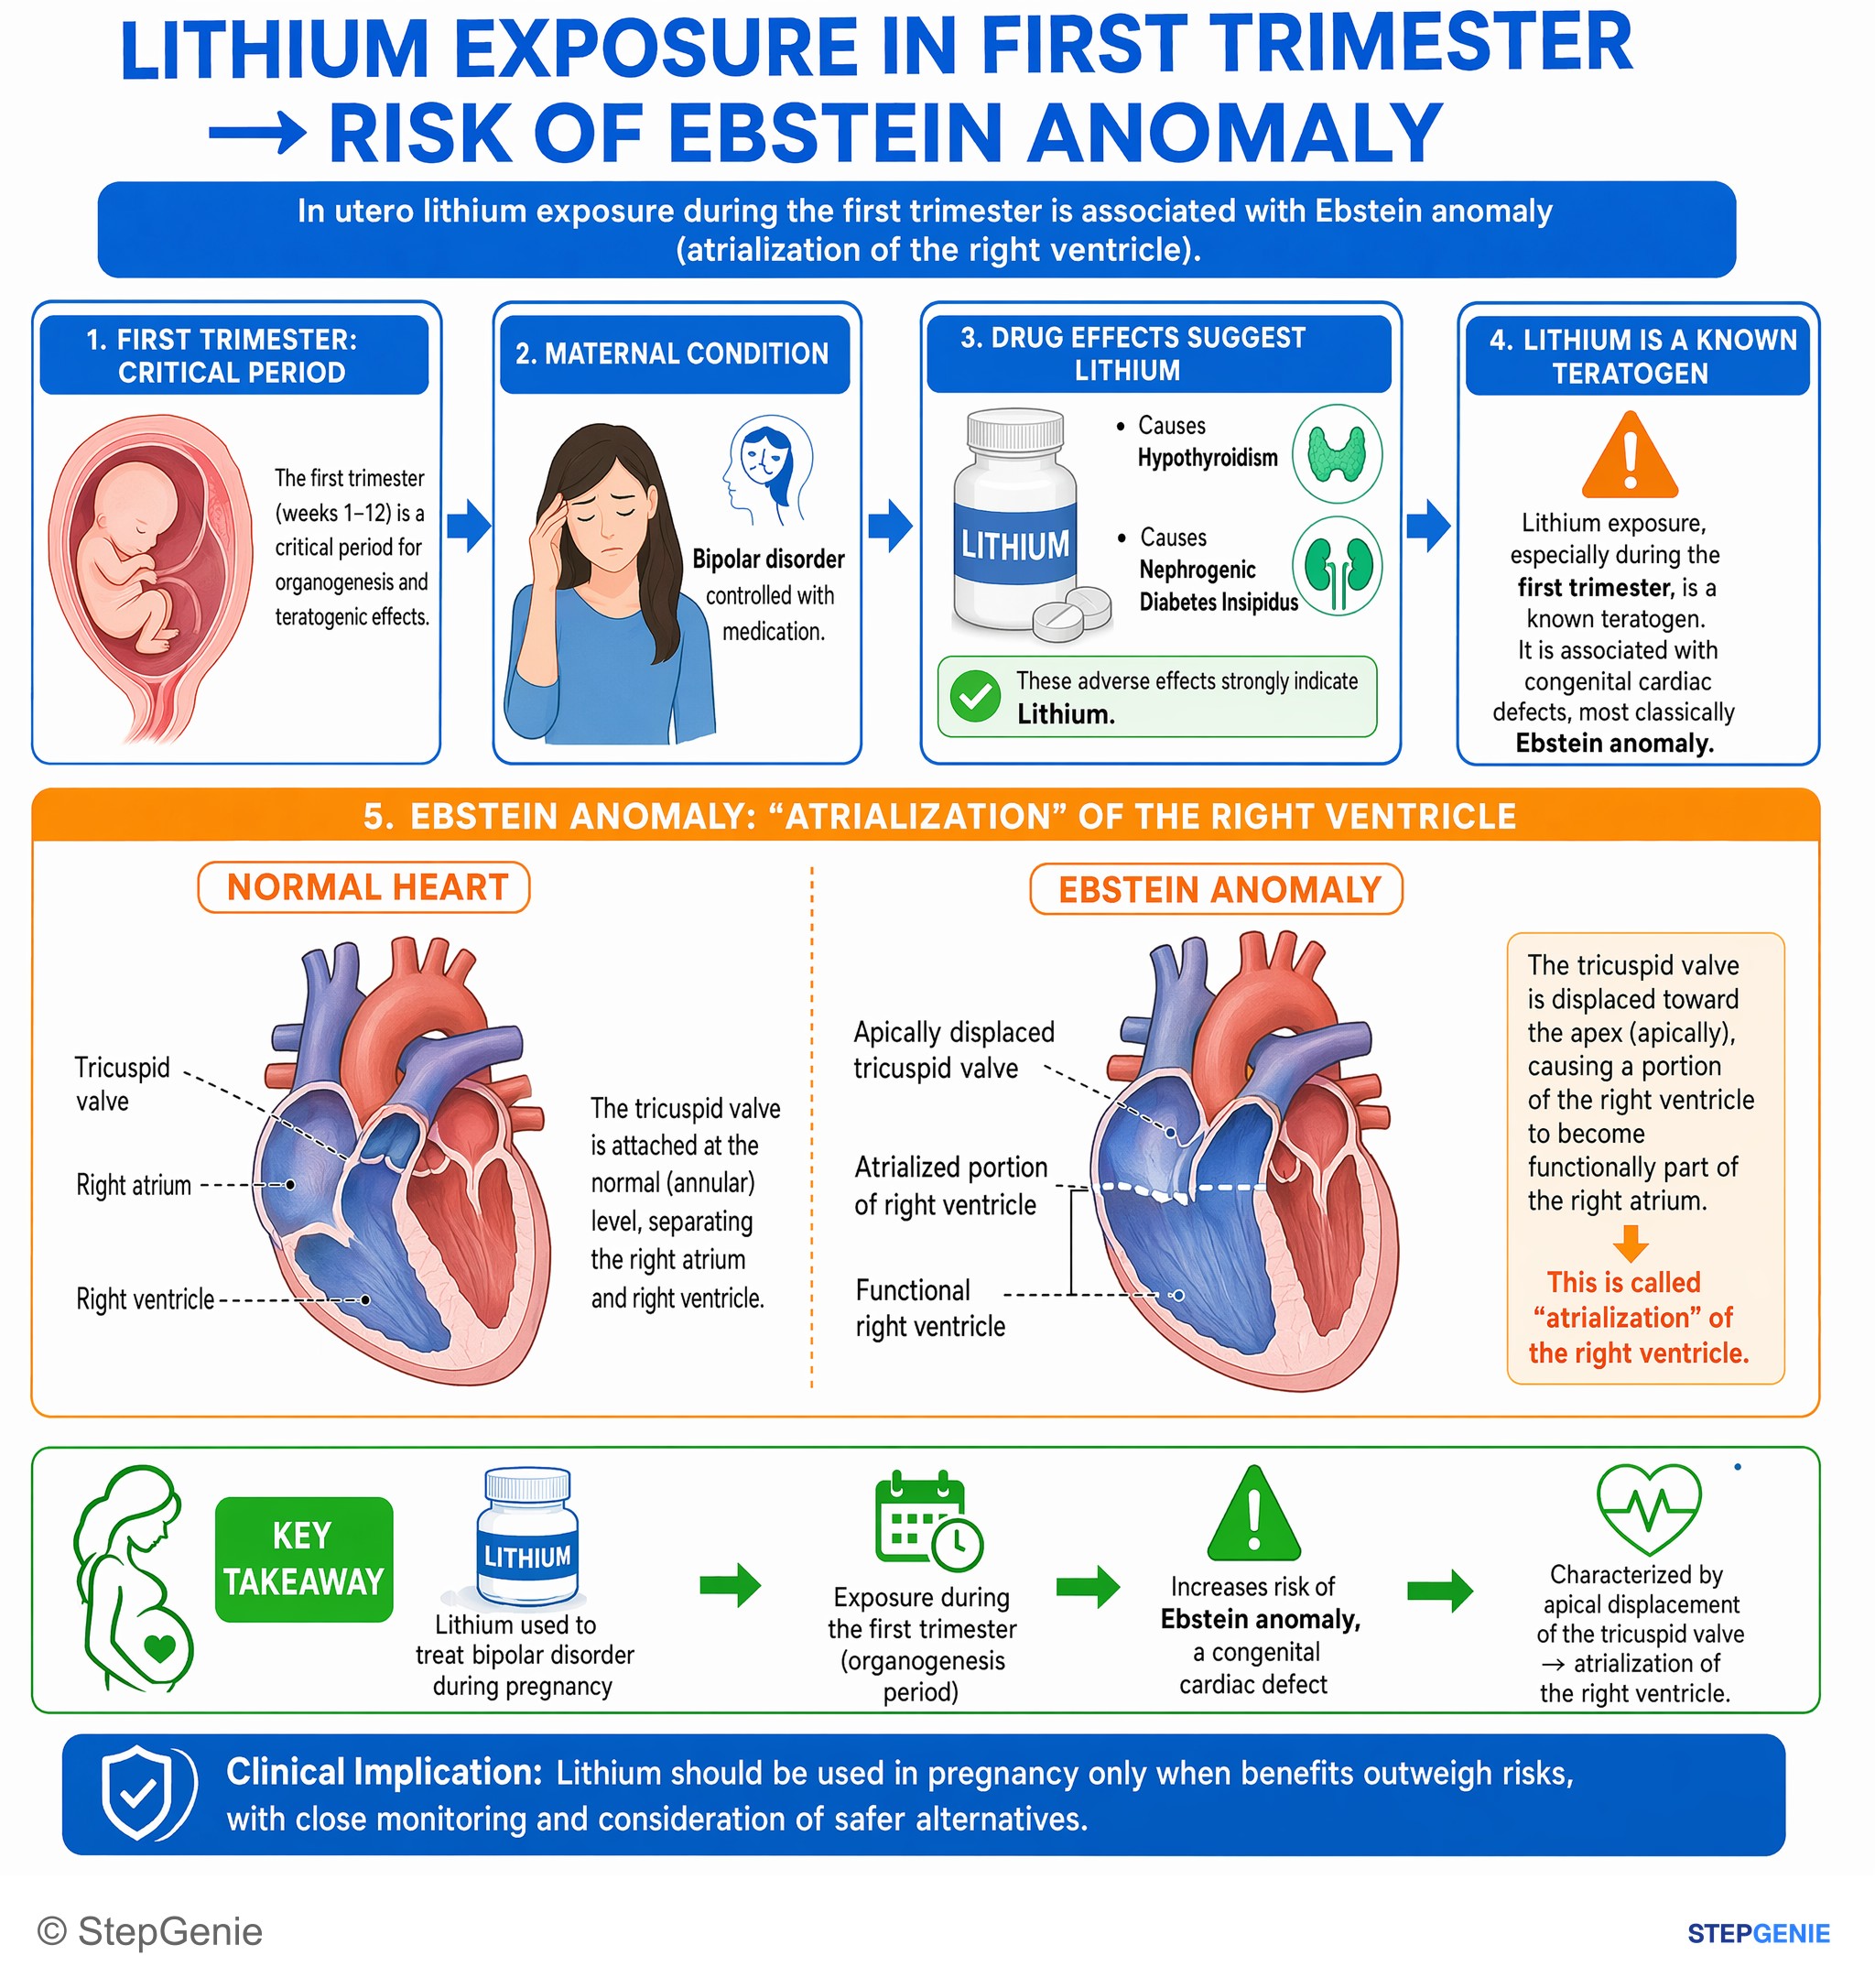
Ebstein anomaly (atrialization of right ventricle) is associated with in utero lithium exposure used for bipolar disorder during pregnancy.
USMLE Step 1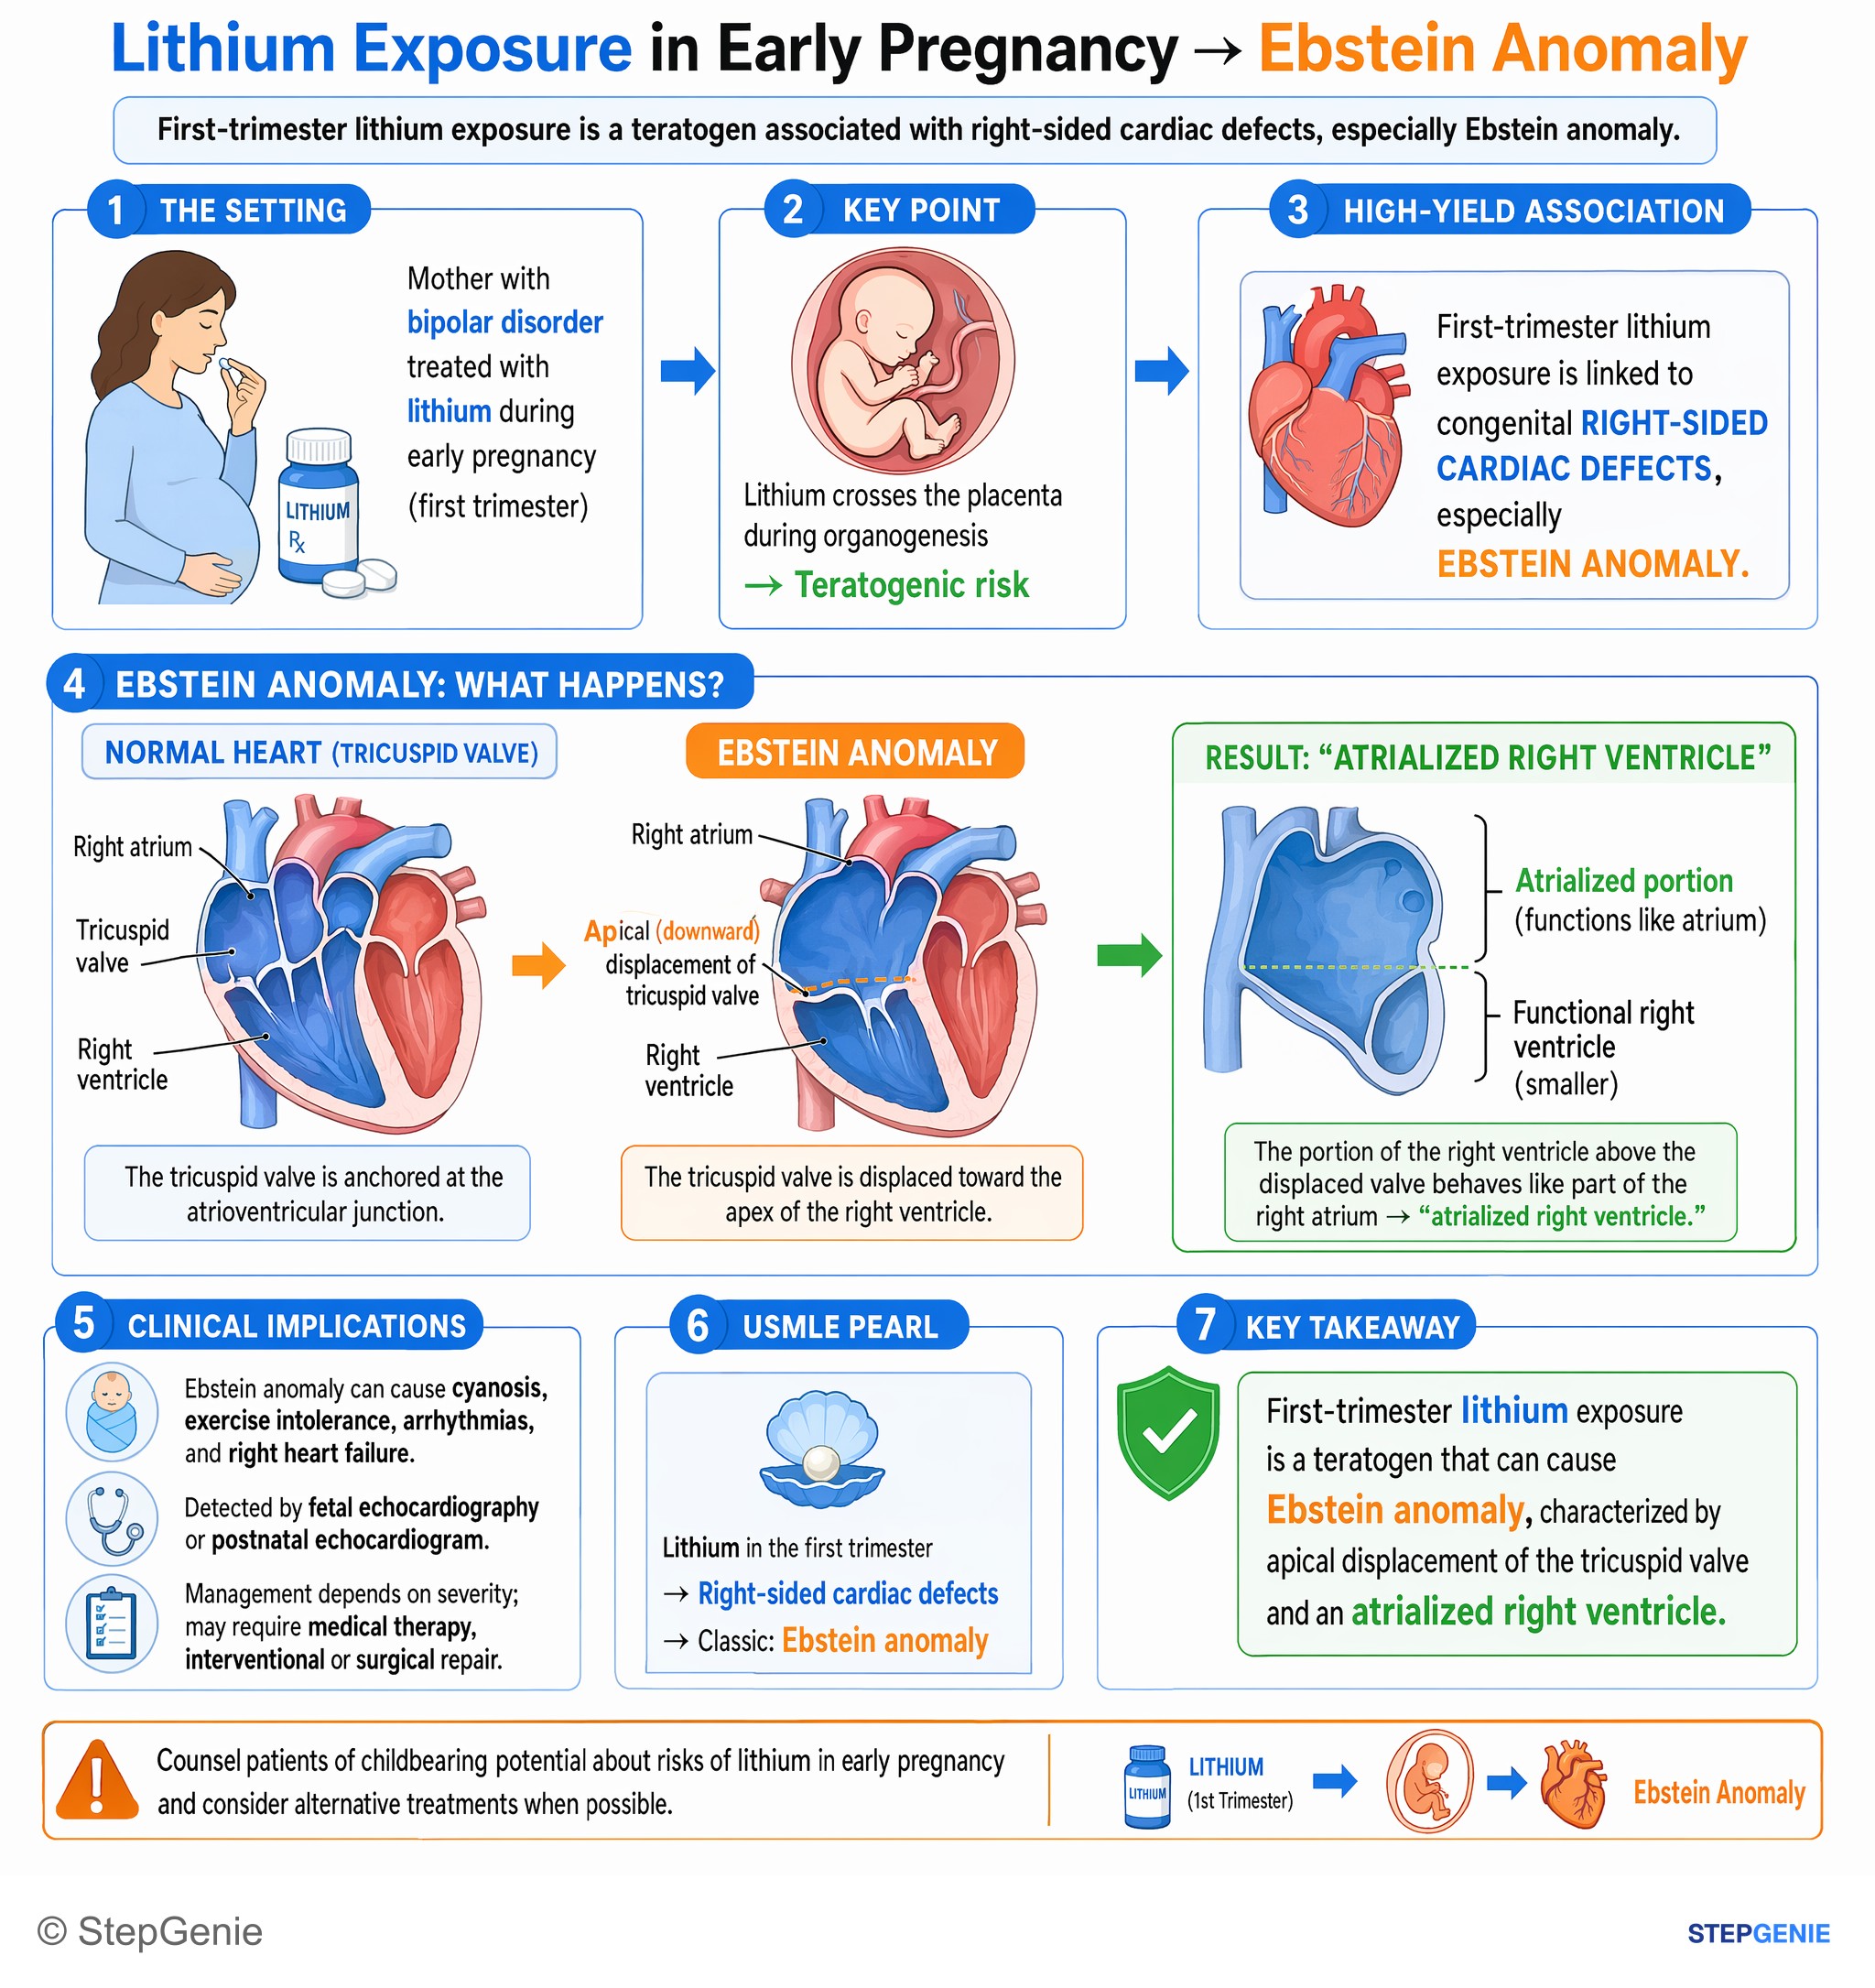
Ebstein anomaly from first-trimester lithium exposure causes apical displacement of the tricuspid valve and an atrialized right ventricle…
USMLE Step 2Frequently Asked Questions
What is Ebstein anomaly?
Ebstein anomaly is a rare congenital heart defect, under 1% of congenital heart disease, in which the septal and posterior leaflets of the tricuspid valve are displaced toward the apex of the right ventricle. The part of the ventricle above the displaced leaflets functions as atrium, the valve leaks, and the right atrium becomes very large. Severity ranges from a cyanotic newborn with a huge heart to an adult who is diagnosed after an arrhythmia.
Why does Ebstein anomaly cause cyanosis?
Tricuspid regurgitation and the small functional right ventricle raise right atrial pressure above left atrial pressure, so deoxygenated blood crosses a patent foramen ovale or atrial septal defect from right to left. In newborns, high pulmonary vascular resistance makes it worse, and cyanosis often eases as that resistance falls. Severely cyanotic newborns may need prostaglandin E1 to keep the ductus arteriosus open in the meantime.
Does lithium in pregnancy cause Ebstein anomaly?
First-trimester lithium exposure is linked to a modest increase in cardiac malformations, including right ventricular outflow tract defects such as Ebstein anomaly, but the risk is far smaller than the roughly 400-fold figure from 1970s voluntary registry reports. In a 2017 cohort of more than 1.3 million pregnancies, cardiac malformations occurred in 2.41% of exposed infants vs 1.15% of unexposed infants, an adjusted risk ratio of 1.65, with higher risk at doses above 900 mg a day. The lithium label suggests considering fetal echocardiography at 16 to 20 weeks after first-trimester exposure.
What ECG findings are seen in Ebstein anomaly?
Tall P waves in leads II and V1 from right atrial enlargement, sometimes giant Himalayan P waves, and a complete or incomplete right bundle branch block are classic. The PR interval may be prolonged from slow conduction through the huge atrium, or short with a delta wave when an accessory pathway causes Wolff-Parkinson-White pre-excitation. Atrial flutter and atrial fibrillation are common in adults.
How do you tell Ebstein anomaly from tricuspid atresia?
Both cause cyanosis with right-to-left shunting at the atrial level, but tricuspid atresia has no tricuspid valve and a hypoplastic right ventricle, so S1 is single and the ECG shows left axis deviation with left ventricular hypertrophy. Ebstein anomaly has a widely split S1, a tricuspid regurgitation murmur, tall P waves with right bundle branch block, and massive cardiomegaly on chest x-ray.
How is Ebstein anomaly treated?
Severely cyanotic newborns receive prostaglandin E1 to keep the ductus arteriosus open until pulmonary vascular resistance falls, and some need a shunt operation. Patients with symptoms, worsening regurgitation or an enlarging right heart undergo surgical repair, often the cone reconstruction of the tricuspid valve with closure of any atrial defect, and some need valve replacement. Accessory pathways are treated with catheter ablation.