You’re cruising through a cardiovascular q-bank and hit a vignette that feels like an aortic dissection… until the answer choices start blurring together: AAA rupture? MI? Pericarditis? PE? The key to these questions isn’t just “spot dissection”—it’s classify it (Stanford A vs B) and then predict complications + management. Let’s break down a classic case the way Step wants you to.
Tag: Cardiovascular > Hypertension & Vascular Disease
The Vignette (Q-Bank Style)
A 62-year-old man with long-standing hypertension presents with sudden-onset severe chest pain that he describes as “tearing” and radiating to the back. He is diaphoretic and anxious. BP is 190/110 mmHg in the right arm and 165/95 mmHg in the left arm. On exam, you hear a new diastolic murmur at the right sternal border. ECG shows nonspecific ST-T changes. Chest X-ray shows a widened mediastinum.
What is the best next step in management?
Answer choices:
A. Immediate IV esmolol and urgent surgical repair
B. IV heparin and CT pulmonary angiography
C. Emergent pericardiocentesis
D. Aspirin + emergent PCI
E. IV labetalol and observation
The Correct Answer: A. Immediate IV esmolol and urgent surgical repair
This is aortic dissection, and the presence of a new aortic regurgitation murmur strongly suggests proximal (ascending) involvement → Stanford type A.
Why Stanford A?
Stanford classification is the one to default to on exams:
| Classification | Involves ascending aorta? | Typical location | Management |
|---|---|---|---|
| Stanford A | Yes | Ascending ± arch ± descending | Surgery + IV BP/HR control |
| Stanford B | No | Descending only (distal to left subclavian) | Medical therapy unless complicated |
Immediate management (Step-style sequence)
-
Reduce shear stress ASAP
- Start IV beta-blocker first (e.g., esmolol, labetalol)
- Targets (high-yield):
- HR < 60
- SBP 100–120 (as long as end-organ perfusion OK)
-
If BP remains high after beta-blockade, add a vasodilator:
- Nicardipine or nitroprusside
- Never start vasodilator before beta-blocker (can cause reflex tachycardia → worse dissection)
-
Stanford A → urgent surgery
- Because of lethal complications: tamponade, coronary artery involvement → MI, acute severe AR, stroke
Imaging pearl (often tested)
- If stable:
- CT angiography is common and fast
- TEE is great if unstable or can’t go to CT
- If classic presentation + unstable, management may proceed rapidly with bedside imaging and surgical coordination.
Why Every Distractor Is Wrong (and What It’s Trying to Trick You Into)
B. IV heparin and CT pulmonary angiography
This is a pulmonary embolism pathway. PE can cause sudden chest pain and dyspnea, but the vignette is screaming dissection:
Clues against PE:
- Tearing pain radiating to back
- BP differential between arms
- Widened mediastinum
- New diastolic murmur (AR)
Testable danger: giving heparin in an aortic dissection can worsen bleeding into the vessel wall and increase risk of catastrophic rupture.
PE clues you’d expect instead:
- Pleuritic chest pain, tachycardia, hypoxemia
- Risk factors: immobilization, malignancy, OCPs, prior DVT
- Signs: unilateral leg swelling; maybe clear CXR
C. Emergent pericardiocentesis
Pericardiocentesis is for cardiac tamponade, which can happen as a complication of Stanford A if blood dissects into the pericardial space.
So why is it wrong here?
- The vignette doesn’t describe tamponade physiology (yet): no hypotension, no JVD, no muffled heart sounds, no pulsus paradoxus mentioned.
- In dissection-related hemopericardium, pericardiocentesis can sometimes be a bridge if crashing, but definitive therapy is surgery. Boards typically want you to recognize the primary diagnosis and correct pathway.
Tamponade clues to memorize:
- Beck triad: hypotension + JVD + muffled heart sounds
- Electrical alternans, low voltage on ECG
- Enlarged “water bottle” cardiac silhouette (subacute)
D. Aspirin + emergent PCI
This is the “treat as MI” trap.
Aortic dissection can mimic MI in two big ways:
- Chest pain
- ECG changes can be nonspecific, and troponins may be elevated
- If dissection involves the coronary ostia (especially RCA), it can cause an inferior MI
But if you miss the dissection and give antiplatelets/anticoagulation, you can cause fatal hemorrhage.
Clues favoring dissection over ACS in this vignette:
- Tearing pain to the back
- Widened mediastinum
- Pulse/BP differential
- New AR murmur
USMLE rule of thumb: if dissection is on the table, control HR/BP and image (or proceed surgically for Type A) before you commit to full ACS anticoagulation.
E. IV labetalol and observation
Labetalol is a reasonable initial medication—but “observation” is the issue.
- If this is Stanford A, it’s a surgical emergency, not a “monitor and reassess” scenario.
- For Stanford B, medical management is often correct, but you still don’t just observe: you manage aggressively and watch for complications.
Stanford B management nuance (commonly tested):
- Uncomplicated Stanford B: IV beta-blocker ± vasodilator, ICU monitoring
- Complicated Stanford B (any of the following): consider TEVAR/endovascular repair
- End-organ ischemia (renal failure, mesenteric ischemia)
- Persistent/refractory pain or hypertension
- Rapid expansion, impending rupture
- Shock
High-Yield “Tell Me in 10 Seconds” Summary
Classic aortic dissection clues
- Sudden severe tearing chest/back pain
- Widened mediastinum on CXR
- Pulse/BP differential between arms
- Neurologic deficits (carotid involvement)
- New diastolic murmur = aortic regurg (proximal involvement)
Risk factors you should list automatically
- Chronic hypertension (biggest)
- Bicuspid aortic valve
- Marfan / Ehlers-Danlos
- Pregnancy
- Cocaine/amphetamine use
- Iatrogenic (cardiac catheterization/surgery)
Stanford A vs B: How the Question Wants You to Think
Stanford A (ascending involved)
Think: “A = Ascending = Alarm”
- Highest risk of:
- Tamponade
- Acute aortic regurg
- MI (coronary involvement)
- Stroke
- Treatment: IV beta-blocker → surgery
Stanford B (descending only)
Think: “B = Below left subclavian”
- Complications skew toward:
- Renal ischemia
- Mesenteric ischemia
- Lower extremity ischemia
- Treatment: aggressive medical management unless complicated
Rapid-Fire Board Pearls (Frequently Tested)
- Beta-blocker first, then vasodilator if needed (avoid reflex tachycardia).
- CXR may be normal—don’t let that falsely reassure you if symptoms are classic.
- New AR murmur is a huge clue for Type A.
- Dissection pain is often described as maximal at onset (vs MI pain can crescendo).
- Don’t anticoagulate until you’ve considered/ruled out dissection when the story fits.
Mini “Distractor Decoder” Table
| If the choice is pushing you toward… | You should look for… | What’s missing in this vignette? |
|---|---|---|
| PE (heparin/CTPA) | Hypoxemia, pleuritic pain, DVT risks | No hypoxemia/DVT signs; has widened mediastinum + AR murmur |
| MI (aspirin/PCI) | Crushing substernal pain, clear dissection red flags absent | Dissection red flags are present; ECG is nonspecific |
| Tamponade (pericardiocentesis) | Hypotension, JVD, muffled sounds | He’s hypertensive; no tamponade signs given |
| “Observe” | Stable condition without high-risk diagnosis | Type A dissection is not observational |
Takeaway
When a vignette suggests aortic dissection, Step expects you to do two things fast:
- Classify it (Stanford A vs B) based on ascending involvement clues (especially AR murmur), and
- Treat shear stress immediately (IV beta-blocker) while moving toward the correct definitive step (surgery for A, medical ± TEVAR for B).
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
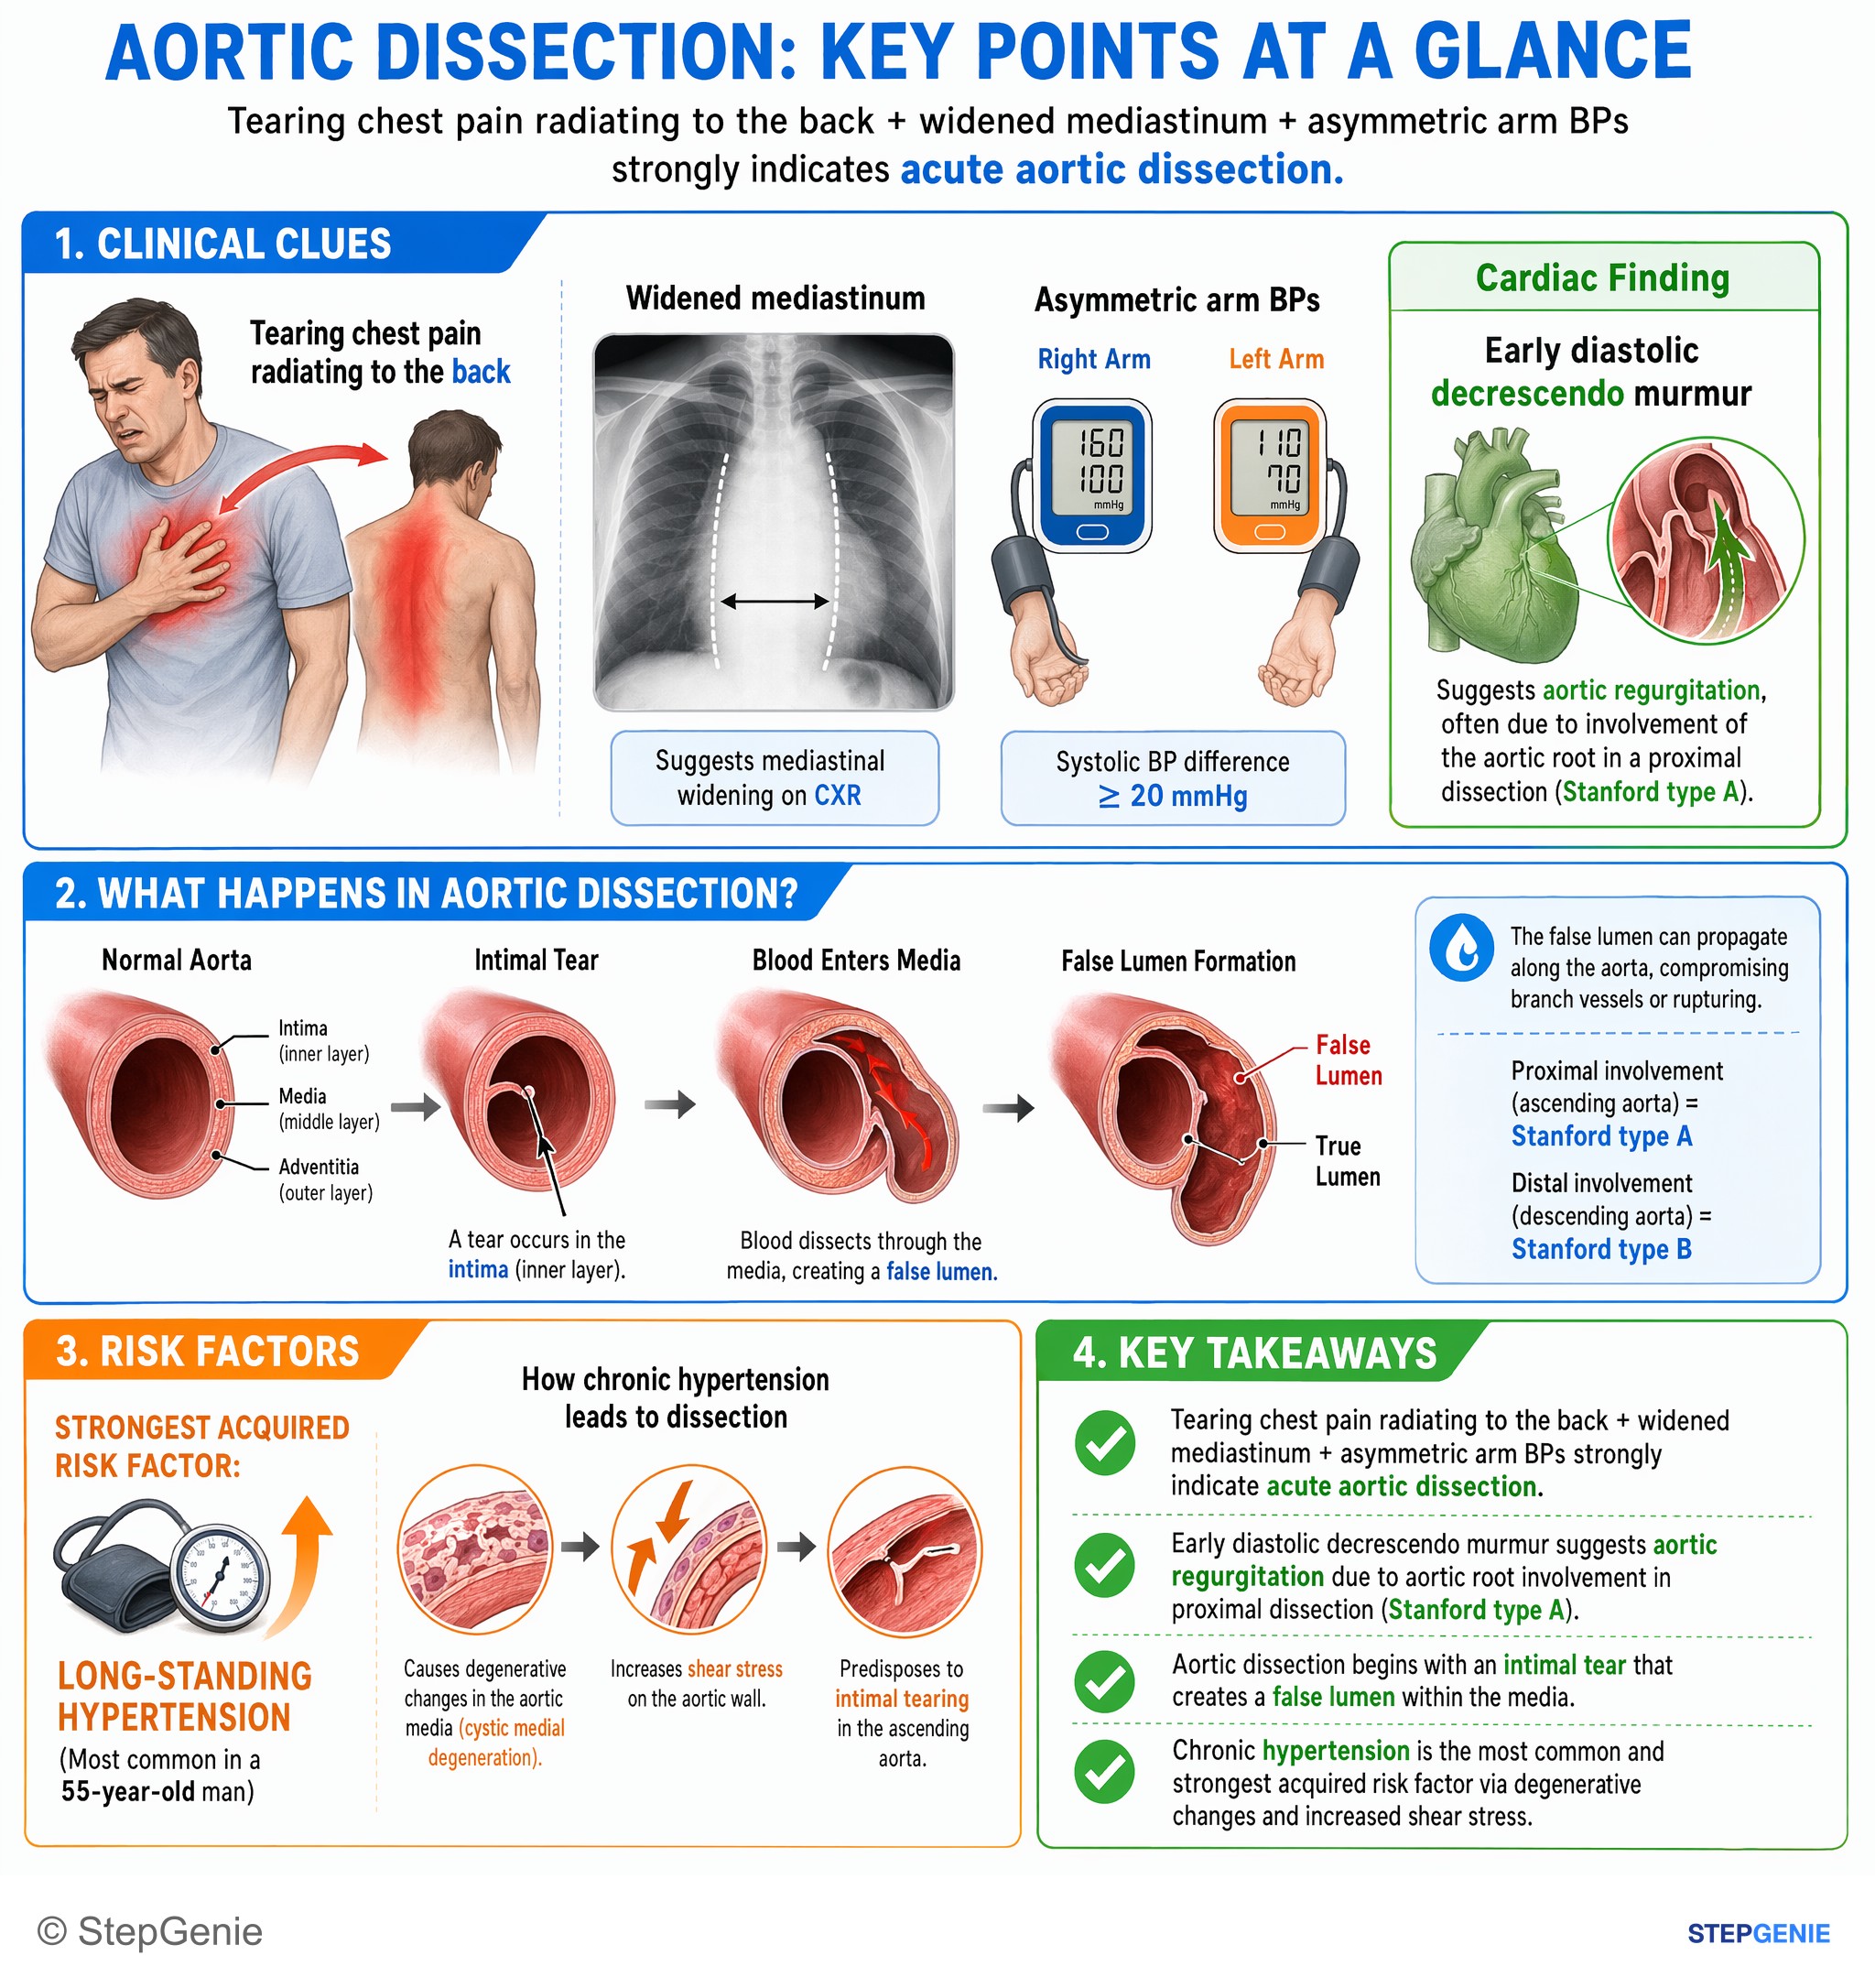
Aortic dissection presents with tearing chest pain radiating to back; strongest acquired risk factor is chronic hypertension causing…
USMLE Step 1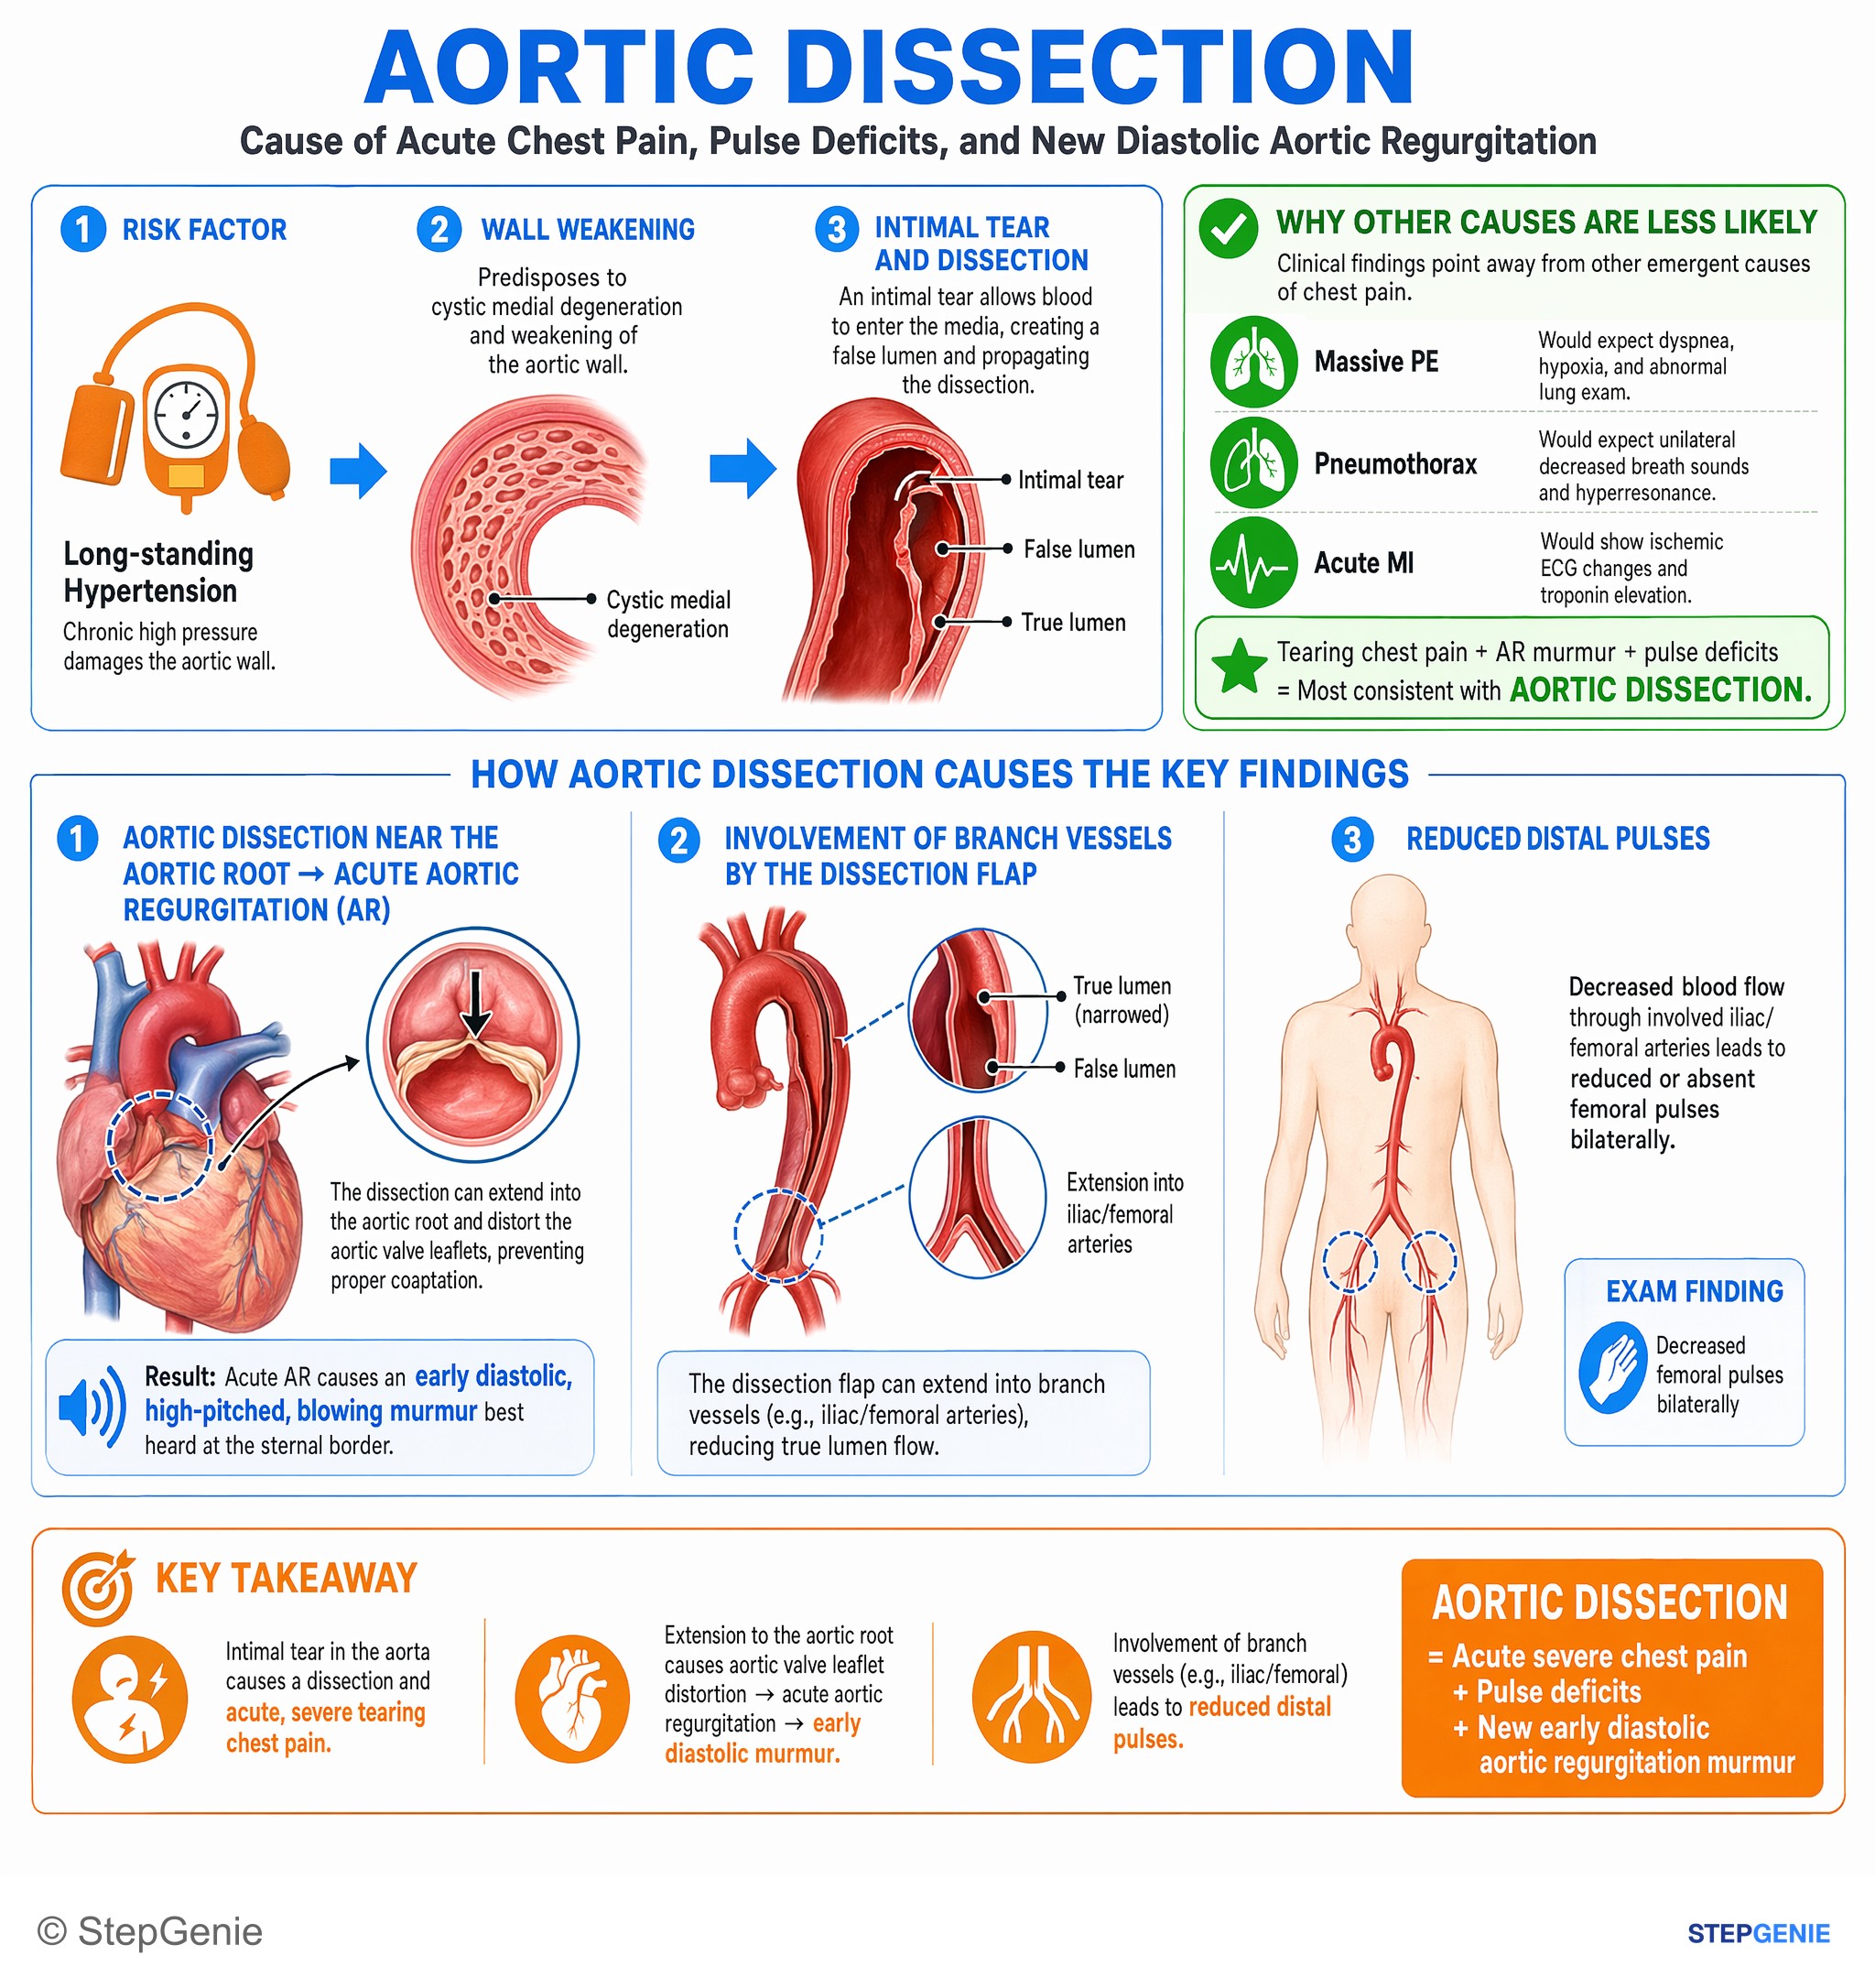
Aortic dissection from intimal tear causes acute severe chest pain, pulse deficits, and new early diastolic aortic regurgitation murmur.
USMLE Step 2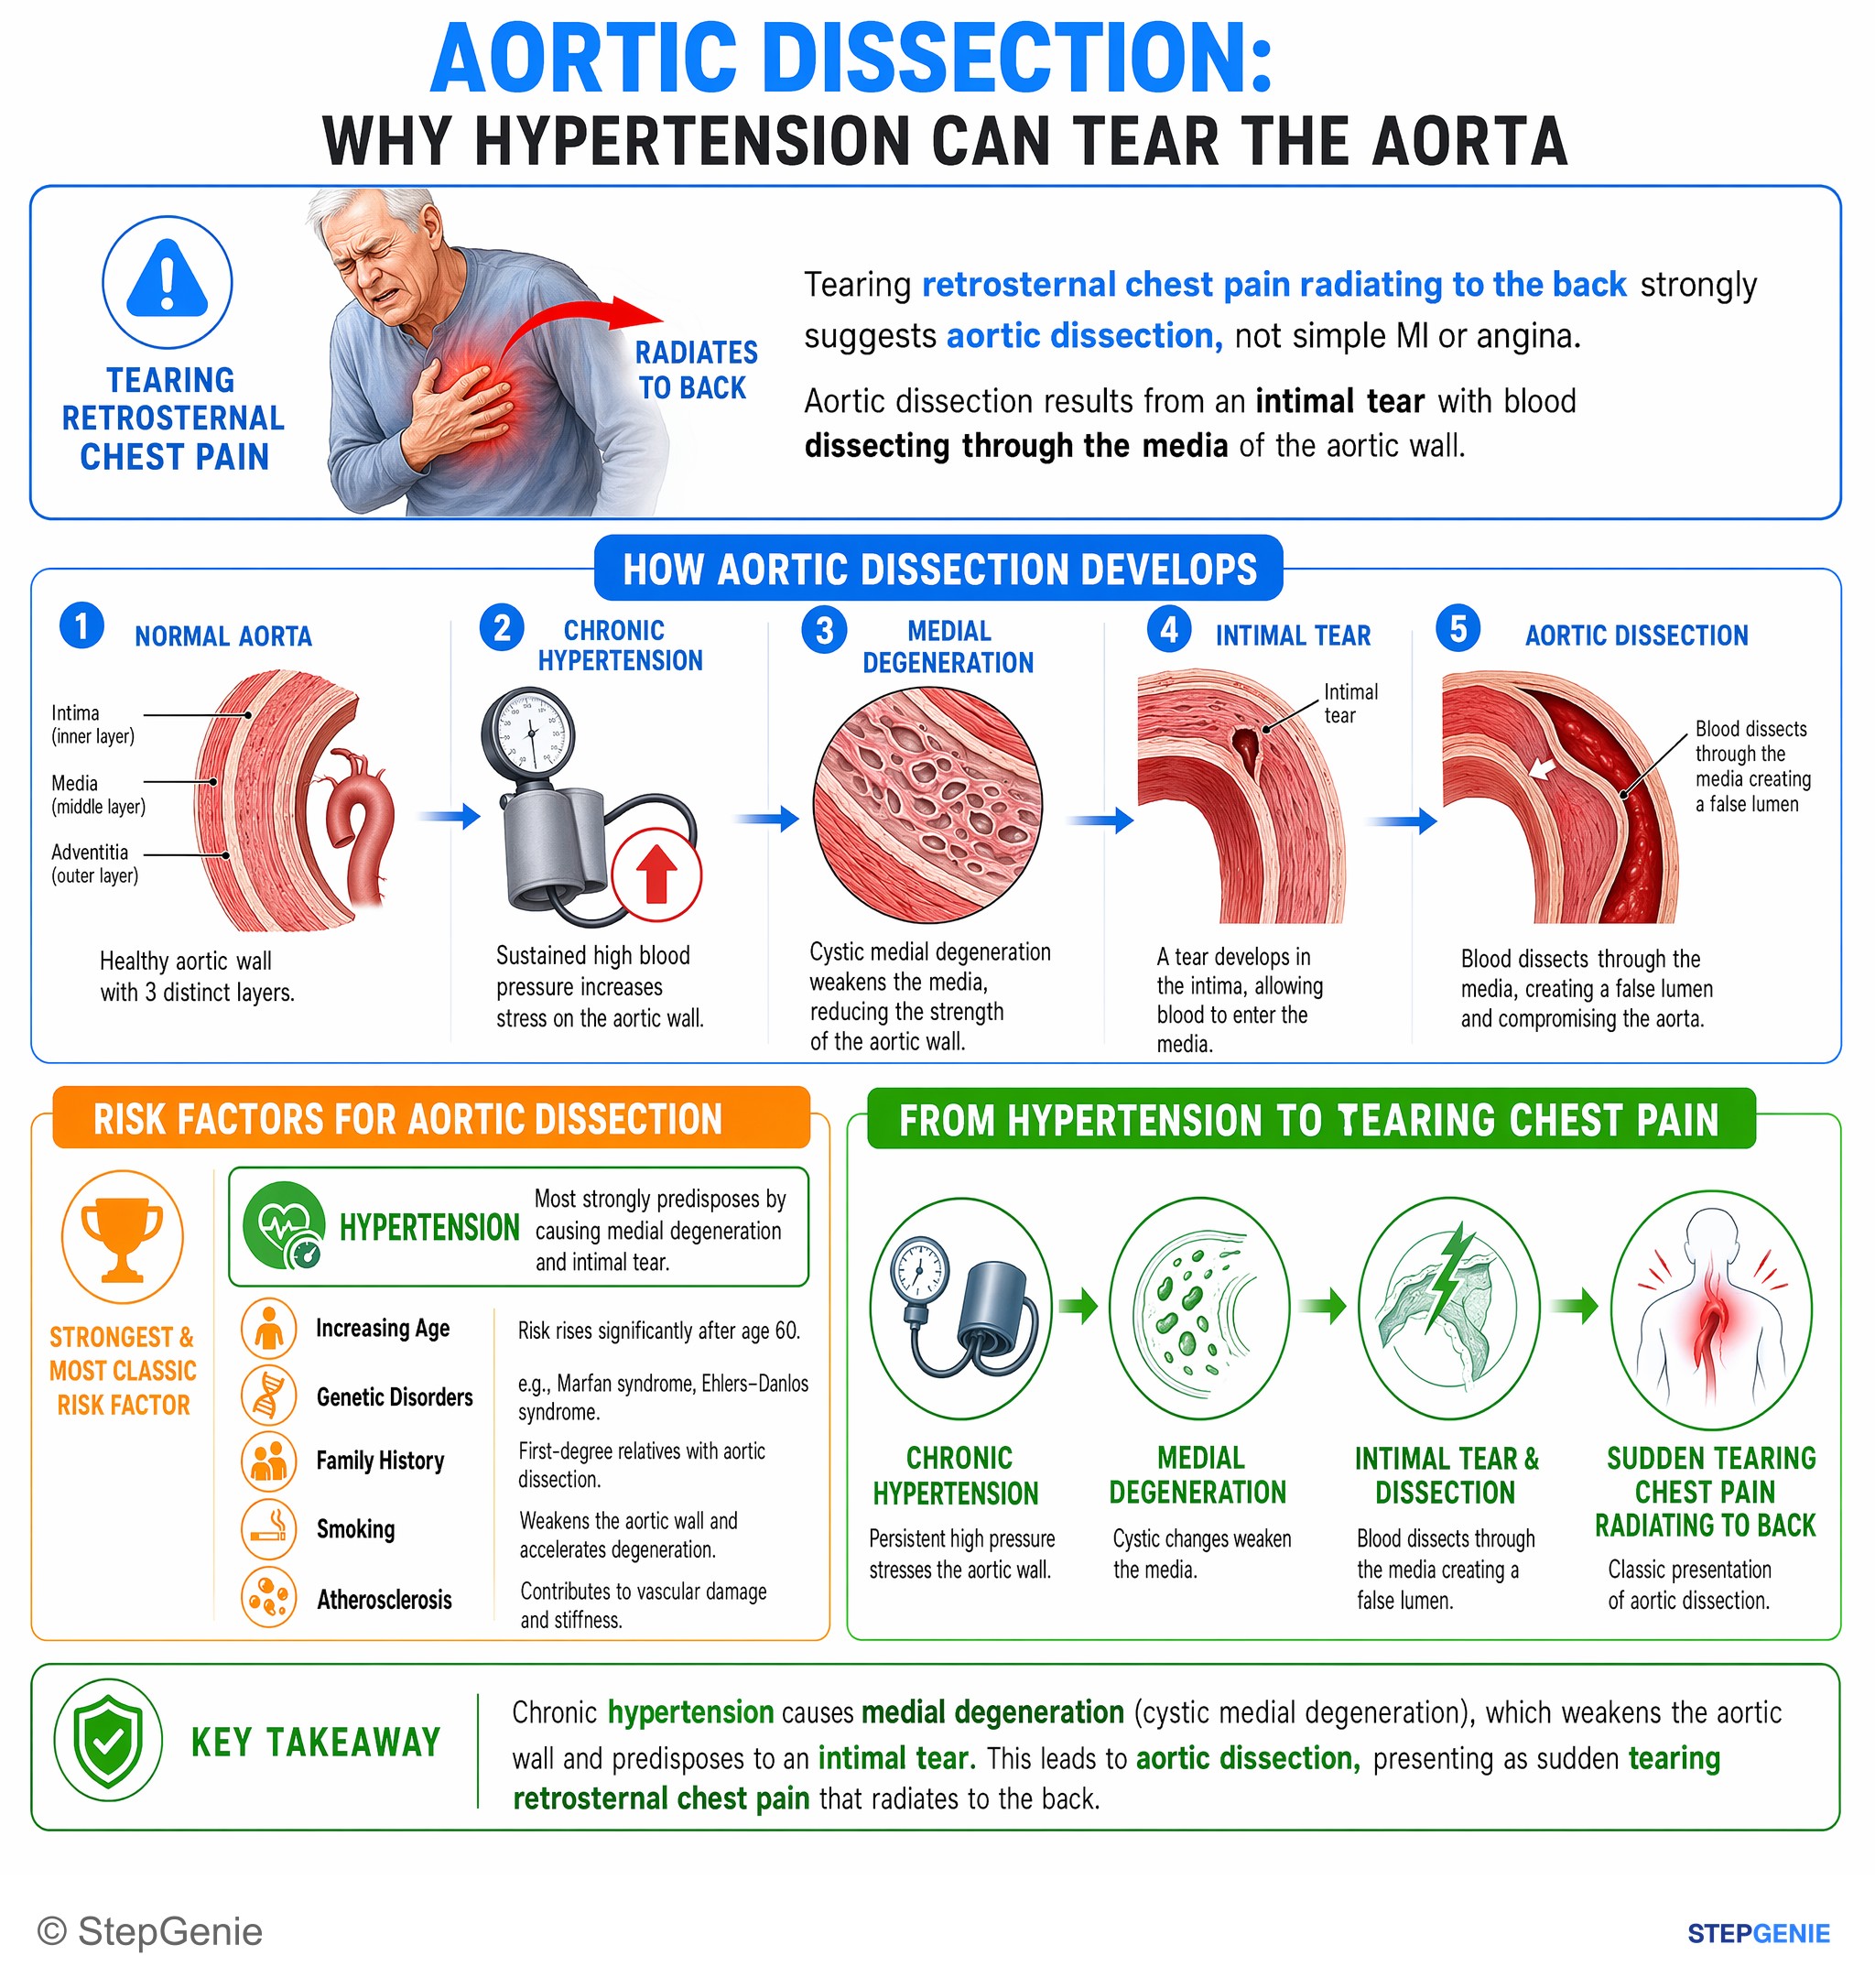
Aortic dissection most strongly predisposed by chronic hypertension, causing medial degeneration and intimal tear → sudden tearing chest…
USMLE Step 2Frequently Asked Questions
What clues point to Stanford type A aortic dissection instead of another cause of chest pain?
Stanford type A aortic dissection is suggested by sudden severe tearing chest pain radiating to the back plus signs of ascending aortic involvement. High-yield clues include a blood pressure difference between arms, a widened mediastinum on chest X-ray, and a new diastolic murmur from aortic regurgitation. Those findings make proximal dissection much more likely than pulmonary embolism, myocardial infarction, or pericarditis.
What is the best next step in management for Stanford A aortic dissection?
The best next step is immediate IV beta-blockade, such as esmolol, followed by urgent surgical repair. Initial treatment aims to reduce shear stress by lowering heart rate and systolic blood pressure. If blood pressure stays elevated after beta-blockade, a vasodilator such as nicardipine or nitroprusside can be added. Stanford type A is a surgical emergency because of life-threatening complications like tamponade, myocardial infarction, acute severe aortic regurgitation, and stroke.
Why do you give a beta-blocker before a vasodilator in aortic dissection?
You give a beta-blocker first to reduce shear stress and avoid reflex tachycardia. In aortic dissection, the initial goal is to lower heart rate and systolic blood pressure quickly, and agents like esmolol or labetalol are used first. Starting a vasodilator before beta-blockade can trigger reflex tachycardia, which worsens the dissection by increasing stress on the aortic wall.
How do you tell aortic dissection from pulmonary embolism or acute MI on a vignette?
Aortic dissection is favored when the chest pain is tearing, radiates to the back, and is accompanied by a widened mediastinum, pulse or blood pressure differences between arms, or a new aortic regurgitation murmur. Pulmonary embolism more often presents with pleuritic chest pain, tachycardia, hypoxemia, and risk factors like immobilization or prior DVT. Acute MI can overlap with chest pain and ECG changes, but the classic dissection clues should shift management away from anticoagulation.
When is Stanford B aortic dissection treated medically instead of surgically?
Stanford B aortic dissection is usually treated medically when it is uncomplicated. Management includes IV beta-blocker therapy, with a vasodilator added if needed, and ICU-level monitoring rather than simple observation. Endovascular repair is considered when Stanford B becomes complicated, such as with end-organ ischemia, persistent or refractory pain or hypertension, rapid expansion, impending rupture, or shock.