Transposition of the great arteries (TGA, also called transposition of the great vessels) in its classic form, d-TGA, connects the aorta to the right ventricle and the pulmonary artery to the left ventricle, so the systemic and pulmonary circulations run in parallel instead of in series. Survival depends on mixing through a patent foramen ovale or ASD, a VSD or a PDA, so the newborn becomes severely cyanotic within hours of birth, typically with a single loud S2, no murmur and an "egg on a string" chest x-ray. Treatment is prostaglandin E1 (alprostadil) to keep the ductus open, balloon atrial septostomy if atrial mixing is inadequate, and the arterial switch operation in the first weeks of life (Merck: typically the first week; CDC: usually the first month). Exam favorites: maternal diabetes and a septum that fails to spiral. Congenitally corrected (L-)TGA is a different condition that usually causes no cyanosis.
D-TGA vs congenitally corrected (L-)TGA
| D-TGA (classic) | Congenitally corrected TGA (L-TGA) | |
|---|---|---|
| Connections | Atria connect to the correct ventricles, but the aorta arises from the RV and the pulmonary artery from the LV | Double discordance: the ventricles are switched relative to both the atria and the great arteries |
| Aorta position | Anterior and to the right of the pulmonary artery | Anterior and to the left |
| Circulation | Parallel: deoxygenated blood recirculates to the body, oxygenated blood to the lungs | In series: blood still reaches the right places |
| Cyanosis | Severe, within hours of birth | Usually none; some people are diagnosed only as adults |
| Main problems | Inadequate mixing and metabolic acidosis; heart failure within weeks if there is a large VSD | The right ventricle pumps to the body and can weaken; leaky tricuspid valve; complete heart block that can develop with age; may come with a VSD or pulmonary valve obstruction |
| Treatment | PGE1, then balloon atrial septostomy if needed, then arterial switch | Monitoring; pacemaker for heart block; tricuspid valve repair or replacement; some have a double switch operation |
Embryology: the septum that didn't spiral
- Normally the aorticopulmonary (conotruncal) septum spirals as it divides the outflow tract, so the pulmonary trunk crosses in front of and to the left of the aorta. Neural crest cells contribute; faulty migration or septation causes conotruncal defects such as d-TGA and tetralogy of Fallot.
- Classic exam answer: in d-TGA the septum fails to spiral and forms straight, so each great artery ends up over the wrong ventricle and the arteries lose their normal criss-cross relationship.
- Newer view: abnormal conal (infundibular) development, with an underdeveloped subpulmonary conus and a persistent subaortic conus. Pick the spiral answer on Step 1.
- Contrast: persistent truncus arteriosus = the septum fails to form; tetralogy of Fallot = the septum is deviated anteriorly and cephalad.
Parallel circulations: why mixing decides survival
- Two closed loops: RA → RV → aorta → body → RA recirculates deoxygenated blood; LA → LV → pulmonary artery → lungs → LA recirculates oxygenated blood.
- The anomaly is not compatible with life unless blood mixes at the atrial, ventricular or great-artery level (a PFO or ASD, a VSD, or a PDA).
- The atrial level matters most: the small pressure difference between the atria allows easy bidirectional shunting.
- About 30-40% have a VSD, and up to 25% have left ventricular outflow tract (pulmonary) obstruction. A large VSD or PDA brings milder cyanosis but heart failure in the first weeks.
Who gets it and how it presents
- How common: 5-7% of congenital heart disease; about 1 in 3,846 US births, roughly 920 babies a year (CDC). Tetralogy of Fallot is the more common cyanotic defect overall, but d-TGA is the most common cardiac cause of cyanosis in newborns.
- Classic baby: a large-for-gestational-age boy born to a mother with diabetes (the "happy, chubby, blue boy"); uncontrolled diabetes in pregnancy is associated with a higher risk of d-TGA, and boys are affected about 1.5 to 3 times as often as girls.
- Timing: severe cyanosis within hours of birth, followed rapidly by metabolic acidosis.
- Exam: little besides cyanosis: a single loud S2 and no murmur unless an associated lesion, such as a VSD, is present.
- Oxygen doesn't fix it: saturation and PaO2 barely rise on 100% oxygen (a failed hyperoxia test), which points to cyanotic heart disease rather than lung disease (though severe lung disease or PPHN can also fail it).
- Reverse differential cyanosis (upper body bluer than lower body) suggests d-TGA with a PDA plus severe coarctation or suprasystemic pulmonary hypertension.
- Screening: newborn pulse oximetry screening can detect d-TGA, and fetal echocardiography can diagnose it before birth.
Diagnosis: x-ray, ECG and echo
- Chest x-ray: the "egg on a string": an egg-shaped heart on a narrow upper mediastinum, because the great arteries lose their normal criss-cross relationship and the thymus may be small.
- ECG: right axis deviation and RVH, which can look normal for a newborn.
- Echocardiography confirms the diagnosis and shows where blood mixes.
Management: PGE1, septostomy, switch
- Stabilize with prostaglandin E1 (alprostadil), starting at 0.05-0.1 mcg/kg/min, and treat metabolic acidosis with sodium bicarbonate. Opening the ductus arteriosus increases pulmonary blood flow, which promotes left-to-right shunting at the atrial level and improves systemic oxygenation.
- Balloon atrial septostomy (Rashkind procedure) for neonates who stay severely hypoxemic on PGE1 or who have a very restrictive foramen ovale: a balloon catheter enlarges the opening between the atria, in the cath lab or at the bedside under echo guidance. About one-third of babies with TGA need it urgently, within hours of birth.
- Arterial switch operation (Jatene): the great arteries are transected and reattached to the correct ventricles, and the coronary arteries are moved to the neo-aorta. Merck says it is typically done during the first week of life; the CDC says usually in the first month. Survival is over 95%.
- Atrial switch (Mustard or Senning): the standard operation before the 1980s (Jatene first performed the arterial switch in 1975). Baffles reroute venous return inside the atria, so the right ventricle stays the systemic pump; survivors face systemic RV dysfunction, atrial arrhythmias and baffle obstruction.
PGE1 pearls:
- If the foramen ovale is small, PGE1 can have the opposite effect: the extra blood returning to the left atrium can push the foramen ovale flap shut and reduce mixing, a cue for septostomy.
- Adverse effects: apnea (boxed warning: about 10-12% of neonates with congenital heart defects, mostly those under 2 kg and within the first hour), fever, flushing, bradycardia, hypotension and seizures; long-bone cortical proliferation and gastric outlet obstruction with prolonged infusion.
Long-term issues after the arterial switch
- Narrowing where the arteries were reconnected (neopulmonary stenosis, RV outflow tract obstruction).
- Neoaortic root dilation and neoaortic valve regurgitation: the original pulmonary valve now serves as the aortic valve and can stretch and leak.
- Coronary artery stenosis after the coronary transfer, plus LV dysfunction, arrhythmias and heart failure.
- All need lifelong adult congenital heart disease follow-up. Endocarditis prophylaxis applies before repair and for the first 6 months after it, then only with a residual defect next to a surgical patch.
- Untreated, about 30% of newborns die in the first week, 50% in the first month and 90% by the end of the first year.
TGA vs the other cyanotic newborn lesions
| Lesion | Key anatomy | Clinical picture | Classic clue |
|---|---|---|---|
| D-TGA | Aorta from the RV, pulmonary artery from the LV | Severe cyanosis within hours; otherwise quiet exam | Single loud S2, egg on a string, infant of a diabetic mother |
| Tetralogy of Fallot | Malalignment VSD + RV outflow obstruction | Cyanosis varies with obstruction; spells peak at 2-4 months | Harsh ejection murmur at the LUSB, boot-shaped heart, 22q11.2 (TOF guide) |
| Truncus arteriosus | One trunk over a large VSD gives rise to the coronary, pulmonary and systemic arteries | Mild cyanosis; heart failure as pulmonary resistance falls | Wide pulse pressure, truncal valve ejection murmur, 22q11.2 |
| TAPVR | All pulmonary veins drain into the systemic veins; an atrial opening fills the left heart | Obstructed: marked cyanosis, respiratory distress, pulmonary edema; unobstructed: milder | Obstructed: small heart, diffuse pulmonary edema; supracardiac: snowman sign (TAPVR breakdown) |
| Tricuspid atresia | No tricuspid valve, hypoplastic RV; obligatory right-to-left shunt through a PFO or ASD | Cyanosis when pulmonary blood flow is low; heart failure when it is high | Left axis deviation with LVH on ECG |
| HLHS or critical coarctation | Left-sided obstruction; the ductus supplies systemic flow | Shock as the ductus closes | A perfusion problem more than a cyanosis problem; PGE1 reopens the ductus (coarctation) |
How USMLE tests TGA
- Cyanosis within hours + no murmur + single loud S2 + egg on a string → d-TGA → start PGE1.
- PGE1 opens the ductus; indomethacin or ibuprofen closes it. Closing a mixing site in d-TGA is the classic wrong answer.
- Hypoxemia despite PGE1, or a restrictive foramen ovale on echo → balloon atrial septostomy.
- Adult with complete heart block or a failing systemic right ventricle → think congenitally corrected TGA (or d-TGA after an atrial switch) (review AV blocks).
Practice question
A 4.3-kg boy is born at 39 weeks to a mother with poorly controlled pregestational diabetes. Two hours after birth he is deeply cyanotic. He is mildly tachypneic without retractions, pulses are normal, and there is a single loud S2 with no murmur. Oxygen saturation is 68% in the right hand and 70% in the foot and barely changes on 100% oxygen. Arterial blood gas shows metabolic acidosis. Chest x-ray shows an egg-shaped cardiac silhouette with a narrow upper mediastinum. Which is the most appropriate next step in management?
A. Intravenous alprostadil (prostaglandin E1) B. Intravenous indomethacin C. Continued 100% oxygen by hood and observation D. Intravenous propranolol E. Immediate arterial switch operation
Answer: A. Early severe cyanosis in a large infant of a diabetic mother, a single loud S2 without a murmur, no response to oxygen, metabolic acidosis and an egg-on-a-string film point to d-TGA. Alprostadil keeps the ductus open, increasing pulmonary blood flow and atrial-level mixing. Echocardiography confirms the anatomy; if he stays severely hypoxemic or the foramen ovale is restrictive, the next step is balloon atrial septostomy, followed by an arterial switch in the first weeks of life.
- B: indomethacin, a COX inhibitor, closes the ductus (it is used for a PDA in preterm infants). Removing a mixing site in d-TGA can be fatal.
- C: oxygen barely changes saturation when the problem is parallel circulations, and waiting lets the acidosis worsen.
- D: propranolol treats and prevents tet spells in tetralogy of Fallot by relaxing the RV outflow tract; it does nothing for mixing.
- E: the arterial switch is the definitive repair, but it comes after stabilization and echocardiographic confirmation of the anatomy.
Key takeaways
- D-TGA: aorta from the RV, pulmonary artery from the LV → parallel circulations; survival depends on mixing (atrial level most important, plus a VSD or PDA).
- The most common cardiac cause of neonatal cyanosis; classically a large boy born to a mother with diabetes.
- Single loud S2, no murmur, egg on a string, failed hyperoxia test, metabolic acidosis.
- PGE1 first (watch for apnea), balloon atrial septostomy if mixing is inadequate, arterial switch in the first weeks of life with coronary transfer.
- Congenitally corrected (L-)TGA: double discordance, usually acyanotic; systemic RV failure, tricuspid regurgitation and complete heart block.
Sources
- Transposition of the Great Arteries (TGA) — Merck Manual Professional Edition (2023)
- Patent Ductus Arteriosus (PDA) — Merck Manual Professional Edition (2023)
- Dextro-Transposition of the Great Arteries (d-TGA) — CDC Congenital Heart Defects (2026)
- d-Transposition of the Great Arteries — American Heart Association (2026)
- L-Transposition of the Great Arteries — American Heart Association (2026)
- Transposition of the Great Arteries — Children's Hospital of Philadelphia
- Total Anomalous Pulmonary Venous Return (TAPVR) — Merck Manual Professional Edition (2023)
- Cyanotic Cardiac Lesions — UTMB Pediatric Education, University of Texas Medical Branch
- Cyanosis — UTMB Pediatric Education, University of Texas Medical Branch
- Embryology — UTMB Pediatric Education, University of Texas Medical Branch
- Pathogenesis and Surgical Treatment of Dextro-Transposition of the Great Arteries (D-TGA): Part II — Journal of Clinical Medicine (2024)
- PROSTIN VR PEDIATRIC (alprostadil) injection label — DailyMed, US National Library of Medicine (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
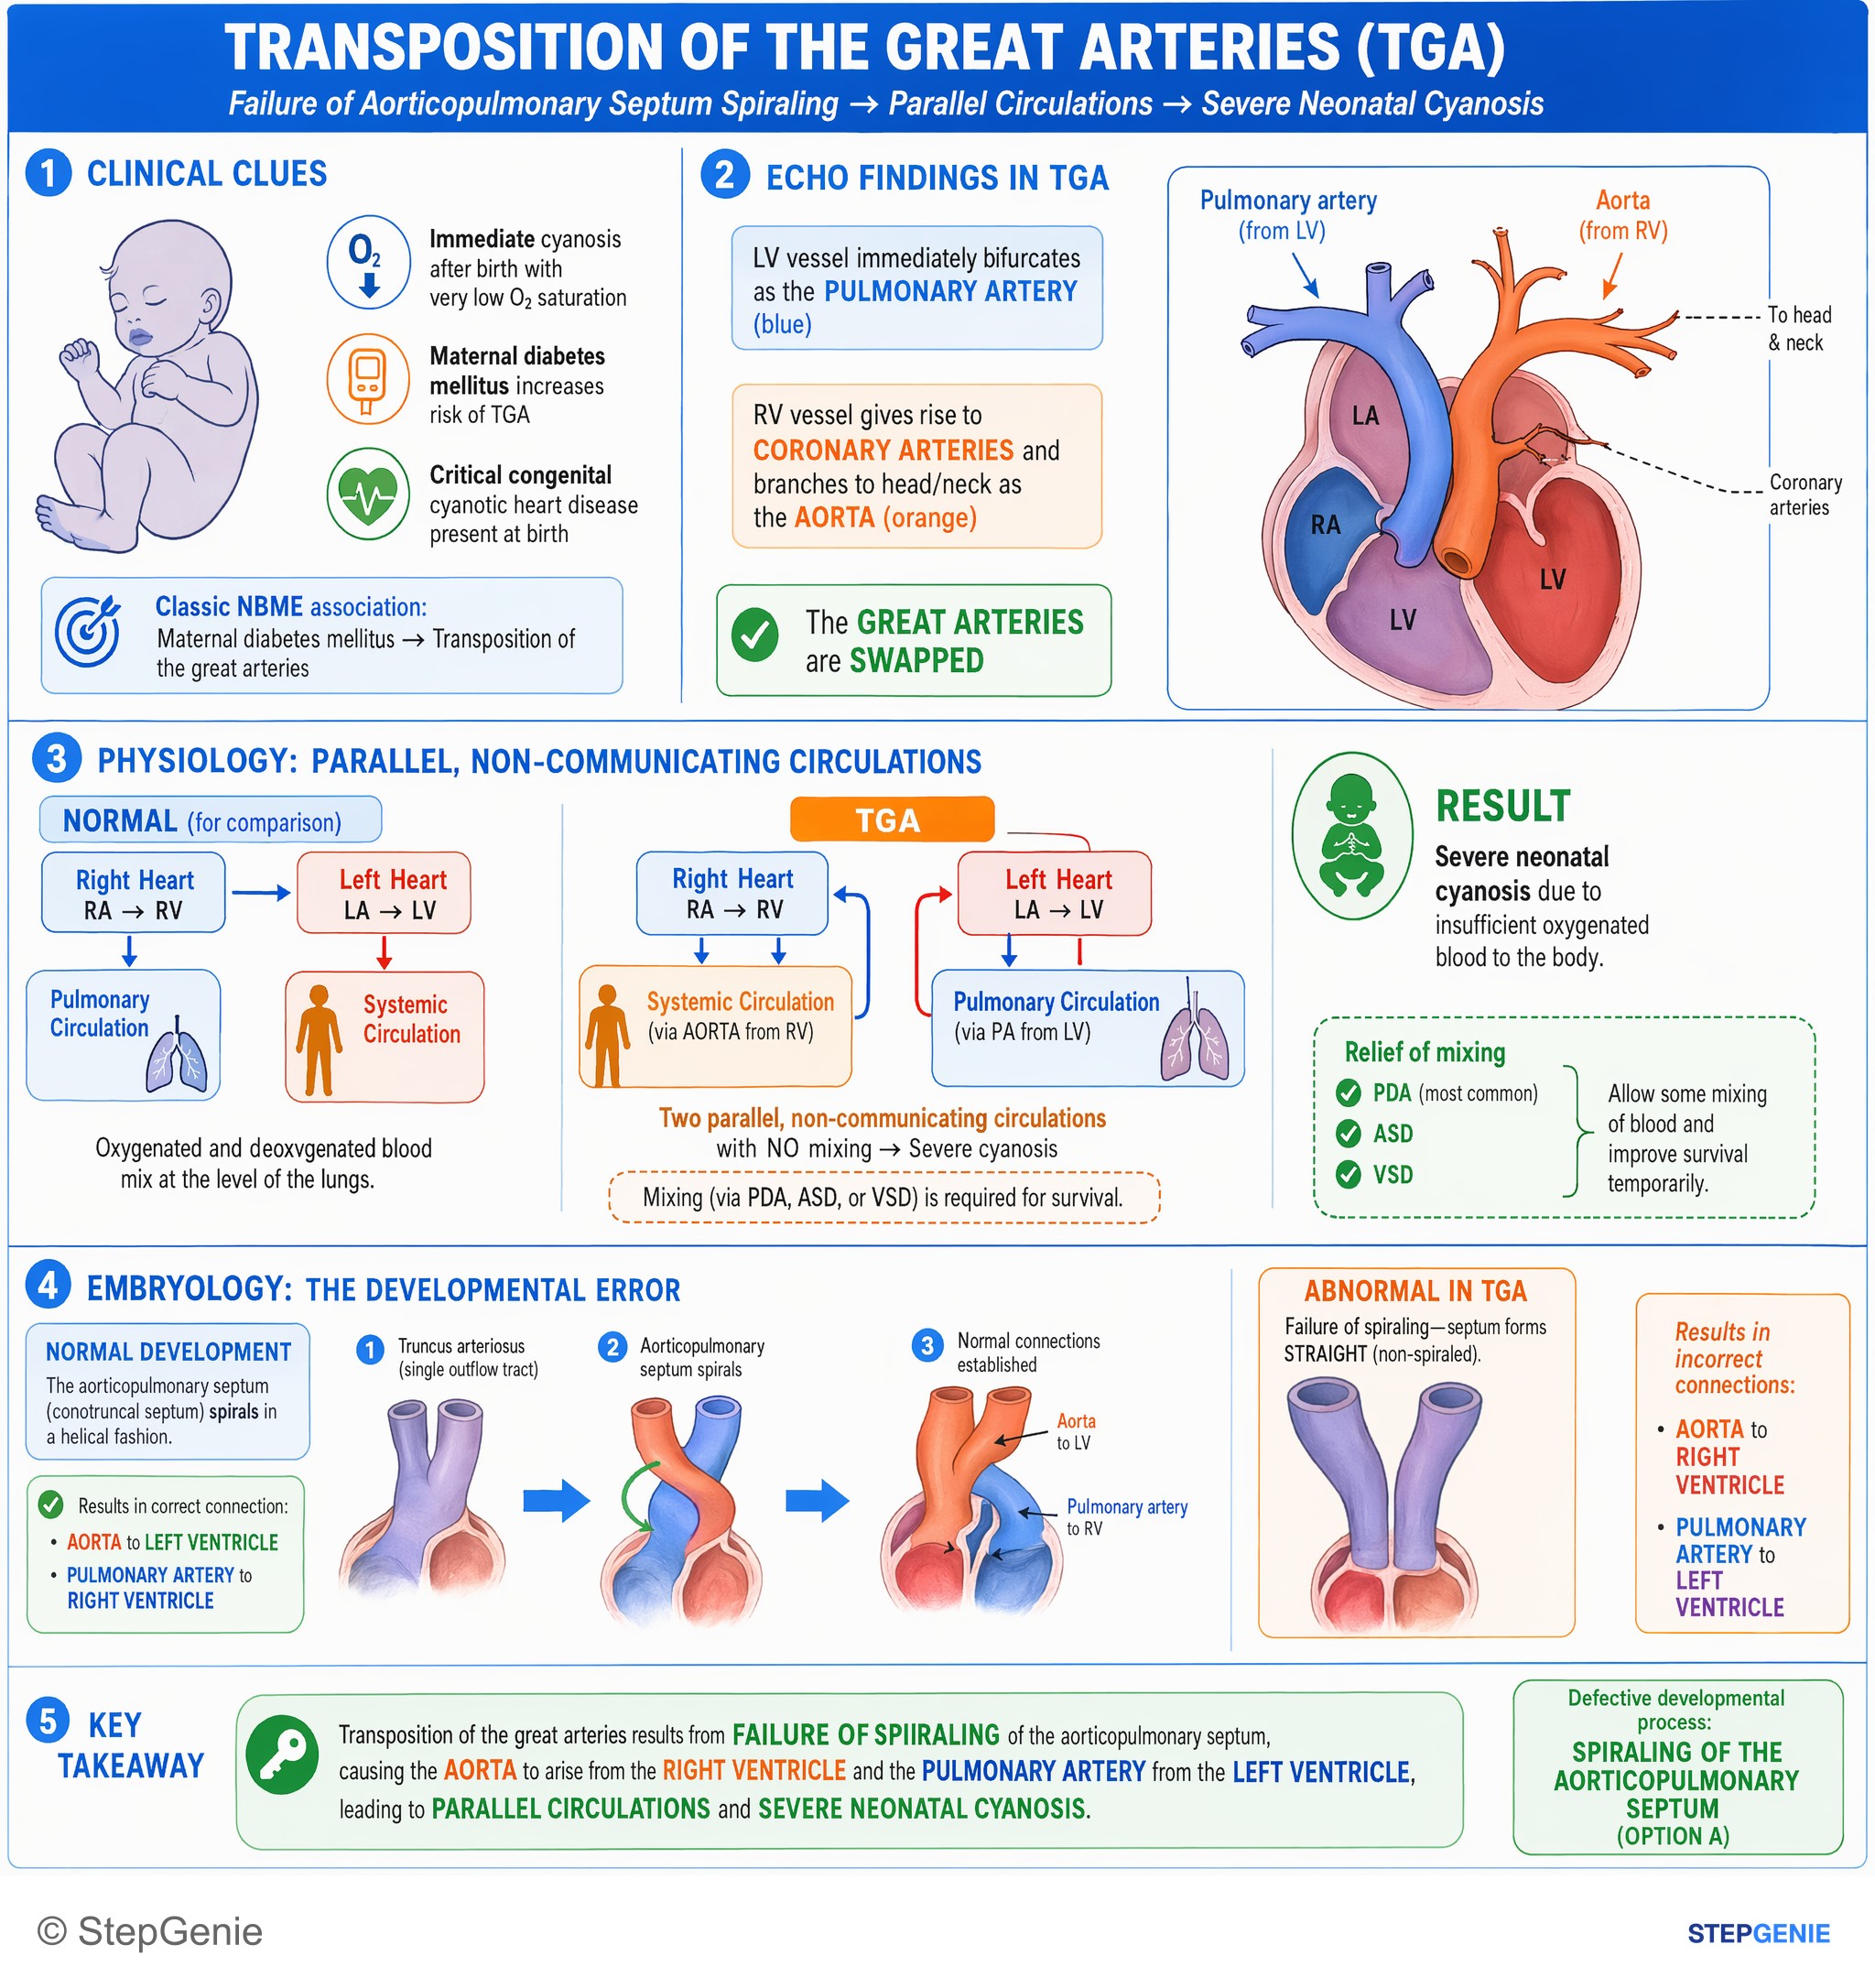
Transposition of the great arteries from failure of aorticopulmonary septum spiraling → parallel circulations → severe neonatal cyanosis.
USMLE Step 1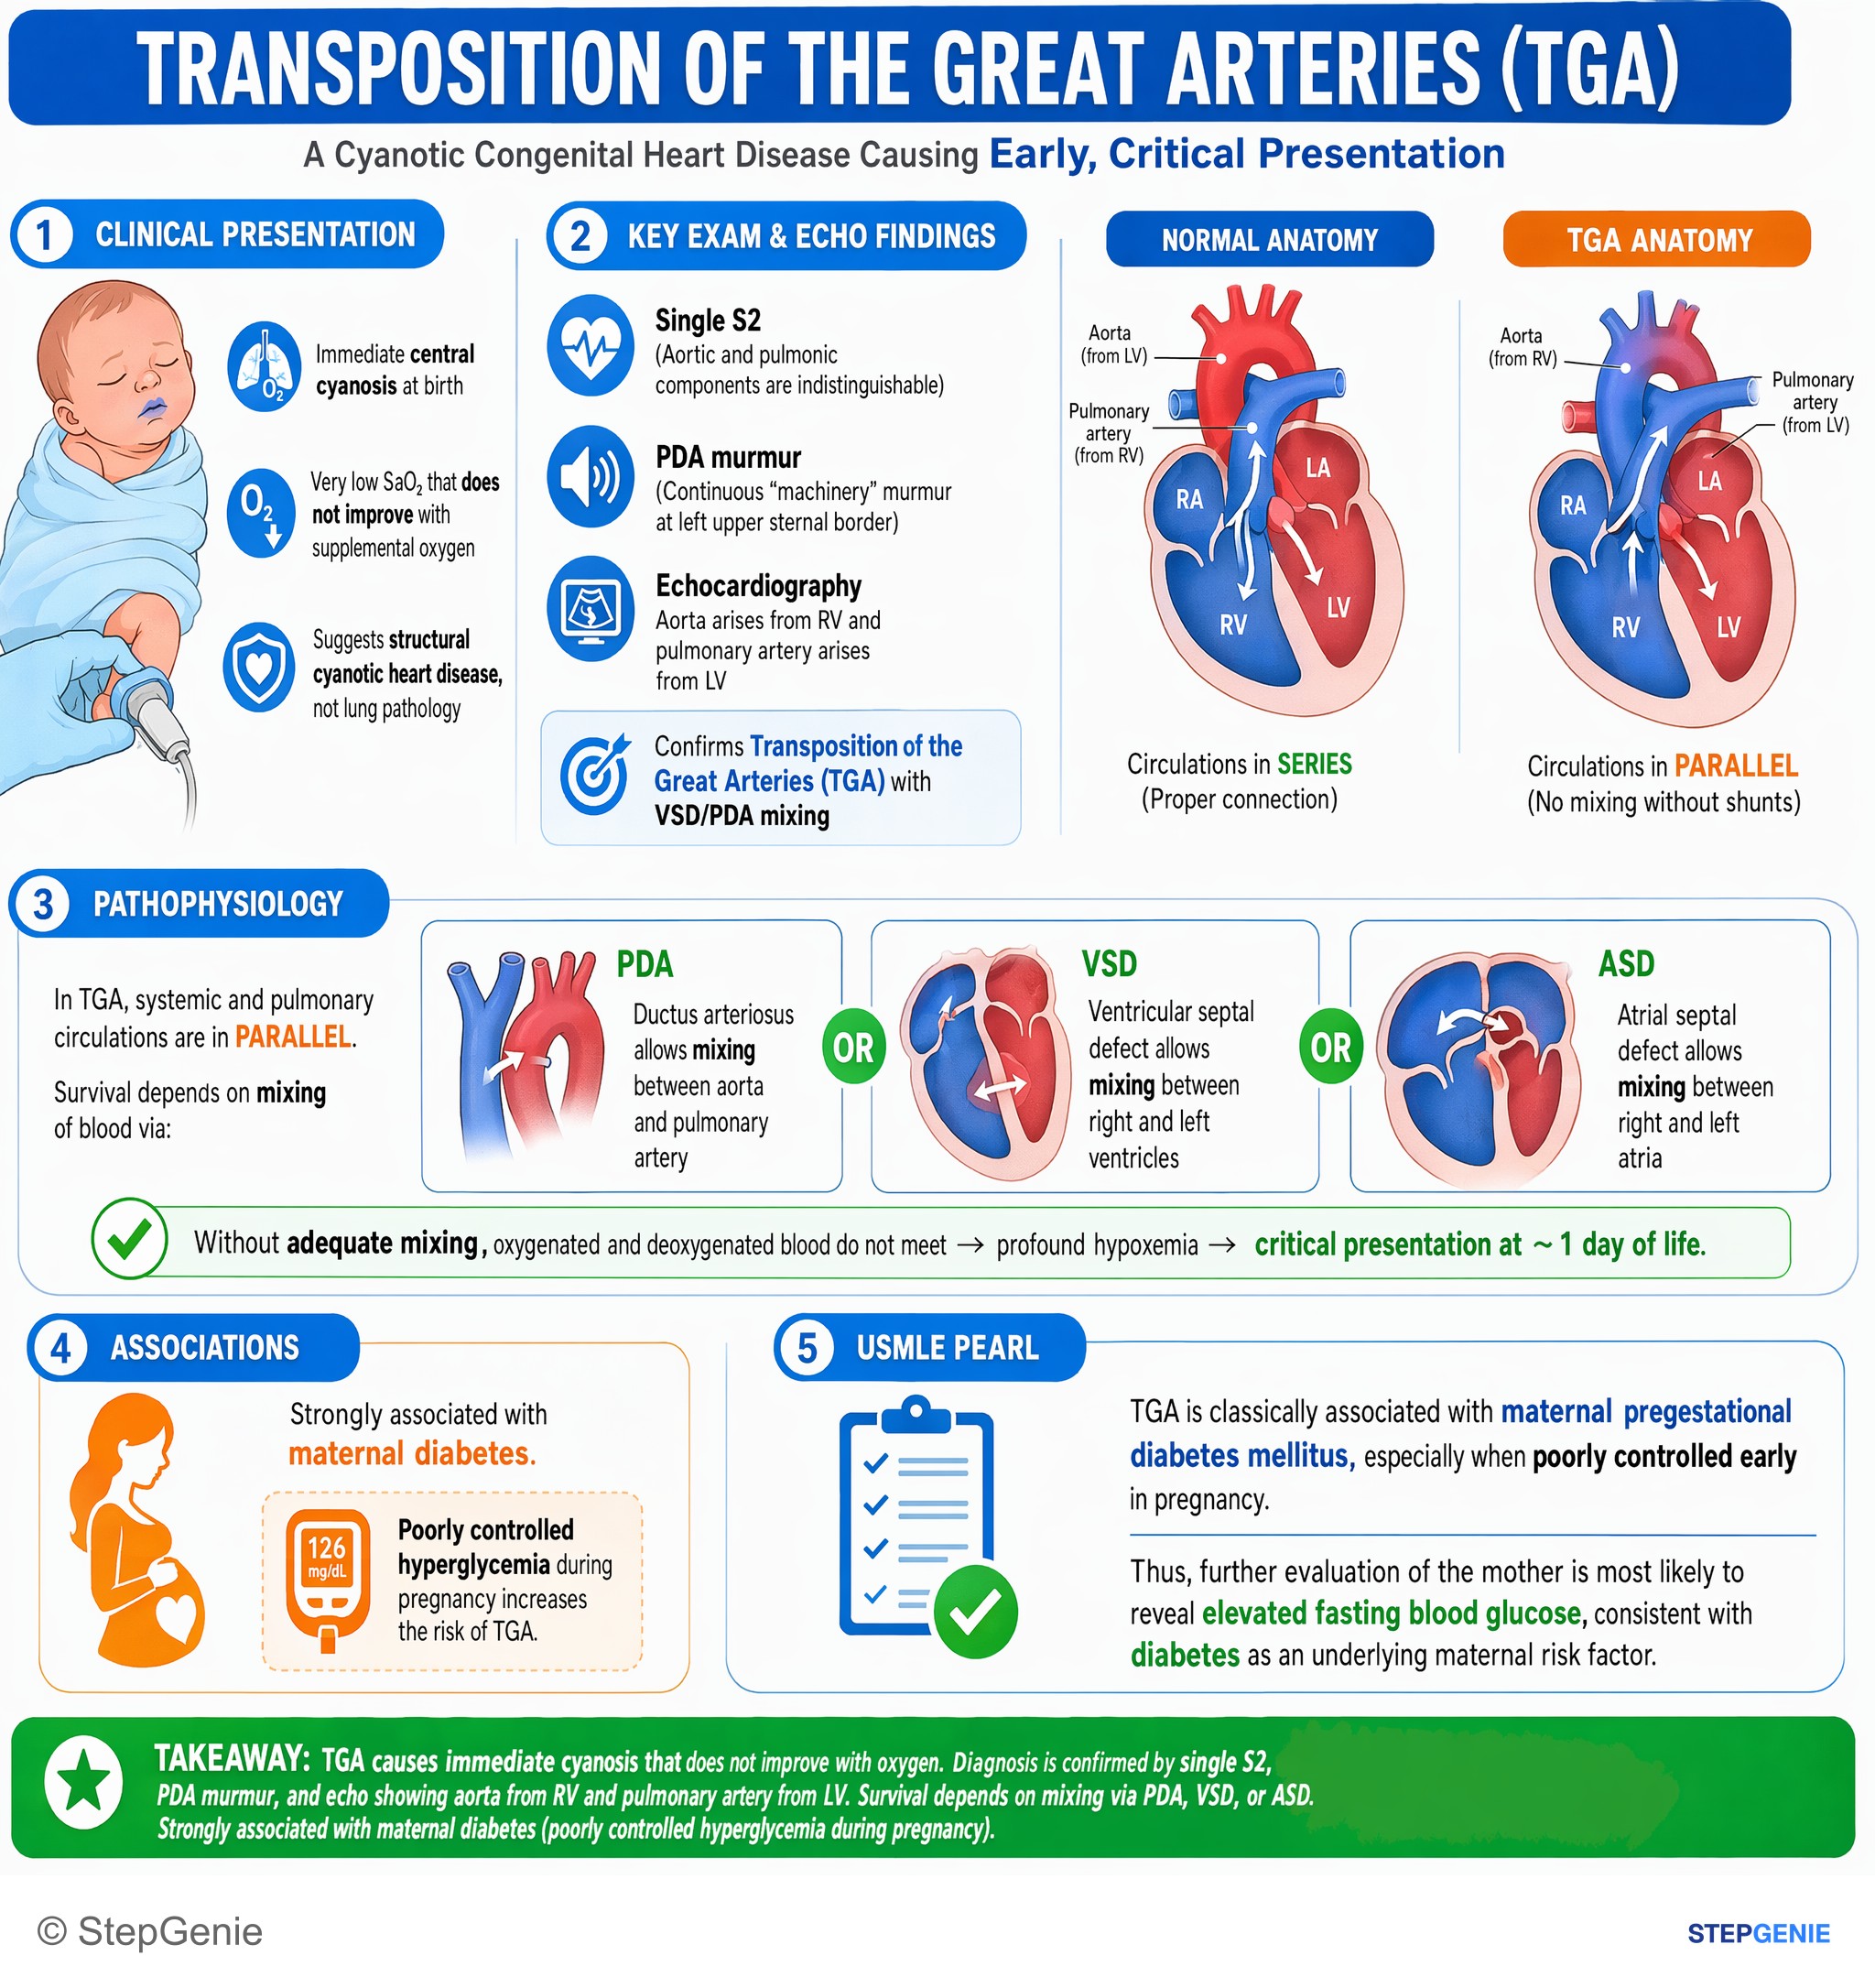
Transposition of the great arteries causes early cyanosis; strongly associated with maternal diabetes (poorly controlled hyperglycemia…
USMLE Step 1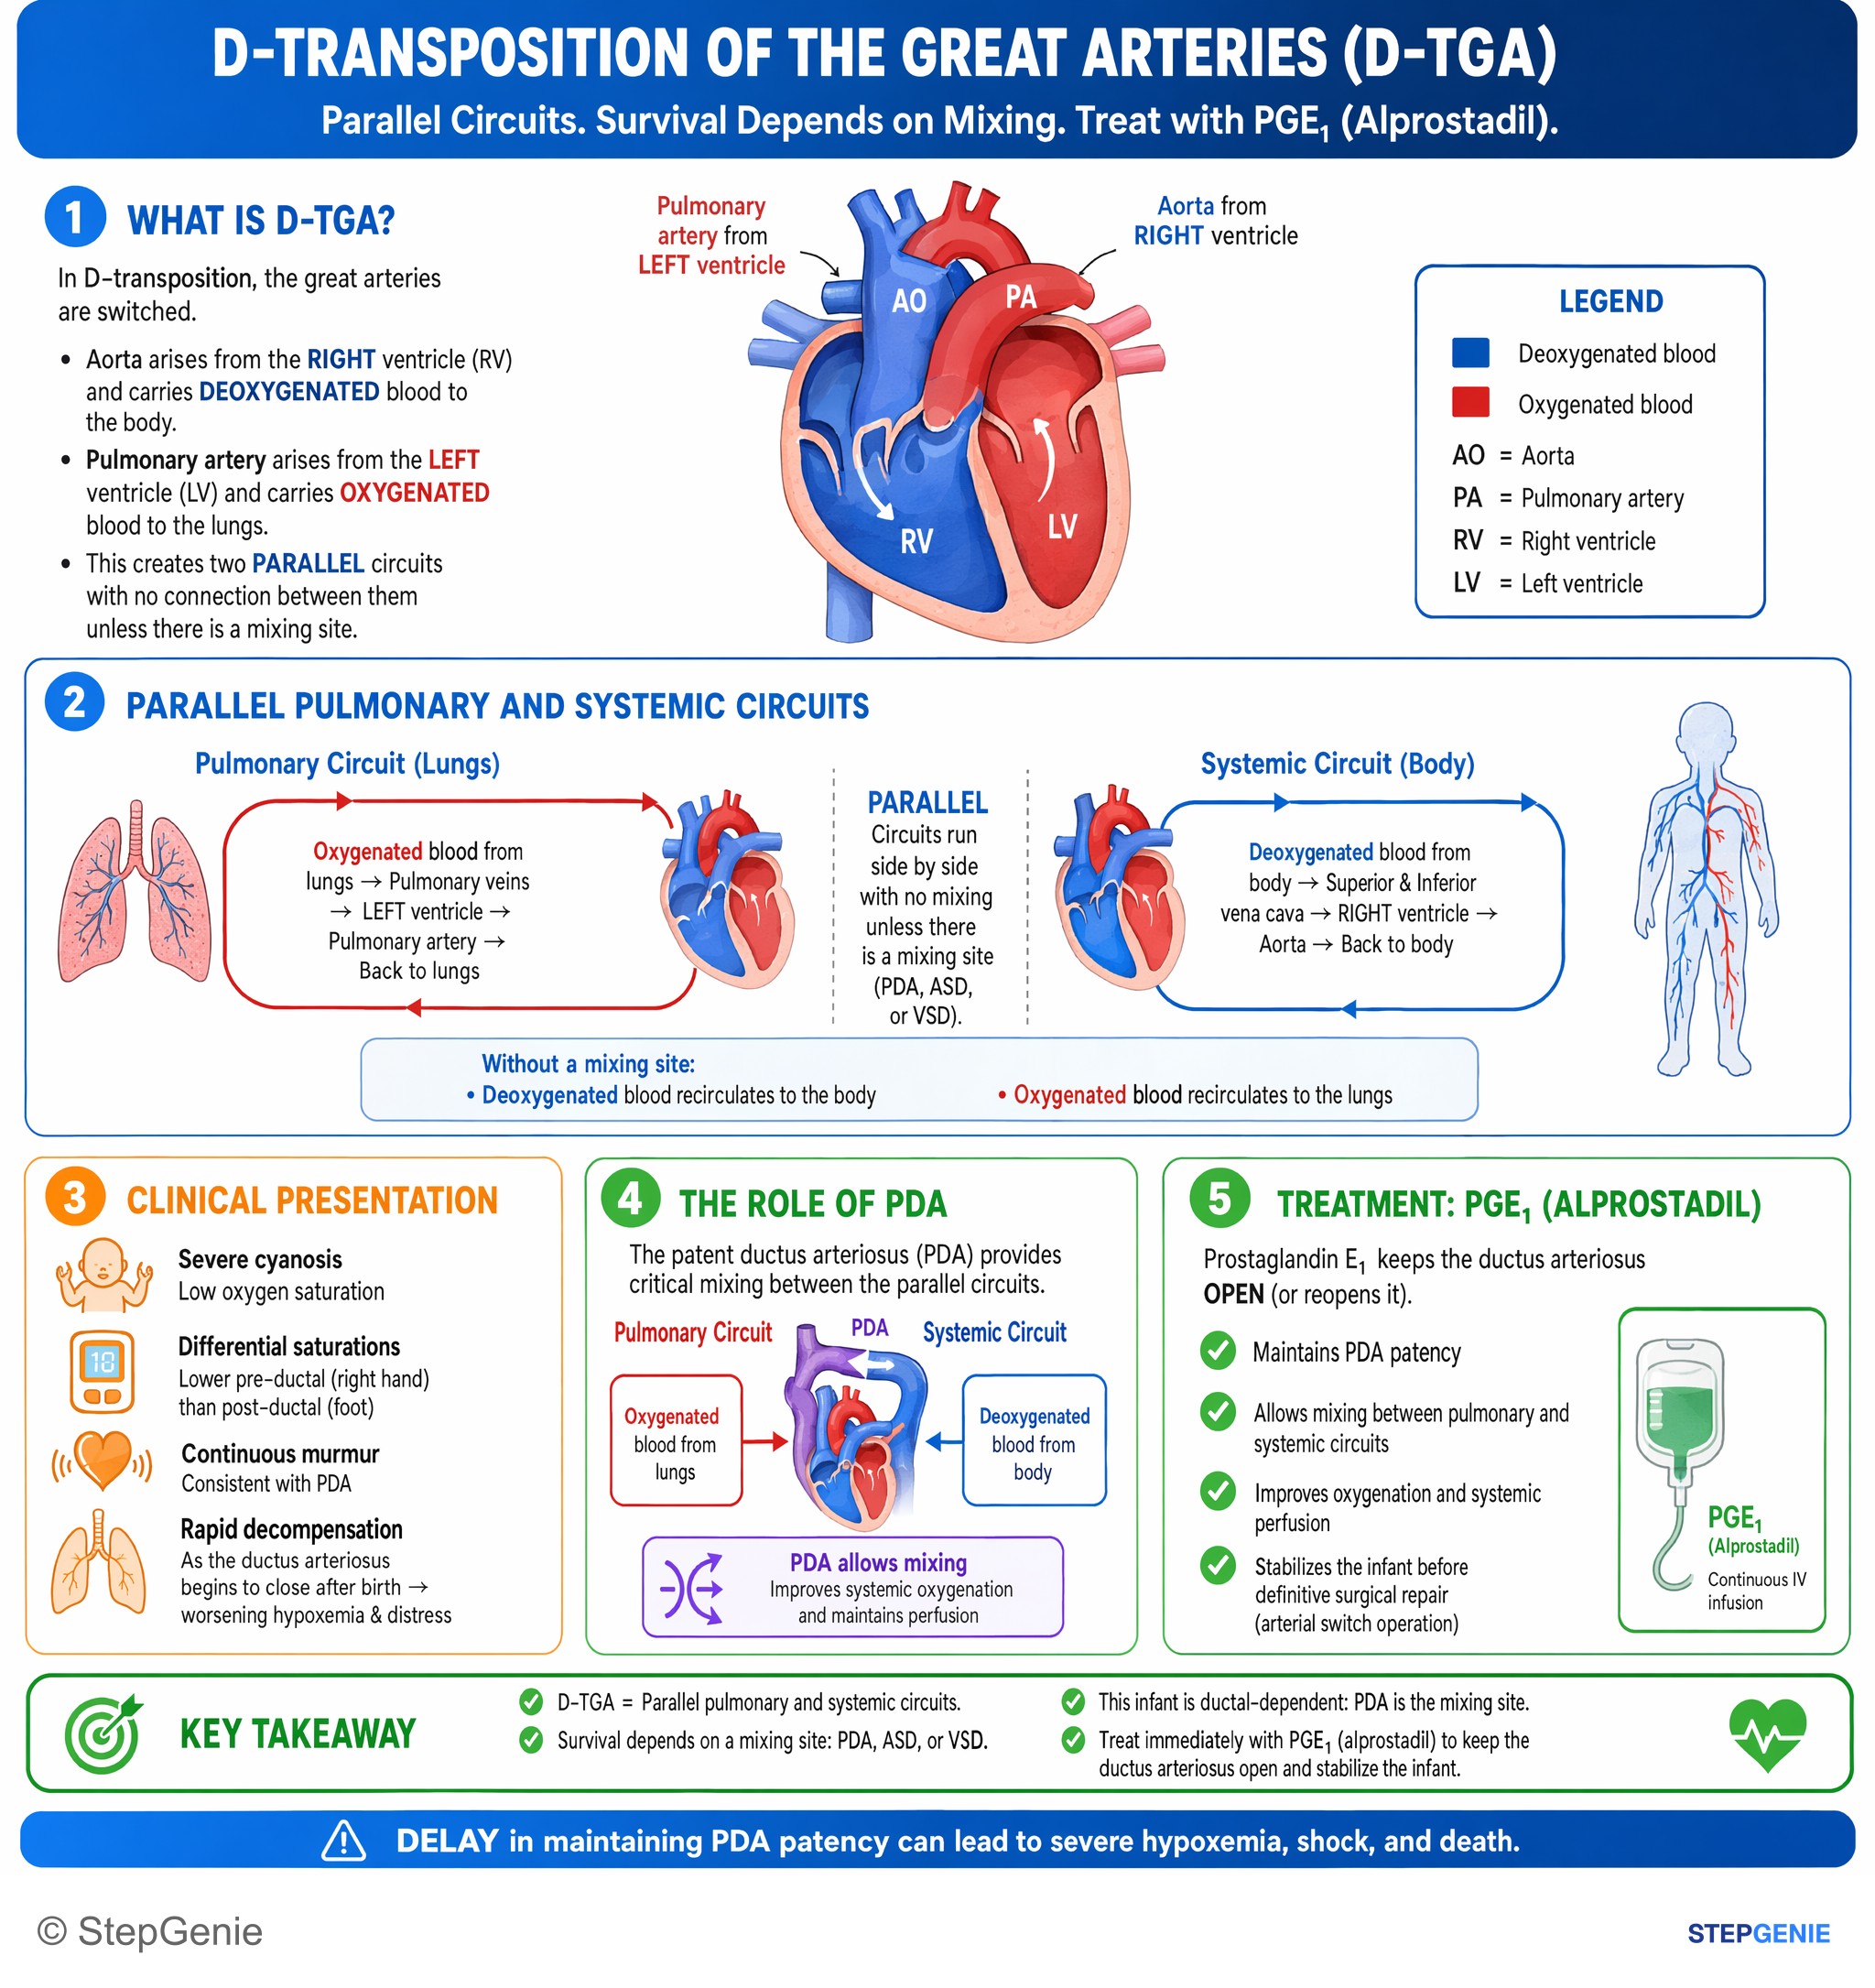
D-transposition of the great arteries: parallel pulmonary/systemic circuits; survival depends on PDA/ASD/VSD. Treat with PGE1…
USMLE Step 2Frequently Asked Questions
Why does transposition of the great arteries cause cyanosis right after birth?
In d-TGA the aorta arises from the right ventricle and the pulmonary artery from the left ventricle, so the two circulations run in parallel. Deoxygenated systemic venous blood is pumped straight back to the body, while oxygenated blood returning from the lungs is pumped back to the lungs. Oxygen reaches the body only where the circuits mix, through a patent foramen ovale or ASD, a VSD or a PDA. Without enough mixing, severe cyanosis and metabolic acidosis develop within hours of birth.
What is the first-line treatment for transposition of the great arteries?
Start a prostaglandin E1 (alprostadil) infusion to keep the ductus arteriosus open, which increases pulmonary blood flow and mixing at the atrial level, and correct metabolic acidosis. If the baby stays severely hypoxemic or the foramen ovale is restrictive, balloon atrial septostomy (the Rashkind procedure) enlarges the atrial opening. The definitive repair is the arterial switch (Jatene) operation with transfer of the coronary arteries, done in the first weeks of life (typically the first week per Merck, usually the first month per the CDC). The PGE1 adverse effect to know is apnea.
What causes the egg on a string sign in transposition of the great arteries?
The egg on a string is the classic chest x-ray of d-TGA: an egg-shaped cardiac silhouette sitting on a narrow upper mediastinum, which forms the string. The mediastinum looks narrow because the great arteries have lost their normal criss-cross relationship, and the thymus may be small. The film supports the diagnosis but does not make it; echocardiography confirms the anatomy and shows where blood is mixing. Contrast it with the boot-shaped heart of tetralogy of Fallot.
What is the difference between d-TGA and congenitally corrected (L-)TGA?
In d-TGA only the great arteries are switched: the aorta leaves the right ventricle and the pulmonary artery leaves the left ventricle, giving parallel circulations and severe cyanosis at birth. In congenitally corrected (L-)TGA the ventricles are also switched relative to the atria, a double discordance, so blood still flows in series and most patients are not cyanotic. Its problems are a right ventricle pumping to the body that can fail, a leaky tricuspid valve and complete heart block, sometimes found only in adulthood.
What are the classic exam clues for transposition of the great arteries?
Think d-TGA when a newborn, classically a large boy born to a mother with diabetes, becomes deeply cyanotic within hours of birth with few other findings: a single loud S2 and no murmur. Oxygen saturation barely rises on 100% oxygen, metabolic acidosis develops, and the chest x-ray shows an egg on a string. Reverse differential cyanosis, with the upper body bluer than the lower body, suggests d-TGA with a PDA plus severe coarctation, an interrupted aortic arch or suprasystemic pulmonary hypertension.
What embryologic defect causes transposition of the great arteries?
The classic Step 1 answer is failure of the aorticopulmonary (conotruncal) septum to spiral: the septum forms straight, so the aorta ends up above the right ventricle and the pulmonary artery above the left. Neural crest cells contribute to this septation, which is why d-TGA is grouped with the other conotruncal defects. A newer explanation focuses on abnormal conal development, with an underdeveloped subpulmonary conus and a persistent subaortic conus. Persistent truncus arteriosus, by contrast, is failure of the septum to form.