Tetralogy of Fallot (TOF) is the most common cyanotic congenital heart defect overall: a large malalignment ventricular septal defect (VSD), right ventricular outflow tract (RVOT) obstruction, an overriding aorta and right ventricular hypertrophy (RVH), all caused by anterosuperior (anterocephalad) deviation of the infundibular (conal) septum. How blue the child is depends on how severe the RVOT obstruction is, because that obstruction drives right-to-left shunting across the VSD. The classic clues are a harsh systolic ejection murmur at the left upper sternal border from the RVOT (not the VSD), a boot-shaped heart with decreased pulmonary markings, an association with 22q11.2 deletion, and hypercyanotic ("tet") spells that peak at 2-4 months and ease with the knee-chest position (or squatting in toddlers), which raises systemic vascular resistance (SVR). Complete repair is usually done at 2-6 months; afterward, pulmonary regurgitation and arrhythmias are the lifelong issues.
The four defects at a glance
Mnemonic: PROVe = Pulmonary (RVOT) stenosis, RVH, Overriding aorta, VSD.
| Component | What it is | What it causes |
|---|---|---|
| VSD | Large, nonrestrictive malalignment VSD | Equal systolic pressures in both ventricles and the aorta; the VSD itself makes little or no murmur |
| RVOT obstruction | Subpulmonary (infundibular) narrowing with pulmonic valve stenosis, sometimes extending into the pulmonary arteries | Sets the direction of the shunt; produces the harsh ejection murmur |
| Overriding aorta | The aorta sits over the VSD | Receives blood from both ventricles |
| RVH | Thickened right ventricle | Pressure load from the obstruction: boot shape on x-ray, RVH with right axis deviation on ECG |
Embryology and associations
- One displaced septum, four findings. The infundibular (conal) septum is displaced anteriorly and superiorly. It crowds the subpulmonary outflow (RVOT obstruction) and leaves a malalignment VSD beneath an aorta that now overrides it; the obstructed right ventricle then hypertrophies.
- Conotruncal defect, neural crest link. Experimental ablation of neural crest cells reproduces conotruncal malformations, and faulty neural crest migration or outflow septation underlies TOF, persistent truncus arteriosus and d-TGA.
- 22q11.2 deletion (DiGeorge) syndrome: conotruncal heart defects (interrupted aortic arch, truncus arteriosus, TOF), thymic hypoplasia with T-cell deficiency, hypocalcemia from hypoparathyroidism and palate anomalies. Review it in the DiGeorge breakdown. TOF also occurs with Down syndrome and Alagille syndrome.
- Associated cardiac findings: right aortic arch (25%), coronary artery anomalies (5-10%), branch pulmonary artery stenosis, aortopulmonary collaterals, ASD, PDA, extra muscular VSDs and complete AV septal defect.
- How common: 7-10% of congenital heart disease; about 1 in 2,041 US births, roughly 1,754 babies a year (CDC). TOF is about twice as common as d-TGA (4.7 vs 2.3 per 10,000 births), but d-TGA is the most common cardiac cause of cyanosis in newborns.
Pathophysiology: why a VSD shunts right to left
- The VSD is large, so both ventricles and the aorta share the same systolic pressure. Right ventricular blood goes where resistance is lower: forward past the obstruction into the pulmonary artery, or across the VSD into the aorta. The balance between RVOT obstruction and SVR decides.
- Mild obstruction: the shunt runs left to right, with little or no cyanosis (an acyanotic or "pink" tet).
- Severe obstruction: the shunt runs right to left, giving cyanosis that responds poorly to supplemental oxygen, because the shunted blood never passes through the lungs (compare dead space vs shunt).
- Newborns with severe obstruction are markedly cyanotic, struggle to breathe during feeds and gain weight poorly. When pulmonary blood flow depends on the ductus, prostaglandin E1 keeps the ductus arteriosus open.
Tet spells and squatting
- When: young infants, with a peak at 2-4 months of age.
- Triggers: crying, defecation, anything that suddenly lowers SVR (such as playing or kicking the legs on waking), tachycardia and hypovolemia. Spells cluster in the morning and in warm weather, when SVR is low; a warm bath can do the same.
- Mechanism: worsening RVOT obstruction, rising pulmonary vascular resistance and falling SVR feed each other in a vicious cycle of more right-to-left shunting and deeper hypoxemia.
- Signs: hyperpnea (rapid, deep breathing), irritability and prolonged crying, deepening cyanosis, and a murmur that fades or disappears because less blood crosses the obstructed outflow tract. Untreated, spells can cause limpness, seizures and occasionally death.
- Squatting: some toddlers squat intermittently. Squatting raises SVR and aortic pressure, which cuts right-to-left shunting and sends more blood to the lungs. The knee-chest position does the same for an infant.
Exam, x-ray, ECG and echo
| Test | TOF finding |
|---|---|
| Auscultation | Harsh grade 3-5/6 systolic ejection murmur at the left mid and upper sternal border; single S2; RV impulse, sometimes a thrill |
| Chest x-ray | Boot-shaped heart (coeur en sabot): upturned apex from RVH and a concave main pulmonary artery segment; decreased pulmonary vascular markings; right aortic arch in 25% |
| ECG | RVH and right axis deviation, sometimes right atrial enlargement |
| Echocardiography | Diagnostic (2-dimensional echo with color flow and Doppler) |
| CT, MRI or catheterization | Mainly to define coronary artery anatomy that echo cannot clarify; catheterization is rarely needed |
| Newborn pulse oximetry screening | Picks up some infants before symptoms appear |
Managing a tet spell
The aim is to raise SVR, relax the infundibulum and break the cycle. Escalate stepwise (the exact order of the drug steps varies between sources):
- Calm the infant (in a parent's arms) in the knee-chest position to raise SVR.
- Oxygen (blow-by).
- Morphine to calm the infant and relax the RVOT obstruction.
- IV isotonic fluid boluses to expand volume.
- IV beta-blocker (propranolol or esmolol): lower contractility relaxes the RVOT, and a slower heart rate improves coronary perfusion.
- Phenylephrine, an α1 agonist, to raise SVR directly.
- Sodium bicarbonate for metabolic acidosis; ketamine is another option.
- Refractory spells: intubation with paralysis and anesthesia, ECMO or urgent surgery.
Between spells, oral propranolol can prevent them until repair. Anything that lowers SVR (vasodilators, a warm bath) or speeds the heart makes spells worse.
Surgery: palliation and complete repair
- Complete repair, usually elective at 2-6 months (earlier for spells or severe obstruction): patch closure of the VSD, widening of the RVOT by muscle resection, pulmonic valvuloplasty and, when needed, patch enlargement of the main pulmonary artery. A transannular patch is placed when the pulmonary valve annulus is hypoplastic. Perioperative mortality is under 5% for uncomplicated TOF.
- Palliation for some neonates with low birth weight or complex anatomy: a modified Blalock-Taussig-Thomas shunt (subclavian artery to pulmonary artery through a synthetic graft) or a catheter-placed stent in the RVOT or ductus.
- Untreated, survival is about 55% at 5 years and 30% at 10 years.
After repair: pulmonary regurgitation and arrhythmias
- Pulmonary regurgitation is the signature late problem: the repaired pulmonary valve often leaks, the right ventricle dilates, and many patients need pulmonary valve replacement in adolescence or early adulthood.
- The 2025 ACC/AHA adult congenital heart disease guideline times referral for pulmonary valve replacement by right ventricular end-systolic volume (>80 mL/m²) and other metrics rather than end-diastolic volume.
- Arrhythmias: repaired TOF carries a higher risk of heart rhythm problems, and the 2025 guideline's updated arrhythmia recommendations include catheter ablation of ventricular tachycardia.
- A bioprosthetic pulmonary valve that fails acutely or subacutely should prompt a search for endocarditis.
- Lifelong follow-up in adult congenital heart disease care. Endocarditis prophylaxis covers unrepaired cyanotic disease, the first 6 months after repair with prosthetic material, residual defects next to a patch, and prosthetic valves (review infective endocarditis).
How USMLE tests TOF
- Murmur source: the RVOT, not the VSD. During a spell the murmur gets softer, not louder.
- Squatting or knee-chest: ↑ SVR → ↓ right-to-left shunt → ↑ pulmonary blood flow.
- TOF vs d-TGA: boot-shaped heart with decreased pulmonary markings vs "egg on a string"; spells peaking at 2-4 months vs cyanosis within hours of birth; 22q11.2 vs maternal diabetes. See the transposition guide.
- TOF vs Eisenmenger: both shunt right to left across a VSD, but in TOF the cause is anatomic RVOT obstruction present from birth, while in Eisenmenger syndrome a left-to-right shunt reverses after years of pulmonary vascular disease.
- PGE1 in a cyanotic newborn: keeps the ductus open for pulmonary blood flow; its boxed warning is apnea (about 10-12% of treated neonates with congenital heart defects, mostly under 2 kg and in the first hour).
Practice question
A 3-month-old boy is brought in after several morning episodes of inconsolable crying with rapid, deep breathing and deepening blue color. Between episodes he is mildly cyanotic. There is a grade 4/6 harsh systolic ejection murmur at the left upper sternal border and a single S2. During an episode in clinic, the murmur becomes much softer and his oxygen saturation falls to 62%. Chest x-ray shows an upturned cardiac apex, a concave main pulmonary artery segment and decreased pulmonary vascular markings. Which is the most appropriate first step?
A. Place the infant in the knee-chest position and give oxygen B. Start an IV dopamine infusion C. Give IV furosemide D. Give IV hydralazine E. Start an IV prostaglandin E1 infusion
Answer: A. This is a hypercyanotic (tet) spell in tetralogy of Fallot: peak age, morning onset, hyperpnea, a murmur that fades as RVOT flow falls, and a boot-shaped heart. The knee-chest position raises SVR and reduces right-to-left shunting, and oxygen is given alongside. If the spell continues: IV fluid boluses and morphine, then phenylephrine and/or an IV beta-blocker.
- B: dopamine increases contractility and heart rate, which worsens the dynamic infundibular obstruction; beta-blockers help for the opposite reason.
- C: furosemide depletes volume, and hypovolemia triggers spells. The lungs are underperfused, not congested.
- D: hydralazine lowers SVR, which increases right-to-left shunting; the drug that helps raises SVR (phenylephrine).
- E: PGE1 is for neonates whose pulmonary blood flow depends on the ductus, not for spells in a 3-month-old, and it can cause apnea.
Key takeaways
- PROVe: pulmonary (RVOT) stenosis, RVH, overriding aorta, VSD, all from anterosuperior deviation of the infundibular septum, a neural crest-related conotruncal defect.
- Most common cyanotic CHD overall (d-TGA is the most common cardiac cause of newborn cyanosis); linked to 22q11.2 deletion, right aortic arch (25%) and coronary anomalies.
- RVOT obstruction vs SVR sets the shunt: mild = pink, severe = right-to-left cyanosis that oxygen doesn't fix.
- Harsh SEM at the LUSB from the RVOT, single S2, boot-shaped heart, decreased pulmonary markings, RVH with right axis deviation.
- Tet spells peak at 2-4 months and the murmur softens; treat with knee-chest position, oxygen, morphine, fluids, a beta-blocker and phenylephrine. Squatting raises SVR.
- Complete repair at 2-6 months; long term, watch for pulmonary regurgitation (valve replacement guided by RV end-systolic volume) and ventricular arrhythmias.
Sources
- Tetralogy of Fallot — Merck Manual Professional Edition (2023)
- Overview of Congenital Cardiovascular Anomalies — Merck Manual Professional Edition (2025)
- DiGeorge Syndrome — Merck Manual Professional Edition (2024)
- Tetralogy of Fallot — CDC Congenital Heart Defects (2026)
- Tetralogy of Fallot — American Heart Association (2026)
- Tetralogy of Fallot — Children's Hospital of Philadelphia
- 2025 ACC/AHA/HRS/ISACHD/SCAI Guideline for the Management of Adults With Congenital Heart Disease: Top Things to Know — American Heart Association (2025)
- New ACC/AHA Guideline Addresses Management of Congenital Heart Disease in Adults — American College of Cardiology (2025)
- Cyanotic Cardiac Lesions — UTMB Pediatric Education, University of Texas Medical Branch
- Embryology — UTMB Pediatric Education, University of Texas Medical Branch
- Tetralogy of Fallot — Medscape Reference (2016)
- PROSTIN VR PEDIATRIC (alprostadil) injection label — DailyMed, US National Library of Medicine (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
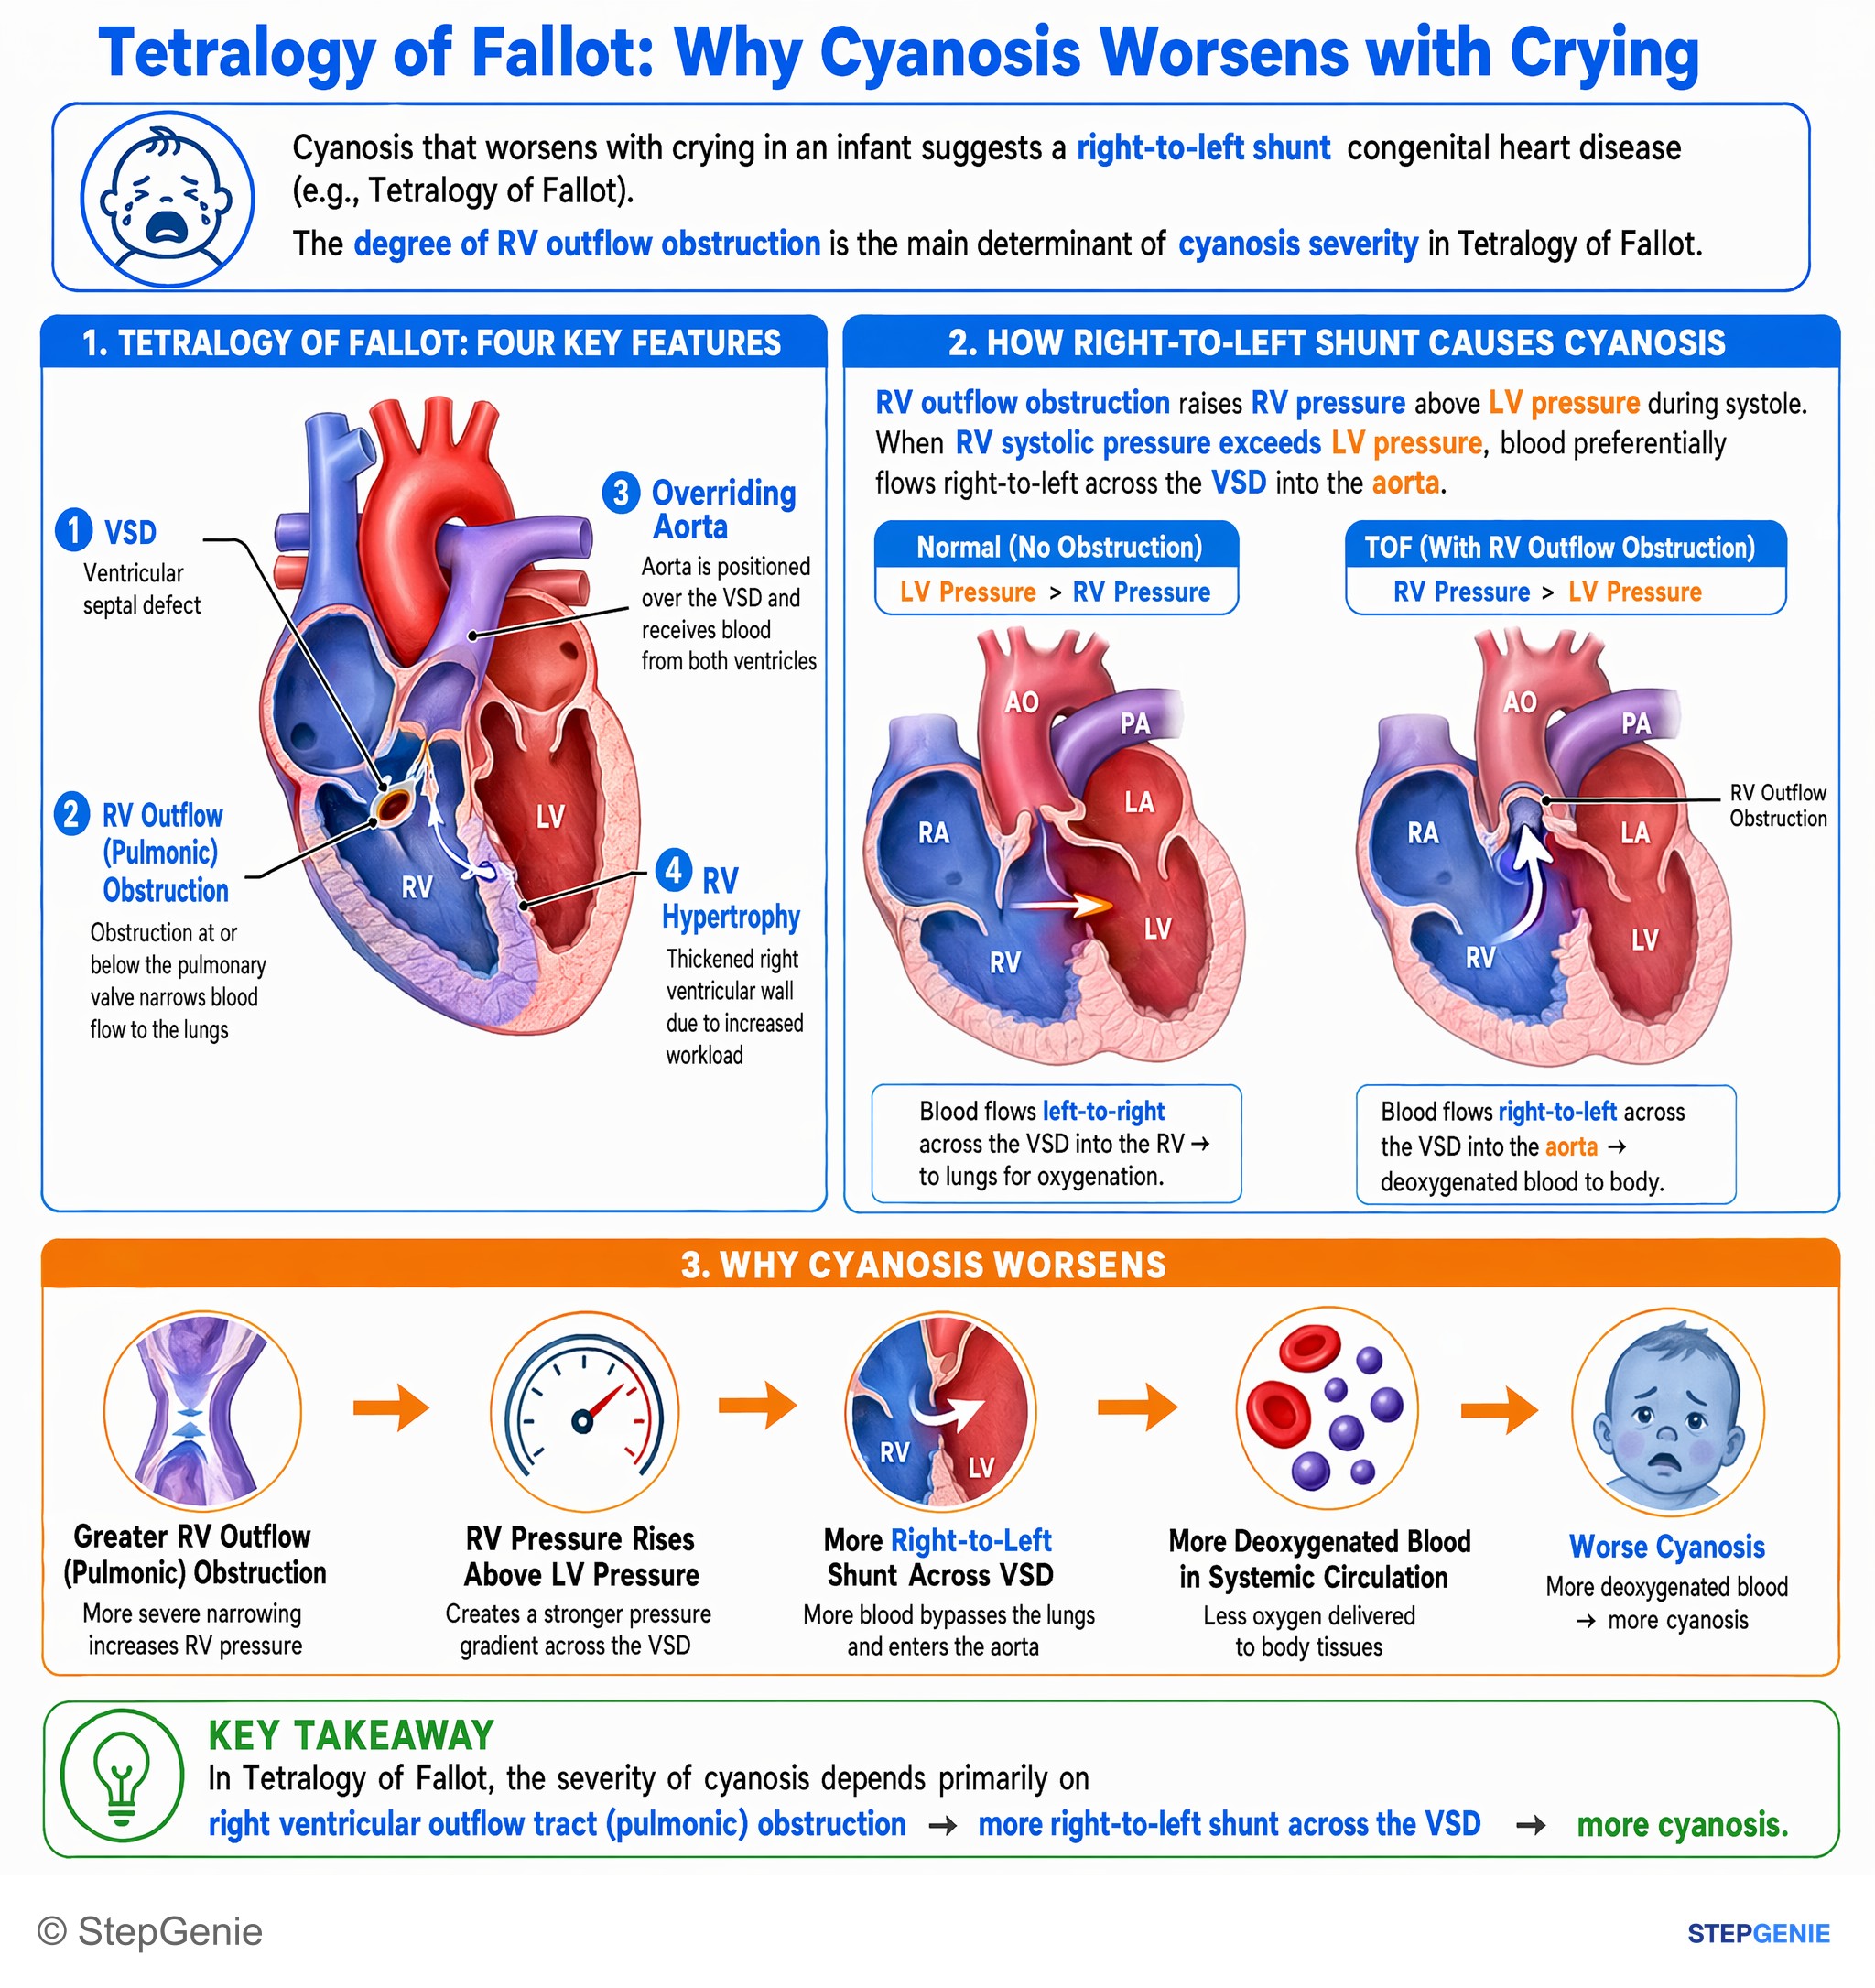
Tetralogy of Fallot cyanosis severity depends primarily on **right ventricular outflow tract (pulmonic) obstruction → more right-to-left…
USMLE Step 1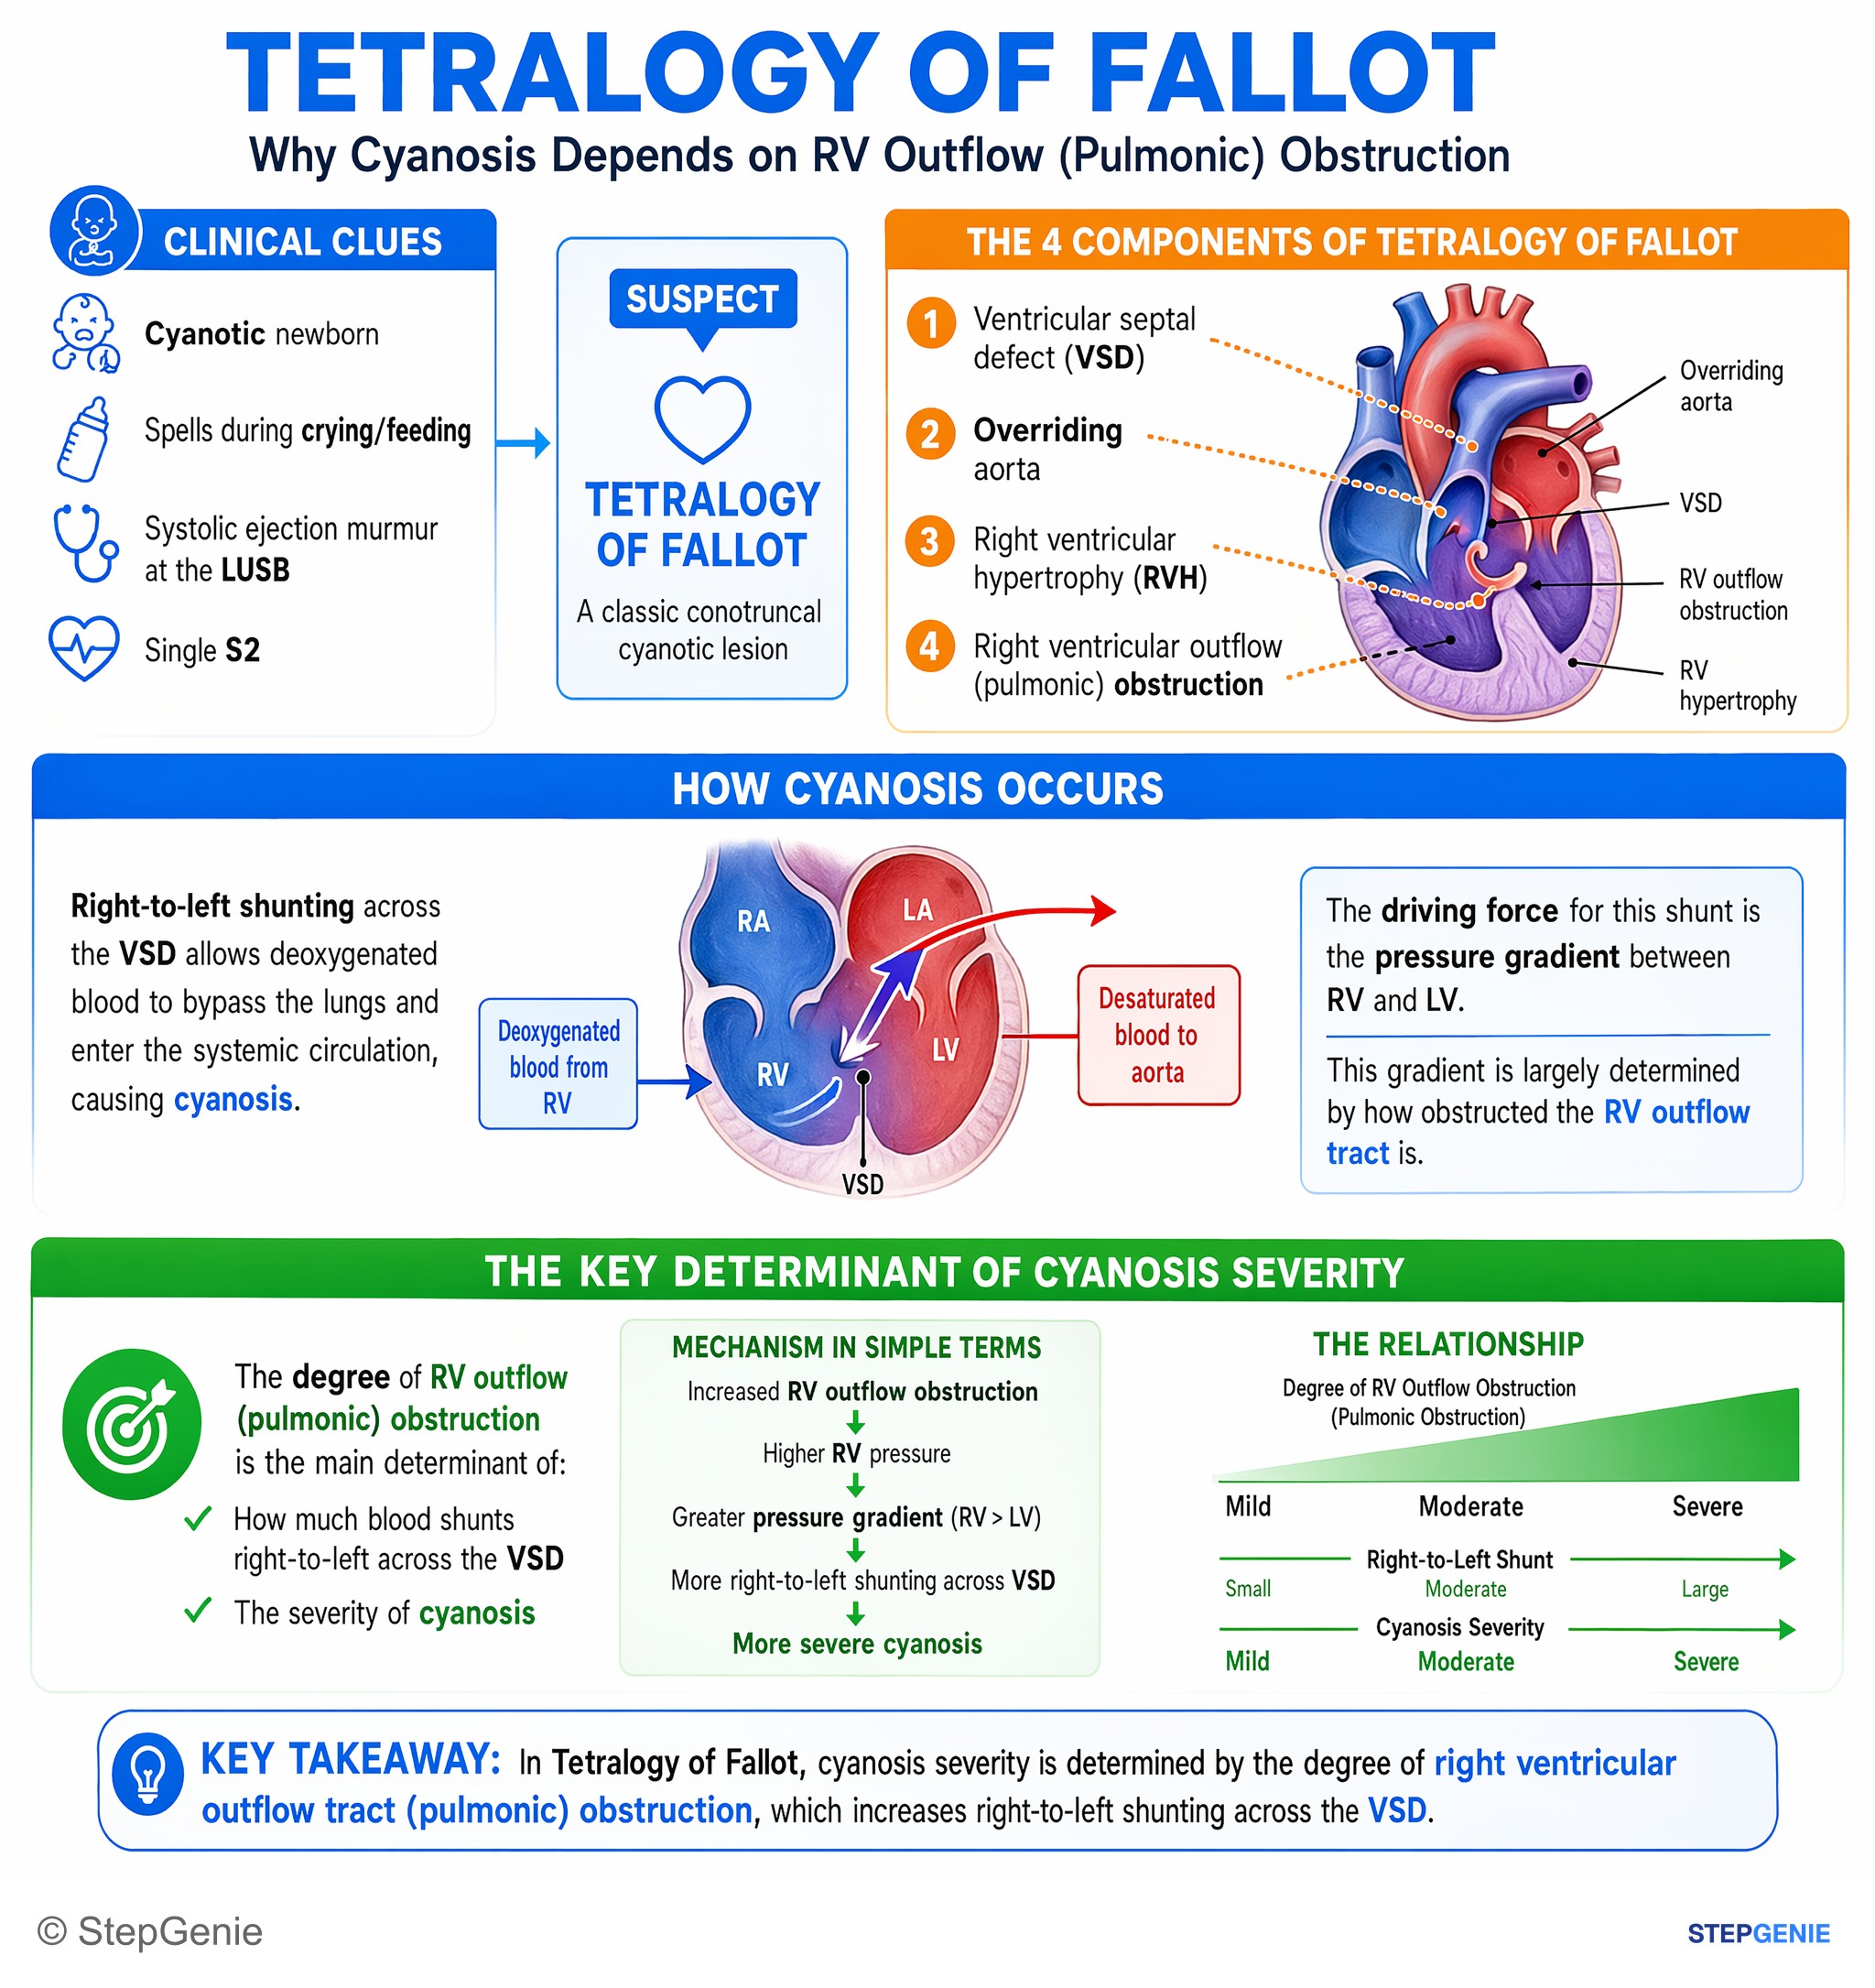
Tetralogy of Fallot cyanosis severity is determined by degree of right ventricular outflow tract (pulmonic) obstruction, which increases…
USMLE Step 1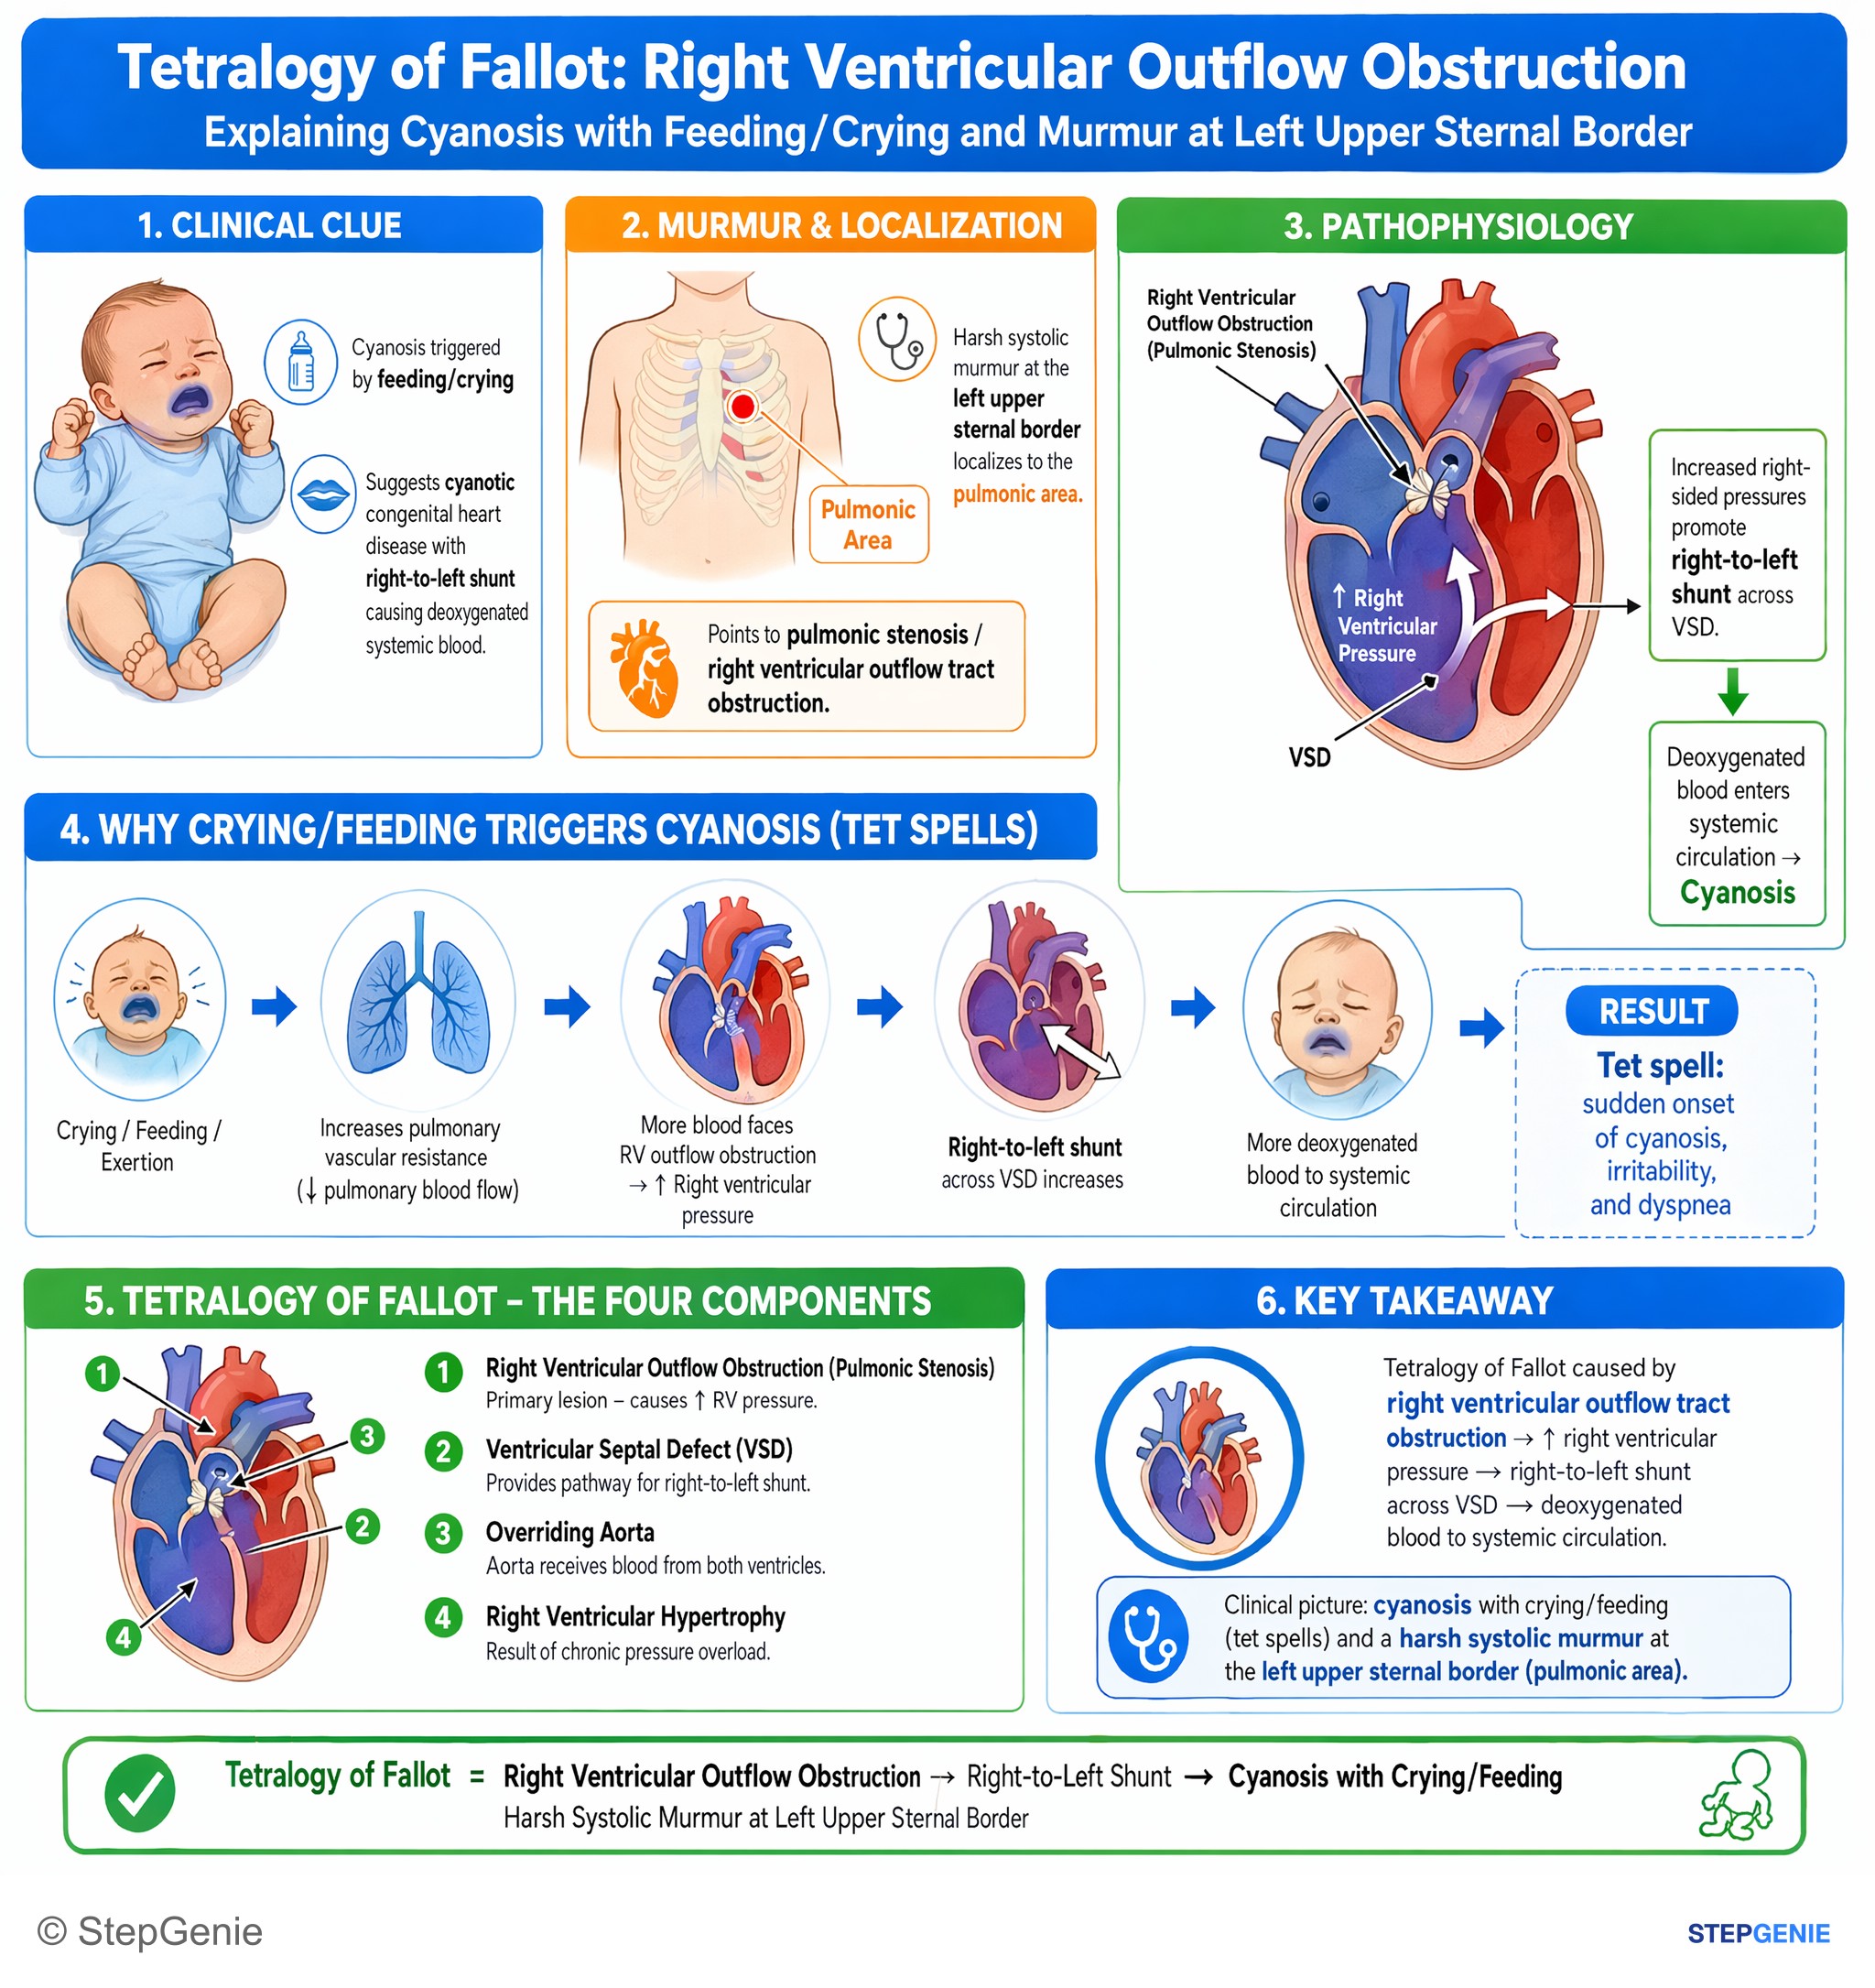
Tetralogy of Fallot from right ventricular outflow tract obstruction → right-to-left shunt, cyanosis with crying/feeding, harsh systolic…
USMLE Step 1Frequently Asked Questions
What are the four defects in tetralogy of Fallot?
Tetralogy of Fallot combines a large ventricular septal defect, right ventricular outflow tract obstruction (infundibular narrowing plus pulmonic valve stenosis), an overriding aorta and right ventricular hypertrophy. The mnemonic PROVe lists them: pulmonary stenosis, RVH, overriding aorta, VSD. All four follow from one embryologic error, anterosuperior deviation of the infundibular (conal) septum, which narrows the outflow tract and leaves a malalignment VSD under the aorta. The hypertrophy is the right ventricle's response to the obstruction.
Why does squatting help in tetralogy of Fallot?
Squatting raises systemic vascular resistance and aortic pressure. In tetralogy of Fallot the large VSD lets right ventricular blood go either into the aorta or past the outflow obstruction into the lungs, and the split depends on the balance between that obstruction and systemic resistance. When squatting raises systemic resistance, less blood shunts right to left into the aorta and more flows to the lungs, so oxygen saturation improves. The knee-chest position used for infants during tet spells works the same way.
What is a tet spell and how is it treated?
A tet spell, or hypercyanotic spell, is a sudden episode of deepening cyanosis with rapid, deep breathing, irritability and prolonged crying, with a peak at 2 to 4 months of age. Crying, defecation, tachycardia, hypovolemia or anything that lowers systemic vascular resistance can trigger it. Treatment escalates from calming the infant in the knee-chest position and giving oxygen, to morphine, IV fluid boluses, an IV beta-blocker such as propranolol or esmolol, and phenylephrine; refractory spells need intubation, ECMO or urgent surgery.
Why is the heart boot-shaped on chest x-ray in tetralogy of Fallot?
The boot shape, called coeur en sabot, comes from two features. Right ventricular hypertrophy turns the cardiac apex upward, and the small, obstructed main pulmonary artery leaves a concave segment along the upper left heart border where it would normally bulge. The lung fields also show decreased pulmonary vascular markings because less blood reaches the lungs. About a quarter of patients have a right-sided aortic arch on the same film.
Which murmur is heard in tetralogy of Fallot, and why does it fade during a spell?
The murmur is a harsh grade 3 to 5 out of 6 systolic ejection murmur at the left mid and upper sternal border. It comes from blood forced through the narrowed right ventricular outflow tract, not from the VSD, which is large and nonrestrictive. The second heart sound is usually single. During a tet spell the outflow obstruction worsens and more blood shunts across the VSD into the aorta, so less blood crosses the outflow tract and the murmur becomes softer or disappears.
When is tetralogy of Fallot repaired, and what problems remain afterward?
Complete repair is usually done electively at 2 to 6 months of age, or sooner if spells or severe obstruction develop: the VSD is patched and the outflow tract widened, with a transannular patch if the pulmonary valve annulus is small. Perioperative mortality is under 5 percent for uncomplicated cases. Long term, the repaired pulmonary valve often leaks and the right ventricle dilates, so many patients need pulmonary valve replacement in adolescence or adulthood. Arrhythmias, including ventricular tachycardia, need lifelong follow-up.