A patent ductus arteriosus (PDA) is a ductus arteriosus that stays open after birth, leaving a channel between the pulmonary artery and the descending aorta; once pulmonary resistance falls, blood shunts left to right, from the aorta into the pulmonary artery, in both systole and diastole. The classic findings are a continuous "machinery" murmur loudest just below the left clavicle, bounding pulses and a wide pulse pressure, and echocardiography confirms it. Prostaglandins keep the ductus open and blocking prostaglandin synthesis helps close it: indomethacin and ibuprofen (FDA approved for preterm infants) or acetaminophen (an off-label option) can close a hemodynamically significant PDA, while alprostadil (PGE1) keeps the ductus open in duct-dependent heart disease. Big associations: prematurity, female sex and congenital rubella.
Why the ductus is open before birth and closes after
- Fetus: pulmonary resistance is high, so about 90-95% of right heart output bypasses the lungs, much of it through the ductus into the aorta (right to left). Low fetal PaO2 (about 25 mm Hg) and locally produced prostaglandins keep the ductus open.
- Birth: systemic resistance rises above pulmonary resistance, so ductal flow reverses to left to right (transitional circulation). The rise in PaO2 and fall in prostaglandins start closure, typically within the first 10-15 hours, and the ductus constricts by about 24-72 hours.
- Reversal risk: asphyxia with hypoxia and hypercarbia constricts pulmonary arterioles and dilates the ductus, pushing a stressed newborn back toward fetal circulation.
- Location: the ductus meets the aorta just beyond the left subclavian artery, the same spot where coarctation forms (see coarctation of the aorta).
| Keeps the ductus open | Helps close it |
|---|---|
| Low PO2 (fetal life, hypoxia, asphyxia) | Rising PaO2 after the first breaths |
| Prostaglandins, including an alprostadil (PGE1) infusion | Falling prostaglandins: indomethacin, ibuprofen (COX inhibitors), acetaminophen |
| Prematurity | Maternal NSAIDs at about 30 weeks or later: premature closure in utero (a labeled NSAID warning) |
Who gets a PDA
- 5-10% of congenital heart disease, with a male:female ratio of 1:3.
- Prematurity: present in about 45% of infants under 1,750 g and 70-80% of those under 1,200 g; about a third close on their own, even in extremely low birth weight infants.
- Congenital rubella: the cardiac defects of congenital rubella syndrome are PDA and pulmonary artery stenosis, alongside cataracts, retinopathy, hearing loss and microcephaly (see measles, mumps and rubella).
- Also more common with neonatal respiratory distress syndrome and Down syndrome, and often present alongside other defects such as hypoplastic left heart syndrome, transposition and pulmonary stenosis.
Hemodynamics and how it presents
Because aortic pressure exceeds pulmonary pressure throughout the cardiac cycle, flow is continuous. The extra pulmonary flow returns to the left atrium and left ventricle (volume overload), and the diastolic runoff into the pulmonary artery lowers diastolic pressure (wide pulse pressure; echo can show diastolic flow reversal in the descending aorta).
| Patient | What you find |
|---|---|
| Small PDA | Usually no symptoms; normal pulses; grade 1-3/6 continuous murmur at the upper left sternal border that runs through S2 into diastole |
| Large PDA, term infant | Heart failure: poor feeding, failure to thrive, tachypnea, sweating or dyspnea with feeds, tachycardia; bounding pulses, wide pulse pressure; loud "machinery" murmur; apical diastolic rumble from high mitral flow |
| Preterm infant | Respiratory distress, apnea, rising ventilator needs, bounding pulses, hyperdynamic precordium; the murmur may be continuous, systolic only, or absent |
| Untreated large PDA → Eisenmenger | Pulmonary hypertension reverses the shunt; desaturated blood enters the aorta beyond the arm vessels → cyanosis and clubbing of the toes but not the fingers (differential cyanosis) |
- Location: loudest at the second intercostal space just below the medial left clavicle (the "left infraclavicular" area of exam stems).
- As pulmonary resistance rises, the diastolic part of the murmur fades, and the murmur can disappear when pressures equalize: a quiet murmur is not always good news.
- Preterm complications of a significant PDA include heart failure, worse lung disease of prematurity, pulmonary hemorrhage, renal insufficiency, feeding intolerance, necrotizing enterocolitis (NEC) and death.
- Eisenmenger (see Eisenmenger syndrome) means the pulmonary vascular disease is irreversible, which rules out simply closing the defect; care shifts to pulmonary vasodilators and, for severe disease, heart-lung transplantation.
Diagnosis
- Echocardiography with color flow and Doppler establishes the diagnosis and its hemodynamic significance: ductal size (compared with the left pulmonary artery), flow velocity, left heart enlargement, diastolic flow reversal in the descending aorta and diastolic antegrade flow in the left pulmonary artery.
- Chest x-ray and ECG are normal with a small PDA. With a large shunt, the x-ray shows enlarged left atrium, left ventricle and ascending aorta with increased pulmonary vascular markings, and the ECG may show left ventricular hypertrophy.
- Cardiac catheterization is needed only for treatment (device closure).
Treatment: close it or keep it open
Preterm infants
- Supportive care: fluid restriction, a diuretic, a hematocrit of at least 35%, a neutral thermal environment and PEEP for ventilated infants. Preterm infants without respiratory or other compromise are typically not treated.
- Timing (2025 AAP clinical report, as summarized in its abstract): trials show no benefit of prophylactic or early (under 2 weeks) medical closure over expectant management, so it is not recommended. Beyond 2 weeks the data are insufficient for firm recommendations, and many clinicians attempt medical closure of a hemodynamically significant PDA.
| Drug | Status | Key points |
|---|---|---|
| Indomethacin IV | FDA approved: preterm infants 500-1,750 g when 48 hours of usual medical management is ineffective | 3 doses 12-24 hours apart, held if urine output falls below 0.6 mL/kg/h; transient oliguria, raised creatinine, bleeding |
| Ibuprofen lysine IV | FDA approved: preterm infants 500-1,500 g, no more than 32 weeks' gestation | Can displace bilirubin from albumin (caution with high bilirubin); platelet inhibition |
| Acetaminophen | Off-label (US labels cover pain and fever only) | Listed with ibuprofen as a medical-closure option in the abstract of the 2025 AAP report |
Shared contraindications (indomethacin and ibuprofen labels): untreated infection, active bleeding (especially intracranial or GI), thrombocytopenia or coagulation defects, NEC, significant renal impairment, and any duct-dependent heart lesion. If the PDA persists despite drugs, or drugs are contraindicated, the options are transcatheter closure (now more common than surgery in many centers, per the AAP abstract) or surgical ligation.
Term infants and children
- COX inhibitors are usually ineffective in full-term infants, so closure after the preterm period is by catheter or surgery.
- Transcatheter device closure is the treatment of choice after age 1, and some prefer it in term neonates and young infants; surgical ligation suits unfavorable anatomy.
- With heart failure or pulmonary hypertension, close after medical stabilization; without them, closure can be elective any time after age 1.
- Endocarditis prophylaxis is not needed before closure; it is required only for the first 6 months after closure, or if a residual defect sits next to a device or surgical material.
Keeping the ductus open: alprostadil (PGE1)
When a newborn's circulation depends on the ductus, an IV prostaglandin E1 infusion (started at 0.05-0.1 mcg/kg/min) keeps it open until surgery or catheter repair.
| Duct-dependent for | Examples |
|---|---|
| Systemic flow | Hypoplastic left heart syndrome, critical aortic stenosis, critical coarctation, interrupted aortic arch |
| Pulmonary flow | Pulmonary atresia, critical pulmonary stenosis, tricuspid atresia, severe tetralogy of Fallot |
| Mixing | Transposition of the great arteries |
Alprostadil boxed warning: apnea in about 10-12% of treated neonates, most often under 2 kg and in the first hour, so ventilatory support must be ready. Other effects: fever (about 14%), flushing (about 10%), bradycardia (about 7%) and seizures (about 4%); long infusions can cause cortical proliferation of the long bones and gastric outlet obstruction from antral hyperplasia (monitor after 120 hours).
How USMLE tests it: murmur look-alikes
| Lesion | Murmur | Discriminator |
|---|---|---|
| PDA | Continuous, machinery-like, below the left clavicle | Bounding pulses, wide pulse pressure, left atrial and ventricular enlargement |
| VSD | Holosystolic, loudest at the lower left sternal border | See the VSD cheat sheet |
| ASD (secundum) | Systolic ejection murmur from extra pulmonic flow | Wide, fixed split S2 |
| Coarctation | Systolic, upper left sternal border, left back | Upper-limb hypertension; weak, delayed femoral pulses |
| Venous hum | Continuous, right supraclavicular fossa | Normal in children |
More murmur pairs are in heart murmurs for USMLE.
Differential cyanosis has two classic stems. In a newborn, it classically points to persistent pulmonary hypertension of the newborn (PPHN) with right-to-left flow through the ductus: postductal (leg) saturation at least 5% lower than preductal (right arm) saturation, treated with oxygen, ventilation and inhaled nitric oxide. In an older child or adult with an unrepaired PDA, it points to Eisenmenger syndrome.
Practice question
A boy born at 26 weeks' gestation (birth weight 850 g) is 16 days old in the neonatal intensive care unit. Over 2 days his ventilator settings have had to be increased. He has bounding peripheral pulses, a hyperdynamic precordium and a continuous murmur at the upper left sternal border. Blood pressure is 52/22 mm Hg. Echocardiography shows a large ductus arteriosus with left-to-right flow and diastolic flow reversal in the descending aorta. Platelet count, renal function and abdominal examination are normal. The team decides to attempt pharmacologic closure. Which drug is most appropriate?
A. Alprostadil B. Ibuprofen lysine C. Inhaled nitric oxide D. Digoxin E. Furosemide
Answer: B. This is a hemodynamically significant PDA in a preterm infant older than 2 weeks, with none of the contraindications to COX inhibitors (bleeding, low platelets, NEC, renal impairment, duct-dependent heart disease). Ibuprofen lysine (or indomethacin) lowers prostaglandin production and promotes ductal constriction; acetaminophen is an off-label alternative.
- A: alprostadil is PGE1, which opens the ductus. It is for duct-dependent lesions, and apnea is its boxed warning.
- C: inhaled nitric oxide is a pulmonary vasodilator for persistent pulmonary hypertension of the newborn; lowering pulmonary resistance would increase this left-to-right shunt.
- D: the indomethacin label lists digitalis among "usual medical management" measures, but digoxin does not close the ductus.
- E: a diuretic can ease fluid overload as supportive care, but it does not close the ductus.
Key takeaways
- PDA = persistent aorta-to-pulmonary artery connection; after birth the shunt is left to right, causing pulmonary overcirculation and left atrial and ventricular volume overload.
- Continuous machinery murmur below the left clavicle, bounding pulses, wide pulse pressure; preterm infants may have no murmur.
- Risk factors: prematurity, female sex (1:3), congenital rubella (PDA plus pulmonary artery stenosis).
- Close it: indomethacin or ibuprofen (FDA approved), acetaminophen off-label; no prophylactic or early (under 2 weeks) treatment (2025 AAP report, per its abstract); device or surgery if drugs fail. COX inhibitors usually fail in term infants.
- Keep it open: alprostadil (PGE1) for duct-dependent lesions; watch for apnea.
- Maternal NSAIDs at about 30 weeks or later can close the ductus before birth.
- Untreated large PDA → Eisenmenger → differential cyanosis (blue toes, pink fingers); closure is then no longer an option.
Sources
- Patent Ductus Arteriosus (PDA) — Merck Manual Professional Edition (2023)
- Overview of Congenital Cardiovascular Anomalies — Merck Manual Professional Edition (2025)
- Eisenmenger Syndrome — Merck Manual Professional Edition (2024)
- Cardiac Auscultation — Merck Manual Professional Edition (2025)
- Congenital Rubella — Merck Manual Professional Edition (2026)
- Patent ductus arteriosus — MedlinePlus Medical Encyclopedia (2025)
- Patent Ductus Arteriosus in Preterm Infants: AAP Clinical Report — Pediatrics (2025), abstract on PubMed
- Indomethacin for Injection label — DailyMed (2023)
- NEOPROFEN (ibuprofen lysine) injection label — DailyMed (2024)
- PROSTIN VR PEDIATRIC (alprostadil) label — DailyMed (2026)
- CELEBREX (celecoxib) label: NSAID fetal toxicity warning — DailyMed (2024)
- Coarctation of the Aorta — Merck Manual Professional Edition (2023)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
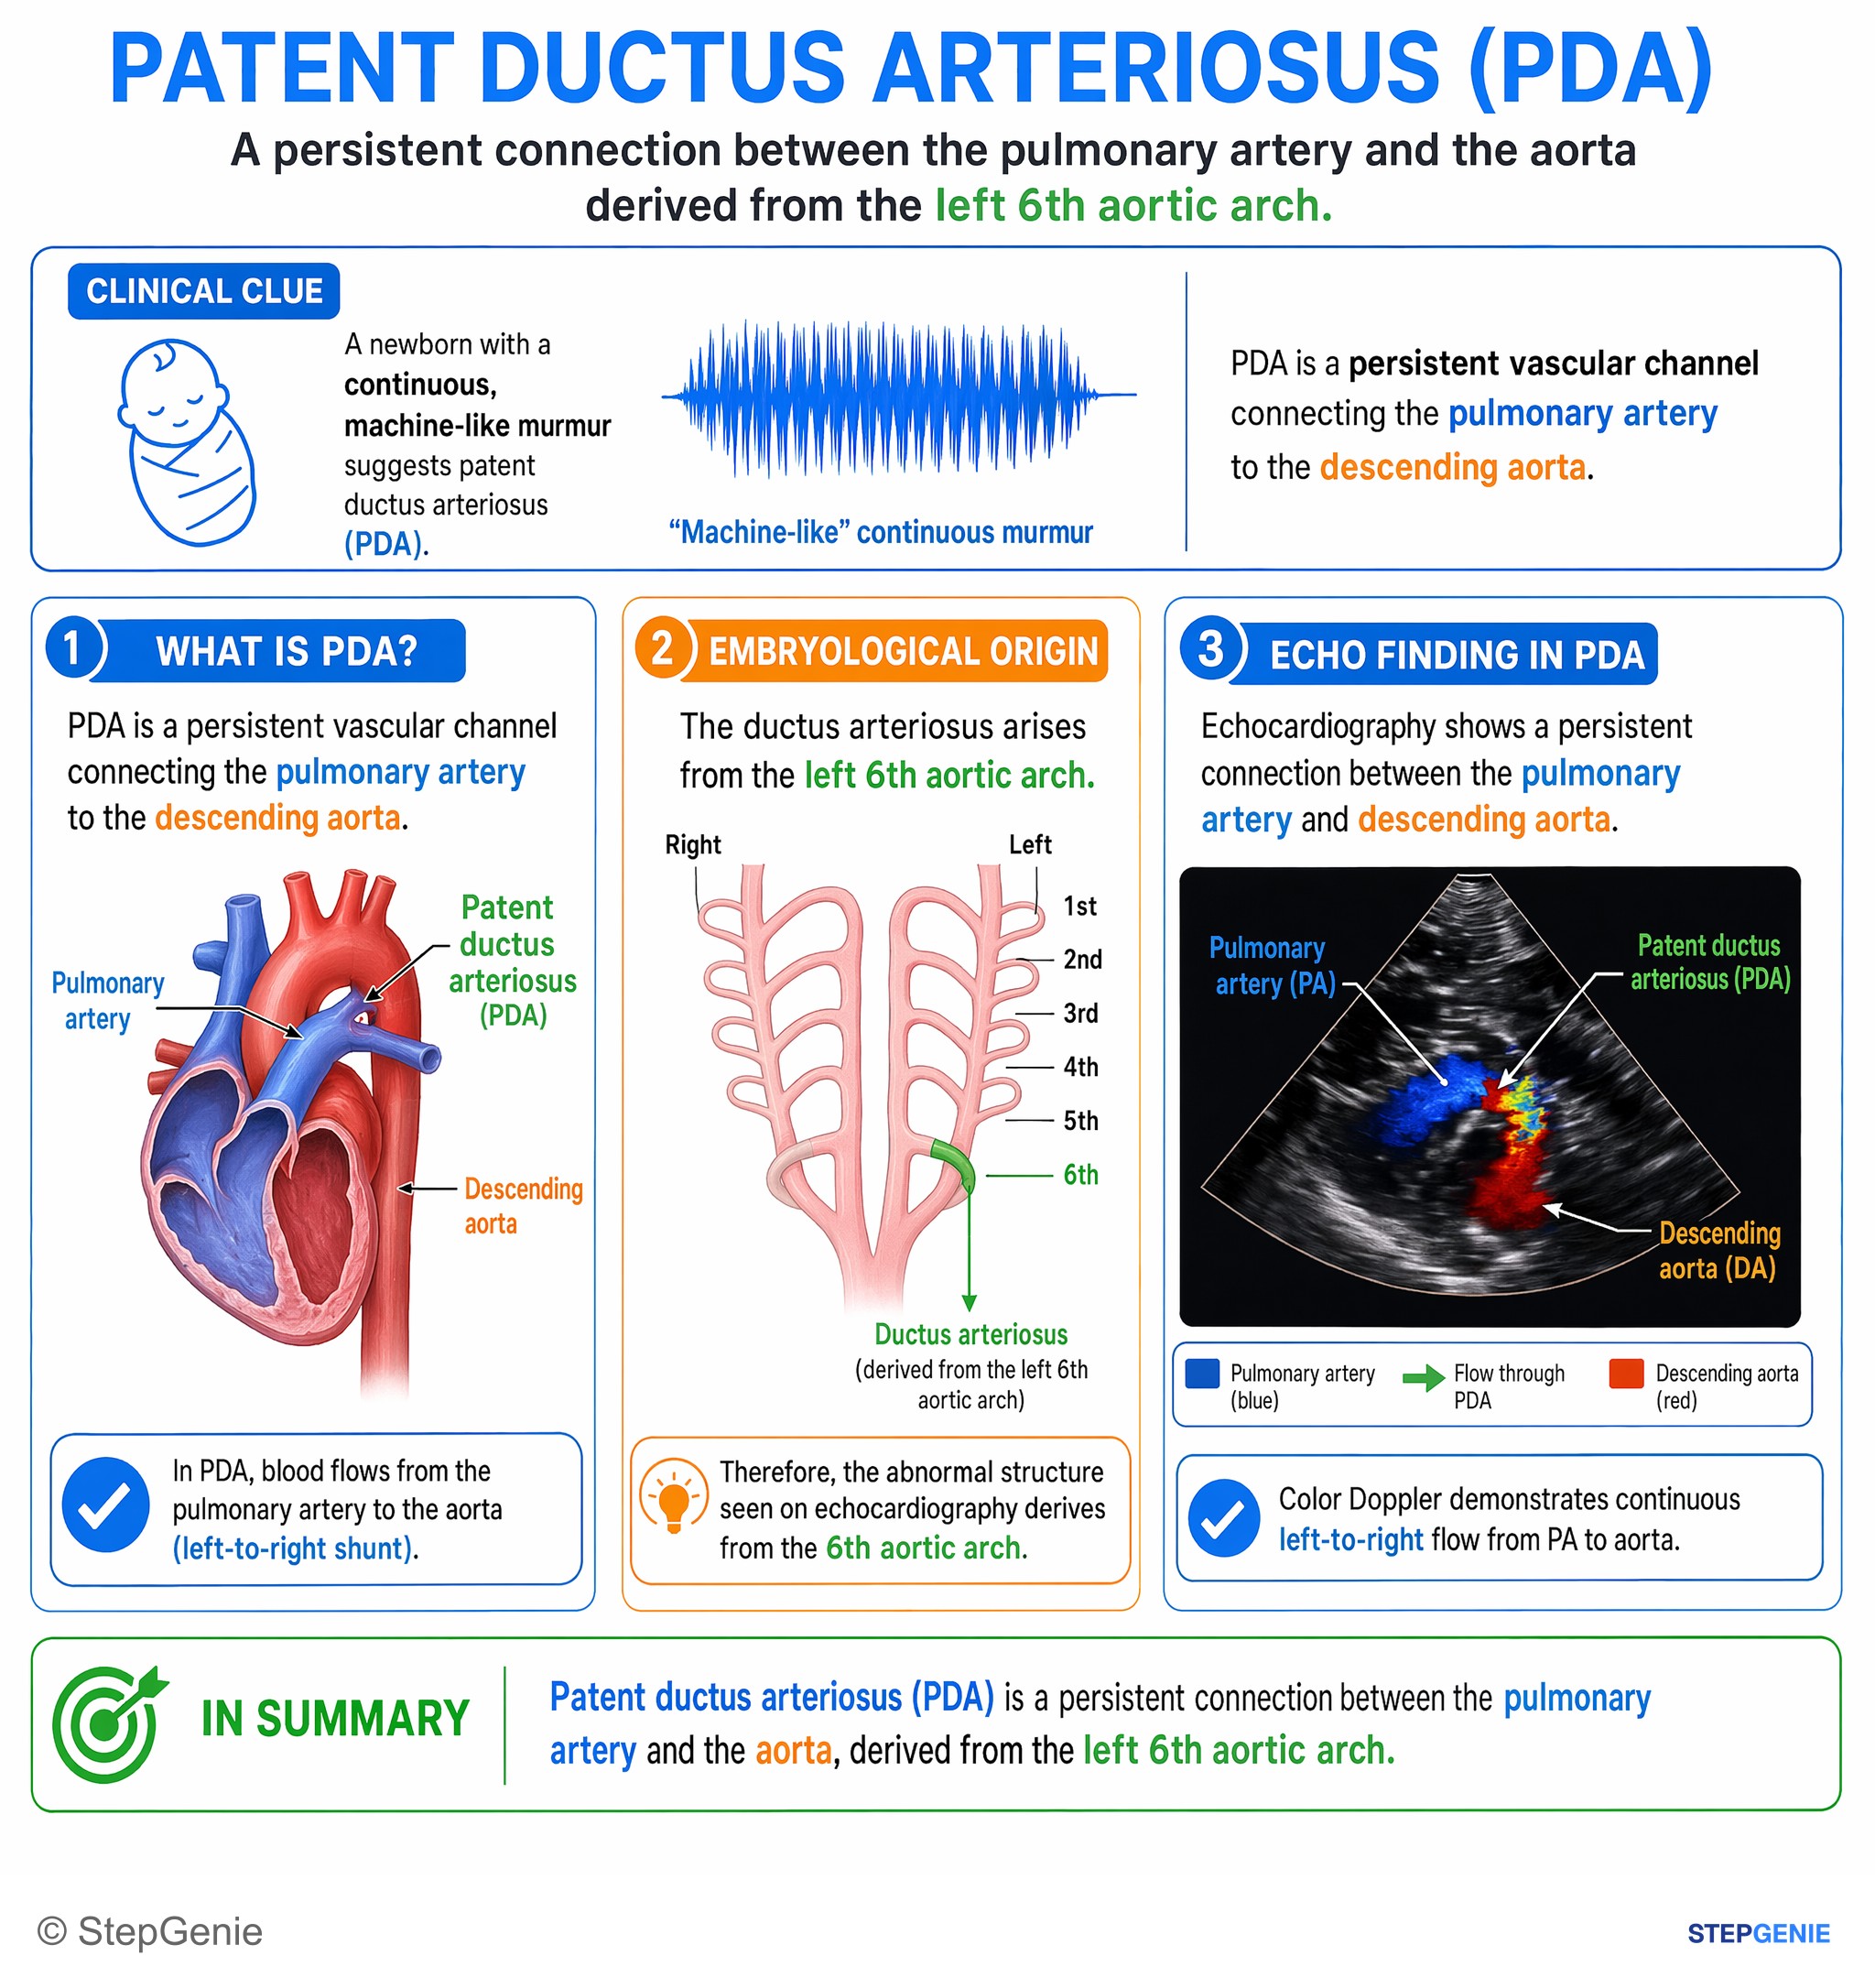
Patent ductus arteriosus is a persistent connection between pulmonary artery and aorta derived from the left 6th aortic arch.
USMLE Step 1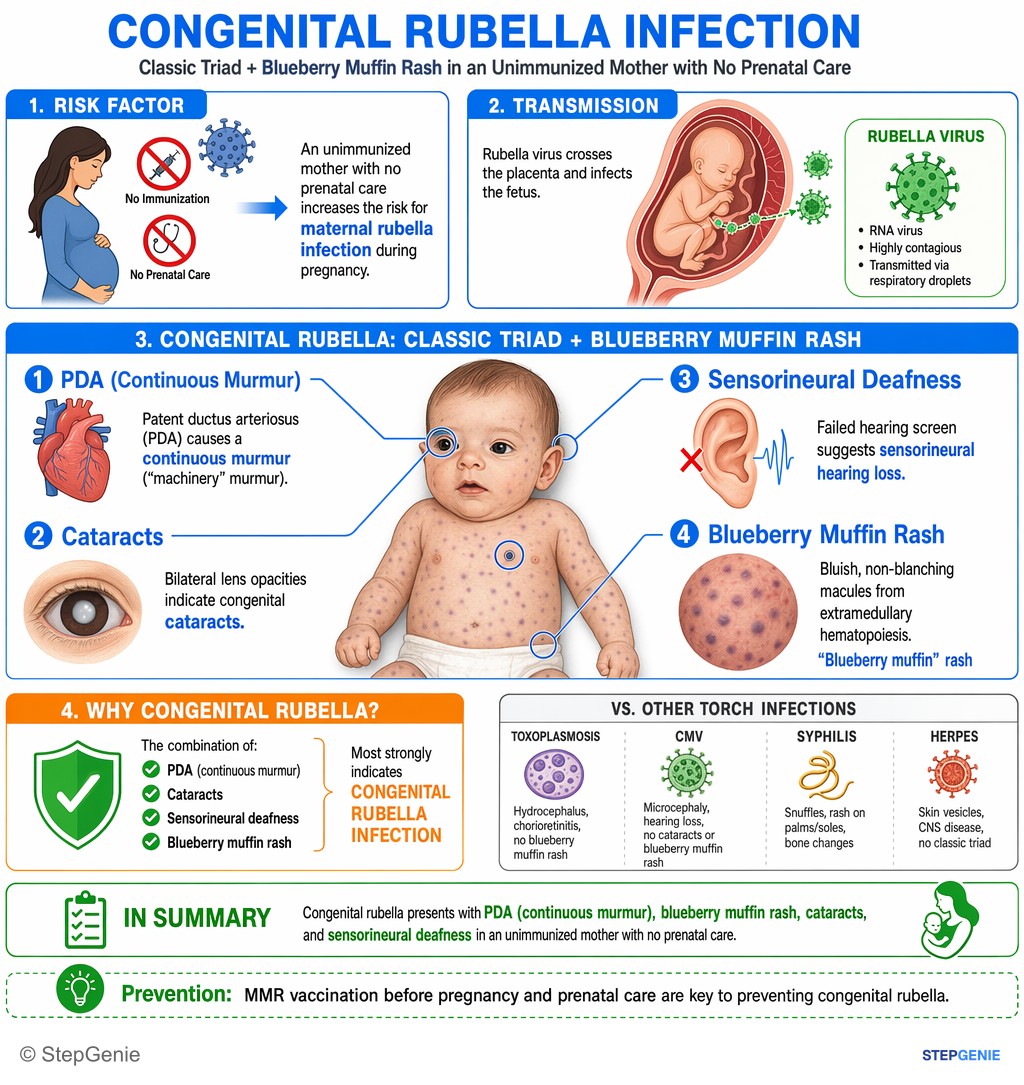
Congenital rubella: PDA (continuous murmur), blueberry muffin rash, cataracts, and sensorineural deafness in an unimmunized mother with no…
USMLE Step 1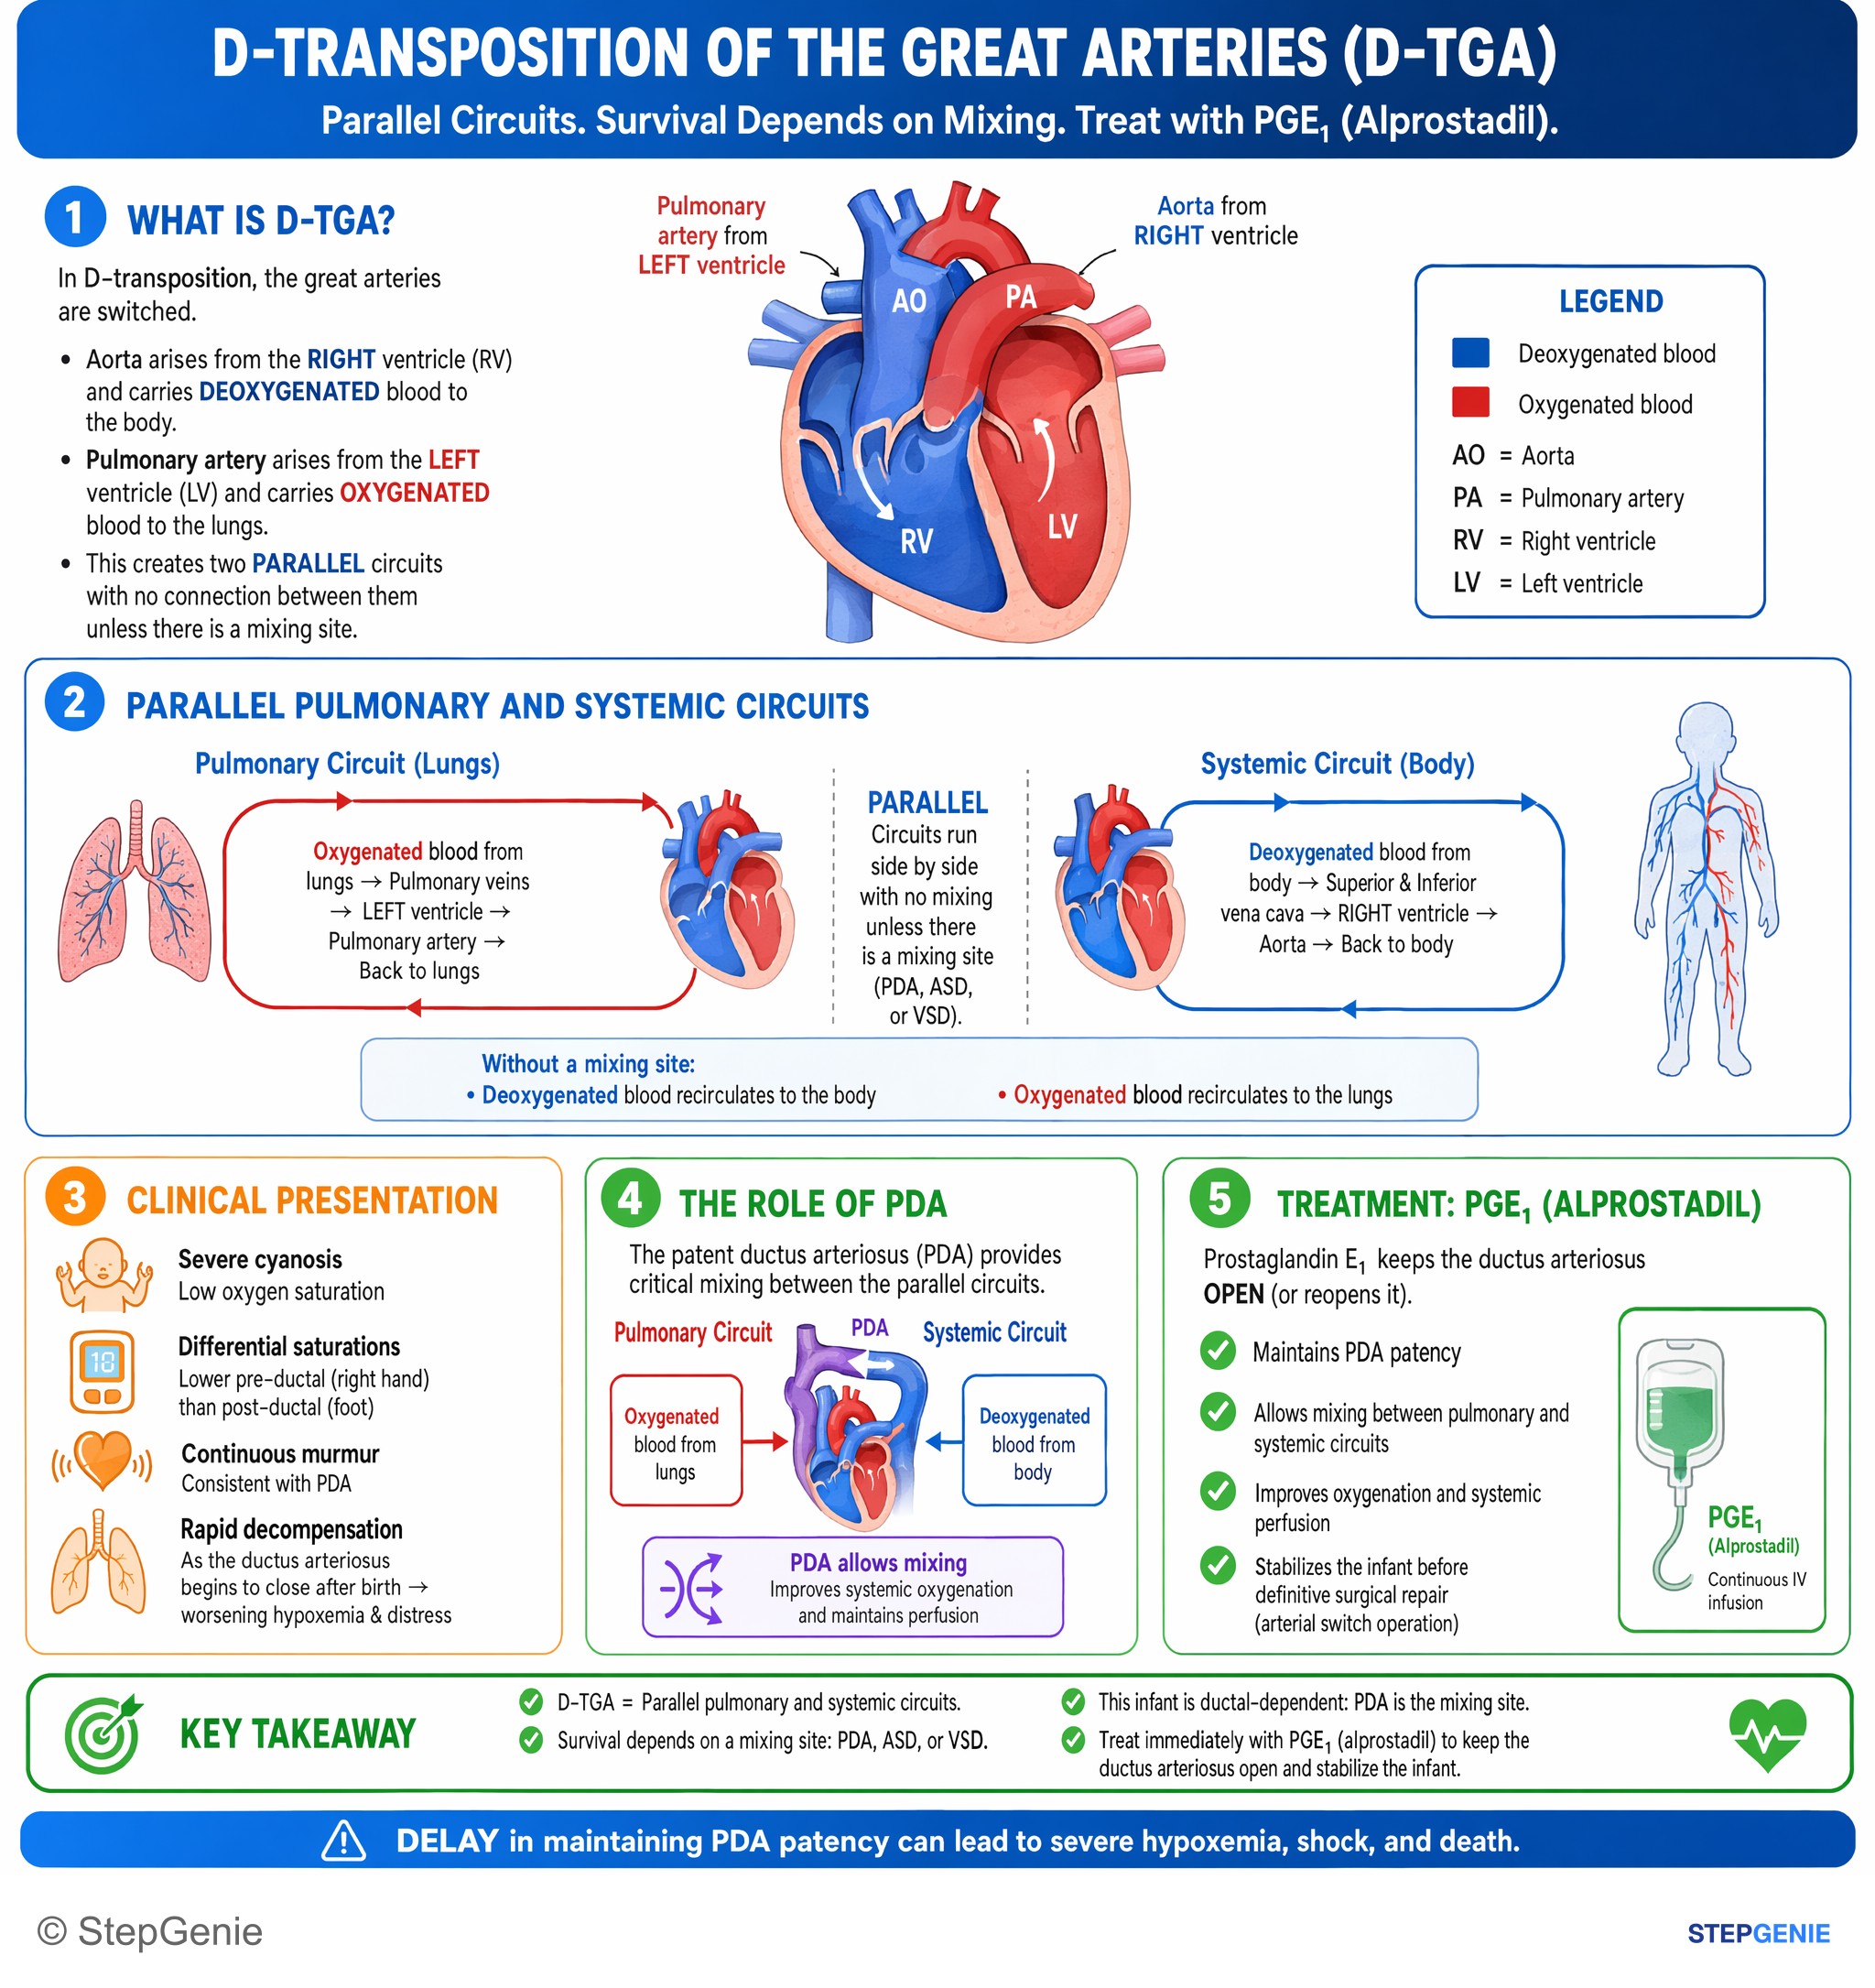
D-transposition of the great arteries: parallel pulmonary/systemic circuits; survival depends on PDA/ASD/VSD. Treat with PGE1…
USMLE Step 2Frequently Asked Questions
What is a patent ductus arteriosus and why does it cause a continuous murmur?
A patent ductus arteriosus is a fetal connection between the pulmonary artery and the descending aorta that fails to close after birth. Because aortic pressure is higher than pulmonary artery pressure in both systole and diastole, blood flows from the aorta into the pulmonary artery throughout the cardiac cycle. That produces a continuous machinery-like murmur, loudest just below the left clavicle, along with bounding pulses and a wide pulse pressure from diastolic runoff.
Why does the ductus arteriosus close after birth?
Before birth, low fetal oxygen levels and locally produced prostaglandins keep the ductus open so blood can bypass the unventilated lungs. After birth, the rise in arterial oxygen and the fall in prostaglandins make the ductus constrict. Closure typically begins within the first 10 to 15 hours of life, and the ductus is constricted by about 24 to 72 hours. Hypoxia and hypercarbia, as in asphyxia, can dilate it again.
Which drugs close a PDA and which keep it open?
Indomethacin and ibuprofen lysine, both given intravenously, are FDA approved to close a significant PDA in preterm infants by reducing prostaglandin production; acetaminophen is an off-label option that the abstract of the 2025 AAP clinical report lists alongside ibuprofen. Alprostadil, which is prostaglandin E1, does the opposite and keeps the ductus open in newborns whose circulation depends on it. NSAIDs taken by the mother at about 30 weeks of pregnancy or later can close the fetal ductus too early.
What are the main risk factors for PDA?
Prematurity is the biggest: a PDA is present in about 45 percent of infants under 1,750 g and 70 to 80 percent of those under 1,200 g. PDA is about three times more common in girls than boys. Congenital rubella syndrome classically causes PDA and pulmonary artery stenosis along with cataracts and hearing loss. Neonatal respiratory distress syndrome and Down syndrome are also associated.
What does differential cyanosis mean in a PDA question?
Differential cyanosis means the legs are bluer than the arms because desaturated blood enters the aorta through the ductus beyond the vessels to the upper body. In an older child or adult with an unrepaired large PDA, cyanosis and clubbing of the toes but not the fingers indicates Eisenmenger syndrome, where the shunt has reversed and closure is no longer possible. In a newborn, it suggests persistent pulmonary hypertension of the newborn with right-to-left ductal flow.
How is a PDA treated in term infants and older children?
COX inhibitors such as indomethacin and ibuprofen are usually ineffective in full-term infants. Transcatheter device closure is the treatment of choice after age 1, and some centers prefer it in term neonates and young infants, while surgical ligation is used when the anatomy is unfavorable. Endocarditis prophylaxis is not needed before closure and is required only for the first 6 months afterward or if a residual leak sits next to a device or surgical material.