Coarctation of the aorta is a congenital, localized narrowing of the aorta, typically just beyond the left subclavian artery and opposite the ductus arteriosus, that causes high blood pressure and strong pulses in the arms with weak, delayed femoral pulses and low leg pressures. A severe coarctation presents in the first 7-10 days of life with shock, metabolic acidosis and renal insufficiency as the ductus closes, and the first step is an infusion of prostaglandin E1 (alprostadil) to reopen it; a milder one surfaces later as hypertension, leg claudication, a systolic murmur over the back and rib notching from enlarged intercostal collaterals. The classic associations are Turner syndrome (coarctation in 10-20%), bicuspid aortic valve and intracranial berry aneurysms.
Where the narrowing sits, and what happened to "preductal vs postductal"
- Location: the proximal descending thoracic aorta, at the isthmus just distal to the left subclavian artery and adjacent to the opening of the ductus arteriosus (Merck). This is the juxtaductal position.
- How common: 6-8% of congenital heart anomalies (Merck), about 1 in 1,724 US births (CDC), and twice as common in males.
- Terminology: many review books still teach "preductal (infantile)" vs "postductal (adult)" coarctation. Current clinical sources describe the typical lesion as juxtaductal and sort babies by how severe the narrowing is, whether lower-body flow depends on the ductus, and whether the transverse arch is hypoplastic. That last feature decides the surgical approach in the 2024 STS guideline. On an exam, read "preductal" as severe, ductal-dependent neonatal coarctation (classically with a hypoplastic arch) and "postductal" as the classic lesion found later with collaterals.
Pathophysiology: three consequences of one pinch point
- Pressure overload proximal to the narrowing: left ventricular hypertrophy and hypertension in the upper body, including the brain.
- Hypoperfusion distal to it: weak, delayed femoral pulses, low or unobtainable leg pressures, cool legs and exertional leg pain; in neonates, oliguria from poor renal perfusion.
- Collaterals in long-standing disease: the pressure gradient enlarges collateral routes to the lower body through the intercostal, internal mammary (internal thoracic) and scapular arteries. Dilated intercostals erode the undersides of the ribs (rib notching) and can produce a continuous murmur.
Why the newborn crashes: before birth, and while the ductus stays open, much of the cardiac output bypasses the coarctation through the ductus arteriosus. When the ductus closes in the first days of life, that bypass is lost and the full obstruction of a severe coarctation is suddenly unmasked.
Presentation: newborn vs older child or adult
| Severe (critical) coarctation in a newborn | Milder coarctation found later | |
|---|---|---|
| When | First 7-10 days, as the ductus closes | Childhood, adolescence or adulthood, often during a work-up for hypertension |
| Symptoms | Poor feeding, breathing difficulty, lethargy, then shock | Often none; headache, chest pain, fatigue, leg claudication with exercise |
| Key findings | Weak or absent femoral pulses, metabolic acidosis, oliguria or anuria, heart failure | Upper-limb hypertension, brachial-femoral pulse delay, low leg BP, systolic murmur at the left upper sternal border and left interscapular area |
| ECG | Usually right ventricular hypertrophy | Usually left ventricular hypertrophy (may be normal) |
| Chest x-ray | Normal heart size unless heart failure develops | "3" sign, rib notching of the 3rd-8th ribs (seldom before age 5) |
| First move | PGE1 infusion, treat shock and acidosis | Confirm with imaging, plan repair, treat BP |
Coarctation counts as a critical congenital heart defect, but newborn pulse oximetry screening may miss it (CDC), so a passed screen does not rule it out.
Exam signs and diagnosis
- Measure BP in all four extremities and compare brachial with femoral pulses (Merck). Expect strong arm pulses with hypertension, and weak, delayed femoral pulses with low or unobtainable leg pressures. A systolic arm-leg gradient over 20 mm Hg suggests significant coarctation (StatPearls).
- Murmur: grade 2-3/6 ejection systolic murmur at the upper left sternal border and left axilla, sometimes loudest in the left interscapular area. Dilated intercostal collaterals can add a continuous murmur. A bicuspid aortic valve may add an ejection click or aortic stenosis murmur; compare lesions in the heart murmurs guide.
- Chest x-ray: the "3" sign (dilation above the narrowing, the indentation itself and post-stenotic dilation) in the upper left mediastinal shadow; heart size is normal unless heart failure develops; rib notching of the 3rd-8th ribs in older children and adults.
- Imaging: echocardiography with color flow and Doppler is first-line in infants and children; CT or MR angiography maps the anatomy, especially in older patients.
Associations to memorize
| Association | What to know |
|---|---|
| Turner syndrome (45,X or mosaic) | Coarctation in 10-20% (Merck); one-third to one-half of people with Turner syndrome are born with a heart defect, most often coarctation or an aortic valve abnormality (MedlinePlus Genetics). Review the karyotypes in the Turner syndrome breakdown |
| Bicuspid aortic valve | The classic companion lesion, present in about 45-75% of patients with coarctation (StatPearls); the valve itself can become stenotic or regurgitant later |
| Intracranial (berry) aneurysms | Saccular aneurysms; untreated coarctation carries a risk of intracranial hemorrhage |
| Other heart lesions | VSD, aortic stenosis, PDA, mitral valve disorders |
Treatment
The crashing newborn
- Prostaglandin E1 (alprostadil), starting at 0.05-0.1 mcg/kg/min, reopens the constricted ductus and restores lower-body flow; the dose is then cut to the lowest effective rate. Coarctation is one of the ductal-dependent lesions named on the FDA label, alongside interrupted aortic arch, pulmonary atresia and transposition (see transposition of the great arteries).
- Boxed warning: apnea in about 10-12% of treated neonates with congenital heart defects, usually in the first hour and most often with birth weight under 2 kg, so be ready to ventilate. Other effects: fever (about 14%), flushing (about 10%), bradycardia, hypotension and seizures; long-term infusion can cause cortical proliferation of the long bones, and infusions over 120 hours call for monitoring for antral hyperplasia and gastric outlet obstruction.
- Correct shock and acidosis, then repair once stable.
Definitive repair
- Neonates, infants and small children: surgery (Merck). The 2024 STS guideline for neonates and infants with isolated coarctation recommends surgery when there is no obvious contraindication: thoracotomy when the arch is not hypoplastic, sternotomy when arch hypoplasia can't be dealt with through a thoracotomy. For repair through a sternotomy, extended end-to-end anastomosis, arch advancement and patch augmentation are all reasonable techniques.
- Older children and adolescents: balloon angioplasty, sometimes with a stent, is an alternative (Merck). Compared with surgery it has fewer periprocedural complications but more restenosis and aneurysm formation. Balloon angioplasty works well for recoarctation after surgery.
- Blood pressure: before repair, beta blockers are used, because ACE inhibitors may worsen renal function; hypertension may persist or appear years after repair, and is then treated with beta blockers, ACE inhibitors, ARBs or calcium channel blockers.
Lifelong follow-up
Repair is not the end: recoarctation (especially after newborn repair), persistent hypertension, aortic dissection, endocarditis, stroke and early coronary artery disease all remain risks (MedlinePlus). Untreated coarctation adds heart failure, hypertensive encephalopathy and a higher risk of aortic dissection or rupture, including in pregnancy. Adults belong in specialized adult congenital heart disease (ACHD) care: the 2025 ACC/AHA/HRS/ISACHD/SCAI ACHD guideline, published in December 2025 to replace the 2018 guideline, stresses access to ongoing care at ACHD centers. Dissection patterns are reviewed in Stanford A vs B.
How USMLE tests it
- Teen or young adult with hypertension, headaches or leg claudication, and weak, delayed femoral pulses: coarctation. It is a classic cause of secondary hypertension in the young; compare the others in essential vs secondary hypertension.
- Newborn who was well, then crashes in the first week with absent femoral pulses and acidosis: critical coarctation; start PGE1.
- Girl with short stature, webbed neck or primary amenorrhea plus hypertension: Turner syndrome with coarctation; look for a bicuspid aortic valve too.
- Rib notching: enlarged intercostal collaterals from long-standing disease, not a newborn finding.
- Indomethacin is the opposite of what a ductal-dependent baby needs: it closes the ductus.
| Look-alike | How to tell it apart |
|---|---|
| PDA | Continuous "machine-like" murmur and bounding pulses in all limbs, no arm-leg BP gradient (PDA guide) |
| Aortic stenosis | Crescendo-decrescendo murmur radiating to the carotids; no arm-leg gradient |
| Transposition of the great arteries | Cyanosis from birth that oxygen does not fix; needs PGE1 and often a balloon atrial septostomy |
| Tetralogy of Fallot | Cyanotic spells and a boot-shaped heart, not a pulse gradient |
Practice question
A 6-day-old boy is brought to the emergency department with 1 day of poor feeding, lethargy and fast breathing. He was born at term after an uncomplicated pregnancy and passed his newborn pulse oximetry screen. Pulse is 182/min and respirations 68/min. Blood pressure is 88/56 mm Hg in the right arm; it cannot be obtained in either leg. Brachial pulses are easy to feel, but femoral pulses are not palpable. His legs are cool and mottled, the liver edge is 4 cm below the costal margin, and he has passed little urine. Arterial blood gas shows a metabolic acidosis. Which is the most appropriate next step in management?
A. IV indomethacin B. IV alprostadil (prostaglandin E1) infusion C. Balloon atrial septostomy D. 100% oxygen and observation E. Emergency surgical repair before any other treatment
Answer: B. A neonate who crashes near the end of the first week with an arm-leg pressure gradient, absent femoral pulses, heart failure and acidosis has critical coarctation unmasked by ductal closure. Alprostadil reopens the ductus, restores flow to the lower body and buys time to correct shock and acidosis before repair. Watch for apnea in the first hour and be ready to ventilate.
- A: indomethacin is a cyclooxygenase inhibitor that closes a patent ductus (used in preterm infants with PDA); here it would cut off the remaining lower-body flow.
- C: balloon atrial septostomy improves atrial mixing in transposition of the great arteries; this baby's problem is obstruction to systemic flow, not mixing.
- D: oxygen does nothing for the obstruction. A rising arterial oxygen tension is one of the signals that closes the ductus, and Merck advises caution with supplemental oxygen in these neonates because lowering pulmonary vascular resistance diverts flow away from the systemic circulation.
- E: surgery is the definitive treatment for a neonate, but it follows stabilization with PGE1 and correction of shock and acidosis rather than replacing it.
Key takeaways
- Coarctation = narrowing just beyond the left subclavian artery, opposite the ductus (juxtaductal); twice as common in males.
- Arm hypertension, weak and delayed femoral pulses, low leg pressures; measure BP in all four limbs.
- Severe coarctation crashes in the first 7-10 days as the ductus closes: PGE1 first (apnea in 10-12%), then surgery.
- Later presentation: hypertension, claudication, interscapular murmur, "3" sign and rib notching (rarely before age 5).
- Turner syndrome (10-20%), bicuspid aortic valve, berry aneurysms.
- "Preductal vs postductal" is review-book shorthand; current sources describe severity, ductal dependence and arch hypoplasia.
- After repair: lifelong follow-up for recoarctation, hypertension and aortic complications, in ACHD care as an adult (2025 ACC/AHA ACHD guideline).
Sources
- Coarctation of the Aorta — Merck Manual Professional Edition (2023)
- Coarctation of the Aorta — StatPearls, NCBI Bookshelf (2024)
- Patent Ductus Arteriosus (PDA) — Merck Manual Professional Edition (2023)
- Coarctation of the aorta — MedlinePlus Medical Encyclopedia (2025)
- About Coarctation of the Aorta — CDC (2026)
- Turner syndrome — MedlinePlus Genetics (2023)
- PROSTIN VR PEDIATRIC (alprostadil) injection label — DailyMed, FDA (2026)
- New Guidelines Developed for Managing Neonates and Infants with Coarctation — The Society of Thoracic Surgeons (2024)
- New clinical guidelines for managing neonates and infants with coarctation — Mayo Clinic (2024)
- New ACC/AHA Guideline Addresses Management of Congenital Heart Disease in Adults — American College of Cardiology (2025)
- ACC/AHA issue new guideline on managing congenital heart disease in adults — American Heart Association Newsroom (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
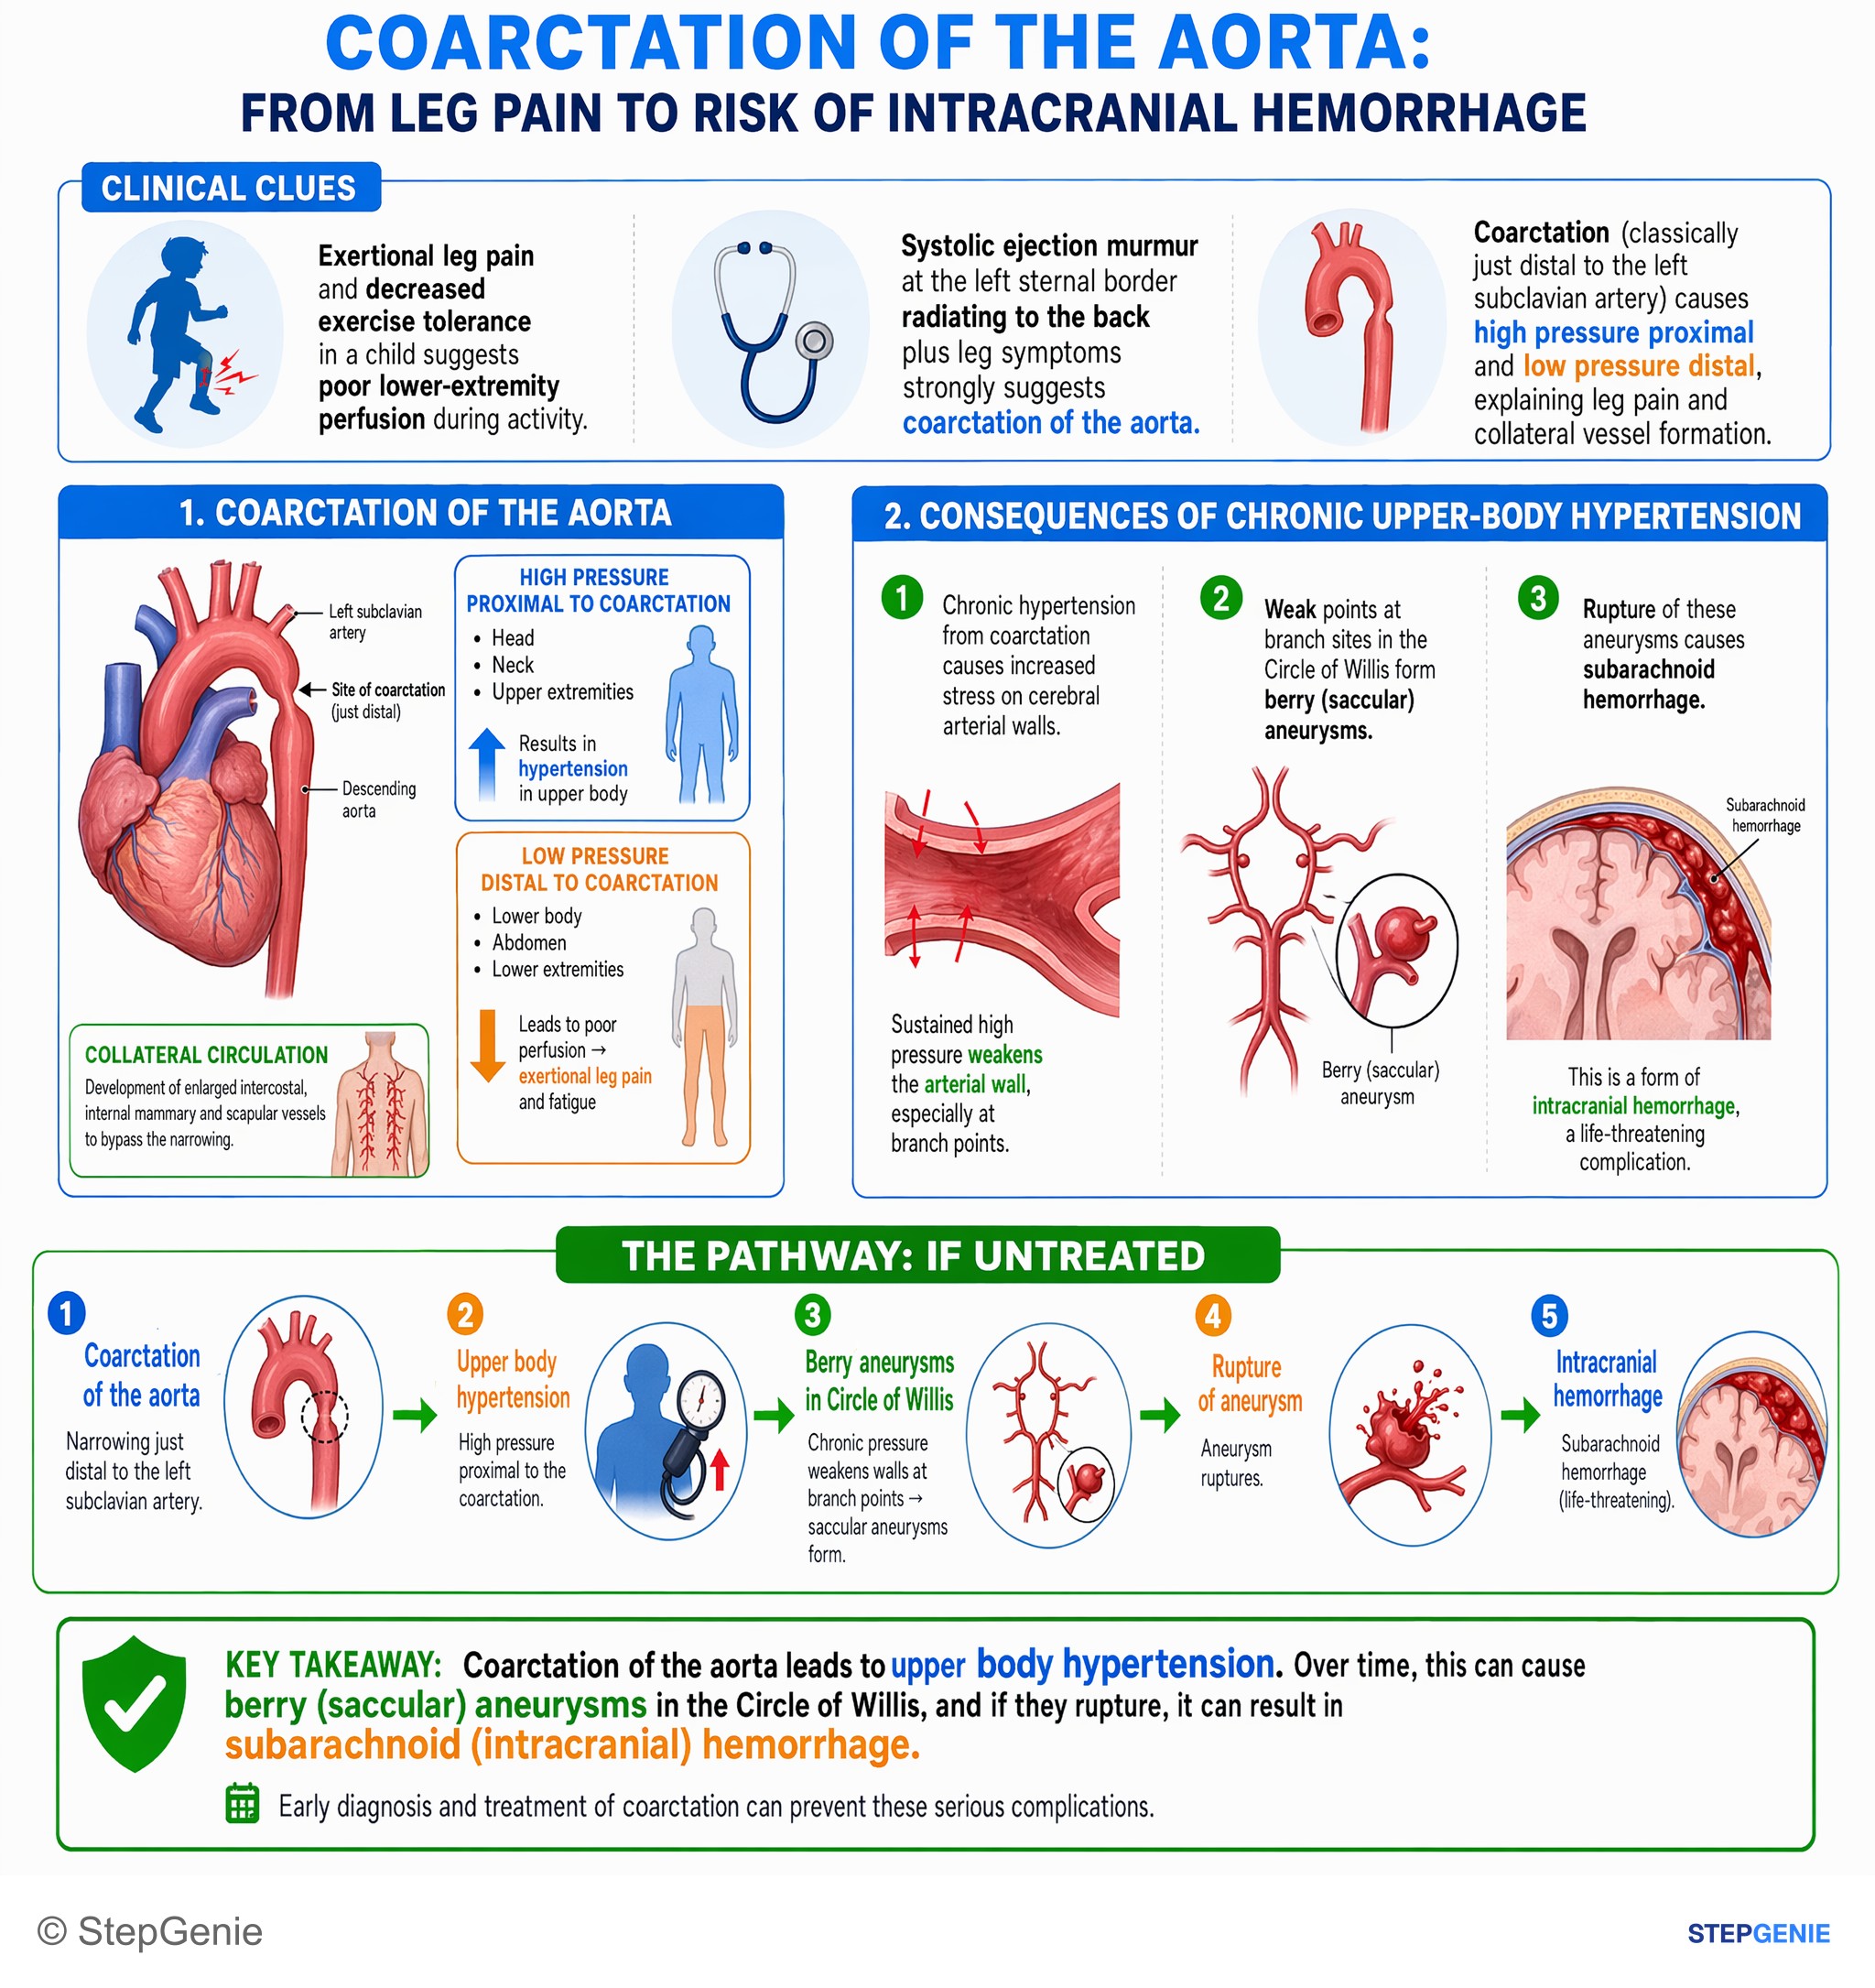
Coarctation of the aorta → upper body hypertension → berry aneurysms in circle of Willis → risk of intracranial hemorrhage if untreated.
USMLE Step 1Frequently Asked Questions
What are the classic signs of coarctation of the aorta?
High blood pressure and strong pulses in the arms, with weak, delayed femoral pulses and low or unobtainable leg pressures, which is why blood pressure should be measured in all four limbs. Many patients have a grade 2-3/6 ejection systolic murmur at the upper left sternal border that can be loudest between the shoulder blades. Long-standing cases add collateral murmurs, left ventricular hypertrophy and rib notching on chest x-ray. Older children may report headache, fatigue or leg pain with exercise.
What is the difference between preductal and postductal coarctation?
These are older review-book labels. Preductal, or infantile, coarctation describes a severe narrowing, classically with a hypoplastic aortic arch, in which lower-body blood flow depends on the ductus arteriosus, so the baby crashes as the ductus closes. Postductal, or adult-type, coarctation describes the classic narrowing found later, with collaterals and arm hypertension. Current sources place most coarctations in the juxtaductal position, opposite the ductus, and classify them by severity, ductal dependence and arch hypoplasia.
Why is prostaglandin E1 given to a newborn with coarctation?
Before the ductus arteriosus closes, much of the cardiac output bypasses the narrowed segment through it. When the ductus closes in the first days of life, a severe coarctation causes shock, metabolic acidosis and renal insufficiency. An alprostadil (prostaglandin E1) infusion, usually started at 0.05-0.1 mcg/kg/min, reopens the ductus and restores lower-body flow until surgery. The FDA label carries a boxed warning for apnea in about 10-12% of treated neonates, usually in the first hour.
Why does coarctation of the aorta cause rib notching?
Long-standing coarctation forces blood around the narrowing through collateral arteries, including the internal thoracic (internal mammary), intercostal and scapular arteries. The enlarged intercostal arteries gradually erode the undersides of the ribs, usually the 3rd to 8th, producing notching on chest x-ray. Because the collaterals take years to develop, rib notching is seldom seen before age 5; it is a clue to coarctation found in older children and adults, not in newborns.
How is coarctation of the aorta linked to Turner syndrome?
Coarctation occurs in about 10-20% of people with Turner syndrome, and one-third to one-half of people with Turner syndrome are born with a heart defect, most often coarctation or an aortic valve abnormality such as a bicuspid valve. About half of people with Turner syndrome have monosomy X (45,X), and many others are mosaic. A girl with short stature, a webbed neck or primary amenorrhea plus high arm blood pressure or weak femoral pulses should be evaluated for coarctation.
Can coarctation come back or cause problems after repair?
Yes. The narrowing can recur, especially after repair in the newborn period, and recurrent coarctation is often treated with balloon angioplasty. Hypertension may persist or develop years after repair, and patients remain at risk of aortic dissection, endocarditis, stroke and early coronary artery disease. That is why lifelong cardiology follow-up is advised, with adults seen in specialized adult congenital heart disease care, as the 2025 ACC/AHA adult congenital heart disease guideline emphasizes.