Peripheral artery disease (PAD) shows up constantly on USMLE stems because it’s common, deadly (CV risk), and treatable. When you’re under time pressure, you need a rapid mental checklist that tells you: Is this PAD? How do I confirm it? What’s the next step?
The “5-Second Rule” for PAD (say it fast in your head)
Pain with walking (claudication)
ABI low ()
Diminished pulses / delayed cap refill
5: 5 Ps of acute limb ischemia (don’t miss it)
One-liner: PAD = atherosclerosis of leg arteries → exertional ischemic muscle pain + low ABI + high MI/stroke risk.
The Visual/Mnemonic Device: “PAD = Pain, ABI, Diminished pulses”
Think of a leg wearing a “PAD” knee brace:
- P = Pain with exertion (claudication)
- A = ABI (your fastest confirmatory test)
- D = Diminished pulses (and cool, shiny, hairless skin)
Then add a flashing red alarm: “5 Ps” = acute limb ischemia emergency.
5-Second Recognition: What the stem will say
Classic chronic PAD (intermittent claudication)
- Crampy calf/thigh/buttock pain with walking
- Relieved by rest (minutes)
- Decreased distal pulses
- Cool extremity, shiny skin, loss of hair, thickened nails
- Nonhealing ulcers on toes/feet (arterial ulcers = “distal and dry”)
Key distinction: Claudication vs neurogenic pain (spinal stenosis)
| Feature | PAD (vascular claudication) | Neurogenic claudication |
|---|---|---|
| Trigger | Walking/exertion | Standing/walking |
| Relief | Rest | Sitting or leaning forward (“shopping cart sign”) |
| Pulses/skin | ↓ pulses, cool skin | Usually normal |
| ABI | Low | Normal |
The Single Best Quick Test: ABI (Ankle-Brachial Index)
Definition:
Interpretation (high-yield):
- Normal: 1.00–1.40
- Borderline: 0.91–0.99
- PAD diagnostic:
- Severe PAD / critical ischemia often: < 0.40
- > 1.40: noncompressible calcified vessels (think diabetes, CKD) → do toe-brachial index or arterial Doppler studies
Board-style twist: If symptoms suggest PAD but resting ABI is normal → do exercise ABI (ABI drops after treadmill).
Management in One Snapshot (what Step questions love)
Everyone with PAD gets “vascular protection”
PAD is a coronary disease equivalent → treat like high ASCVD risk.
Foundational (memorize):
- Smoking cessation (most powerful modifiable factor)
- High-intensity statin (e.g., atorvastatin 40–80)
- Antiplatelet therapy: aspirin or clopidogrel
- Control BP and diabetes (ACEi/ARB commonly used for CV risk reduction)
- Supervised exercise therapy (improves walking distance significantly)
Symptom relief for claudication
- Cilostazol (PDE-3 inhibitor) improves claudication symptoms
- Contraindicated in heart failure (classic USMLE trap)
When to revascularize
- Lifestyle-limiting claudication despite optimal medical therapy + exercise
- Critical limb-threatening ischemia: rest pain, ulcers, gangrene
- Think: pain at rest (often at night), relieved by dangling leg off bed
The “5” in the 5-Second Rule: Don’t miss Acute Limb Ischemia (ALI)
ALI = sudden arterial occlusion (embolus or thrombosis) → limb-threatening emergency.
The 5 Ps (sometimes taught as 6 Ps)
- Pain
- Pallor
- Pulselessness
- Paresthesia
- Paralysis
- (+ Poikilothermia = cold)
Immediate steps (high yield):
- IV heparin now (unless contraindicated)
- Urgent vascular surgery/intervention (thromboembolectomy, thrombolysis, etc.)
Stem clue: “Sudden onset” + “cold, pale foot” + “no pulses” = treat immediately—don’t waste time with long workups.
High-Yield Associations & Risk Factors (USMLE favorites)
- Smoking, diabetes, hyperlipidemia, hypertension, age
- PAD strongly predicts MI and stroke risk (systemic atherosclerosis)
Physical exam pearls:
- Bruits (femoral)
- Dependent rubor (reddish when dangling) + pallor on elevation
- Arterial ulcers: painful, “punched-out,” distal toes/foot, poor bleeding
Rapid-Fire Self-Test (5 seconds each)
- Exertional calf pain that stops with rest + ↓ dorsalis pedis pulse → PAD
- ABI = 0.65 → diagnostic of PAD
- ABI = 1.5 in diabetic with claudication → calcified noncompressible vessels → toe-brachial index
- Claudication med that’s contraindicated in HF → cilostazol
- Sudden cold pulseless painful leg → heparin + emergent vascular eval
Takeaway “Sticky Note”
PAD = Pain with walking + ABI + diminished pulses.
Treat the patient’s legs, but protect the patient’s heart and brain (statin + antiplatelet + stop smoking).
Sudden symptoms? Think ALI → 5 Ps → heparin + emergent intervention.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
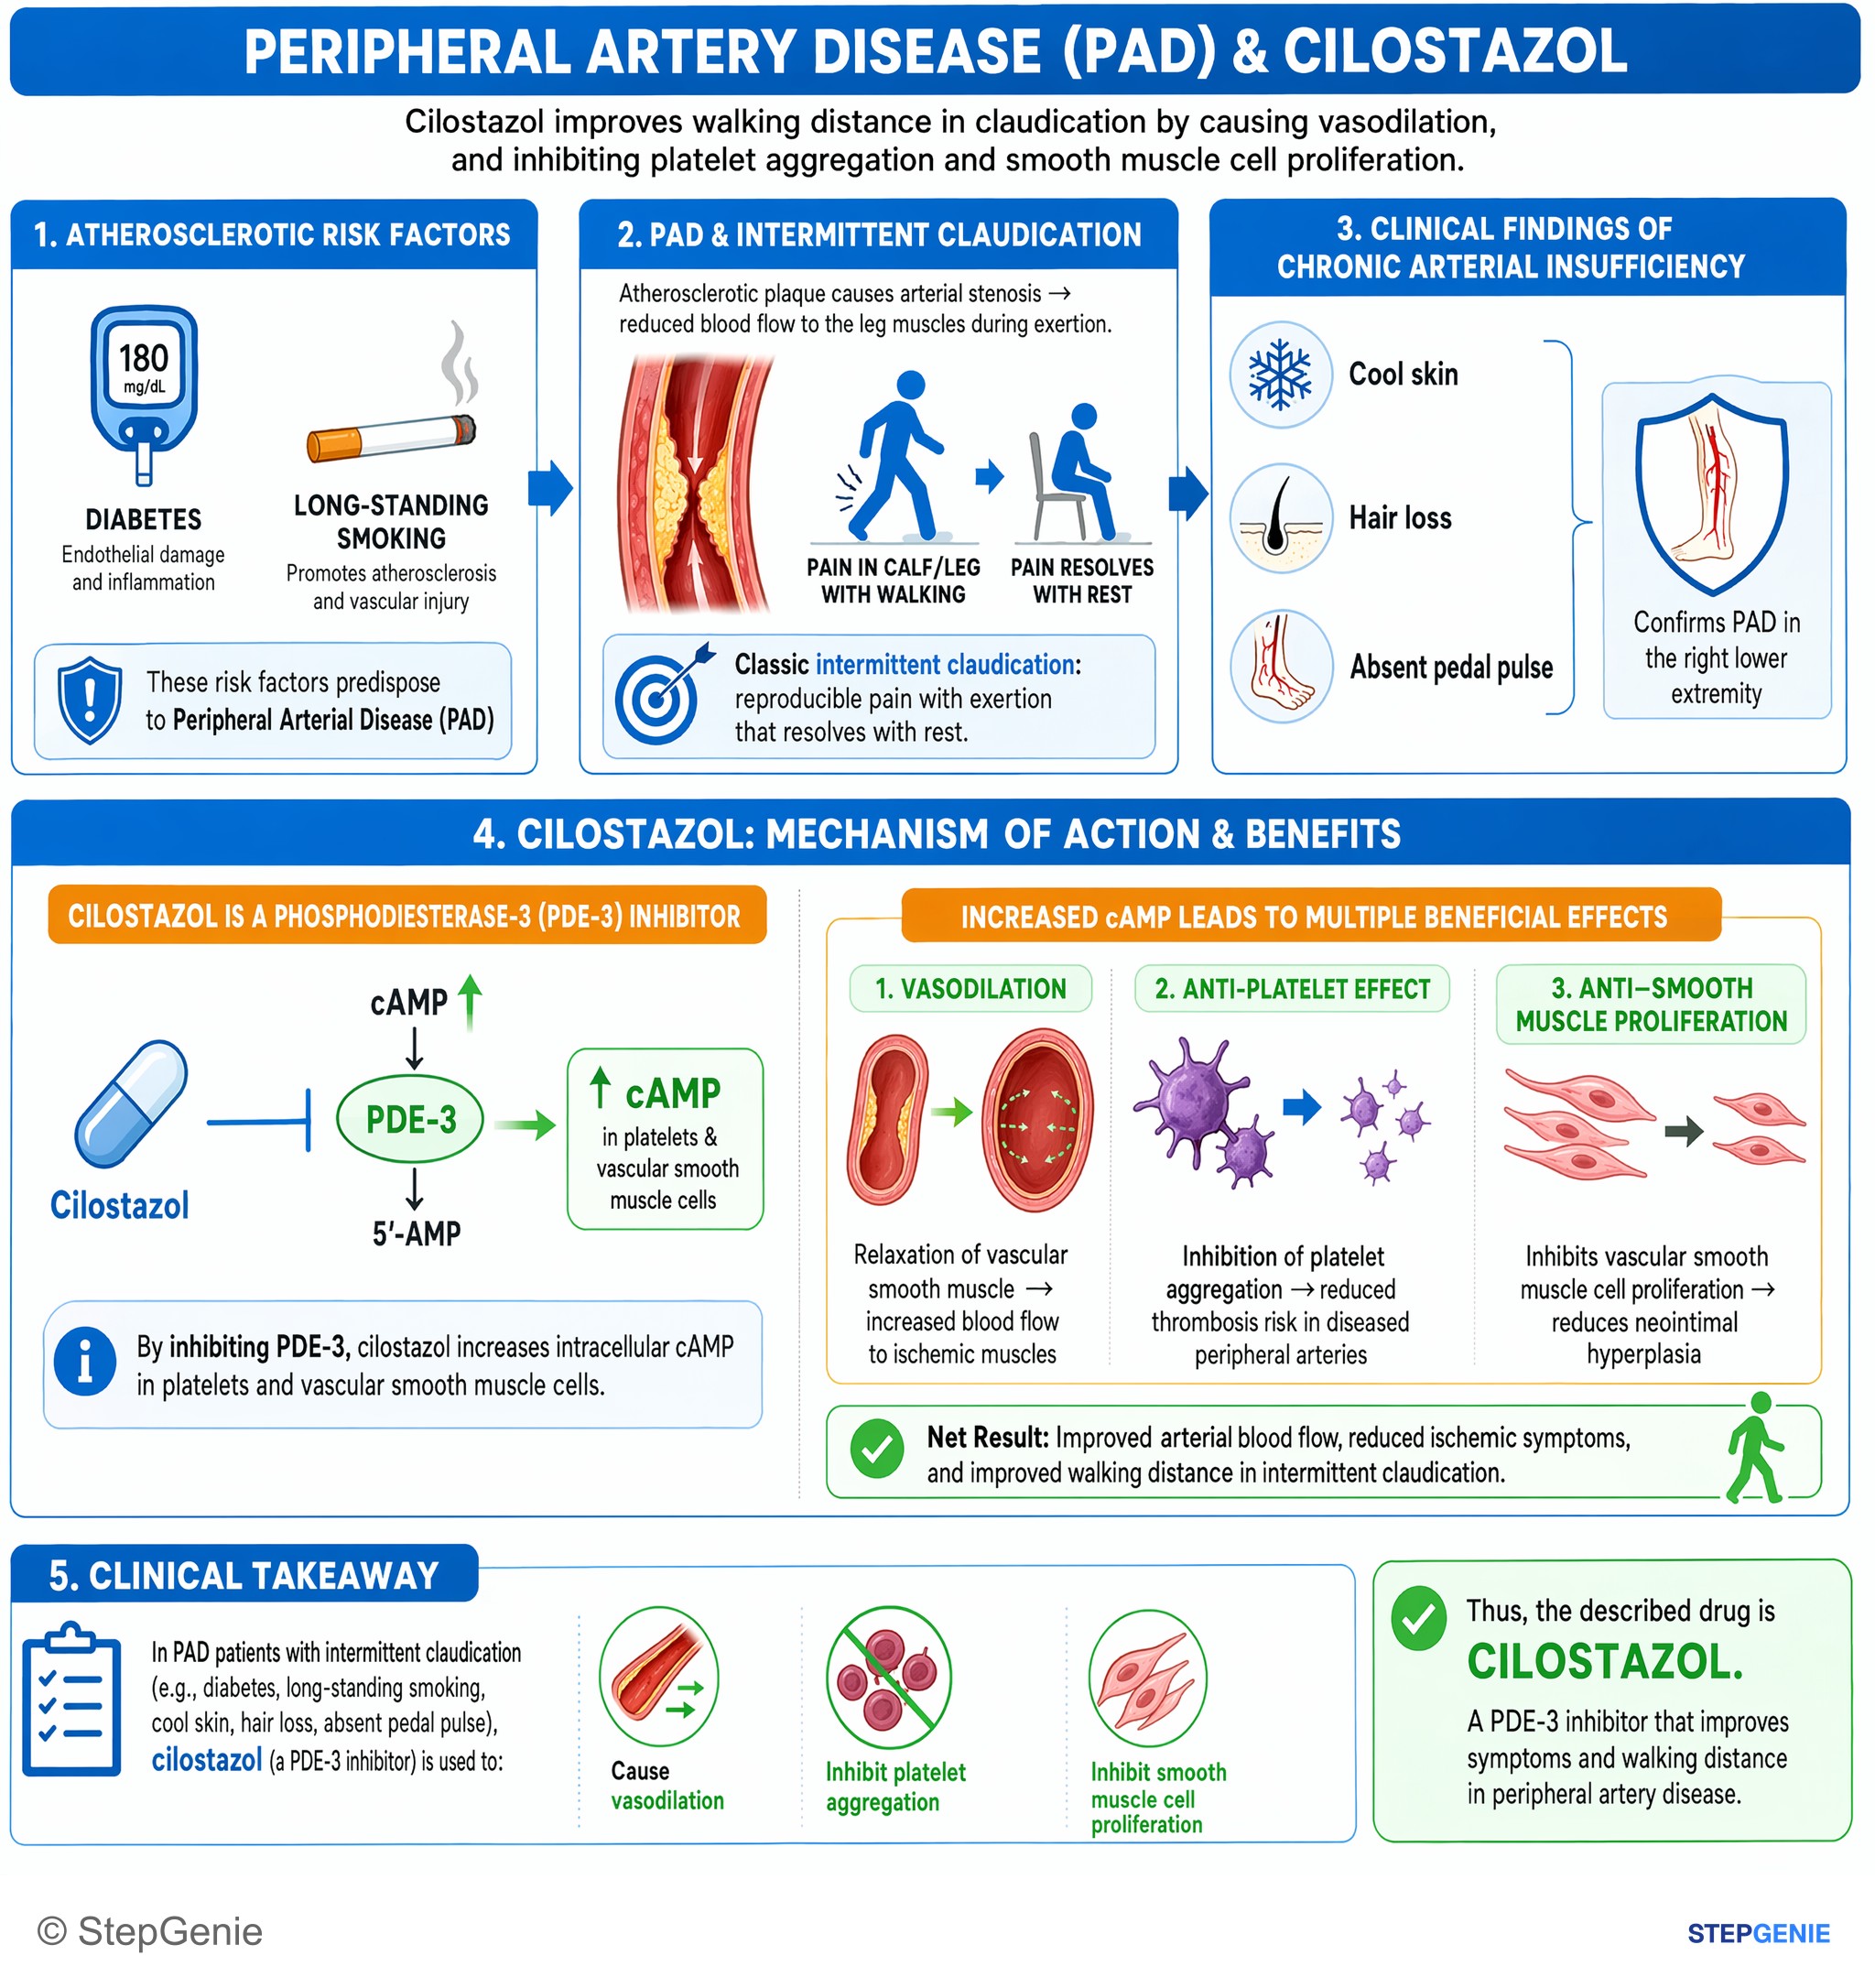
Peripheral artery disease causing claudication is treated with cilostazol, a PDE-3 inhibitor that causes vasodilation and inhibits…
USMLE Step 1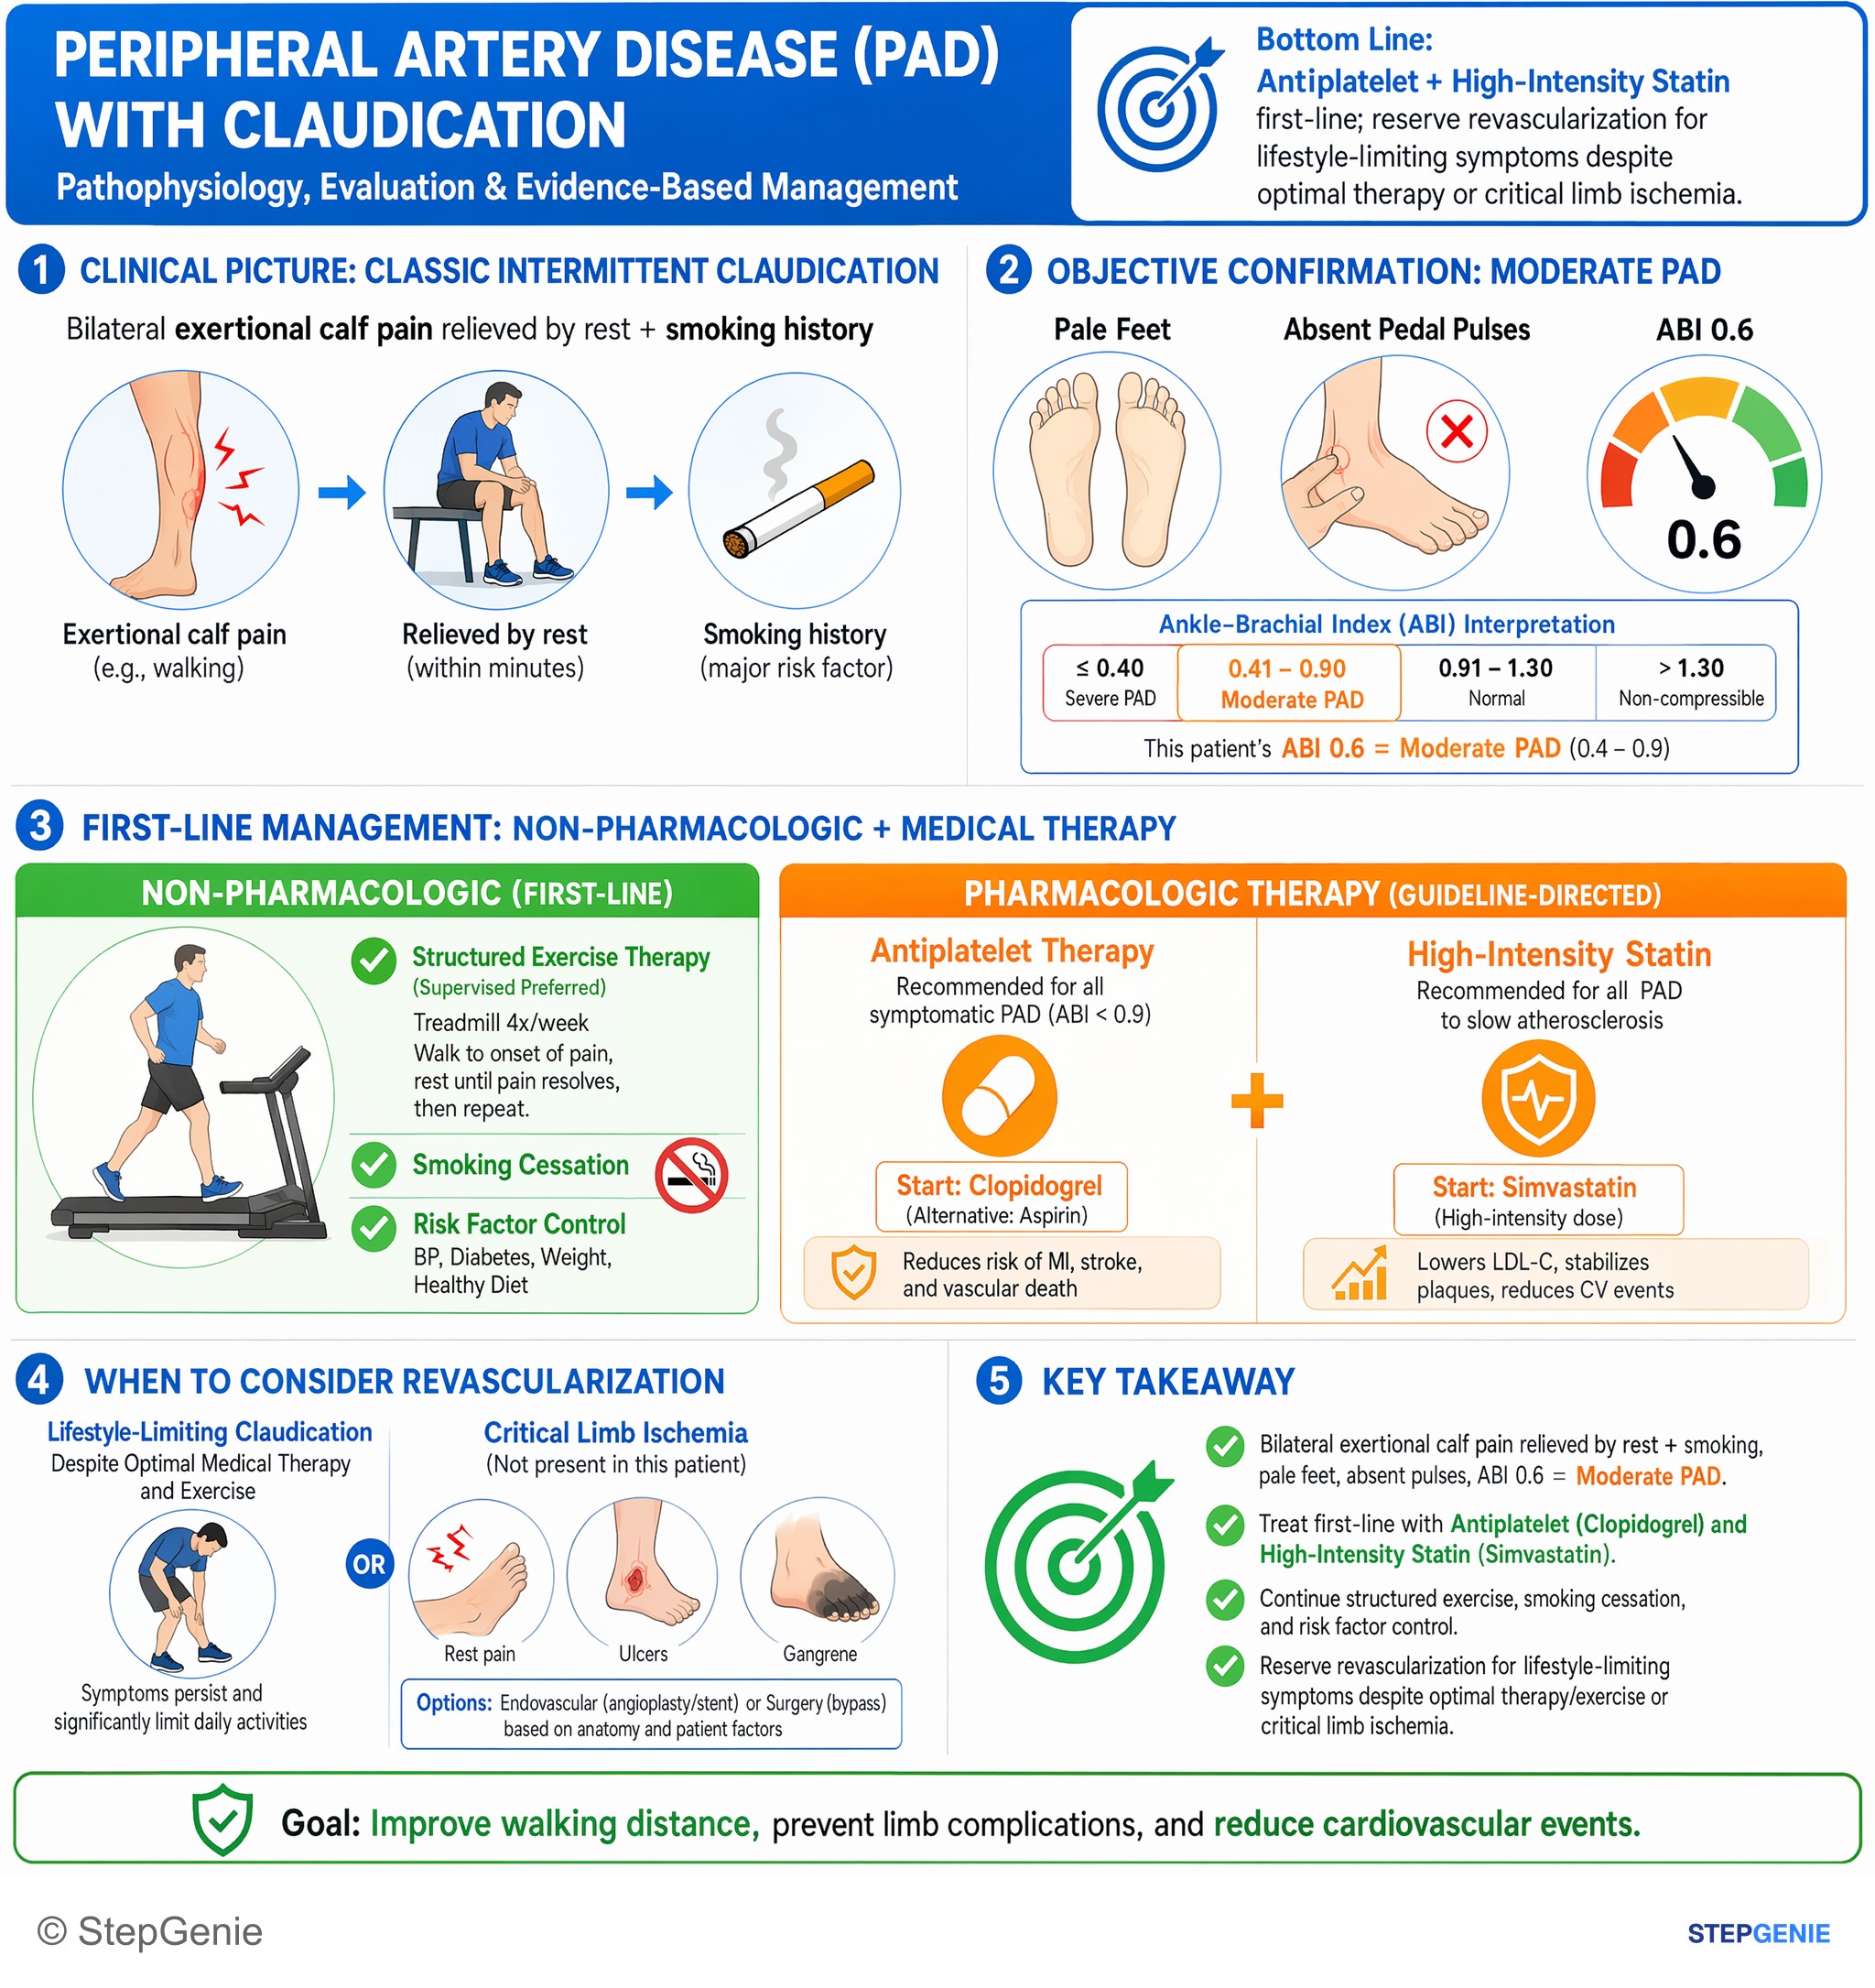
Peripheral artery disease (PAD) with claudication and ABI 0.6 is treated first-line with antiplatelet and high-intensity statin; reserve…
USMLE Step 2
Peripheral artery disease from atherosclerosis causes exertional calf/leg claudication; first-line therapy is supervised exercise program…
USMLE Step 2Frequently Asked Questions
How do you quickly recognize peripheral artery disease on a USMLE-style stem?
Peripheral artery disease is suggested by pain with walking, a low ABI, and diminished pulses. Classic chronic PAD causes crampy calf, thigh, or buttock pain with exertion that is relieved within minutes by rest. Stems often also include decreased distal pulses, cool extremities, shiny hairless skin, thickened nails, and nonhealing distal dry ulcers on the toes or feet.
What is the best quick test to confirm PAD, and what ABI value is diagnostic?
The fastest confirmatory test for PAD is the ankle-brachial index, and an ABI of 0.90 or less is diagnostic. ABI is calculated as ankle systolic pressure divided by brachial systolic pressure. Normal is 1.00 to 1.40, borderline is 0.91 to 0.99, and severe ischemia is often seen with ABI below 0.40. If resting ABI is normal despite symptoms, exercise ABI can reveal a drop after treadmill testing.
How do you tell vascular claudication from neurogenic claudication?
Vascular claudication from PAD is triggered by walking or exertion and improves with simple rest, whereas neurogenic claudication is relieved by sitting or leaning forward. PAD also has vascular exam findings such as decreased pulses and cool skin, and the ABI is low. In neurogenic claudication from spinal stenosis, pulses and skin are usually normal and the ABI is normal.
What is the first-line treatment approach for chronic peripheral artery disease?
Chronic PAD is treated with vascular protection for everyone, plus symptom-directed therapy when needed. Foundational management includes smoking cessation, a high-intensity statin, antiplatelet therapy with aspirin or clopidogrel, and control of blood pressure and diabetes. Supervised exercise therapy improves walking distance significantly. For claudication symptoms, cilostazol can help, but it is contraindicated in heart failure.
What should you do for sudden cold, painful, pulseless leg symptoms in PAD?
A sudden cold, pale, painful, pulseless leg should be treated as acute limb ischemia with immediate IV heparin and urgent vascular intervention. This is a limb-threatening emergency caused by sudden arterial occlusion. The key bedside clues are the 5 Ps: pain, pallor, pulselessness, paresthesia, and paralysis, sometimes with poikilothermia. In this setting, do not delay treatment with a long workup.