Rheumatic heart disease (RHD) is permanent valve damage left by one or more attacks of acute rheumatic fever (ARF), an autoimmune reaction that follows group A streptococcal (GAS) pharyngitis by about 2-3 weeks through molecular mimicry (a type II hypersensitivity reaction). The mitral valve is affected most often, then the aortic valve: acute carditis typically causes mitral regurgitation, while chronic RHD classically causes mitral stenosis, with commissural fusion giving a "fish-mouth" valve, a loud S1, an opening snap and a mid-diastolic rumble at the apex. ARF is diagnosed with the 2015 AHA revised Jones criteria (2 major, or 1 major plus 2 minor, with evidence of a preceding GAS infection). Recurrences are prevented with benzathine penicillin G every 3-4 weeks, continued for 5 years to decades depending on whether carditis and residual valve disease are present. RHD affects an estimated 55 million people worldwide and causes about 360,000 deaths a year (WHO).
The Q-bank question
A 27-year-old woman who emigrated from Nepal 4 years ago is at 26 weeks' gestation. She has had 3 weeks of worsening shortness of breath on exertion, orthopnea, and one episode of blood-streaked sputum. As a child she had a febrile illness with painful, swollen joints that moved from one joint to another. Pulse is 118/min and irregularly irregular. Auscultation reveals a loud S1, an early diastolic opening snap, and a low-pitched mid-diastolic rumble at the apex, heard best with the bell while she lies in the left lateral decubitus position. Fine crackles are heard at both lung bases.
Which of the following best describes the underlying valve pathology?
A. Myxomatous degeneration with prolapse of the mitral leaflets into the left atrium B. Commissural fusion and leaflet thickening producing a fish-mouth mitral orifice C. Calcification of the mitral annulus D. Bulky, friable vegetations on the mitral leaflets E. Calcific degeneration of a congenitally bicuspid aortic valve
Answer: B. A loud S1, an opening snap and an apical mid-diastolic rumble mean mitral stenosis. In a young woman who grew up where rheumatic fever is common and had migratory polyarthritis as a child, the cause is chronic RHD: fused commissures and thickened leaflets narrow the orifice into a fish-mouth shape. Pregnancy unmasked it: Merck notes that pulmonary edema in mitral stenosis appears particularly in pregnancy, when blood volume rises. Hemoptysis (rupture of small pulmonary vessels) and atrial fibrillation from left atrial enlargement complete the picture.
Why every other answer is wrong
- A. Myxomatous degeneration (mitral valve prolapse). Gives a mid-systolic click, followed by a late systolic murmur once regurgitation develops. Standing and Valsalva move the click earlier; squatting delays it. Associations include Marfan and Ehlers-Danlos syndromes. Systolic sounds, not a diastolic rumble; see mitral valve prolapse.
- C. Mitral annular calcification. A growing cause of mitral stenosis in older patients, where calcium in the annulus, rather than fused commissures, narrows the valve. A 27-year-old with a rheumatic history does not fit.
- D. Infective endocarditis vegetations. Expect fever, a new or changing regurgitant murmur, positive blood cultures (2, ideally 3, sets), emboli, and peripheral signs: painful Osler nodes, painless Janeway lesions, splinter hemorrhages and Roth spots. Rheumatic valve disease is a major predisposing factor for endocarditis, but this afebrile, slowly progressive stenosis is not an infection. Compare infective endocarditis.
- E. Calcified bicuspid aortic valve. Causes aortic stenosis: a crescendo-decrescendo systolic ejection murmur at the upper sternal borders radiating to the carotids, often with an ejection click, and the triad of exertional syncope, angina and dyspnea. A bicuspid valve is the main cause of aortic stenosis before age 70. Wrong timing (systolic) and wrong location.
From strep throat to scarred valve
- Trigger. ARF follows GAS pharyngitis by about 2-3 weeks (CDC gives a range of 1-5 weeks), mostly in children aged 5-15. Treating strep throat with appropriate antibiotics prevents rheumatic fever; that is primary prevention.
- Mechanism. GAS M proteins share epitopes with proteins in synovium, heart muscle and heart valves, so the immune response against the bacterium cross-reacts with the host (molecular mimicry). StatPearls classes it as a type II hypersensitivity reaction. Host genetics matter too (class II HLA antigens, the D8/17 B-cell antigen). More in molecular mimicry and the Streptococcus pyogenes 5-second rule.
- Pancarditis. Carditis involves the valves and endocardium, then the myocardium, and finally the pericardium. The classic histology is the Aschoff body, a granulomatous collection of leukocytes, myocytes and interstitial collagen.
- Which valves. Left-sided valves dominate: mitral most often (the mitral valve alone in an estimated 50-60% of cases), then aortic. The tricuspid valve is involved in about 10%, and only together with mitral or aortic disease; the pulmonary valve rarely.
- Acute vs chronic. During ARF, mitral regurgitation (an apical pansystolic murmur radiating to the axilla) is most common. Over 2-3 decades, healing with scarring leaves stenosis and/or regurgitation, and mitral stenosis predominates in chronic disease; symptoms may not appear until 15 or more years after the attack. StatPearls describes the stiff anterior leaflet as a "hockey-stick" deformity.
2015 AHA revised Jones criteria
| Low-risk population | Moderate- or high-risk population | |
|---|---|---|
| Definition | ARF incidence ≤2 per 100,000 school-aged children per year, or all-age RHD prevalence ≤1 per 1,000 per year | Populations not clearly low risk |
| Major: carditis | Clinical and/or subclinical (echocardiographic valvulitis) | Clinical and/or subclinical |
| Major: arthritis | Polyarthritis only | Monoarthritis or polyarthritis, or polyarthralgia (once other causes are excluded) |
| Major: other | Chorea, erythema marginatum, subcutaneous nodules | Same |
| Minor: joints | Polyarthralgia | Monoarthralgia |
| Minor: fever | ≥38.5°C | ≥38°C |
| Minor: inflammation | ESR ≥60 mm/h and/or CRP ≥3.0 mg/dL | ESR ≥30 mm/h and/or CRP ≥3.0 mg/dL |
| Minor: ECG | Prolonged PR interval for age (not if carditis is counted as major) | Same |
- Initial ARF: 2 major, or 1 major plus 2 minor. Recurrent ARF: 2 major, 1 major plus 2 minor, or 3 minor. Both need evidence of a preceding GAS infection: a positive throat culture or rapid antigen test, or a raised or rising streptococcal antibody titer (such as antistreptolysin O).
- Fever cut-off: the AHA statement uses 38.5°C for low-risk and 38°C for moderate- or high-risk populations. CDC's summary page lists 38.5°C for both groups, but the AHA statement is the primary source.
- Echocardiography with Doppler is recommended for every confirmed or suspected case; subclinical carditis found this way counts as a major criterion.
- Mnemonic J♥NES: Joints, ♥ carditis, Nodules, Erythema marginatum, Sydenham chorea.
- How common: carditis occurs in 50-70% of first episodes and arthritis in up to 75% (CDC). Arthritis is migratory and affects large joints. Erythema marginatum is a serpiginous, flat or slightly raised, painless, nonscarring rash; nodules sit over extensor surfaces, usually with arthritis and carditis. Sydenham chorea (rapid irregular jerks, "milkmaid's grip," tongue darting) often appears after the other features have settled, sometimes months after the strep infection.
Mitral stenosis: what you hear and what follows
| Finding | Why |
|---|---|
| Loud S1 | Stiff, stenotic leaflets close abruptly |
| Opening snap in early diastole | Leaflets billow into the LV; the closer the snap is to S2, the more severe the stenosis |
| Low-pitched mid-diastolic rumble with presystolic accentuation | Heard best with the bell at the apex, left lateral decubitus, end-expiration; atrial contraction adds the presystolic crescendo |
| Atrial fibrillation, stroke | Left atrial enlargement; untreated AF with mitral stenosis carries up to about 5% stroke risk per year |
| Dyspnea, orthopnea, hemoptysis | Rising left atrial and pulmonary venous pressure; pulmonary edema, especially in pregnancy |
| Hoarseness (Ortner syndrome) | Dilated left atrium or pulmonary artery compresses the left recurrent laryngeal nerve |
| Malar flush, right heart failure | Severe pulmonary hypertension with low cardiac output |
Normal mitral valve area is 4-5 cm²; severe stenosis is a valve area of 1.5 cm² or less. The ECG shows left atrial enlargement (broad P wave), and the chest x-ray shows straightening of the left heart border from a dilated left atrial appendage, with Kerley B lines when there is interstitial edema. Echocardiography makes the diagnosis. For the full murmur set, see heart murmurs for USMLE.
Management
Acute rheumatic fever
- Eradicate GAS: a 10-day course of oral penicillin or amoxicillin, or a single injection of benzathine penicillin G.
- Anti-inflammatory treatment with aspirin; corticosteroids for moderate to severe carditis.
Secondary prophylaxis (prevents recurrences that add valve damage)
- Benzathine penicillin G IM every 3-4 weeks; every 3 weeks works better than every 4 in high-burden regions. Alternatives: oral penicillin V twice daily or sulfadiazine; erythromycin or azithromycin if allergic to both penicillin and sulfa.
| Rheumatic fever history | Duration of prophylaxis (2020 ACC/AHA valvular guideline) |
|---|---|
| Carditis with residual heart disease | 10 years or until age 40, whichever is longer (many experts continue it indefinitely) |
| Carditis without residual heart disease | 10 years or until age 21, whichever is longer |
| No carditis | 5 years or until age 21, whichever is longer |
Rheumatic mitral stenosis
- Diuretics for congestion; beta-blockers or nondihydropyridine calcium channel blockers to slow the heart rate (a longer diastole gives the left atrium more time to empty).
- Atrial fibrillation with rheumatic mitral stenosis: long-term warfarin (a vitamin K antagonist); DOACs are not recommended. See atrial fibrillation.
- Symptomatic severe stenosis with favorable valve anatomy: percutaneous balloon mitral commissurotomy; otherwise surgical repair or replacement.
- Merck notes that endocarditis prophylaxis is not recommended for mitral stenosis itself (it applies after valve replacement). Do not confuse dental endocarditis prophylaxis with long-term rheumatic fever prophylaxis.
How USMLE tests it
- Young immigrant, opening snap, diastolic rumble, atrial fibrillation = rheumatic mitral stenosis until proven otherwise; in older patients, think mitral annular calcification.
- Child 2-3 weeks after a sore throat with migratory arthritis and a new apical holosystolic murmur = ARF with carditis (acute mitral regurgitation).
- Mechanism question: molecular mimicry against M protein, type II hypersensitivity; histology shows Aschoff bodies.
- Pregnancy is a classic trigger for decompensation of known or hidden mitral stenosis.
- Two prophylaxes: long-term benzathine penicillin prevents ARF recurrences; dental prophylaxis prevents endocarditis in specific high-risk patients. Know which the stem is asking about.
- Anticoagulant trap: AF with rheumatic mitral stenosis needs warfarin, not a DOAC.
Key takeaways
- RHD = valve scarring after ARF, which follows GAS pharyngitis via molecular mimicry (type II hypersensitivity).
- Mitral > aortic; acute ARF gives mitral regurgitation, chronic RHD gives mitral stenosis with commissural fusion (fish-mouth).
- Mitral stenosis: loud S1, opening snap, apical mid-diastolic rumble; left atrial enlargement, AF, hemoptysis, hoarseness; severe at ≤1.5 cm².
- 2015 Jones: 2 major or 1 major + 2 minor (+ GAS evidence); thresholds differ for low-risk and moderate/high-risk populations; echocardiography in all cases.
- Benzathine penicillin G every 3-4 weeks: 10 years or to age 40 with residual valve disease; 10 years or to 21 after carditis without it; 5 years or to 21 without carditis.
- AF with rheumatic MS: warfarin, not DOACs; severe symptomatic MS with favorable anatomy: balloon commissurotomy.
Sources
- Rheumatic Fever — Merck Manual Professional Edition (2026)
- Technology Enhances Historical Criteria: The Revision of the Jones Criteria for Acute Rheumatic Fever — American Heart Association Professional Heart Daily (2015, updated 2023)
- Diagnosing Acute Rheumatic Fever — Centers for Disease Control and Prevention (2025)
- Clinical Guidance for Acute Rheumatic Fever — Centers for Disease Control and Prevention (2025)
- 2020 ACC/AHA Guideline for the Management of Patients With Valvular Heart Disease — Journal of the American College of Cardiology (2021)
- Mitral Stenosis — Merck Manual Professional Edition (2025)
- Rheumatic Heart Disease — World Health Organization Fact Sheet (2025)
- Rheumatic Heart Disease — StatPearls, NCBI Bookshelf (2023)
- Mitral Valve Repair — StatPearls, NCBI Bookshelf (2026)
- Mitral Valve Prolapse (MVP) — Merck Manual Professional Edition (2025)
- Aortic Stenosis — Merck Manual Professional Edition (2025)
- Infective Endocarditis — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
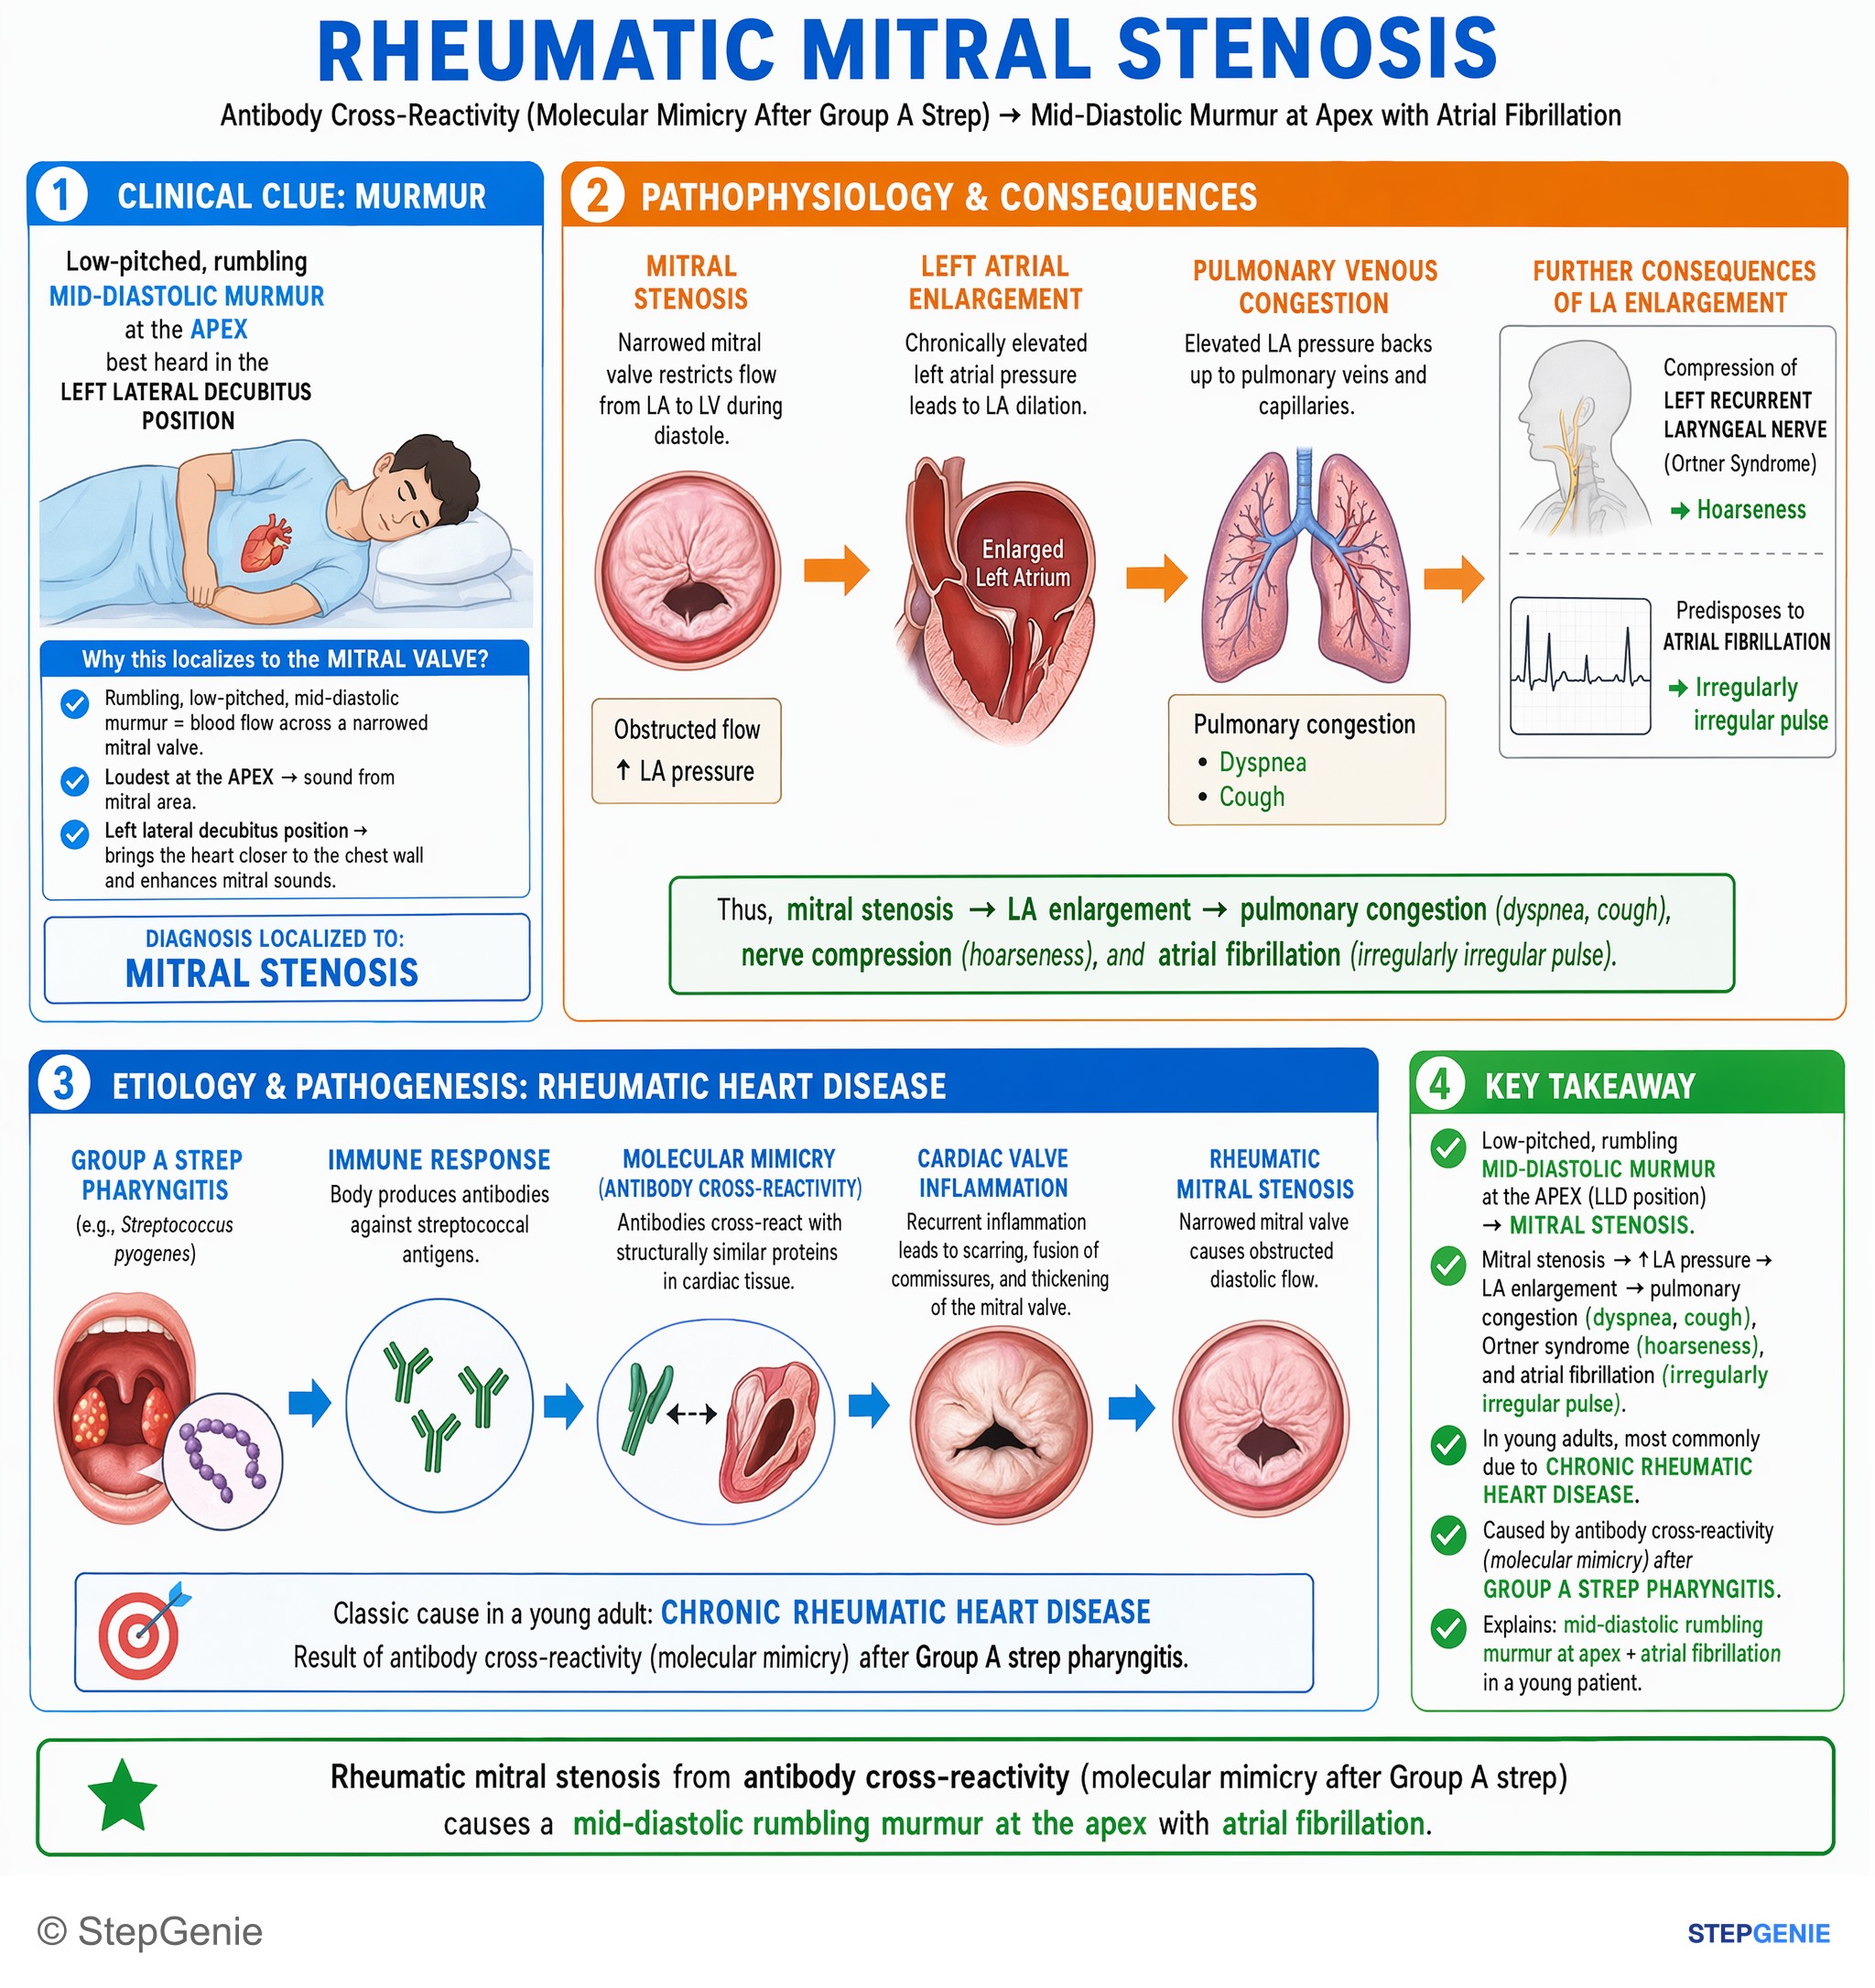
Rheumatic mitral stenosis from antibody cross-reactivity (molecular mimicry after group A strep) causes mid-diastolic rumbling murmur at…
USMLE Step 1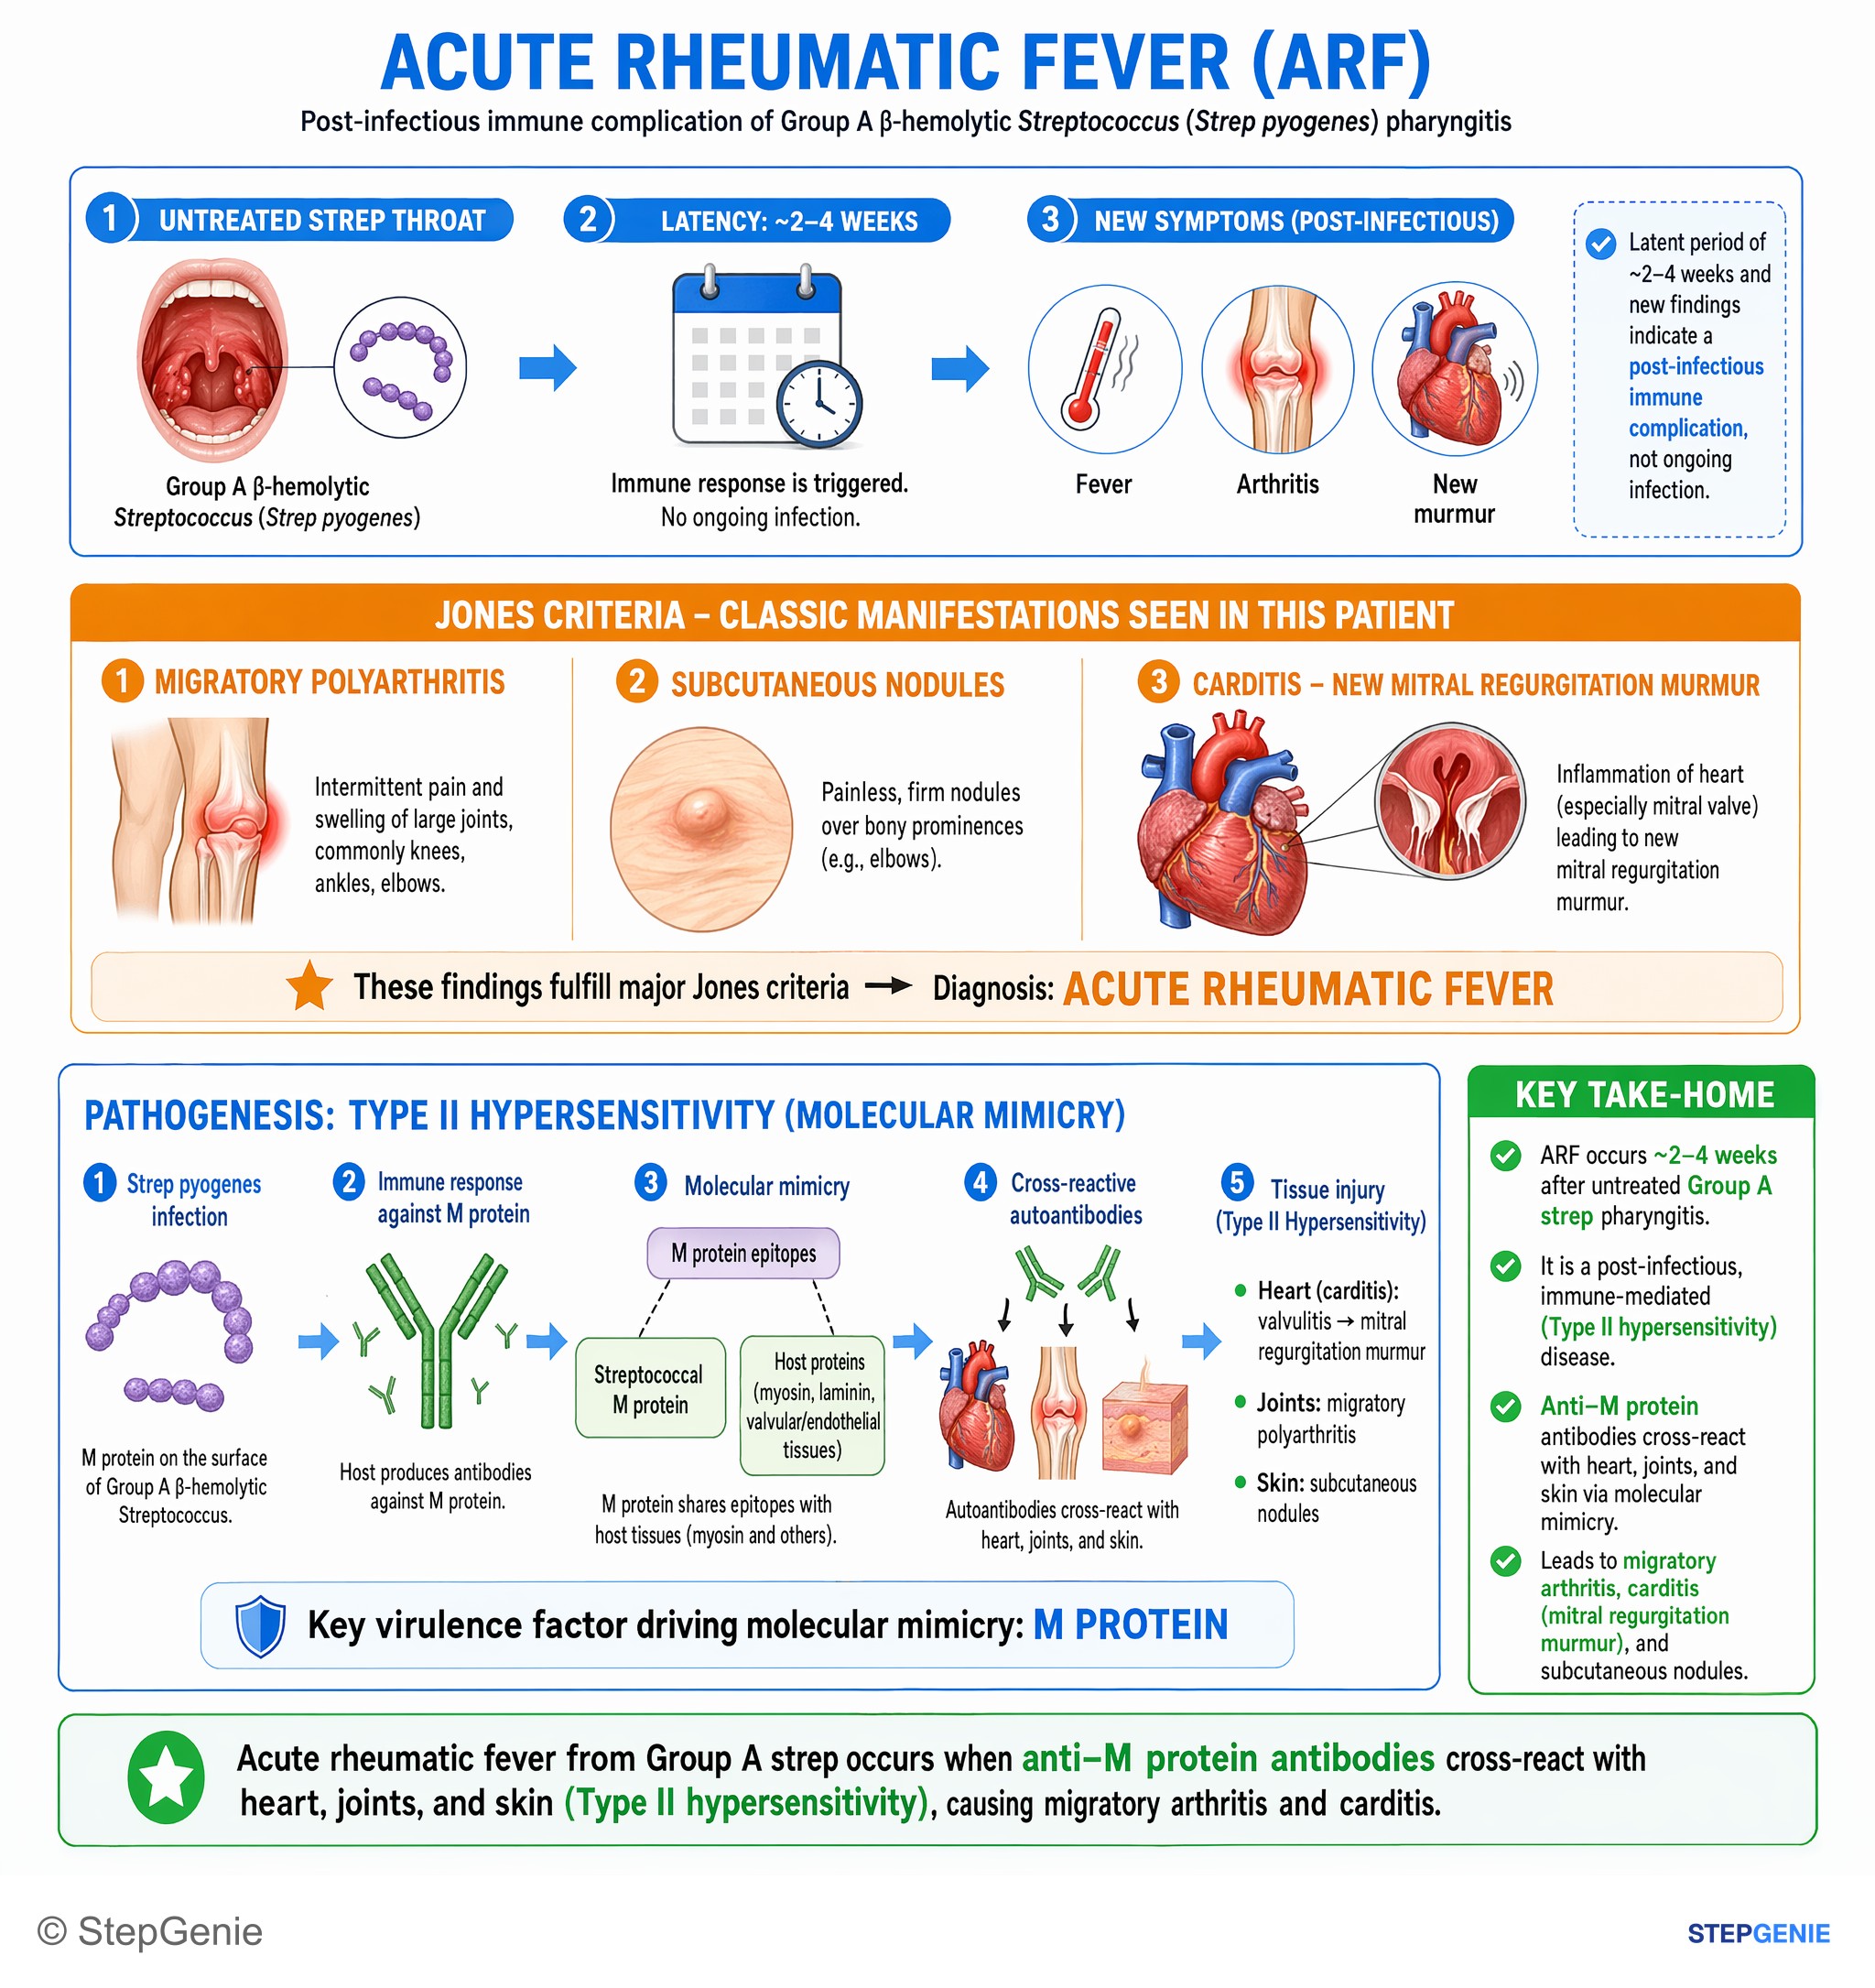
Acute rheumatic fever from group A strep: anti–M protein antibodies cross-react with heart, joints, skin (type II hypersensitivity)…
USMLE Step 1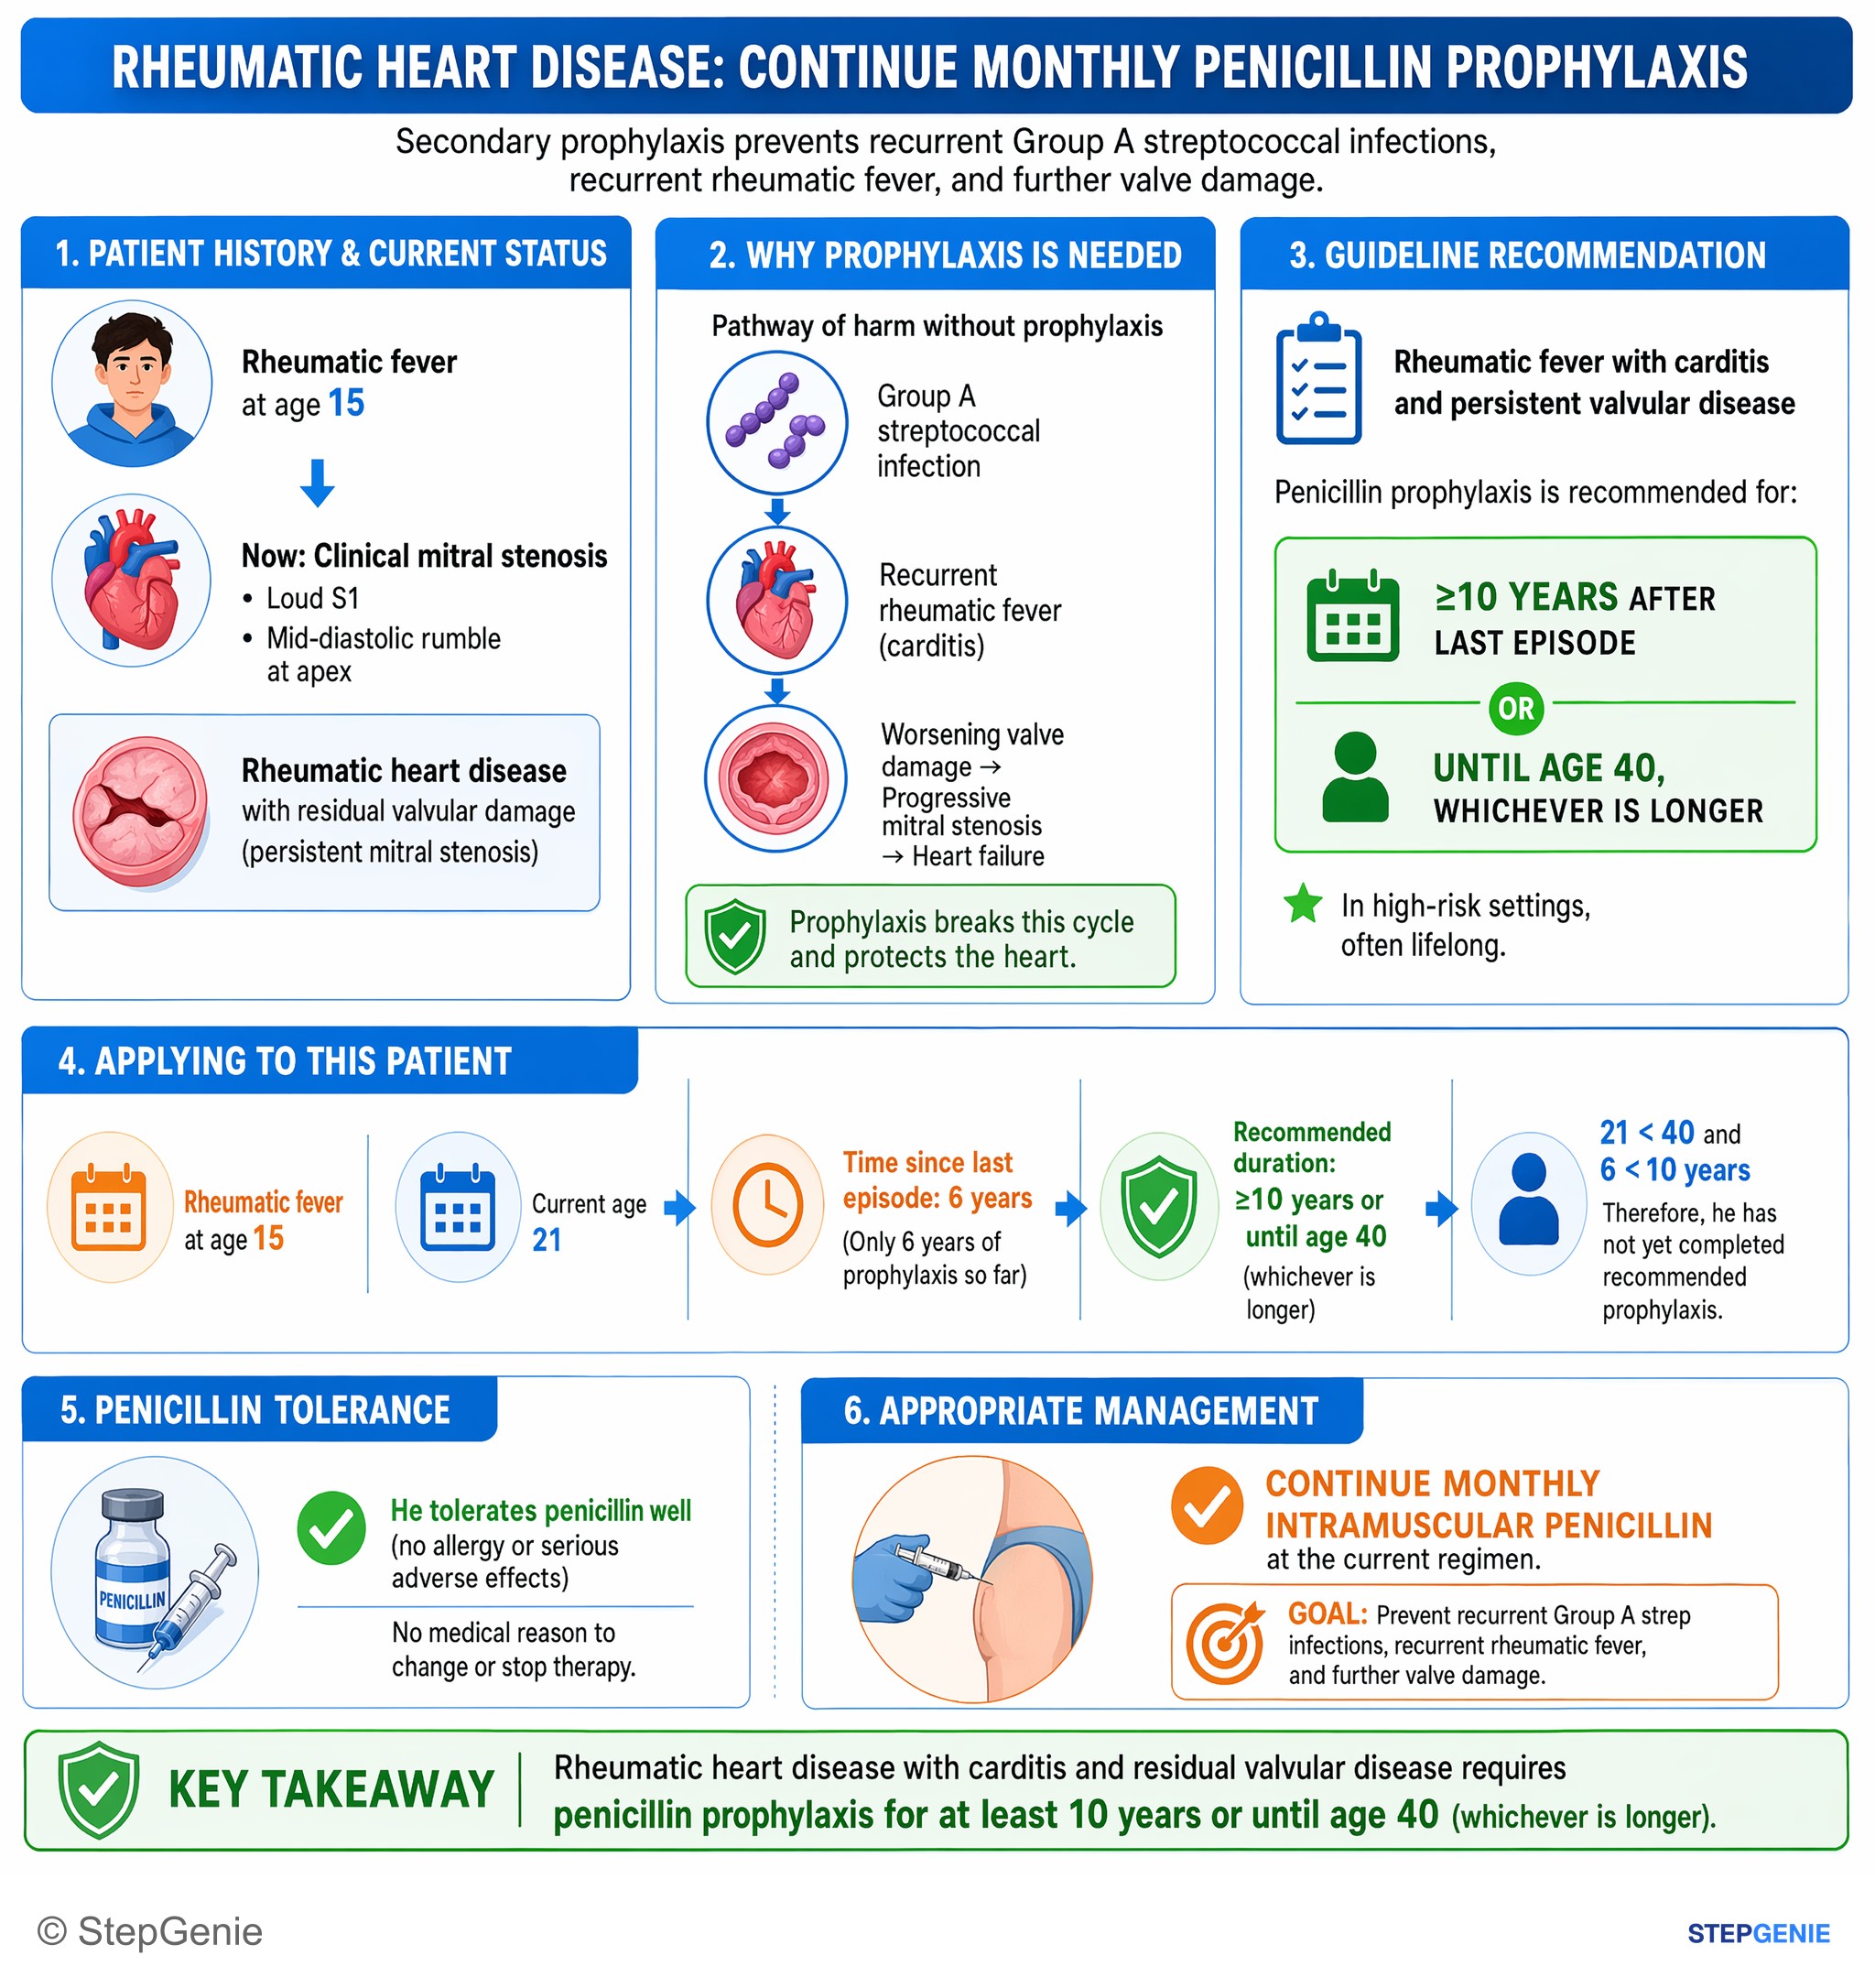
Rheumatic heart disease with carditis and residual valvular disease requires penicillin prophylaxis for at least 10 years or until age 40…
USMLE Step 2Frequently Asked Questions
What causes rheumatic heart disease?
Rheumatic heart disease is permanent heart valve damage left by one or more attacks of acute rheumatic fever. Acute rheumatic fever is an autoimmune reaction that follows group A streptococcal pharyngitis by about 2 to 3 weeks, mostly in children aged 5 to 15. Streptococcal M proteins share epitopes with proteins in heart valves, heart muscle and joints, so the immune response cross-reacts with the heart (molecular mimicry, a type II hypersensitivity reaction). Treating strep throat with antibiotics prevents rheumatic fever.
Which heart valve is most affected in rheumatic heart disease?
The mitral valve is affected most often, followed by the aortic valve; the tricuspid valve is involved in about 10% of cases and only together with mitral or aortic disease, and the pulmonary valve rarely. During acute rheumatic fever, mitral regurgitation is the most common lesion. Over years to decades, scarring with commissural fusion produces mitral stenosis, the classic lesion of chronic rheumatic heart disease, with a fish-mouth valve orifice.
What are the revised Jones criteria?
The 2015 AHA revised Jones criteria diagnose acute rheumatic fever. Major criteria are carditis (clinical or subclinical on echocardiography), arthritis, chorea, erythema marginatum and subcutaneous nodules. Minor criteria are arthralgia, fever, raised ESR or CRP, and a prolonged PR interval, with lower thresholds in moderate- and high-risk populations. A first attack needs 2 major or 1 major plus 2 minor criteria, plus evidence of a preceding group A strep infection; a recurrence can also be diagnosed with 3 minor criteria.
How long is penicillin prophylaxis needed after rheumatic fever?
Secondary prophylaxis, usually benzathine penicillin G injections every 3 to 4 weeks, prevents recurrences. Per the 2020 ACC/AHA valvular heart disease guideline: after rheumatic fever with carditis and residual heart disease, 10 years or until age 40, whichever is longer; with carditis but no residual heart disease, 10 years or until age 21; and without carditis, 5 years or until age 21, whichever is longer. Many experts continue it indefinitely when valve damage persists.
What are the signs of rheumatic mitral stenosis?
Auscultation reveals a loud S1, an opening snap in early diastole and a low-pitched mid-diastolic rumble at the apex, heard best with the bell in the left lateral decubitus position; the closer the snap is to S2, the more severe the stenosis. Patients develop exertional dyspnea, orthopnea, hemoptysis, atrial fibrillation from left atrial enlargement, and sometimes hoarseness (Ortner syndrome). Pregnancy often brings on pulmonary edema because blood volume increases.
Why is warfarin used instead of DOACs in rheumatic mitral stenosis with atrial fibrillation?
The 2020 ACC/AHA valvular heart disease guideline recommends long-term vitamin K antagonist anticoagulation, that is warfarin, for patients with atrial fibrillation and rheumatic mitral stenosis. These patients were excluded from the DOAC trials, and the guideline says DOAC use cannot be supported over warfarin. Untreated atrial fibrillation with mitral stenosis carries up to about a 5% yearly risk of stroke, so anticoagulation is essential. Picking a DOAC for this patient is a common exam trap.