Ventricular septal defect (VSD) is the most common congenital heart defect, and it’s a classic USMLE “murmur + physiology” question. The trick isn’t memorizing a thousand facts—it’s knowing what changes with size, what happens over time, and what murmur you’re actually hearing.
The One-Liner (commit this)
VSD = hole between ventricles → left-to-right shunt (postnatal) → ↑ pulmonary blood flow; small = loud murmur, large = heart failure + pulmonary HTN → Eisenmenger late.
Visual + Mnemonic Device
“Loud Little, Quiet Big”
- Small VSD: Loud murmur, Low symptoms
- Large VSD: Quieter murmur (less turbulence as pressures equalize), Quite sick (CHF, pulmonary HTN)
Think: “Little hole screams; big hole whispers.”
Flow doodle (mentally sketch it)
LV (high P) → RV (low P) → lungs (overcirculation)
Over time, lungs remodel → pulmonary vascular resistance rises → shunt can flip.
What It Is (and why it happens)
A VSD is an abnormal opening in the interventricular septum, most often:
- Membranous VSD (most common subtype)
Associations/high-yield context:
- Can be isolated or seen with congenital syndromes (e.g., trisomy 21 often has septal defects, especially AV septal defects, but VSDs can occur)
- Some close spontaneously (especially smaller muscular defects)
Hemodynamics: the testable logic
Why it’s left-to-right after birth
After birth, systemic vascular resistance (SVR) > pulmonary vascular resistance (PVR), so:
- LV pressure > RV pressure → blood flows LV → RV during systole
Qp:Qs (concept you should recognize)
Shunt size relates to pulmonary vs systemic blood flow:
- Left-to-right shunts increase (pulmonary flow)
- Clinically: more shunt → more pulmonary overcirculation → more CHF risk
Classic Murmur Findings (what your ears should “see”)
The hallmark murmur
- Harsh holosystolic murmur best heard at the left lower sternal border (LLSB)
- Often with a thrill if small/moderate
Size vs murmur intensity (high-yield trap)
| VSD Size | Shunt magnitude | Murmur | Symptoms |
|---|---|---|---|
| Small (restrictive) | Small | Very loud (high turbulence), harsh holosystolic | Often asymptomatic |
| Moderate | Moderate | Loud holosystolic | May develop mild CHF |
| Large (nonrestrictive) | Large early, then pressure equalizes | Softer murmur may occur | CHF, poor feeding, diaphoresis; later pulmonary HTN |
Additional heart sounds you might see
- With significant left-to-right shunt: mid-diastolic rumble at apex (increased flow across mitral valve)
- With pulmonary HTN developing: loud P2 can appear
Presentation: what Step questions like to describe
Small VSD
- Incidental murmur in otherwise well child
- Normal growth and feeding
Large VSD (weeks to months after birth)
Symptoms often appear after PVR physiologically falls:
- Tachypnea, poor feeding, diaphoresis
- Failure to thrive
- Recurrent respiratory infections
Natural History: Eisenmenger is the endgame
Untreated significant shunt → chronic pulmonary overcirculation → pulmonary arteriolar hypertrophy → pulmonary HTN.
When PVR exceeds SVR, shunt reverses:
- Right-to-left shunt → cyanosis (often later childhood/adulthood)
- Eisenmenger syndrome
High-yield consequences:
- Differential cyanosis is more PDA-classic; VSD Eisenmenger tends to cause more generalized cyanosis.
- Clubbing, erythrocytosis, hyperviscosity symptoms can develop.
Diagnostics: what to order and what it shows
Echocardiography (best test)
- Direct visualization of defect
- Estimates shunt severity, RV pressure, pulmonary pressures
Chest X-ray (pattern recognition)
- Small VSD: may be normal
- Large VSD: cardiomegaly + increased pulmonary vascular markings
ECG
- Small: often normal
- Larger shunts: LVH (volume load), possible biventricular hypertrophy if severe
Management: the “what do we do” algorithm
Small (restrictive) VSD
- Often observe (many close spontaneously)
- Endocarditis prophylaxis is not routine for uncomplicated VSD (mainly for certain high-risk conditions or prior endocarditis)
Symptomatic large VSD (CHF signs)
- Medical therapy to stabilize:
- Diuretics (e.g., furosemide)
- +/- afterload reduction (institution-dependent; conceptually decreases LV workload)
- Definitive closure (catheter or surgery) if:
- Persistent symptoms despite medical therapy
- Poor growth
- Rising pulmonary pressures (prevent irreversible pulmonary vascular disease)
Eisenmenger physiology
- Do not close the defect once irreversible pulmonary vascular disease is established (can precipitate RV failure)
- Manage pulmonary HTN, avoid triggers; pregnancy is high risk.
High-Yield Differentials (don’t mix these up)
| Condition | Key clue | Murmur location/quality | Other high-yield point |
|---|---|---|---|
| VSD | Loud holosystolic at LLSB | Harsh holosystolic | Small = loud, large = CHF + pulmonary HTN |
| ASD | Fixed split S2 | Systolic ejection at LUSB | Increased flow across pulmonic valve; paradoxical emboli risk |
| PDA | Continuous “machine-like” | Left infraclavicular | Differential cyanosis late; associated with congenital rubella |
| TOF | Cyanotic spells, boot-shaped heart | Harsh systolic at LUSB | Right-to-left shunt due to RVOT obstruction |
Rapid-Fire USMLE Pearls (the stuff that scores points)
- Most common congenital heart defect overall: VSD
- Most common subtype: membranous VSD
- Holosystolic murmur at LLSB = think VSD first
- Symptoms appear after PVR falls (weeks) → large VSD becomes clinically obvious
- Loud murmur ≠ severe disease (small restrictive defects are loud)
- Untreated large VSD → pulmonary HTN → Eisenmenger → cyanosis + clubbing
- Large shunt can cause failure to thrive and recurrent respiratory infections
The 10-second Cheat Sheet (shareable)
VSD: LV → RV shunt postnatally. Harsh holosystolic murmur at LLSB. Small = loud/benign; large = CHF + ↑ pulm flow → pulm HTN → Eisenmenger (cyanosis late). Dx echo. Treat CHF + close before irreversible pulm HTN.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
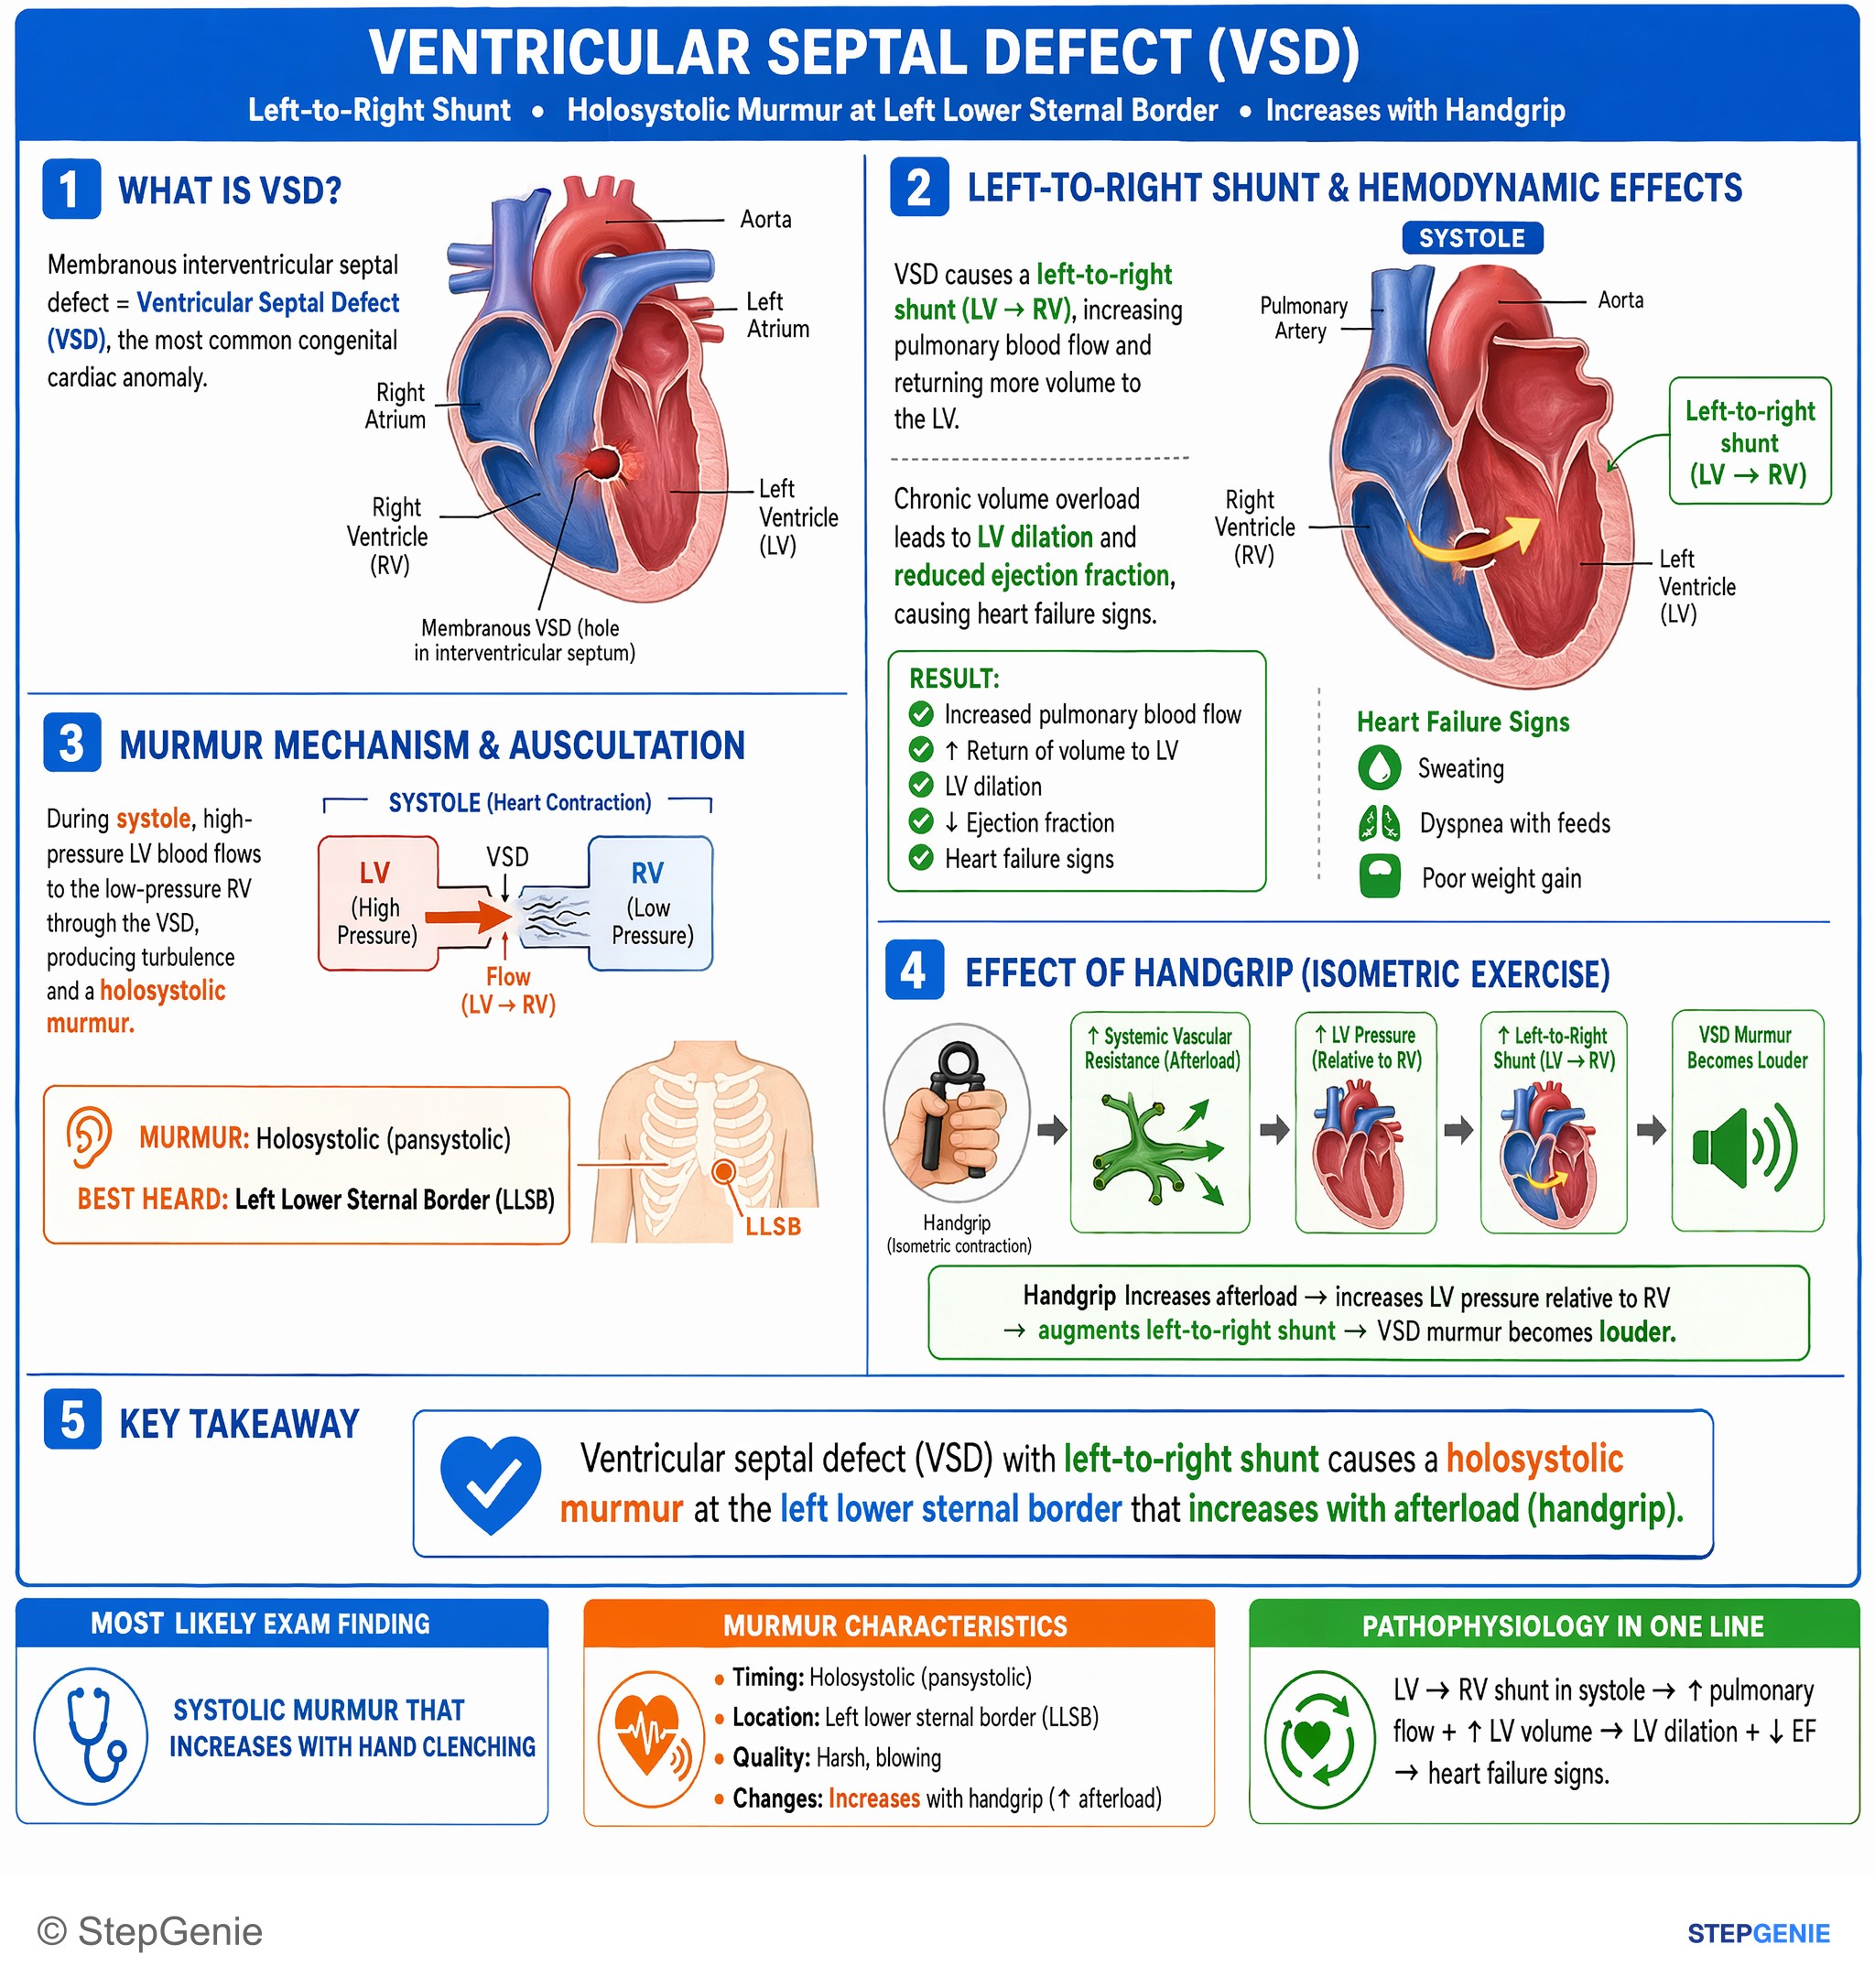
Ventricular septal defect (VSD) with left-to-right shunt causes a holosystolic murmur at left lower sternal border that increases with…
USMLE Step 1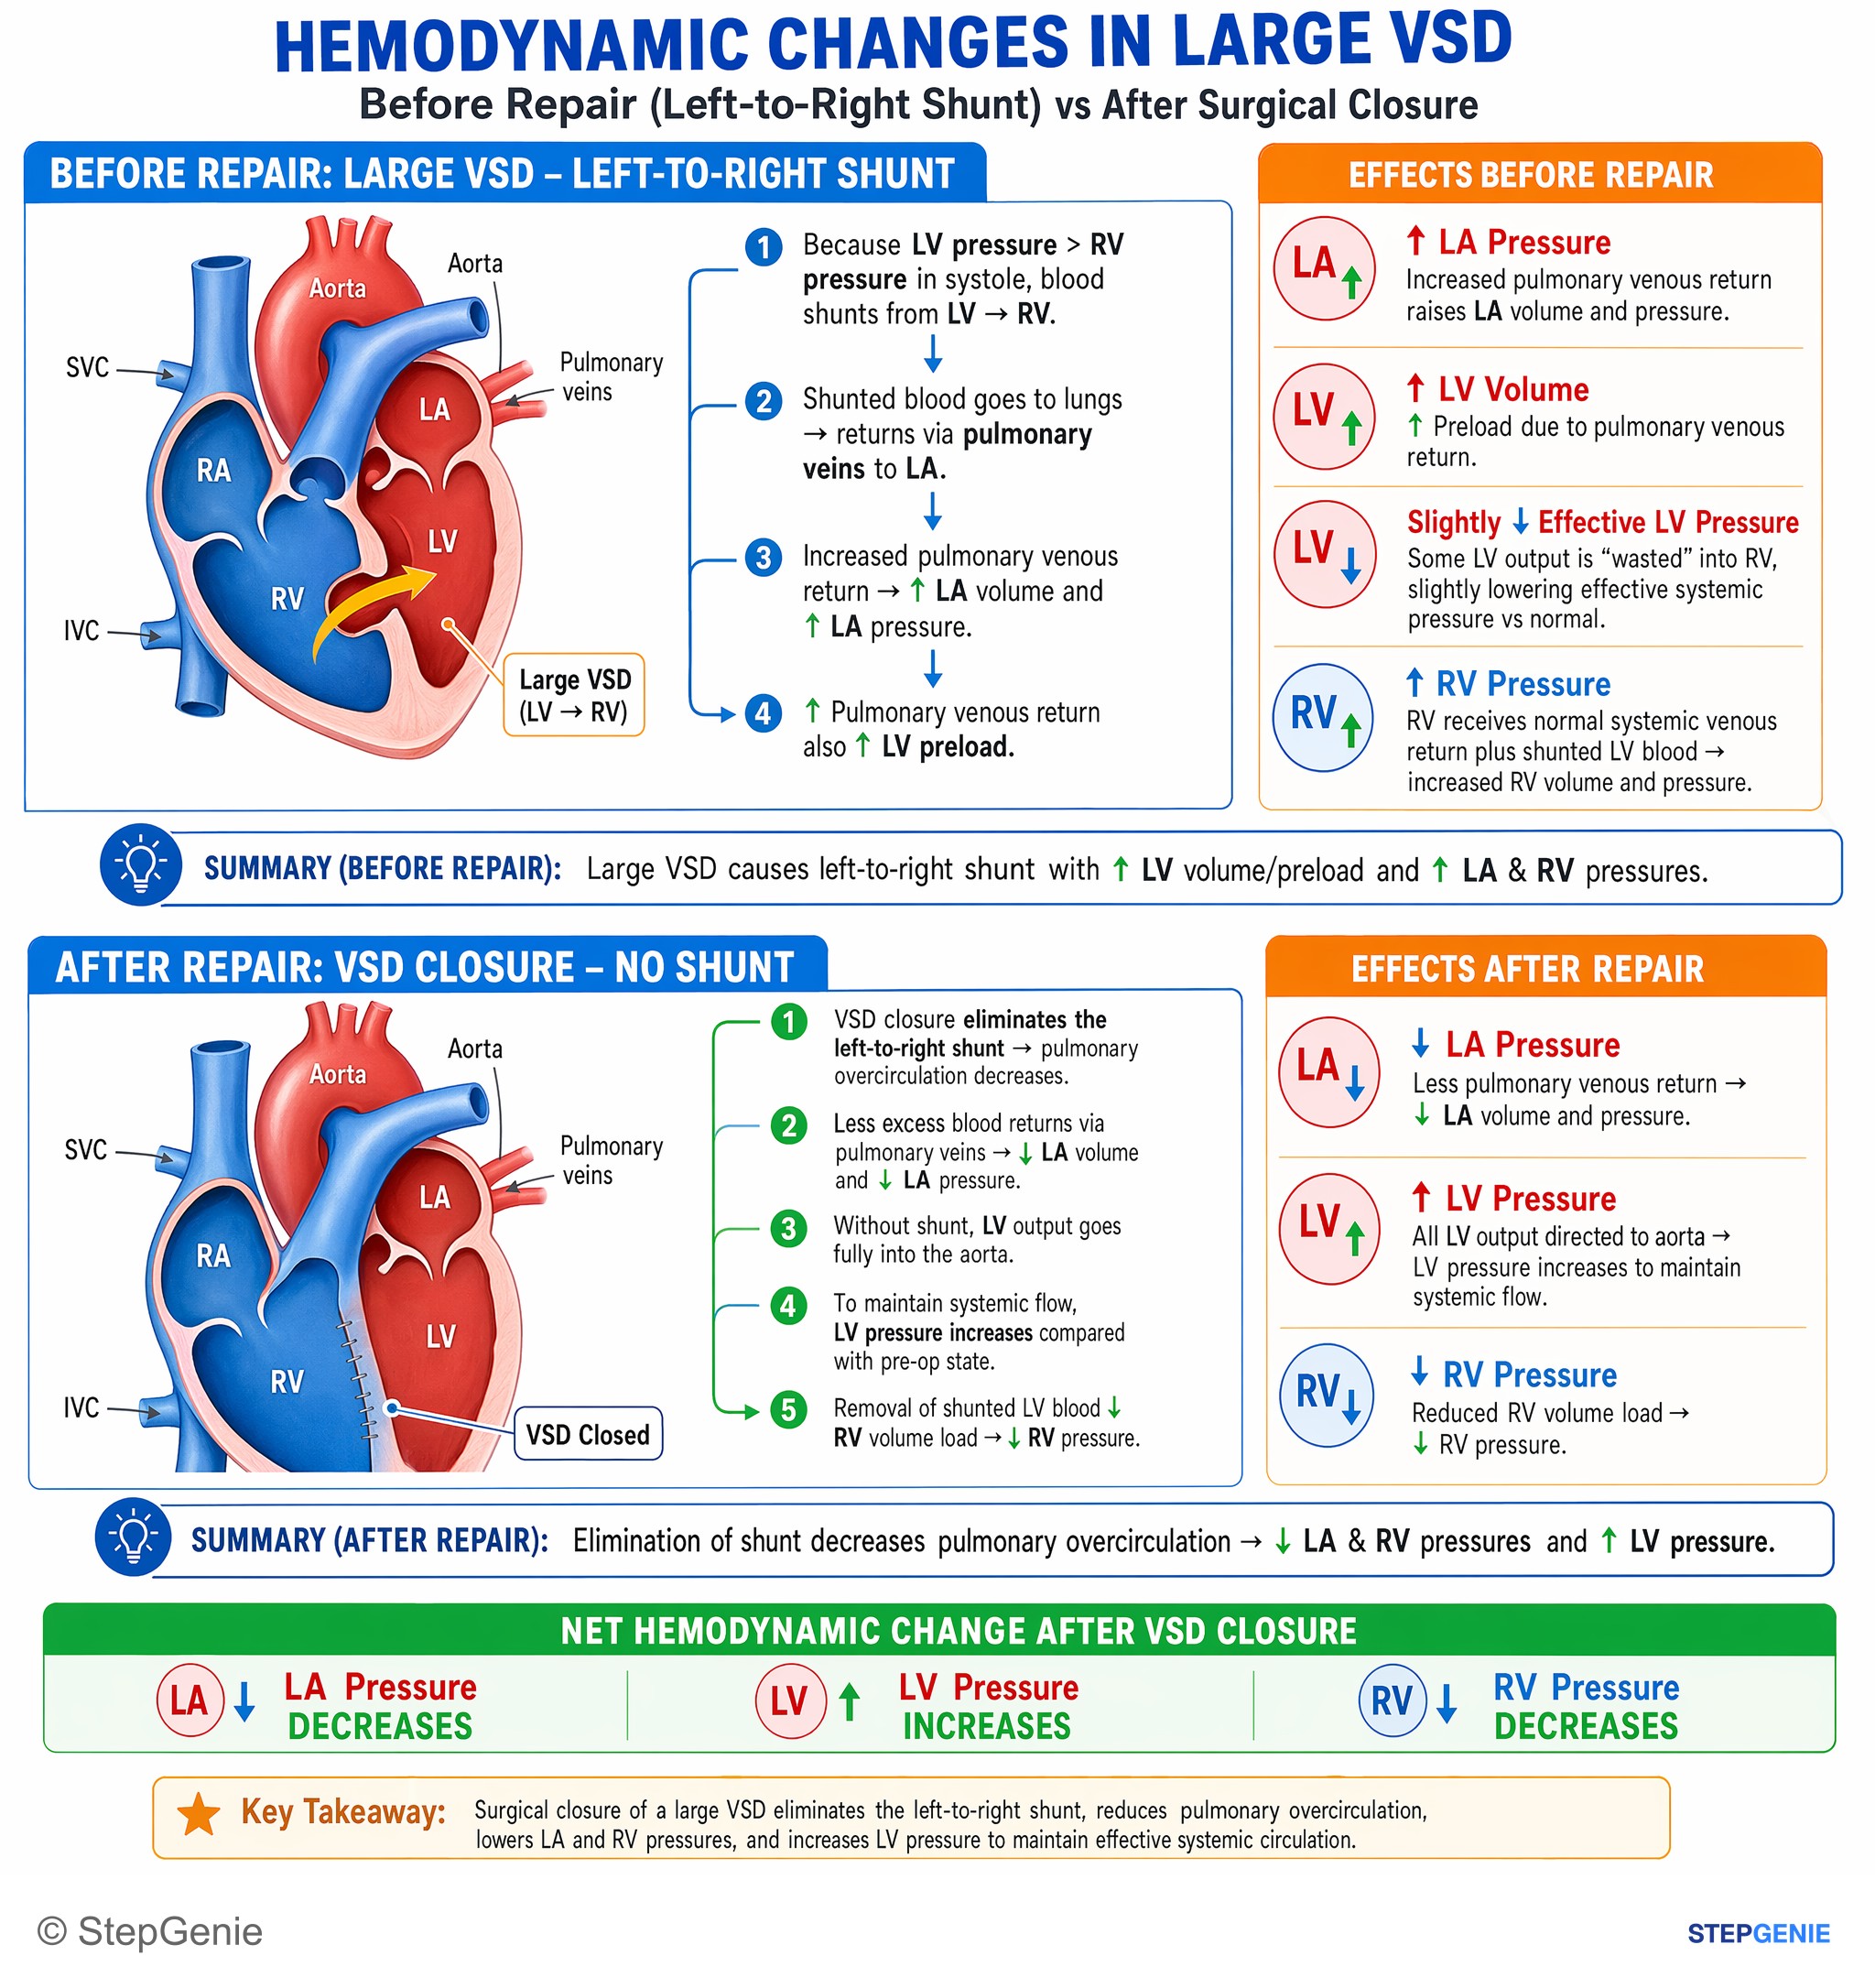
Large VSD causes left-to-right shunt with ↑ LV volume/pressure and ↑ LA, RV pressures; surgical closure ↓ LA & RV pressures, ↑ LV pressure.
USMLE Step 1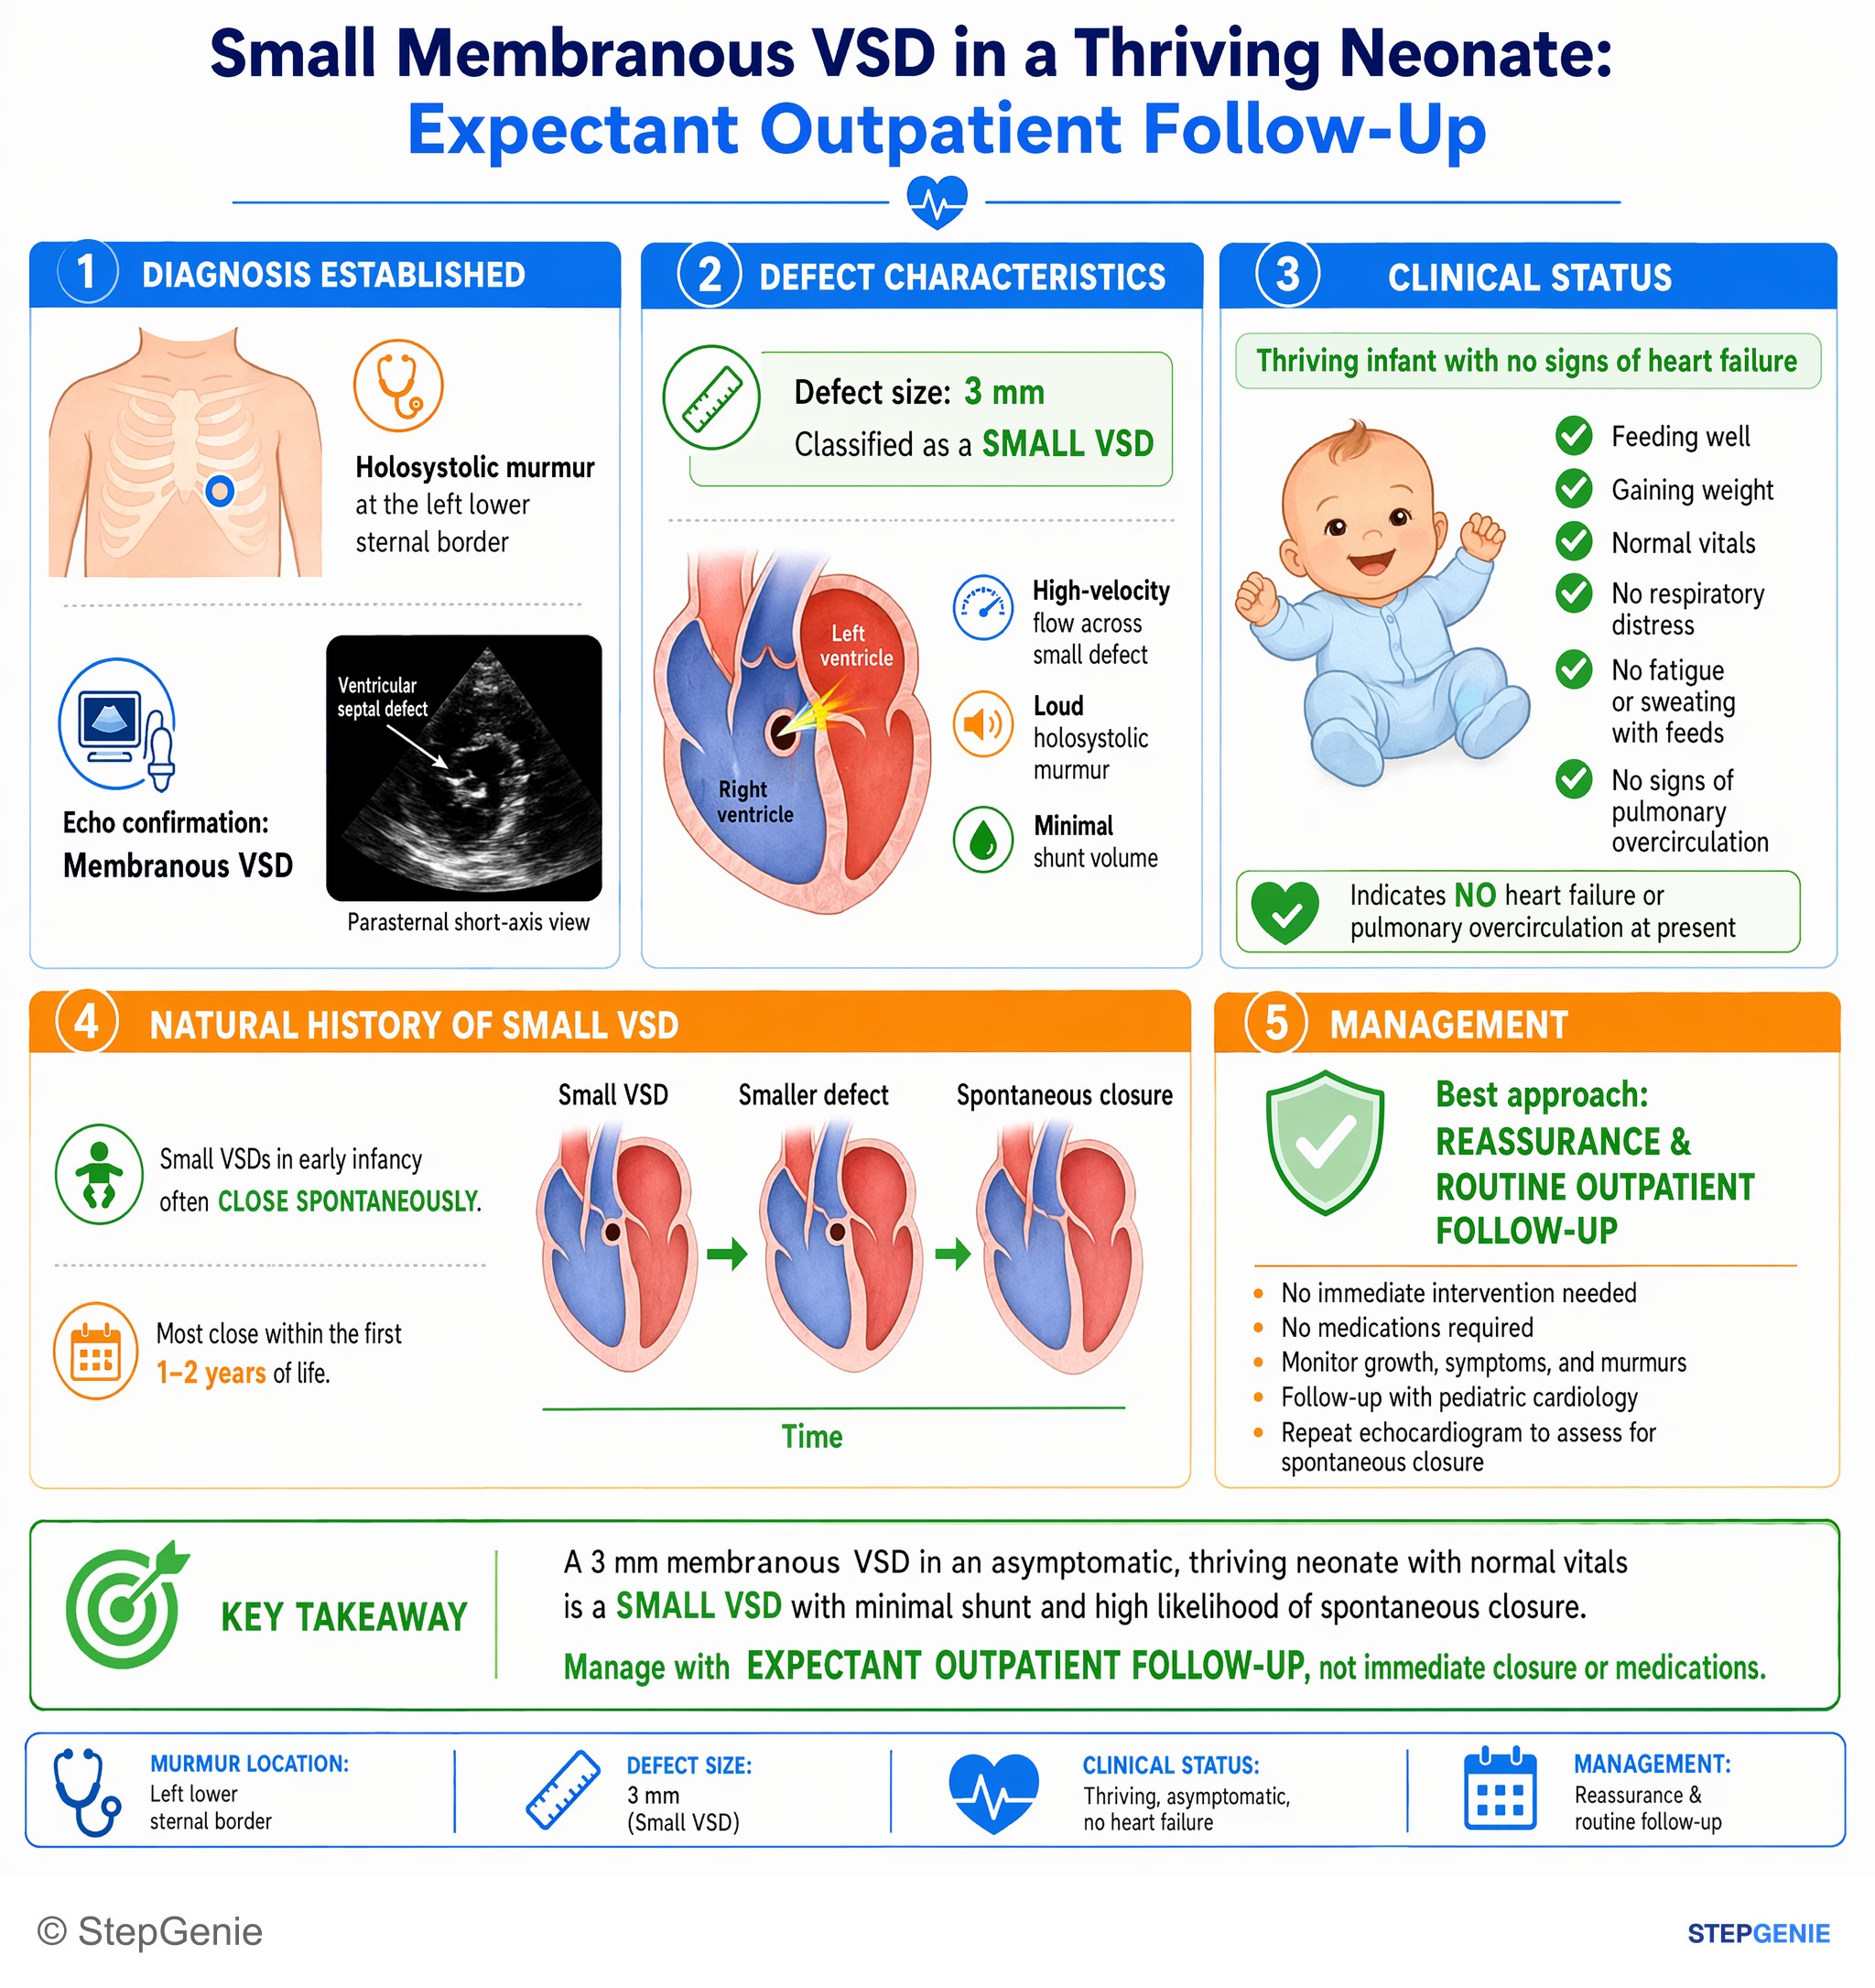
Small membranous VSD in an asymptomatic, thriving neonate with normal vitals is managed with expectant outpatient follow-up, not immediate…
USMLE Step 2Frequently Asked Questions
Why is a small VSD louder than a large VSD?
A small VSD is louder because blood is forced through a restrictive opening, creating high turbulence and a harsh holosystolic murmur. A large VSD can sound softer because pressures between the ventricles begin to equalize, which reduces turbulence. This is why a loud murmur does not necessarily mean more severe disease in VSD.
When do symptoms from a large VSD usually show up after birth?
Symptoms from a large VSD usually appear weeks to months after birth, once pulmonary vascular resistance physiologically falls. At that point, left-to-right shunting increases, causing pulmonary overcirculation and congestive heart failure symptoms. Typical findings include tachypnea, poor feeding, diaphoresis, failure to thrive, and recurrent respiratory infections.
What murmur is classic for VSD, and where is it heard best?
The classic murmur of VSD is a harsh holosystolic murmur best heard at the left lower sternal border. Small or moderate defects may also have a palpable thrill. With a significant left-to-right shunt, a mid-diastolic rumble at the apex can occur from increased flow across the mitral valve, and a loud P2 may appear if pulmonary hypertension develops.
How do you tell VSD from ASD, PDA, and tetralogy of Fallot on exam?
VSD is suggested by a harsh holosystolic murmur at the left lower sternal border, especially when a small defect is loud. ASD classically has a fixed split S2 with a systolic ejection murmur at the left upper sternal border. PDA causes a continuous machine-like murmur near the left infraclavicular area, and tetralogy of Fallot presents with cyanotic spells and a harsh systolic murmur at the left upper sternal border.
What is the best test for VSD, and how is it managed?
Echocardiography is the best test for VSD because it directly visualizes the defect and estimates shunt severity, right ventricular pressure, and pulmonary pressures. Small restrictive VSDs are often observed because many close spontaneously. Symptomatic large VSDs are first stabilized with medical therapy such as diuretics, then definitively closed if symptoms persist, growth is poor, or pulmonary pressures are rising.