Left-sided heart failure backs blood up into the lungs, causing dyspnea, orthopnea, paroxysmal nocturnal dyspnea (PND), crackles, an S3 and pleural effusions. Right-sided heart failure backs blood up into the systemic veins, causing jugular venous distension (JVD), hepatojugular reflux, tender hepatomegaly, ascites and pitting leg edema. The most common cause of right-sided failure is left-sided failure, which raises pulmonary venous pressure and overloads the right ventricle. Right-sided failure caused by lung disease and pulmonary hypertension is cor pulmonale, most often from COPD. Diagnosis rests on BNP or NT-proBNP and a transthoracic echocardiogram, and the 2022 AHA/ACC/HFSA guideline treats HFrEF with four drug classes (an ARNi, or an ACE inhibitor or ARB; an evidence-based beta-blocker; an MRA; and an SGLT2 inhibitor) plus diuretics for congestion.
Left vs right at a glance
| Feature | Left-sided HF | Right-sided HF |
|---|---|---|
| Blood backs up into | Pulmonary veins and capillaries | Systemic veins: neck, liver, gut, legs |
| Pressure that rises | Left atrial pressure and pulmonary capillary wedge pressure (PCWP) | Right atrial (central venous) pressure |
| Key symptoms | Exertional dyspnea, orthopnea, PND, cough or wheeze ("cardiac asthma"), fatigue | Leg swelling, abdominal fullness, right upper quadrant pain, early satiety, anorexia, fatigue |
| Key signs | Basilar crackles, laterally displaced apex, S3 (and S4), pleural effusions | JVD, hepatojugular reflux, tender hepatomegaly, ascites, pitting edema, left parasternal lift |
| Organ pathology | "Heart failure cells": hemosiderin-laden macrophages in alveoli | "Nutmeg liver": centrilobular congestion, which can progress to cardiac cirrhosis |
| Classic causes | Ischemic heart disease or prior MI, hypertension, valve disease, cardiomyopathy | Left-sided HF (the most common cause), lung disease (cor pulmonale), RV infarction, pulmonary hypertension |
Picture it: the failing ventricle cannot empty, so pressure climbs in the chamber and veins behind it. Behind the left ventricle are the lungs; behind the right ventricle is the whole body.
Left-sided failure: why the lungs flood
- Starling forces: when pulmonary capillary pressure exceeds the oncotic pressure of plasma proteins (about 24 mm Hg in Merck's account), fluid moves into the interstitium and then the alveoli, stiffening the lungs and raising the work of breathing. The balance of forces is covered in the Starling forces guide.
- Orthopnea: dyspnea soon after lying flat, relieved promptly by sitting up, because lying down shifts blood from the legs and abdomen into the chest.
- PND: dyspnea that wakes the patient several hours after lying down and eases only after sitting up for 15–20 minutes.
- Acute pulmonary edema: severe dyspnea, diaphoresis, wheezing and sometimes blood-tinged frothy sputum.
- Severe or chronic failure: pleural effusions develop, and faster breathing lowers the PaCO₂ (respiratory alkalosis).
Ejection fraction subtypes (2022 guideline): HFrEF (LVEF 40% or less), HFmrEF (41–49%), HFpEF (50% or more, with evidence of raised filling pressures) and HFimpEF (previously 40% or less, now above 40%). Coronary disease and myocardial infarction are classic causes of HFrEF; high blood pressure is the main cause of HFpEF. Both types congest the lungs. The two are contrasted in the HFrEF vs HFpEF mnemonic.
Right-sided failure and cor pulmonale
Left-sided failure is the most common cause of right-sided failure (per Merck and the NHLBI): high left-sided filling pressures pass back through the lungs, causing pulmonary hypertension that overloads the right ventricle, often worsened by functional tricuspid regurgitation. Isolated right heart failure is much less common. Its causes include:
- Lung disease (cor pulmonale): COPD is the most common cause of chronic cor pulmonale; a massive pulmonary embolism causes acute cor pulmonale.
- Right ventricular infarction: usually with an inferior MI.
- Pulmonary vascular disease: pulmonary arterial hypertension, chronic unresolved pulmonary emboli.
- Valve and congenital disease: tricuspid or pulmonic valve disease, mitral stenosis, Ebstein anomaly and Eisenmenger syndrome.
- Others: arrhythmogenic right ventricular cardiomyopathy, restrictive cardiomyopathy, pericardial disease and obstructive sleep apnea.
Cor pulmonale is right ventricular enlargement and eventual failure caused by pulmonary hypertension from a lung disorder: loss of capillary beds (emphysema, emboli), hypoxic vasoconstriction, raised alveolar pressure and medial hypertrophy of arterioles. Hypoxia-driven polycythemia thickens the blood and adds to the load. By definition it excludes right ventricular enlargement caused by left heart failure, congenital heart disease or acquired valve disease. Signs: a left parasternal lift, a loud P2, murmurs of functional tricuspid and pulmonic regurgitation, and later JVD, hepatomegaly and leg edema.
The liver in right-sided failure (congestive hepatopathy): raised central venous pressure congests the liver, with sinusoidal distention, hepatocyte atrophy and centrizonal fibrosis that can progress to cardiac cirrhosis. Expect modest increases in bilirubin (usually under 3 mg/dL), aminotransferases and PT/INR. Ascites has a serum-ascites albumin gradient of 1.1 g/dL or more with a high ascitic protein (over 2.5 g/dL), whereas cirrhotic ascites has a low protein. The hepatojugular reflux is present, unlike in Budd-Chiari syndrome.
Tests: labs and imaging
| Test | Left-sided HF | Right-sided HF and cor pulmonale |
|---|---|---|
| BNP or NT-proBNP | High; Class 1 in the 2022 guideline to support or exclude HF in a patient with dyspnea | Also raised; supports the diagnosis and tracks response |
| Transthoracic echo (Class 1 at initial evaluation) | LVEF, wall motion, valves, LV hypertrophy, filling pressures | Dilated, hypertrophied RV; septum bowing into the LV (D-shaped LV); RA enlargement; functional tricuspid regurgitation; estimated RV pressure |
| Chest X-ray | Cardiomegaly, upper-lobe vessel prominence (cephalization), Kerley B lines, perihilar "bat-wing" edema, effusions | Enlarged RV and proximal pulmonary arteries with pruned distal vessels |
| ECG | Prior MI, ischemia, LV hypertrophy, atrial fibrillation | Right axis deviation, dominant R waves in V1–V3 (RV hypertrophy) |
| Right heart catheterization | PCWP over 15 mm Hg (post-capillary pulmonary hypertension) | Pre-capillary pattern in cor pulmonale: mean PA pressure over 20 mm Hg, PCWP 15 mm Hg or less, PVR over 2 Wood units |
BNP caveat: a normal BNP does not exclude heart failure, especially in HFpEF or obesity. Merck notes that up to 30% of patients with acute HFpEF have a BNP below the usual 100 pg/mL threshold.
Treatment (consistent with the 2022 AHA/ACC/HFSA guideline)
HFrEF (LVEF 40% or less): four foundational drug classes
| Class | Examples | Key rule |
|---|---|---|
| Renin-angiotensin inhibition | ARNi (sacubitril-valsartan) first line for NYHA class II–III; ACE inhibitor if an ARNi is not feasible; ARB if the ACE inhibitor causes cough or angioedema | Reduces morbidity and mortality |
| Evidence-based beta-blocker | Bisoprolol, carvedilol, sustained-release metoprolol succinate | Start once the patient is stable, not in acute decompensation |
| Mineralocorticoid receptor antagonist | Spironolactone, eplerenone | If eGFR is over 30 mL/min/1.73 m² and potassium is under 5.0 mEq/L |
| SGLT2 inhibitor | Dapagliflozin, empagliflozin | Recommended with or without type 2 diabetes |
- Loop diuretics relieve congestion and improve symptoms in any patient with fluid retention; they are not one of the four mortality-lowering pillars.
- Hydralazine plus isosorbide dinitrate is recommended for self-identified African American patients with NYHA class III–IV HFrEF on optimal therapy.
- Digoxin might be considered to reduce hospitalizations when symptoms persist despite guideline-directed therapy.
- Devices: an ICD for primary prevention when LVEF is 35% or less with NYHA class II–III symptoms on therapy (at least 40 days after an MI); CRT when LVEF is 35% or less with sinus rhythm, left bundle branch block, a QRS of 150 ms or more and NYHA class II to ambulatory IV symptoms on guideline-directed therapy.
HFmrEF and HFpEF: an SGLT2 inhibitor can be beneficial (Class 2a); control blood pressure; use diuretics for congestion; an MRA, ARB or ARNi may be considered in selected patients. Beta-blockers have proven benefit only in reduced EF.
Acute cardiogenic pulmonary edema: oxygen and ventilatory support (noninvasive ventilation such as BiPAP when needed), an IV loop diuretic, nitrates, inotropes for low output, and treatment of the trigger.
Right-sided failure and cor pulmonale:
- Treat the cause. When right-sided failure comes from left-sided failure, guideline-directed therapy for the left side applies.
- Diurese cautiously: the right ventricle depends on preload, so small drops in preload can cause hypotension.
- Cor pulmonale: treat the lung disease and correct hypoxia. Pulmonary arterial hypertension drugs are generally not indicated when the pulmonary hypertension comes from chronic lung disease.
- Right ventricular infarction: hypotension with JVD and clear lungs after an inferior MI. Give IV fluids (1–2 L of normal saline) and avoid nitrates and diuretics, which drop preload and can cause severe hypotension.
Exam traps
- Crackles plus leg edema usually means left-sided failure that has caused right-sided failure, not two separate diseases.
- The PCWP separates them: high in left-sided failure, normal (15 mm Hg or less) in cor pulmonale and pulmonary arterial hypertension.
- Right ventricular enlargement from left heart failure, a shunt or valve disease is not cor pulmonale.
- Kussmaul sign (JVP rising on inspiration) appears in severe right ventricular failure but also in constrictive pericarditis, restrictive cardiomyopathy and severe tricuspid regurgitation.
Practice question
A 66-year-old man with severe COPD and a 60 pack-year smoking history presents with 3 weeks of worsening ankle swelling and right upper quadrant fullness. His resting oxygen saturation is 86% on room air. His jugular venous pressure is elevated, pressing on the liver raises it further, and he has a left parasternal lift, a loud P2 and pitting edema to the knees. The lungs are hyperinflated, with scattered wheezes and no crackles. Echocardiography shows a dilated, hypertrophied right ventricle with a D-shaped left ventricle and an LVEF of 60%. Right heart catheterization shows a mean pulmonary artery pressure of 38 mm Hg and a PCWP of 9 mm Hg. Which of the following best explains his findings?
- A. Cor pulmonale from hypoxic pulmonary vasoconstriction
- B. Heart failure with preserved ejection fraction
- C. Constrictive pericarditis
- D. Cirrhosis with portal hypertension
- E. Right ventricular infarction
Answer: A. Chronic hypoxemia from COPD constricts the pulmonary arterioles, causing pre-capillary pulmonary hypertension (high PA pressure, normal PCWP) that enlarges and then fails the right ventricle. Treat the COPD, correct the hypoxemia with oxygen and use diuretics cautiously for the edema.
Why the others are wrong:
- B: HFpEF is defined by raised left-sided filling pressures, so the PCWP would typically be over 15 mm Hg with pulmonary congestion; it cannot explain pre-capillary pulmonary hypertension with a normal PCWP.
- C: Constrictive pericarditis gives JVD, a Kussmaul sign and a pericardial knock, but catheterization shows roughly equal, raised diastolic pressures in all chambers (including the PCWP) with a normal or only modestly raised pulmonary artery systolic pressure.
- D: Cirrhosis with portal hypertension causes ascites and edema but does not raise the jugular venous pressure, so it cannot explain his raised JVP, loud P2, parasternal lift or hypertrophied right ventricle.
- E: Right ventricular infarction is acute, usually accompanies an inferior MI and presents with hypotension; it does not produce right ventricular hypertrophy.
Key takeaways
- Left-sided failure = lungs (dyspnea, orthopnea, PND, crackles, S3, effusions); right-sided failure = systemic veins (JVD, hepatojugular reflux, hepatomegaly, ascites, edema).
- The most common cause of right-sided failure is left-sided failure; COPD is the most common cause of chronic cor pulmonale.
- Cor pulmonale is right ventricular failure from lung-disease pulmonary hypertension, with a normal PCWP.
- Workup: BNP or NT-proBNP (normal values do not exclude HFpEF, especially with obesity), transthoracic echo, chest X-ray and ECG.
- HFrEF therapy (2022 guideline): ARNi (or ACE inhibitor or ARB), evidence-based beta-blocker, MRA and SGLT2 inhibitor, plus diuretics for congestion.
- Right ventricular infarction: fluids, no nitrates or diuretics.
Sources
- Overview of Heart Failure — Merck Manual Professional Edition
- Right Heart Failure and Cor Pulmonale — Merck Manual Professional Edition
- Chronic Heart Failure — Merck Manual Professional Edition
- Acute Heart Failure — Merck Manual Professional Edition
- 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure: Guideline at a Glance — American Heart Association (2022)
- 2022 AHA/ACC/HFSA Heart Failure Guideline: Key Perspectives — American College of Cardiology (2022)
- Heart Failure: Causes and Risk Factors — NHLBI, NIH
- Congestive Hepatopathy — Merck Manual Professional Edition
- Pulmonary Hypertension — Merck Manual Professional Edition
- Complications of Acute Coronary Syndromes — Merck Manual Professional Edition
- Pulmonary Edema — Merck Manual Professional Edition
- Pulmonary Pathology: Heart Failure Cells — WebPath, University of Utah
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
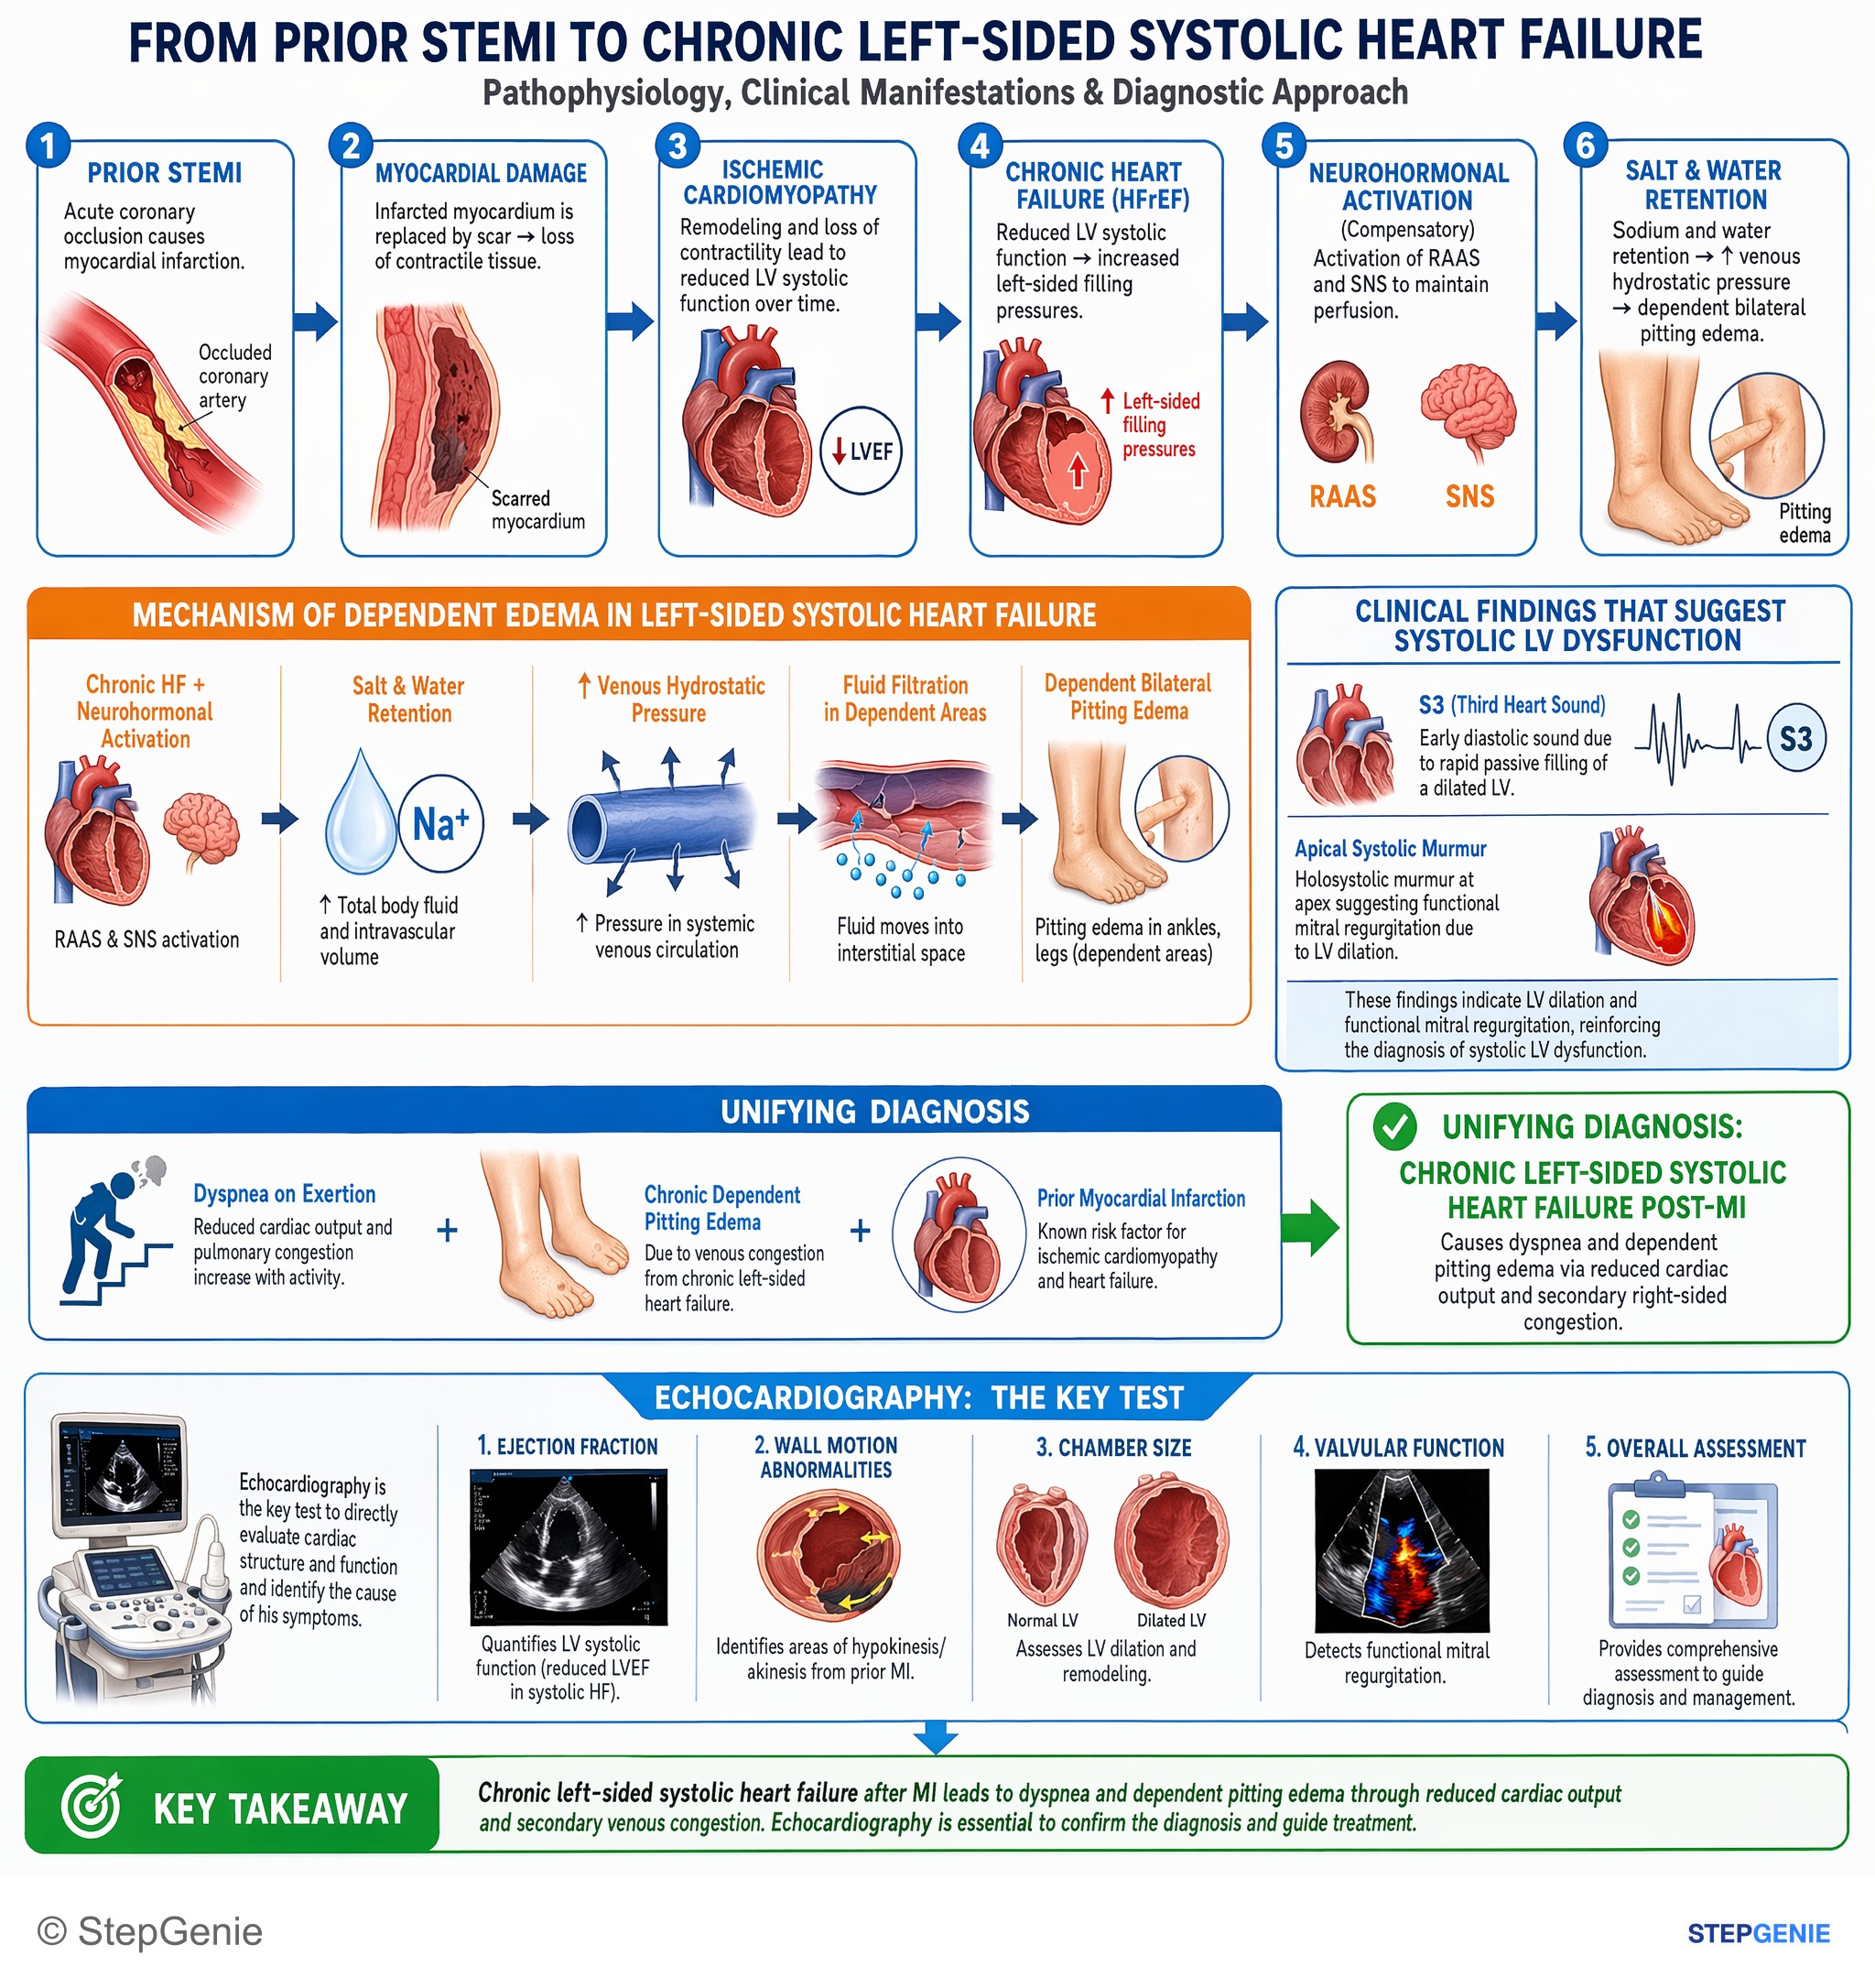
Chronic left-sided systolic heart failure post-MI causes dyspnea and dependent pitting edema via reduced cardiac output and secondary…
USMLE Step 2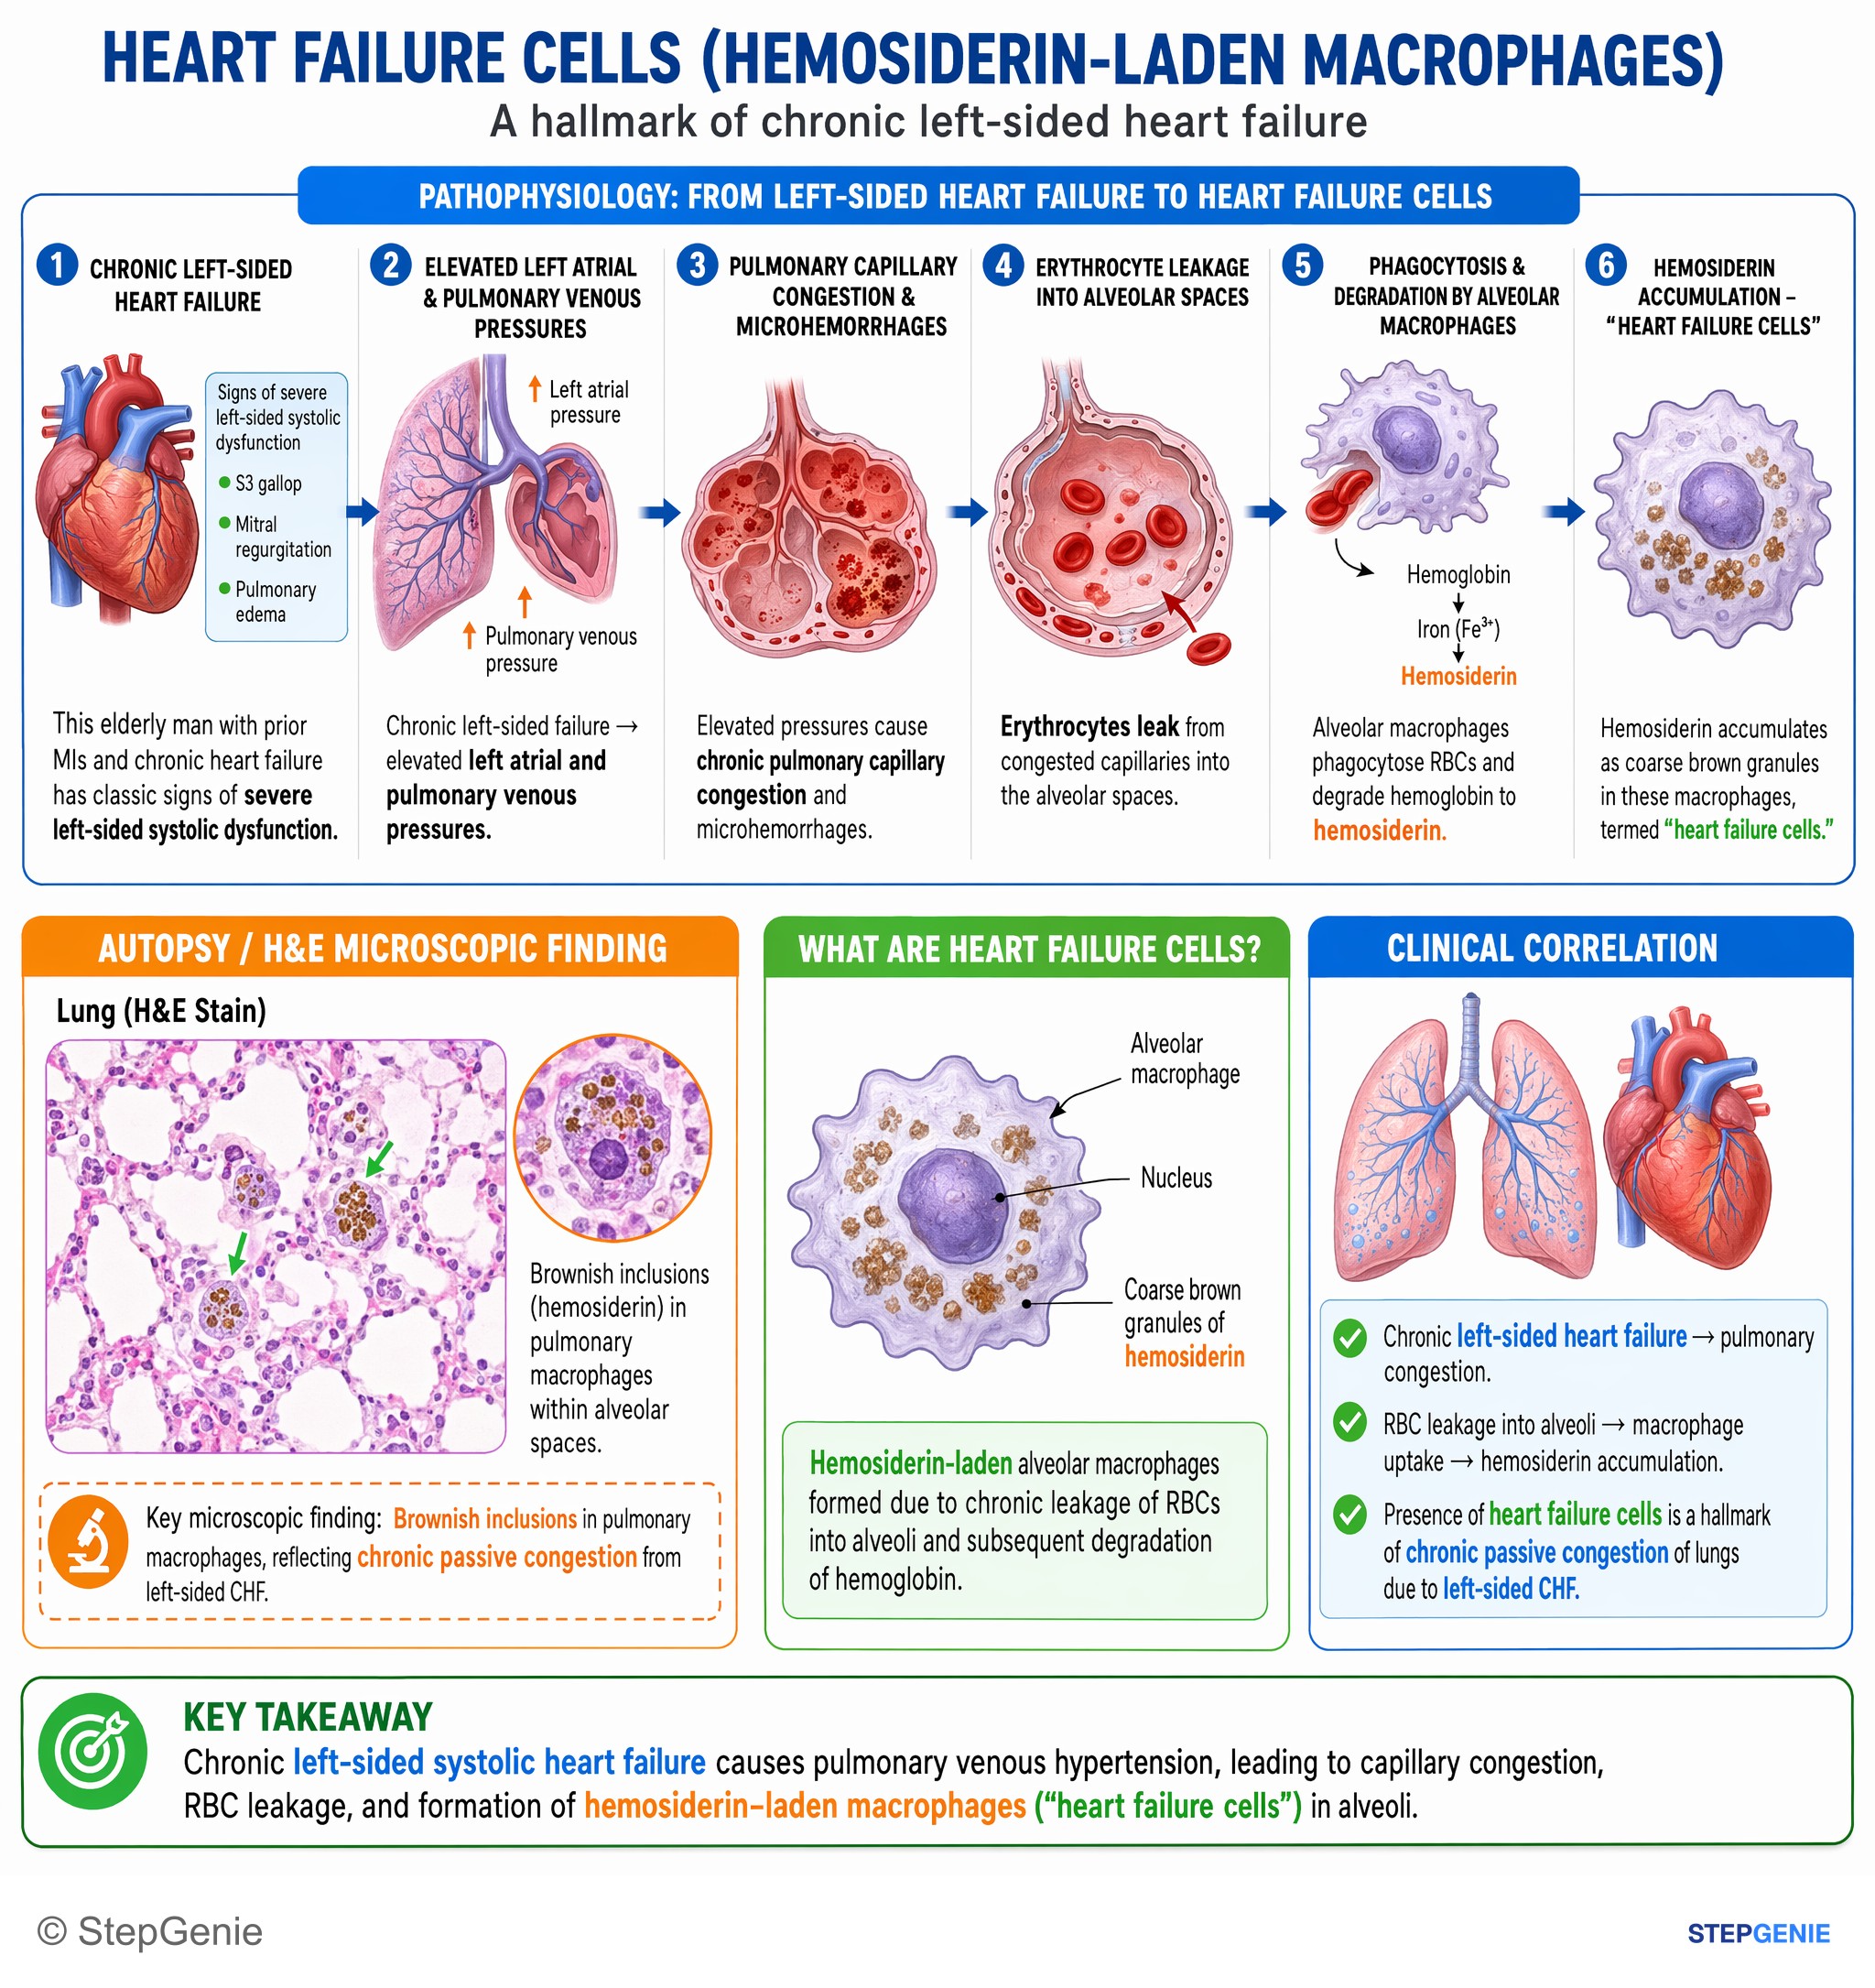
Chronic left-sided heart failure causes pulmonary congestion with heart failure cells (hemosiderin-laden macrophages) containing brown…
USMLE Step 1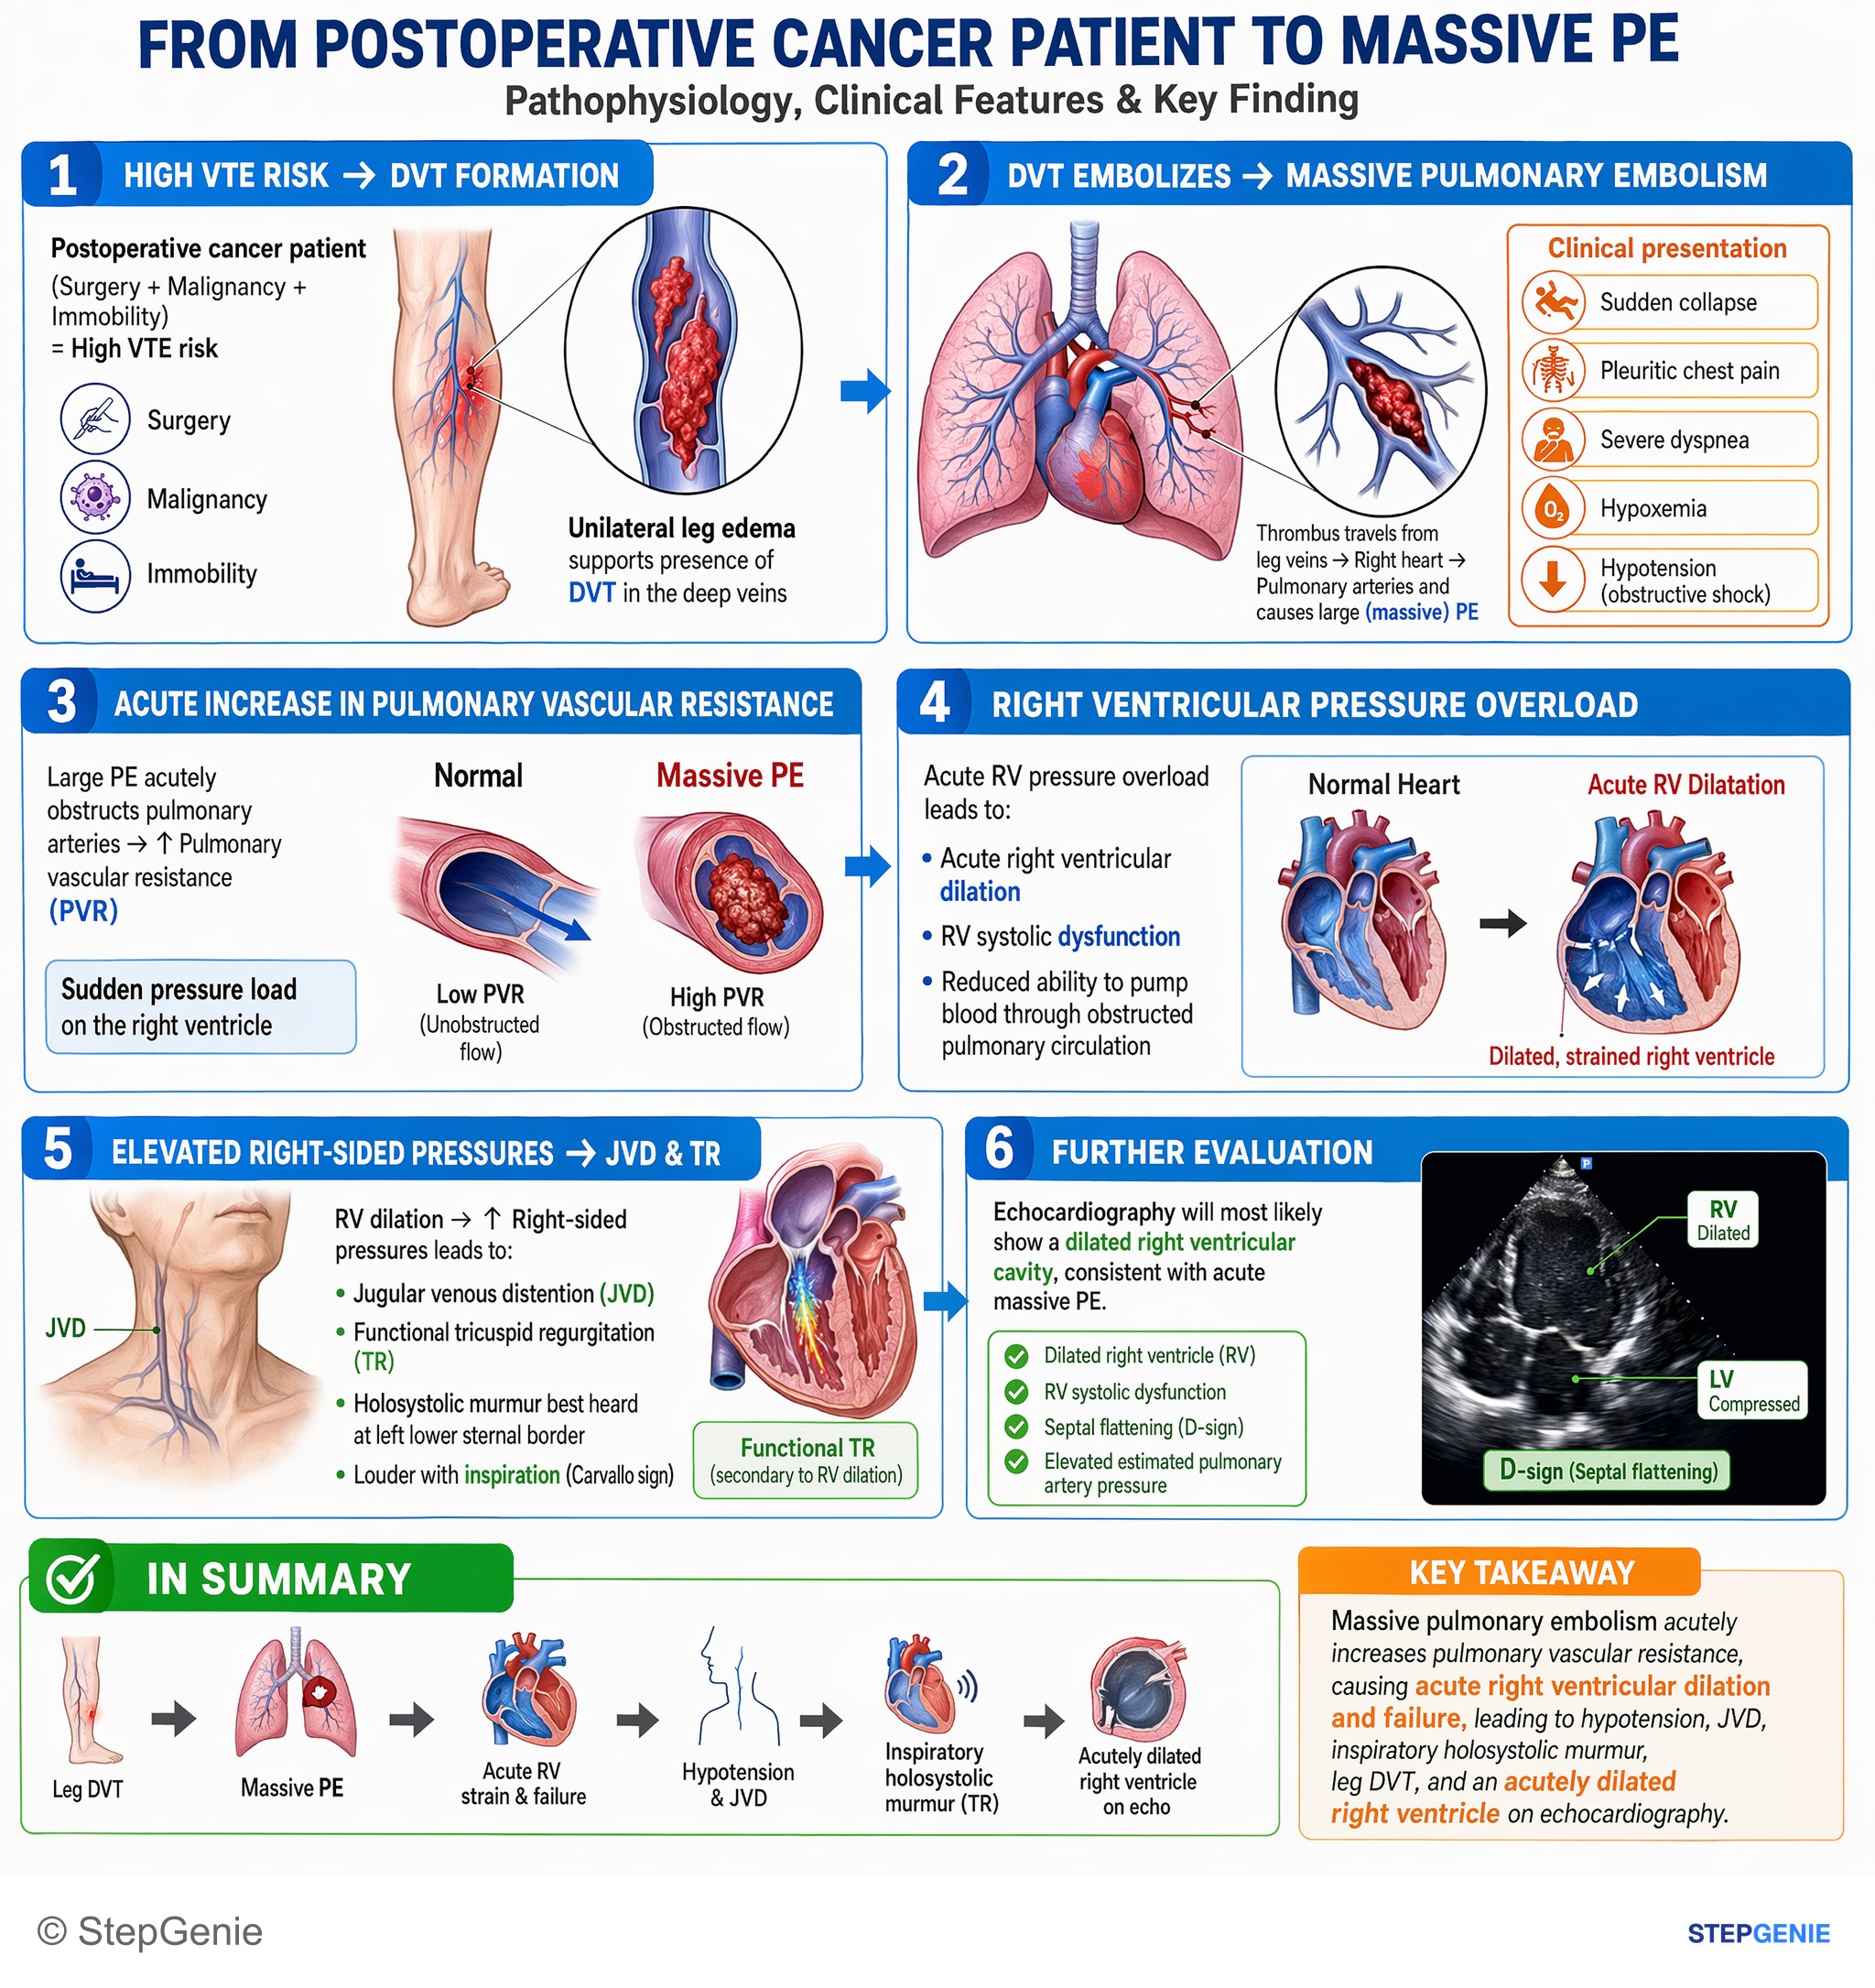
Massive pulmonary embolism → acute right heart strain and failure → hypotension, JVD, inspiratory holosystolic murmur, leg DVT, and…
USMLE Step 2Frequently Asked Questions
What is the difference between left-sided and right-sided heart failure?
Left-sided heart failure backs blood up into the lungs, so patients have exertional dyspnea, orthopnea, paroxysmal nocturnal dyspnea, crackles and sometimes pleural effusions. Right-sided heart failure backs blood up into the systemic veins, causing jugular venous distension, hepatojugular reflux, an enlarged tender liver, ascites and leg edema. Many patients have both, because left-sided failure commonly leads to right-sided failure.
What is the most common cause of right-sided heart failure?
Left-sided heart failure is the most common cause. High left-sided filling pressures are transmitted back through the lungs, producing pulmonary hypertension that overloads the right ventricle. Isolated right-sided failure is less common and comes from lung disease (cor pulmonale), right ventricular infarction, pulmonary arterial hypertension, pulmonary emboli or right-sided valve disease.
What is cor pulmonale?
Cor pulmonale is enlargement and eventual failure of the right ventricle caused by pulmonary hypertension from a lung disorder, most often COPD. Hypoxic vasoconstriction and loss of pulmonary capillary beds raise the load on the right ventricle. By definition it excludes right ventricular failure caused by left heart disease, congenital heart disease or valve disease, and the pulmonary capillary wedge pressure is normal.
Why does left-sided heart failure cause orthopnea and paroxysmal nocturnal dyspnea?
Lying flat shifts blood from the legs and abdomen into the chest, which raises pressure in the pulmonary veins behind a failing left ventricle and pushes fluid into the lungs. Orthopnea comes on soon after lying down and is relieved promptly by sitting up. Paroxysmal nocturnal dyspnea wakes the patient several hours after lying down and eases only after sitting up for 15 to 20 minutes.
Which tests distinguish left-sided from right-sided heart failure?
BNP or NT-proBNP supports a heart failure diagnosis, and a transthoracic echocardiogram shows which ventricle is failing, the ejection fraction and estimated pressures. Right heart catheterization separates them most clearly: the pulmonary capillary wedge pressure is above 15 mm Hg in left-sided failure but 15 mm Hg or less in cor pulmonale. A chest X-ray shows pulmonary edema in left-sided failure.
How is heart failure with reduced ejection fraction treated?
The 2022 AHA/ACC/HFSA guideline recommends four drug classes that reduce morbidity and mortality: an ARNi (or an ACE inhibitor or ARB when an ARNi is not feasible), an evidence-based beta-blocker, a mineralocorticoid receptor antagonist and an SGLT2 inhibitor. Loop diuretics are added to relieve congestion. Selected patients also benefit from hydralazine with isosorbide dinitrate, an ICD or cardiac resynchronization therapy.