Cardiogenic shock is what happens when the heart fails as a pump so badly that tissues can’t get enough perfusion—despite adequate intravascular volume. On Step 1, it’s a classic “cold and wet” shock state tied most commonly to an acute MI, and it’s loaded with testable hemodynamics, murmur clues, and “what pressor/inotrope next?” management decisions.
Where cardiogenic shock fits in shock physiology
Definition (board-style): Shock due to primary cardiac pump failure → ↓ cardiac output → systemic hypoperfusion, typically with ↑ filling pressures.
Key hemodynamic signature
- ↓ Cardiac output (CO)
- ↑ Systemic vascular resistance (SVR) (compensatory vasoconstriction)
- ↑ PCWP (pulmonary capillary wedge pressure) = left-sided filling pressure (pulmonary congestion)
- ↑ CVP/JVP if right-sided involvement (e.g., RV infarct)
Quick comparison table (high-yield)
| Shock type | CO | SVR | PCWP | Skin | Classic clue |
|---|---|---|---|---|---|
| Cardiogenic | ↓ | ↑ | ↑ | Cold, clammy | MI, pulmonary edema |
| Hypovolemic | ↓ | ↑ | ↓ | Cold, clammy | Hemorrhage, dehydration |
| Obstructive (PE, tamponade) | ↓ | ↑ | variable | Cold, clammy | JVP up, clear lungs in PE/tamponade patterns |
| Distributive (septic) | ↑ early / ↓ late | ↓ | ↓ | Warm early | Fever, bounding pulses early |
First Aid cross-reference: Shock hemodynamics table; MI complications; HF pharmacology (inotropes/vasopressors).
Pathophysiology: why the spiral happens
Cardiogenic shock is often a vicious cycle:
- Pump failure (most commonly acute MI) → ↓ stroke volume → ↓ CO
- ↓ MAP triggers sympathetic response:
- ↑ HR
- ↑ contractility (limited reserve)
- ↑ SVR (afterload goes up)
- Afterload increases → the failing LV struggles more → even lower CO
- ↑ LV end-diastolic pressure → ↑ left atrial pressure → pulmonary edema (↑ PCWP)
- Myocardial ischemia worsens (low coronary perfusion, higher wall stress) → further pump failure
- End-organ hypoperfusion → lactic acidosis, AKI, altered mental status
Core concept to remember
Cardiogenic shock = low forward flow + high backward pressure.
- Forward failure: hypotension, cool extremities, organ hypoperfusion
- Backward failure: pulmonary congestion/edema (left), JVP elevation (right)
Etiologies (what Step 1 loves)
#1 cause
- Acute MI (especially large anterior MI from LAD occlusion)
Other high-yield causes
- Mechanical complications post-MI (timing matters; see below)
- Arrhythmias
- Sustained VT/VF
- Complete heart block (inferior MI pattern)
- Acute decompensated heart failure
- Severe valvular disease
- Acute mitral regurgitation (papillary muscle rupture)
- Critical aortic stenosis (older patients)
- Myocarditis (viral, giant cell, etc.)
- Stress (Takotsubo) cardiomyopathy (often mimics MI)
Clinical presentation: “cold and wet” clues
Symptoms
- Dyspnea, orthopnea (pulmonary edema)
- Chest pain (if MI)
- Fatigue, confusion, syncope (low perfusion)
- Oliguria
Signs
- Hypotension (often SBP < 90 or MAP low)
- Cool, clammy extremities (high SVR)
- Tachycardia (compensatory; unless bradyarrhythmia)
- Crackles/rales, frothy sputum (pulmonary edema)
- S3 gallop (volume overload + systolic dysfunction)
- JVP elevation (esp. RV failure or biventricular)
- Narrow pulse pressure (low stroke volume)
Labs and imaging “supporting cast”
- ↑ Lactate (tissue hypoperfusion)
- Metabolic acidosis
- Elevated troponin if ischemic cause
- CXR: pulmonary edema, cardiomegaly
- EKG: STEMI/NSTEMI patterns, conduction blocks, arrhythmias
- Echo: low EF, wall-motion abnormalities, mechanical complications
Diagnosis: what seals it on exams and in real life
Clinical diagnosis: shock + evidence of cardiac dysfunction (and not primarily hypovolemia or distributive).
Hemodynamic criteria (Step-style)
- Low CO/CI (cardiac index often < 2.2 L/min/m²)
- High PCWP (often > 15–18 mmHg)
- High SVR
The must-not-miss: post-MI mechanical complications
These can present with sudden hypotension and new murmurs—high yield.
| Complication | Timing after MI | Key finding | Murmur | Mechanism/artery |
|---|---|---|---|---|
| Papillary muscle rupture | 2–7 days | Acute pulmonary edema, shock | Holosystolic at apex → radiates to axilla (MR) | Posteromedial papillary muscle, RCA/PDA (single blood supply) |
| Ventricular septal rupture | 3–5 days | Shock + pulmonary edema | Harsh holosystolic at LLSB | LAD (anterior septum) |
| Free wall rupture → tamponade | 5–14 days | PEA arrest, JVD, hypotension | Often none; muffled heart sounds | LAD; risk ↑ with transmural MI |
| LV aneurysm | Weeks–months | HF, arrhythmias, thrombus | — | Persistent ST elevation, mural thrombus |
First Aid cross-reference: MI complications + murmurs; tamponade physiology.
Treatment: stabilize first, then fix the cause
Think in two tracks:
- Immediate stabilization (ABCs + perfusion)
- Definitive therapy (revascularize or fix structural problem)
Step 1 algorithm mindset
Cardiogenic shock due to MI → urgent revascularization is the definitive move.
Immediate management (high-yield)
- Oxygen as needed; consider intubation if severe pulmonary edema/respiratory failure
- IV access, continuous monitoring, urine output
- Careful fluids
- Many are “wet,” so fluid boluses can worsen pulmonary edema
- Exception: RV infarct—often preload dependent; gentle fluids can help
Medications: what the exam expects you to choose
1) Norepinephrine (first-line pressor in many cardiogenic shock protocols)
- α1 vasoconstriction ↑ SVR → ↑ MAP
- β1 some inotropy
- Used to maintain perfusion pressure when hypotensive
2) Inotropes (dobutamine, milrinone)
- Dobutamine (β1 > β2): ↑ contractility, can ↓ SVR slightly
- Great for low-output states if BP can tolerate it
- Milrinone (PDE-3 inhibitor): ↑ inotropy + vasodilation
- Can cause hypotension; useful in certain HF patients, including with pulmonary HTN/RV failure contexts
3) Diuretics (e.g., furosemide)
- For pulmonary congestion once perfusion is stabilized
4) Avoid/hold negative inotropes in acute shock
- β-blockers can worsen acute cardiogenic shock (they’re chronic mortality meds, not acute shock meds)
- Many vasodilators (e.g., nitrates) can drop BP in shock
First Aid cross-reference: Autonomics drugs; HF meds (dobutamine, milrinone); shock pressors.
Definitive therapy (what saves the myocardium)
- Acute MI: PCI (or thrombolysis if PCI unavailable and indicated)
- Mechanical complication: emergent surgery (e.g., VSD repair, papillary rupture repair)
- Arrhythmia-driven shock: cardioversion/defibrillation or pacing
Mechanical circulatory support (Step 1/2 concepts)
- Intra-aortic balloon pump (IABP) (classic board concept):
- Inflates in diastole → ↑ coronary perfusion
- Deflates in systole → ↓ afterload
- Other devices exist (Impella, VA-ECMO), but IABP remains the “teachable” one.
Special scenario: Right ventricular infarct (testable twist)
Clues
- Inferior MI (II, III, aVF) + JVP up, clear lungs, hypotension
- Often RCA infarct affecting RV
Management difference
- RV is preload dependent → give IV fluids cautiously to optimize preload
- Avoid nitrates/diuretics initially if they tank preload and worsen hypotension
High-yield associations & “exam traps”
1) Hemodynamics are not optional
If you see shock + pulmonary edema, think:
- PCWP high (backward congestion)
- SVR high (compensation)
- CO low (primary problem)
2) New murmur after MI = mechanical complication until proven otherwise
- MR murmur (apex holosystolic) → papillary muscle rupture
- VSD murmur (LLSB harsh holosystolic) → septal rupture
Both can produce rapid cardiogenic shock.
3) “Cold and clammy” is a catecholamine clue
Cardiogenic shock looks like hypovolemic shock on the skin exam (both high SVR), but cardiogenic has congestion (high PCWP, pulmonary edema).
4) Don’t reflexively give big fluid boluses
Unless RV infarct or clear evidence of hypovolemia, aggressive fluids worsen pulmonary edema.
Rapid review (what to memorize)
Cardiogenic shock
- Cause: pump failure (most often MI)
- Findings: hypotension, cool/clammy, pulmonary edema, ↑ JVP (sometimes), S3
- Hemodynamics: ↓ CO, ↑ SVR, ↑ PCWP
- Dx tools: EKG, troponin, echo, CXR, lactate
- Tx: stabilize (pressors/inotropes, oxygen/ventilation), urgent revascularization for MI, fix mechanical complications, consider IABP
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
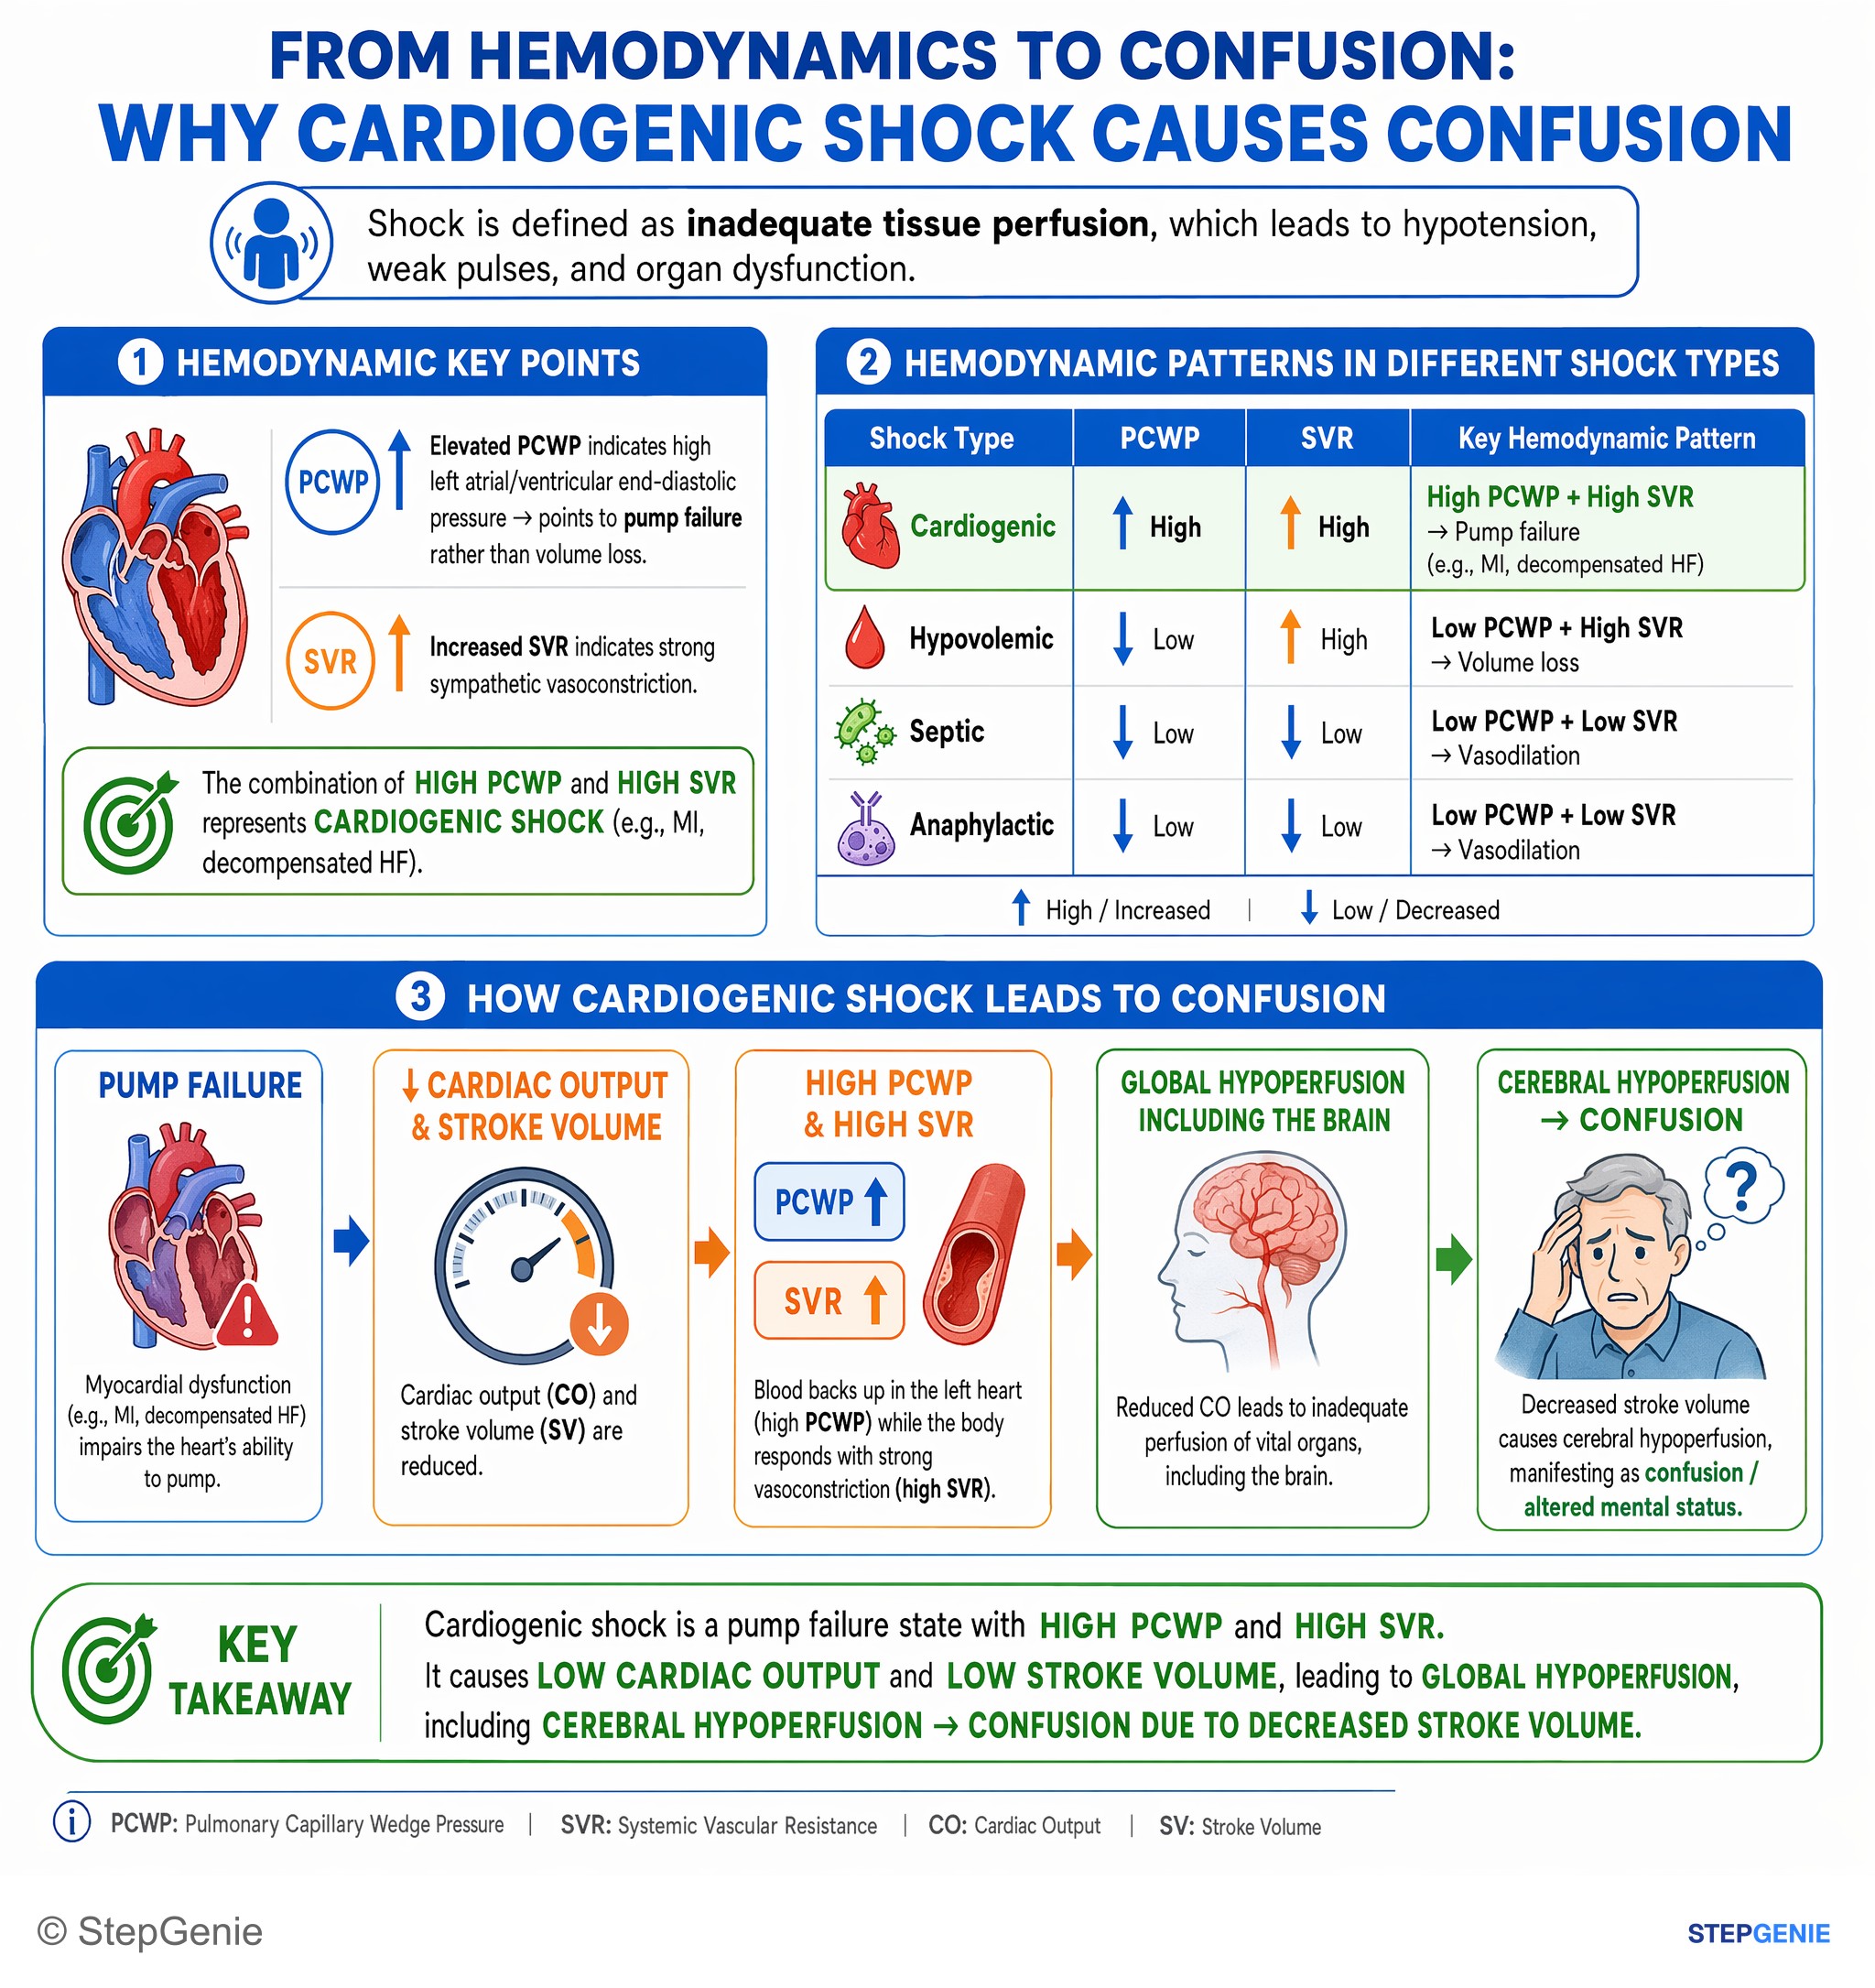
Cardiogenic shock causes low cardiac output with high PCWP and high SVR, leading to cerebral hypoperfusion and confusion from decreased…
USMLE Step 1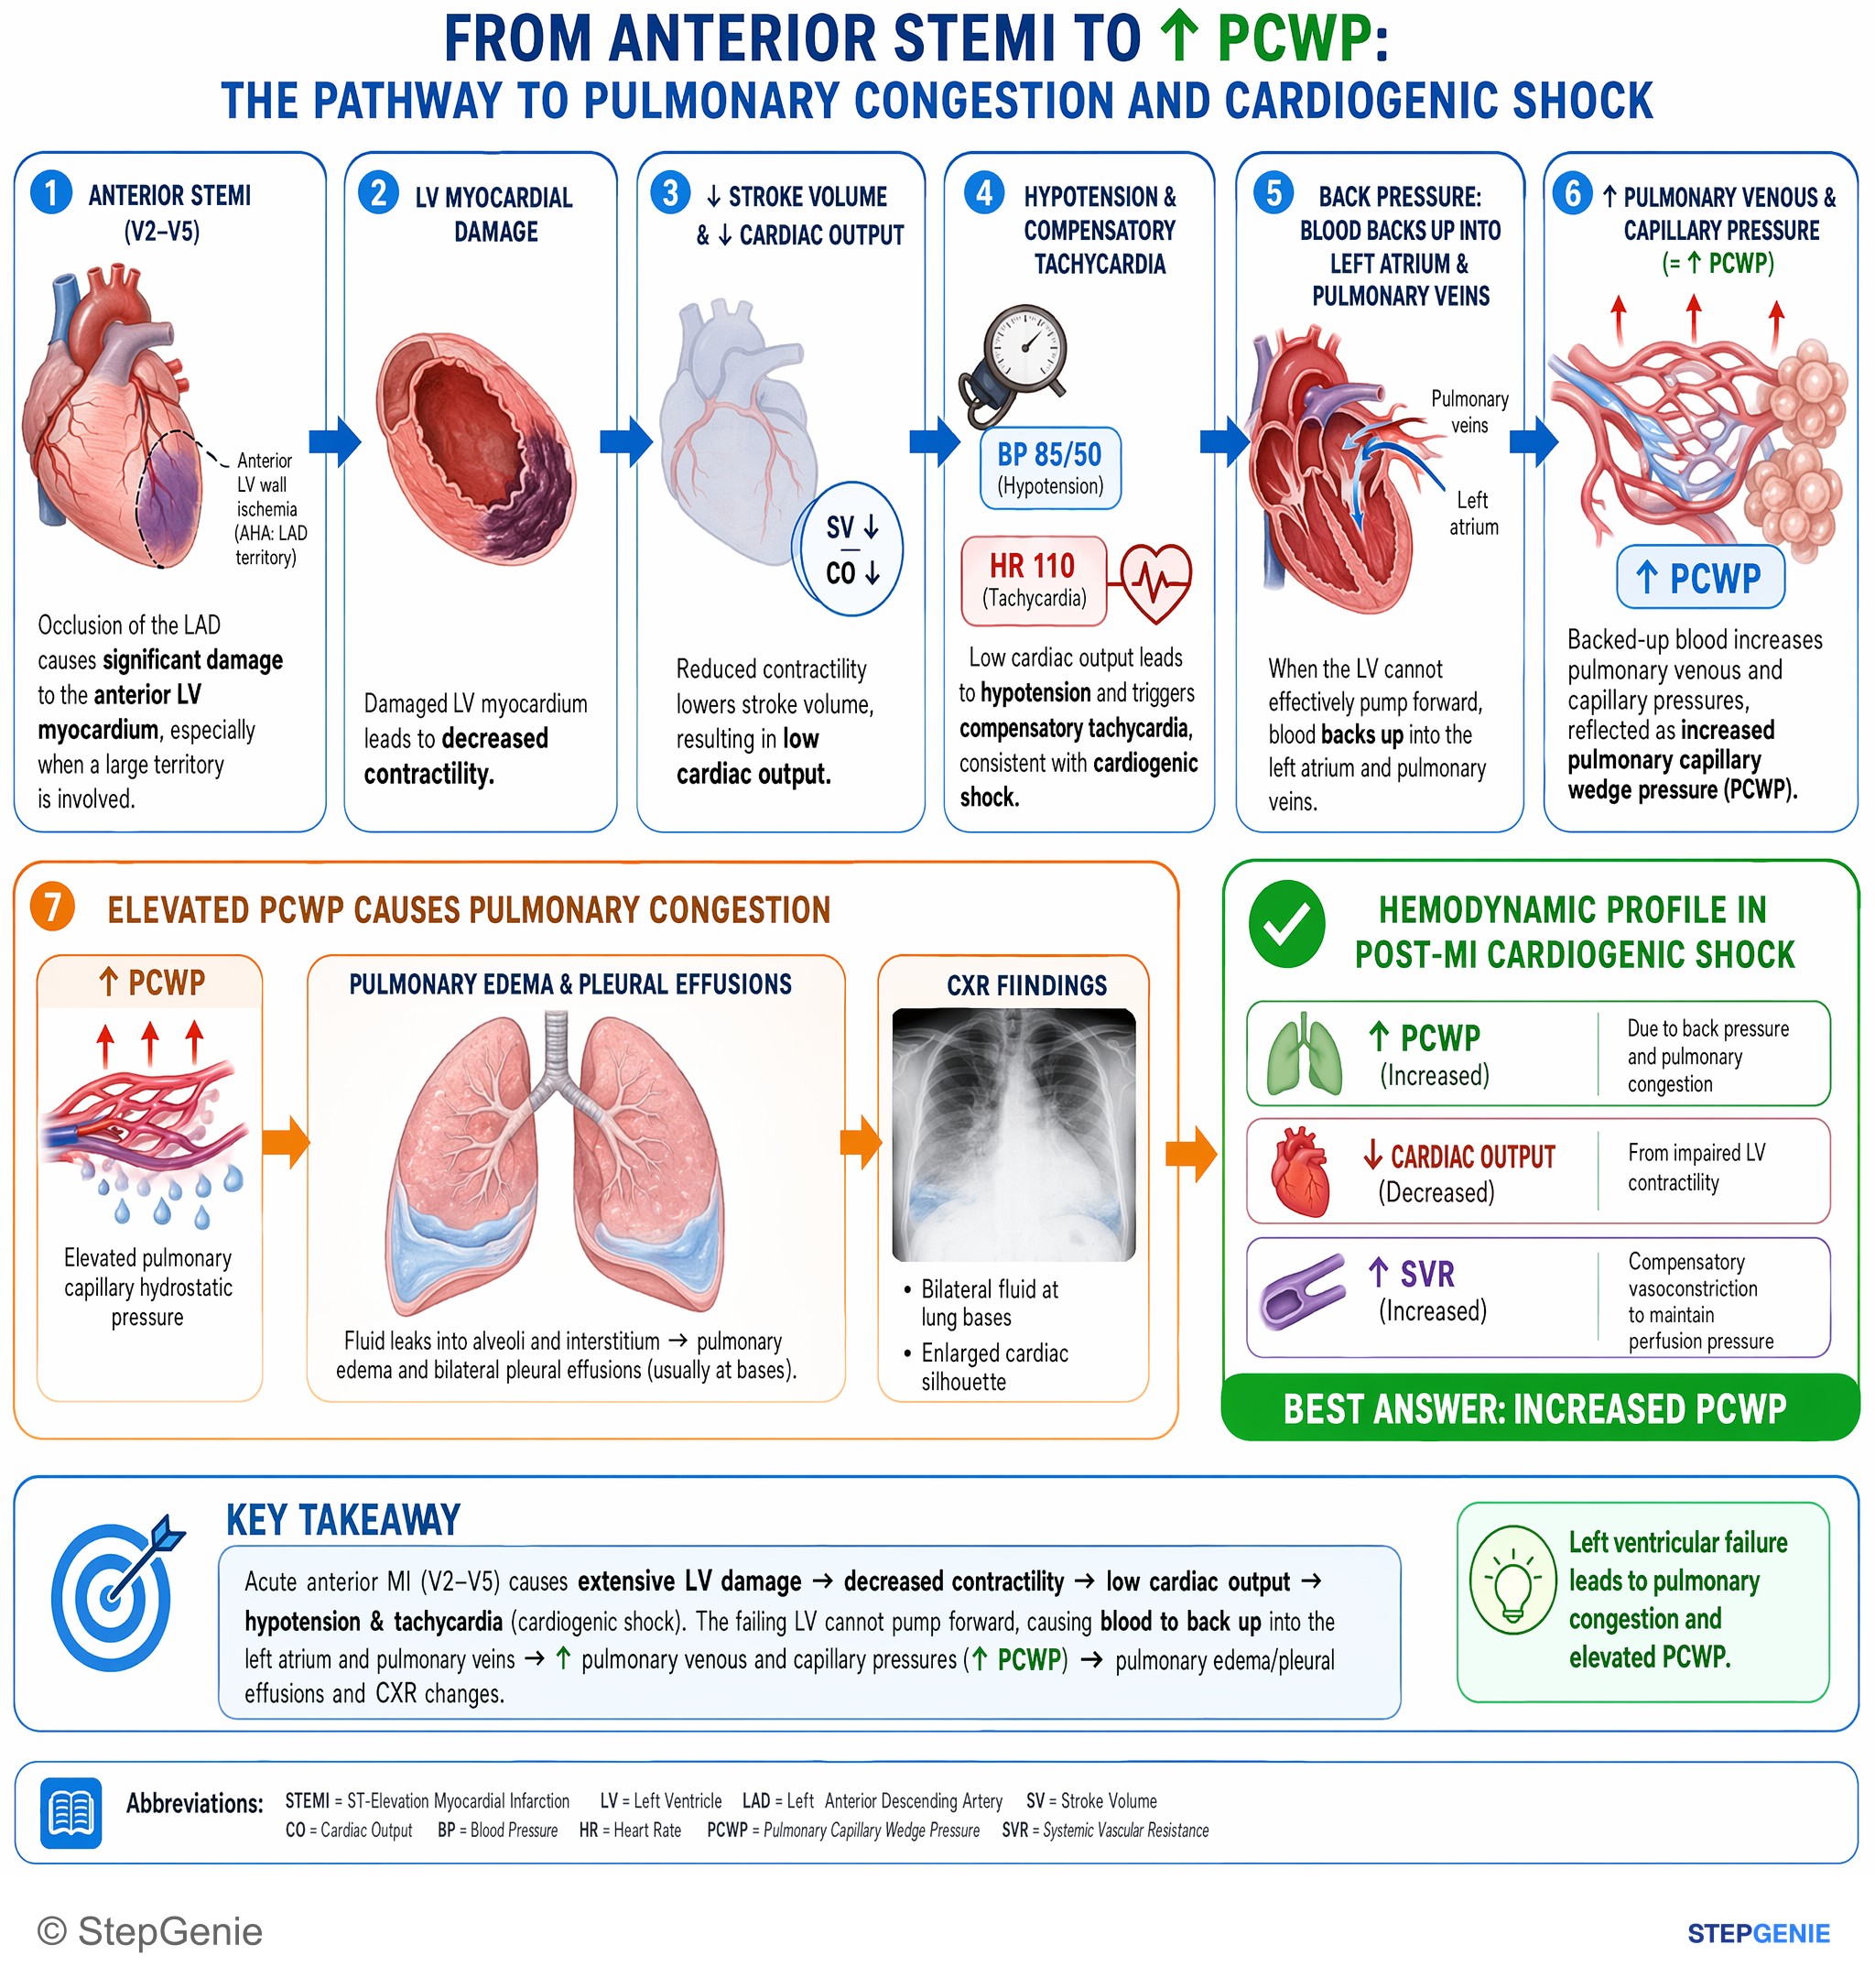
Acute anterior MI with cardiogenic shock → left ventricular failure → blood backs into lungs → elevated pulmonary capillary wedge pressure…
USMLE Step 1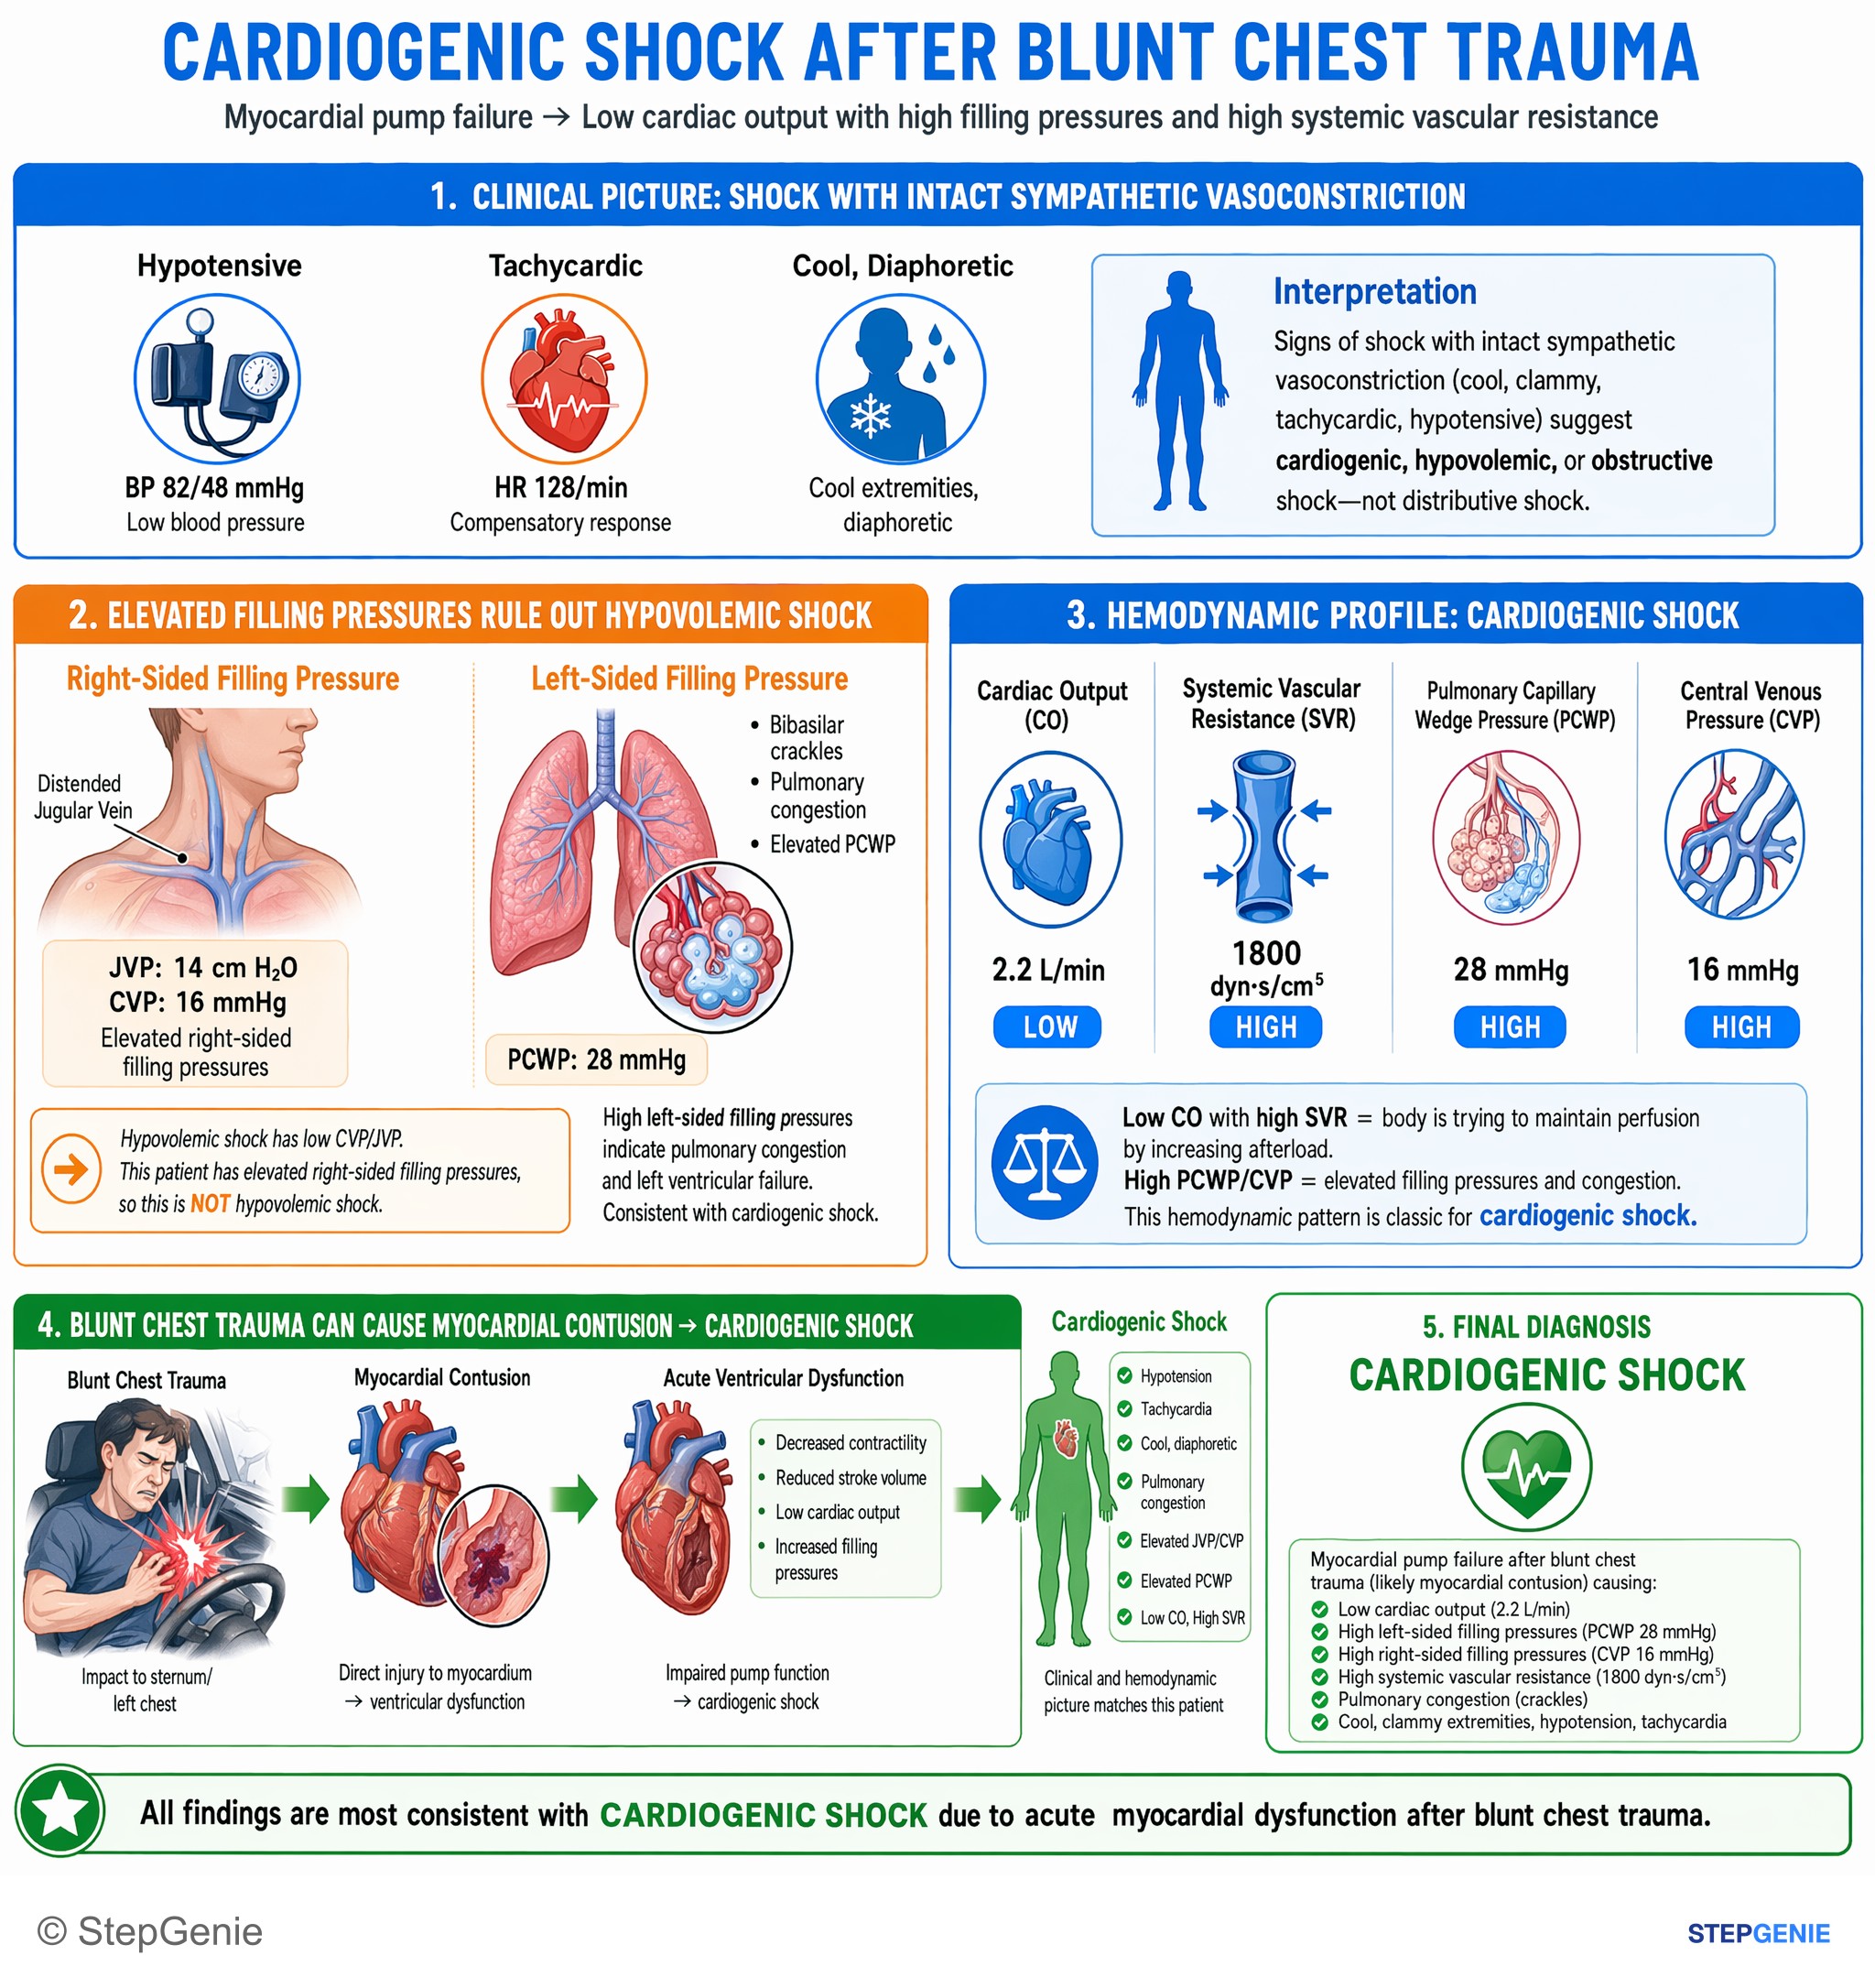
Cardiogenic shock: myocardial pump failure after blunt chest trauma → low CO, high PCWP, high SVR, cool/clammy extremities, pulmonary…
USMLE Step 2Frequently Asked Questions
What are the classic hemodynamics of cardiogenic shock?
Cardiogenic shock classically shows low cardiac output, high systemic vascular resistance, and high filling pressures. The failing heart cannot generate enough forward flow, so cardiac output drops. The body compensates with vasoconstriction, which raises SVR, while left-sided pump failure raises LV end-diastolic and left atrial pressures, increasing PCWP and causing pulmonary congestion. CVP or JVP can also rise if there is right-sided involvement.
Why does cardiogenic shock cause pulmonary edema and cool, clammy skin?
Cardiogenic shock causes pulmonary edema because left-sided pump failure raises left ventricular end-diastolic pressure, then left atrial pressure, which increases pulmonary capillary wedge pressure. It causes cool, clammy skin because low mean arterial pressure triggers a sympathetic response with vasoconstriction, raising SVR. That combination produces the classic board-style picture of low forward flow with high backward pressure, or “cold and wet.”
How do you tell cardiogenic shock from hypovolemic or septic shock on exam questions?
Cardiogenic shock is suggested by a cold, clammy patient with low cardiac output and elevated PCWP, often with pulmonary edema or an MI clue. Hypovolemic shock also has low cardiac output and high SVR, but PCWP is low. Septic shock is different because it is warm early, with low SVR and low PCWP. Pulmonary edema, crackles, and evidence of cardiac dysfunction point toward cardiogenic shock.
What is the most common cause of cardiogenic shock, and what findings go with it?
The most common cause of cardiogenic shock is acute MI, especially a large anterior MI from LAD occlusion. Typical accompanying findings include chest pain, hypotension, dyspnea, crackles from pulmonary edema, cool extremities, tachycardia, elevated lactate, and elevated troponin if the cause is ischemic. EKG may show STEMI or NSTEMI patterns, and echocardiography can show low ejection fraction or wall-motion abnormalities.
What is the first-line treatment approach for cardiogenic shock from MI?
The key treatment approach is immediate stabilization followed by urgent revascularization, which is the definitive therapy for cardiogenic shock due to MI. Initial management includes oxygen as needed, continuous monitoring, IV access, and cautious use of fluids because many patients are already volume overloaded. Norepinephrine is a first-line pressor in many protocols when hypotension threatens perfusion, and inotropes such as dobutamine or milrinone can be used to support contractility.