Dilated cardiomyopathy (DCM) is one of those “looks scary, but tests predictably” topics: the ventricle gets big and weak, blood backs up, and the patient shows up with classic systolic heart failure. If you can visualize the anatomy, you can usually predict the murmurs, complications, and next best step on USMLE-style questions.
The Visual Hack (draw this in 5 seconds)
Picture a floppy balloon that’s been overstretched.
- The balloon = left ventricle
- It’s dilated (big chamber)
- The wall is thin/weak → it can’t squeeze well
One-liner: DCM = dilated, weak ventricle → ↓EF (HFrEF) + congestion + functional MR/TR.
“4 D’s” Micro-Mnemonic
Dilated ventricle
Decreased contractility
Decreased ejection fraction
Decompensated heart failure (pulmonary + systemic congestion)
What’s Actually Happening (Pathophys you can use on exams)
In DCM, the main problem is impaired systolic function.
- ↓ Contractility → ↓ Stroke volume
- Body compensates with:
- SNS activation (tachycardia, vasoconstriction)
- RAAS activation (fluid retention, remodeling)
- Net result: HFrEF with volume overload
Hemodynamics (high-yield)
- Ejection fraction: low (often < 40%)
- End-systolic volume (ESV): increased
- End-diastolic volume (EDV): increased
- Laplace law: wall stress rises as radius rises
Bigger radius () → more wall stress → worse pump function (vicious cycle).
Etiologies: The Board-Favorite Causes (think “DCM = toxins, time, infection, pregnancy”)
High-yield causes and associations
- Alcohol (most classic toxin)
- Doxorubicin (anthracyclines) → cardiomyopathy (free radical injury)
- Coxsackie B viral myocarditis → can progress to DCM
- Chagas disease (T. cruzi) → DCM + arrhythmias (LatAm hx)
- Peripartum cardiomyopathy (late pregnancy to postpartum)
- Hemochromatosis (iron overload; often included with DCM/restrictive overlap in questions)
- Thiamine deficiency (wet beriberi) → high-output HF that can look DCM-like
- Familial/genetic (often titin mutations)
“Toxic Timebomb” mini-list (fast recall)
- Ethanol
- Doxorubicin
- Cocaine/amphetamines (ischemia, myocarditis risk)
Key Findings: Symptoms, Exam, and “What murmur is this?”
DCM presents like congestive heart failure.
Symptoms
- Dyspnea on exertion, orthopnea, PND
- Fatigue, exercise intolerance
- Peripheral edema, abdominal distension (R-sided congestion can develop)
Physical exam
- S3 gallop (classic for volume overload in systolic HF)
- JVD, crackles, pitting edema, hepatomegaly
Murmurs you can predict from the anatomy
As the ventricle dilates, it stretches the valve annuli:
- Functional mitral regurgitation (MR)
- Holosystolic murmur at apex → radiates to axilla
- Functional tricuspid regurgitation (TR) (esp with RV dilation/pulm HTN)
- Holosystolic at LLSB, increases with inspiration
Quick logic: Big ventricle → stretched ring → leaky valve.
Echo/EKG/Imaging: What USMLE wants you to say
Echocardiogram (most important)
- Dilated LV (often all chambers can dilate)
- ↓ EF
- Global hypokinesis (not regional, unless ischemic cardiomyopathy)
- Possible mural thrombus (stasis in a big, weak chamber)
Chest X-ray
- Cardiomegaly
- Pulmonary edema/pleural effusions if congested
EKG (nonspecific but testable complications)
- Atrial fibrillation/flutter
- Ventricular arrhythmias
- Conduction delays (e.g., LBBB)
Big Complications (favorite NBME twists)
- Arrhythmias → sudden cardiac death risk
- Mural thrombus → embolic stroke (esp with severe LV dysfunction)
- Progressive HF → cardiogenic shock in severe decompensation
Exam clue: patient with DCM + neuro deficit = think cardioembolic stroke from LV thrombus or atrial fibrillation.
DCM vs HCM vs Restrictive (fast differentiator table)
| Feature | Dilated CM (DCM) | Hypertrophic CM (HCM) | Restrictive CM |
|---|---|---|---|
| Main dysfunction | Systolic | Diastolic (impaired filling) | Diastolic (stiff ventricle) |
| EF | ↓ | Normal/↑ | Usually normal |
| Chamber size | Dilated | Small LV cavity | Normal/small |
| Classic sound | S3 | S4; harsh systolic murmur (outflow) | S4 common |
| Common causes | Alcohol, doxo, viral, Chagas, peripartum | AD sarcomere mutations | Amyloid, sarcoid, hemochromatosis, endocardial fibrosis |
Treatment (Step-friendly framework)
Chronic HFrEF basics (core concept)
- Decrease preload: diuretics (symptom relief)
- Decrease afterload + remodeling: ACEi/ARB/ARNI
- Neurohormonal blockade: evidence-based beta blockers (metoprolol succinate, carvedilol, bisoprolol)
- Add-ons: MRA (spironolactone/eplerenone), SGLT2 inhibitors
Device therapy (common test point)
- ICD for primary prevention in severe HFrEF (low EF despite optimal medical therapy)
- CRT if wide QRS (e.g., LBBB) with persistent symptoms
Treat the cause when possible
- Stop alcohol/cardiotoxins
- Manage hemochromatosis (phlebotomy/chelation)
- Chagas-specific therapy when appropriate + HF management
Ultra-High-Yield “If you remember nothing else…”
- DCM = HFrEF: big weak heart, low EF, S3
- Most common murmur = functional MR from annular dilation
- Classic causes: alcohol, doxorubicin, viral myocarditis (Coxsackie B), Chagas, peripartum
- Complications: arrhythmias + mural thrombus → embolic events
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
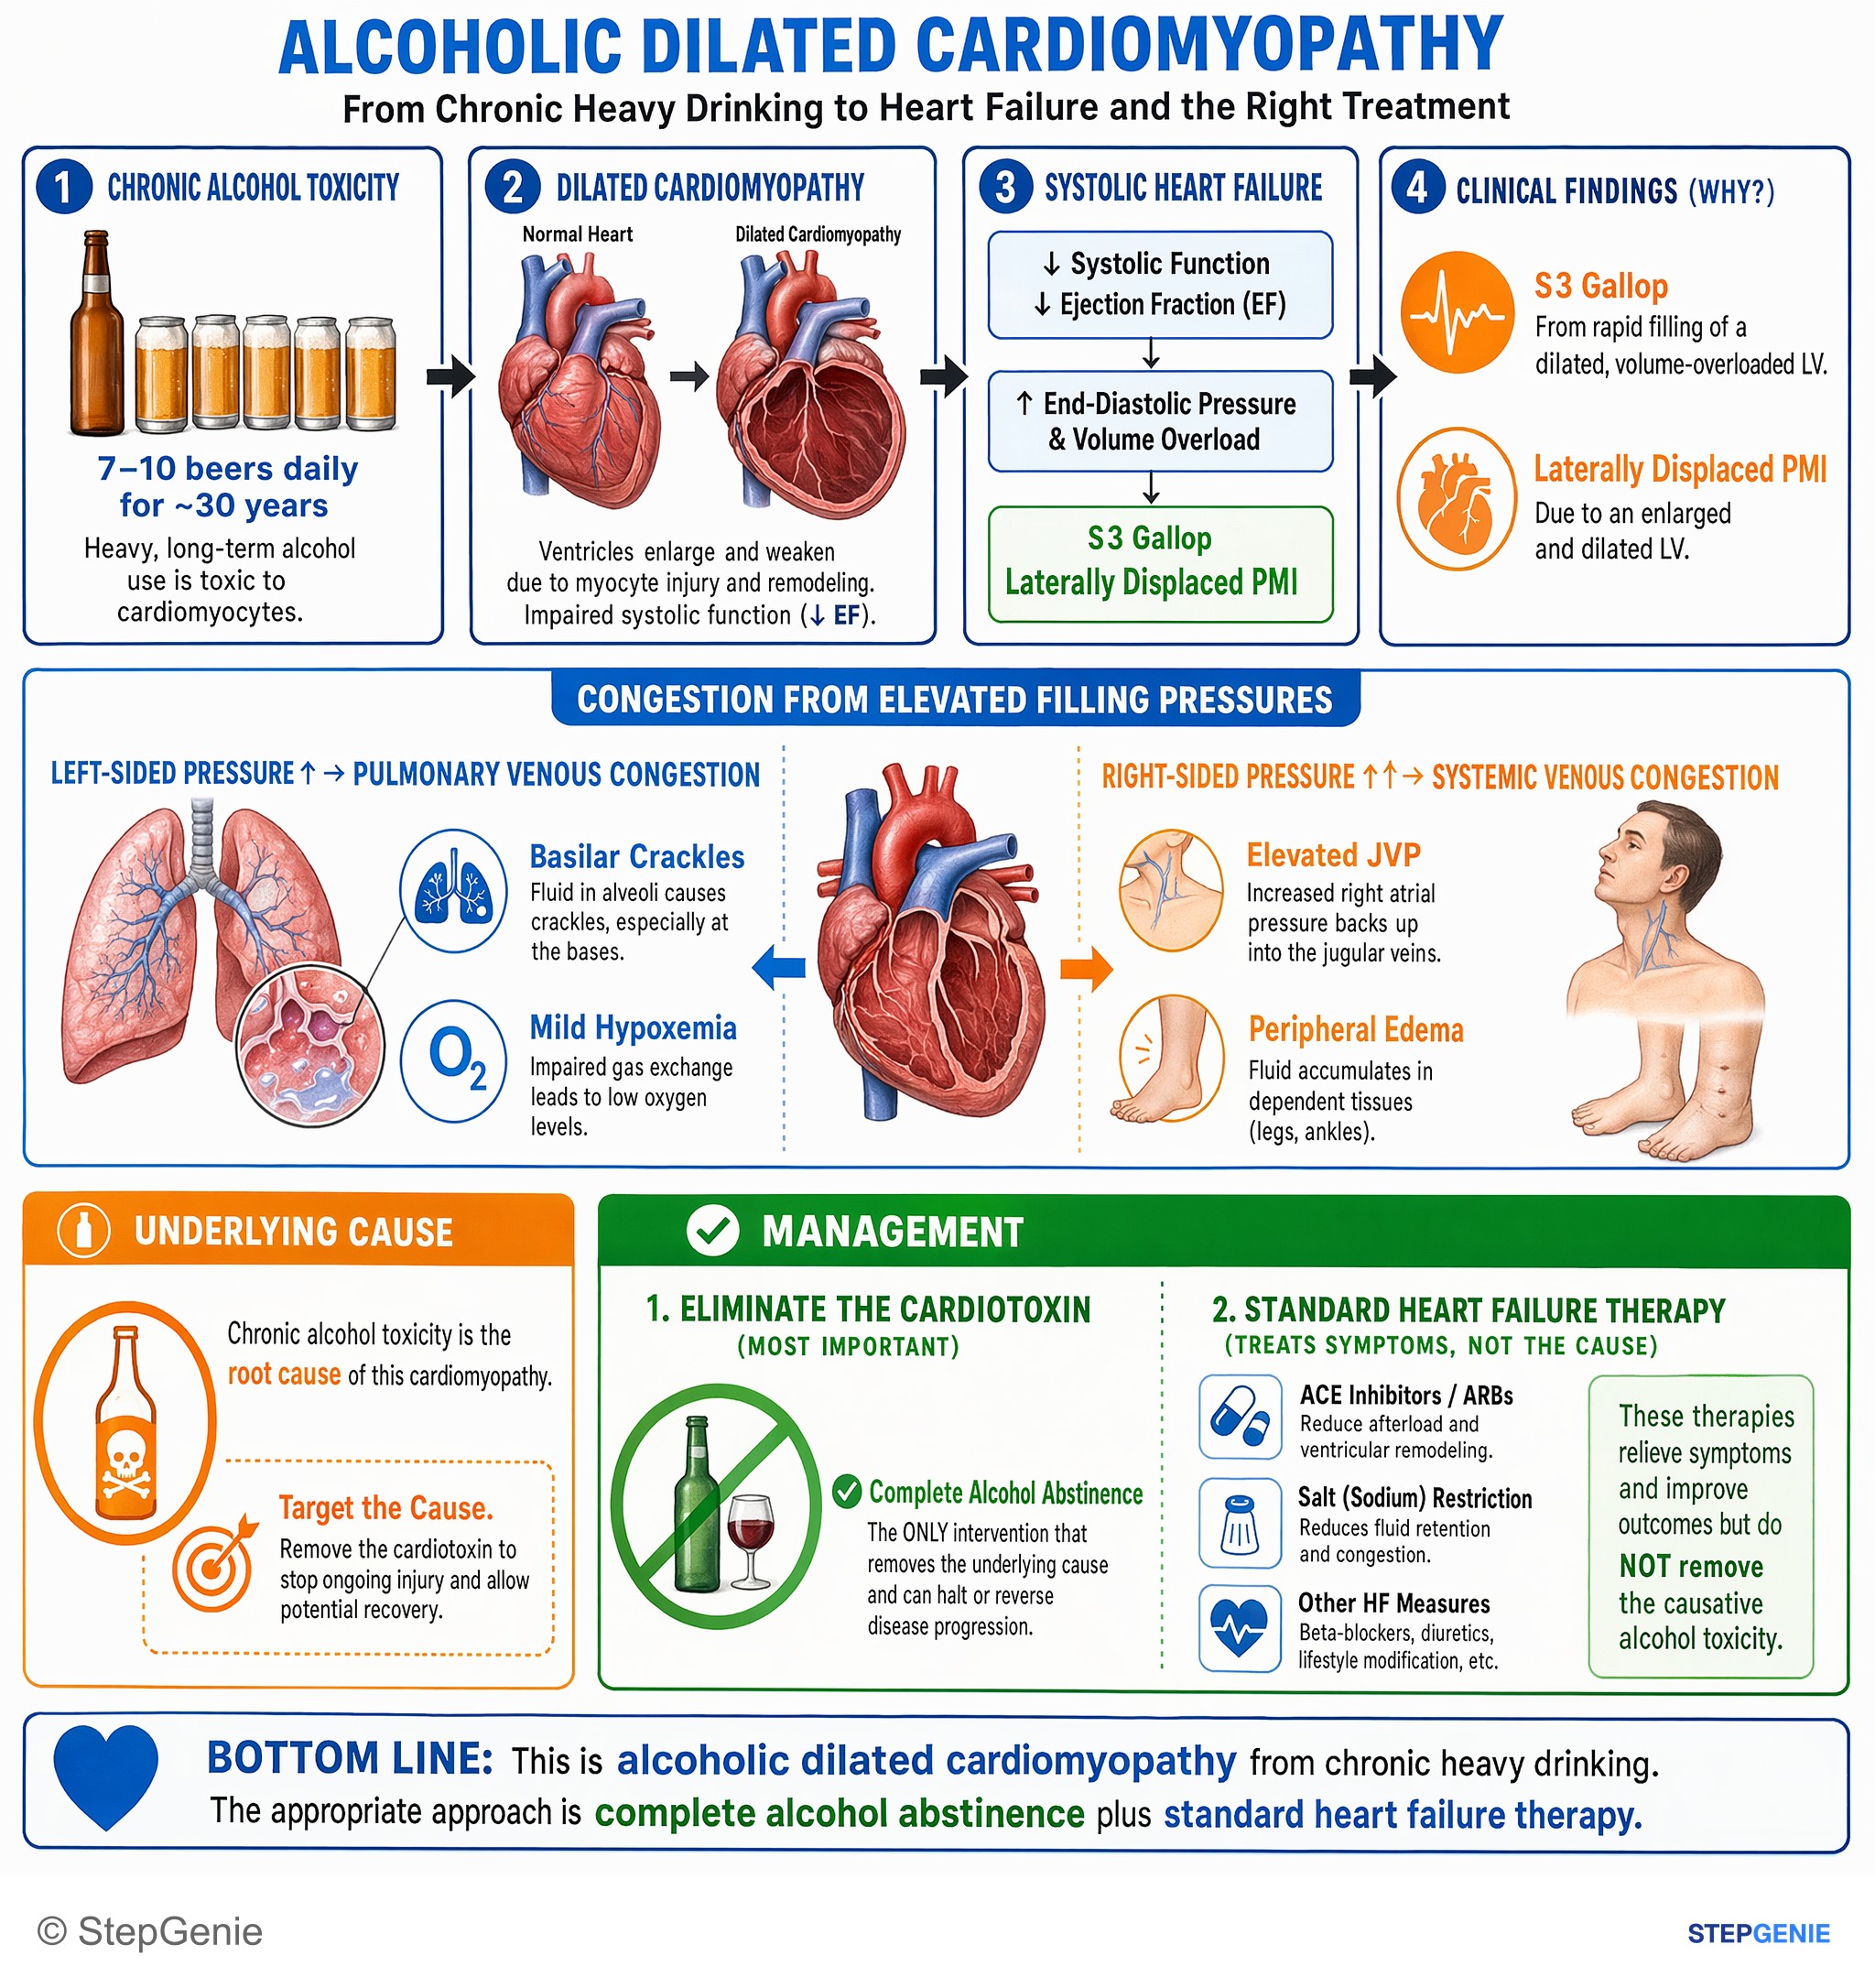
Alcoholic dilated cardiomyopathy from chronic heavy drinking; treat underlying cause with complete alcohol abstinence plus standard heart…
USMLE Step 2Frequently Asked Questions
Why does dilated cardiomyopathy cause a low ejection fraction and congestive heart failure?
Dilated cardiomyopathy causes a low ejection fraction because the ventricle becomes enlarged and weak, so it cannot contract effectively. Decreased contractility lowers stroke volume, and the body responds with sympathetic activation and RAAS activation, which increase fluid retention and remodeling. The net result is systolic heart failure with volume overload, pulmonary congestion, and systemic congestion.
Why do patients with dilated cardiomyopathy get mitral or tricuspid regurgitation murmurs?
Patients with dilated cardiomyopathy develop functional mitral or tricuspid regurgitation because the enlarged ventricle stretches the valve annuli. That annular dilation prevents the valves from closing tightly, creating leaky valves. This produces a holosystolic murmur, classically mitral regurgitation at the apex radiating to the axilla, and tricuspid regurgitation at the left lower sternal border that increases with inspiration.
How do you tell dilated cardiomyopathy from hypertrophic or restrictive cardiomyopathy on exams?
Dilated cardiomyopathy is distinguished by systolic dysfunction with a dilated ventricle and decreased ejection fraction. Hypertrophic and restrictive cardiomyopathies are primarily diastolic problems, and their ejection fraction is usually normal or increased in hypertrophic disease and usually normal in restrictive disease. A classic sound in dilated cardiomyopathy is an S3, whereas hypertrophic and restrictive patterns more often feature an S4.
What is the most important test finding in dilated cardiomyopathy?
The most important test finding in dilated cardiomyopathy is an echocardiogram showing a dilated left ventricle with decreased ejection fraction. Echo may also show global hypokinesis and, in some cases, a mural thrombus due to stasis in a large, weak chamber. This imaging pattern matches the core physiology of a big, poorly contracting ventricle causing systolic heart failure.
What complications should you think about in dilated cardiomyopathy questions?
The key complications to think about are arrhythmias, mural thrombus, and progressive heart failure. Dilated cardiomyopathy can lead to atrial or ventricular arrhythmias and conduction delays, creating a risk of sudden cardiac death. Stasis in the enlarged, weak ventricle can produce a mural thrombus, which may embolize and cause a cardioembolic stroke, especially when a neurologic deficit appears.