Heart failure questions are “free points” only if you train your brain to stop pattern-matching on buzzwords and start interrogating every answer choice. The USMLE loves to give you a convincing vignette and then test whether you can distinguish systolic (HFrEF) from diastolic (HFpEF)—and whether you know what would push the case into an entirely different diagnosis.
The Vignette (Q-bank style)
A 72-year-old woman comes to the clinic for progressive shortness of breath over 4 months. She reports dyspnea when walking one block and waking at night gasping for air. She sleeps on 3 pillows. History includes long-standing hypertension and type 2 diabetes. She has never had a myocardial infarction. Medications include hydrochlorothiazide and metformin.
Vitals: BP 168/92 mm Hg, HR 88/min, RR 18/min. Exam shows bibasilar crackles and 1+ pitting edema. S4 is present. No murmurs.
ECG shows left ventricular hypertrophy.
Echocardiogram shows left atrial enlargement, concentric LV hypertrophy, normal ejection fraction (60%), and impaired LV relaxation.
Question: Which of the following is the most likely underlying abnormality?
A. Decreased ventricular compliance due to concentric LV hypertrophy
B. Reduced cardiac output due to decreased contractility
C. Loss of dystrophin leading to dilated cardiomyopathy
D. Autoantibodies against desmosomal proteins causing RV failure
E. Pulmonary venous hypertension due to mitral stenosis
Step 1: Identify the Syndrome
This patient has classic heart failure symptoms:
- Dyspnea on exertion
- Paroxysmal nocturnal dyspnea (PND)
- Orthopnea
- Pulmonary crackles and peripheral edema
Now decide: systolic or diastolic?
Clues pushing strongly toward diastolic HF (HFpEF):
- Older woman with long-standing HTN
- Concentric LV hypertrophy + LVH on ECG
- S4 (stiff ventricle)
- Normal EF (60%)
- Echo: impaired relaxation + left atrial enlargement (chronic high filling pressures)
So: HFpEF driven by stiff ventricle → impaired filling.
Correct Answer: A. Decreased ventricular compliance due to concentric LV hypertrophy
Why it’s correct (mechanism)
Chronic hypertension → pressure overload → concentric hypertrophy (sarcomeres added in parallel) → decreased ventricular compliance.
Key physiology:
- EF can be normal because systolic function (fraction ejected) is preserved.
- The primary issue is elevated LV end-diastolic pressure (LVEDP) due to poor relaxation/stiffness.
- Elevated LVEDP backs up into the left atrium → left atrial enlargement and pulmonary congestion symptoms.
High-yield equation tie-in:
- Stroke volume depends on filling and ejection:
In HFpEF, EDV falls (can’t fill well), so SV can drop even with preserved EF:
EF can stay “normal” because both SV and EDV decrease proportionally.
HFpEF buzzwords to memorize
- S4
- Concentric LVH
- Older, female, hypertension, diabetes, obesity, CAD
- Amyloidosis or restrictive cardiomyopathy can mimic (also stiff ventricles)
Now the Real Learning: Why the Distractors Are Wrong (and what they would mean)
B. Reduced cardiac output due to decreased contractility
This describes systolic heart failure (HFrEF).
What you’d expect instead:
- Reduced EF (often <40%)
- Dilated LV (eccentric remodeling; sarcomeres in series)
- S3 (volume overload)
- Common causes: ischemic cardiomyopathy (MI), dilated cardiomyopathy, myocarditis, toxins (alcohol, doxorubicin)
How the vignette rules it out:
- EF is normal
- LVH is concentric, not dilated
- S4, not S3
- No MI history; strong HTN pressure-overload story
USMLE pearl: HFrEF = pump problem. HFpEF = filling problem.
C. Loss of dystrophin leading to dilated cardiomyopathy
This points to Duchenne/Becker muscular dystrophy → dilated cardiomyopathy → HFrEF.
What you’d expect:
- Much younger patient (child/adolescent for Duchenne; later for Becker)
- Progressive muscle weakness, Gowers sign, calf pseudohypertrophy
- Dilated cardiomyopathy with reduced EF
Why it’s wrong here:
- 72-year-old woman with HTN and LVH
- No neuromuscular symptoms
- Echo shows concentric hypertrophy, not dilation
D. Autoantibodies against desmosomal proteins causing RV failure
This is getting at arrhythmogenic right ventricular cardiomyopathy (ARVC)—classically due to mutations in desmosomal proteins (e.g., plakoglobin, desmoplakin), not “autoantibodies.”
What you’d expect:
- Young person, syncope or palpitations
- Ventricular arrhythmias, sudden death (often with exercise)
- ECG: T-wave inversions in V1–V3, epsilon wave
- RV dilation/fibrofatty replacement → RV failure signs later (JVD, hepatomegaly)
Why it’s wrong here:
- Symptoms are classic left-sided HF with pulmonary congestion
- Echo shows LV hypertrophy, not RV pathology
- The stem describes HFpEF physiology, not an arrhythmia syndrome
USMLE pearl: ARVC is a sudden death/arrhythmia question first, heart failure question second.
E. Pulmonary venous hypertension due to mitral stenosis
Mitral stenosis can cause dyspnea and pulmonary congestion because it raises left atrial pressure, but the rest of the picture doesn’t fit.
What you’d expect:
- Opening snap + diastolic rumble at apex
- Often history of rheumatic fever
- Marked left atrial enlargement (yes), possibly atrial fibrillation
- Echo: thickened mitral valve with restricted opening
Why it’s wrong here:
- No murmur, no opening snap
- The echo focuses on concentric LVH + impaired relaxation and normal EF (primary ventricular filling problem)
- Mitral stenosis is a valvular inflow obstruction problem, not LV compliance from hypertrophy
Quick distinction:
- MS: problem at the valve (LA can’t empty into LV)
- HFpEF: problem in the LV (LV can’t relax/fill)
High-Yield Comparison Table: HFrEF vs HFpEF
| Feature | HFrEF (Systolic) | HFpEF (Diastolic) |
|---|---|---|
| EF | Decreased | Normal or near-normal |
| Primary issue | ↓ Contractility | ↓ Relaxation / ↑ stiffness |
| LV size | Dilated (eccentric) | Normal or thickened (concentric) |
| Heart sound | S3 common | S4 common |
| Common causes | MI/ischemia, DCM, myocarditis, alcohol, doxorubicin | HTN, aging, obesity, DM, restrictive CM (amyloid), hypertrophic CM |
| Pressure/volume | Volume overload | Pressure overload |
| BNP | Increased | Increased (often less dramatic than HFrEF) |
The “Answer Choice Mindset” for Heart Failure Questions
When you see “HF symptoms,” force a 10-second checklist:
- EF normal or low? (echo is king)
- S3 vs S4?
- Concentric vs eccentric remodeling?
- Most likely cause given demographics and risk factors?
- Anything that screams valvular disease, restrictive disease, or primary arrhythmia disorder?
Takeaway (what you should remember on test day)
- HFpEF = stiff ventricle → impaired filling → S4, concentric LVH, LA enlargement, normal EF.
- Long-standing hypertension is the classic driver via pressure overload → concentric hypertrophy.
- Distractors often name HFrEF etiologies (dystrophin, DCM) or “nearby” causes of dyspnea (mitral stenosis, ARVC). Treat each answer as its own mini-diagnosis.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
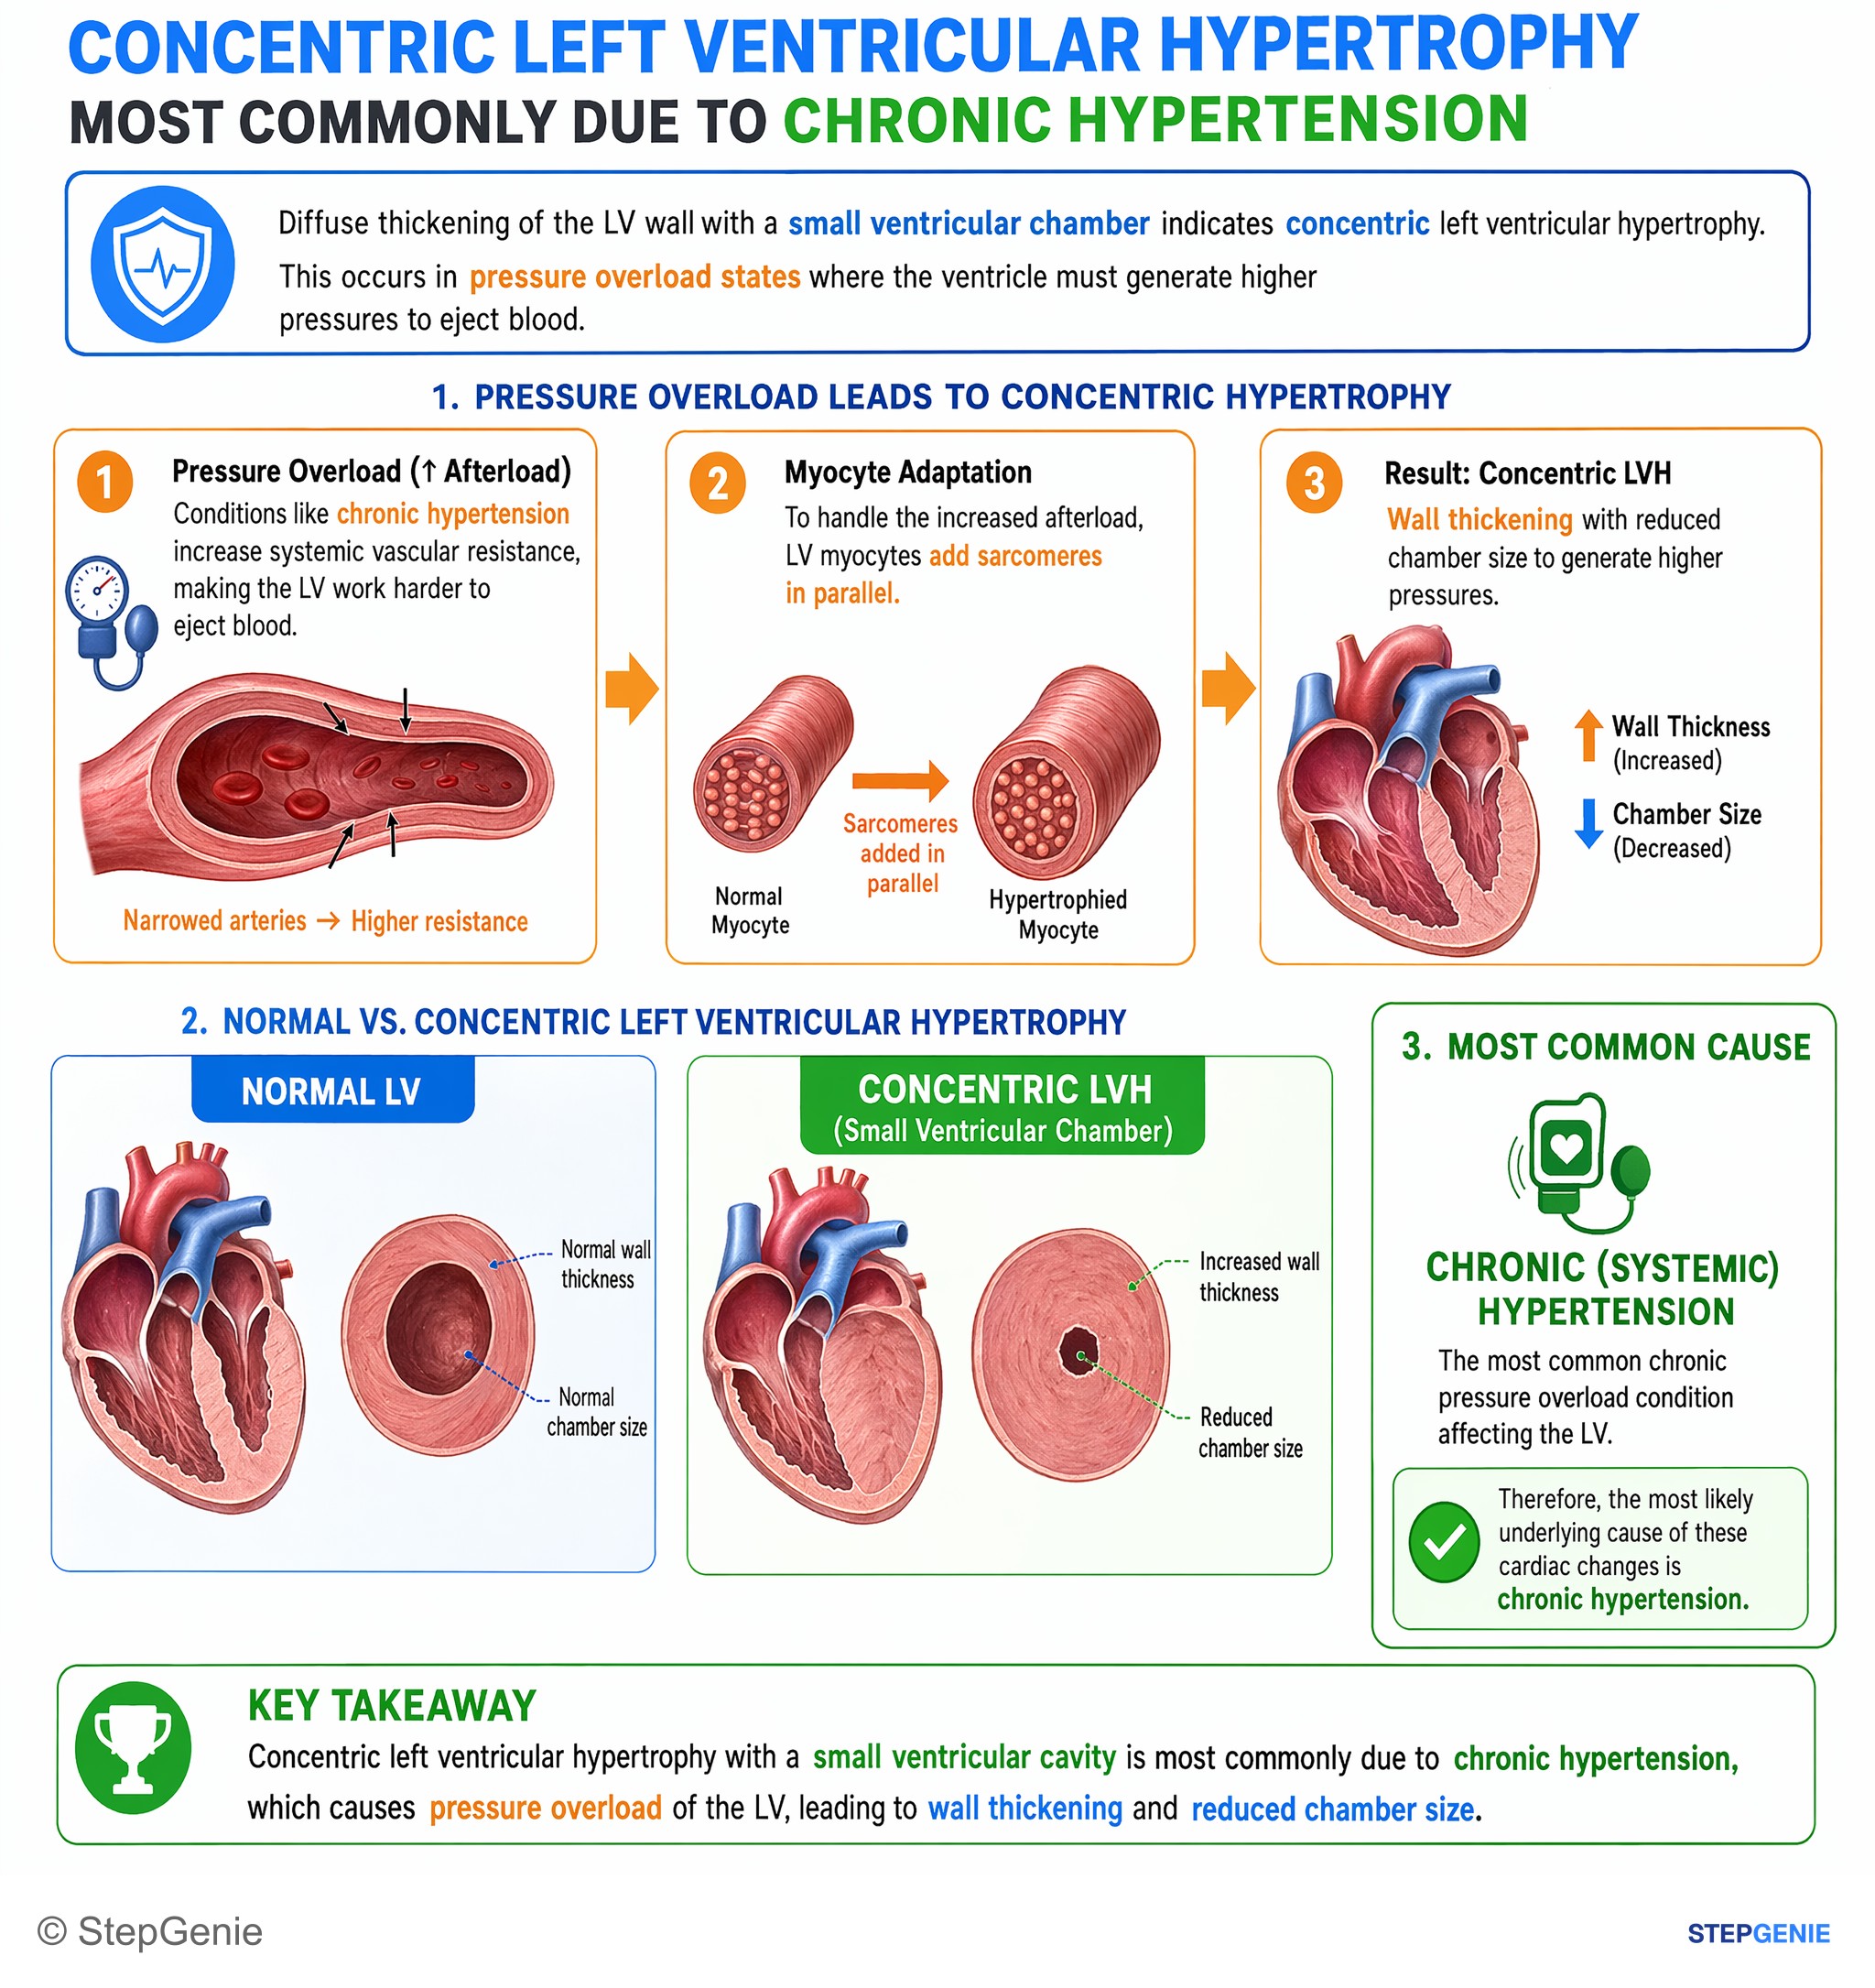
Concentric left ventricular hypertrophy with small ventricular cavity is most commonly due to chronic hypertension causing pressure…
USMLE Step 1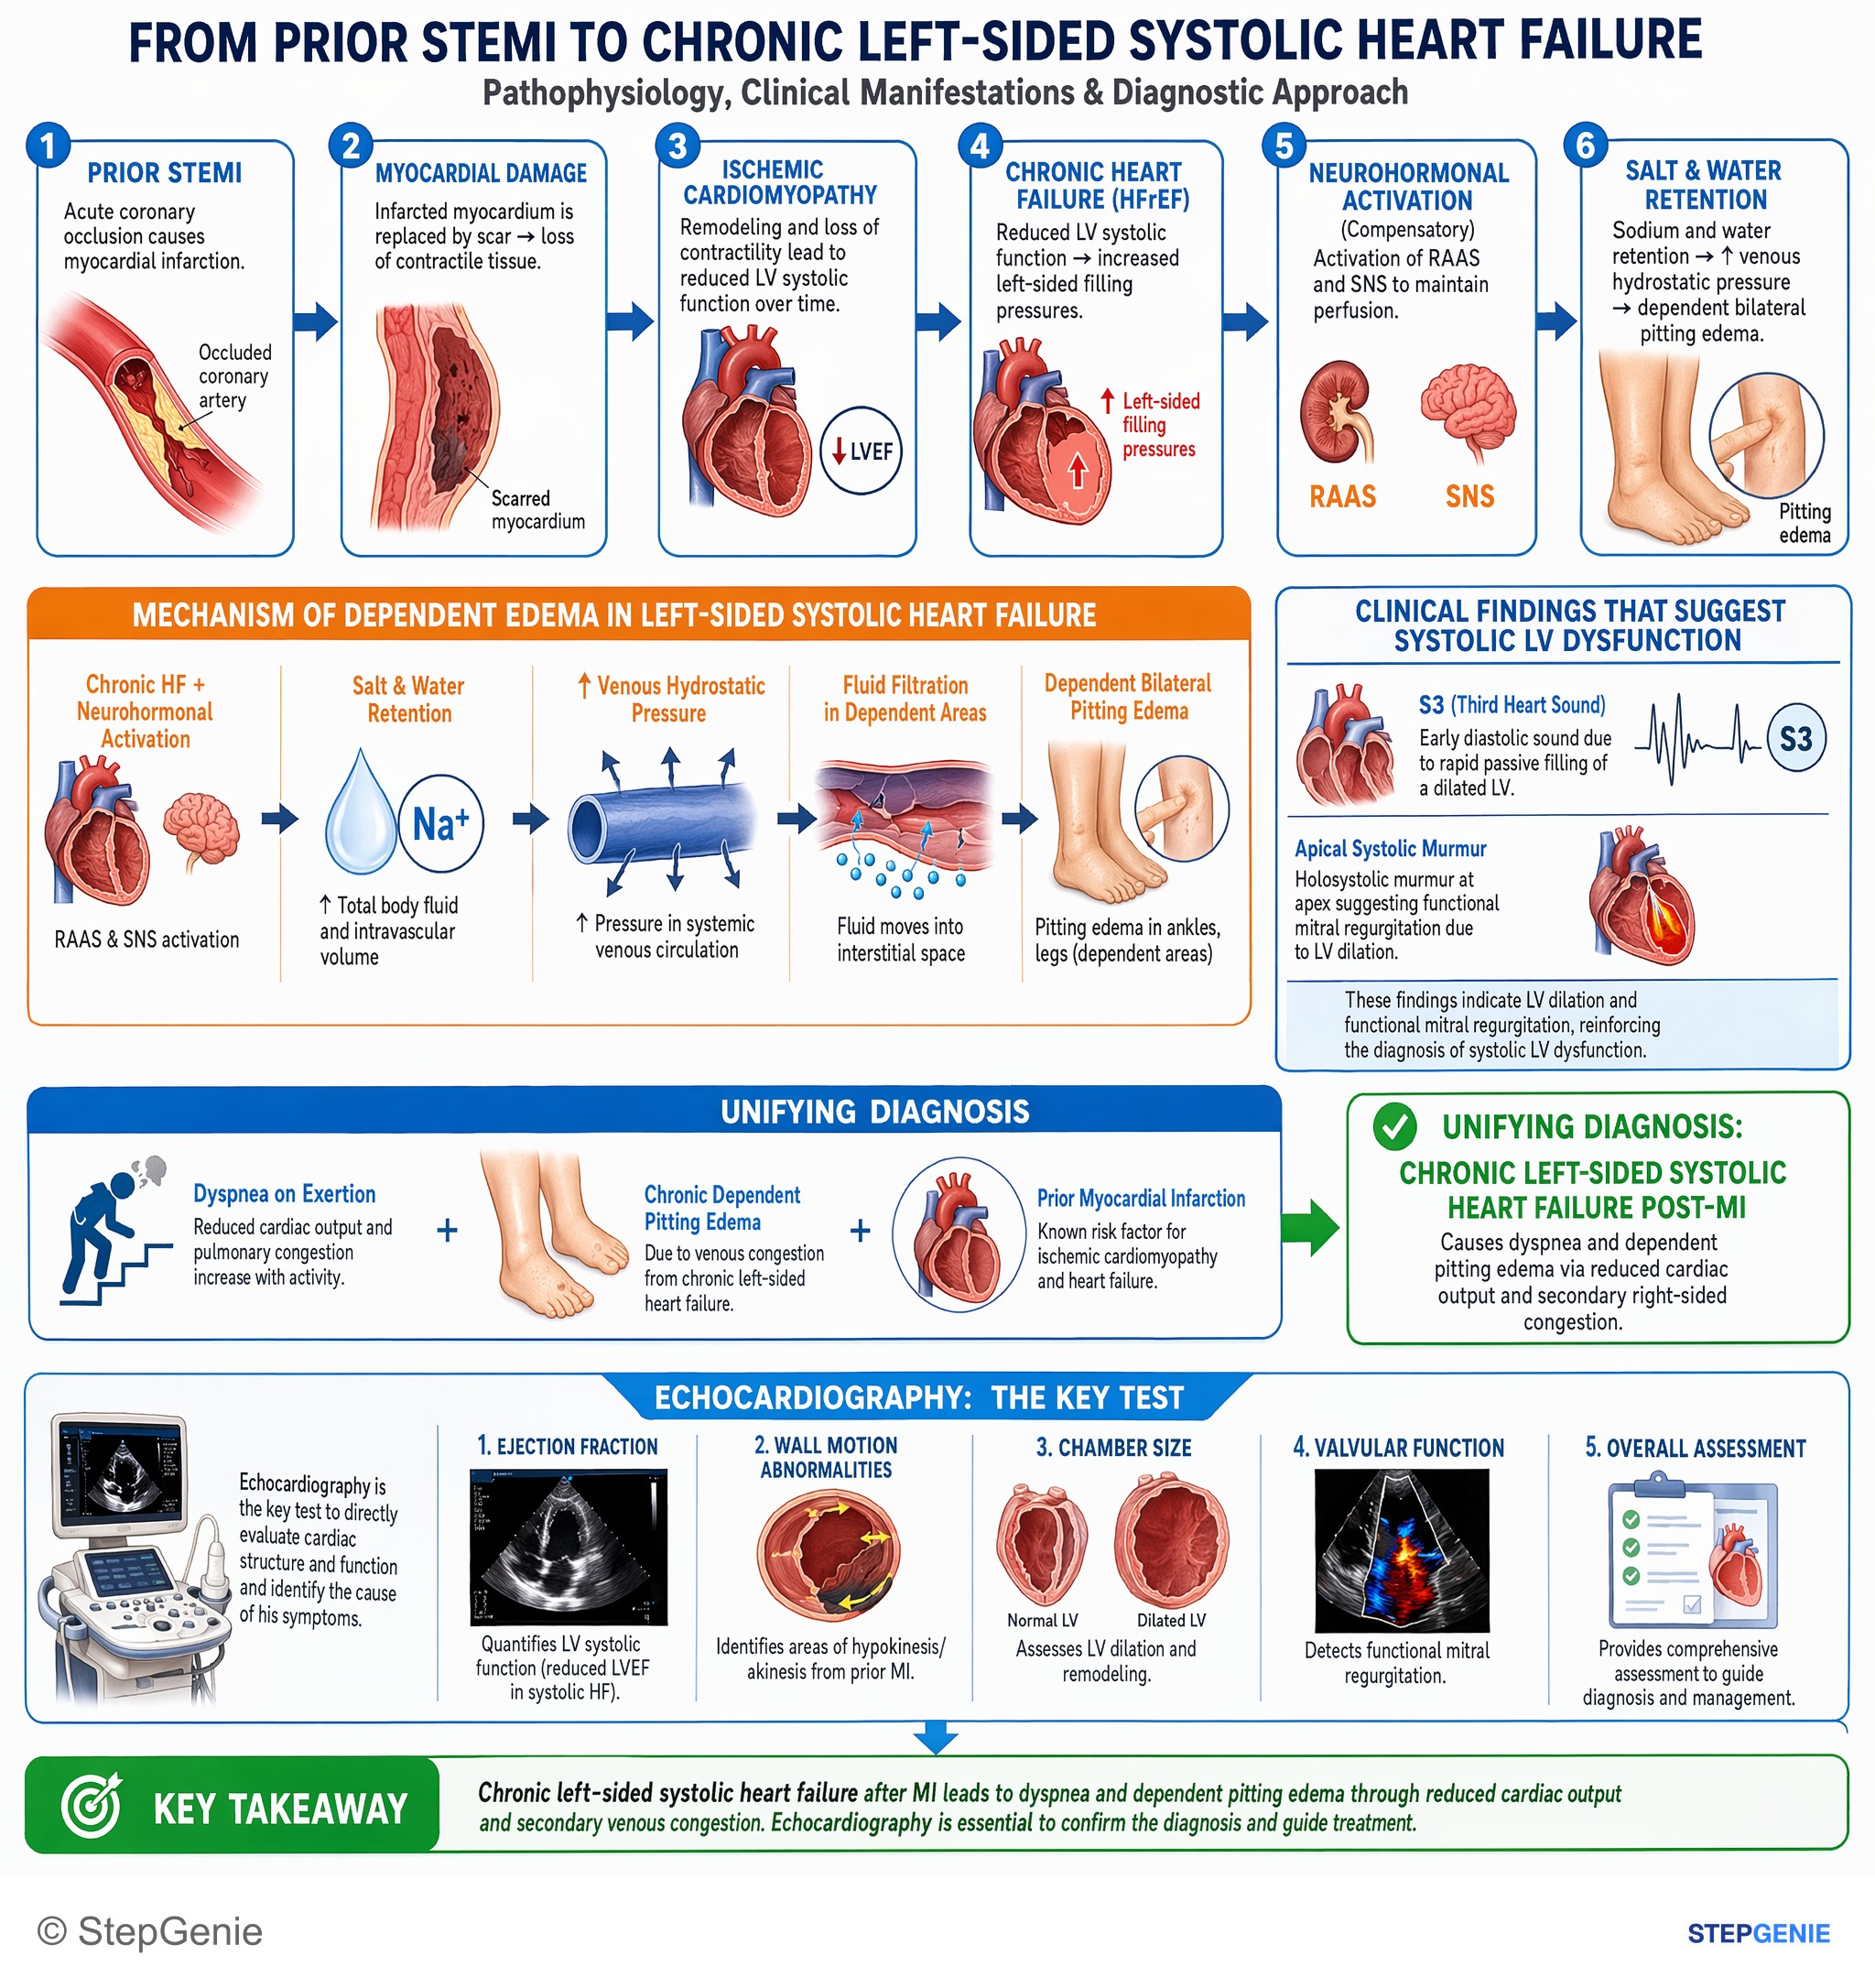
Chronic left-sided systolic heart failure post-MI causes dyspnea and dependent pitting edema via reduced cardiac output and secondary…
USMLE Step 2Frequently Asked Questions
How do you tell diastolic heart failure from systolic heart failure on a vignette?
Diastolic heart failure is suggested by preserved ejection fraction with impaired filling, while systolic heart failure is suggested by reduced ejection fraction with impaired contractility. Clues for HFpEF include an older patient with long-standing hypertension, concentric LV hypertrophy, S4, left atrial enlargement, and impaired LV relaxation on echocardiogram. HFrEF instead points to a dilated ventricle, reduced EF, and often an S3.
Why does long-standing hypertension cause HFpEF?
Long-standing hypertension causes HFpEF by creating pressure overload that leads to concentric left ventricular hypertrophy and decreased ventricular compliance. Sarcomeres are added in parallel, making the ventricle stiff and impairing relaxation. That raises left ventricular end-diastolic pressure, which backs up into the left atrium and lungs, producing left atrial enlargement and pulmonary congestion even when ejection fraction remains normal.
Why can ejection fraction stay normal in diastolic heart failure?
Ejection fraction can remain normal in diastolic heart failure because the main problem is poor filling, not poor squeezing. In HFpEF, the stiff ventricle has reduced end-diastolic volume, so stroke volume can fall even though the fraction of blood ejected is preserved. Since both stroke volume and end-diastolic volume decrease proportionally, the ejection fraction may still look normal.
What findings in this case point to HFpEF instead of mitral stenosis?
The key findings point to HFpEF because the echocardiogram shows concentric LV hypertrophy, normal ejection fraction, and impaired LV relaxation, which indicate a primary ventricular filling problem. Mitral stenosis would instead suggest a valvular inflow obstruction, typically with an opening snap, a diastolic rumble at the apex, and echocardiographic evidence of a thickened mitral valve with restricted opening.
What are the classic buzzwords for HFpEF on Step 1-style questions?
Classic HFpEF buzzwords include S4, concentric left ventricular hypertrophy, older age, female sex, hypertension, diabetes, obesity, coronary artery disease, impaired relaxation, left atrial enlargement, and preserved ejection fraction. The exam pattern is a stiff ventricle that cannot fill well, causing dyspnea, orthopnea, paroxysmal nocturnal dyspnea, pulmonary crackles, and edema despite a normal EF.