Prinzmetal angina (also called variant or vasospastic angina) is angina at rest, typically at night or in the early morning, caused by transient spasm of an epicardial coronary artery. During an attack the ECG shows transient ST elevation (sometimes ST depression) that disappears when the spasm ends, and sublingual nitroglycerin relieves the pain promptly. Smoking is the classic risk factor, and cocaine, methamphetamine, alcohol and triptans can provoke spasm. Long-acting calcium channel blockers (CCBs) are first-line prevention, long-acting nitrates are second-line, and beta-blockers are avoided because they can worsen spasm. The diagnosis is confirmed by provocation testing with intracoronary acetylcholine or ergonovine during coronary angiography.
The Q-bank question
A 39-year-old woman has had recurrent episodes of chest tightness for 2 months. They wake her between 4 and 6 AM, last 10-15 minutes and resolve within minutes of sublingual nitroglycerin. She plays tennis twice a week without symptoms. She smokes 1 pack of cigarettes per day. During an episode in the emergency department, the ECG shows 3-mm ST elevation in leads II, III and aVF that resolves completely after nitroglycerin; serial troponins are normal. Coronary angiography shows no stenosis greater than 30%. Intracoronary acetylcholine reproduces her pain with more than 90% narrowing of the right coronary artery and inferior ST elevation, reversed by intracoronary nitroglycerin.
In addition to smoking cessation, which of the following is the most appropriate long-term therapy?
A. Long-acting diltiazem B. Propranolol C. Aspirin plus ticagrelor for 12 months D. Percutaneous coronary intervention (PCI) with a drug-eluting stent in the right coronary artery E. Isosorbide mononitrate alone
Answer: A. Long-acting diltiazem. Rest pain in the early morning, exercise without symptoms, transient inferior ST elevation that vanishes with nitroglycerin, normal troponins, no significant fixed stenosis and a positive acetylcholine provocation test (transient narrowing of more than 90% with ischemic ECG changes) make this vasospastic angina. CCBs are the first-line preventive therapy: Merck names the long-acting nondihydropyridines diltiazem and verapamil, and the Japanese Circulation Society guideline calls the efficacy of CCBs for coronary spasm well established.
Why every other answer is wrong
- B. Propranolol. Beta-blockade is the classic trap. Blocking beta-2-mediated coronary vasodilation leaves alpha-mediated vasoconstriction unopposed, so beta-blockers can make spasm worse, and Merck does not recommend them. The Japanese criteria even list "attacks suppressed by CCBs but not by beta-blockers" as a supporting feature. Beta-blockers belong in stable angina, where the goal is to lower demand.
- C. Aspirin plus ticagrelor. Dual antiplatelet therapy treats thrombosis: acute coronary syndromes and stents. Spasm is a smooth-muscle problem, and this patient has neither an ACS nor a stent. Antiplatelet therapy and lipid control are reasonable risk-factor care if atherosclerosis coexists, but they do not prevent spasm.
- D. PCI with a stent. There is no fixed stenosis to treat: the artery narrows only during spasm and is near-normal between attacks. Stents treat obstructive lesions and acute thrombotic occlusion; recurrent spasm in a normal-looking artery is prevented with drugs.
- E. Isosorbide mononitrate alone. Nitrates relieve and help prevent spasm, which is why sublingual nitroglycerin aborts attacks. But long-acting nitrates are second-line, added when a CCB alone does not control symptoms, and daily use needs a nitrate-free interval to avoid tolerance.
What is happening in the artery
- Spasm, not plaque rupture. An epicardial coronary artery constricts so hard that flow nearly stops for minutes. The ischemia is transmural, so the ECG shows ST elevation in the leads facing that artery (inferior leads for the right coronary artery, as in the vignette; see coronary artery anatomy). When the spasm relaxes, the ST segments return to baseline.
- Mechanism. The Japanese Circulation Society guideline describes hypercontraction of vascular smooth muscle driven by an overactive Rho-kinase pathway, together with endothelial dysfunction with reduced nitric oxide production.
- Fixed disease can coexist. Many patients with vasospastic angina also have significant fixed obstruction of at least one major coronary artery. Merck puts 5-year survival at about 95% when obstructive disease is absent or limited to one vessel, and about 80% with multivessel obstructive disease.
- Who gets it. Typically adults in midlife. The Japanese guideline says spasm is generally believed to be more common in East Asian than in Western populations, but it is not rare in Europe and the US.
Triggers and associations
| Trigger or association | Exam point |
|---|---|
| Smoking | The classic, widely recognized risk factor; quitting is part of treatment |
| Cocaine, methamphetamine | Sympathomimetic spasm; in cocaine chest pain, benzodiazepines first and no beta-blockers |
| Triptans (eg, sumatriptan) | Labels list coronary artery vasospasm, including Prinzmetal angina, as a contraindication |
| Alcohol | Risk factor for spasm in the Japanese guideline |
| Hyperventilation, cold | Can provoke attacks; hyperventilation is also used as a provocation test |
| Beta-blockers | Can aggravate spasm |
| Migraine, Raynaud phenomenon | Other vasospastic disorders sometimes seen in the same patients |
For the stimulant side of this, see cocaine and amphetamine intoxication.
Diagnosis
- History: angina at rest, especially at night and early morning, usually lasting 5-15 minutes; attacks are only rarely and inconsistently brought on by exertion. The Japanese guideline adds marked diurnal variation in exercise tolerance, attacks induced by hyperventilation, and attacks suppressed by CCBs but not beta-blockers.
- ECG during an attack: transient ST elevation or ST depression of at least 0.1 mV, or new negative U waves, in 2 or more contiguous leads (Japanese criteria). The 2024 ESC chronic coronary syndromes guideline says to suspect vasospastic angina when transient ST elevation or depression with U-wave changes appears during an attack at rest. A Holter recording that catches ST shifts during nocturnal pain is a useful clue.
- Troponin: usually normal, but prolonged spasm can cause myocardial infarction, and spasm is one cause of MI with nonobstructive coronary arteries (MINOCA).
- Angiography with provocation testing: first exclude fixed stenosis, then give intracoronary acetylcholine or ergonovine (hyperventilation is an alternative). A positive test is transient total or subtotal occlusion (more than 90% narrowing) with signs or symptoms of ischemia (angina, ischemic ECG changes).
Treatment
| Goal | What to use | Notes |
|---|---|---|
| Abort an attack | Sublingual nitroglycerin | Relief is prompt |
| Prevent attacks | Long-acting CCB | Diltiazem or verapamil (Merck); dihydropyridines such as nifedipine also carry an FDA indication for vasospastic angina |
| Add if still symptomatic | Long-acting nitrate | Second-line; plan a nitrate-free interval |
| Remove triggers | Stop smoking; avoid cocaine, amphetamines and triptans | Treat coexisting atherosclerosis with risk-factor control (antiplatelet, lipids) |
| Avoid | Beta-blockers, especially nonselective ones like propranolol | Unopposed alpha-mediated vasoconstriction |
| After ventricular fibrillation or cardiac arrest | Implantable cardioverter-defibrillator | Reported in survivors of ventricular fibrillation or arrest |
Spasm can cause ventricular arrhythmias, cardiac arrest and MI, and patients with spasm in several arteries have a worse long-term outlook. For drug-class details, see 3 tips for calcium channel blockers.
Prinzmetal angina vs the look-alikes
| Condition | When pain occurs | ECG during pain | Troponin | Mechanism | Treatment |
|---|---|---|---|---|---|
| Prinzmetal angina | Rest, night or early morning | Transient ST elevation | Usually normal | Epicardial coronary spasm | CCB, nitrates |
| Stable angina | Exertion, emotion | ST depression | Normal | Fixed stenosis, demand ischemia | Beta-blocker, nitrates, aspirin, statin |
| Unstable angina / NSTEMI | Rest or crescendo | ST depression, T-wave inversion | Normal (UA) or raised (NSTEMI) | Plaque disruption, nonocclusive thrombus | ACS pathway |
| STEMI | Persistent | ST elevation not quickly reversed by nitroglycerin | Raised | Usually occlusive thrombus | Emergency reperfusion |
| Acute pericarditis | Pleuritic, positional | Diffuse ST elevation, PR depression | Normal or raised | Pericardial inflammation | NSAID or aspirin plus colchicine |
The stable vs unstable distinction is broken down in stable vs unstable angina.
How USMLE tests it
- The classic stem: a younger smoker with chest pain in the early morning, normal exercise tolerance, ST elevation that resolves with nitroglycerin, and normal or near-normal coronary arteries. Answer: coronary vasospasm.
- "Best drug to prevent attacks": a CCB. "Drug that worsens it": a nonselective beta-blocker. "Drug to avoid for her migraines": a triptan.
- "Best test to confirm": coronary angiography with acetylcholine or ergonovine provocation.
- Persistent ST elevation is a STEMI until proven otherwise. Merck defines STEMI as ST elevation not quickly reversed by nitroglycerin; only transient, nitroglycerin-responsive elevation fits spasm. Review the territories in the 5-second rule for STEMI patterns.
- Cocaine chest pain: benzodiazepines first, then nitrates (or phentolamine); beta-blockers are contraindicated.
- A normal angiogram does not mean the pain is not cardiac: spasm (and MINOCA) can occur in arteries without fixed stenosis.
Key takeaways
- Prinzmetal (vasospastic) angina = rest angina, often at night or early morning, from transient epicardial coronary spasm.
- Transient ST elevation during pain that resolves with nitroglycerin; troponin usually normal.
- Smoking is the classic risk factor; cocaine, methamphetamine, alcohol, triptans and hyperventilation can trigger spasm.
- Confirm with intracoronary acetylcholine or ergonovine provocation (more than 90% transient narrowing with ischemia).
- CCBs first-line, long-acting nitrates second-line, sublingual nitroglycerin for attacks, no beta-blockers, stop smoking.
- Complications: ventricular arrhythmias, cardiac arrest, MI; coexisting multivessel obstructive disease worsens prognosis.
Sources
- Vasospastic (Variant) Angina — Merck Manual Professional Edition (2026)
- JCS/CVIT/JCC 2023 Guideline Focused Update on Diagnosis and Treatment of Vasospastic Angina and Coronary Microvascular Dysfunction — Journal of Cardiology (2023)
- 2024 ESC Guidelines for the Management of Chronic Coronary Syndromes — European Heart Journal (2024)
- Prinzmetal Angina (archived) — StatPearls, NCBI Bookshelf (2023)
- Angina Pectoris — Merck Manual Professional Edition (2026)
- Overview of Acute Coronary Syndromes (ACS) — Merck Manual Professional Edition (2026)
- Cocaine — Merck Manual Professional Edition (2026)
- Nifedipine Capsules: Prescribing Information — DailyMed, NLM (2018)
- Imitrex (Sumatriptan) Tablets: Prescribing Information — DailyMed, NLM (2025)
- Pericarditis — Merck Manual Professional Edition (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
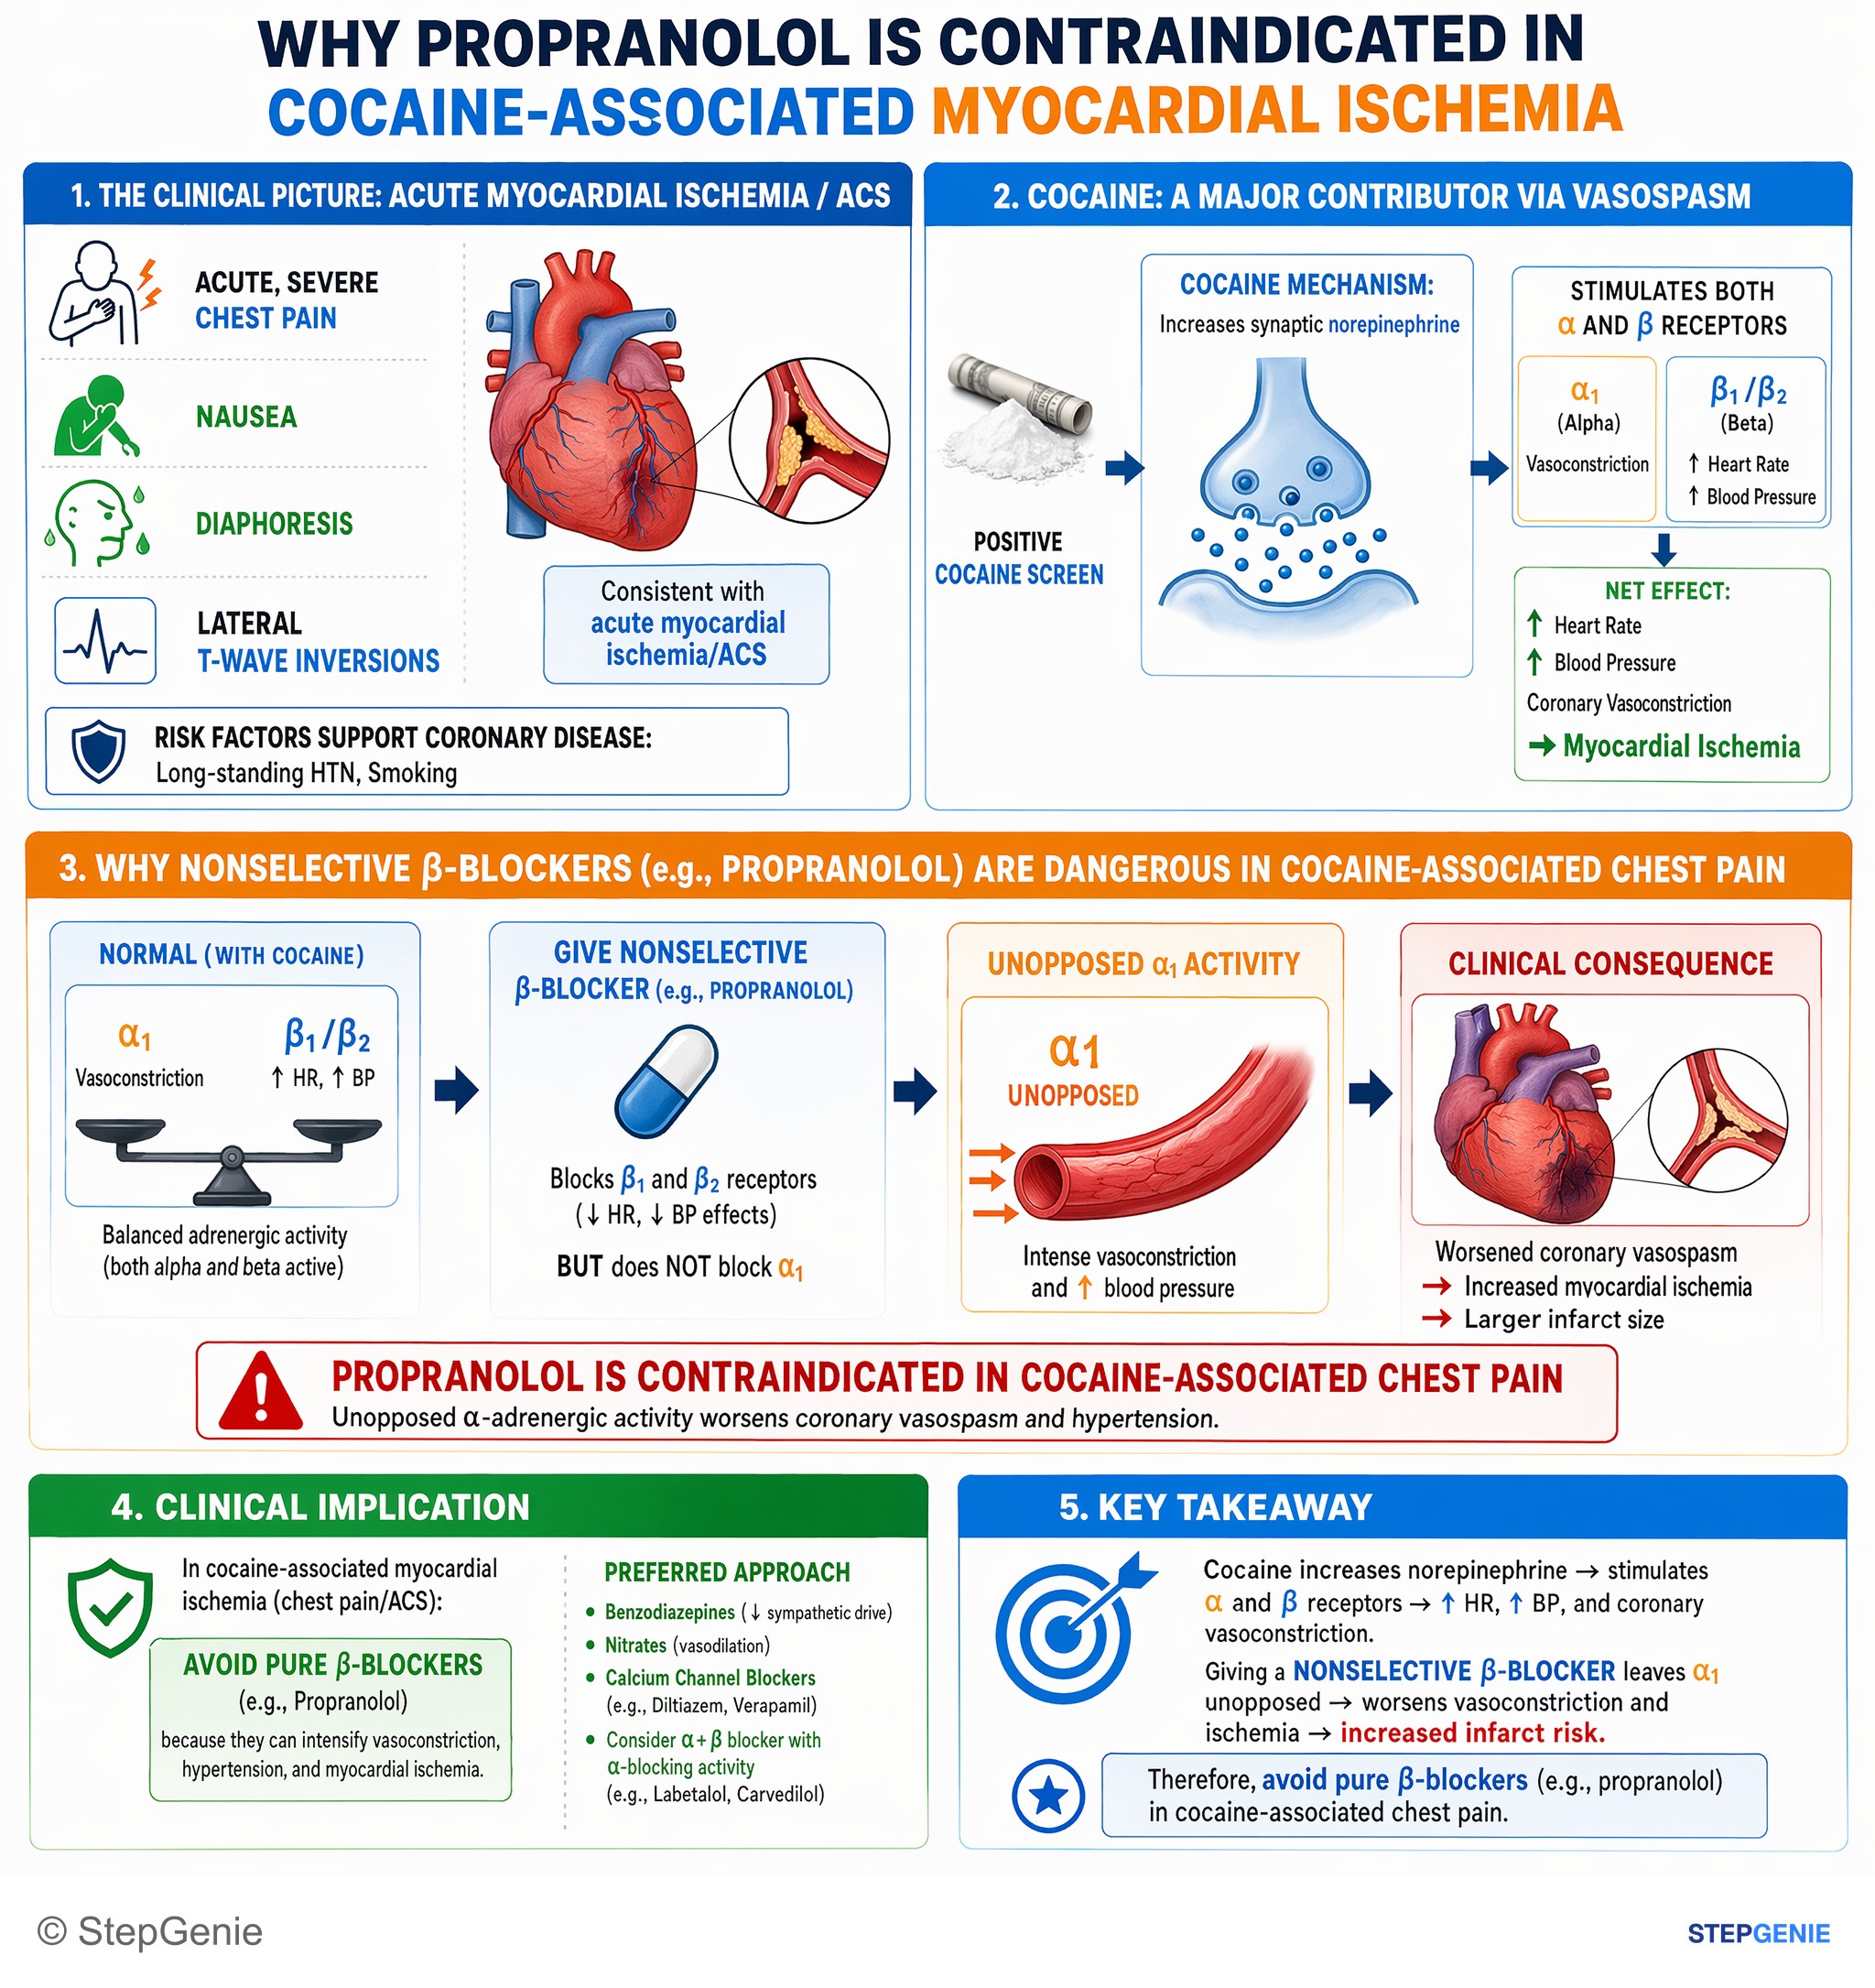
Cocaine-associated myocardial ischemia: avoid pure β-blockers (e.g., propranolol) because unopposed α-adrenergic activity worsens coronary…
USMLE Step 2Frequently Asked Questions
What is Prinzmetal angina?
Prinzmetal angina, also called variant or vasospastic angina, is chest pain caused by temporary spasm of an epicardial coronary artery rather than by a fixed blockage or a clot. Attacks usually come at rest, often at night or in the early morning, last minutes, and are relieved quickly by sublingual nitroglycerin. During an attack the ECG shows transient ST elevation that returns to normal when the spasm stops. Smoking is the classic risk factor.
What ECG changes are seen in Prinzmetal angina?
During an attack, the ECG typically shows ST-segment elevation in the leads facing the affected artery, for example II, III and aVF when the right coronary artery goes into spasm. ST depression or new negative U waves can also occur. The key feature is that the changes are transient: they resolve when the spasm relaxes or nitroglycerin is given. ST elevation that persists and is not quickly reversed by nitroglycerin should be treated as a STEMI.
What is the first-line treatment for Prinzmetal angina?
Long-acting calcium channel blockers are first-line for preventing attacks; the Merck Manual names diltiazem and verapamil, and nifedipine also has an FDA indication for vasospastic angina. Sublingual nitroglycerin relieves individual attacks, and long-acting nitrates are added as second-line therapy when a calcium channel blocker alone is not enough. Stopping smoking and avoiding triggers such as cocaine, amphetamines and triptans are essential.
Why are beta-blockers avoided in Prinzmetal angina?
Coronary arteries dilate in response to beta-2 stimulation and constrict in response to alpha stimulation. Blocking beta receptors, especially with a nonselective drug such as propranolol, leaves alpha-mediated vasoconstriction unopposed, which can make coronary spasm worse. For this reason the Merck Manual does not recommend beta-blockers for vasospastic angina, and Japanese diagnostic criteria note that attacks are suppressed by calcium channel blockers but not by beta-blockers.
How is vasospastic angina diagnosed?
The history (rest angina at night or early morning with prompt relief from nitrates) and an ECG captured during an attack showing transient ST changes suggest it, and a Holter monitor can catch nocturnal episodes. Coronary angiography excludes a fixed stenosis, and provocation testing with intracoronary acetylcholine or ergonovine confirms spasm when it produces transient total or subtotal narrowing of more than 90% with signs or symptoms of ischemia.
What triggers Prinzmetal angina?
Smoking is the classic, widely recognized risk factor. Spasm can also be provoked by cocaine and methamphetamine, alcohol, hyperventilation, cold exposure and triptan migraine drugs such as sumatriptan, whose labels list coronary artery vasospasm, including Prinzmetal angina, as a contraindication. Beta-blockers can aggravate spasm. Some patients also have other vasospastic conditions such as migraine or Raynaud phenomenon. Attacks cluster at rest, at night and in the early morning.