My favorite way to stop missing “post-MI complication” questions is to treat them like a timeline matching game: the stem gives you a day/week/month after infarct, and every answer choice is basically a timestamp. Once you anchor the classic windows (24 hours, 1–3 days, 3–14 days, weeks to months), a huge chunk of cardiovascular Q-bank becomes pattern recognition instead of guesswork.
Tag: Cardiovascular > Coronary & Ischemic Heart Disease
The Post‑MI Timeline You Actually Use on Exams
Here’s the backbone. Memorize this and you’ll start eliminating distractors instantly.
High-yield timeline table
| Time after MI | What’s happening pathologically | Big complications (classic presentations) |
|---|---|---|
| 0–24 hours | Coagulative necrosis begins; “wavy fibers”; edema/hemorrhage | Arrhythmias (most common cause of death), acute HF, cardiogenic shock |
| 1–3 days | Heavy neutrophils | Fibrinous pericarditis (pleuritic CP, friction rub) |
| 3–14 days (peak ~day 5) | Macrophages clear dead tissue → wall is softest | Free wall rupture → tamponade, VSD → harsh holosystolic murmur, papillary muscle rupture → acute severe MR, pseudoaneurysm |
| 1–2 weeks+ | Granulation tissue; early scar | True ventricular aneurysm (weeks–months) starts becoming possible |
| Weeks to months | Dense collagen scar | Dressler syndrome (autoimmune pericarditis), true aneurysm, mural thrombus → emboli |
Exam mindset:
- Days 3–14 = rupture window (macrophages are “cleanup crew” that weaken the wall).
- Weeks–months = scar problems (aneurysm, Dressler).
Clinical Vignette (Q‑Bank Style)
A 62-year-old man is admitted for an acute anterior STEMI and undergoes successful PCI. On hospital day 5, he suddenly becomes profoundly hypotensive and collapses. On exam, he is diaphoretic with distended neck veins and muffled heart sounds. ECG shows sinus tachycardia. Bedside ultrasound reveals a large pericardial effusion with right ventricular diastolic collapse.
What is the most likely underlying cause?
A. Autoimmune pericarditis due to antibodies against myocardial proteins
B. Fibrinous pericarditis from transmural inflammation
C. Left ventricular free wall rupture due to macrophage-mediated tissue breakdown
D. Papillary muscle rupture causing acute mitral regurgitation
E. Ventricular septal rupture causing left-to-right shunting
Correct Answer: C. Left ventricular free wall rupture due to macrophage-mediated tissue breakdown
Why it’s correct
- Timing: Day 5 is right in the 3–14 day rupture window (peak around day 5).
- Mechanism: Macrophages are clearing necrotic myocardium → structural integrity is lowest (“softening”).
- Presentation: Cardiac tamponade = hypotension + JVD + muffled heart sounds (Beck triad) + ultrasound evidence (RV diastolic collapse).
- Big association: More common after transmural MI (e.g., anterior STEMI).
Path buzzwords that should trigger you
- “Sudden collapse” + “day 5” + “pericardial effusion/tamponade” = free wall rupture until proven otherwise.
Why Each Distractor Matters (and how to eliminate it fast)
A. Autoimmune pericarditis due to antibodies against myocardial proteins
This is Dressler syndrome.
- Timing: Weeks to months after MI (not day 5).
- Symptoms: Fever, malaise, pleuritic chest pain, pericardial friction rub; may see pericardial effusion but not typically sudden catastrophic tamponade on day 5.
- Mechanism: Autoimmune reaction to exposed cardiac antigens.
Key differentiator:
- Early pericarditis = 1–3 days (direct inflammation)
- Dressler = weeks–months (autoimmune)
B. Fibrinous pericarditis from transmural inflammation
This is the early post‑MI pericarditis complication.
- Timing: 1–3 days after transmural MI.
- Clues: Pleuritic chest pain that improves leaning forward, friction rub, diffuse ST elevations can occur (pericarditis pattern), but the stem here is classic for tamponade from rupture at day 5.
Why it’s wrong here: The patient’s problem is hemodynamic collapse with tamponade physiology at day 5, which screams mechanical rupture.
D. Papillary muscle rupture causing acute mitral regurgitation
This is a classic mechanical complication in the same rupture window, so you must separate it by presentation.
- Timing: 3–14 days post MI (often around day 2–7; classically ~day 5).
- Risk territory: Inferior MI (RCA) → posteromedial papillary muscle has single blood supply, making it more vulnerable.
- Presentation: Sudden pulmonary edema, hypotension, and a new loud systolic murmur (may be holosystolic at apex radiating to axilla), plus large V waves on PCWP.
Why it’s wrong here: The ultrasound shows pericardial effusion with RV collapse, not pulmonary edema from MR.
E. Ventricular septal rupture causing left-to-right shunting
Another mechanical complication in the rupture window—again, separate by the hemodynamics and auscultation.
- Timing: 3–14 days post MI (often 3–5 days).
- Presentation: Acute HF, hypotension, new harsh holosystolic murmur at the left sternal border + thrill.
- Hemodynamics: Step-up in oxygen saturation in the RV (L→R shunt).
Why it’s wrong here: The stem is tamponade physiology, not a new murmur with shunt physiology.
One-Pager: Post‑MI Complications by Time (Answer-Choice Elimination Tool)
Days 0–1 (first 24 hours)
- Most common cause of death: Arrhythmia (VT/VF)
- Acute HF/cardiogenic shock can occur early
- Path: early coagulative necrosis, wavy fibers
Days 1–3
- Fibrinous pericarditis
- Pleuritic CP, friction rub
- Path: neutrophils
Days 3–14 (peak around day 5)
- Mechanical ruptures (think: “the wall is mushy”)
- Free wall rupture → tamponade
- Papillary muscle rupture → acute MR
- Septal rupture → VSD
- Path: macrophages
Weeks to months
- Dressler syndrome (autoimmune pericarditis)
- True ventricular aneurysm (scarred wall bulges)
- Can cause HF, arrhythmias, mural thrombus
- Mural thrombus → systemic emboli (esp. LV)
True Aneurysm vs Pseudoaneurysm (Common Distractor Pair)
| Feature | True aneurysm | Pseudoaneurysm |
|---|---|---|
| Wall composition | Scarred myocardium (all layers) | Contained rupture (pericardium/fibrous tissue) |
| Timing | Weeks–months | Often after MI; can be earlier, higher urgency |
| Rupture risk | Low | High (surgical emergency) |
| Classic association | Persistent ST elevation, mural thrombus | Narrow neck on imaging |
USMLE trick: If the vignette sounds like contained rupture with high rupture risk → pseudoaneurysm.
High‑Yield Takeaways (What You Want in Your Head During Test Day)
- Day 5 + tamponade = LV free wall rupture (macrophage phase).
- 1–3 days = fibrinous pericarditis (neutrophils).
- Weeks–months = Dressler + true aneurysm.
- Inferior MI (RCA) + sudden pulmonary edema + new systolic murmur = papillary muscle rupture (acute MR).
- New harsh holosystolic murmur + shock days after MI = VSD.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
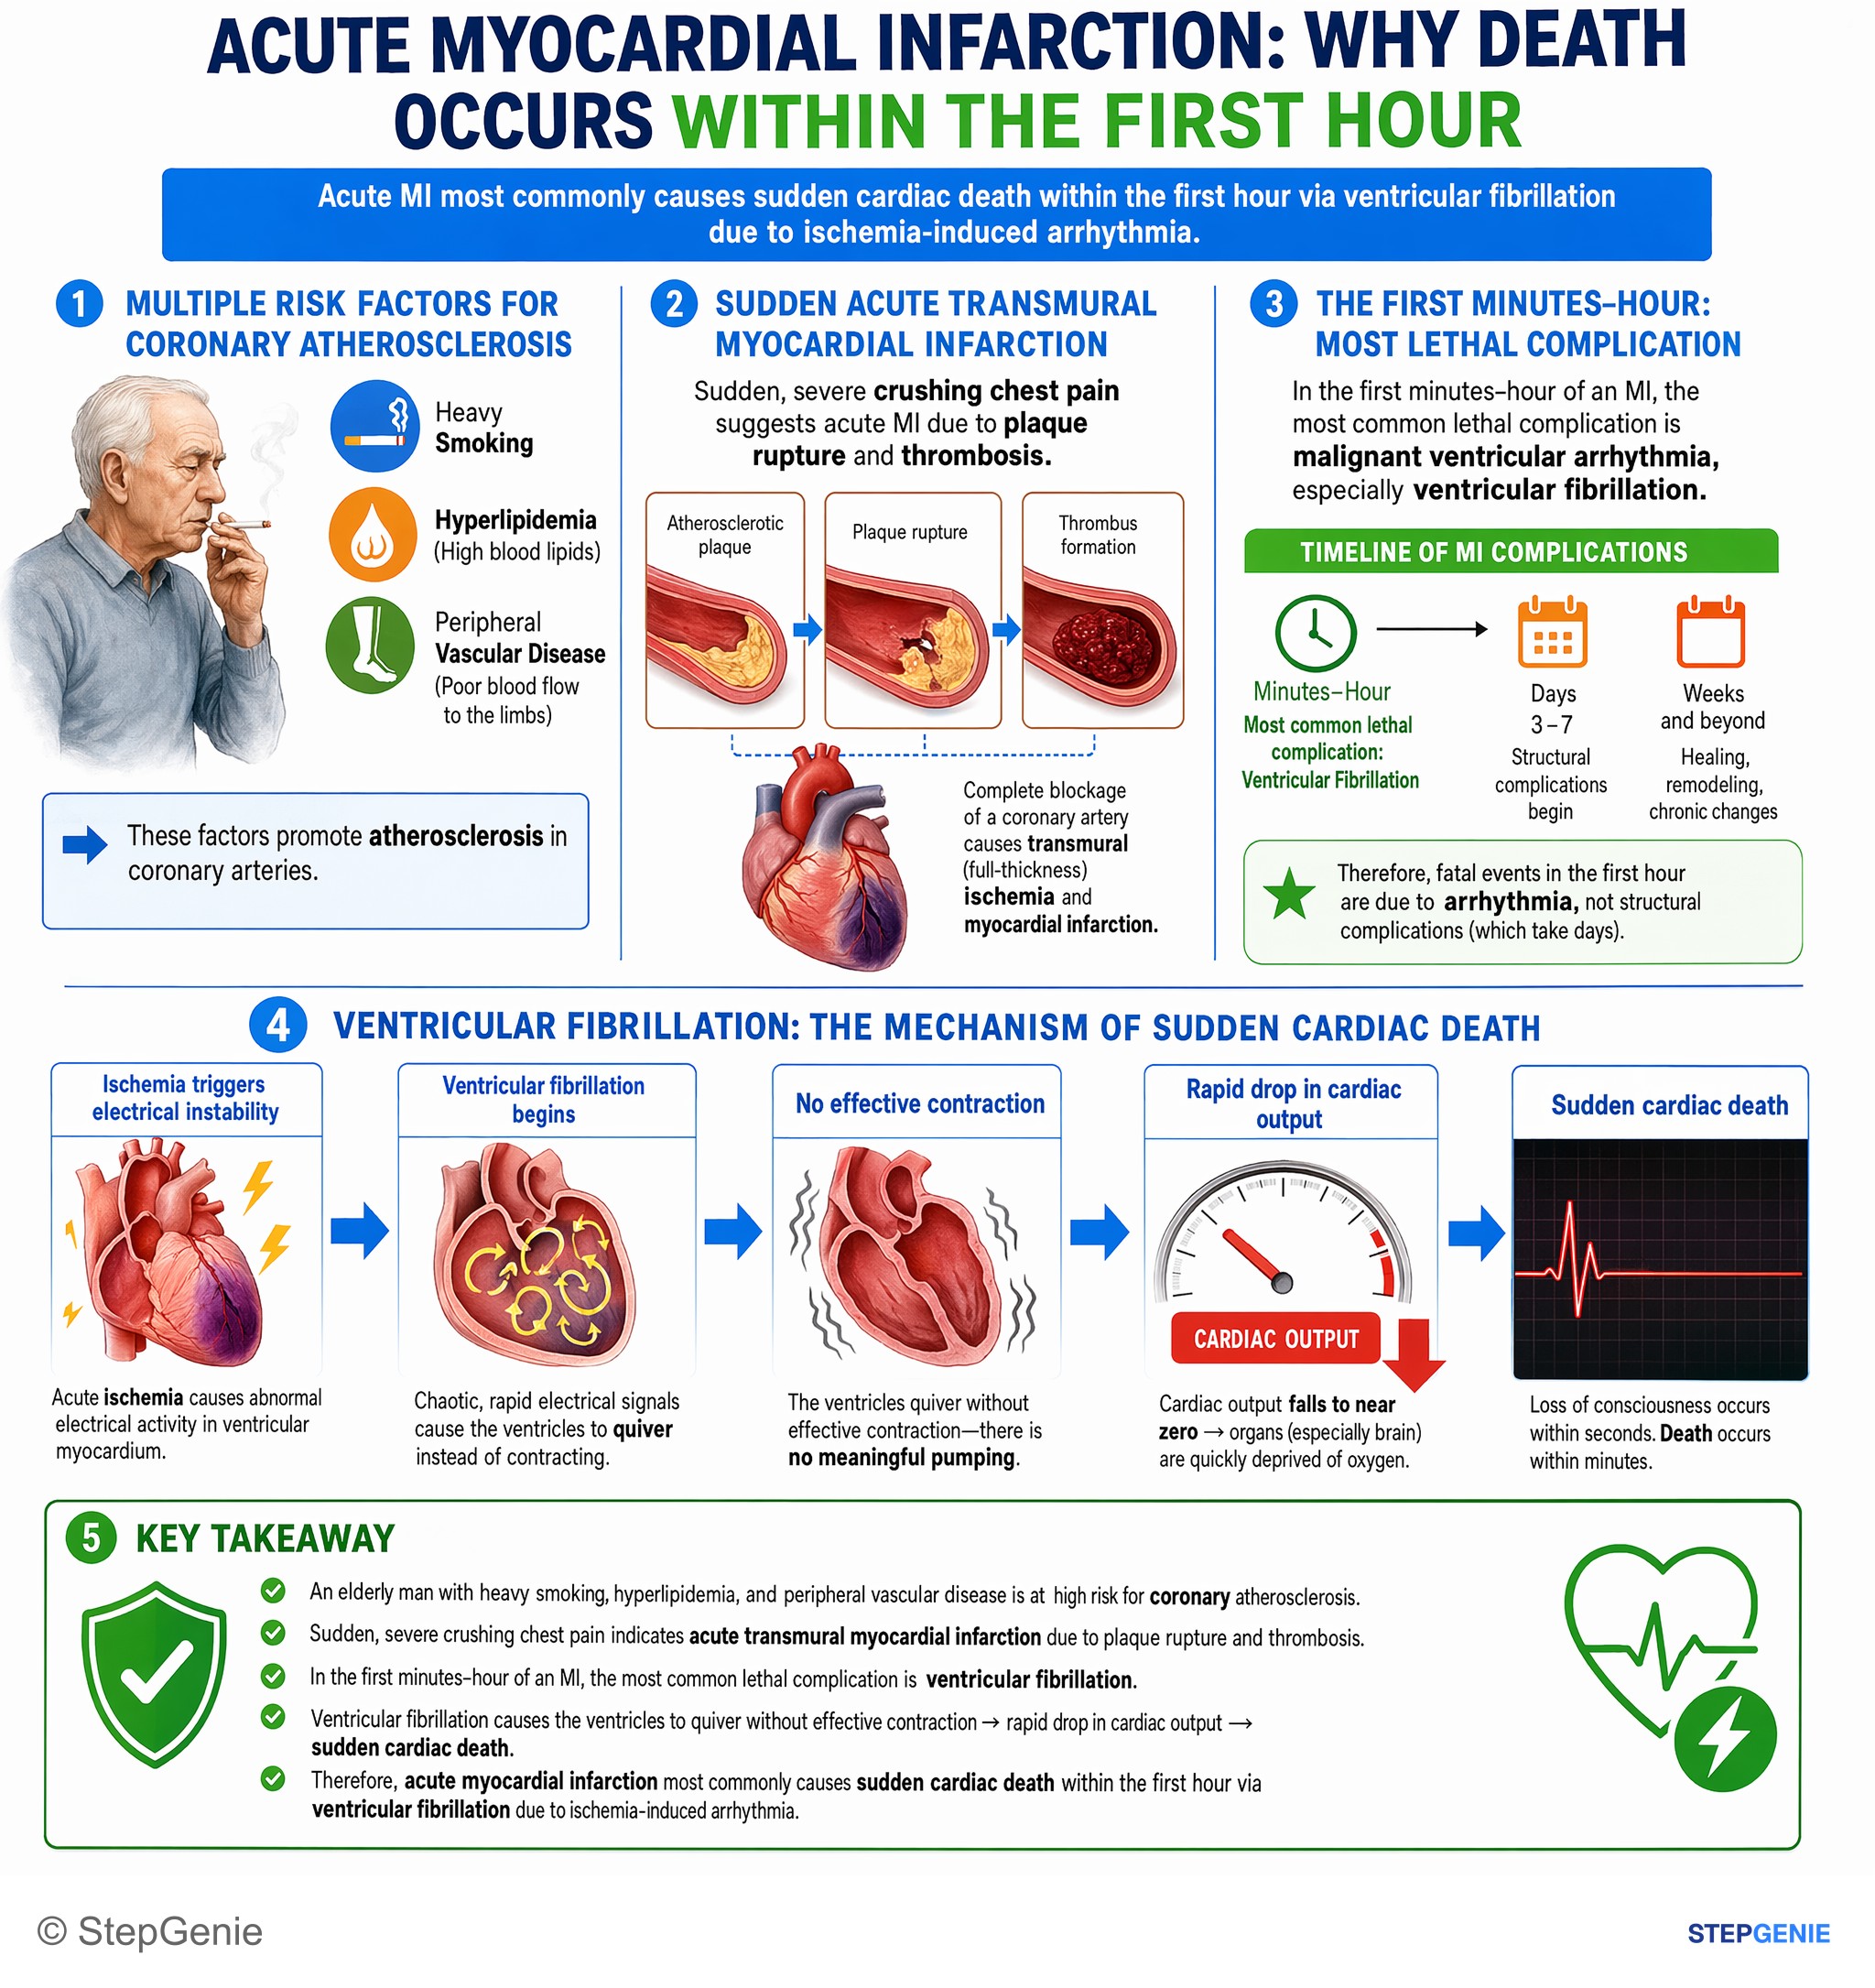
Acute myocardial infarction most commonly causes sudden cardiac death within the first hour via ventricular fibrillation due to…
USMLE Step 2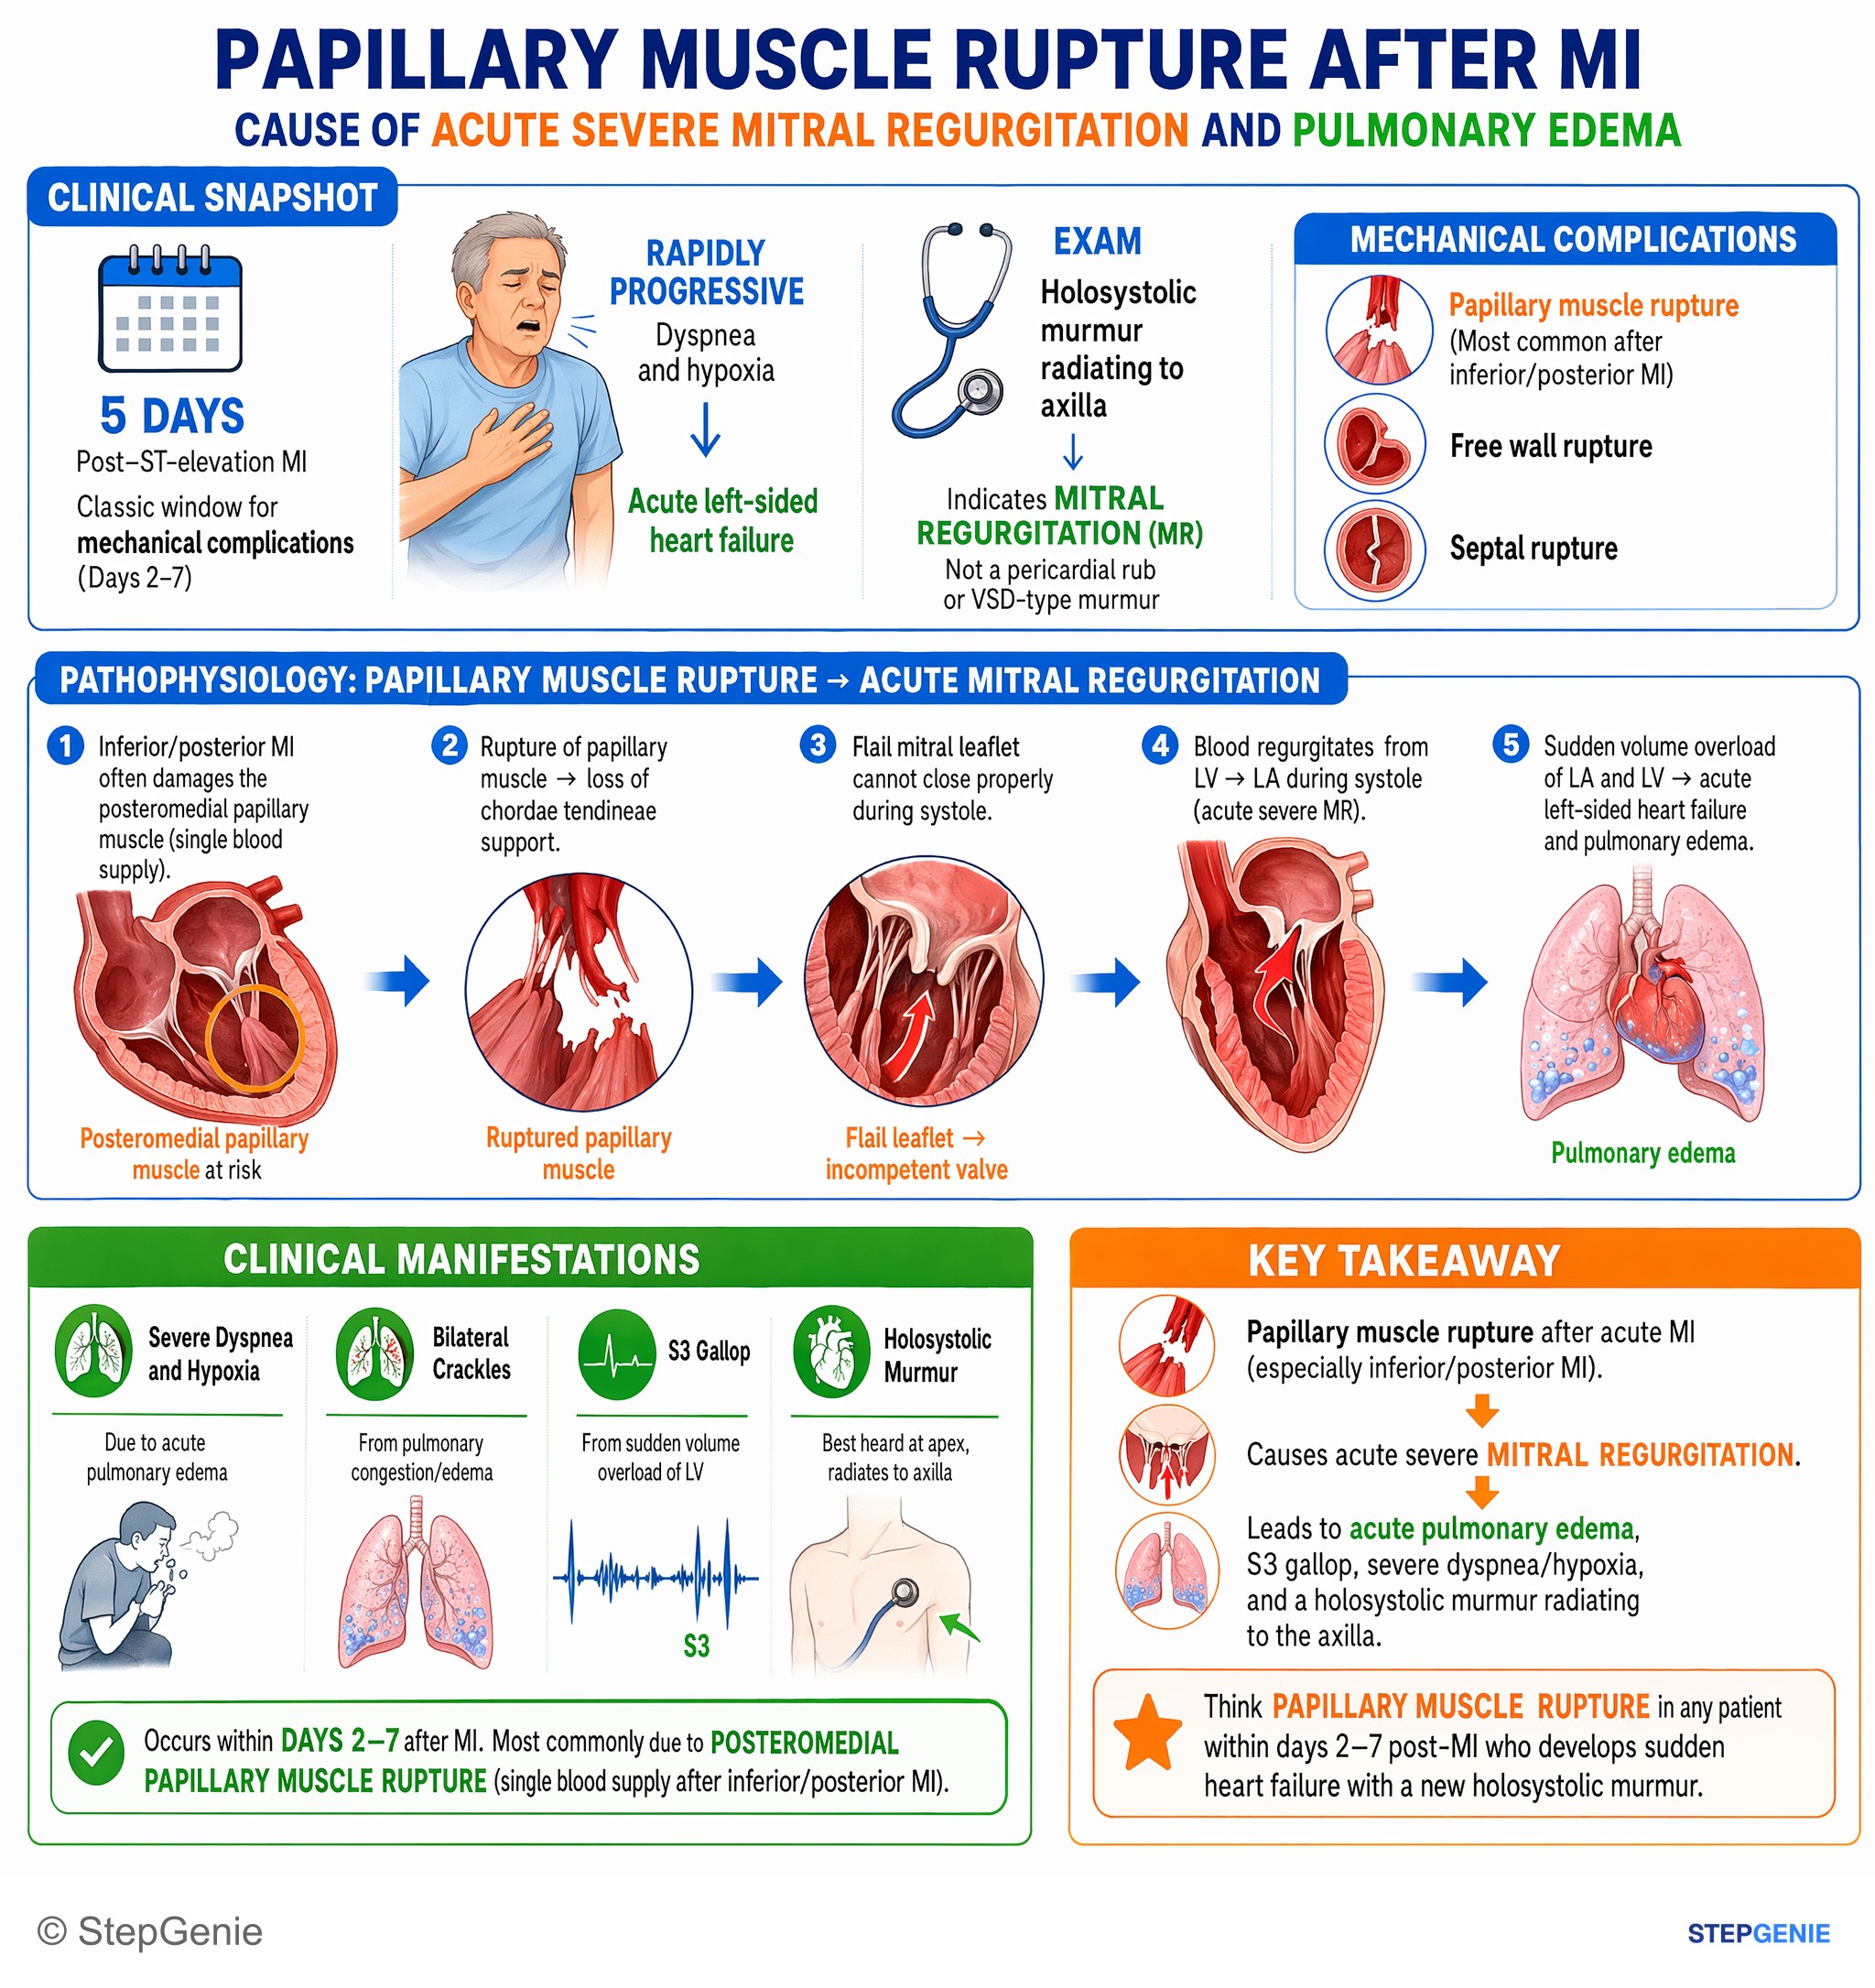
Papillary muscle rupture after acute MI causes acute severe mitral regurgitation, pulmonary edema, S3, and holosystolic murmur to axilla…
USMLE Step 2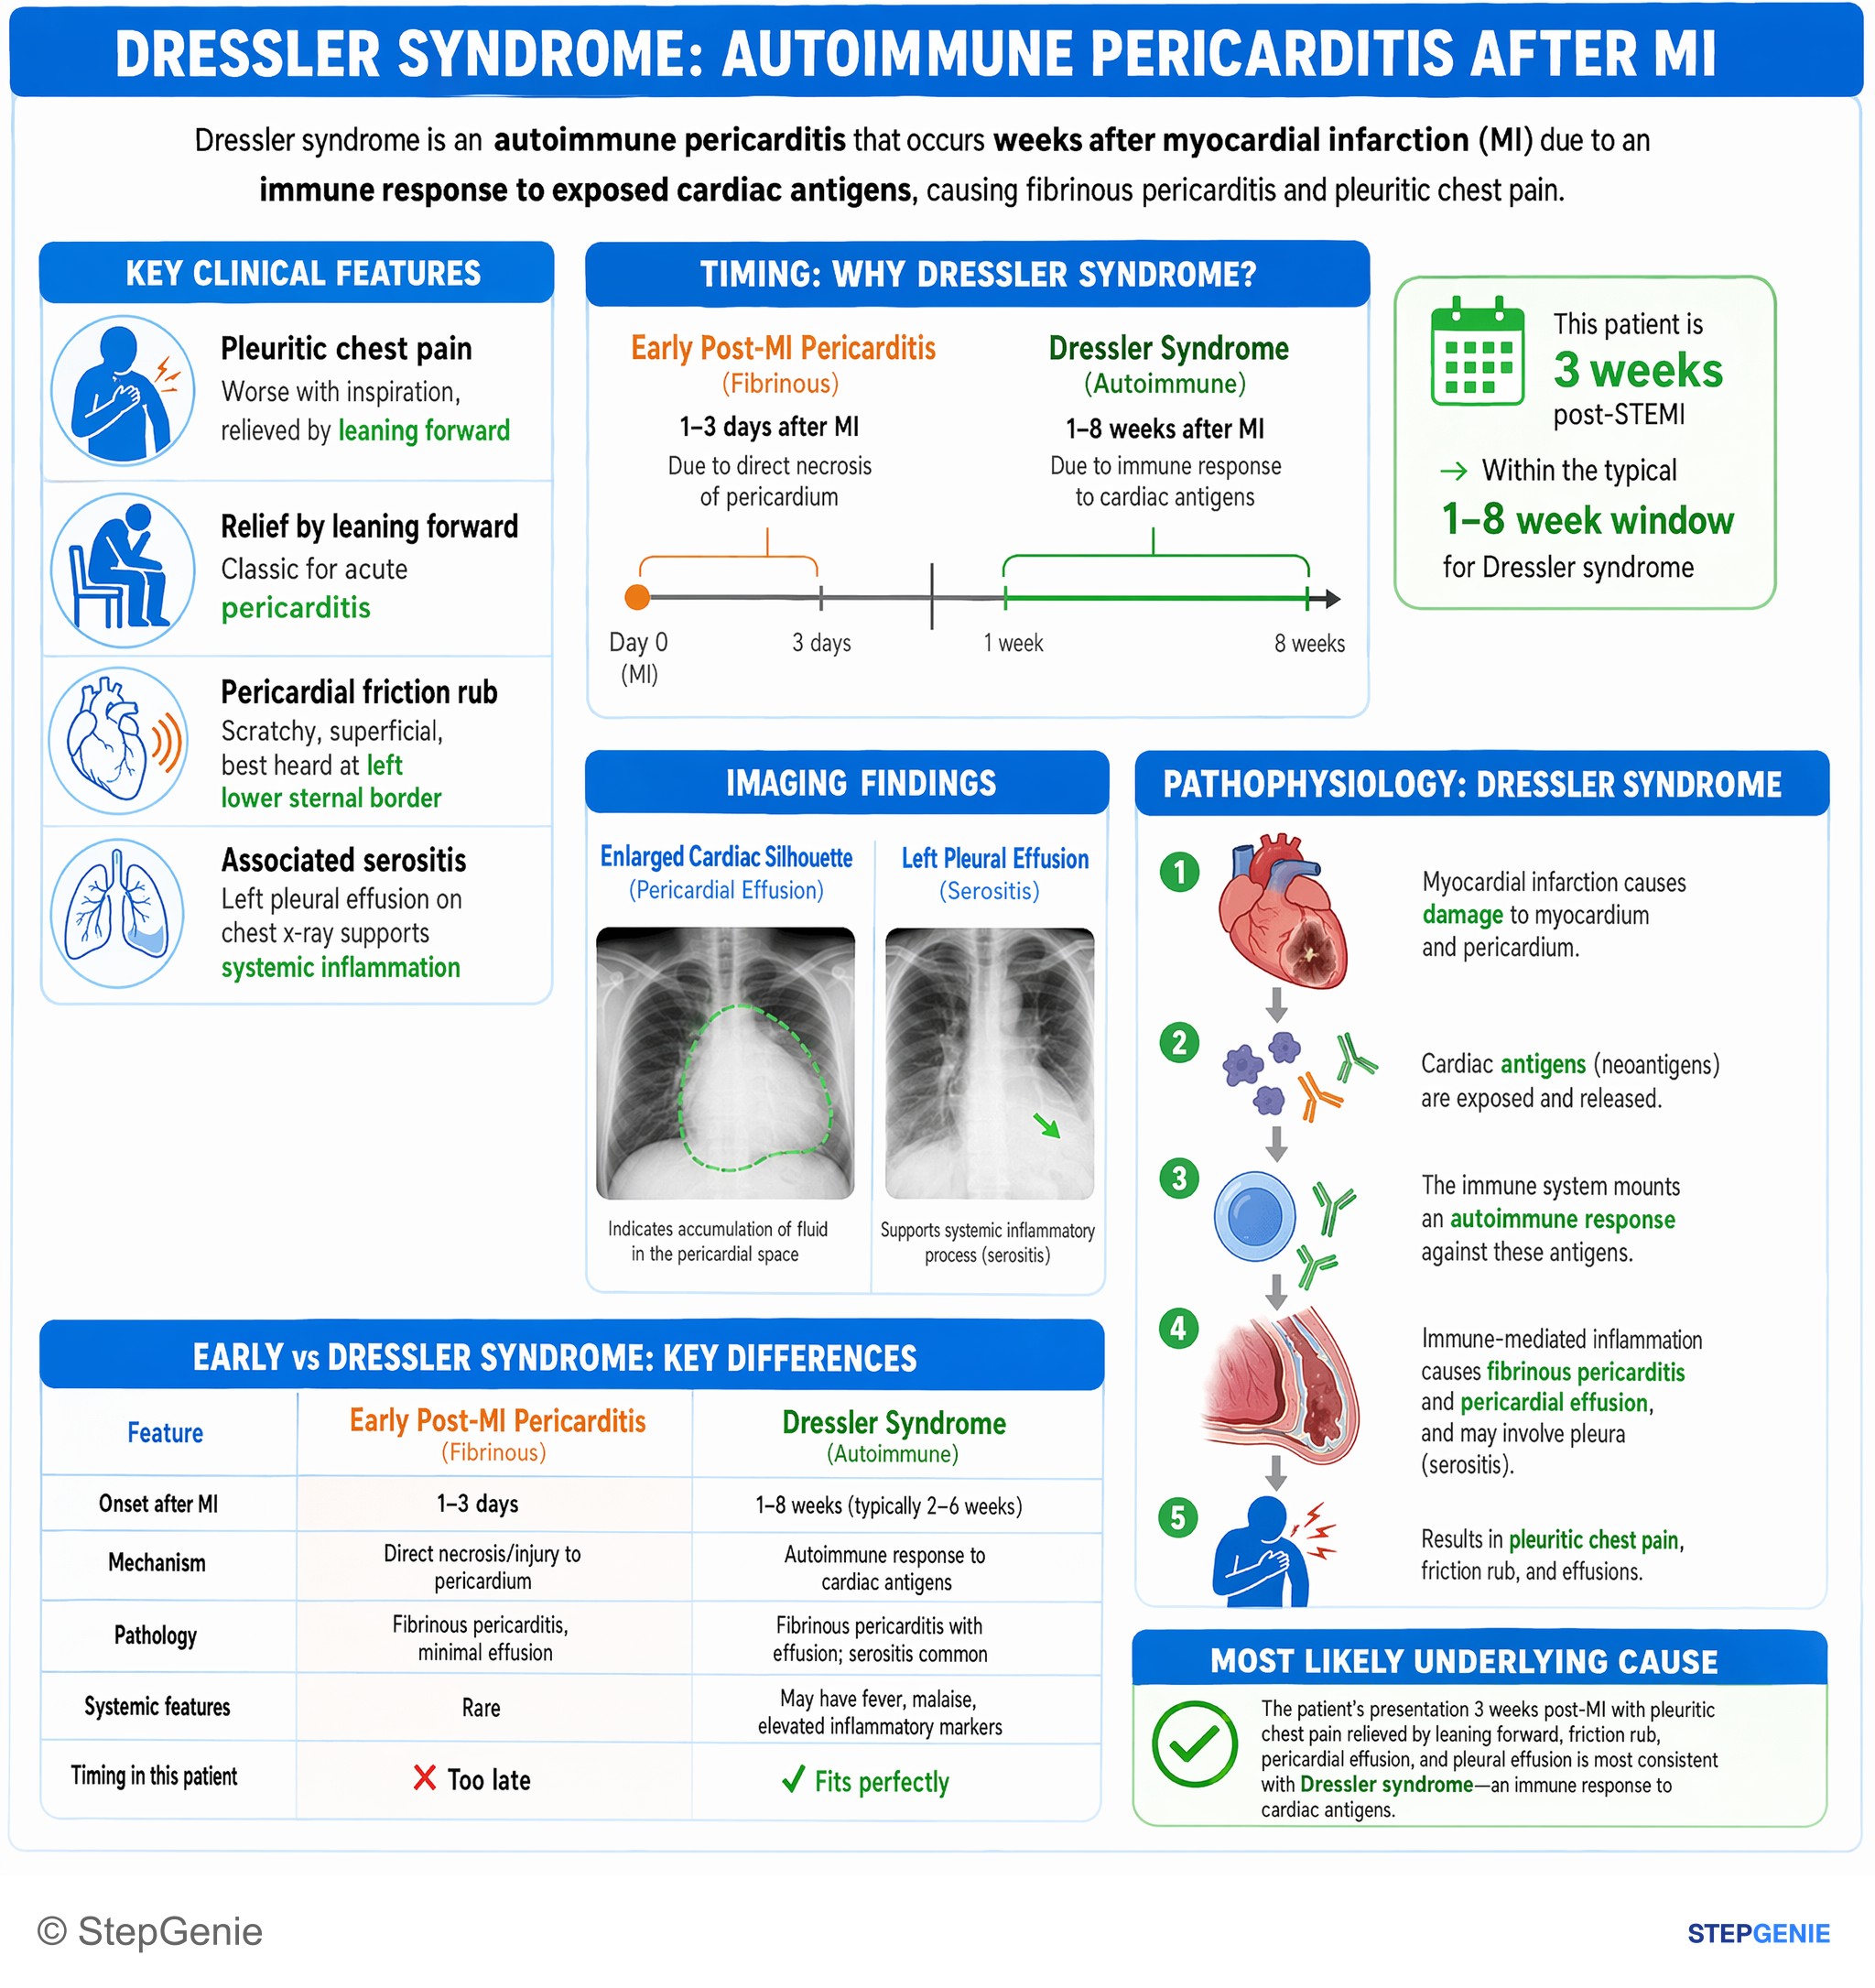
Dressler syndrome: autoimmune pericarditis weeks after MI due to immune response to exposed cardiac antigens causing fibrinous…
USMLE Step 1Frequently Asked Questions
What post-MI complication causes sudden collapse on day 5 with hypotension, JVD, and muffled heart sounds?
The classic diagnosis is left ventricular free wall rupture causing cardiac tamponade. Day 5 falls in the 3–14 day rupture window, when macrophages are clearing necrotic myocardium and the ventricular wall is at its softest. Sudden collapse with hypotension, distended neck veins, muffled heart sounds, and ultrasound showing pericardial effusion with right ventricular diastolic collapse points to tamponade from free wall rupture.
Why is the heart most likely to rupture 3 to 14 days after an MI?
Rupture is most likely 3 to 14 days after MI because macrophages are clearing dead myocardial tissue during that period, which weakens structural integrity. This is the window when the wall becomes softest, with a peak risk around day 5. That weakening sets up major mechanical complications such as free wall rupture, ventricular septal rupture, papillary muscle rupture, and pseudoaneurysm.
How do you tell early post-MI pericarditis from Dressler syndrome?
Early post-MI pericarditis occurs 1 to 3 days after a transmural MI, while Dressler syndrome appears weeks to months later. Early pericarditis is due to direct transmural inflammation and presents with pleuritic chest pain and a friction rub. Dressler syndrome is an autoimmune pericarditis caused by antibodies against exposed myocardial antigens and is associated with fever, malaise, pleuritic chest pain, and a friction rub.
How do you distinguish free wall rupture from papillary muscle rupture or VSD after an MI?
The key is the presentation, not just the timing, because all can occur in the 3–14 day rupture window. Free wall rupture causes tamponade physiology with hypotension, JVD, muffled heart sounds, and pericardial effusion. Papillary muscle rupture causes acute severe mitral regurgitation with pulmonary edema, hypotension, and a new loud systolic murmur. Ventricular septal rupture causes acute heart failure, hypotension, and a harsh holosystolic murmur at the left sternal border.
What is the most common cause of death in the first 24 hours after an MI?
Arrhythmia is the most common cause of death in the first 24 hours after an MI. This early period is marked by coagulative necrosis beginning, along with wavy fibers, edema, and hemorrhage. Acute heart failure and cardiogenic shock can also occur early, but when a question asks for the most common early fatal complication, arrhythmias are the key association.