You just finished a myocardial infarction question, felt good about recognizing post-MI complications… and then the stem pivots: fever, chest pain, and a pericardial friction rub weeks later. That’s where a lot of people start mixing up Dressler syndrome, post-MI pericarditis, and tamponade/rupture. This post is a “Q-bank breakdown” style walk-through: we’ll nail the correct diagnosis and then go line-by-line through classic distractors—because on Step, every answer choice is teaching you something.
Tag: Cardiovascular > Coronary & Ischemic Heart Disease
The vignette (classic Q-bank style)
A 62-year-old man presents with pleuritic chest pain and low-grade fever. He had an ST-elevation MI 3 weeks ago treated with PCI. Pain is worse when supine and improves when leaning forward. Exam reveals a pericardial friction rub. ECG shows diffuse ST-segment elevations with PR depressions. Troponin is not significantly elevated.
Most likely diagnosis? → Dressler syndrome
Why the correct answer is Dressler syndrome
What it is (one-liner)
Dressler syndrome is a delayed, autoimmune pericarditis that occurs weeks to months after myocardial injury (classically after MI, but also after cardiac surgery, trauma, or ablation).
Timing is the giveaway
- Early post-MI pericarditis: typically 1–3 days after a transmural MI
- Dressler syndrome: typically 2–8 weeks after MI (can be later)
Pathophysiology (the “why”)
Necrotic myocardium exposes antigens → immune system generates antibodies → immune complex deposition and inflammation of the pericardium and pleura.
Symptoms/signs you’re expected to recognize
- Fever
- Pleuritic chest pain (worse with inspiration, better leaning forward)
- Pericardial friction rub
- Often pericardial effusion
- Can be associated with pleuritis → pleural effusion
ECG pattern (high-yield)
Pericarditis classically shows:
- Diffuse ST elevation (often concave up)
- PR depression
- No territorial pattern like an MI (i.e., not limited to a coronary distribution)
Treatment (Step-relevant)
- NSAIDs (first-line)
- Colchicine (often added to reduce recurrence)
- Corticosteroids: can work but typically reserved (higher recurrence risk in idiopathic pericarditis; still may be used if refractory/contraindicated)
Pearl: After an MI, aspirin is often preferred among NSAIDs, because some NSAIDs can interfere with myocardial healing.
Rapid table: Dressler vs early post-MI pericarditis vs reinfarction
| Feature | Dressler syndrome | Early post-MI pericarditis | Reinfarction |
|---|---|---|---|
| Timing | Weeks–months after MI | 1–3 days after MI | Any time, often days |
| Mechanism | Autoimmune | Direct inflammation from adjacent necrosis | New ischemia/infarct |
| Fever | Common | Possible | Sometimes |
| ECG | Diffuse ST↑, PR↓ | Diffuse ST↑, PR↓ | ST changes in territory, may see new Q waves |
| Troponin | Usually not markedly elevated | May be mildly elevated from recent MI | New rise (key clue) |
| Chest pain | Pleuritic, positional | Pleuritic, positional | Pressure-like, exertional, not positional |
Now the real Step skill: dismantling the distractors
Below are the most common answer choices that try to “steal” this question.
Distractor 1: Early post-MI fibrinous pericarditis (1–3 days)
Why it tempts you
- Also causes pleuritic chest pain, friction rub, and diffuse ST elevations.
Why it’s wrong here
- The stem says 3 weeks after MI, which is too late for early post-MI pericarditis.
- Dressler is the delayed immune-mediated version.
High-yield phrasing:
- “2–3 days after transmural MI” → early pericarditis
- “Weeks later + fever” → Dressler
Distractor 2: Papillary muscle rupture → acute severe mitral regurgitation
Why it tempts you
This is a classic post-MI complication, and timing overlaps with “days after MI.”
What you would see instead
- 2–7 days post-MI (often inferoposterior MI; RCA/PDA territory)
- Acute pulmonary edema
- Hypotension/cardiogenic shock
- New loud holosystolic murmur at apex radiating to axilla
- Possible V waves on PCWP tracing
Why it’s wrong here
- Our patient has pleuritic positional pain + rub, not pulmonary edema or shock.
Distractor 3: Ventricular free wall rupture → cardiac tamponade
Why it tempts you
It’s a famous cause of sudden deterioration after MI.
What you would see instead
- 3–7 days post-MI (classically 5–14 days in some sources; think “about a week”)
- Sudden collapse, PEA arrest
- Tamponade signs: hypotension, JVD, muffled heart sounds (Beck triad)
- Pulsus paradoxus
- Echo: pericardial effusion with diastolic chamber collapse
Why it’s wrong here
- Patient is stable enough for a clinic-style vignette, with rub and diffuse ST elevations, not hemodynamic collapse.
Distractor 4: Left ventricular aneurysm (true aneurysm)
Why it tempts you
It’s a late complication—so students reach for it when they see “weeks later.”
What you would see instead
- Occurs weeks to months after MI (esp. anterior MI)
- Persistent ST elevations in the same leads as the original infarct (not diffuse)
- Can cause:
- Heart failure
- Ventricular arrhythmias
- Mural thrombus → embolic stroke
Why it’s wrong here
- LV aneurysm doesn’t cause fever or a pericardial rub.
- ST elevations are persistent and localized, not diffuse with PR depression.
Distractor 5: Ventricular septal rupture (VSD) after MI
Why it tempts you
Another “mechanical complication” classic in the first week.
What you would see instead
- 3–5 days post-MI
- Harsh holosystolic murmur at the left sternal border
- Biventricular failure, hypotension, shock
- Diagnosis: echo with color Doppler
Why it’s wrong here
- Again, the stem is screaming pericarditis, not a new murmur + shock syndrome.
Distractor 6: Pulmonary embolism
Why it tempts you
Pleuritic chest pain + tachycardia + recent hospitalization can push people toward PE.
What you would see instead
- Dyspnea is usually prominent
- Hypoxemia, tachycardia
- ECG may show sinus tachycardia, right heart strain, sometimes S1Q3T3 (not sensitive)
- No classic diffuse ST elevation + PR depression
- No friction rub (you might get pleural rub, but pericardial findings are different)
Why it’s wrong here
- The ECG and positional nature of pain point to pericarditis, plus the timing post-MI supports Dressler.
Distractor 7: Reinfarction (new MI)
Why it tempts you
Chest pain after a recent MI is always concerning.
What you would see instead
- Pain tends to be pressure-like, not positional/pleuritic
- New ischemic ECG changes in a coronary distribution
- New rise in troponin (serial measurement is key)
Why it’s wrong here
- The stem gives classic pericarditis ECG changes and suggests troponin is not newly rising.
High-yield Dressler facts (what Step wants you to “carry”)
- Cause: autoimmune response to myocardial antigens after injury
- Timing: weeks to months after MI (or after any myocardial injury)
- Symptoms: fever + pleuritic, positional chest pain + pericardial rub
- ECG: diffuse ST elevation + PR depression
- Treatment: NSAIDs ± colchicine (steroids if refractory/contraindicated)
- Complication: pericardial effusion (rarely progresses to tamponade)
Test-taking shortcuts (fast pattern recognition)
If you see:
- Post-MI + weeks later + fever + pleuritic chest pain + friction rub → Dressler
- Post-MI + 1–3 days + pericarditis findings → early fibrinous pericarditis
- Post-MI + 3–7 days + sudden shock/new murmur/PEA → think rupture complications
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
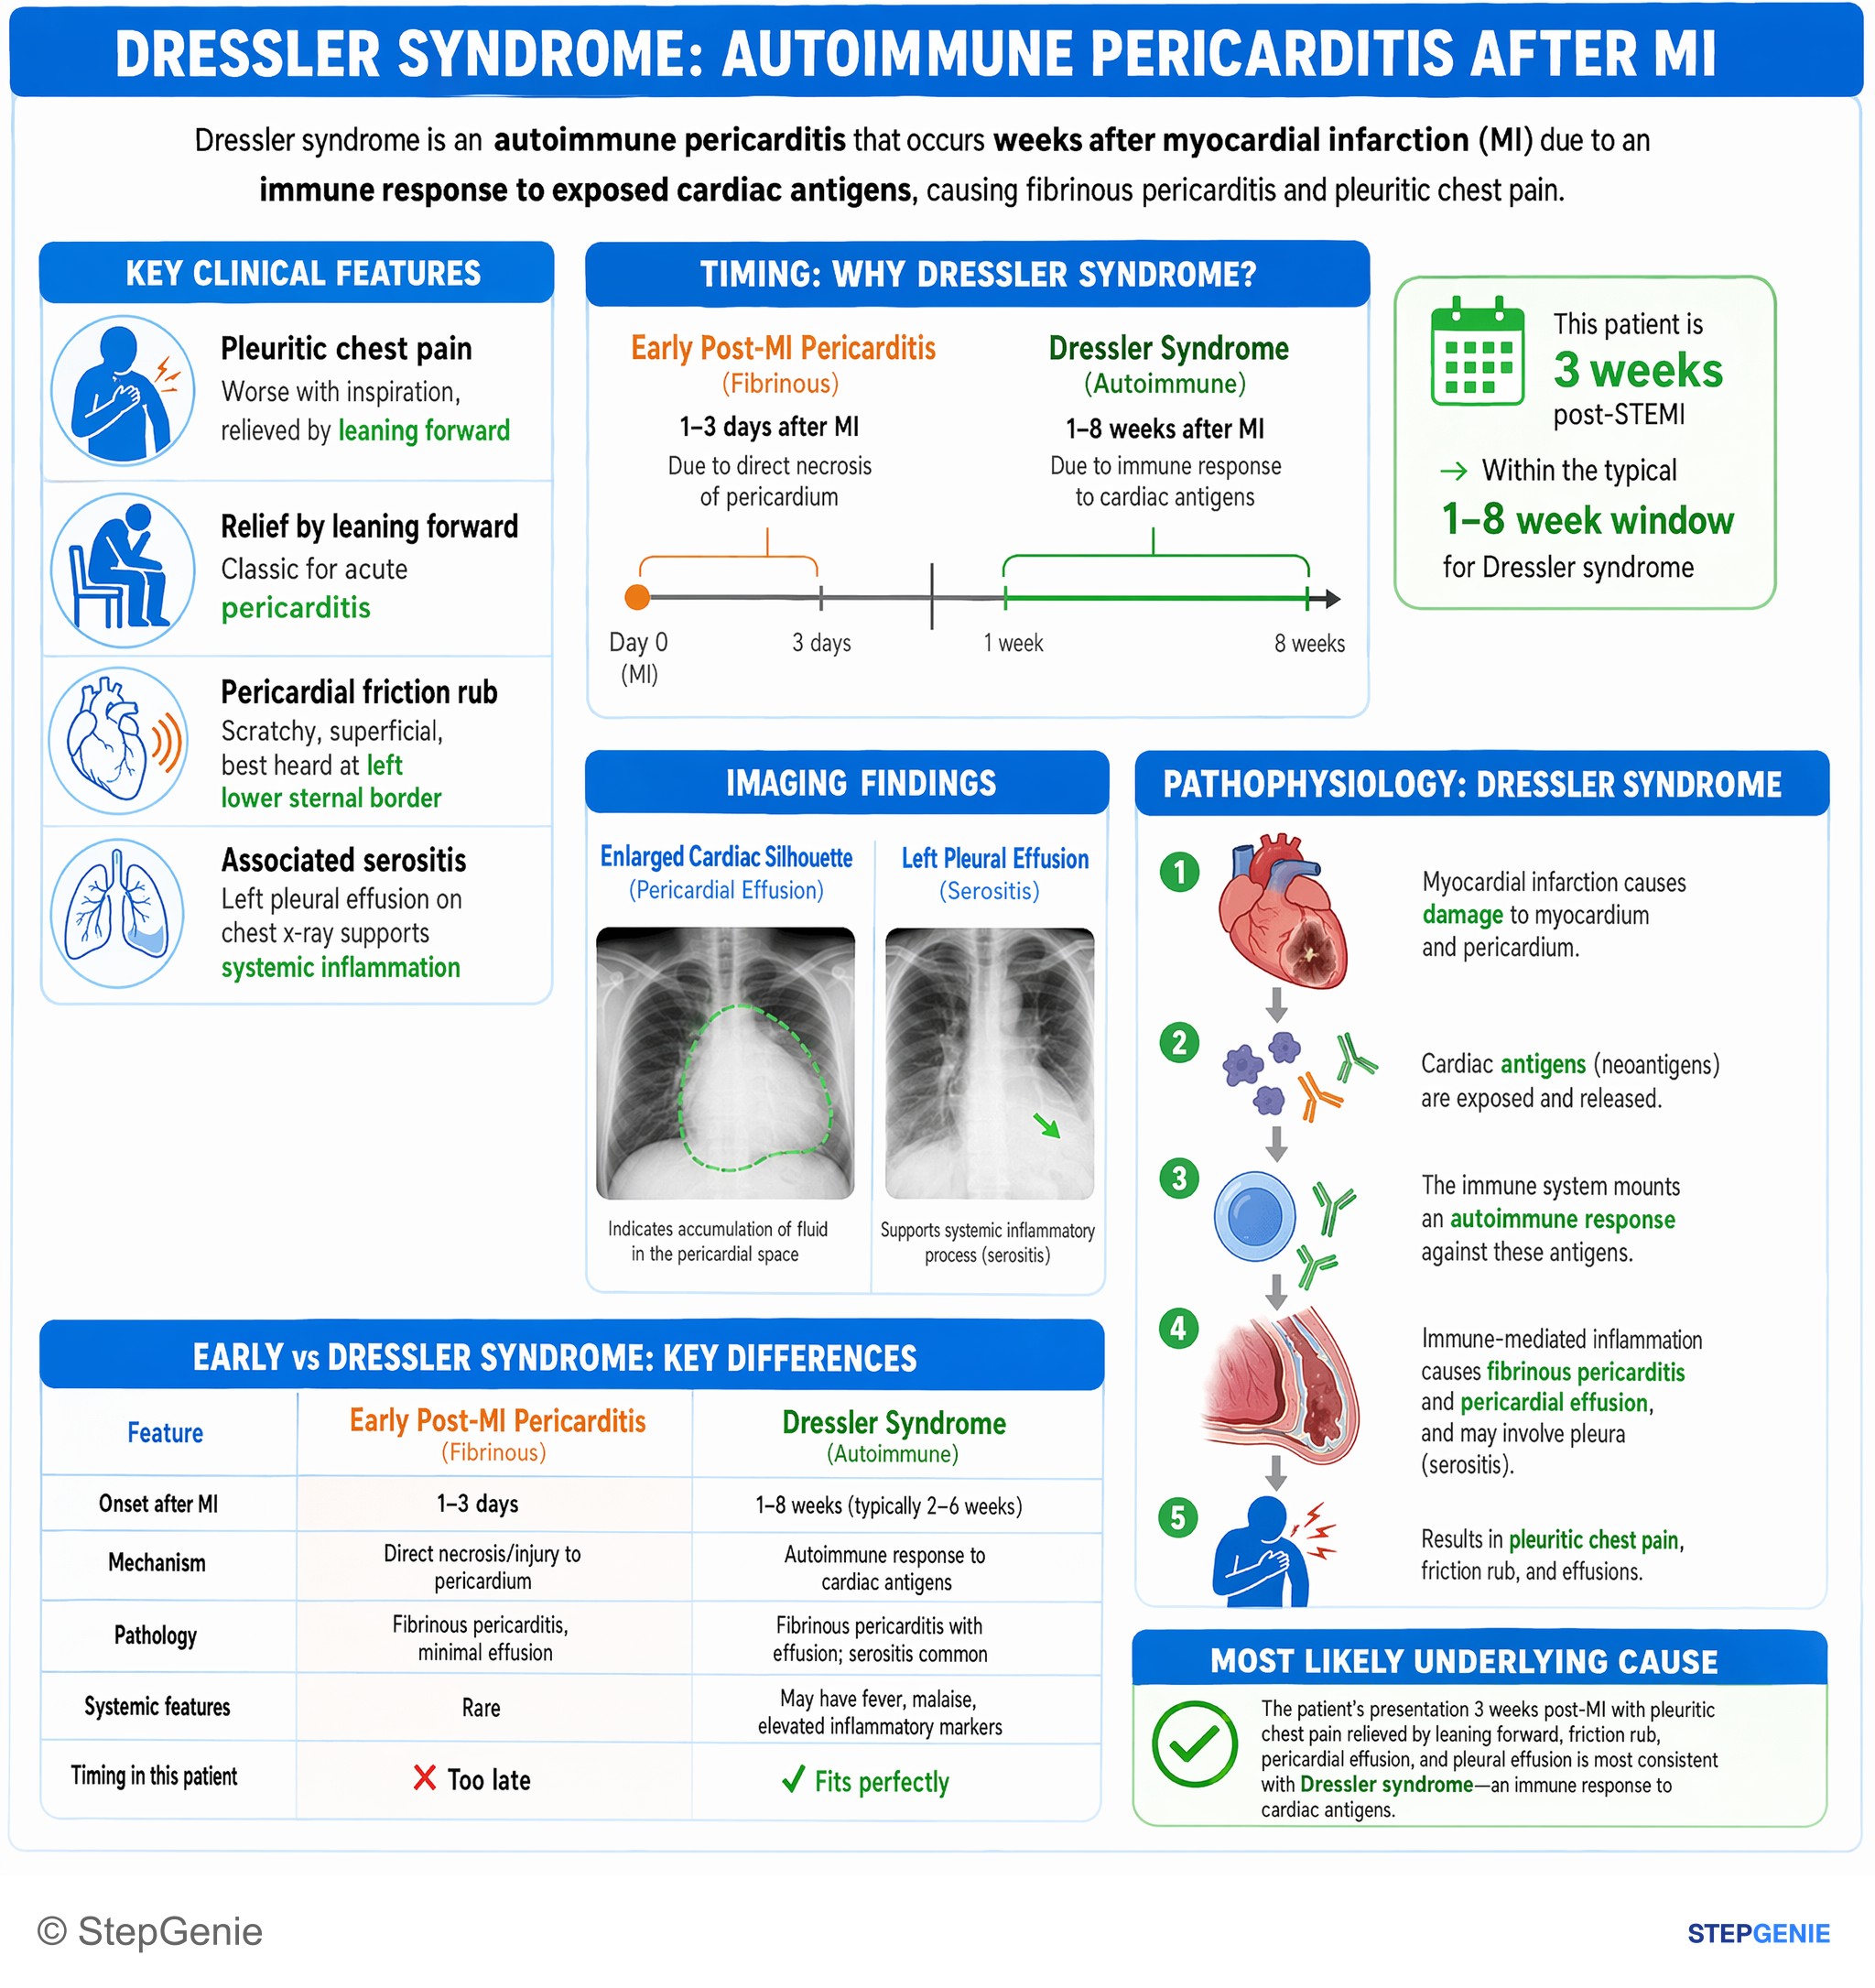
Dressler syndrome: autoimmune pericarditis weeks after MI due to immune response to exposed cardiac antigens causing fibrinous…
USMLE Step 1Frequently Asked Questions
How do you tell Dressler syndrome from early post-MI pericarditis?
The key difference is timing. Dressler syndrome is a delayed autoimmune pericarditis that usually appears 2 to 8 weeks after an MI, whereas early post-MI pericarditis typically occurs 1 to 3 days after a transmural MI. Both can cause pleuritic, positional chest pain, a pericardial friction rub, and diffuse ST elevations, but fever weeks later strongly points to Dressler syndrome.
Why does Dressler syndrome happen weeks after a myocardial infarction?
Dressler syndrome happens because it is an autoimmune reaction to myocardial injury. Necrotic myocardium exposes antigens, which leads the immune system to generate antibodies. That immune response causes immune complex deposition and inflammation in the pericardium and pleura. Because this is a delayed immune-mediated process rather than direct inflammation from the infarct itself, it typically shows up weeks to months later.
What ECG findings suggest Dressler syndrome instead of reinfarction?
Dressler syndrome classically shows diffuse ST-segment elevations with PR depressions, reflecting pericarditis rather than a new infarct in one coronary territory. Reinfarction is more likely to produce ST changes limited to a specific territory and may show new Q waves. Troponin is also usually not significantly elevated in Dressler syndrome, while reinfarction is suggested by a new rise in troponin.
What is the first-line treatment for Dressler syndrome after MI?
NSAIDs are first-line treatment for Dressler syndrome, and colchicine is often added to reduce recurrence. After an MI, aspirin is often preferred among NSAIDs because some other NSAIDs can interfere with myocardial healing. Corticosteroids can also work, but they are typically reserved for cases that are refractory or when standard therapy is contraindicated.
How do you tell Dressler syndrome from cardiac tamponade due to free wall rupture after MI?
Dressler syndrome presents with pleuritic, positional chest pain, low-grade fever, a pericardial friction rub, and diffuse ST elevations with PR depression, usually weeks after MI. Free wall rupture causing tamponade instead leads to sudden hemodynamic collapse, often with hypotension, jugular venous distension, muffled heart sounds, pulsus paradoxus, and possibly PEA arrest. The tamponade patient is unstable, unlike the classic stable Dressler vignette.