You’re mid-Q-bank grind, and a “simple” coronary anatomy question shows up—then suddenly every answer choice looks plausible. The trick isn’t memorizing a diagram; it’s linking arteries → territories → ECG leads → complications so you can eliminate distractors fast under test pressure.
Tag: Cardiovascular > Coronary & Ischemic Heart Disease
The Vignette (USMLE-Style)
A 62-year-old man with hypertension and hyperlipidemia develops sudden substernal chest pressure radiating to his left arm. ECG shows ST-segment elevations in leads II, III, and aVF. Shortly after arrival, he becomes hypotensive with clear lungs and has prominent JVP. Cardiac exam reveals bradycardia.
Which coronary artery is most likely occluded?
A. Left anterior descending (LAD) artery
B. Left circumflex (LCX) artery
C. Right coronary artery (RCA)
D. Posterior descending artery (PDA)
E. Obtuse marginal artery
Stepwise Approach (What the Stem Is Really Testing)
1) Localize the infarct by ECG leads
- II, III, aVF = inferior wall MI
- Inferior wall is most often supplied by the RCA (in right-dominant circulation, which is most people).
2) Use the hemodynamics to strengthen the call
- Hypotension + JVP up + clear lungs → think right ventricular infarct
- RV infarct strongly suggests a proximal RCA occlusion (because RCA supplies the RV free wall in many patients).
- Bradycardia also fits: RCA often supplies the SA node (and AV node via PDA in right dominance).
Correct answer: C. Right coronary artery (RCA)
Why the RCA Is the Best Answer (High-Yield Anatomy + Clinical Correlates)
Key territories (classic USMLE framing)
RCA supplies:
- Inferior wall of LV (often via PDA in right dominance)
- Right ventricle
- SA node (classically ~60%) and AV node (often via PDA, especially in right dominance)
High-yield complications of RCA/inferior MI
- Bradyarrhythmias (sinus bradycardia, AV block)
- Hypotension (especially with RV involvement)
- Right ventricular infarct clues:
- Elevated JVP, clear lungs
- Often worse with nitrates (preload dependent!)
- Confirm with right-sided ECG leads (V4R) showing ST elevation
USMLE favorite: Inferior MI + hypotension after nitrates = think RV infarct from proximal RCA occlusion.
Now, Destroy the Distractors (Each Choice Matters)
A. LAD — Tempting, but the leads don’t match
What LAD supplies:
- Anterior wall of LV
- Anterior 2/3 of interventricular septum
- Often the apex
ECG leads:
- ST elevation in V1–V4 (anteroseptal)
Classic complications:
- Ventricular arrhythmias
- Pump failure (large anterior MI)
- Septal rupture (VSD) risk (septal infarct)
- Bundle branch blocks (septal conduction system)
Why it’s wrong here:
- The stem gives inferior leads (II, III, aVF), not anterior leads.
B. LCX — Only if it’s a lateral MI (or left dominance)
What LCX supplies:
- Lateral wall of LV (via obtuse marginals)
- Can supply PDA in left-dominant circulation (less common)
ECG leads:
- Lateral: I, aVL, V5, V6
Why it’s wrong here (most likely):
- The ECG is inferior, and the vignette screams RCA with RV infarct (hypotension + JVP + clear lungs).
- Yes, LCX can cause inferior MI in left dominance, but NBME-style questions usually reward the most common anatomy unless dominance is specified.
Test-day tip: If they want LCX, they often mention left-dominant circulation or highlight posterior MI features without RCA node findings.
D. PDA — Sounds right for inferior MI… but it’s not the best first pick
What PDA supplies:
- Inferior wall (posterior/inferior LV)
- Posterior 1/3 of interventricular septum
Where PDA comes from (dominance):
- Right-dominant (most common): PDA from RCA
- Left-dominant: PDA from LCX
Why “PDA” is a distractor here:
- The question asks for the most likely occluded coronary artery—clinically and on USMLE, you usually name the parent vessel (RCA) in a classic inferior MI with node/RV findings.
- A proximal RCA occlusion can knock out RV branches and nodal branches before the PDA even matters.
When PDA would be the best answer:
- If the vignette is specifically about posterior septal infarct findings or the question explicitly targets dominance and names PDA as the culprit branch.
E. Obtuse marginal artery — A lateral wall branch (not inferior/RV)
What obtuse marginal (OM) supplies:
- Lateral wall of LV (branch of LCX)
ECG leads:
- Lateral: I, aVL, V5–V6
Why it’s wrong here:
- Doesn’t fit inferior lead ST elevations or RV infarct physiology.
Board-style clue: If they mention lateral MI + papillary muscle involvement, LCX/OM becomes more relevant.
One Table to Lock It In (Artery → Territory → Leads → Classic Complications)
| Vessel | Main territory | ECG leads | High-yield complications |
|---|---|---|---|
| LAD | Anterior wall, septum, apex | V1–V4 | Ventricular arrhythmias, HF, VSD, bundle branch blocks |
| RCA | Inferior wall, RV, SA/AV node (often) | II, III, aVF | Bradycardia, AV block, RV infarct (↑JVP, clear lungs) |
| LCX | Lateral wall; PDA if left-dominant | I, aVL, V5–V6 | Lateral MI, can cause inferior MI in left dominance |
| PDA | Inferior/posterior LV, posterior septum | Inferior ± posterior patterns | Posterior septal involvement; depends on dominance |
| OM (LCX branch) | Lateral LV | I, aVL, V5–V6 | Lateral wall ischemia patterns |
High-Yield Extras USMLE Loves
Coronary dominance (quick)
- Right-dominant (most common): PDA from RCA
- Left-dominant: PDA from LCX
- Dominance matters most for inferior/posterior MI patterns and AV node perfusion patterns.
Posterior MI pattern
Posterior MI can be sneaky because standard leads don’t directly look at the posterior wall.
- Suggestive ECG findings: ST depression in V1–V3 with tall R waves (mirror image)
- Confirm: posterior leads V7–V9 show ST elevation
- Often involves PDA territory (from RCA in right dominance, from LCX in left dominance)
Nitrates and RV infarct
- Nitrates reduce preload → can crash BP in RV infarct
- If inferior MI + hypotension + clear lungs: give IV fluids first, consider inotropes; be cautious with preload reducers.
Q-Bank Takeaway (How to Answer Fast Next Time)
- Read the ECG leads first → localize wall.
- Map wall to vessel using most common anatomy.
- Use “bonus clues” (bradycardia, JVP, clear lungs, new murmur) to confirm and eliminate distractors.
- If dominance is relevant, the stem will usually tell you—otherwise pick the classic.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
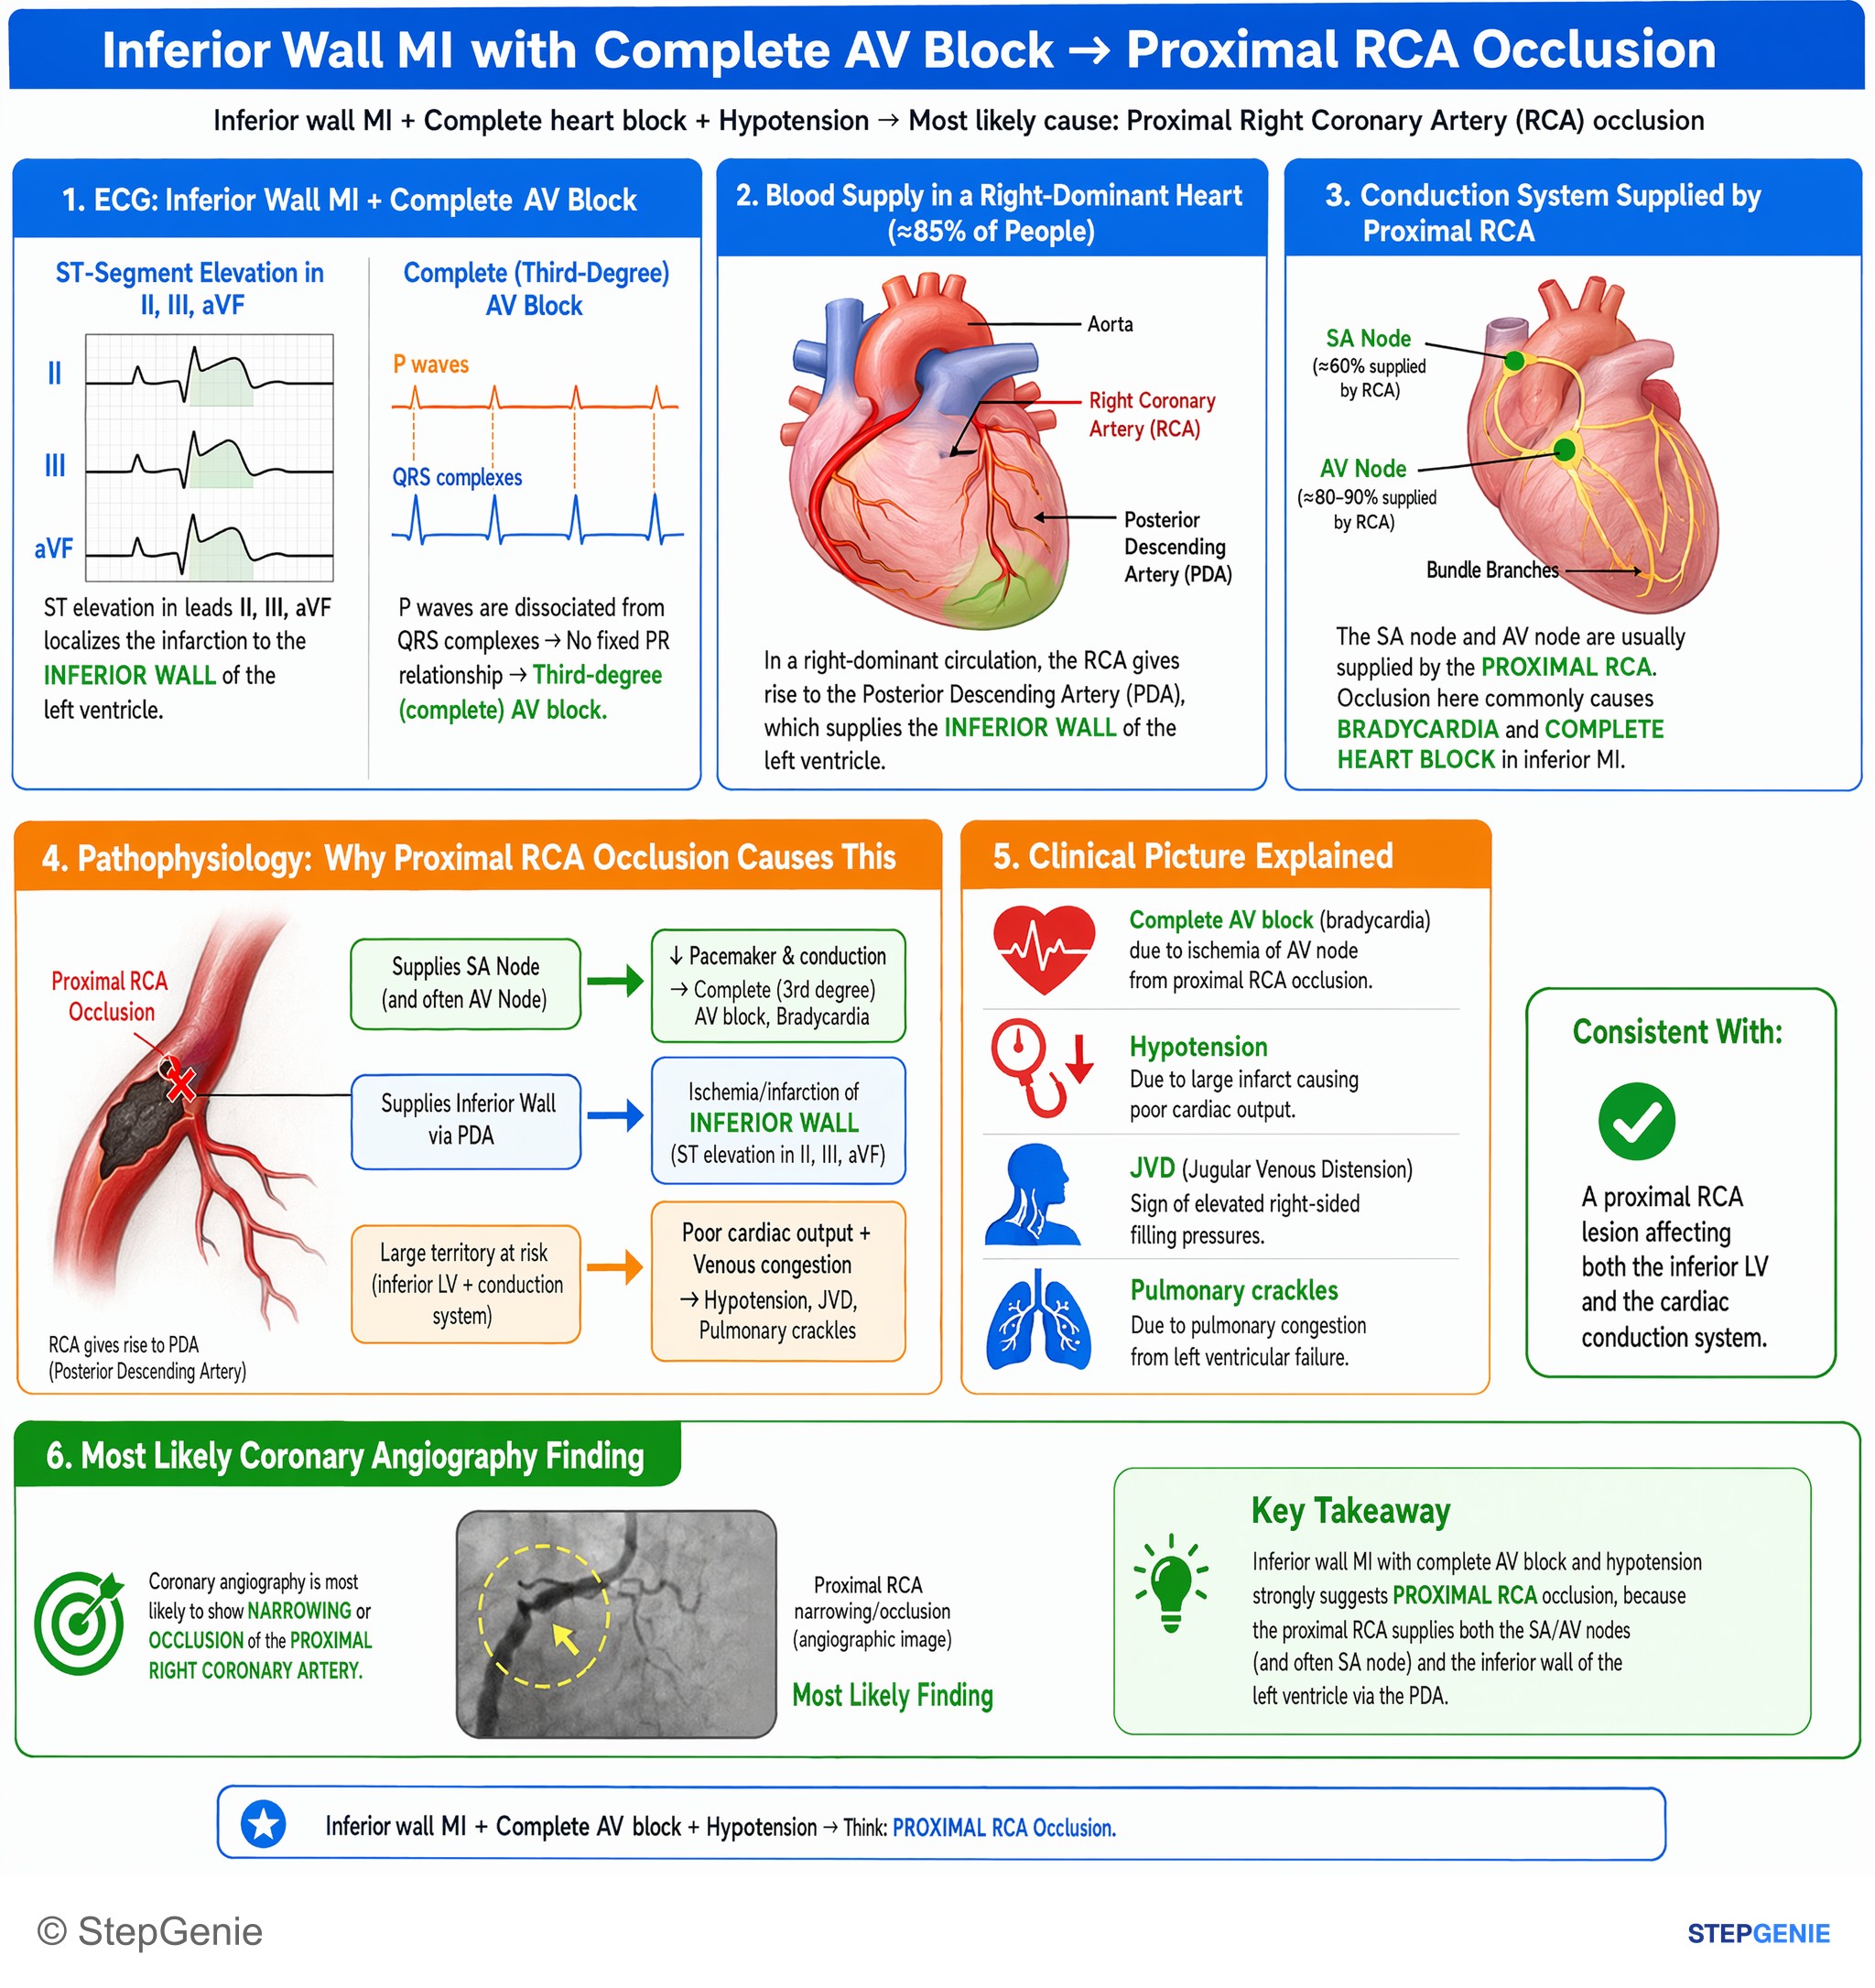
Inferior wall MI with complete AV block and hypotension implies proximal RCA occlusion supplying SA/AV nodes and inferior LV wall.
USMLE Step 1Frequently Asked Questions
Which artery is most likely occluded in inferior ST elevations with hypotension, high JVP, clear lungs, and bradycardia?
The right coronary artery is the most likely occluded vessel. ST elevations in leads II, III, and aVF localize an inferior wall MI, which is most often supplied by the RCA in right-dominant circulation. The added findings of hypotension, elevated JVP, clear lungs, and bradycardia point to right ventricular involvement and nodal ischemia, which strongly support a proximal RCA occlusion.
Why does an inferior MI from RCA occlusion often cause bradycardia and AV block?
RCA infarcts often cause bradycardia because the RCA commonly supplies the SA node and often contributes to AV node perfusion through the PDA in right-dominant circulation. When the RCA is occluded, especially proximally, nodal blood flow can be compromised. That is why inferior MI from RCA occlusion is classically associated with sinus bradycardia and AV conduction disturbances.
How do you tell RCA inferior MI from LAD MI on ECG?
You distinguish them by the lead pattern. RCA-related inferior MI produces ST elevations in leads II, III, and aVF, while LAD occlusion produces ST elevations in V1 through V4, reflecting anteroseptal infarction. The clinical complications also differ: RCA infarcts more often cause bradycardia and right ventricular infarct findings, whereas LAD infarcts are linked to ventricular arrhythmias, pump failure, septal rupture, and bundle branch blocks.
How do you tell an RCA infarct from LCX or obtuse marginal occlusion?
RCA infarct is favored when the ECG shows inferior leads and the patient has right ventricular infarct physiology such as elevated JVP, clear lungs, hypotension, and bradycardia. LCX and obtuse marginal vessels classically supply the lateral wall, which corresponds to leads I, aVL, V5, and V6. LCX can cause inferior MI in left-dominant circulation, but unless dominance is specified, the most likely answer is usually RCA.
Why is PDA a distractor instead of the best answer in a classic inferior MI question?
PDA is a distractor because USMLE-style questions usually want the parent coronary artery rather than the downstream branch when the presentation is classic. The PDA supplies the inferior wall, but in most people it arises from the RCA. A proximal RCA occlusion also explains the right ventricular and nodal findings, making RCA a better answer than PDA in an inferior MI with bradycardia and elevated JVP.