Complications of acute MI run on a clock: arrhythmias and pump failure in the first 24 hours, early fibrinous pericarditis at 1-3 days, mechanical ruptures (papillary muscle, ventricular septum, free wall) most often 3-5 days after a transmural infarct, and aneurysm, pseudoaneurysm, mural thrombus and post-cardiac injury (Dressler) syndrome over the following weeks. The highest-yield pairing is inferior MI → posteromedial papillary muscle rupture: that muscle has a single blood supply (the posterior descending artery, from the RCA or circumflex depending on dominance), and its rupture causes acute mitral regurgitation, flash pulmonary edema and shock. Mechanical complications are now rare (about 0.27% after STEMI), but in-hospital mortality approaches 50%; the patients at risk are those with large infarcts or late or absent reperfusion.
The vignette
A 64-year-old man is admitted 14 hours after the onset of crushing substernal chest pressure that he had tried to sleep off. ECG shows ST-segment elevation in leads II, III and aVF, and troponin I is markedly elevated. He undergoes PCI of an occluded right coronary artery. On hospital day 3 he suddenly becomes severely short of breath and anxious. Blood pressure is 86/58 mm Hg, pulse 122/min, respirations 30/min and oxygen saturation 86% on room air. He has cool, clammy extremities, crackles over both lung fields and a new holosystolic murmur at the apex radiating to the axilla. Which of the following is the most likely cause of his deterioration?
A. Free wall rupture with cardiac tamponade B. Interventricular septal rupture C. Papillary muscle rupture D. Early fibrinous pericarditis E. Left ventricular aneurysm F. Right ventricular infarction
Answer: C. Papillary muscle rupture
Four clues line up:
- Territory: inferior STEMI from an RCA occlusion. The posteromedial papillary muscle depends on one artery, while the anterolateral muscle has a dual supply (LAD diagonal branches and circumflex marginal branches). Posteromedial rupture is 6-12 times more common (StatPearls), and anterolateral rupture is extremely uncommon.
- Timing: day 3, inside the classic 3-5 day window after a transmural infarct.
- Hemodynamics: a normal-sized left atrium cannot absorb a sudden regurgitant jet, so left atrial pressure spikes and the lungs flood: flash pulmonary edema plus cardiogenic shock. Left ventricular ejection fraction is often normal or low-normal.
- Murmur: apical holosystolic murmur radiating to the axilla is mitral regurgitation. Beware: the murmur can be soft or absent, because left atrial and left ventricular pressures equalize quickly.
Confirm with echocardiography: transthoracic echo can miss partial rupture, and transesophageal echo is the most sensitive test. Stabilize with afterload reduction (IV nitroglycerin or nitroprusside if blood pressure allows), a vasopressor such as norepinephrine if hypotensive, and an intra-aortic balloon pump or other mechanical support as a bridge. Definitive treatment is emergency mitral valve surgery, preferably within 24 hours: usually replacement, with repair in selected cases (AHA 2021). Mortality is 10-40%. The physiology of acute versus chronic MR is in the mitral regurgitation breakdown.
Why every other answer is wrong
A. Free wall rupture with tamponade. Blood fills the pericardium and causes obstructive shock: hypotension, distended neck veins, pulsus paradoxus, muffled heart sounds and often sudden pulseless electrical activity (electromechanical dissociation), with no new murmur and no pulmonary edema. Timing overlaps (commonly 3-5 days, cases up to 2-3 weeks). Risk factors: age over 70, female sex, a first MI, hypertension and late fibrinolysis or delayed reperfusion. Bedside echo, then emergency surgery (ECMO can stabilize a patient who is collapsing); pericardiocentesis does not fix the tear and is relatively contraindicated because it can extend the rupture.
B. Interventricular septal rupture. Same window (3-5 days, with an earlier peak in the first 24 hours) and also shock, but the murmur is harsh, holosystolic and at the left lower sternal border, with a thrill in about half of patients. The left-to-right shunt loads both ventricles, and right heart catheterization shows an oxygen step-up from the right atrium to the right ventricle. Anterior MI (LAD) causes apical defects (about 60%); inferior MI causes basal defects, which are harder to repair. Treatment: afterload reduction and a balloon pump or LV assist device, then surgical or, in high-risk patients, percutaneous closure.
D. Early fibrinous pericarditis. It appears 1-3 days after MI (the rub usually begins at 24-96 hours) and is now rare in the reperfusion era: pleuritic, positional pain, a friction rub and diffuse ST elevation with PR depression in a stable patient. Treat with aspirin, adding colchicine if needed; high-dose or prolonged NSAIDs or glucocorticoids may impair infarct healing. It never explains shock with a new apical murmur.
E. Left ventricular aneurysm. A thin, scarred, dyskinetic wall, usually anterior or apical after LAD occlusion, that develops over days to months. It causes heart failure, ventricular tachycardia and mural thrombus with emboli, shows persistent ST elevation, rarely ruptures and is usually managed medically. Not a sudden day-3 collapse.
F. Right ventricular infarction. It accompanies inferior MI and presents as hypotension with ST elevation in right-sided leads. A failing right ventricle underfills the left, giving low output with high right-sided pressures, not flooded lungs or a new apical murmur. Treat with IV fluids (1-2 L of saline), dobutamine if needed, and no nitrates or diuretics, which cut preload and cause severe hypotension.
The timeline: what kills when
| Time after MI | Complication | Board clue | Key step |
|---|---|---|---|
| 0-24 hours | VT/VF, AV block, acute LV failure, cardiogenic shock, RV infarction | Sudden collapse; bradycardia with inferior MI; hypotension with inferior MI | Defibrillate; keep potassium above 4.0 mEq/L; pace symptomatic high-grade block |
| 1-3 days | Early fibrinous pericarditis | Pleuritic, positional pain, rub, diffuse ST elevation | Aspirin, colchicine |
| 3-5 days (first week or two) | Papillary muscle rupture, septal rupture, free wall rupture | New murmur plus shock, or sudden PEA | Echo, then emergency surgery |
| Days to months | True LV aneurysm, mural thrombus | Persistent ST elevation, dyskinetic bulge, embolic stroke | Echo; anticoagulate a confirmed thrombus |
| Weeks to years | LV pseudoaneurysm | Contained rupture with a narrow neck, often inferior or lateral | Urgent surgery |
| About 1-6 weeks | Post-cardiac injury (Dressler) syndrome | Fever, pericarditis, effusion, pleuritis | NSAID (high-dose aspirin), colchicine |
Older mnemonics push free wall rupture to days 7-14. Current sources (AHA 2021, StatPearls) put most ruptures at 3-5 days, so read the timeline as "ruptures cluster in the first week," not as a single day. Why the first week matters histologically is covered in the post-MI timeline breakdown.
Sort a new murmur after MI in 10 seconds
| Papillary muscle rupture | Septal rupture | Free wall rupture | |
|---|---|---|---|
| Usual infarct | Inferior or lateral (posteromedial muscle) | Anterior (apical septum) or inferior (basal septum) | Transmural, first MI, delayed reperfusion |
| Murmur | Apical holosystolic → axilla; may be soft or absent | Harsh holosystolic at the left lower sternal border, thrill in about half | None; muffled heart sounds |
| Hemodynamics | Flash pulmonary edema, shock | Biventricular failure, shock | Tamponade, PEA |
| Clinching test | Echo (TEE most sensitive) | Echo; O2 step-up RA → RV | Bedside echo |
| Mortality (AHA 2021) | 10-40% | 30-40% | Over 50% |
Memory hook: "MR = Mitral = Moist." Acute MR floods the lungs; a septal rupture sounds harsh at the sternal border; a ruptured free wall is silent and collapses.
Pericarditis after MI: early vs post-cardiac injury (Dressler)
| Early post-infarction pericarditis | Post-cardiac injury (Dressler) syndrome | |
|---|---|---|
| Timing | Rub starts 24-96 hours after MI | Usually 1-6 weeks; can be days to months |
| Mechanism | Inflammation of the pericardium overlying the infarct | Immune reaction to injured myocardium (antimyocardial antibodies) |
| Features | Pleuritic, positional pain, rub, diffuse ST elevation, PR depression | Fever, pericarditis, pericardial and pleural effusions, pulmonary infiltrates, joint pain, raised ESR and CRP |
| Treatment | Aspirin, colchicine | NSAIDs (aspirin 500-1000 mg every 6-8 hours), colchicine; steroids only if refractory; drain tamponade |
Naming: Dressler syndrome is also called post-MI syndrome. Current sources file it under post-cardiac injury syndrome (PCIS), the umbrella that also covers postpericardiotomy syndrome after cardiac surgery and pericarditis after other cardiac procedures. The 2025 ESC myocarditis and pericarditis guidelines discuss it in a dedicated PCIS section. Exam stems may still say "Dressler." Both forms are now uncommon in the reperfusion era. More practice: the Dressler syndrome breakdown.
Other complications to recognize
- Arrhythmias: VT or VF within 24 hours of primary PCI for STEMI occurs in about 9% (Merck); prophylactic lidocaine is not recommended. Mobitz I is common and usually self-limited with inferior MI; Mobitz II, or complete block with wide QRS complexes, usually signals a massive anterior MI (see the AV block cheat sheet). Atrial arrhythmias (atrial ectopic beats, atrial fibrillation and, less often, flutter) occur in about 10-20% (Merck).
- Cardiogenic shock: pump failure from a large infarct or any mechanical complication; see the cardiogenic shock guide.
- Mural thrombus: forms over akinetic anterior or apical wall (3.9% during the admission in one study of anterior MI treated with PCI); a confirmed thrombus is anticoagulated.
Terminology update: MI "types" in 2026
The Fifth Universal Definition of MI (ESC/ACC/AHA/World Heart Federation, 28 August 2026) replaced types 1-5 with three clinical types:
- Primary MI (old type 1, plus other acute coronary causes): atherothrombosis, spontaneous coronary artery dissection, coronary embolism, vasospasm, and restenosis, stent thrombosis or graft failure more than 30 days after a procedure.
- Secondary MI (old type 2 supply-demand mismatch): imbalance caused by another acute condition, such as tachyarrhythmia, hypotension, hypoxia or anemia.
- Procedure-related MI (old types 4 and 5): a coronary complication within 30 days of PCI, cardiac surgery or another cardiac procedure. Old type 3 (sudden death) was dropped.
Acute myocardial injury is defined as a rise and/or fall of troponin with at least one value above the sex-specific 99th percentile, and the STEMI and NSTEMI labels remain. Merck (updated July 2026) and older study materials still use "type 1" and "type 2," so know both vocabularies.
How USMLE tests it
- Anchor every stem on four things: time since MI, infarct territory, hemodynamics (wet lungs, tamponade or shunt) and murmur location.
- A quiet murmur does not exclude papillary muscle rupture; flash pulmonary edema after inferior MI is enough to suspect it.
- Sudden PEA with distended neck veins days after a first transmural MI: free wall rupture. Next step: bedside echo and emergency surgery.
- Hypotension after inferior MI without pulmonary edema: RV infarction. Give fluids, not nitrates.
- Rub on day 2: early pericarditis, not reinfarction. Fever, effusion and pleuritis weeks later: post-cardiac injury (Dressler) syndrome.
- Narrow-necked outpouching: pseudoaneurysm, which needs surgery.
- Mechanical complications are most likely with late presentation or no reperfusion, older age, female sex and a first MI. Territories are reviewed in the coronary artery anatomy breakdown.
Key takeaways
- 0-24 h: VT/VF and pump failure. 1-3 days: fibrinous pericarditis. 3-5 days: papillary muscle, septal and free wall rupture. Weeks: aneurysm, mural thrombus, Dressler; pseudoaneurysm can come weeks to years later.
- Posteromedial papillary muscle = single supply from the PDA (RCA or circumflex) → ruptures after inferior or lateral MI → acute MR, flash pulmonary edema, shock, sometimes with a soft murmur.
- Septal rupture = harsh left sternal border murmur, thrill, O2 step-up RA → RV.
- Free wall rupture = tamponade and PEA without a murmur.
- Pseudoaneurysm needs surgery; a true aneurysm is usually managed medically.
- Dressler syndrome is now framed as post-cardiac injury syndrome.
- Fifth Universal Definition (2026): primary, secondary and procedure-related MI.
Sources
- Complications of Acute Coronary Syndromes — Merck Manual Professional Edition (2026)
- Mechanical Complications of Acute Myocardial Infarction: A Scientific Statement From the American Heart Association — Circulation (2021), full-text copy
- Systems of Care and Team-Based Approach to the Management of Mechanical Complications Following Acute Myocardial Infarction — American Heart Association Professional Heart Daily (2026)
- Papillary Muscle Rupture — StatPearls, NCBI Bookshelf (2024)
- Postinfarction Ventricular Septal Rupture — StatPearls, NCBI Bookshelf (2026)
- Left Ventricular Rupture — StatPearls, NCBI Bookshelf (2024)
- Ventricular Aneurysm — StatPearls, NCBI Bookshelf (2023)
- Dressler Syndrome — StatPearls, NCBI Bookshelf (2023)
- Pericarditis after heart attack — MedlinePlus Medical Encyclopedia (2024)
- 2025 ESC Guidelines for the management of myocarditis and pericarditis — European Heart Journal (2025)
- Fifth Universal Definition of Myocardial Infarction (2026) — Global Heart, ESC/ACC/AHA/WHF (2026)
- Acute Myocardial Infarction (MI) — Merck Manual Professional Edition (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
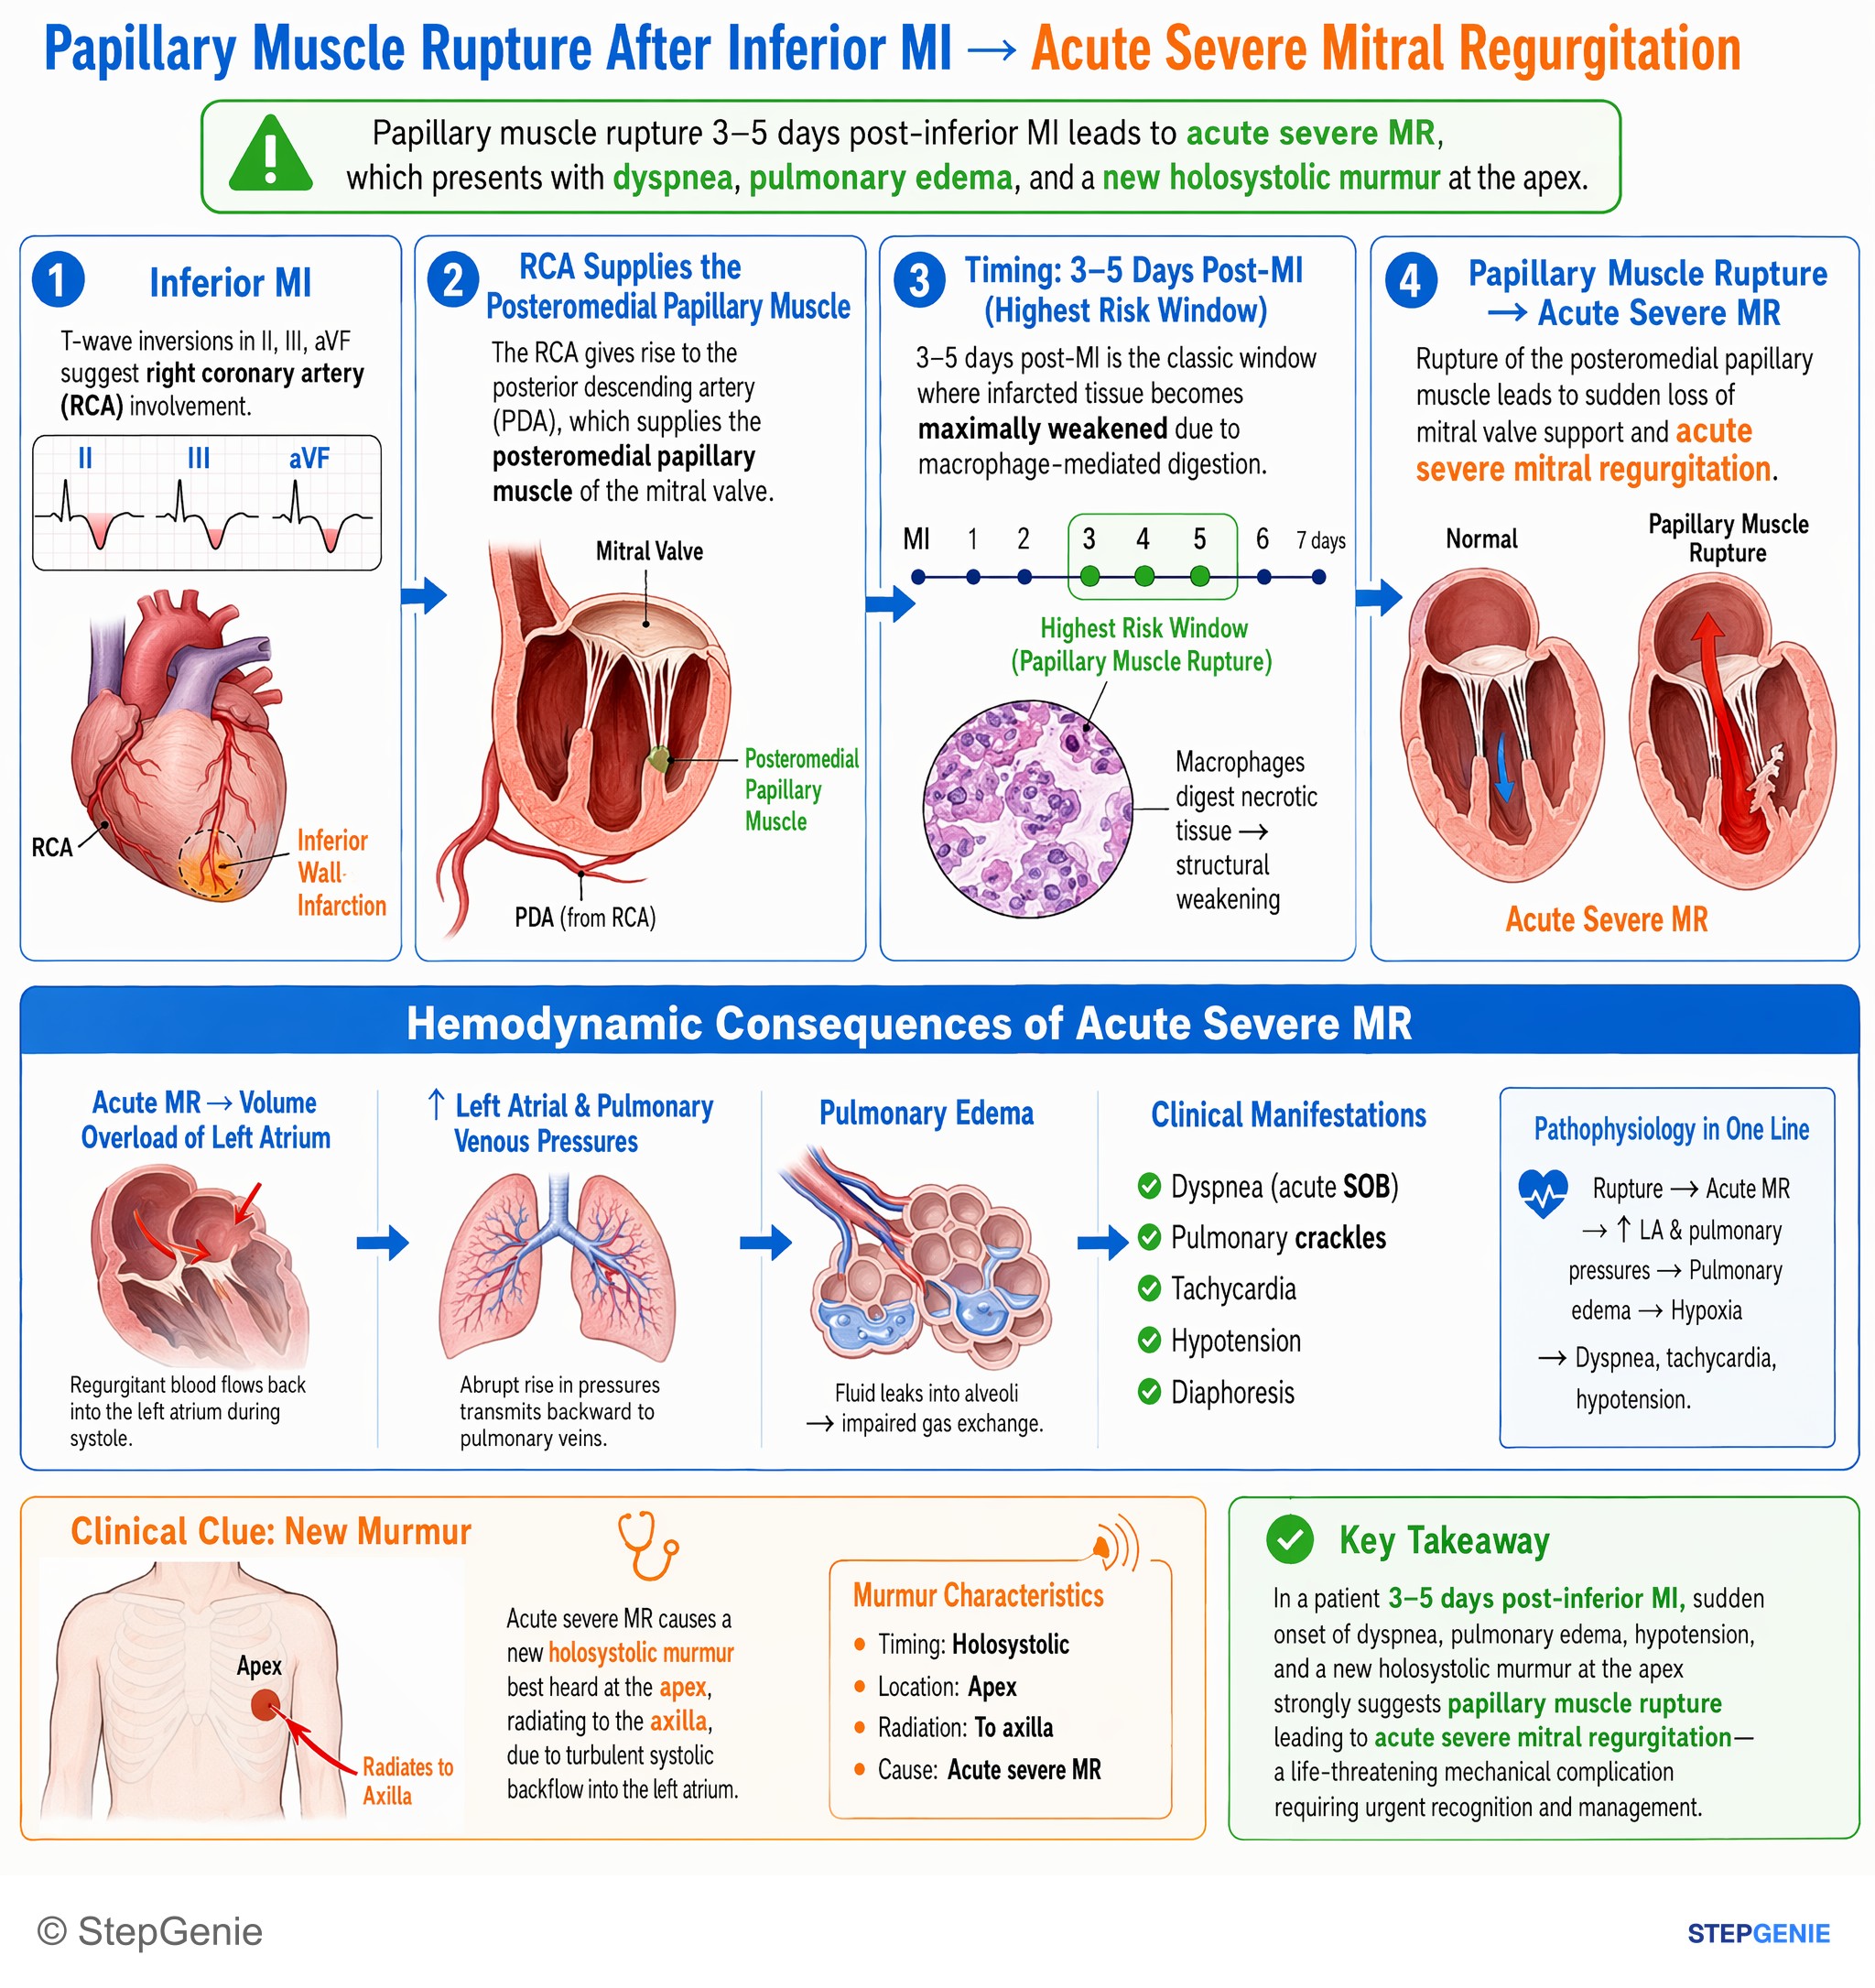
Papillary muscle rupture 3–5 days post-inferior MI → acute severe MR → dyspnea, pulmonary edema, new holosystolic murmur at apex.
USMLE Step 2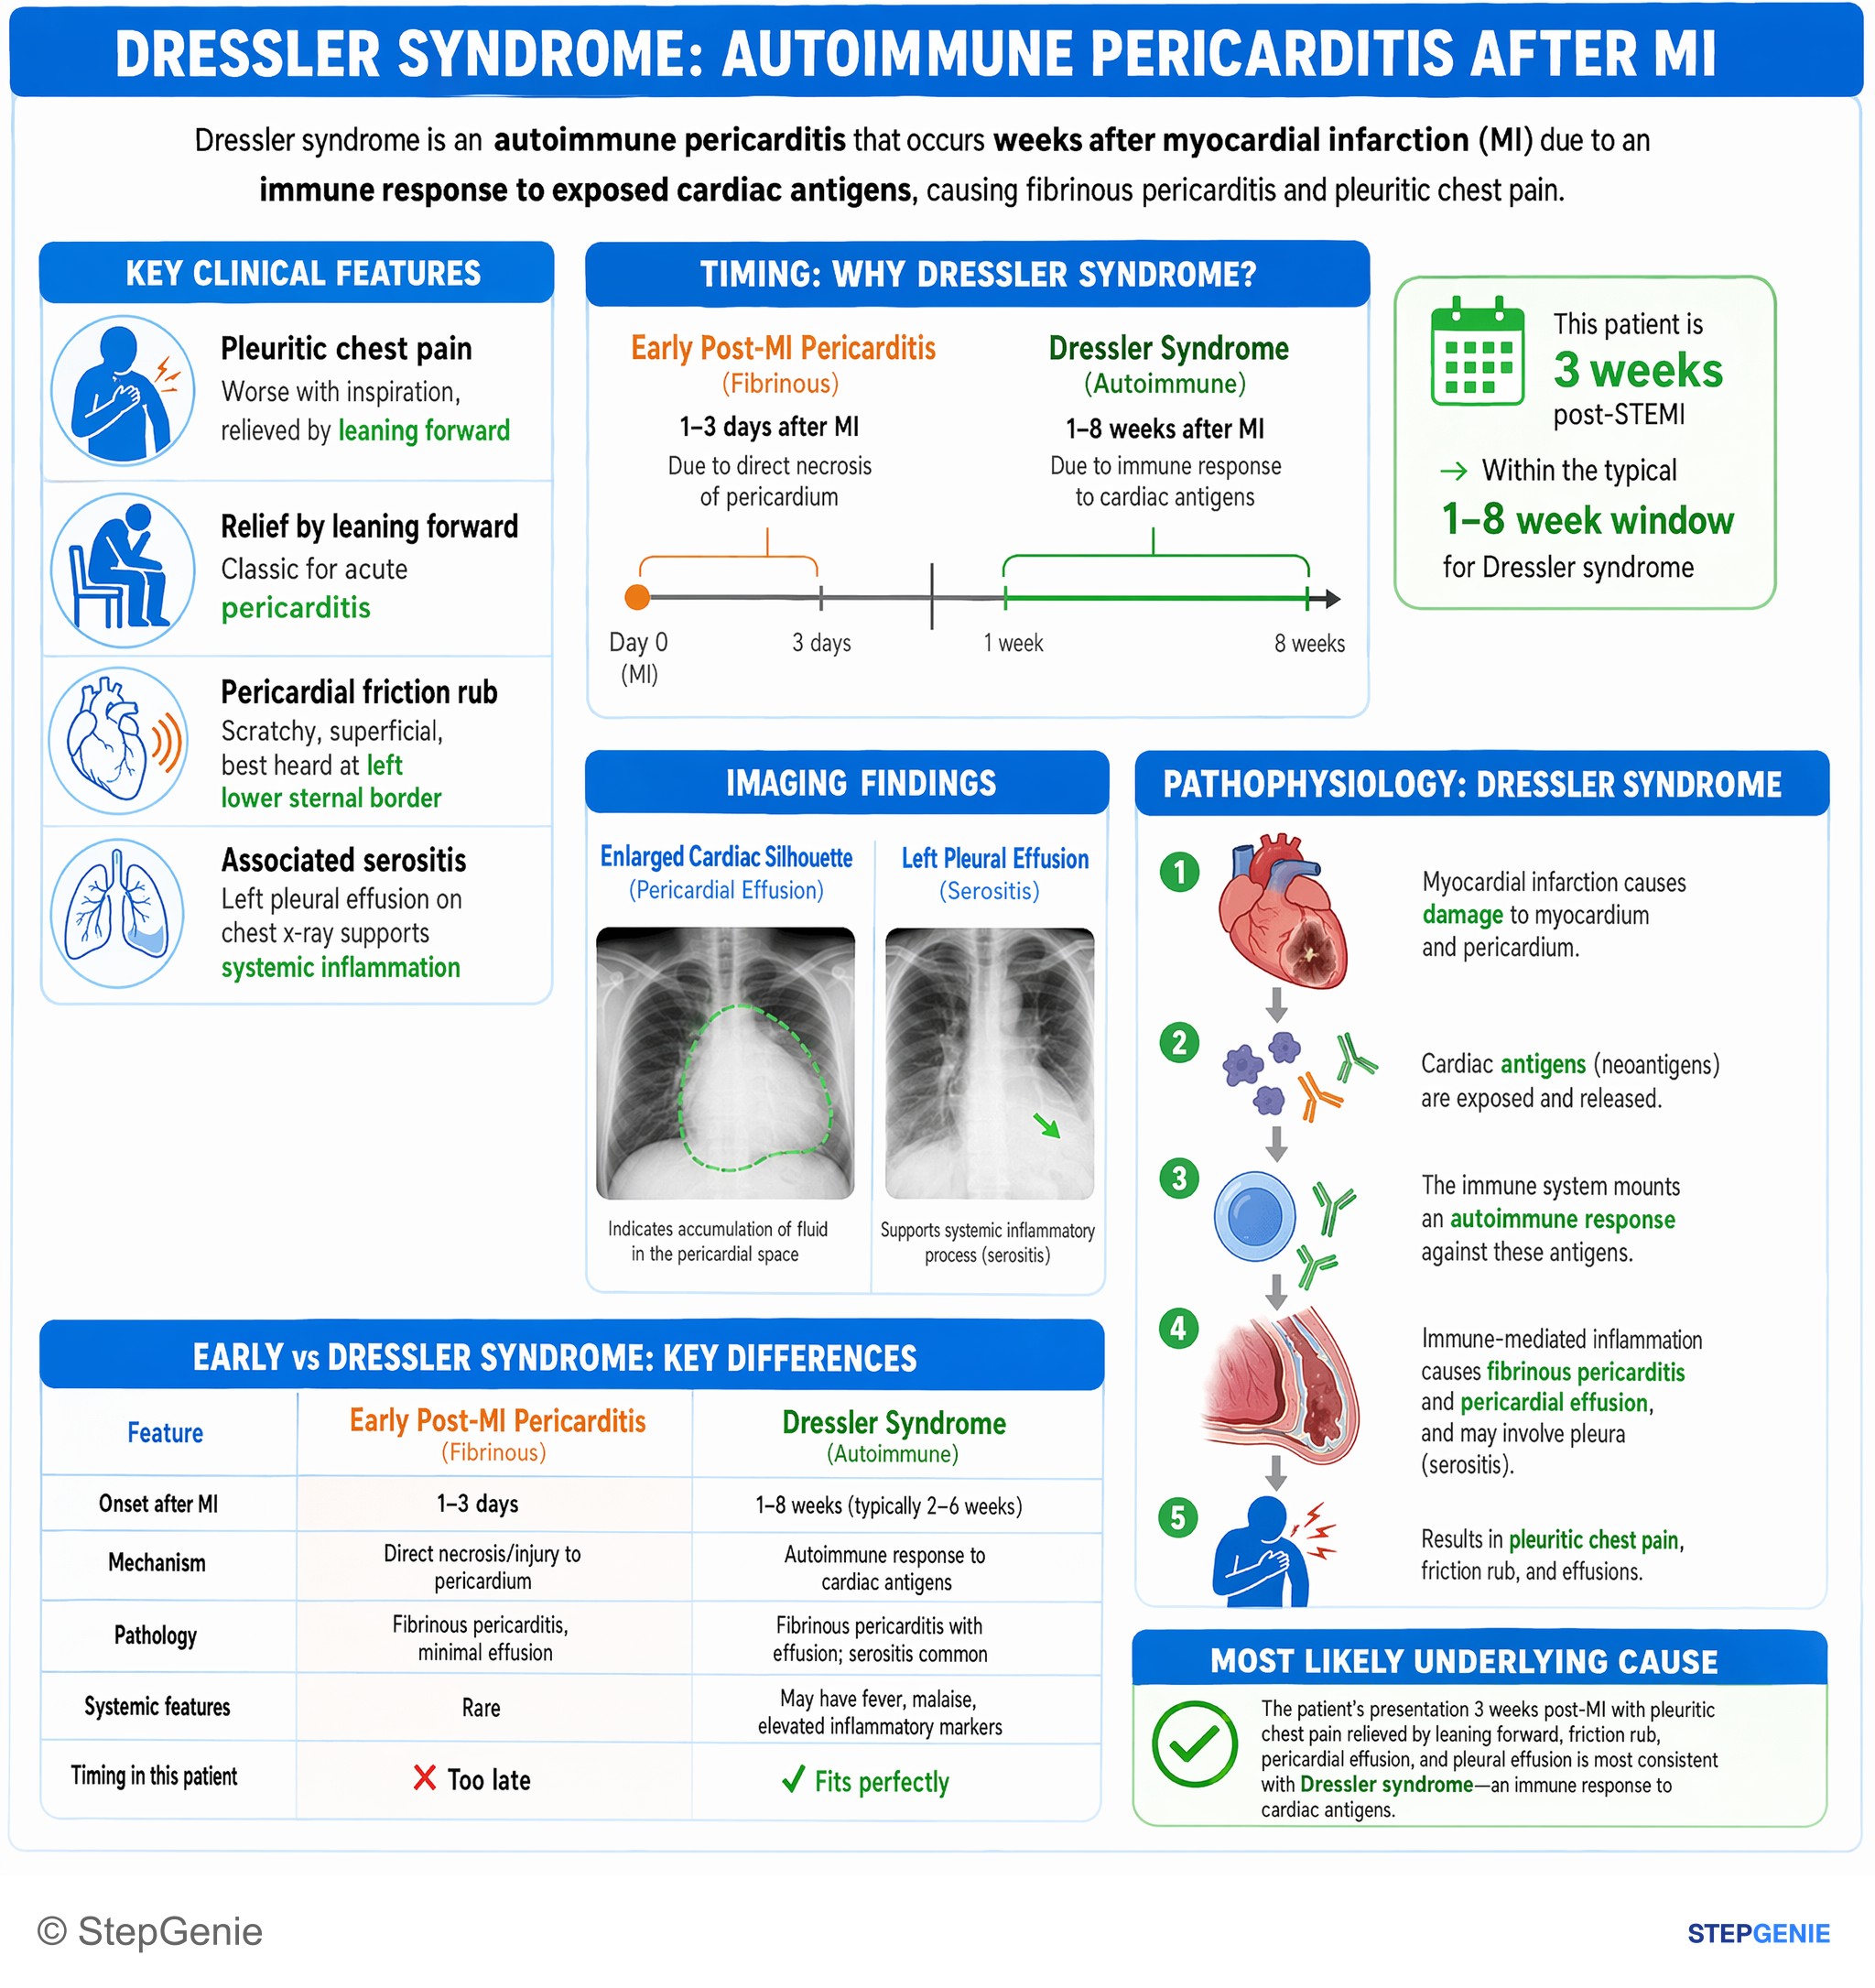
Dressler syndrome: autoimmune pericarditis weeks after MI due to immune response to exposed cardiac antigens causing fibrinous…
USMLE Step 1Frequently Asked Questions
What are the complications of acute MI by timeline?
In the first 24 hours the main killers are ventricular arrhythmias (VT and VF), AV block and pump failure with cardiogenic shock. Early fibrinous pericarditis appears at 1-3 days. Papillary muscle rupture, ventricular septal rupture and free wall rupture cluster 3-5 days after a transmural infarct. Over the following weeks come true left ventricular aneurysm, mural thrombus and post-cardiac injury (Dressler) syndrome at about 1-6 weeks, while a pseudoaneurysm can appear weeks to years later.
Why does the posteromedial papillary muscle rupture after an inferior MI?
The posteromedial papillary muscle has a single blood supply from the posterior descending artery, which comes from the right coronary artery in right-dominant hearts or the circumflex in left-dominant hearts. The anterolateral muscle has a dual supply from LAD diagonal and circumflex marginal branches, so it rarely ruptures. Posteromedial rupture is 6-12 times more common and follows inferior or lateral infarcts, causing acute mitral regurgitation with flash pulmonary edema and shock.
How do you tell papillary muscle rupture from ventricular septal rupture after MI?
Both cause a new holosystolic murmur and shock, usually 3-5 days after MI. Papillary muscle rupture gives an apical murmur radiating to the axilla, which can be soft or absent, with dramatic pulmonary edema from acute mitral regurgitation. Septal rupture gives a harsh murmur at the left lower sternal border, a thrill in about half of patients and biventricular failure from a left-to-right shunt. Echocardiography separates them, and right heart catheterization in septal rupture shows an oxygen step-up from the right atrium to the right ventricle.
What are the signs of free wall rupture after MI?
Free wall rupture fills the pericardium with blood and causes tamponade: sudden hypotension, distended neck veins, pulsus paradoxus, muffled heart sounds and often pulseless electrical activity, with no new murmur. It usually occurs 3-5 days after a transmural MI, especially a first MI in an older patient, a woman, or someone with delayed reperfusion. Bedside echocardiography confirms it, and emergency surgery is the treatment; pericardiocentesis does not fix the tear and is relatively contraindicated because it can extend the rupture. Mortality is over 50%.
Is Dressler syndrome the same as post-cardiac injury syndrome?
Current sources treat Dressler syndrome (post-MI syndrome) as one form of post-cardiac injury syndrome, an immune-mediated pericarditis that can also follow cardiac surgery (postpericardiotomy syndrome) and other cardiac procedures. After MI it usually appears 1-6 weeks later with fever, pleuritic chest pain, a friction rub, pericardial and pleural effusions and raised ESR and CRP. It is treated with an NSAID such as high-dose aspirin plus colchicine, with steroids reserved for refractory cases. It is distinct from early pericarditis at 1-3 days.
What changed in the Fifth Universal Definition of MI?
Published on 28 August 2026 by the ESC, ACC, AHA and World Heart Federation, it replaced the numbered types 1-5 with three clinical types. Primary MI is caused by an acute coronary pathology such as atherothrombosis, dissection, embolism or vasospasm. Secondary MI comes from a supply-demand imbalance due to another acute condition, such as anemia, hypoxia, hypotension or tachyarrhythmia. Procedure-related MI is a coronary complication within 30 days of PCI, cardiac surgery or another cardiac procedure. The old type 3 was dropped, and the terms STEMI and NSTEMI remain.