Wolff-Parkinson-White (WPW) is one of those Step 1 ECG diagnoses that’s very pattern-based: if you can recognize it quickly, you’ll also know exactly what not to give in treatment. The test writers love WPW because it ties together anatomy (accessory pathways), electrophysiology (reentry), and pharm (AV nodal blockers) in a single, highly predictable vignette.
What Is Wolff-Parkinson-White?
Definition: WPW is a pre-excitation syndrome caused by an accessory conduction pathway (classically the Bundle of Kent) that allows atrial impulses to bypass the AV node and reach the ventricles early.
Core idea: You’ve created a second route from atrium → ventricle, so the ventricle gets activated sooner than it should.
First Aid cross-reference: First Aid 2024 (Cardiovascular → Arrhythmias): WPW = short PR, delta wave, wide QRS, and risk of AVRT.
Pathophysiology (Mechanism You Need for Step Questions)
Normal conduction (for comparison)
SA node → atria → AV node (physiologic delay) → His-Purkinje → ventricles
The AV node’s delay is why the PR interval exists.
WPW conduction
Atria → ventricles via:
- AV node, and
- Accessory pathway (Kent)
Because the accessory pathway does not impose the usual AV nodal delay:
- PR interval becomes short (early ventricular activation)
- Ventricular myocardium begins depolarizing “cell-to-cell” at first → slurred upstroke (delta wave)
- Overall depolarization becomes less synchronized → wide QRS
Why it causes tachyarrhythmias
The accessory pathway sets up a reentry circuit called AV reentrant tachycardia (AVRT). Two classic patterns:
| Circuit Type | Conduction Pattern | ECG appearance |
|---|---|---|
| Orthodromic AVRT (most common) | Down AV node → up accessory pathway | Narrow-complex SVT (often no visible delta wave during tachycardia) |
| Antidromic AVRT | Down accessory pathway → up AV node | Wide-complex tachycardia (can mimic VT) |
High-yield step nuance: During tachycardia, the delta wave may not be obvious—don’t rely on it during SVT. The baseline ECG is where you catch classic WPW.
Clinical Presentation: How It Shows Up on Exams
Most patients are young and otherwise healthy, presenting with paroxysmal palpitations.
Common symptoms:
- Palpitations
- Lightheadedness, dizziness
- Chest discomfort
- Dyspnea
- Syncope (less common but important)
Classic tachyarrhythmias you should associate with WPW:
- AVRT (paroxysmal SVT)
- Atrial fibrillation (AF) with WPW — dangerous because accessory pathway can conduct very rapidly to the ventricles
Why AF + WPW is scary
The AV node normally filters atrial impulses. In WPW, AF impulses can travel through the accessory pathway with less “gatekeeping” → very fast ventricular rates → risk of degeneration into ventricular fibrillation.
Diagnosis: The ECG Findings You Must Recognize
Baseline ECG (sinus rhythm) in WPW
The classic triad:
- Short PR interval: typically < 120 ms
- Delta wave: slurred upstroke at the start of QRS
- Wide QRS: often > 120 ms
Quick visual memory:
- “PR is too short, QRS is too wide, and the upstroke is messy.”
Key ECG pearls for Step 1
- Short PR = early ventricular activation
- Delta wave = ventricular myocardium is being activated abnormally early (slow cell-to-cell spread before Purkinje takes over)
- Wide QRS = fusion of early abnormal activation + later normal conduction
Differentials (High-Yield ECG Comparisons)
| Condition | PR interval | QRS | Hallmark |
|---|---|---|---|
| WPW | Short | Wide | Delta wave |
| LGL syndrome (rare; less tested) | Short | Normal | No delta wave |
| Bundle branch block | Normal | Wide | No delta wave; QRS morphology consistent with RBBB/LBBB |
| VT | N/A | Wide | AV dissociation, capture/fusion beats (not always present) |
Test writer trick: Antidromic AVRT can be a regular wide-complex tachycardia. If you’re told the patient has known WPW or has baseline delta waves, that pushes you away from VT.
Treatment: The “What to Give” and “Never Give” Lists
Treatment depends on the rhythm.
1) Stable orthodromic AVRT (regular narrow-complex SVT)
Treat like typical SVT:
- Vagal maneuvers
- Adenosine (often used for acute termination)
(Caveat: When you are confident it’s regular narrow-complex SVT and not AF with WPW.)
2) Atrial fibrillation with WPW (irregular wide-complex tachycardia)
This is the board-favorite danger zone.
Give:
- Procainamide (classic Step answer)
- Ibutilide (another option you may see)
- Synchronized cardioversion if unstable
Avoid (contraindicated): AV nodal blockers These can increase conduction down the accessory pathway and worsen ventricular rate:
- Adenosine
- Beta-blockers
- Non-DHP calcium channel blockers (verapamil, diltiazem)
- Digoxin
- (Often also amiodarone is avoided in many teaching settings for AF + WPW questions; Step exams classically steer you to procainamide.)
Why AV nodal blockers are dangerous (the mechanism)
Blocking the AV node “forces” more impulses to travel down the accessory pathway → even faster ventricular response → VF risk.
3) Definitive therapy
- Radiofrequency catheter ablation of the accessory pathway (curative in many patients)
First Aid cross-reference: First Aid 2024 (Arrhythmias): WPW management emphasizes ablation and procainamide for AF with WPW; avoid AV nodal blockers.
High-Yield Associations & Board-Style Clues
Vignette clues that scream WPW
- Teen/young adult with episodic palpitations
- Baseline ECG shows short PR + delta wave + wide QRS
- Episodes triggered by exertion, caffeine, stimulants
- “Irregularly irregular wide-complex tachycardia” → think AF with WPW
Congenital/clinical associations
- Can be associated with Ebstein anomaly (downward displacement of tricuspid valve)
- Right atrial enlargement, tricuspid regurgitation, arrhythmias
- May be found incidentally on ECG in asymptomatic patients
Rapid Review Table (Step 1 “Lock It In”)
| Category | High-yield takeaways |
|---|---|
| Definition | Accessory pathway (Bundle of Kent) bypasses AV node → pre-excitation |
| Baseline ECG | Short PR, delta wave, wide QRS |
| Common arrhythmia | AVRT (paroxysmal SVT) |
| Dangerous rhythm | AF with WPW → can lead to VF |
| Treat AF + WPW | Procainamide (or cardioversion if unstable) |
| Avoid | AV nodal blockers (adenosine, BB, verapamil/diltiazem, digoxin) |
| Definitive therapy | Catheter ablation |
A Quick “If You See This, Do That” Algorithm
-
WPW pattern on baseline ECG (short PR, delta wave, wide QRS)
→ counsel, consider EP referral; ablation if symptomatic/high risk -
Regular narrow-complex tachycardia in a WPW patient (likely orthodromic AVRT)
→ vagal maneuvers → adenosine -
Irregular wide-complex tachycardia (think AF + WPW)
→ procainamide (stable) or synchronized cardioversion (unstable)
→ do NOT give AV nodal blockers
Common Exam Pitfalls
- Mistaking AF + WPW for “just AF” and giving diltiazem/metoprolol: that’s the classic wrong answer.
- Assuming all wide-complex tachycardias are VT: if the stem hints WPW history or shows baseline delta waves, consider antidromic AVRT or AF with WPW.
- Looking for delta wave during tachycardia: it may disappear in orthodromic AVRT; use the baseline ECG or history.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
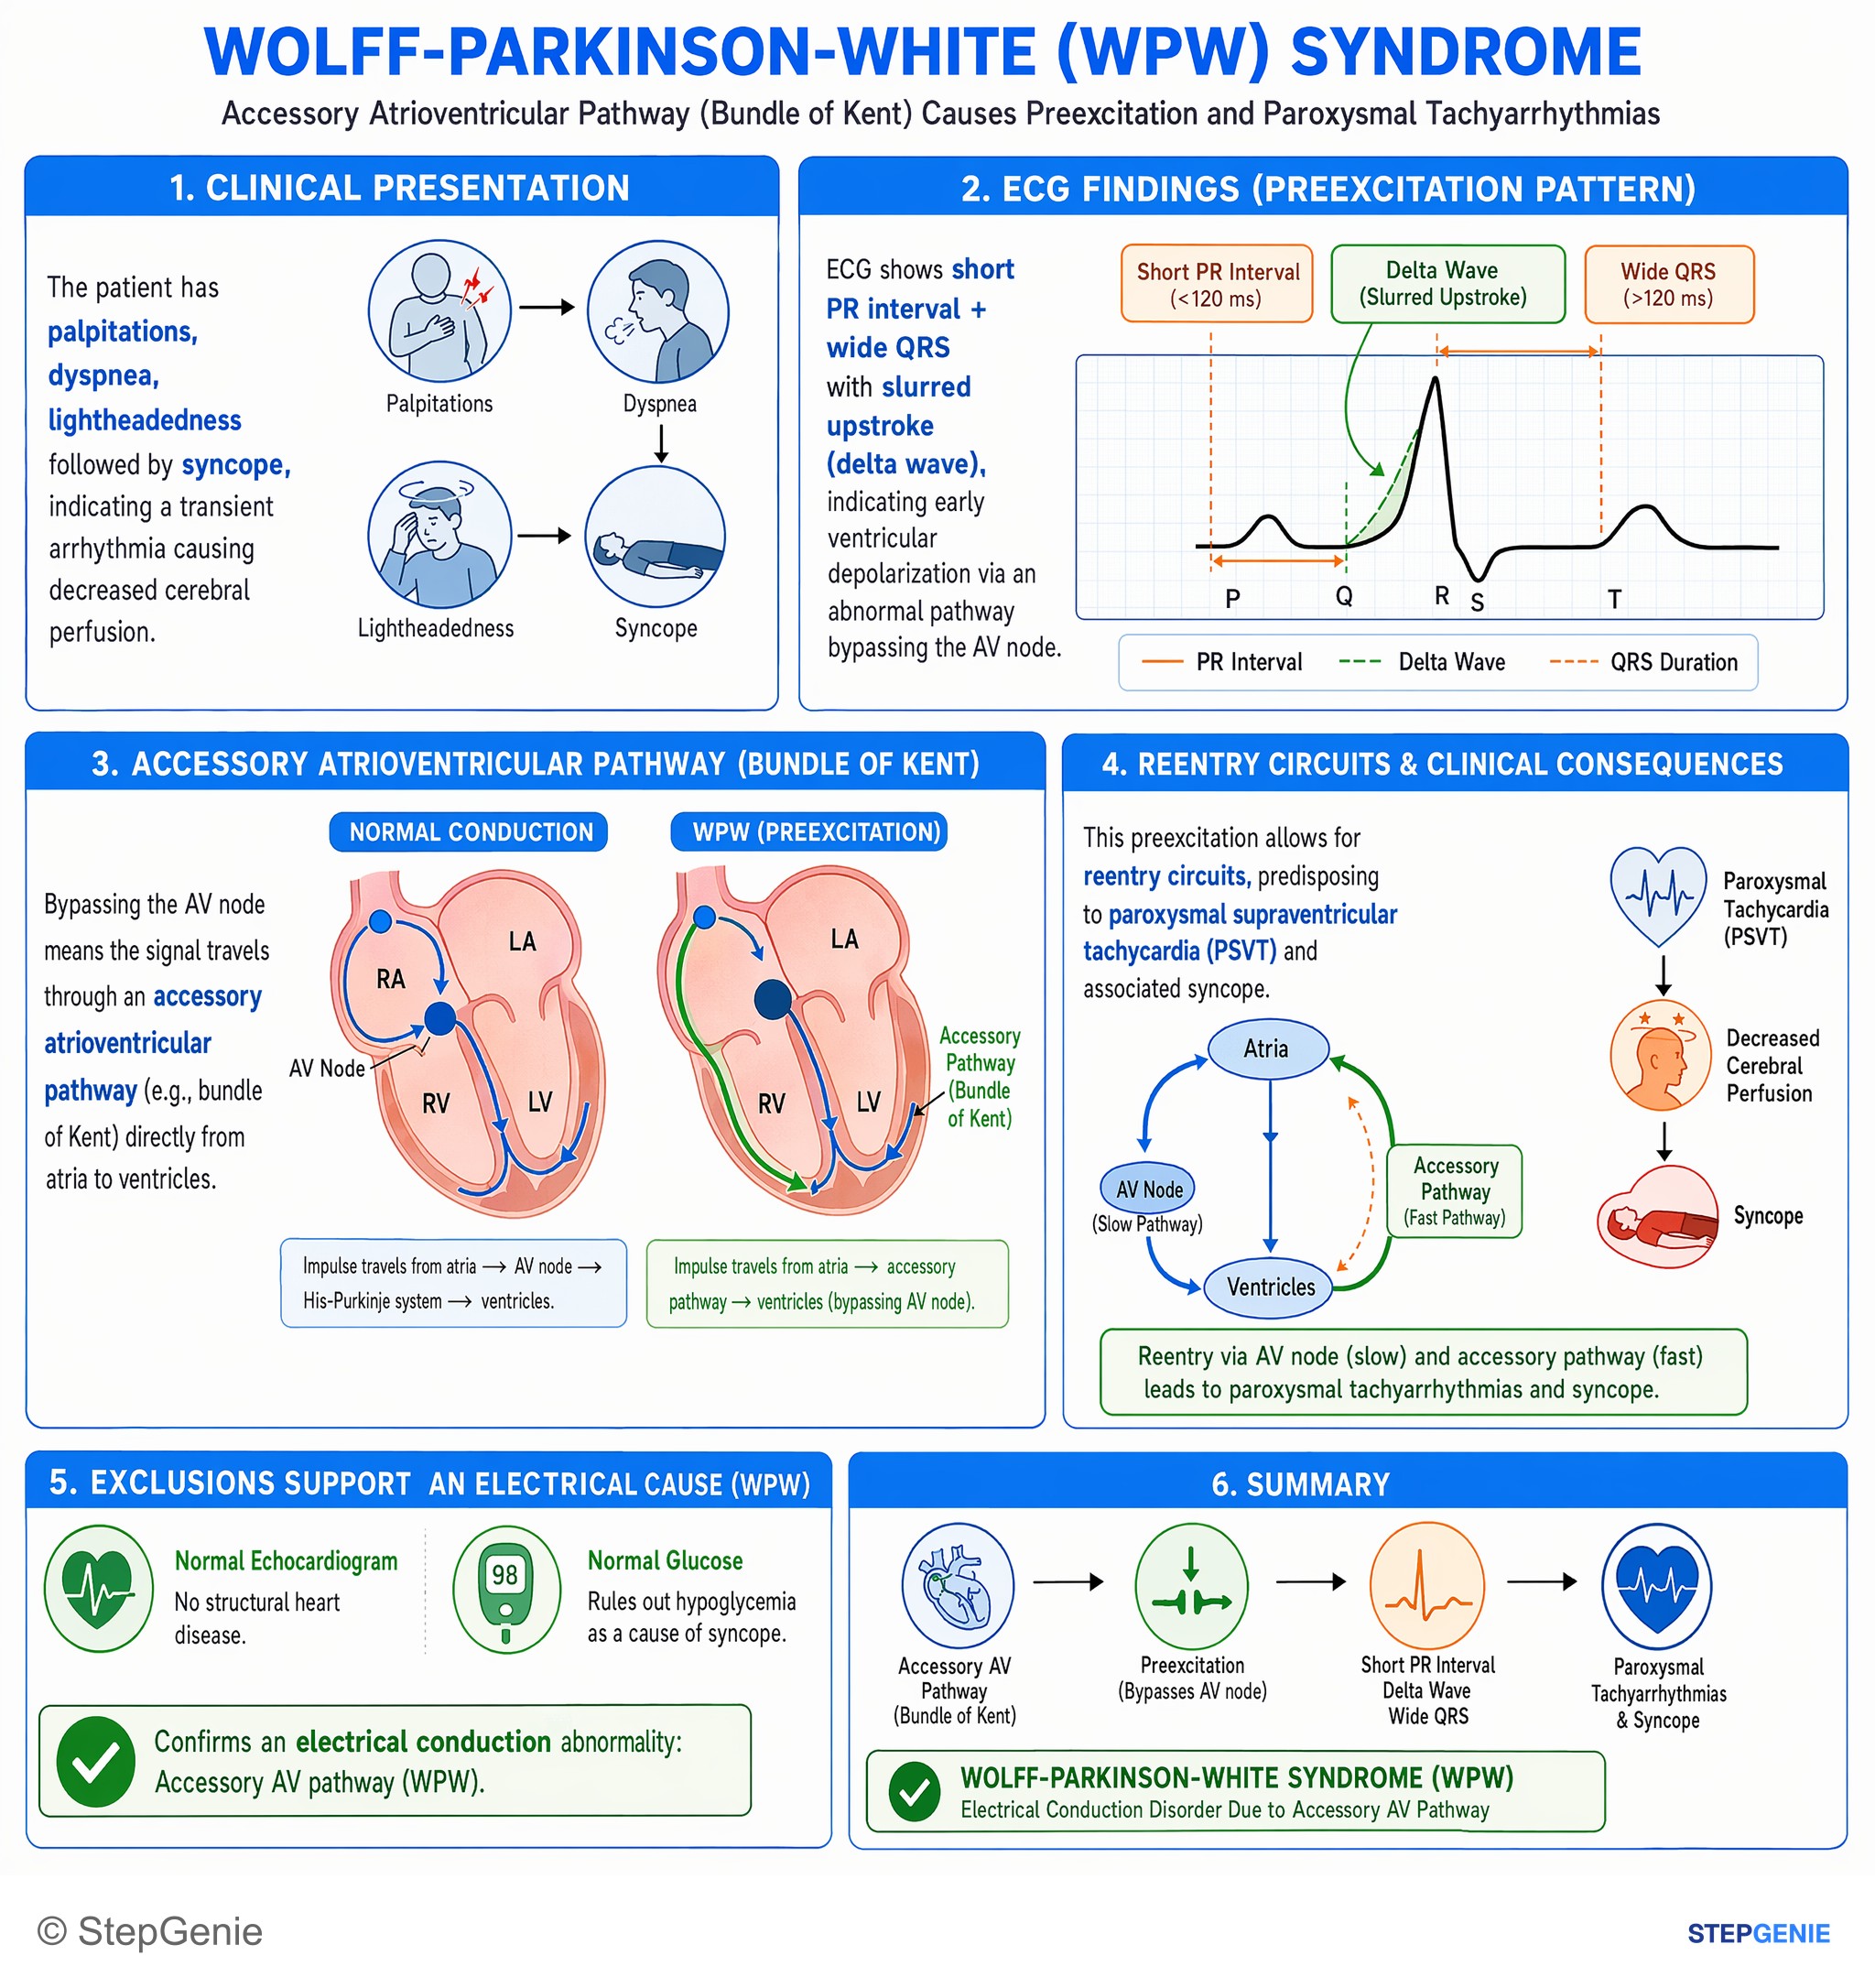
Wolff-Parkinson-White syndrome: accessory AV pathway (bundle of Kent) causes preexcitation → short PR, delta wave, wide QRS, paroxysmal…
USMLE Step 1Frequently Asked Questions
What ECG findings should make you think of Wolff-Parkinson-White on Step 1?
The classic ECG triad is a short PR interval, a delta wave, and a wide QRS complex. WPW is a pre-excitation syndrome caused by an accessory pathway that bypasses the AV node, so the ventricles are activated early. That early cell-to-cell ventricular depolarization creates the slurred upstroke called the delta wave, while the abnormal early activation also widens the QRS.
Why does Wolff-Parkinson-White cause a short PR interval and delta wave?
WPW causes a short PR interval and delta wave because atrial impulses bypass the normal AV nodal delay through an accessory pathway. Since the accessory pathway does not slow conduction like the AV node, the ventricles begin depolarizing earlier than normal, shortening the PR interval. The initial ventricular activation spreads slowly from cell to cell before the normal conduction system takes over, producing the slurred delta wave.
How do you tell WPW apart from LGL syndrome or bundle branch block on ECG?
WPW is distinguished by a short PR interval, a wide QRS, and a delta wave. LGL syndrome also has a short PR interval, but its QRS is normal and it does not have a delta wave. Bundle branch block causes a wide QRS, but the PR interval is normal and there is no delta wave; instead, the QRS morphology fits a right or left bundle branch block pattern.
What is the first-line treatment for atrial fibrillation with WPW, and what should you avoid?
Procainamide is the classic first-line board answer for atrial fibrillation with WPW, with ibutilide as another option and synchronized cardioversion if the patient is unstable. You should avoid AV nodal blockers such as adenosine, beta-blockers, non-DHP calcium channel blockers, and digoxin. Blocking the AV node can force more impulses through the accessory pathway, causing an even faster ventricular response and increasing the risk of ventricular fibrillation.
Why is atrial fibrillation with WPW dangerous?
Atrial fibrillation with WPW is dangerous because the accessory pathway can conduct atrial impulses to the ventricles very rapidly without the usual AV nodal filtering. In a normal heart, the AV node acts as a gatekeeper and limits how many atrial impulses reach the ventricles. In WPW, that protection is bypassed, so ventricular rates can become extremely fast and may degenerate into ventricular fibrillation.