Long QT syndrome (LQTS) is delayed ventricular repolarization, seen on the ECG as a prolonged corrected QT interval (QTc), that predisposes to torsades de pointes, a polymorphic ventricular tachycardia that causes syncope and sudden death. It can be congenital, from ion-channel mutations (LQT1 = KCNQ1, triggered by exercise and swimming; LQT2 = KCNH2/hERG, triggered by sudden loud noises; LQT3 = SCN5A, events at rest or during sleep), acquired, from QT-prolonging drugs, hypokalemia, hypomagnesemia, hypocalcemia or bradycardia, or both. Torsades is treated with IV magnesium sulfate (unsynchronized defibrillation if the patient is unstable), and congenital LQTS is managed long term with a long-acting beta-blocker (nadolol or slow-release propranolol), avoidance of QT-prolonging drugs and, for the highest-risk patients, an ICD.
QT, QTc and the numbers to know
- The QT interval runs from the start of the QRS complex to the end of the T wave: ventricular depolarization plus repolarization. It shortens as the heart rate rises, so it is corrected for rate, most often with Bazett's formula (intervals in seconds):
- Worked number: at 60/min the RR interval is 1.0 s, so QTc equals QT. At 100/min (RR = 0.6 s), a QT of 400 ms corrects to s, about 516 ms by Bazett: prolonged, although 400 ms looks normal (Merck notes that Bazett overestimates the QTc at fast heart rates).
- Cutoffs vary by source, so learn the pattern rather than one number:
| QTc | What it means |
|---|---|
| Above about 440–450 ms (men) or 460–470 ms (women) | Prolonged, per Merck |
| 470 ms (men) or 480 ms (women) | Approximate 99th percentile in healthy adults (AHA/ACCF 2010) |
| 480 ms or more (repeated ECGs) | Scores 3.5 points on the current LQTS risk score, enough on its own for a diagnosis (score above 3) when no secondary cause is present (GeneReviews); the original Schwartz score gave it 3 points |
| Over 500 ms | Highly abnormal in both sexes; torsades risk rises steeply |
A rise of 60 ms or more from the patient's pre-drug baseline is also a warning sign.
Why a long QT causes torsades
- Repolarization (phase 3) is driven by two outward potassium currents: the slow delayed rectifier (KCNQ1 channel) and the rapid delayed rectifier (KCNH2, the hERG channel). Inward current, including a small late sodium current through the SCN5A channel, opposes it.
- Less outward K⁺, or a persistent "late" inward Na⁺ current, lengthens the plateau, so the action potential and the QT interval get longer.
- Early afterdepolarizations (EADs) arise during that prolonged plateau and repolarization (phases 2 and 3). An EAD that reaches threshold fires a premature beat on the T wave, which sets off torsades.
- Pauses make it worse: torsades typically starts with a short-long-short sequence (a premature beat, then a pause that further lengthens the QT of the next normal beat, then a premature beat on that beat's T wave that launches torsades), and bradycardia is a risk factor.
- Torsades itself: polymorphic VT whose QRS complexes twist around the baseline at about 200–250/min. It is often self-terminating, causing palpitations or syncope, but it can degenerate into ventricular fibrillation.
Chain to memorize: less outward K⁺ (or more late Na⁺) → longer action potential → long QT → EADs → R-on-T premature beat → torsades → VF.
Congenital LQTS: LQT1, LQT2 and LQT3
Picture-able hook: 1 = swim, 2 = sound, 3 = sleep.
| Type | Gene (channel) | Defect | Classic trigger | T wave | Share of gene-positive cases (Merck) |
|---|---|---|---|---|---|
| LQT1 | KCNQ1 () | Loss of function: less outward K⁺ | Exercise, especially swimming; emotional stress | Broad-based | 40–55% |
| LQT2 | KCNH2 (hERG, ) | Loss of function: less outward K⁺ | Sudden noise (alarm clock, phone), emotion; high-risk postpartum period | Low-amplitude, notched (bifid) | 30–45% |
| LQT3 | SCN5A (Nav1.5) | Gain of function: persistent late Na⁺ current | Rest or sleep | Long ST segment, late normal-looking T | 5–10% |
- Inheritance: autosomal dominant with incomplete penetrance, so relatives with the same variant can look very different. Merck puts the incidence at at least 1 in 2,000, and a causative gene is found in only 70–85% of cases.
- Presentation: syncope, palpitations or cardiac arrest in a young person. Episodes are well known to be misdiagnosed as epilepsy, and in an estimated 10–15% of people who die of LQTS, death is the first sign.
Romano-Ward vs Jervell and Lange-Nielsen
| Feature | Romano-Ward syndrome | Jervell and Lange-Nielsen syndrome |
|---|---|---|
| Inheritance | Autosomal dominant (one altered copy) | Autosomal recessive (both copies) |
| Genes | KCNQ1, KCNH2, SCN5A most often (rare others) | KCNQ1 (about 90%) or KCNE1 |
| Hearing | Normal | Congenital profound sensorineural deafness |
| QTc | Variable; can be normal | Usually over 500 ms; events begin in early childhood |
| Frequency (MedlinePlus) | Most common form of inherited LQTS, which affects about 1 in 2,000 people | 1.6–6 per million; at least 1 in 200,000 in Scandinavia |
Why deafness? KCNQ1 and KCNE1 form a potassium channel that also maintains the ion balance of inner-ear fluid, so losing both copies disrupts hearing as well as repolarization. Some carriers, such as an affected child's parents, have a long QT with normal hearing. The recessive pattern is reviewed in the autosomal recessive inheritance guide. Rarer syndromic forms include Andersen-Tawil syndrome (periodic paralysis, craniofacial dysmorphism) and Timothy syndrome (syndactyly, congenital heart disease, immunodeficiency, developmental delay).
Acquired long QT: drugs, electrolytes and bradycardia
Most QT-prolonging drugs block (hERG), the same channel that is mutated in LQT2. Remember them as ABCDEF plus methadone:
| Hook | Class | Examples |
|---|---|---|
| Anti-arrhythmics | Class IA and III | Quinidine, procainamide, disopyramide; sotalol, dofetilide, ibutilide. Amiodarone prolongs the QT but causes torsades less often |
| Anti-Biotics | Macrolides, fluoroquinolones, other anti-infectives | Erythromycin, clarithromycin, fluoroquinolones; pentamidine and some antimalarials |
| Anti-"C"ychotics | Antipsychotics | Haloperidol, thioridazine, chlorpromazine, ziprasidone |
| Anti-Depressants | TCAs, some SSRIs | Tricyclics, citalopram |
| Anti-Emetics | 5-HT₃ antagonists | Ondansetron: dose-dependent QT prolongation; the FDA says to avoid a single 32 mg IV dose |
| Anti-Fungals | Azoles | Azole antifungals |
| Plus | Opioid | Methadone |
Class IA and III drugs and their toxicities are compared in the antiarrhythmics Q-bank breakdown.
- Hypokalemia and hypomagnesemia raise torsades risk; correct both, because with low magnesium the kidneys keep wasting potassium. Potassium disorders are covered in the hypokalemia and hyperkalemia breakdown.
- Hypocalcemia prolongs the QT by lengthening the ST segment; hypercalcemia shortens it.
- Other risk factors: bradycardia or AV block, female sex (about twice the in-hospital risk), age over 65, heart failure or structural heart disease, hypothyroidism, major acute brain injury, eating disorders, organophosphate poisoning, rapid IV infusion, liver or kidney dysfunction, two or more QT-prolonging drugs, and an unrecognized congenital LQTS.
Treatment
Torsades de pointes (acute):
- Pulseless or unstable: unsynchronized defibrillation (the changing QRS shape makes synchronized shocks unreliable).
- IV magnesium sulfate 2 g over 1–2 minutes, even if the serum magnesium is normal; repeat if torsades recurs.
- Stop the offending drug and correct electrolytes; the AHA/ACCF statement says raising potassium to 4.5–5 mmol/L may be considered.
- Recurrent, pause-dependent (acquired) torsades: raise the heart rate with temporary transvenous pacing or IV isoproterenol, which shortens the QT and removes the pauses. Isoproterenol is contraindicated in congenital LQTS, where adrenergic stimulation can trigger events; there the acute drug is an IV beta-blocker, and temporary pacing can still help.
- Lidocaine (class IB) may help, especially in drug-induced cases. Avoid class IA, IC and III antiarrhythmics.
Congenital LQTS (long term):
- Beta-blockers are the mainstay, most effective in LQT1 and LQT2. A long-acting nonselective agent (nadolol or slow-release propranolol) is preferred; short-acting metoprolol is avoided.
- Avoid QT-prolonging drugs and genotype triggers: strenuous exercise and unsupervised swimming in LQT1, loud noises such as alarm clocks and ringing phones in LQT2.
- ICD: for survivors of cardiac arrest and for cardiac syncope despite a beta-blocker; considered when the QTc stays over 500 ms on a beta-blocker.
- Left cardiac sympathetic denervation for high-risk patients when beta-blockers fail or are not tolerated, or an ICD is refused or contraindicated.
- Mexiletine (class IB sodium channel blocker) is added in LQT3 when a beta-blocker is not enough.
Mimics and traps
- Brugada syndrome is SCN5A loss of function: coved ST elevation in V1–V2, events at night or with fever, mostly in young men. LQT3 is SCN5A gain of function with a long QT.
- Amiodarone is class III and prolongs the QT, but torsades is less common than with sotalol, dofetilide or ibutilide.
- Hypokalemia's large U wave can merge with the T wave and mimic QT prolongation.
- A normal resting ECG does not rule out congenital LQTS: about 25% of people with a confirmed LQTS variant have a normal QTc (GeneReviews).
Practice question
A 15-year-old girl is brought to the emergency department after she lost consciousness while swimming laps and was pulled from the pool. Last year she fainted during a basketball game, which was attributed to a seizure. Her paternal uncle drowned at age 19. Her hearing is normal, she takes no medications, and her electrolytes are normal. An ECG shows sinus rhythm at 62/min, a QTc of 510 ms and broad-based T waves. Which of the following is the most likely underlying defect?
- A. Loss of function of the slow delayed rectifier potassium current ()
- B. Loss of function of the rapid delayed rectifier potassium current ()
- C. Gain of function of the cardiac sodium channel with a persistent late current
- D. Loss of function of the cardiac sodium channel
- E. Biallelic loss of function of the KCNQ1/KCNE1 potassium channel
Answer: A. Syncope during exertion, especially swimming, a family history of unexplained drowning and broad-based T waves point to LQT1 (KCNQ1, ). Next steps: a long-acting nonselective beta-blocker such as nadolol, avoidance of QT-prolonging drugs and unsupervised swimming, and genetic testing, with ECG screening of her first-degree relatives. An ICD is indicated if she has cardiac syncope despite the beta-blocker.
Why the others are wrong:
- B: LQT2 (KCNH2/hERG) events follow sudden noise or emotional arousal, such as an alarm clock, and the T waves are notched.
- C: LQT3 (SCN5A gain of function) events occur at rest or during sleep, with a long ST segment.
- D: SCN5A loss of function is Brugada syndrome: coved ST elevation in V1–V2, not a long QT.
- E: Biallelic KCNQ1 or KCNE1 variants cause Jervell and Lange-Nielsen syndrome, which comes with profound deafness from birth; her hearing is normal.
Classic acquired stem: an older woman with hypokalemia is started on haloperidol and a fluoroquinolone and has self-terminating runs of polymorphic VT. Give IV magnesium sulfate, stop both drugs and replete potassium and magnesium.
Key takeaways
- Long QT = delayed repolarization → EADs → torsades de pointes, which can degenerate into VF.
- LQT1 KCNQ1 (swimming, exercise), LQT2 KCNH2/hERG (loud noise, postpartum), LQT3 SCN5A gain of function (sleep, rest).
- Romano-Ward is autosomal dominant with normal hearing; Jervell and Lange-Nielsen is autosomal recessive with congenital deafness.
- Acquired LQTS: class IA and III antiarrhythmics, macrolides, fluoroquinolones, antipsychotics, TCAs, ondansetron, azole antifungals and methadone, plus low K⁺, Mg²⁺ or Ca²⁺ and bradycardia. Most of these drugs block hERG.
- QTc over 500 ms is highly abnormal and sharply raises torsades risk.
- Torsades: IV magnesium first (even with normal magnesium), defibrillate if unstable, and raise the heart rate for recurrent pause-dependent runs: pacing in any patient, isoproterenol only in acquired LQTS (congenital LQTS gets an IV beta-blocker instead).
- Congenital LQTS: nadolol or slow-release propranolol, avoid QT-prolonging drugs and triggers, ICD for arrest survivors or syncope despite a beta-blocker, and mexiletine as an add-on in LQT3.
Sources
- Long QT Interval Syndromes — Merck Manual Professional Edition
- Torsades de Pointes Ventricular Tachycardia — Merck Manual Professional Edition
- Groffen AJ, Bikker H, Christiaans I. Long QT Syndrome Overview — GeneReviews, NCBI Bookshelf (2024)
- Jervell and Lange-Nielsen syndrome — MedlinePlus Genetics
- Romano-Ward syndrome — MedlinePlus Genetics
- Drew BJ, et al. Prevention of Torsade de Pointes in Hospital Settings: AHA/ACCF Scientific Statement — Circulation (2010)
- Nachimuthu S, Assar MD, Schussler JM. Drug-induced QT interval prolongation: mechanisms and clinical management — Therapeutic Advances in Drug Safety (2012)
- New information regarding QT prolongation with ondansetron (Zofran) — FDA Drug Safety Communication (2012)
- Medications for Arrhythmias — Merck Manual Professional Edition
- Brugada Syndrome — Merck Manual Professional Edition
- Hypokalemia — Merck Manual Professional Edition
- Electrocardiography — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
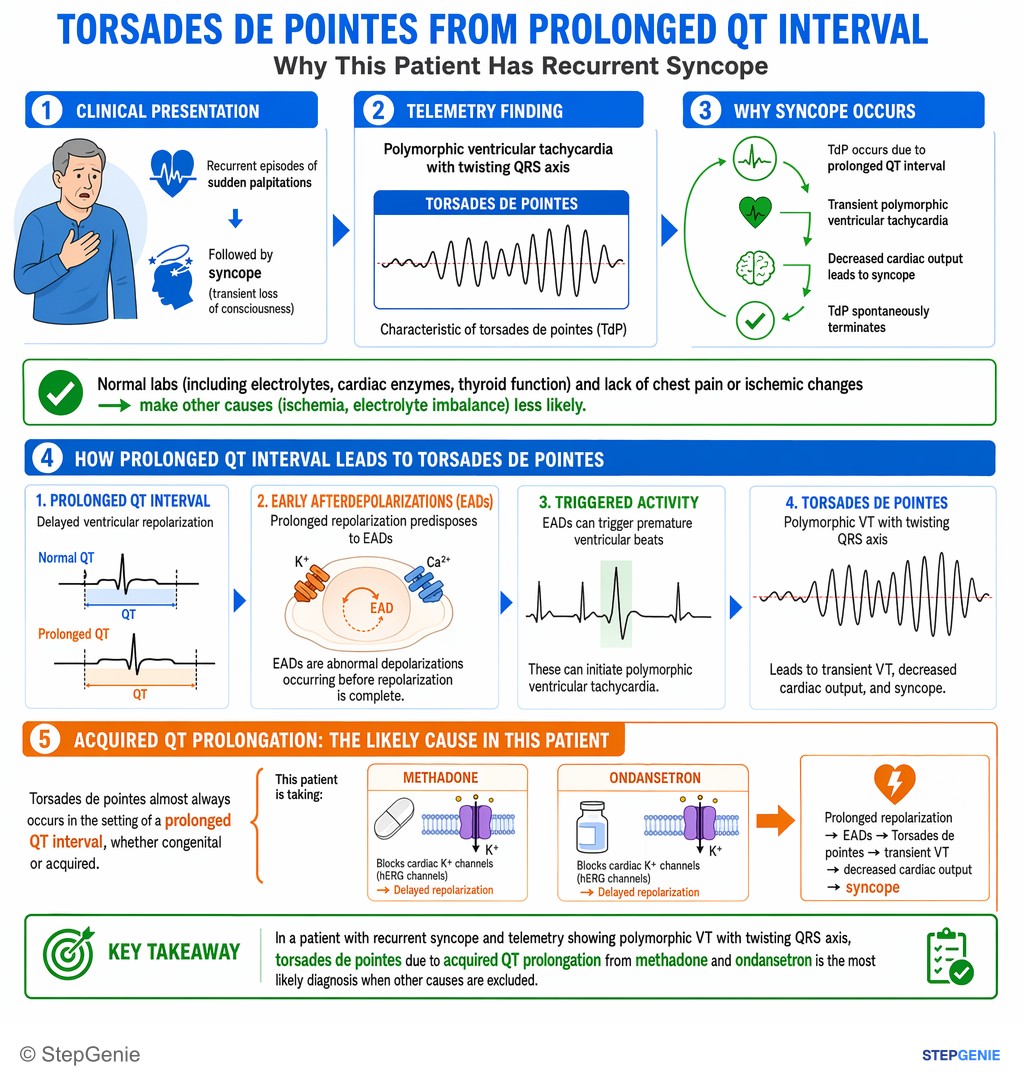
Torsades de pointes from prolonged QT interval causes recurrent syncope due to transient polymorphic ventricular tachycardia spontaneously…
USMLE Step 2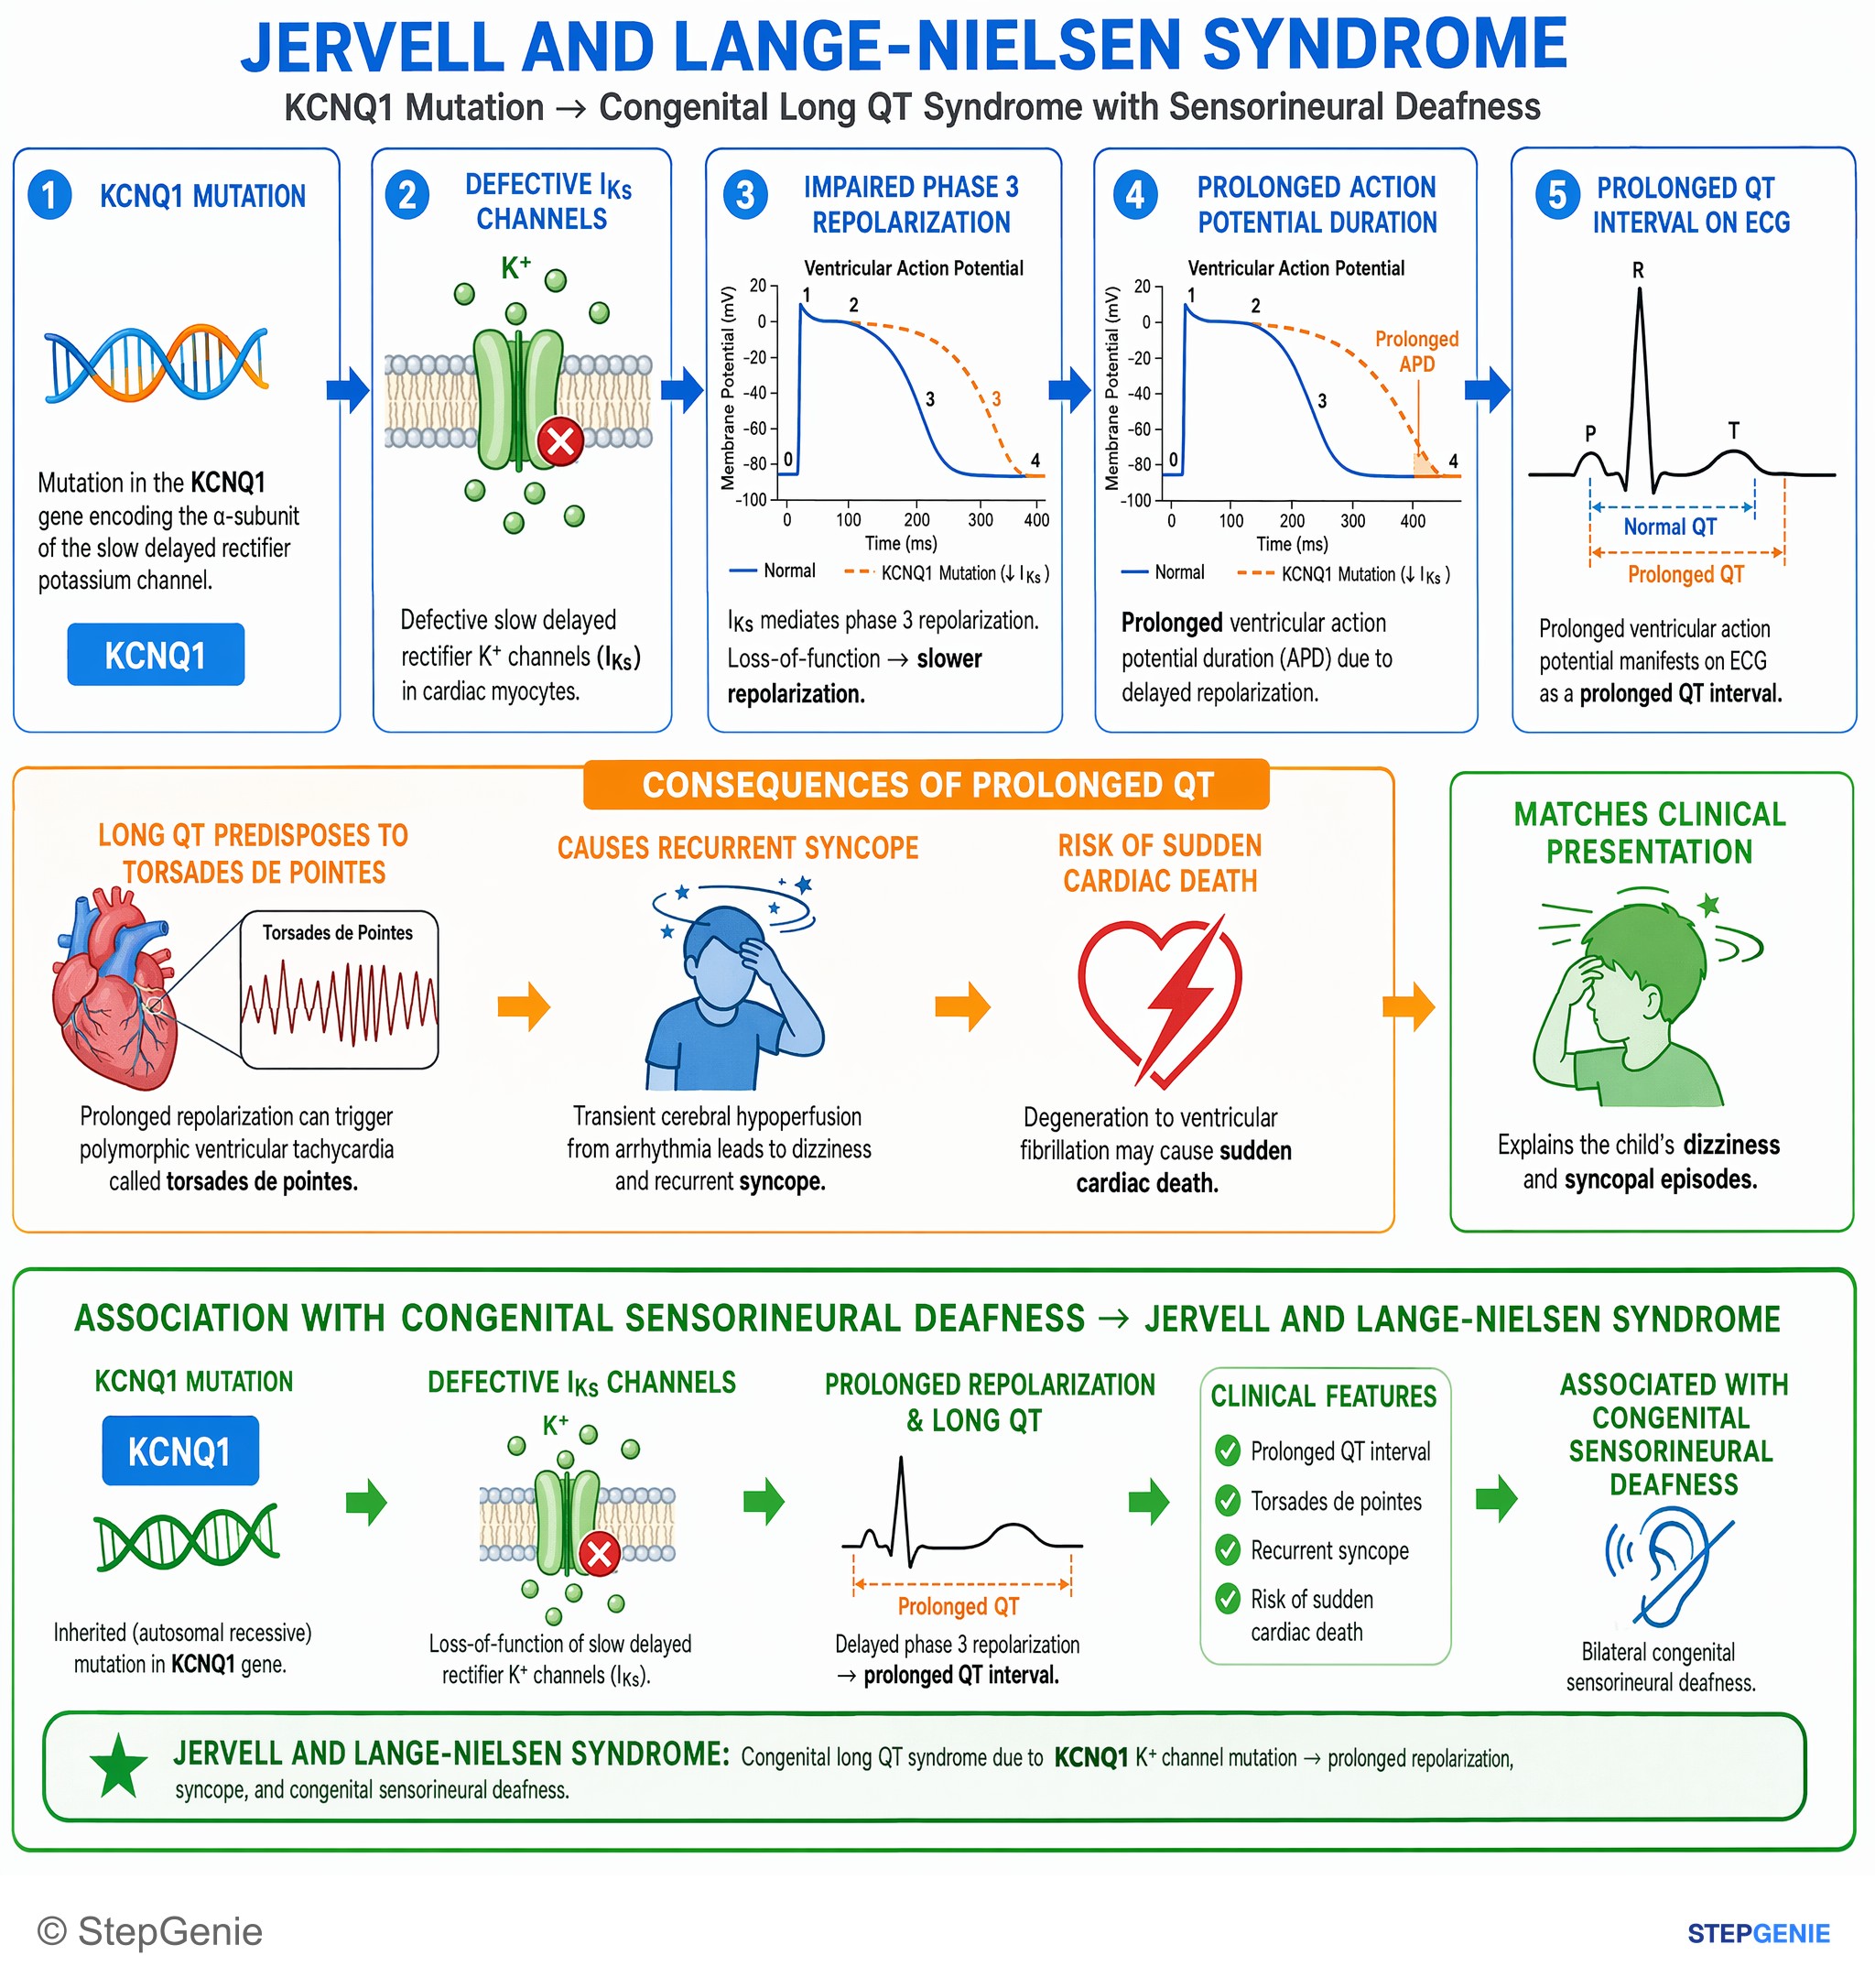
Jervell and Lange-Nielsen syndrome: congenital long QT due to KCNQ1 K+ channel mutation → prolonged repolarization, syncope, congenital…
USMLE Step 1Frequently Asked Questions
What causes long QT syndrome?
Long QT syndrome is either congenital or acquired. Congenital forms come from ion channel mutations, most often in KCNQ1 (LQT1), KCNH2 (LQT2) or SCN5A (LQT3), which reduce outward potassium current or add a persistent inward sodium current. Acquired long QT comes from QT-prolonging drugs, low potassium, magnesium or calcium, and bradycardia, and several of these often act together.
What are the triggers for LQT1, LQT2 and LQT3?
LQT1 events are triggered by exercise, classically swimming, and by emotional stress. LQT2 events follow sudden loud noises such as an alarm clock or a ringing phone, and the postpartum period carries high risk. LQT3 events tend to occur at rest or during sleep. A quick way to remember them is 1 = swim, 2 = sound, 3 = sleep.
What is the difference between Romano-Ward and Jervell and Lange-Nielsen syndrome?
Romano-Ward syndrome is the common, autosomal dominant form of inherited long QT syndrome, and hearing is normal. Jervell and Lange-Nielsen syndrome is autosomal recessive, caused by variants in both copies of KCNQ1 or KCNE1, and combines congenital profound sensorineural deafness with a very long QT, usually over 500 ms. Its arrhythmia risk begins in early childhood.
What QTc is dangerous?
Cutoffs for a prolonged QTc vary by source, roughly above 440 to 450 ms in men and 460 to 470 ms in women. A QTc over 500 ms is considered highly abnormal in both sexes and sharply raises the risk of torsades de pointes. A rise of 60 ms or more from a patient's baseline after starting a drug is also a warning sign.
How is torsades de pointes treated?
A pulseless or unstable patient needs unsynchronized defibrillation. Otherwise, give IV magnesium sulfate 2 g even if the magnesium level is normal, stop QT-prolonging drugs and correct potassium and magnesium. Recurrent, pause-dependent torsades in acquired long QT can be suppressed by raising the heart rate with temporary pacing or isoproterenol, but isoproterenol is contraindicated in congenital long QT syndrome, where an IV beta-blocker is used instead.
Which drugs cause long QT syndrome?
Classic culprits are class IA and III antiarrhythmics such as quinidine, procainamide, sotalol and dofetilide, macrolides and fluoroquinolones, azole antifungals, antipsychotics such as haloperidol, tricyclic antidepressants and citalopram, ondansetron and methadone. Most of them block the hERG potassium channel that carries the rapid delayed rectifier current. The risk climbs when two such drugs are combined or when potassium or magnesium is low.